
Lansoprazole 30 mg Tablet, Orally Disintegrating, Delayed Release
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Proton Pump Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Prescription lansoprazole is used to treat the symptoms of gastroesophageal reflux disease (GERD), a condition in which backward flow of acid from the stomach causes heartburn and possible injury of the esophagus (the tube between the throat and stomach) in adults and children 1 year of age and older. Prescription lansoprazole is used to treat the damage from GERD in adults and children 1 year of age and older. Prescription lansoprazole is used to allow the esophagus to heal and prevent further damage to the esophagus in adults with GERD. Prescription lansoprazole is also used to treat ulcers...
Read the full MedlinePlus article ↗- It does a lot more than heartburn relief. Lansoprazole is used to heal ulcers in the stomach and small intestine, treat acid reflux disease (GERD), repair acid damage to the esopha...
- What exactly is lansoprazole treating — is it just for heartburn?
- Timing actually matters quite a bit with lansoprazole. It works best when taken before a meal — ideally about 30 minutes before you eat. If you take it after food, your body absorb...
- Does it matter when I take it — can I just take it whenever it's convenient?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lansoprazole — tap one for details:
Lansoprazole may be associated with lower levels of 9 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII Z0H242BBR1
Aspartame is an artificial sweetener made from amino acids. It's added to medicines to improve taste, making bitter or unpleasant-tasting drugs easier to take.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 0E53J927NA
Magnesium carbonate is a mineral powder used in medicines as a filler to add bulk and as a buffer to help regulate acidity in the formulation.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 8MDF5V39QO
A white powder form of baking soda that acts as a buffer and pH regulator in medicines. It helps maintain the right acid-base balance and may aid tablet disintegration.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
20 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.210 | $221.03 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $3.19 | $318.57 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $5.05 | $504.54 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lansoprazole 30 mg 00093-3009-93 | Teva | 1 tablet | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mgthis 00378-6982-88 | Mylan | 10 tablets | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mg 16714-0186-02 | NorthStar | 10 tablets | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mg 43598-0561-78 | Dr.Reddys | 10 tablets | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mg 65862-0896-78 | Aurobindo | 10 tablets | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mg 68382-0772-77 | Zydus | 10 tablets | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mg 72603-0314-10 | NorthStar | 10 tablets | $2.210 | AB | Availability likely | — |
| Lansoprazole 30 mg 55154-4848-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Prevacid SoluTab 30 mg 64764-0544-05 | Takeda | 3 tablets | — | AB | FDA listed | — |
| Lansoprazole 30 mg 70771-1133-04 | Zydus | 10 tablets | — | AB | FDA listed | — |
| Lansoprazole 30 mg 55154-8340-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00378-6982-88 You're viewing this | 2 CARTON in 1 BOX (0378-6982-88) / 5 BLISTER PACK in 1 CARTON (0378-6982-85) / 10 TABLET, ORALLY DISINTEGRATING, DELAYED RELEASE in 1 BLISTER PACK (0378-6982-32) | 2018-11-29 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lansoprazole delayed-release orally disintegrating tablets are a proton pump inhibitor (PPI) indicated for the: • Treatment of active duodenal ulcer in adults. ( 1.1 ) • Eradication of H. pylori to reduce the risk of duodenal ulcer recurrence in adults. ( 1.2 ) • Maintenance of healed duodenal ulcers in adults.
( 1.3 ) • Treatment of active benign gastric ulcer in adults. ( 1.4 ) • Healing of nonsteroidal anti-inflammatory drugs (NSAID)-associated gastric ulcer in adults. ( 1.5 ) • Risk reduction of NSAID-associated gastric ulcer in adults.
( 1.6 ) • Treatment of symptomatic gastroesophageal reflux disease (GERD) in adults and pediatric patients 1 year of age and older. ( 1.7 ) • Treatment of erosive esophagitis (EE) in adults and pediatric patients 1 year of age and older. ( 1.8 ) • Maintenance of healing of EE in adults.
( 1.9 ) • Pathological hypersecretory conditions, including Zollinger-Ellison syndrome (ZES) in adults. ( 1.10 )
1.1Treatment of Active Duodenal Ulcer Lansoprazole delayed-release orally disintegrating tablets are indicated in adults for short-term treatment (for four weeks) for healing and symptom relief of active duodenal ulcer [see Clinical Studies (14.1) ] .
1.2Eradication of H. pylori to Reduce the Risk of Duodenal Ulcer Recurrence Triple Therapy Lansoprazole Delayed-Release Orally Disintegrating Tablets/Amoxicillin/Clarithromycin Lansoprazole delayed-release orally disintegrating tablets in combination with amoxicillin plus clarithromycin as triple therapy are indicated in adults for the treatment of patients with H. pylori infection and duodenal ulcer disease (active or one year history of a duodenal ulcer) to eradicate H. pylori . Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence [see Clinical Studies (14.2) ] .
Please refer to the full prescribing information for amoxicillin and clarithromycin. Dual Therapy Lansoprazole Delayed-Release Orally Disintegrating Tablets/Amoxicillin Lansoprazole delayed-release orally disintegrating tablets in combination with amoxicillin as dual therapy are indicated in adults for the treatment of patients with H. pylori infection and duodenal ulcer disease (active or one year history of a duodenal ulcer) who are either allergic or intolerant to clarithromycin or in whom resistance to clarithromycin is known or suspected (see the clarithromycin prescribing information, Microbiology section).
Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence [see Clinical Studies (14.2) ] . Please refer to the full prescribing information for amoxicillin.
1.3Maintenance of Healed Duodenal Ulcers Lansoprazole delayed-release orally disintegrating tablets are indicated in adults to maintain healing of duodenal ulcers. Controlled studies do not extend beyond 12 months [see Clinical Studies (14.3) ] .
1.4Treatment of Active Benign Gastric Ulcer Lansoprazole delayed-release orally disintegrating tablets are indicated in adults for short-term treatment (up to eight weeks) for healing and symptom relief of active benign gastric ulcer [see Clinical Studies (14.4) ] .
1.5Healing of NSAID-Associated Gastric Ulcer Lansoprazole delayed-release orally disintegrating tablets are indicated in adults for the treatment of NSAID-associated gastric ulcer in patients who continue NSAID use. Controlled studies did not extend beyond eight weeks [see Clinical Studies (14.5) ] .
1.6Risk Reduction of NSAID-Associated Gastric Ulcer Lansoprazole delayed-release orally disintegrating tablets are indicated in adults for reducing the risk of NSAID-associated gastric ulcers in patients with a history of a documented gastric ulcer who require the use of an NSAID. Controlled studies did not extend beyond 12 weeks [see Clinical Studies (14.6) ] .
1.7Treatment of Symptomatic Gastroesophageal Reflux Disease (GERD) Lansoprazole delayed-release orally disintegrating tablets are indicated for short-term treatment in adult…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage: • See full prescribing information for complete dosing information for lansoprazole delayed-release orally disintegrating tablets by indication and age group and dosage adjustment in patients with severe hepatic impairment. ( 2.1 , 2.2 , 2.3 ) Administration Instructions ( 2.4 ): Lansoprazole Delayed-Release Orally Disintegrating Tablets • Should not be broken or cut. • Should not be chewed. • Place the tablet on the tongue and allow it to disintegrate, with or without water, until the pellets can be swallowed. • See full prescribing information for alternative administration options.
2.1Recommended Adult Dosage by Indication Indication Recommended Dose Frequency Duodenal Ulcers Short-Term Treatment 15 mg Once daily for 4 weeks Maintenance of Healed 15 mg Once daily Eradication of H. pylori to Reduce the Risk of Duodenal Ulcer Recurrence Please refer to the amoxicillin and clarithromycin full prescribing information, Contraindications and Warnings and Precautions sections, and for information regarding dosing in elderly and renally-impaired patients. Triple Therapy: Lansoprazole Delayed-Release Orally Disintegrating Tablets 30 mg Twice daily for 10 or 14 days Amoxicillin 1 gram Twice daily for 10 or 14 days Clarithromycin 500 mg Twice daily for 10 or 14 days Dual Therapy: Lansoprazole Delayed-Release Orally Disintegrating Tablets 30 mg Three times daily for 14 days Amoxicillin 1 gram Three times daily for 14 days Benign Gastric Ulcer Short-Term Treatment 30 mg Once daily for up to 8 weeks NSAID-Associated Gastric Ulcer Healing 30 mg Once daily for 8 weeks Controlled studies did not extend beyond indicated duration.
Risk Reduction 15 mg Once daily for up to 12 weeks Gastroesophageal Reflux Disease (GERD) Short-Term Treatment of Symptomatic GERD 15 mg Once daily for up to 8 weeks Short-Term Treatment of Erosive Esophagitis 30 mg Once daily for up to 8 weeks For patients who do not heal with lansoprazole delayed-release orally disintegrating tablets for eight weeks (5 to 10%), it may be helpful to give an additional eight weeks of treatment. If there is a recurrence of erosive esophagitis, an additional eight week course of lansoprazole delayed-release orally disintegrating tablets may be considered.
Maintenance of Healing of Erosive Esophagitis 15 mg Once daily Controlled studies did not extend beyond 12 months. Pathological Hypersecretory Conditions Including Zollinger-Ellison Syndrome 60 mg Once daily Varies with individual patient. Recommended adult starting dose is 60 mg once daily.
Doses should be adjusted to individual patient needs and should continue for as long as clinically indicated. Dosages up to 90 mg twice daily have been administered. Daily dose of greater than 120 mg should be administered in divided doses.
Some patients with Zollinger-Ellison syndrome have been treated continuously with lansoprazole delayed-release orally disintegrating tablets for more than four years.
2.2Recommended Pediatric Dosage by Indication Pediatric Patients 1 to 11 Years of Age In clinical studies, lansoprazole delayed-release orally disintegrating tablets were not administered beyond 12 weeks in 1 to 11 year olds. It is not known if lansoprazole delayed-release orally disintegrating tablets are safe and effective if used longer than the recommended duration. Do not exceed the recommended dose and duration of use in pediatric patients as outlined below [see Use in Specific Populations (8.4) ] .
Indication Recommended Dose Frequency Short-Term Treatment of Symptomatic GERD and Short-Term Treatment of Erosive Esophagitis ≤ 30 kg 15 mg Once daily for up to 12 weeks > 30 kg 30 mg Once daily for up to 12 weeks Pediatric Patients 12 to 17 Years of Age Indication Recommended Dose Frequency Short-Term Treatment of Symptomatic GERD Non-erosive GERD 15 mg Once daily for up to 8 weeks Erosive Esophagitis 30 mg Once daily for up to 8 weeks
2.3 Hepatic Impairment The recommended dosage is 15 mg oral…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lansoprazole Delayed-Release Orally Disintegrating Tablets are available containing 15 mg or 30 mg of lansoprazole, USP. • 15 mg tablets are pale yellow, round, flat-faced, speckled, unscored tablets debossed with M on one side of the tablet and LP1 on the other side. • 30 mg tablets are pale yellow, round, flat-faced, speckled, unscored tablets debossed with M on one side of the tablet and LP2 on the other side. • Delayed-release orally disintegrating tablets: 15 mg and 30 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Lansoprazole delayed-release orally disintegrating tablets are contraindicated in patients with known hypersensitivity to any component of the formulation. Hypersensitivity reactions may include anaphylaxis, anaphylactic shock, angioedema, bronchospasm, acute tubulointerstitial nephritis, and urticaria [see Warnings and Precautions (5.2) , Adverse Reactions (6) ] . • Proton Pump Inhibitors (PPIs), including lansoprazole delayed-release orally disintegrating tablets, are contraindicated with rilpivirine-containing products [see Drug Interactions (7) ] . • For information about contraindications of antibacterial agents (clarithromycin and amoxicillin) indicated in combination with lansoprazole delayed-release orally disintegrating tablets, refer to the Contraindications section of their prescribing information. • Contraindicated in patients with known hypersensitivity to any component of the lansoprazole delayed-release orally disintegrating tablet formulation.
( 4 ) • Patients receiving rilpivirine-containing products. ( 4 , 7 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Gastric Malignancy: In adults, symptomatic response with lansoprazole delayed-release orally disintegrating tablets does not preclude the presence of gastric malignancy. Consider additional follow-up and diagnostic testing. ( 5.1 ) • Acute Tubulointerstitial Nephritis: Discontinue treatment and evaluate patients.
( 5.2 ) • Clostridium difficile -Associated Diarrhea: PPI therapy may be associated with increased risk of Clostridium difficile -associated diarrhea. ( 5.3 ) • Bone Fracture: Long-term and multiple daily dose PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist or spine. ( 5.4 ) • Severe Cutaneous Adverse Reactions: Discontinue at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation.
( 5.5 ) • Cutaneous and Systemic Lupus Erythematosus: Mostly cutaneous; new onset or exacerbation of existing disease; discontinue lansoprazole delayed-release orally disintegrating tablets and refer to specialist for evaluation. ( 5.6 ) • Cyanocobalamin (Vitamin B12) Deficiency: Daily long-term use (e.g., longer than 3 years) may lead to malabsorption or a deficiency of cyanocobalamin. ( 5.7 ) • Hypomagnesemia and Mineral Metabolism: Hypomagnesemia has been reported rarely with prolonged treatment with PPIs.
( 5.8 ) • Interactions with Investigations for Neuroendocrine Tumors: Increases in intragastric pH may result in hypergastrinemia and enterochromaffin-like cell hyperplasia and increased chromogranin A levels which may interfere with diagnostic investigations for neuroendocrine tumors. ( 5.9 , 7 ) • Interaction with Methotrexate: Concomitant use with PPIs may elevate and/or prolong serum concentrations of methotrexate and/or its metabolite, possibly leading to toxicity. With high-dose methotrexate administration, consider a temporary withdrawal of lansoprazole delayed-release orally-disintegrating tablets.
( 5.10 , 7 ) • Patients with Phenylketonuria: Each 15 mg lansoprazole delayed-release orally disintegrating tablet contains 3.37 mg and each 30 mg lansoprazole delayed-release orally disintegrating tablet contains 6.74 mg of phenylalanine. ( 5.11 ) • Fundic Gland Polyps: Risk increases with long-term use, especially beyond 1 year. Use the shortest duration of therapy.
( 5.12 ) • Risk of Heart Valve Thickening in Pediatric Patients Less Than One Year of Age: Lansoprazole is not recommended in pediatric patients less than 1 year of age. ( 5.13 , 8.4 )
5.1Presence of Gastric Malignancy In adults, symptomatic response to therapy with lansoprazole delayed-release orally disintegrating tablets does not preclude the presence of gastric malignancy. Consider additional follow-up and diagnostic testing in adult patients who have a suboptimal response or an early symptomatic relapse after completing treatment with a PPI. In older patients, also consider an endoscopy.
5.2Acute Tubulointerstitial Nephritis Acute tubulointerstitial nephritis (TIN) has been observed in patients taking PPIs and may occur at any point during PPI therapy. Patients may present with varying signs and symptoms from symptomatic hypersensitivity reactions to non-specific symptoms of decreased renal function (e.g., malaise, nausea, anorexia). In reported case series, some patients were diagnosed on biopsy and in the absence of extra-renal manifestations (e.g., fever, rash or arthralgia).
Discontinue lansoprazole delayed-release orally disintegrating tablets and evaluate patients with suspected acute TIN [see Contraindications (4) ] .
5.3Clostridium difficile -Associated Diarrhea Published observational studies suggest that PPI therapy like lansoprazole delayed-release orally disintegrating tablets may be associated with an increased risk of Clostridium difficile -associated diarrhea (CDAD), especially in hospitalized patients. This diagnosis should be considered for diarrhea that does not improve [see Adverse…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in labeling: • Acute Tubulointerstitial Nephritis [see Warnings and Precautions (5.2) ] • Clostridium difficile -Associated Diarrhea [see Warnings and Precautions (5.3) ] • Bone Fracture [see Warnings and Precautions (5.4) ] • Severe Cutaneous Adverse Reactions [see Warnings and Precautions (5.5) ] • Cutaneous and Systemic Lupus Erythematosus [see Warnings and Precautions (5.6) ] • Cyanocobalamin (Vitamin B12) Deficiency [see Warnings and Precautions (5.7) ] • Hypomagnesemia and Mineral Metabolism [see Warnings and Precautions (5.8) ] • Fundic Gland Polyps [see Warnings and Precautions (5.12) ] Most commonly reported adverse reactions (≥ 1%): diarrhea, abdominal pain, nausea and constipation.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Worldwide, over 10,000 patients have been treated with lansoprazole in Phase 2 or Phase 3 clinical trials involving various dosages and durations of treatment. In general, lansoprazole treatment has been well-tolerated in both short-term and long-term trials.
The following adverse reactions were reported by the treating physician to have a possible or probable relationship to drug in 1% or more of lansoprazole-treated patients and occurred at a greater rate in lansoprazole-treated patients than placebo-treated patients in Table 1 . Table 1. Incidence of Possibly or Probably Treatment-Related Adverse Reactions in Short-Term, Placebo-Controlled Lansoprazole Studies Body System/ Adverse Reaction Lansoprazole (N = 2768) % Placebo (N = 1023) % Body as a Whole Abdominal Pain 2.1
1.2Digestive System Constipation 1.0
0.4Diarrhea 3.8
2.3Nausea 1.3
1.2Headache was also seen at greater than 1% incidence but was more common on placebo. The incidence of diarrhea was similar between patients who received placebo and patients who received 15 and 30 mg of lansoprazole, but higher in the patients who received 60 mg of lansoprazole (2.9, 1.4, 4.2, and 7.4%, respectively). The most commonly reported possibly or probably treatment-related adverse event during maintenance therapy was diarrhea.
In the risk reduction study of lansoprazole for NSAID-associated gastric ulcers, the incidence of diarrhea for patients treated with lansoprazole, misoprostol, and placebo was 5, 22, and 3%, respectively. Another study for the same indication, where patients took either a COX-2 inhibitor or lansoprazole and naproxen, demonstrated that the safety profile was similar to the prior study. Additional reactions from this study not previously observed in other clinical trials with lansoprazole included contusion, duodenitis, epigastric discomfort, esophageal disorder, fatigue, hunger, hiatal hernia, hoarseness, impaired gastric emptying, metaplasia, and renal impairment.
Additional adverse experiences occurring in less than 1% of patients or subjects who received lansoprazole in domestic trials are shown below: Body as a Whole: abdomen enlarged, allergic reaction, asthenia, back pain, candidiasis, carcinoma, chest pain (not otherwise specified), chills, edema, fever, flu syndrome, halitosis, infection (not otherwise specified), malaise, neck pain, neck rigidity, pain, pelvic pain Cardiovascular System: angina, arrhythmia, bradycardia, cerebrovascular accident/cerebral infarction, hypertension/hypotension, migraine, myocardial infarction, palpitations, shock (circulatory failure), syncope, tachycardia, vasodilation Digestive System: abnormal stools, anorexia, bezoar, cardiospasm, cholelithiasis, colitis, dry mouth, dyspepsia, dysphagia, ente…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Tables 2 and 3 include drugs with clinically important drug interactions and interaction with diagnostics when administered concomitantly with lansoprazole delayed-release orally disintegrating tablets and instructions for preventing or managing them. Consult the labeling of concomitantly used drugs to obtain further information about interactions with PPIs. Table 2.
Clinically Relevant Interactions Affecting Drugs Coadministered with Lansoprazole Delayed-Release Orally Disintegrating Tablets and Interactions with Diagnostics Antiretrovirals Clinical Impact: The effect of PPIs on antiretroviral drugs is variable. The clinical importance and the mechanisms behind these interactions are not always known. • Decreased exposure of some antiretroviral drugs (e.g., rilpivirine, atazanavir, and nelfinavir) when used concomitantly with lansoprazole may reduce antiviral effect and promote the development of drug resistance. • Increased exposure of other antiretroviral drugs (e.g., saquinavir) when used concomitantly with lansoprazole may increase toxicity of the antiretroviral drugs. • There are other antiretroviral drugs which do not result in clinically relevant interactions with lansoprazole.
Intervention: Rilpivirine-containing products: Concomitant use with lansoprazole delayed-release orally disintegrating tablets is contraindicated [see Contraindications (4) ] . See prescribing information. Atazanavir: See prescribing information for atazanavir for dosing information.
Nelfinavir: Avoid concomitant use with lansoprazole delayed-release orally disintegrating tablets. See prescribing information for nelfinavir. Saquinavir: See the prescribing information for saquinavir and monitor for potential saquinavir toxicities.
Other antiretrovirals: See prescribing information. Warfarin Clinical Impact: Increased INR and prothrombin time in patients receiving PPIs and warfarin concomitantly. Increases in INR and prothrombin time may lead to abnormal bleeding and even death.
Intervention: Monitor INR and prothrombin time. Dose adjustment of warfarin may be needed to maintain target INR range. See prescribing information for warfarin.
Methotrexate Clinical Impact: Concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum concentrations of methotrexate and/or its metabolite hydroxymethotrexate, possibly leading to methotrexate toxicities. No formal drug interaction studies of high-dose methotrexate with PPIs have been conducted [see Warnings and Precautions (5.10) ] . Intervention: A temporary withdrawal of lansoprazole delayed-release orally disintegrating tablets may be considered in some patients receiving high-dose methotrexate.
Digoxin Clinical Impact: Potential for increased exposure of digoxin. Intervention: Monitor digoxin concentrations. Dose adjustment of digoxin may be needed to maintain therapeutic drug concentrations.
See prescribing information for digoxin. Theophylline Clinical Impact: Increased clearance of theophylline [see Clinical Pharmacology (12.3) ] . Intervention: Individual patients may require additional titration of their theophylline dosage when lansoprazole delayed-release orally disintegrating tablets are started or stopped to ensure clinically effective blood concentrations.
Drugs Dependent on Gastric pH for Absorption (e.g., iron salts, erlotinib, dasatinib, nilotinib, mycophenolate mofetil, ketoconazole/itraconazole) Clinical Impact: Lansoprazole can reduce the absorption of other drugs due to its effect on reducing intragastric acidity. Intervention: Mycophenolate mofetil (MMF): Coadministration of PPIs in healthy subjects and in transplant patients receiving MMF has been reported to reduce the exposure to the active metabolite, mycophenolic acid (MPA), possibly due to a decrease in MMF solubility at an increased gastric pH.
The clinical relevance of reduced MPA exposure on organ rejection has not been established in transplant patients receiving lansopra…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: Based on animal data, may cause adverse effects on fetal bone growth and development. ( 8.1 ) • Pediatrics: Use is not recommended for the treatment of symptomatic GERD in patients 1 month to less than 1 year of age; efficacy was not demonstrated and nonclinical studies have demonstrated adverse effects in juvenile rats. ( 5.13 , 8.4 )
8.1Pregnancy Risk Summary Available data from published observational studies overall do not indicate an association of adverse pregnancy outcomes with lansoprazole treatment (see Data ) . In animal reproduction studies, oral administration of lansoprazole to rats during organogenesis through lactation at 6.4 times the maximum recommended human dose produced reductions in the offspring in femur weight, femur length, crown-rump length and growth plate thickness (males only) on postnatal Day 21 (see Data ) . These effects were associated with reduction in body weight gain.
Advise pregnant women of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. If lansoprazole delayed-release orally disintegrating tablets are administered with clarithromycin, the pregnancy information for clarithromycin also applies to the combination regimen. Refer to the prescribing information for clarithromycin for more information on use in pregnancy.
Data Human Data Available data from published observational studies failed to demonstrate an association of adverse pregnancy-related outcomes and lansoprazole use. Methodological limitations of these observational studies cannot definitely establish or exclude any drug-associated risk during pregnancy. In a prospective study by the European Network of Teratology Information Services, outcomes from a group of 62 pregnant women administered median daily doses of 30 mg of lansoprazole were compared to a control group of 868 pregnant women who did not take any PPIs.
There was no difference in the rate of major malformations between women exposed to PPIs and the control group, corresponding to a Relative Risk (RR) = 1.04, [95% Confidence Interval (CI) 0.25-4.21]. In a population-based retrospective cohort study covering all live births in Denmark from 1996 to 2008, there was no significant increase in major birth defects during analysis of first trimester exposure to lansoprazole in 794 live births. A meta-analysis that compared 1,530 pregnant women exposed to PPIs in at least the first trimester with 133,410 unexposed pregnant women showed no significant increases in risk for congenital malformations or spontaneous abortion with exposure to PPIs (for major malformations Odds Ratio (OR) = 1.12, [95% CI 0.86-1.45] and for spontaneous abortions OR = 1.29, [95% CI 0.84-1.97]).
Animal Data No adverse effects on embryo-fetal development occurred in studies performed in pregnant rats at oral lansoprazole doses up to 150 mg/kg/day (40 times the recommended human dose [30 mg/day] based on body surface area) administered during organogenesis and pregnant rabbits at oral lansoprazole doses up to 30 mg/kg/day (16 times the recommended human dose based on body surface area) administered during organogenesis. A pre- and postnatal developmental toxicity study in rats with additional endpoints to evaluate bone development was performed with lansoprazole at oral doses of 10 to 100 mg/kg/day (0.7 to 6.4 times the maximum recommended human lansoprazole dose of 30 mg based on AUC [area under the plasma concentration-time curve]) administered during organogenesis through lactation.
Maternal effects observed at 100 mg/kg/day (6.4 times the maximum recommended human lansoprazole dose of 30 mg based on AU…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published observational studies overall do not indicate an association of adverse pregnancy outcomes with lansoprazole treatment (see Data ) . In animal reproduction studies, oral administration of lansoprazole to rats during organogenesis through lactation at 6.4 times the maximum recommended human dose produced reductions in the offspring in femur weight, femur length, crown-rump length and growth plate thickness (males only) on postnatal Day 21 (see Data ) . These effects were associated with reduction in body weight gain.
Advise pregnant women of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. If lansoprazole delayed-release orally disintegrating tablets are administered with clarithromycin, the pregnancy information for clarithromycin also applies to the combination regimen. Refer to the prescribing information for clarithromycin for more information on use in pregnancy.
Data Human Data Available data from published observational studies failed to demonstrate an association of adverse pregnancy-related outcomes and lansoprazole use. Methodological limitations of these observational studies cannot definitely establish or exclude any drug-associated risk during pregnancy. In a prospective study by the European Network of Teratology Information Services, outcomes from a group of 62 pregnant women administered median daily doses of 30 mg of lansoprazole were compared to a control group of 868 pregnant women who did not take any PPIs.
There was no difference in the rate of major malformations between women exposed to PPIs and the control group, corresponding to a Relative Risk (RR) = 1.04, [95% Confidence Interval (CI) 0.25-4.21]. In a population-based retrospective cohort study covering all live births in Denmark from 1996 to 2008, there was no significant increase in major birth defects during analysis of first trimester exposure to lansoprazole in 794 live births. A meta-analysis that compared 1,530 pregnant women exposed to PPIs in at least the first trimester with 133,410 unexposed pregnant women showed no significant increases in risk for congenital malformations or spontaneous abortion with exposure to PPIs (for major malformations Odds Ratio (OR) = 1.12, [95% CI 0.86-1.45] and for spontaneous abortions OR = 1.29, [95% CI 0.84-1.97]).
Animal Data No adverse effects on embryo-fetal development occurred in studies performed in pregnant rats at oral lansoprazole doses up to 150 mg/kg/day (40 times the recommended human dose [30 mg/day] based on body surface area) administered during organogenesis and pregnant rabbits at oral lansoprazole doses up to 30 mg/kg/day (16 times the recommended human dose based on body surface area) administered during organogenesis. A pre- and postnatal developmental toxicity study in rats with additional endpoints to evaluate bone development was performed with lansoprazole at oral doses of 10 to 100 mg/kg/day (0.7 to 6.4 times the maximum recommended human lansoprazole dose of 30 mg based on AUC [area under the plasma concentration-time curve]) administered during organogenesis through lactation.
Maternal effects observed at 100 mg/kg/day (6.4 times the maximum recommended human lansoprazole dose of 30 mg based on AUC) included increased gestation period, decreased body weight gain during gestation, and decreased food consumption. The number of stillbirths was increased at this dose, which may have been secondary to maternal toxicity. Body weight of pups was reduced at 100 mg/kg/day starting on postnatal Day 11.
Femur weight, femur length, and crown-rump length were reduced at 100 mg/kg/day…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of lansoprazole delayed-release orally disintegrating tablets have been established in pediatric patients one year to 17 years of age for short-term treatment of symptomatic GERD and erosive esophagitis. In clinical studies of symptomatic GERD and erosive esophagitis, lansoprazole was not administered beyond 12 weeks in patients one year to 11 years of age. It is not known if lansoprazole delayed-release orally disintegrating tablets are safe and effective if used longer than the recommended duration.
Do not exceed the recommended dose and duration of use in pediatric patients (see Juvenile Animal Toxicity Data ) . Lansoprazole was not effective in pediatric patients with symptomatic GERD one month to less than one year of age in a multicenter, double-blind, placebo-controlled study. Therefore, safety and effectiveness have not been established in patients less than one year of age.
Nonclinical studies in juvenile rats have demonstrated an adverse effect of heart valve thickening and bone changes at lansoprazole doses higher than the maximum recommended equivalent human dose. Neonate to Less Than One Year of Age The pharmacokinetics of lansoprazole were studied in pediatric patients with GERD aged less than 28 days and one to 11 months. Compared to healthy adults receiving 30 mg, neonates had higher exposure (mean weight-based normalized AUC values 2.04- and 1.88-fold higher at doses of 0.5 and 1 mg/kg/day, respectively).
Infants aged ≤ 10 weeks had clearance and exposure values that were similar to neonates. Infants aged greater than 10 weeks who received 1 mg/kg/day had mean AUC values that were similar to adults who received a 30 mg dose. Lansoprazole was not found to be effective in a U.S. and Polish four week, multicenter, double-blind, placebo-controlled, parallel-group study of 162 patients between one month and less than 12 months of age with symptomatic GERD based on a medical history of crying/fussing/irritability associated with feedings who had not responded to conservative GERD management (i.e., nonpharmacologic intervention) for seven to 14 days.
Patients received lansoprazole as a suspension daily (0.2 to 0.3 mg/kg/day in infants ≤ 10 weeks of age or 1.0 to 1.5 mg/kg/day in infants greater than 10 weeks or placebo) for up to four weeks of double-blind treatment. The primary efficacy endpoint was assessed by greater than 50% reduction from baseline in either the percent of feedings with a crying/fussing/irritability episode or the duration (minutes) of a crying/fussing/irritability episode within one hour after feeding. There was no difference in the percentage of responders between the lansoprazole pediatric suspension group and placebo group (54% in both groups).
There were no adverse events reported in pediatric clinical studies (one month to less than 12 months of age) that were not previously observed in adults. Based on the results of the Phase 3 efficacy study, lansoprazole was not shown to be effective. Therefore, these results do not support the use of lansoprazole in treating symptomatic GERD in infants.
One Year to 11 Years of Age In an uncontrolled, open-label, U.S. multicenter study, 66 pediatric patients (one year to 11 years of age) with GERD were assigned, based on body weight, to receive an initial dose of either lansoprazole 15 mg daily if ≤ 30 kg or lansoprazole 30 mg daily if greater than 30 kg administered for eight to 12 weeks. The lansoprazole dose was increased (up to 30 mg twice daily) in 24 of 66 pediatric patients after two or more weeks of treatment if they remained symptomatic. At baseline, 85% of patients had mild to moderate overall GERD symptoms (assessed by investigator interview), 58% had non-erosive GERD and 42% had erosive esophagitis (assessed by endoscopy).
After eight to 12 weeks of lansoprazole treatment, the intent-to-treat analysis demonstrated an approximate 50% reduction in frequency and severity of GERD symptoms. Twenty-on…
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients (n = 21,486) in clinical studies of lansoprazole, 16% of patients were aged 65 years and over, while 4% were 75 years and over. No overall differences in safety or effectiveness were observed between these patients and younger patients and other reported clinical experience has not identified significant differences in responses between geriatric and younger patients, but greater sensitivity of some older individuals cannot be ruled out [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE Lansoprazole is not removed from the circulation by hemodialysis. In one reported overdose, a patient consumed 600 mg of lansoprazole with no adverse reaction. Oral lansoprazole doses up to 5000 mg/kg in rats [approximately 1300 times the 30 mg human dose based on body surface area (BSA)] and in mice (about 675.7 times the 30 mg human dose based on BSA) did not produce deaths or any clinical signs.
In the event of over-exposure, treatment should be symptomatic and supportive. If over-exposure occurs, call your poison control center at 1-800-222-1222 for current information on the management of poisoning or over-exposure.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lansoprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that suppress gastric acid secretion by specific inhibition of the (H + , K + )-ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the parietal cell, lansoprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production. This effect is dose-related and leads to inhibition of both basal and stimulated gastric acid secretion irrespective of the stimulus.
Lansoprazole does not exhibit anticholinergic or histamine type-2 antagonist activity.
12.2Pharmacodynamics Antisecretory Activity After oral administration, lansoprazole was shown to significantly decrease the basal acid output and significantly increase the mean gastric pH and percent of time the gastric pH was greater than three and greater than four. Lansoprazole also significantly reduced meal-stimulated gastric acid output and secretion volume, as well as pentagastrin-stimulated acid output. In patients with hypersecretion of acid, lansoprazole significantly reduced basal and pentagastrin-stimulated gastric acid secretion.
Lansoprazole inhibited the normal increases in secretion volume, acidity and acid output induced by insulin. The intragastric pH results of a five day, pharmacodynamic, crossover study of 15 and 30 mg of once daily lansoprazole are presented in Table 6 : Table 6. Mean Antisecretory Effects After Single and Multiple Daily Lansoprazole Dosing NOTE: An intragastric pH of greater than four reflects a reduction in gastric acid by 99%.
Lansoprazole Parameter Baseline Value 15 mg 30 mg Day 1 Day 5 Day 1 Day 5 Mean 24 Hour pH 2.1 2.7 (p < 0.05) vs baseline only. 4.0 3.6 (p < 0.05) vs baseline and lansoprazole 15 mg.
4.9Mean Nighttime pH 1.9 2.4 3.0 2.6 3.8 % Time Gastric pH > 3 18 33 59 51 72 % Time Gastric pH > 4 12 22 49 41 66 After the initial dose in this study, increased gastric pH was seen within one to two hours with 30 mg of lansoprazole and two to three hours with 15 mg of lansoprazole. After multiple daily dosing, increased gastric pH was seen within the first hour postdosing with 30 mg of lansoprazole and within one to two hours postdosing with 15 mg of lansoprazole. Acid suppression may enhance the effect of antimicrobials in eradicating Helicobacter pylori (H. pylori) .
The percentage of time gastric pH was elevated above five and six was evaluated in a crossover study of lansoprazole given daily, twice daily and three times daily (Table 7) . Table 7. Mean Antisecretory Effects After Five Days of Twice Daily and Three Times Daily Dosing Lansoprazole Parameter 30 mg daily 15 mg twice daily 30 mg twice daily 30 mg three times daily % Time Gastric pH > 5 43 47 59 (p < 0.05) vs lansoprazole 30 mg daily.
77 (p < 0.05) vs lansoprazole 30 mg daily, 15 and 30 mg twice daily. % Time Gastric pH > 6 20 23 28 45 The inhibition of gastric acid secretion as measured by intragastric pH gradually returned to normal over two to four days after multiple doses. There was no indication of rebound gastric acidity. Enterochromaffin-like (ECL) Cell Effects During lifetime exposure of rats with up to 150 mg/kg/day of lansoprazole dosed seven days per week, marked hypergastrinemia was observed followed by ECL cell proliferation and formation of carcinoid tumors, especially in female rats.
Gastric biopsy specimens from the body of the stomach from approximately 150 patients treated continuously with lansoprazole for at least one year did not show evidence of ECL cell effects similar to those seen in rat studies. Longer term data are needed to rule out the possibility of an increased risk of the development of gastric tumors in patients receiving long-term therapy with lansoprazole [see Nonclinical Toxicology (13.1) ] . Other Gastric Effects in Humans Lansoprazole did not significantly af…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lansoprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that suppress gastric acid secretion by specific inhibition of the (H + , K + )-ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the parietal cell, lansoprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production. This effect is dose-related and leads to inhibition of both basal and stimulated gastric acid secretion irrespective of the stimulus.
Lansoprazole does not exhibit anticholinergic or histamine type-2 antagonist activity.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Lansoprazole Delayed-Release Orally Disintegrating Tablets are available containing 15 mg or 30 mg of lansoprazole, USP. The 15 mg tablets are pale yellow, round, flat-faced, speckled, unscored tablets debossed with M on one side of the tablet and LP1 on the other side. They are available as follows: NDC 0378-6981-88 cartons of 100 unit-dose tablets (10 x 10) The 30 mg tablets are pale yellow, round, flat-faced, speckled, unscored tablets debossed with M on one side of the tablet and LP2 on the other side.
They are available as follows: NDC 0378-6982-88 cartons of 100 unit-dose tablets (10 x 10) Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
11 DESCRIPTION The active ingredient in lansoprazole delayed-release orally disintegrating tablets is lansoprazole, a substituted benzimidazole, 2-[[[3-methyl-4-(2,2,2-trifluoro-ethoxy)-2-pyridinyl]methyl]sulfinyl]-1H-benzimidazole, a compound that inhibits gastric acid secretion. Its molecular formula is C 16 H 14 F 3 N 3 O 2 S with a molecular weight of 369.37. Lansoprazole has the following structure: Lansoprazole, USP is a white to brownish-white powder which melts with decomposition at approximately 166°C.
Lansoprazole is freely soluble in dimethylformamide; soluble in methanol; sparingly soluble in ethanol; slightly soluble in ethyl acetate, dichloromethane and acetonitrile; very slightly soluble in ether; and practically insoluble in hexane and water. Lansoprazole is stable when exposed to light for up to two months. The rate of degradation of the compound in aqueous solution increases with decreasing pH.
The degradation half-life of the drug substance in aqueous solution at 25°C is approximately 0.5 hour at pH 5.0 and approximately 18 hours at pH 7.0. Lansoprazole is supplied in delayed-release orally disintegrating tablets for oral administration. Lansoprazole delayed-release orally disintegrating tablets are available in two dosage strengths: 15 and 30 mg of lansoprazole per tablet.
Each delayed-release orally disintegrating tablet contains enteric-coated pellets consisting of 15 or 30 mg of lansoprazole (active ingredient) and the following inactive ingredients: artificial strawberry flavor, aspartame 1 , citric acid monohydrate, crospovidone, hydroxypropyl cellulose, magnesium carbonate, magnesium stearate, mannitol, methacrylic acid copolymer type C, microcrystalline cellulose, polyethylene glycol, polysorbate 80, sodium bicarbonate, sodium hydroxide, sodium lauryl sulfate, sodium starch glycolate (potato), sugar spheres (corn starch and sucrose), talc, triethyl citrate and yellow iron oxide.
1 Phenylketonurics: Lansoprazole delayed-release orally disintegrating tablets contain phenylalanine 3.37 mg per 15 mg tablet and 6.74 mg per 30 mg tablet. Lansoprazole Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide and Instructions for Use ). Advise patients to: Acute Tubulointerstitial Nephritis: To call their healthcare provider if they experience signs and/or symptoms associated with acute tubulointerstitial nephritis [see Warnings and Precautions (5.2) ] . Clostridium difficile -Associated Diarrhea: To immediately call their healthcare provider if they experience diarrhea that does not improve [see Warnings and Precautions (5.3) ] .
Bone Fracture: To report any fractures, especially of the hip, wrist or spine, to their healthcare provider [see Warnings and Precautions (5.4) ] . Severe Cutaneous Adverse Reactions: To discontinue lansoprazole delayed-release orally disintegrating tablets and immediately call their healthcare provider for further evaluation [see Warnings and Precautions (5.5) ] . Cutaneous and Systemic Lupus Erythematosus: To immediately call their healthcare provider for any new or worsening of symptoms associated with cutaneous or systemic lupus erythematosus [see Warnings and Precautions (5.6) ] .
Cyanocobalamin (Vitamin B12) Deficiency: To report any clinical symptoms that may be associated with cyanocobalamin deficiency to their healthcare provider, if they have been receiving lansoprazole delayed-release orally disintegrating tablets for longer than three years [see Warnings and Precautions (5.7) ] . Hypomagnesemia and Mineral Metabolism: To report any clinical symptoms that may be associated with hypomagnesemia, hypocalcemia, and/or hypokalemia to their healthcare provider, if they have been receiving lansoprazole delayed-release orally disintegrating tablets for at least three months [see Warnings and Precautions (5.8) ] .
Drug Interactions: Advise patients to report to their healthcare provider if they are taking rilpivirine-containing products [see Contraindications (4) ] or high-dose methotrexate [see Warnings and Precautions (5.10) ] . Pregnancy: Advise a pregnant woman of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Use in Specific Populations (8.1) ] .
Administration: • Missed doses: If a dose is missed, administer as soon as possible. However, if the next scheduled dose is due, do not take the missed dose, and take the next dose on time. Do not take two doses at one time to make up for a missed dose. • Lansoprazole delayed-release orally disintegrating tablets should be taken before eating. • Do not crush or chew lansoprazole delayed-release orally disintegrating tablets. • Take lansoprazole delayed-release orally disintegrating tablets at least 30 minutes prior to sucralfate. • Phenylketonurics: Contains phenylalanine 3.37 mg per 15 mg lansoprazole delayed-release orally disintegrating tablet and 6.74 mg per 30 mg lansoprazole delayed-release orally disintegrating tablet.
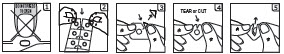
Lansoprazole Delayed-Release Orally Disintegrating Tablets: • Do not break or cut. • Place the tablet on the tongue; allow it to disintegrate, with or without water, until the pellets can be swallowed. Do not chew the pellets. • The tablet typically disintegrates in less than one minute. • Alternatively, for children or other patients who have difficulty swallowing tablets, lansoprazole delayed-release orally disintegrating tablets can be administered with water via oral syringe or NG tube, as described in the Instructions for Use.
💬 Medication Guide ▾
Medication Guide Lansoprazole Delayed-Release Orally Disintegrating Tablets (lan soe′ pra zole) What is the most important information that I should know about lansoprazole delayed-release orally disintegrating tablets? You should take lansoprazole delayed-release orally disintegrating tablets exactly as prescribed, at the lowest dose possible and for the shortest time needed. Lansoprazole delayed-release orally disintegrating tablets may help your acid-related symptoms, but you could still have serious stomach problems.
Talk with your doctor. Lansoprazole delayed-release orally disintegrating tablets can cause serious side effects, including: • A type of kidney problem (acute tubulointerstitial nephritis). Some people who take proton pump inhibitor (PPI) medicines, including lansoprazole delayed-release orally disintegrating tablets, may develop a kidney problem called acute tubulointerstitial nephritis that can happen at any time during treatment with PPI medicines including lansoprazole delayed-release orally disintegrating tablets.
Call your doctor right away if you have a decrease in the amount that you urinate or if you have blood in your urine. • Diarrhea caused by an infection ( Clostridium difficile ) in your intestines. Call your doctor right away if you have watery stools or stomach pain that does not go away. You may or may not have a fever. • Bone fractures (hip, wrist, or spine).
Bone fractures in the hip, wrist, or spine may happen in people who take multiple daily doses of PPI medicines and for a long period of time (a year or longer). Tell your doctor if you have a bone fracture, especially in the hip, wrist, or spine. • Certain types of lupus erythematosus. Lupus erythematosus is an autoimmune disorder (the body’s immune cells attack other cells or organs in the body).
Some people who take PPI medicines, including lansoprazole delayed-release orally disintegrating tablets, may develop certain types of lupus erythematosus or have worsening of the lupus they already have. Call your doctor right away if you have new or worsening joint pain or a rash on your cheeks or arms that gets worse in the sun. Talk to your doctor about your risk of these serious side effects.
Lansoprazole delayed-release orally disintegrating tablets can have other serious side effects. See “What are the possible side effects of lansoprazole delayed-release orally disintegrating tablets?” . What are lansoprazole delayed-release orally disintegrating tablets?
A prescription medicine called a proton pump inhibitor (PPI) used to reduce the amount of acid in your stomach. In adults, lansoprazole delayed-release orally disintegrating tablets are used for: • 4 weeks for the healing and symptom relief of duodenal ulcers. • 10 to 14 days with certain antibiotics to treat an infection caused by bacteria called H. pylori . • maintaining healing of duodenal ulcers. Lansoprazole has not been studied beyond 12 months for this purpose. • up to 8 weeks for the healing and symptom relief of stomach ulcers. • up to 8 weeks for the healing of stomach ulcers in people taking pain medicines called nonsteroidal anti-inflammatory drugs (NSAIDs).
Lansoprazole has not been studied beyond 8 weeks for this purpose. • reducing the risk of stomach ulcers in people who are at risk of developing stomach ulcers with NSAIDs. Lansoprazole has not been studied beyond 12 weeks for this purpose. • up to 8 weeks to treat heartburn and other symptoms that happen with gastroesophageal reflux disease (GERD). GERD happens when acid in your stomach backs up into the tube (esophagus) that connects your mouth to your stomach.
This may cause a burning feeling in your chest or throat, sour taste or burping. • up to 8 weeks for the healing and symptom relief of acid-related damage to the lining of the esophagus (called erosive esophagitis or EE). Your doctor may prescribe another 8 to 16 weeks of lansoprazole delayed-release orally disintegrating tablets for patients whose EE does not…