
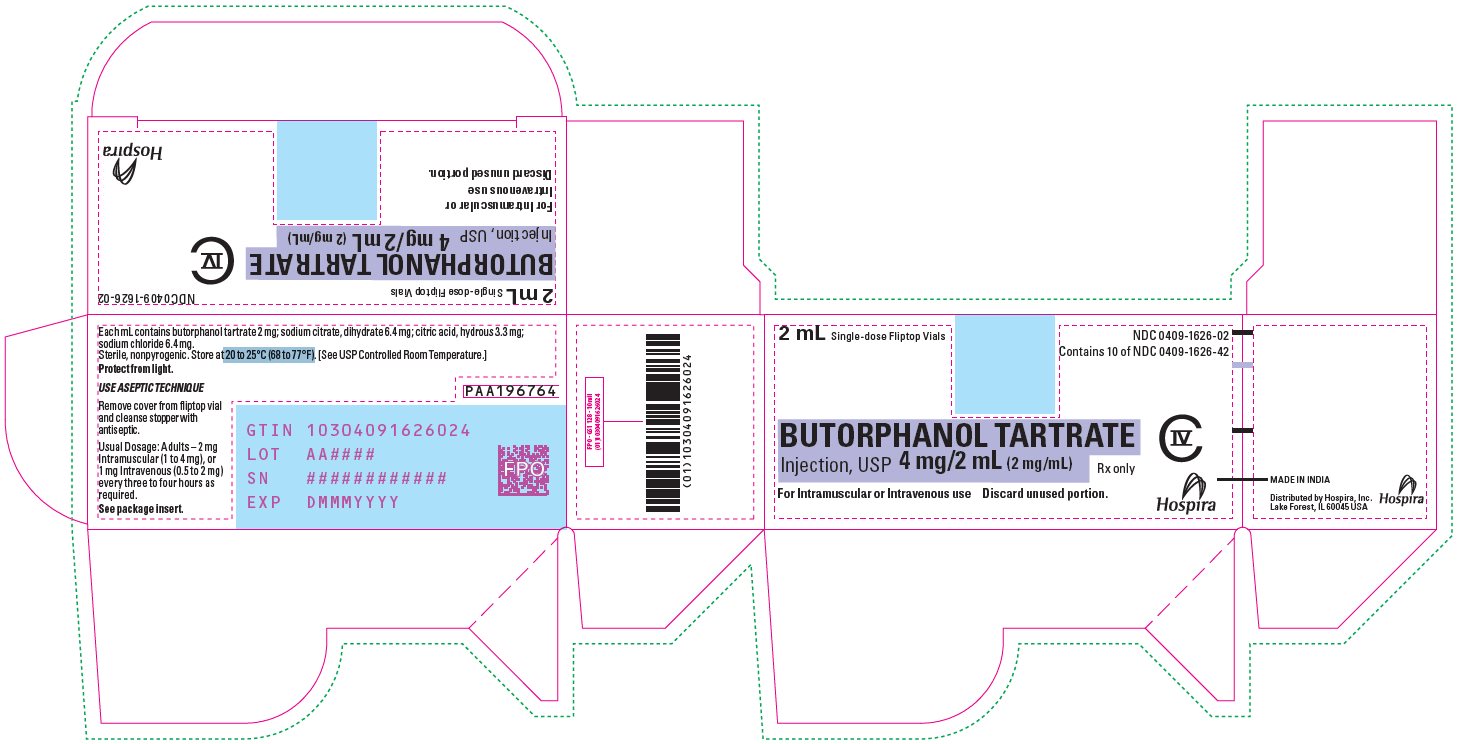
Butorphanol Tartrate 2 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Opioid Agonist/Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Butorphanol injection is used to relieve severe pain. Butorphanol injection is also used to relieve pain during labor and to prevent pain and decrease awareness before or during surgery. Butorphanol is in a class of medications called opioid agonist-antagonists. It works by changing the way the body senses pain.
Read the full MedlinePlus article ↗- Butorphanol injection is an opioid pain medication used in medical settings for a few specific purposes: managing severe pain that other treatments can't adequately control, prepar...
- What is butorphanol injection actually used for?
- If it's given into your vein (IV), you can start feeling pain relief within just a few minutes, with the peak effect hitting around 30 to 60 minutes. If it's given as a muscle inje...
- How fast does butorphanol injection work, and how long does it last?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
3.3 mg / 1 mL
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
6.4 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
6.4 mg / 1 mL
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0595 | $10.508 / J0595 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Butorphanol Tartrate 2 mg/mLthis 00409-1626-02 | Hospira, | 10 vials | — | AP | FDA listed | — |
| Butorphanol Tartrate 2 mg/mL 00143-9867-10 | Hikma | 1 ml | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-1626-01 | 10 VIAL, SINGLE-DOSE in 1 CARTON (0409-1626-01) / 1 mL in 1 VIAL, SINGLE-DOSE (0409-1626-21) | 2006-03-17 | Active |
| 00409-1626-02 You're viewing this | 10 VIAL, SINGLE-DOSE in 1 CARTON (0409-1626-02) / 2 mL in 1 VIAL, SINGLE-DOSE (0409-1626-42) | 2005-12-20 | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 00409-1626-02?
What NDC number is used to bill for this package of Butorphanol Tartrate 2 mg/mL Injection, Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF BUTORPHANOL TARTRATE INJECTION Addiction, Abuse, and Misuse Because the use of Butorphanol Tartrate Injection exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient’s risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [see WARNINGS ] . Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of Butorphanol Tartrate Injection, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of Butorphanol Tartrate Injection are essential [see WARNINGS ] . Risks From Concomitant Use With Benzodiazepines Or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of Butorphanol Tartrate Injection and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate [see WARNINGS , PRECAUTIONS ; Drug Interactions ] .
Neonatal Opioid Withdrawal Syndrome (NOWS) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery [see WARNINGS ] .
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Butorphanol Tartrate Injection is indicated - as a preoperative or pre-anesthetic medication - as a supplement to balanced anesthesia - for the relief of pain during labor, and - for the management of pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate. Limitations of Use: Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy [see WARNINGS ], reserve opioid analgesics, including butorphanol tartrate, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Important Dosage and Administration Instructions Butorphanol Tartrate Injection should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals [see WARNINGS ]. Because the risk of overdose increases as opioid doses increase, reserve titration to higher doses of Butorphanol Tartrate Injection for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks. There is variability in the opioid analgesic dose and duration needed to adequately manage pain due both to the cause of pain and to individual patient factors.
Initiate the dosing regimen for each patient individually, taking into account the patient’s underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse [see WARNINGS ]. Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with Butorphanol Tartrate Injection. Consider this risk when selecting an initial dose and when making dose adjustments [see WARNINGS ].
Initial Dosage Factors to be considered in determining the dose are age, body weight, physical status, underlying pathological condition, use of other drugs, type of anesthesia to be used, and surgical procedure involved. Use in the elderly, patients with hepatic or renal disease, or in labor requires extra caution [see PRECAUTIONS ; CLINICAL PHARMACOLOGY: Individualization of Dosage ]. The following doses are for patients who do not have impaired hepatic or renal function and who are not on CNS active agents.
Use for Pain Intravenous The usual recommended single-dose for IV administration is 1 mg repeated every three to four hours as necessary. The effective dosage range, depending on the severity of pain, is 0.5 to 2 mg repeated every three to four hours. Intramuscular The usual recommended single-dose for IM administration is 2 mg in patients who will be able to remain recumbent, in the event drowsiness or dizziness occurs.
This may be repeated every three to four hours, as necessary. The effective dosage range depending on the severity of pain is 1 to 4 mg repeated every three to four hours. There are insufficient clinical data to recommend single-doses above 4 mg.
Use as Preoperative/Preanesthetic Medication The preoperative medication dosage of Butorphanol Tartrate Injection should be individualized [see CLINICAL PHARMACOLOGY: Individualization of Dosage ]. The usual adult dose is 2 mg IM, administered 60 to 90 minutes before surgery. This is approximately equivalent in sedative effect to 10 mg morphine or 80 mg meperidine.
Use in Balanced Anesthesia The usual dose of Butorphanol Tartrate Injection is 2 mg IV shortly before induction and/or 0.5 to 1 mg IV in increments during anesthesia. The increment may be higher, up to 0.06 mg/kg (4 mg/70 kg), depending on previous sedative, analgesic, and hypnotic drugs administered. The total dose of butorphanol injection will vary; however, patients seldom require less than 4 mg or more than 12.5 mg (approximately 0.06 to 0.18 mg/kg).
Labor In patients at full term in early labor a 1 to 2 mg dose of butorphanol tartrate IV or IM may be administered and repeated after 4 hours. Alternative analgesia should be used for pain associated with delivery or if delivery is expected to occur within 4 hours. If concomitant use of butorphanol with drugs that may potentiate its effects is deemed necessary [see PRECAUTIONS: Drug Interactions ] the lowest effective dose should be employed.
Dosage Modifications in Elderly Patients and Patients with Renal or Hepatic Impairment The initial dose sequence in elderly patients and patients with hepatic or renal impairmen…
⛔ Contraindications ▾
CONTRAINDICATIONS Butorphanol Tartrate Injection is contraindicated in: • Patients with significant respiratory depression [see WARNINGS ] • Patients with acute of severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see WARNINGS ] • Patients with known or suspected gastrointestinal obstruction, including paralytic ileus [see WARNINGS ] • Patients with hypersensitivity to butorphanol tartrate or any of the formulation excipients (e.g., anaphylaxis) [see WARNINGS ]
⚠️ Warnings ▾
WARNINGS Addiction, Abuse, and Misuse Butorphanol Tartrate Injection is a Schedule IV controlled substance. As an opioid, butorphanol tartrate exposes users to the risks of addiction, abuse, and misuse [see DRUG ABUSE AND DEPENDENCE ]. Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed butorphanol tartrate.
Addiction can occur at recommended dosages and if the drug is misused or abused. The risk of opioid-related overdose or overdose-related death is increased with higher opioid doses, and this risk persists over the course of therapy. In postmarketing studies, addiction, abuse, misuse, and fatal and non-fatal opioid overdose were observed in patients with long-term opioid use [see ADVERSE REACTIONS ].
Assess each patient's risk for opioid addiction, abuse, or misuse prior to prescribing Butorphanol Tartrate Injection, and monitor all patients receiving butorphanol tartrate for the development of these behaviors or conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression). The potential for these risks should not, however, prevent the proper management of pain in any given patient.
Patients at increased risk may be prescribed opioids such as Butorphanol Tartrate Injection, but use in such patients necessitates intensive counseling about the risks and proper use of Butorphanol Tartrate Injection along with frequent monitoring for signs of addiction, abuse, and misuse. Opioids are sought for nonmedical use and are subject to diversion from legitimate prescribed use. Consider these risks when prescribing or dispensing Butorphanol Tartrate Injection. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity.
Contact local state professional licensing board or state-controlled substances authority for information on how to prevent and detect abuse or diversion of this product. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death.
Management of respiratory depression may include close observation, supportive measures, and use of opioid overdose reversal agents (e.g., naloxone, nalmefene), depending on the patient's clinical status [see OVERDOSAGE ]. Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids. While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of butorphanol tartrate, the risk is greatest during the initiation of therapy or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of butorphanol tartrate are essential [see DOSAGE AND ADMINISTRATION ]. Overestimating the butorphanol tartrate dosage when converting patients from another opioid product can result in a fatal overdose with the first dose. Opioids can cause sleep-related breathing disorders including central sleep apnea (CSA) and sleep-related hypoxemia.
Opioid use increases the risk of CSA in a dose-dependent fashion. In patients who present with CSA, consider decreasing the opioid dosage using best practices for opioid taper [see DOSAGE AND ADMINISTRATION ]. Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants Profound sedation, respiratory depression, coma, and death may result from the concomitant use of butorphanol tartrate with benzodiazepines and/or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids).
Because of these risks, reserve concomitant…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical Trial Experience A total of 1658 patients were studied in premarketing clinical trials of Butorphanol Tartrate Injection. In nearly all cases the type and incidence of side effects with butorphanol were those commonly observed with opioid analgesics. The adverse experiences described below are based on data from short- and long-term clinical trials in patients receiving Butorphanol Tartrate Injection.
The most frequently reported adverse experiences across all clinical trials with Butorphanol Tartrate Injection and Nasal Spray were somnolence (43%), dizziness (19%), nausea and/or vomiting (13%). The following adverse experiences were reported at a frequency of 1% or greater in clinical trials and were considered to be probably related to the use of butorphanol: Body as a Whole: Asthenia/Lethargy, Headache, Sensation of Heat Cardiovascular: Vasodilation, Palpitations Digestive: Anorexia, Constipation, Dry Mouth, Nausea and/or Vomiting, Stomach Pain Nervous: Anxiety, Confusion, Dizziness, Euphoria, Floating Feeling, Insomnia, Nervousness, Paresthesia, Somnolence, Tremor Respiratory: Cough, Dyspnea Skin and Appendages: Sweating, Pruritus Special Senses: Blurred Vision, Ear Pain, Tinnitus, Unpleasant Taste The following adverse experiences were reported with a frequency of less than 1% in clinical trials and were considered to be probably related to the use of butorphanol: Cardiovascular: Hypotension, Syncope Nervous: Abnormal Dreams, Agitation, Dysphoria, Hallucinations, Hostility, Withdrawal Symptoms Skin and Appendages: Rash/Hives Urogenital: Impaired Urination The following infrequent additional adverse experiences were reported in a frequency of less than 1% of the patients studied in short-term butorphanol tartrate nasal sprays trials and under circumstances where the association between these events and butorphanol administration is unknown.
They are being listed as alerting information for the physician due to their clinical significance: Body as a Whole: Edema Cardiovascular: Chest Pain, Hypertension, Tachycardia Nervous: Depression Respiratory: Shallow Breathing Postmarketing Experience The following adverse reactions have been identified during post approval use of Butorphanol Tartrate Injection. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. • Serotonin syndrome: Cases of serotonin syndrome, a potentially life-threatening condition, have been reported during concomitant use of opioids with serotonergic drugs. • Adrenal insufficiency: Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. • Anaphylaxis: Anaphylaxis has been reported with ingredients contained in Butorphanol Tartrate Injection. • Androgen deficiency: Cases of androgen deficiency have occurred with use of opioids for an extended period of time [see CLINICAL PHARMACOLOGY ]. • Hyperalgesia and Allodynia: Cases of hyperalgesia and allodynia have been reported with opioid therapy of any duration [see WARNINGS ]. • Hypoglycemia: Cases of hypoglycemia have been reported in patients taking opioids.
Most reports were in patients with at least one predisposing risk factor (e.g., diabetes). • Opioid-induced esophageal dysfunction (OIED): Cases of OIED have been reported in patients taking opioids and may occur more frequently in patients taking higher doses of opioids, and/or in patients taking opioids longer term [see WARNINGS ]. Adverse Reactions from Observational Studies A prospective, observational cohort study estimated the risks of addiction, abuse, and misuse in patients initiating long-term use of Schedule II opioid analgesics between 2017 and 2021.
Study participants included in one or more analyses had been enrolled in selected insurance plans or health systems for at least one year, were free of at least on…
🔄 Drug Interactions ▾
Drug Interactions Benzodiazepines and Other Central Nervous System (CNS) Depressants Due to additive pharmacologic effect, the concomitant use of benzodiazepines or other CNS depressants such as alcohol, sedatives/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids (gabapentin or pregabalin), and other opioids, can increase the risk of respiratory depression, profound sedation, coma, and death. Reserve concomitant prescribing of these drugs for use in patients for whom alternative treatment options are inadequate.
Limit dosages and durations to the minimum required. Monitor patients closely for signs of respiratory depression and sedation [see WARNINGS ]. If concomitant use is warranted, consider prescribing naloxone for the emergency treatment of opioid overdose.
Serotonergic Drugs The concomitant use of opioids with other drugs that affect the serotonergic neurotransmitter system, such as selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), tricyclic antidepressants (TCAs), triptans, 5-HT3 receptor antagonists, drugs that affect the serotonin neurotransmitter system (e.g., mirtazapine, trazodone, tramadol), certain muscle relaxants (eg., cyclobenzaprine, metaxalone), and monoamine oxidase (MAO) inhibitors (those intended to treat psychiatric disorders and also others, such as linezolid and intravenous methylene blue), has resulted in serotonin syndrome [see PRECAUTIONS; INFORMATION FOR PATIENTS ].
If concomitant use is warranted, regularly monitor the patient, particularly during treatment initiation and dose adjustment. Discontinue Butorphanol Tartrate Injection if serotonin syndrome is suspected. Cytochrome P450 (CYP 450) Interactions It is not known if the effects of Butorphanol Tartrate Injection are altered by concomitant medications that affect hepatic metabolism of drugs (CYP 450 inhibitors or inducers) (e.g., erythromycin, theophylline, etc.), but physicians should be alert to the possibility that a smaller initial dose and longer intervals between doses may be needed.
Monoamine Oxidase inhibitors (MAOIs) No information is available about the use of butorphanol concurrently with MAO inhibitors. Advise patient to avoid concomitant use of these drugs.
🤰 Pregnancy ▾
Pregnancy Reproduction studies in mice, rats, and rabbits during organogenesis did not reveal any teratogenic potential to butorphanol. However, pregnant rats treated subcutaneously with butorphanol at 1 mg/kg (5.9 mg/m 2 ) had a higher frequency of stillbirths than controls. Butorphanol at 30 mg/kg/oral (360 mg/m 2 ) and 60 mg/kg/oral (720 mg/m 2 ) also showed higher incidences of post‑implantation loss in rabbits.
There are no adequate and well-controlled studies of Butorphanol Tartrate Injection in pregnant women before 37 weeks of gestation. Butorphanol Tartrate Injection should be used during pregnancy only if the potential benefit justifies the potential risk to the infant. Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see WARNINGS ].
🧒 Pediatric Use ▾
Pediatric Use Butorphanol is not recommended for use in patients below 18 years of age because safety and efficacy have not been established in this population.
🧓 Geriatric Use ▾
Geriatric Use Elderly patients (aged 65 years or older) may have increased sensitivity to butorphanol tartrate. In general, use caution when selecting a dosage for an elderly patient, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Respiratory depression is the chief risk for elderly patients treated with opioids, and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of Butorphanol Tartrate Injection slowly in geriatric patients and frequently monitor the patient for signs of central nervous system and respiratory depression [see WARNINGS ]. This drug is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
OVERDOSAGE Clinical Presentation Acute overdose with butorphanol tartrate can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see CLINICAL PHARMACOLOGY ]. Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
Treatment of Overdose In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures.
For clinically significant respiratory or circulatory depression secondary to butorphanol tartrate overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene. As butorphanol is a mixed opioid agonist/antagonist, larger doses of naloxone or nalmefene may be needed to reverse the effects of an overdose. Opioid antagonists should not be administered in the absence of clinically significant respiratory or circulatory depression secondary to butorphanol tartrate overdose.
Because the duration of opioid reversal is expected to be less than the duration of action of butorphanol in Butorphanol Tartrate Injection, carefully monitor the patient until spontaneous respiration is reliably re-established. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product's prescribing information. In an individual physically dependent on opioids, administration of the recommended usual dosage of the overdose reversal agent will precipitate an acute withdrawal syndrome.
The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically-dependent patient, administration of the reversal agent should be begun with care and by titration with smaller than usual doses of the reversal agent.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Butorphanol is a partial opioid agonist at the mu opioid receptor and a full agonist at the kappa opioid receptor. The principal therapeutic action of butorphanol is analgesia. Clinically, dosage is titrated to provide adequate analgesia and may be limited by adverse reactions, including respiratory and CNS depression.
The precise mechanism of the analgesic action is unknown. However, specific CNS opioid receptors for endogenous compounds with opioid-like activity have been identified throughout the brain and spinal cord and are thought to play a role in the analgesic effects of this drug. Pharmacodynamics The analgesic effect of butorphanol is influenced by the route of administration.
Onset of analgesia is within a few minutes for intravenous administration and within 15 minutes for intramuscular injection. Peak analgesic activity occurs within 30 to 60 minutes following intravenous and intramuscular administration. The duration of analgesia varies depending on the pain model as well as the route of administration, but is generally 3 to 4 hours with IM and IV doses as defined by the time 50% of patients required remedication.
In postoperative studies, the duration of analgesia with IV or IM butorphanol was similar to morphine, meperidine and pentazocine when administered in the same fashion at equipotent doses [see Clinical Trials ]. Effects on the Central Nervous System Butorphanol produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation.
In human studies involving individuals without significant respiratory dysfunction, 2 mg of butorphanol IV and 10 mg of morphine sulfate IV depressed respiration to a comparable degree. At higher doses, the magnitude of respiratory depression with butorphanol is not appreciably increased; however, the duration of respiratory depression is longer. Respiratory depression noted after administration of butorphanol to humans by any route is reversed by treatment with naloxone, a specific opioid antagonist [see OVERDOSAGE ].
Butorphanol, like other mixed agonist-antagonists with a high affinity for the kappa receptor, may produce unpleasant psychotomimetic effects in some individuals. Nausea and/or vomiting may be produced by doses of 1 mg or more administered by any route. In human studies of butorphanol [see CLINICAL PHARMACOLOGY; Clinical Trials ], sedation is commonly noted at doses of 0.5 mg or more.
Narcosis is produced by 10 to 12 mg doses of butorphanol administered over 10 to 15 minutes intravenously. Butorphanol causes miosis, even in total darkness. Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings).
Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Butorphanol causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum. Digestion of food in the small intestine is delayed and propulsive contractions are decreased.
Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED). Effects on the Cardiovascular System Hemodynamic changes noted during cardiac catheterization in patients receiving single 0.025 mg/kg intravenous doses of butorphanol have included increases in pulmonary artery pressure, wedge pressure and vascular resistance, increases in left ventricular end diastolic pressure and in systemic…
🧬 Mechanism of Action ▾
Mechanism of Action Butorphanol is a partial opioid agonist at the mu opioid receptor and a full agonist at the kappa opioid receptor. The principal therapeutic action of butorphanol is analgesia. Clinically, dosage is titrated to provide adequate analgesia and may be limited by adverse reactions, including respiratory and CNS depression.
The precise mechanism of the analgesic action is unknown. However, specific CNS opioid receptors for endogenous compounds with opioid-like activity have been identified throughout the brain and spinal cord and are thought to play a role in the analgesic effects of this drug.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Butorphanol Tartrate Injection, USP is supplied as single-dose glass fliptop vials, and available as follows: Unit of Sale Concentration (Total Butorphanol Concentration Per Container) NDC 0409-1623-01 Carton of 10 – 1 mL Single-Dose Glass Fliptop Vials 1 mg/mL NDC 0409-1626-01 Carton of 10 – 1 mL Single-Dose Glass Fliptop Vials 2 mg/mL NDC 0409-1626-02 Carton of 10 – 2 mL Single-Dose Glass Fliptop Vials 4 mg/2 mL (2 mg/mL) Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Protect from light.
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Protect from light.
📋 Description ▾
DESCRIPTION Butorphanol tartrate is a synthetically derived opioid agonist-antagonist analgesic of the phenanthrene series. The chemical name is (-)-17-(cyclobutylmethyl) morphinan-3, 14-diol D-(-)- tartrate (1:1) (salt). The molecular formula is C 21 H 29 NO 2 ∙ C 4 H 6 O 6 , which corresponds to a molecular weight of 477.56 and the following structural formula: Butorphanol tartrate is a white crystalline substance.
The dose is expressed as the tartrate salt. One milligram of the salt is equivalent to 0.68 mg of the free base. The n-octanol/aqueous buffer partition coefficient of butorphanol is 180:1 at pH 7.5.
Butorphanol Tartrate Injection is a sterile, nonpyrogenic parenteral aqueous solution of butorphanol tartrate for intravenous or intramuscular administration. Each milliliter (mL) contains butorphanol tartrate 1 or 2 mg; sodium citrate, dihydrate, 6.4 mg; citric acid hydrous 3.3 mg; sodium chloride 6.4 mg. The pH is 4.5 (3.0 to 5.5).
Chemical Structure
💬 Information for Patients ▾
Information for Patients Addiction, Abuse, and Misuse Inform patients that the use of butorphanol tartrate, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see WARNINGS ]. Instruct patients not to share butorphanol tartrate with others and to take steps to protect butorphanol tartrate from theft or misuse. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when starting butorphanol tartrate or when the dosage is increased, and that it can occur even at recommended dosages [see WARNINGS ].
Advise patients how to recognize respiratory depression and to seek medical attention if breathing difficulties develop. Interactions with Benzodiazepines and Other CNS Depressants Inform patients and caregivers that potentially fatal additive effects may occur if butorphanol tartrate is used with benzodiazepines or other CNS depressants, including alcohol (e.g., non-benzodiazepine sedative/hypnotics, anxiolytics, tranquilizers, muscle relaxants, general anesthetics, antipsychotics, gabapentinoids [gabapentin or pregabalin], and other opioids), and not to use these concomitantly unless supervised by a healthcare provider [see WARNINGS , PRECAUTIONS; Drug Interactions ].
Hyperalgesia and Allodynia Advise patients to seek medical attention if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see WARNINGS ; ADVERSE REACTIONS ]. Serotonin Syndrome Inform patients that butorphanol tartrate could cause a rare but potentially life-threatening condition resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop after discharge from the hospital.
Instruct patients to inform their healthcare providers if they are taking, or plan to take serotonergic medications [see PRECAUTIONS; Drug Interactions ]. Constipation Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention [see ADVERSE REACTIONS ]. Driving or Operating Heavy Machinery Inform patients that Butorphanol Tartrate Injection may impair the mental and/or physical abilities required for the performance of potentially hazardous tasks such as driving a car or operating machinery and to avoid such tasks while taking this product, until they know how they will react to the medication.
Anaphylaxis Inform patients that anaphylaxis has been reported with ingredients contained in Butorphanol Tartrate Injection. Advise patients how to recognize such a reaction and when to seek medical attention [see CONTRAINDICATIONS ; ADVERSE REACTIONS ] . Pregnancy Neonatal Opioid Withdrawal Syndrome Inform female patients of reproductive potential that use of Butorphanol Tartrate Injection for an extended period of time during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life‑threatening if not recognized and treated [see WARNINGS , PRECAUTIONS; Pregnancy ].
Embryo-Fetal Toxicity Inform female patients of reproductive potential that Butorphanol Tartrate Injection can cause fetal harm and to inform the healthcare prescriber of a known or suspected pregnancy [see PRECAUTIONS; Pregnancy ]. Lactation Advise nursing mothers to carefully observe infants for increased sleepiness (more than usual), breathing difficulties, or limpness. Instruct nursing mothers to seek immediate medical care if they notice these signs [see PRECAUTIONS; Nursing Mothers ].
Infertility Inform patients that use of opioids for an extended period of time may cause reduced fertility. It is not known whether these effects on fertility are reversible [see ADVERSE REACTIONS ] .