
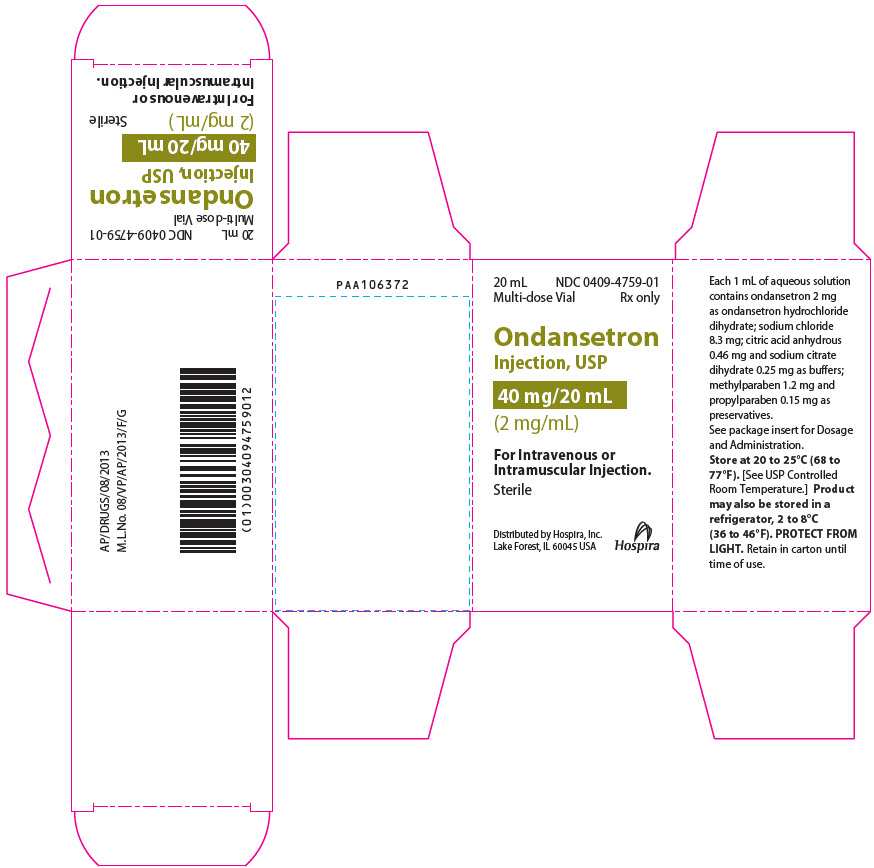
Ondansetron 2 mg/mL Injection, Solution
Other active recalls for Ondansetron (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin-3 Receptor Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Not at all. Ondansetron is approved to prevent nausea and vomiting from cancer chemotherapy, radiation therapy to the abdomen or whole body, and surgery. So you might receive it be...
- What exactly is ondansetron used for — is it just for chemo patients?
- The regular tablet is swallowed like any other pill. The orally disintegrating tablet (ODT) is placed on your tongue and allowed to dissolve — don't chew or swallow it whole. For c...
- How do I take the tablet or the dissolving tablet correctly?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ondansetron — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.46 mg / 1 mL
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
1.2 mg / 1 mL
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
0.15 mg / 1 mL
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
8.3 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
0.25 mg / 1 mL
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.170 | $3.40 / 20 ml |
| Medicaid paysCMS SDUD · 12 mo | $4.14 | $82.82 / 20 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2405 | $0.088 / J2405 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| ondansetron 2 mg/mL 16729-0298-05 | Accord | 20 ml | $0.164 | AP | Availability likely | save 3% |
| Ondansetron 2 mg/mLthis 00409-4759-01 | Hospira, | 1 vial | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 00641-6079-01 | Hikma | 20 ml | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 00641-6286-01 | Hikma | 20 ml | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 23155-0549-31 | Heritage | 1 vial | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 23155-0550-31 | Heritage | 1 vial | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 63323-0374-20 | Fresenius | 1 vial | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 72266-0124-01 | Fosun | 1 vial | $0.170 | AP | Availability likely | — |
| Ondansetron 2 mg/mL 72572-0520-25 | Civica, | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 00641-6080-25 | Hikma | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 72266-0123-25 | Fosun | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 00409-0009-25 | Hospira, | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 00409-4755-03 | Hospira, | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 00641-6078-25 | Hikma | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 60505-6130-05 | Apotex | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 00409-2271-25 | Hospira, | 25 vials | $0.177 | AP | Availability likely | +4% |
| Ondansetron 2 mg/mL 00143-9890-01 | West-Ward | 20 ml | — | — | FDA listed | — |
| Ondansetron 2 mg/mL 51662-1377-01 | HF | 20 ml | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 55150-0126-20 | Eugia | 1 vial | — | — | FDA listed | — |
| Ondansetron 2 mg/mL 68083-0114-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 71872-7107-01 | Medical | 1 vial | — | — | FDA listed | — |
| ondansetron hydrochloride 2 mg/mL 83270-0161-01 | Onesource | 1 vial | — | — | FDA listed | — |
| Ondansetron 2 mg/mL 85766-0199-20 | Sportpharm | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 86211-0115-01 | JVET | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 00143-9891-25 | West-Ward | 25 vials | — | — | FDA listed | — |
| Ondansetron 2 mg/mL 67184-0507-05 | Qilu | 5 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 51662-1366-01 | HF | 2 ml | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 71872-7068-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 71872-7140-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 71872-7162-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 23155-0548-41 | Heritage | 10 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 51662-1469-01 | HF | 2 ml | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 23155-0547-41 | Heritage | 10 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 51662-1245-01 | HF | 2 ml | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 50090-4935-00 | A-S | 25 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 55154-2876-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 68083-0113-01 | Gland | 5 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 84549-0130-05 | ProPharma | 2 ml | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 00404-9930-02 | Henry | 1 vial | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 55154-2877-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 55154-6976-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Ondansetron 2 mg/mL 85766-0234-25 | Sportpharm | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-4759-01 You're viewing this | 1 VIAL, MULTI-DOSE in 1 CARTON (0409-4759-01) / 20 mL in 1 VIAL, MULTI-DOSE | 2006-11-07 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ondansetron Injection is a 5-HT 3 receptor antagonist indicated for the prevention of: • nausea and vomiting associated with initial and repeat courses of emetogenic cancer chemotherapy. ( 1.1 ) • postoperative nausea and/or vomiting. ( 1.2 )
1.1Prevention of Nausea and Vomiting Associated With Initial and Repeat Courses of Emetogenic Cancer Chemotherapy Ondansetron Injection is indicated for the prevention of nausea and vomiting associated with initial and repeat courses of emetogenic cancer chemotherapy, including high-dose cisplatin. Ondansetron is approved for patients aged 6 months and older.
1.2Prevention of Postoperative Nausea and/or Vomiting Ondansetron Injection is indicated for the prevention of postoperative nausea and/or vomiting. As with other antiemetics, routine prophylaxis is not recommended for patients in whom there is little expectation that nausea and/or vomiting will occur postoperatively. In patients in whom nausea and/or vomiting must be avoided postoperatively, Ondansetron Injection is recommended even when the incidence of postoperative nausea and/or vomiting is low.
For patients who do not receive prophylactic Ondansetron Injection and experience nausea and/or vomiting postoperatively, Ondansetron Injection may be given to prevent further episodes. Ondansetron is approved for patients aged 1 month and older.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prevention of Nausea and Vomiting Associated With Initial and Repeat Courses of Emetogenic Cancer Chemotherapy ( 2.1 ): • Dilution of Ondansetron Injection in 50 mL of 5% Dextrose Injection or 0.9% Sodium Chloride Injection is required before administration to adult and pediatric patients. • Adults and pediatric patients 6 months of age and older: The recommended dosage is 0.15 mg/kg per dose for 3 doses (maximum of 16 mg per dose), infused intravenously over 15 minutes. • Administer the first dose 30 minutes before the start of chemotherapy and subsequent doses 4 and 8 hours after the first dose.
Prevention of Postoperative Nausea and/or Vomiting ( 2.2 ): • Dilution of Ondansetron Injection is not required before administration to adult and pediatric patients. • See full prescribing information for the recommended dosage and administration instructions for adult and pediatric patients 1 month of age and older. Patients With Severe Hepatic Impairment ( 2.3 ): • Do not exceed a total daily dose of 8 mg.
2.1Prevention of Nausea and Vomiting Associated With Initial and Repeat Courses of Emetogenic Chemotherapy Important Preparation Instructions • Dilution of Ondansetron Injection in 50 mL of 5% Dextrose Injection or 0.9% Sodium Chloride Injection is required before administration to adult and pediatric patients for the prevention of nausea and vomiting associated with emetogenic chemotherapy. For pediatric patients between 6 months and 1 year of age and/or 10 kg or less: Depending on the fluid needs of the patient, Ondansetron Injection may be diluted in 10 to 50 mL of 5% Dextrose Injection or 0.9% Sodium Chloride Injection. • Occasionally, ondansetron precipitates at the stopper/vial interface in vials stored upright.
Potency and safety are not affected. If a precipitate is observed, resolubilize by shaking the vial vigorously. • Do not mix Ondansetron Injection with solutions for which physical and chemical compatibility has not been established. In particular, this applies to alkaline solutions as a precipitate may form. • Inspect the diluted Ondansetron Injection solution for particulate matter and discoloration before administration; discard if present. • Storage : After dilution, do not use beyond 24 hours.
Although Ondansetron Injection is chemically and physically stable when diluted as recommended, sterile precautions should be observed because diluents generally do not contain preservative. • Compatibility : Ondansetron Injection is compatible and stable at room temperature under normal lighting conditions for 48 hours after dilution with the following intravenous fluids: 0.9% Sodium Chloride Injection, 5% Dextrose Injection, 5% Dextrose and 0.9% Sodium Chloride Injection, 5% Dextrose and 0.45% Sodium Chloride Injection, and 3% Sodium Chloride Injection.
Dosage and Administration The recommended dosage for adult and pediatric patients 6 months of age and older for prevention of nausea and vomiting associated with emetogenic chemotherapy is 0.15 mg/kg per dose for 3 doses (maximum of 16 mg per dose). Caution : Dilution of Ondansetron Injection is required in adult and pediatric patients prior to administration. Infuse intravenously over 15 minutes beginning 30 minutes before the start of emetogenic chemotherapy and then repeat 4 and 8 hours after the first dose.
2.2Prevention of Postoperative Nausea and/or Vomiting Important Preparation Instructions • Dilution of Ondansetron Injection is not required before administration to adult and pediatric patients. • Inspect Ondansetron Injection visually for particulate matter and discoloration before administration; discard if present. Dosage and Administration The recommended dose and administration instructions for adult and pediatric patients 1 month of age and older for prevention of postoperative nausea and vomiting are shown in Table 1.
Table 1. Recommended Dose and Administration of Ondansetron Injection for Prevention of Postoperative Nausea…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ondansetron Injection USP: 2 mg/mL clear, colorless, nonpyrogenic, sterile solution in a 2 mL single-dose vial and 20 mL multiple-dose vial. Ondansetron Injection (2 mg/mL): 2 mL single-dose vial and 20 mL multiple-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Ondansetron Injection is contraindicated for patients known to have hypersensitivity (e.g., anaphylaxis) to this product or any of its components. Anaphylactic reactions have been reported in patients taking ondansetron [see Adverse Reactions (6.2) ] . The concomitant use of apomorphine with ondansetron is contraindicated based on reports of profound hypotension and loss of consciousness when apomorphine was administered with ondansetron. • Patients known to have hypersensitivity (e.g., anaphylaxis) to this product or any of its components.
( 4 ) • Concomitant use of apomorphine. ( 4 , 7.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hypersensitivity Reactions : Hypersensitivity reactions, including anaphylaxis and bronchospasm have been reported in patients who have exhibited hypersensitivity to other selective 5-HT 3 receptor antagonists. ( 5.1 ) • QT Prolongation and Torsade de Pointes : QT prolongation occurs in a dose-dependent manner. Cases of Torsade de Pointes have been reported.
Avoid ondansetron in patients with congenital long QT syndrome. ( 5.2 ) • Serotonin Syndrome : Serotonin syndrome has been reported with 5-HT 3 receptor agonists alone but particularly with concomitant use of serotonergic drugs. ( 5.3 ) • Myocardial Ischemia : Do not exceed the recommended infusion rate and monitor patients during and after administration.
( 2.1 , 2.2 , 5.4 ) • Masking of Progressive Ileus and/or Gastric Distension Following Abdominal Surgery or Chemotherapy-Induced Nausea and Vomiting: Monitor for decreased bowel activity, particularly in patients with risk factors for gastrointestinal obstruction. ( 5.5 )
5.1Hypersensitivity Reactions Hypersensitivity reactions, including anaphylaxis and bronchospasm, have been reported in patients who have exhibited hypersensitivity to other selective 5-HT 3 receptor antagonists.
5.2QT Prolongation Ondansetron prolongs the QT interval in a dose-dependent manner [see Clinical Pharmacology (12.2) ] . In addition, postmarketing cases of Torsade de Pointes have been reported in patients using ondansetron. Avoid ondansetron in patients with congenital long QT syndrome.
Electrocardiogram (ECG) monitoring is recommended in patients with electrolyte abnormalities (e.g., hypokalemia or hypomagnesemia), congestive heart failure, bradyarrhythmias, or patients taking other medicinal products that lead to QT prolongation.
5.3Serotonin Syndrome The development of serotonin syndrome has been reported with 5-HT 3 receptor antagonists. Most reports have been associated with concomitant use of serotonergic drugs (e.g., selective serotonin reuptake inhibitors (SSRIs), serotonin and norepinephrine reuptake inhibitors (SNRIs), monoamine oxidase inhibitors, mirtazapine, fentanyl, lithium, tramadol, and intravenous methylene blue). Some of the reported cases were fatal.
Serotonin syndrome occurring with overdose of ondansetron alone has also been reported. The majority of reports of serotonin syndrome related to 5-HT 3 receptor antagonist use occurred in a post-anesthesia care unit or an infusion center. Symptoms associated with serotonin syndrome may include the following combination of signs and symptoms: mental status changes (e.g., agitation, hallucinations, delirium, and coma), autonomic instability (e.g., tachycardia, labile blood pressure, dizziness, diaphoresis, flushing, hyperthermia), neuromuscular symptoms (e.g., tremor, rigidity, myoclonus, hyperreflexia, incoordination), seizures, with or without gastrointestinal symptoms (e.g., nausea, vomiting, diarrhea).
Patients should be monitored for the emergence of serotonin syndrome, especially with concomitant use of ondansetron and other serotonergic drugs. If symptoms of serotonin syndrome occur, discontinue ondansetron and initiate supportive treatment. Patients should be informed of the increased risk of serotonin syndrome, especially if ondansetron is used concomitantly with other serotonergic drugs [see Drug Interactions (7.5) , Overdosage (10) ] .
5.4Myocardial Ischemia Myocardial ischemia has been reported in patients treated with ondansetron. In some cases, predominantly during intravenous administration, the symptoms appeared immediately after administration but resolved with prompt treatment. Coronary artery spasm appears to be the most common underlying cause.
Therefore, do not exceed the recommended infusion rate of ondansetron and monitor patients for signs and symptoms of myocardial ischemia during and after administration [see Dosage and Administration (2.1 , 2.2) and Adverse Reactions (6.2) ] .
5.5 Masking of Progressive Ileus and Gastri…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Hypersensitivity Reactions [see Warnings and Precautions (5.1) ] • QT Prolongation [see Warnings and Precautions (5.2) ] • Serotonin Syndrome [see Warnings and Precautions (5.3) ] • Myocardial Ischemia [see Warnings and Precautions (5.4) ] • Masking of Progressive Ileus and Gastric Distension [see Warnings and Precautions (5.5) ] Chemotherapy-Induced Nausea and Vomiting: • The most common adverse reactions (≥ 7%) in adults are diarrhea, headache, and fever.
( 6.1 ) Postoperative Nausea and/or Vomiting: • The most common adverse reaction (≥ 10%) which occurs at a higher frequency compared with placebo in adults is headache. ( 6.1 ) • The most common adverse reaction (≥ 2%) which occurs at a higher frequency compared with placebo in pediatric patients aged 1 to 24 months is diarrhea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The following adverse reactions have been reported in clinical trials of adult patients treated with ondansetron, the active ingredient of intravenous ondansetron across a range of dosages. A causal relationship to therapy with ondansetron was unclear in many cases.
Chemotherapy-Induced Nausea and Vomiting Table 2. Adverse Reactions Reported in > 5% of Adult Patients Who Received Ondansetron at a Dosage of Three 0.15 mg/kg Doses Number of Adult Patients With Reaction Adverse Reaction Ondansetron Injection 0.15 mg/kg × 3 (n = 419) Metoclopramide (n = 156) Placebo (n = 34) Diarrhea 16% 44% 18% Headache 17% 7% 15% Fever 8% 5% 3% Cardiovascular : Rare cases of angina (chest pain), electrocardiographic alterations, hypotension, and tachycardia have been reported. Gastrointestinal : Constipation has been reported in 11% of chemotherapy patients receiving multiday ondansetron.
Hepatic : In comparative trials in cisplatin chemotherapy patients with normal baseline values of aspartate transaminase (AST) and alanine transaminase (ALT), these enzymes have been reported to exceed twice the upper limit of normal in approximately 5% of patients. The increases were transient and did not appear to be related to dose or duration of therapy. On repeat exposure, similar transient elevations in transaminase values occurred in some courses, but symptomatic hepatic disease did not occur.
Integumentary : Rash has occurred in approximately 1% of patients receiving ondansetron. Neurological : There have been rare reports consistent with, but not diagnostic of, extrapyramidal reactions in patients receiving Ondansetron Injection, and rare cases of grand mal seizure. Other : Rare cases of hypokalemia have been reported.
Postoperative Nausea and/or Vomiting The adverse reactions in Table 3 have been reported in ≥ 2% of adults receiving ondansetron at a dosage of 4 mg intravenous over 2 to 5 minutes in clinical trials. Table 3. Adverse Reactions Reported in ≥ 2% (and with greater frequency than the placebo group) of Adult Patients Receiving Ondansetron at a Dosage of 4 mg Intravenous Over 2 to 5 Minutes Adverse Reaction Adverse reactions: Rates of these reactions were not significantly different in the ondansetron and placebo groups. , Patients were receiving multiple concomitant perioperative and postoperative medications.
Ondansetron Injection 4 mg Intravenous (n = 547) Placebo (n = 547) Headache 92 (17%) 77 (14%) Drowsiness/Sedation 44 (8%) 37 (7%) Injection-site reaction 21 (4%) 18 (3%) Fever 10 (2%) 6 (1%) Cold sensation 9 (2%) 8 (1%) Pruritus 9 (2%) 3 (< 1%) Paresthesia 9 (2%) 2 (< 1%) Pediatric Use : Rates of adverse reac…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Drugs Affecting Cytochrome P-450 Enzymes Ondansetron does not appear to induce or inhibit the cytochrome P-450 drug-metabolizing enzyme system of the liver. Because ondansetron is metabolized by hepatic cytochrome P-450 drug-metabolizing enzymes (CYP3A4, CYP2D6, CYP1A2), inducers or inhibitors of these enzymes may change the clearance and, hence, the half-life of ondansetron [see Clinical Pharmacology (12.3) ] . On the basis of limited available data, no dosage adjustment is recommended for patients on these drugs.
7.2Apomorphine Based on reports of profound hypotension and loss of consciousness when apomorphine was administered with ondansetron, the concomitant use of apomorphine with ondansetron is contraindicated [see Contraindications (4) ] .
7.3Phenytoin, Carbamazepine, and Rifampin In patients treated with potent inducers of CYP3A4 (i.e., phenytoin, carbamazepine, and rifampin), the clearance of ondansetron was significantly increased and ondansetron blood concentrations were decreased. However, on the basis of available data, no dosage adjustment for ondansetron is recommended for patients on these drugs [see Clinical Pharmacology (12.3) ] .
7.4Tramadol Although there are no data on pharmacokinetic drug interactions between ondansetron and tramadol, data from two small trials indicate that concomitant use of ondansetron may result in reduced analgesic activity of tramadol. Patients on concomitant ondansetron self-administered tramadol more frequently in these trials, leading to an increased cumulative dose in patient-controlled administration of tramadol.
7.5Serotonergic Drugs Serotonin syndrome (including altered mental status, autonomic instability, and neuromuscular symptoms) has been described following the concomitant use of 5-HT 3 receptor antagonists and other serotonergic drugs, including SSRIs and SNRIs [see Warnings and Precautions (5.3) ] .
7.6Chemotherapy In humans, carmustine, etoposide, and cisplatin do not affect the pharmacokinetics of ondansetron. In a crossover trial in 76 pediatric patients, intravenous ondansetron did not increase blood levels of high-dose methotrexate.
7.7Temazepam The coadministration of ondansetron had no effect on the pharmacokinetics and pharmacodynamics of temazepam.
7.8Alfentanil and Atracurium Ondansetron does not alter the respiratory depressant effects produced by alfentanil or the degree of neuromuscular blockade produced by atracurium. Interactions with general or local anesthetics have not been studied.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Published epidemiological studies on the association between ondansetron use and major birth defects have reported inconsistent findings and have important methodological limitations that preclude conclusions about the safety of ondansetron use in pregnancy (see Data ) . Available postmarketing data have not identified a drug-associated risk of miscarriage or adverse maternal outcomes. Reproductive studies in rats and rabbits did not show evidence of harm to the fetus when ondansetron was administered intravenously during organogenesis at approximately 3.6 and 2.9 times the maximum recommended human intravenous dose of 0.15 mg/kg given three times a day, based on body surface area (BSA), respectively (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, miscarriages, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Human Data Available data on ondansetron use in pregnant women from several published epidemiological studies preclude an assessment of a drug-associated risk of adverse fetal outcomes due to important methodological limitations, including the uncertainty of whether women who filled a prescription actually took the medication, the concomitant use of other medications or treatments, recall bias, and other unadjusted confounders. Ondansetron exposure in utero has not been associated with overall major congenital malformations in aggregate analyses.
One large retrospective cohort study examined 1970 women who received a prescription for ondansetron during pregnancy and reported no association between ondansetron exposure and major congenital malformations, miscarriage, stillbirth, preterm delivery, infants of low birth weight, or infants small for gestational age. Two large retrospective cohort studies and one case-control study have assessed ondansetron exposure in the first trimester and risk of cardiovascular defects with inconsistent findings. Relative risks (RR) ranged from 0.97 (95% CI 0.86 to 1.10) to 1.62 (95% CI 1.04, 2.54).
A subset analysis in one of the cohort studies observed that ondansetron was specifically associated with cardiac septal defects (RR 2.05, 95% CI 1.19, 3.28); however this association was not confirmed in other studies. Several studies have assessed ondansetron and the risk of oral clefts with inconsistent findings. A retrospective cohort study of 1.8 million pregnancies in the US Medicaid Database showed an increased risk of oral clefts among 88,467 pregnancies in which oral ondansetron was prescribed in the first trimester (RR 1.24, 95% CI 1.03, 1.48), but no such association was reported with intravenous ondansetron in 23,866 pregnancies (RR 0.95, 95% CI 0.63, 1.43).
In the subgroup of women who received both forms of administration, the RR was 1.07 (95% CI 0.59, 1.93). Two case-control studies, using data from birth defects surveillance programs, reported conflicting associations between maternal use of ondansetron and isolated cleft palate (OR 1.6 [95% CI 1.1, 2.3] and 0.5 [95% CI 0.3, 1.0]). It is unknown whether ondansetron exposure in utero in the cases of cleft palate occurred during the time of palate formation (the palate is formed between the 6th and 9th weeks of pregnancy).
Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received intravenous doses of ondansetron up to 10 mg/kg/day and 4 mg/kg/day, respectively, during the period of organogenesis. With the exception of short periods of maternal weight loss and a slight increase in the incidence of early uterine deaths at the high dose level in rabbits, there were no significant effects of ondansetron on the maternal animals or the development of the offspring. A…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published epidemiological studies on the association between ondansetron use and major birth defects have reported inconsistent findings and have important methodological limitations that preclude conclusions about the safety of ondansetron use in pregnancy (see Data ) . Available postmarketing data have not identified a drug-associated risk of miscarriage or adverse maternal outcomes. Reproductive studies in rats and rabbits did not show evidence of harm to the fetus when ondansetron was administered intravenously during organogenesis at approximately 3.6 and 2.9 times the maximum recommended human intravenous dose of 0.15 mg/kg given three times a day, based on body surface area (BSA), respectively (see Data ) .
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, miscarriages, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Human Data Available data on ondansetron use in pregnant women from several published epidemiological studies preclude an assessment of a drug-associated risk of adverse fetal outcomes due to important methodological limitations, including the uncertainty of whether women who filled a prescription actually took the medication, the concomitant use of other medications or treatments, recall bias, and other unadjusted confounders. Ondansetron exposure in utero has not been associated with overall major congenital malformations in aggregate analyses.
One large retrospective cohort study examined 1970 women who received a prescription for ondansetron during pregnancy and reported no association between ondansetron exposure and major congenital malformations, miscarriage, stillbirth, preterm delivery, infants of low birth weight, or infants small for gestational age. Two large retrospective cohort studies and one case-control study have assessed ondansetron exposure in the first trimester and risk of cardiovascular defects with inconsistent findings. Relative risks (RR) ranged from 0.97 (95% CI 0.86 to 1.10) to 1.62 (95% CI 1.04, 2.54).
A subset analysis in one of the cohort studies observed that ondansetron was specifically associated with cardiac septal defects (RR 2.05, 95% CI 1.19, 3.28); however this association was not confirmed in other studies. Several studies have assessed ondansetron and the risk of oral clefts with inconsistent findings. A retrospective cohort study of 1.8 million pregnancies in the US Medicaid Database showed an increased risk of oral clefts among 88,467 pregnancies in which oral ondansetron was prescribed in the first trimester (RR 1.24, 95% CI 1.03, 1.48), but no such association was reported with intravenous ondansetron in 23,866 pregnancies (RR 0.95, 95% CI 0.63, 1.43).
In the subgroup of women who received both forms of administration, the RR was 1.07 (95% CI 0.59, 1.93). Two case-control studies, using data from birth defects surveillance programs, reported conflicting associations between maternal use of ondansetron and isolated cleft palate (OR 1.6 [95% CI 1.1, 2.3] and 0.5 [95% CI 0.3, 1.0]). It is unknown whether ondansetron exposure in utero in the cases of cleft palate occurred during the time of palate formation (the palate is formed between the 6th and 9th weeks of pregnancy).
Animal Data In embryo-fetal development studies in rats and rabbits, pregnant animals received intravenous doses of ondansetron up to 10 mg/kg/day and 4 mg/kg/day, respectively, during the period of organogenesis. With the exception of short periods of maternal weight loss and a slight increase in the incidence of early uterine deaths at the high dose level in rabbits, there were no significant effects of ondansetron on the maternal animals or the development of the offspring. At doses of 10 mg/kg/day in rat…
🧒 Pediatric Use ▾
8.4Pediatric Use Little information is available about the use of ondansetron in pediatric surgical patients younger than 1 month [see Clinical Studies (14.2) ] . Little information is available about the use of ondansetron in pediatric cancer patients younger than 6 months [see Clinical Studies (14.1) , Dosage and Administration (2) ] . The clearance of ondansetron in pediatric patients aged 1 month to 4 months is slower and the half-life is ~2.5-fold longer than patients who are aged > 4 to 24 months.
As a precaution, it is recommended that patients younger than 4 months receiving this drug be closely monitored [see Clinical Pharmacology (12.3) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects enrolled in cancer chemotherapy-induced and postoperative nausea and vomiting US- and foreign-controlled clinical trials, 862 were aged 65 years and older. No overall differences in safety or effectiveness were observed between subjects 65 years and older and younger subjects. A reduction in clearance and increase in elimination half-life were seen in patients older than 75 years compared with younger subjects [see Clinical Pharmacology (12.3) ] .
There were an insufficient number of patients older than 75 years of age and older in the clinical trials to permit safety or efficacy conclusions in this age-group. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Dosage adjustment is not needed in patients over the age of 65.
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific antidote for ondansetron overdose. Patients should be managed with appropriate supportive therapy. Individual intravenous doses as large as 150 mg and total daily intravenous doses as large as 252 mg have been inadvertently administered without significant adverse events.
These doses are more than 10 times the recommended daily dose. In addition to the adverse reactions listed above, the following events have been described in the setting of ondansetron overdose: "Sudden blindness" (amaurosis) of 2 to 3 minutes' duration plus severe constipation occurred in one patient that was administered 72 mg of ondansetron intravenously as a single-dose. Hypotension (and faintness) occurred in another patient that took 48 mg of ondansetron hydrochloride tablets.
Following infusion of 32 mg over only a 4-minute period, a vasovagal episode with transient second-degree heart block was observed. In all instances, the events resolved completely. Pediatric cases consistent with serotonin syndrome have been reported after inadvertent oral overdoses of ondansetron (exceeding estimated ingestion of 5 mg/kg) in young children.
Reported symptoms included somnolence, agitation, tachycardia, tachypnea, hypertension, flushing, mydriasis, diaphoresis, myoclonic movements, horizontal nystagmus, hyperreflexia, and seizure. Patients required supportive care, including intubation in some cases, with complete recovery without sequelae within 1 to 2 days.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ondansetron is a selective 5-HT 3 receptor antagonist. While ondansetron's mechanism of action has not been fully characterized, it is not a dopamine-receptor antagonist.
12.2Pharmacodynamics In normal volunteers, single intravenous doses of 0.15 mg/kg of ondansetron had no effect on esophageal motility, gastric motility, lower esophageal sphincter pressure, or small intestinal transit time. In another trial in 6 normal male volunteers, a 16 mg dose infused over 5 minutes showed no effect of the drug on cardiac output, heart rate, stroke volume, blood pressure, or ECG. Multiday administration of ondansetron has been shown to slow colonic transit in normal volunteers.
Ondansetron has no effect on plasma prolactin concentrations. In a gender balanced pharmacodynamic trial (n = 56), ondansetron 4 mg administered intravenously or intramuscularly was dynamically similar in the prevention of nausea and vomiting using the ipecacuanha model of emesis. Cardiac Electrophysiology QTc interval prolongation was studied in a double-blind, single intravenous dose, placebo- and positive-controlled, crossover trial in 58 healthy subjects.
The maximum mean (95% upper confidence bound) difference in QTcF from placebo after baseline correction was 19.5 (21.8) ms and 5.6 (7.4) ms after 15-minute intravenous infusions of 32 mg and 8 mg Ondansetron Injection, respectively. A significant exposure-response relationship was identified between ondansetron concentration and ΔΔQTcF. Using the established exposure-response relationship, 24 mg infused intravenously over 15 minutes had a mean predicted (95% upper prediction interval) ΔΔQTcF of 14.0 (16.3) ms.
In contrast, 16 mg infused intravenously over 15 minutes using the same model had a mean predicted (95% upper prediction interval) ΔΔQTcF of 9.1 (11.2) ms. In this study, the 8 mg dose infused over 15 minutes did not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics In normal adult volunteers, the following mean pharmacokinetic data have been determined following a single 0.15 mg/kg intravenous dose. Table 4. Pharmacokinetics in Normal Adult Volunteers Age-group (years) n Peak Plasma Concentration (ng/mL) Mean Elimination Half-life (h) Plasma Clearance (L/h/kg) 19–40 11 102 3.5 0.381 61–74 12 106 4.7 0.319 ≥ 75 11 170 5.5 0.262 Absorption A trial was performed in normal volunteers (n = 56) to evaluate the pharmacokinetics of a single 4 mg dose administered as a 5-minute infusion compared with a single intramuscular injection.
Systemic exposure as measured by mean area under curve (AUC) were equivalent, with values of 156 [95% CI 136, 180] and 161 [95% CI 137, 190] ng∙h/mL for intravenous and intramuscular groups, respectively. Mean peak plasma concentrations were 42.9 [95% CI 33.8, 54.4] ng/mL at 10 minutes after intravenous infusion and 31.9 [95% CI 26.3, 38.6] ng/mL at 41 minutes after intramuscular injection. Distribution Plasma protein binding of ondansetron as measured in vitro was 70% to 76%, over the pharmacologic concentration range of 10 to 500 ng/mL.
Circulating drug also distributes into erythrocytes. Elimination Metabolism : Ondansetron is extensively metabolized in humans, with approximately 5% of a radiolabeled dose recovered as the parent compound from the urine. The primary metabolic pathway is hydroxylation on the indole ring followed by subsequent glucuronide or sulfate conjugation.
Although some nonconjugated metabolites have pharmacologic activity, these are not found in plasma at concentrations likely to significantly contribute to the biological activity of ondansetron. The metabolites are observed in the urine. In vitro metabolism studies have shown that ondansetron is a substrate for multiple human hepatic cytochrome P-450 enzymes, including CYP1A2, CYP2D6, and CYP3A4.
In terms of overall ondansetron turnover, CYP3A4 plays a predominant role while formation of the major in vivo metabolites is appare…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ondansetron is a selective 5-HT 3 receptor antagonist. While ondansetron's mechanism of action has not been fully characterized, it is not a dopamine-receptor antagonist.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ondansetron Injection, USP, 2 mg/mL, is supplied as follows: Unit of Sale Concentration NDC 0409-4755-03 Tray of 25 2 mL Single-dose Vials 4 mg/2 mL (2 mg/mL) NDC 0409-4759-01 Carton of 1 20 mL Multiple-dose Vials 40 mg/20 mL (2 mg/mL) Storage: Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Product may also be stored in a refrigerator, 2°C to 8°C (36°F to 46°F). Retain in carton until time of use. Protect from light.
📦 Storage and Handling ▾
Storage: Store at 20°C to 25°C (68°F to 77°F). [See USP Controlled Room Temperature.] Product may also be stored in a refrigerator, 2°C to 8°C (36°F to 46°F). Retain in carton until time of use. Protect from light.
📋 Description ▾
11 DESCRIPTION The active ingredient of Ondansetron Injection, USP is ondansetron hydrochloride, a selective blocking agent of the serotonin 5-HT 3 receptor type. Its chemical name is (±) 1, 2, 3, 9‑ tetrahydro-9-methyl-3-[(2-methyl-1H-imidazol-1-yl)methyl]-4H-carbazol-4-one, monohydrochloride, dihydrate. It has the following structural formula: The empirical formula is C 18 H 19 N 3 O∙HCl∙2H 2 O, representing a molecular weight of 365.9 g/mol.
Ondansetron HCl is a white to off-white powder that is soluble in water and normal saline. Each 1 mL of aqueous solution in the 2-mL single-dose vial contains 2 mg of ondansetron as the hydrochloride dihydrate; 9 mg of sodium chloride, USP; and 0.46 mg of citric acid anhydrous, USP and 0.25 mg of sodium citrate dihydrate, USP as buffers in Water for Injection, USP. Each 1 mL of aqueous solution in the 20-mL multiple-dose vial contains 2 mg of ondansetron as the hydrochloride dihydrate; 8.3 mg of sodium chloride, USP; 0.46 mg of citric acid anhydrous, USP and 0.25 mg of sodium citrate dihydrate, USP as buffers; and 1.2 mg of methylparaben, NF and 0.15 mg of propylparaben, NF as preservatives in Water for Injection, USP.
Ondansetron Injection, USP is a clear, colorless, nonpyrogenic, sterile solution for intravenous or intramuscular use. The pH of the injection solution is 3.3 to 4.0. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Inform patients that Ondansetron Injection may cause hypersensitivity reactions, some as severe as anaphylaxis and bronchospasm. The patient should report any signs and symptoms of hypersensitivity reactions, including fever, chills, rash, or breathing problems [see Warnings and Precautions (5.1) ] QT Prolongation Patients should be informed that Ondansetron Injection may cause serious cardiac arrhythmias, such as QT prolongation. Patients should be instructed to tell their healthcare provider right away if they perceive a change in their heart rate, if they feel lightheaded, or if they have a syncopal episode.
Patients should be informed that the chances of developing severe cardiac arrhythmias, such as QT prolongation and Torsade de Pointes are higher in the following people: • Patients with a personal or family history of abnormal heart rhythms, such as congenital long QT syndrome; • Patients who take medications, such as diuretics, which may cause electrolyte abnormalities; • Patients with hypokalemia or hypomagnesemia. Ondansetron Injection should be avoided in these patients, since they may be more at risk for cardiac arrhythmias, such as QT prolongation and Torsade de Pointes [see Warnings and Precautions (5.2) ] .
Drug Interactions • Instruct the patient to report the use of all medications, especially apomorphine, to their healthcare provider. Concomitant use of apomorphine and Ondansetron Injection may cause a significant drop in blood pressure and loss of consciousness. • Advise patients of the possibility of serotonin syndrome with concomitant use of Ondansetron Injection and another serotonergic agent, such as medications to treat depression and migraines. Advise patients to seek immediate medical attention if the following symptoms occur: changes in mental status, autonomic instability, neuromuscular symptoms with or without gastrointestinal symptoms [see Warnings and Precautions (5.3) ] .
Myocardial Ischemia Inform patients that Ondansetron Injection may cause myocardial ischemia during or after the administration. Advise patients to seek immediate medical help if any symptoms suggestive of a myocardial ischemia occur, such as sudden chest pain or chest tightness [see Warnings and Precautions (5.4) ] . Masking of Progressive Ileus and Gastric Distension Inform patients following abdominal surgery or those with chemotherapy-induced nausea and vomiting that Ondansetron Injection may mask signs and symptoms of bowel obstruction.
Instruct patients to immediately report any signs or symptoms consistent with a potential bowel obstruction to their healthcare provider [see Warnings and Precautions (5.5) ] .