
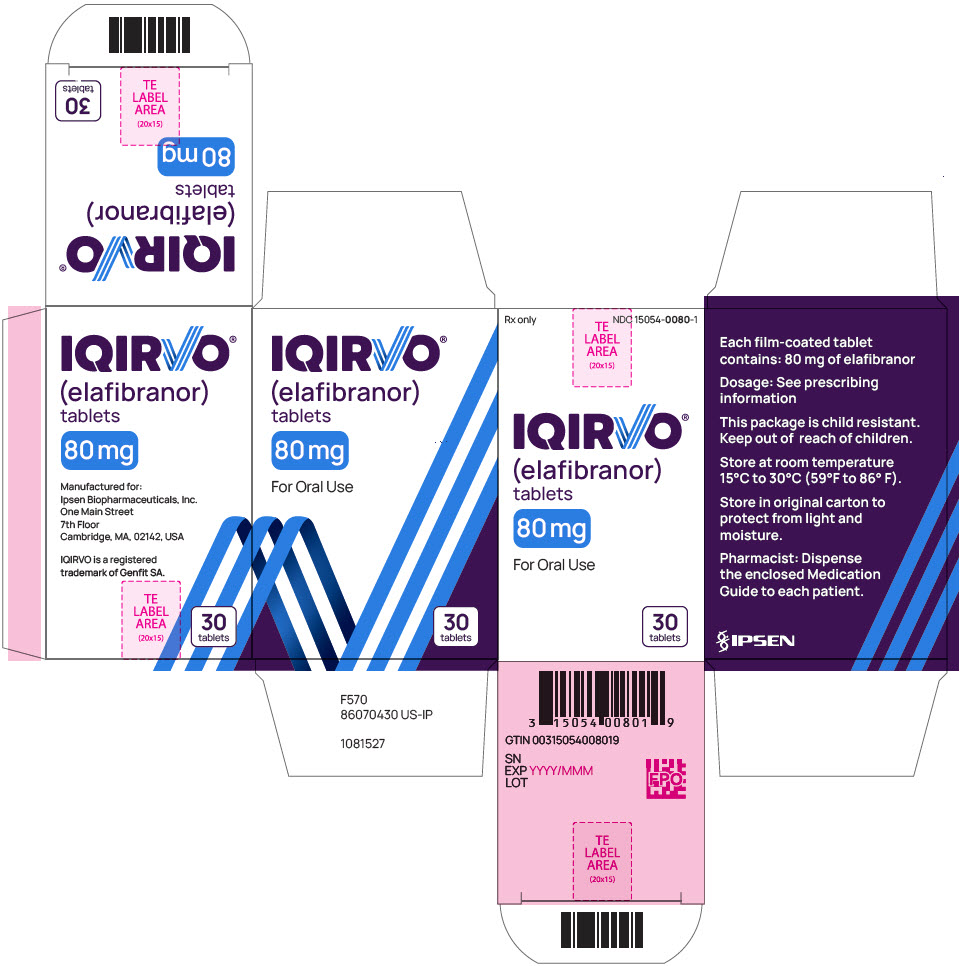
Iqirvo elafibranor 80 mg Tablet, Film Coated, 30-count — NDC 15054-0080-1 (Billing 15054-0080-01)
This is a package of 30 tablets of Iqirvo elafibranor 80 mg Tablet, Film Coated from Ipsen Biopharmaceuticals, Inc., marketed since Jun 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 15054-0080-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 15054 labeler · 0080 product · 1 package
- Package marketed since
- Jun 10, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 1505400801 9
- Medicaid fills, this package
- 533 prescriptions in the last four reported quarters
- FDA record last changed
- Aug 27, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 086187
- GCN: 55863
- HICL (First Databank): 049672
- AHFS class code: 56:14.00.00
- RxCUI (RxNorm): 2684946
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Peroxisome Proliferator-activated Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Elafibranor is used alone or in combination with ursodiol to treat primary biliary cholangitis (PBC; a type of liver disease that destroys bile ducts, which allows bile to stay in the liver and cause damage) in people who cannot take ursodiol or in people who were not treated successfully with ursodiol alone. Elafibranor is in a class of medications called peroxisome proliferator-activated receptor (PPAR) agonists. It works by decreasing the production of bile acids and increasing movement of bile acids out of the liver, resulting in decreased toxic levels of bile acids that accumulate in the...
Read the full MedlinePlus article ↗- Primary biliary cholangitis (PBC) is a chronic liver disease where your immune system gradually damages the small bile ducts inside your liver. Over time, bile builds up and can ca...
- What exactly is primary biliary cholangitis, and why do I need this medication?
- You take one Iqirvo tablet by mouth once a day, and you can take it with or without food — both are fine. If you eat a high-fat meal it may slow down how quickly the drug is absorb...
- How should I take Iqirvo, and does it matter if I take it with food?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $386.63 | $11,598.92 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $384.04 | $11,521.28 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 15054-0080-01 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 30 TABLET, FILM COATED in 1 BOTTLE | 2024-06-10 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Iqirvo 80 mgthis 15054-0080-01 | Ipsen | 30 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11857523 ↗ | Method of use | U-3955 | Mar 30, 2037 |
| US 11850223 ↗ | Method of use | U-1854 | Mar 30, 2037 |
| US 11331292 ↗ | Method of use | U-1854 | Mar 30, 2037 |
| US 11185519 ↗ | Method of use | U-3955 | Mar 30, 2037 |
| US 12310935 ↗ | Method of use | U-1854 | Mar 30, 2037 |
| US 12295928 ↗ | Method of use | U-1854 | Mar 30, 2037 |
| US 12295927 ↗ | Method of use | U-1854 | Mar 30, 2037 |
| US 12233038 ↗ | Method of use | U-1854 | Mar 30, 2037 |
| US 12673035 ↗ | Method of use | U-1854 | Mar 5, 2044 |
| US 12589086 ↗ | Method of use | U-4473 | Mar 30, 2037 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Jun 10, 2029 |
| ODE-486 | Orphan Drug Exclusivity (7-year) | Jun 10, 2031 |
Is there a generic version of IQIRVO 80 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Ipsen Biopharmaceuticals, Inc. labeler code 15054
- Sohonos palovarotene 1 mg Capsule NDC 15054-0010-1
- Sohonos palovarotene 1.5 mg Capsule NDC 15054-0015-1
- Sohonos palovarotene 2.5 mg Capsule NDC 15054-0025-1
- Onivyde IRINOTECAN HYDROCHLORIDE 4.3 mg/mL Injection, Powder, For Solution NDC 15054-0043-1
- Sohonos palovarotene 5 mg Capsule NDC 15054-0050-1
- Sohonos palovarotene 10 mg Capsule NDC 15054-0100-1
- Dysport Botulinum Toxin Type A 500 U Injection, Powder, Lyophilized, For Solution NDC 15054-0500-1
- Dysport Botulinum Toxin Type A 300 U Injection, Powder, Lyophilized, For Solution NDC 15054-0530-6
- Increlex mecasermin 40 mg/4mL Injection, Solution NDC 15054-1040-5
- SOMATULINE DEPOT lanreotide acetate 60 mg/.2mL Injection NDC 15054-1060-4
- SOMATULINE DEPOT lanreotide acetate 90 mg/.3mL Injection NDC 15054-1090-4
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE IQIRVO is indicated for the treatment of primary biliary cholangitis (PBC) in combination with ursodeoxycholic acid (UDCA) in adults who have had an inadequate response to UDCA, or as monotherapy in patients unable to tolerate UDCA. This indication is approved under accelerated approval based on reduction of alkaline phosphatase (ALP) [see Clinical Studies (14) ] . Improvement in survival or prevention of liver decompensation events have not been demonstrated.
Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trial(s). IQIRVO is a peroxisome proliferator-activated receptor (PPAR) agonist indicated for the treatment of primary biliary cholangitis (PBC) in combination with ursodeoxycholic acid (UDCA) in adults who have an inadequate response to UDCA, or as monotherapy in patients unable to tolerate UDCA. This indication is approved under accelerated approval based on reduction of alkaline phosphatase (ALP).
Improvement in survival or prevention of liver decompensation events have not been demonstrated. Continued approval for this indication may be contingent upon verification and description of clinical benefit in confirmatory trial(s). ( 1 ) Limitations of Use Use of IQIRVO is not recommended in patients who have or develop decompensated cirrhosis (e.g., ascites, variceal bleeding, hepatic encephalopathy).
( 8.7 , 12.3 ) Limitations of Use Use of IQIRVO is not recommended in patients who have or develop decompensated cirrhosis (e.g., ascites, variceal bleeding, hepatic encephalopathy) [see Use in Specific Populations (8.7) , Clinical Pharmacology (12.3) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Before treatment, evaluate for muscle pain or myopathy, and/or verify that females of reproductive potential are not pregnant. ( 2.1 ) The recommended dosage is 80 mg orally once daily with or without food. ( 2.2 )
2.1Recommended Evaluation Before Initiating IQIRVO Before initiating IQIRVO: Evaluate for muscle pain or myopathy [see Warnings and Precautions (5.1) ] . Verify that females of reproductive potential are not pregnant prior to initiating treatment with IQIRVO [ see Warnings and Precautions (5.3) , Use in Specific Populations (8.1 , 8.3) ] .
2.2Recommended Dosage and Administration The recommended dosage of IQIRVO is 80 mg taken orally once daily with or without food [see Clinical Pharmacology (12.3) ] .
2.3Administration Modification for Bile Acid Sequestrants Administer IQIRVO at least 4 hours before or 4 hours after administering the bile acid sequestrant, or at as great an interval as possible [see Drug Interactions (7.2) ] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 80 mg, round, orange, film-coated tablets, debossed with "ELA 80" on one side and plain on the other side. Tablets: 80 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myalgia, Myopathy, and Rhabdomyolysis : Assess for muscle pain and myopathy prior to IQIRVO initiation. Consider periodic assessment (clinical exam, CPK measurement). Interrupt IQIRVO if there is new onset or worsening of muscle injury, or muscle pain.
( 5.1 ) Fractures: The risk of fracture should be considered in the care of patients treated with IQIRVO. Apply current standards of care for assessing and maintaining bone health. ( 5.2 ) Adverse Effects on Fetal and Newborn Development : May cause fetal harm.
Verify that a female of reproductive potential is not pregnant prior to initiating IQIRVO. Advise females of reproductive potential to avoid use of hormonal contraceptives containing ethinyl estradiol and to use alternative contraception. ( 5.3 , 8.1 , 8.3 ) Drug-Induced Liver Injury : Obtain clinical and laboratory assessments at treatment initiation and monitor thereafter according to routine patient management.
Interrupt the treatment if liver tests worsen, or patients develop signs and symptoms consistent with clinical hepatitis. Consider permanent discontinuation if liver tests worsen after restarting IQIRVO. ( 5.4 ) Hypersensitivity Reactions : If severe hypersensitivity reactions occur, permanently discontinue IQIRVO.
If a mild or moderate hypersensitivity reaction occurs, interrupt IQIRVO and treat promptly. Monitor until signs and symptoms resolve. ( 5.5 ) Biliary Obstruction : Avoid use in patients with complete biliary obstruction.
If biliary obstruction is suspected, interrupt IQIRVO and treat as clinically indicated. ( 5.6 )
5.1Myalgia, Myopathy, and Rhabdomyolysis Rhabdomyolysis resulting in acute kidney injury occurred in one IQIRVO-treated patient who had cirrhosis at baseline and was also taking a stable dose of an HMG-CoA reductase inhibitor (statin). Myalgia or myopathy, with or without CPK elevations, occurred in patients treated with IQIRVO alone or treated concomitantly with a stable dose of an HMG-CoA reductase inhibitor [see Adverse Reactions (6.1) ] . Assess for myalgia and myopathy prior to IQIRVO initiation.
Consider periodic assessment (clinical exam, CPK measurement) during treatment with IQIRVO, especially in those who have signs and symptoms of new onset or worsening of muscle pain or myopathy. Interrupt IQIRVO treatment if there is new onset or worsening of muscle pain, or myopathy, or rhabdomyolysis. IQIRVO may be restarted if an alternative etiology for these signs and symptoms has been identified and resolved.
However, discontinue IQIRVO if signs and symptoms recur. Patients concomitantly taking peroxisome proliferator-activated receptor-alpha (PPAR-alpha) agonists (e.g., fenofibrate, fenofibric acid) may have an increased risk of muscle injury. Monitor for signs and symptoms of muscle injury during concomitant use with IQIRVO [see Drug Interactions (7.2) ] .
5.2Fractures Fractures occurred in 6% of IQIRVO-treated patients compared to no placebo-treated patients [see Adverse Reactions (6.1) ] . Consider the risk of fracture in the care of patients treated with IQIRVO and monitor bone health according to current standards of care.
5.3Adverse Effects on Fetal and Newborn Development Based on findings from animal reproduction studies, IQIRVO may cause fetal harm when administered during pregnancy. Treatment of pregnant rats with elafibranor at maternal plasma drug exposures lower than or approximately equal to human exposure at the recommended dose resulted in stillbirths, reduced survival, decrease in pup body weight, and/or blue/black discoloration of the caudal section of body [see Use in Specific Populations (8.1) ] . For females of reproductive potential, verify that the patient is not pregnant prior to initiation of therapy.
IQIRVO may reduce the effectiveness of hormonal contraceptives containing ethinyl estradiol. Advise females of reproductive potential to avoid use of hormonal contraceptives containing ethinyl estradiol and to use alternative contrace… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Myalgia, Myopathy, and Rhabdomyolysis [see Warnings and Precautions (5.1) ] Fractures [see Warnings and Precautions (5.2) ] Drug-Induced Liver Injury [see Warnings and Precautions (5.4) ] Hypersensitivity Reactions [see Warnings and Precautions (5.5) ] Most common adverse reactions with IQIRVO (reported in ≥ 5% and higher compared to placebo) are weight gain, diarrhea, abdominal pain, nausea, vomiting, arthralgia, constipation, muscle injury, fracture, gastroesophageal reflux disease, dry mouth, weight loss, and rash.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ipsen Biopharmaceuticals, Inc. at 1-855-463-5127 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of IQIRVO is based on Study 1 consisting of 161 patients who were randomized to receive IQIRVO 80 mg (n=108) or placebo (n=53) once daily with a median duration of exposure during the double-blind period of 62 weeks (inter quartile range: 52, 84) [see Clinical Studies (14) ] .
IQIRVO or placebo was administered in combination with UDCA in 95% of patients and as monotherapy in 5% of patients who were unable to tolerate UDCA. The most common adverse reaction leading to treatment discontinuation was increased CPK (4%). Common Adverse Reactions Table 1 presents common adverse reactions that occurred in Study 1.
Table 1: Common Adverse Reactions Occurring During the Double-Blind Period in Adult Patients with PBC (Study 1) Included 8 patients (5%) who were intolerant to UDCA and initiated treatment as monotherapy: 6 patients (5%) in the IQIRVO arm and 2 patients (4%) in the placebo arm. Adverse Reaction Occurring in greater than or equal to 5% of patients in the IQIRVO treatment arm and at an incidence greater than or equal to 1% higher than in the placebo treatment arm. IQIRVO 80 mg Once Daily N = 108 % (n) Placebo N = 53 % (n) Weight gain Weight gain, abdominal pain, muscle pain, fracture, and rash include other related terms.
23% (25) 21% (11) Diarrhea 11% (12) 9% (5) Abdominal pain 11% (12) 6% (3) Nausea 11% (12) 6% (3) Vomiting 11% (12) 2% (1) Arthralgia 8% (9) 4% (2) Constipation 8% (9) 2% (1) Muscle pain 7% (8) 2% (1) Fracture 6% (7) 0 Gastroesophageal reflux disease 6% (7) 2% (1) Dry mouth 5% (5) 2% (1) Weight loss 5% (5) 0 Rash 5% (5) 4% (2) Gastrointestinal Adverse reactions Gastrointestinal symptoms were observed in 35 (32%) IQIRVO-treated patients compared to 6 (11%) in the placebo-treated patients. The severity of gastrointestinal events was mild in 43% of events and was moderate in 51% of events.
The median time to onset was 13 (0.3 to 92) weeks for diarrhea, 4 (0.1 to 26) weeks for nausea, and 23 (4 to 55) weeks for vomiting. The median duration of events was 0.6 (0.3 to 86) weeks for diarrhea, 2 (0.1 to 89) weeks for nausea and 0.3 (0.1 to 51) weeks for vomiting without requiring discontinuation of IQIRVO. Myalgia, Myopathy, and Rhabdomyolysis Muscle injury included rhabdomyolysis, CPK elevation with or without myalgia, and myopathy.
Rhabdomyolysis and acute kidney injury (AKI) occurred in one IQIRVO-treated patient who had cirrhosis at baseline and was also on a stable dose of an HMG-CoA reductase inhibitor for a year. Median time to development of myalgia was 85.5 days (interquartile range: 29, 291). CPK elevation and/or myalgia occurred in patients on IQIRVO monotherapy as well as in patients who were concomitantly treated with an HMG-CoA reductase inhibitor.
Table 2 presents the frequency of muscle injury related adverse reactions in Study 1. Table 2: Muscle Injury Related Adverse Reactions During the Double-Blind Period in Adult Pati… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Hormonal Contraceptives: Switch to progestin only products containing levonorgestrel/norgestrel, intrauterine systems, or effective non-hormonal contraceptives during treatment and for at least 3 weeks after last dose. ( 5.3 , 7.1 ) HMG-CoA Reductase Inhibitors : Monitor for signs and symptoms of muscle injury. ( 5.1 , 7.1 ) Strong CYP2C8 Inhibitors: Avoid concomitant use with strong CYP2C8 inhibitors (e.g. gemfibrozil).
If concomitant use cannot be avoided, monitor patients for adverse reactions. ( 7.2 ) Other Peroxisome Proliferator-Activated Receptor-Alpha (PPAR-alpha) Agonists : Monitor for signs and symptoms of liver injury and muscle injury. (7.2) Other PPAR-gamma Agonists : Monitor for signs and symptoms of liver injury (7.2) Rifampin: Monitor the biochemical response (e.g., ALP and bilirubin) when patients initiate rifampin during IQIRVO treatment.
( 7.2 ) Bile Acid Sequestrants: Administer at least 4 hours before or 4 hours after taking a bile acid binding sequestrant, or at as great an interval as possible. ( 2.3 , 7.2 )
7.1Effects of IQIRVO on Other Drugs Table 3 includes clinically significant drug interactions affecting other drugs. Table 3: Clinically Significant Interactions Affecting Other Drugs Hormonal Contraceptives Clinical Impact IQIRVO is a weak CYP3A4 inducer [see Clinical Pharmacology (12.3) ] . A clinical interaction study demonstrated that co-administration of IQIRVO and a combined oral hormonal contraceptive produced a decrease of ethinylestradiol which may lead to contraceptive failure and/or an increase in breakthrough bleeding, while levonorgestrel exposure remained unaffected.
Intervention Switch to progestin only product containing levonorgestrel/norgestrel, intrauterine system, or effective non-hormonal contraceptives when using hormonal contraceptives during treatment with IQIRVO and for at least 3 weeks after last dose [see Warnings and Precautions (5.3) , Use in Specific Populations (8.1 , 8.3) ] . HMG-CoA Reductase Inhibitors Clinical Impact CPK elevation and/or myalgia occurred in patients on IQIRVO monotherapy. Co-administration of IQIRVO and HMG-CoA reductase inhibitors (statins) which have a risk of myalgia, can increase the risk of myopathy by a mechanism that has not been fully characterized [see Adverse Reactions (6.1) ] .
Intervention Monitor for signs and symptoms of muscle injury. Consider periodic assessment (clinical exam, CPK) during treatment. Interrupt IQIRVO treatment if there is new onset or worsening of muscle pain or myopathy [see Warnings and Precautions (5.1) ] .
7.2Effects of Other Drugs on IQIRVO Table 4 includes clinically significant drug interactions affecting IQIRVO. Table 4: Clinically Significant Interactions Affecting IQIRVO Strong CYP2C8 Inhibitors Clinical Impact The major active metabolite of elafibranor, GFT1007, is a CYP2C8 substrate. Concomitant use with a strong CYP2C8 inhibitor may increase systemic exposure of GFT1007 [see Clinical Pharmacology (12.3) ] , which may increase the risk of IQIRVO adverse reactions.
Intervention Avoid concomitant use of IQIRVO with strong CYP2C8 inhibitors (e.g. gemfibrozil). If concomitant use cannot be avoided, monitor patients for adverse reactions. Other Peroxisome Proliferator-Activated Receptor-Alpha (PPAR-alpha) Agonists Clinical impact Co-administration of IQIRVO with other PPAR-alpha agonists (e.g., fenofibrate, fenofibric acid) may increase risk of liver injury and muscle injury.
Intervention Monitor for signs and symptoms of liver injury and muscle injury [see Warnings and Precautions (5.1 , 5.4) ] . Other Peroxisome Proliferator-Activated Receptor-gamma (PPAR-gamma) Agonists Clinical impact Co-administration of IQIRVO with PPAR-gamma agonists (e.g., pioglitazone, rosiglitazone) may increase risk of liver injury. Intervention Monitor for signs and symptoms of liver injury [see Warnings and Precautions (5.4) ].
Rifampin Clinical Impact Co-administration of IQIRVO with rifampin, an inducer of… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed during treatment and for 3 weeks after last dose. ( 8.2 ) Hepatic Impairment: Monitor patients with cirrhosis for evidence of decompensation. Consider discontinuation if patient progresses to moderate or severe hepatic impairment (Child-Pugh B or C). ( 8.7 )
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, IQIRVO may cause fetal harm when administered during pregnancy. Treatment of pregnant rats with elafibranor during organogenesis through lactation resulted in stillbirths, reduced survival, decrease in pup body weight, and/or blue/black discoloration of the caudal section of body, which occurred at maternal plasma drug exposures lower than or approximately equal to human exposure at the recommended dose ( see Data ). There are insufficient data from human pregnancies exposed to IQIRVO to allow an assessment of a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
There is a pregnancy safety study for IQIRVO. If IQIRVO is administered during pregnancy, healthcare providers should report IQIRVO exposure by contacting Ipsen Biopharmaceuticals, Inc. at 1-844-990-0239 or www.iqirvopregnancyregistry.com. Data Animal Data No effects on embryo-fetal development were observed in pregnant rats treated orally with up to 300 mg/kg/day elafibranor (15-times the recommended dose based on combined AUC [area under the plasma concentration-time curve] for elafibranor and GFT1007) during the period of organogenesis.
No adverse effects on embryo-fetal development were observed in pregnant rabbits treated orally with doses up to 100 mg/kg/day elafibranor, which produced systemic exposures (combined AUC for elafibranor and GFT1007) during the period of organogenesis that were less than the human exposure. Administration of 300 mg/kg/day (3.9-times the recommended dose based on combined AUC for elafibranor and GFT1007) produced marked maternal toxicity, embryo-lethality, reduced fetal weight, and a low incidence of fetal malformations.
Variations in ossification of distal limb bones occurred at 100 mg/kg/day, which was associated with strong signs of maternal toxicity (e.g., body weight loss). A pre- and postnatal development study was performed using oral administration of 10, 30, or 100 mg/kg/day elafibranor in female rats during organogenesis through lactation. All doses produced a reduction in pup survival (during postnatal days 1-4 at 100 mg/kg/day and postnatal days 5-21 at 10 mg/kg/day and higher), a decrease in pup body weight (dose-dependent, up to -28% on postnatal day 1), blue/black discoloration of the caudal section of body, and developmental delays based on evaluation of physical landmarks and functional tests.
The developmental delays were likely caused by the decrease in body weight. Adverse effects in the offspring occurred at maternal exposures at or above 0.6-times the recommended dose based on combined AUC for elafibranor and GFT1007. Stillbirths were observed in the 30 and 100 mg/kg/day groups (1.3 and 4.9-times the recommended dose, respectively, based on combined AUC for elafibranor and GFT1007).
Aortic or iliac arterial thrombosis was found in decedent pups from females treated with 30 or 100 mg/kg/day. The surviving adult offspring showed no effects on learning and memory, reflex development, or reproductive capability.
8.2Lactation Risk Summary There are no data available on the presence of elafibranor or its metabolites in human or animal milk, or on effects of the drug on the breastfed infant or the effects on milk producti… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, IQIRVO may cause fetal harm when administered during pregnancy. Treatment of pregnant rats with elafibranor during organogenesis through lactation resulted in stillbirths, reduced survival, decrease in pup body weight, and/or blue/black discoloration of the caudal section of body, which occurred at maternal plasma drug exposures lower than or approximately equal to human exposure at the recommended dose ( see Data ). There are insufficient data from human pregnancies exposed to IQIRVO to allow an assessment of a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes.
The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
There is a pregnancy safety study for IQIRVO. If IQIRVO is administered during pregnancy, healthcare providers should report IQIRVO exposure by contacting Ipsen Biopharmaceuticals, Inc. at 1-844-990-0239 or www.iqirvopregnancyregistry.com. Data Animal Data No effects on embryo-fetal development were observed in pregnant rats treated orally with up to 300 mg/kg/day elafibranor (15-times the recommended dose based on combined AUC [area under the plasma concentration-time curve] for elafibranor and GFT1007) during the period of organogenesis.
No adverse effects on embryo-fetal development were observed in pregnant rabbits treated orally with doses up to 100 mg/kg/day elafibranor, which produced systemic exposures (combined AUC for elafibranor and GFT1007) during the period of organogenesis that were less than the human exposure. Administration of 300 mg/kg/day (3.9-times the recommended dose based on combined AUC for elafibranor and GFT1007) produced marked maternal toxicity, embryo-lethality, reduced fetal weight, and a low incidence of fetal malformations.
Variations in ossification of distal limb bones occurred at 100 mg/kg/day, which was associated with strong signs of maternal toxicity (e.g., body weight loss). A pre- and postnatal development study was performed using oral administration of 10, 30, or 100 mg/kg/day elafibranor in female rats during organogenesis through lactation. All doses produced a reduction in pup survival (during postnatal days 1-4 at 100 mg/kg/day and postnatal days 5-21 at 10 mg/kg/day and higher), a decrease in pup body weight (dose-dependent, up to -28% on postnatal day 1), blue/black discoloration of the caudal section of body, and developmental delays based on evaluation of physical landmarks and functional tests.
The developmental delays were likely caused by the decrease in body weight. Adverse effects in the offspring occurred at maternal exposures at or above 0.6-times the recommended dose based on combined AUC for elafibranor and GFT1007. Stillbirths were observed in the 30 and 100 mg/kg/day groups (1.3 and 4.9-times the recommended dose, respectively, based on combined AUC for elafibranor and GFT1007).
Aortic or iliac arterial thrombosis was found in decedent pups from females treated with 30 or 100 mg/kg/day. The surviving adult offspring showed no effects on learning and memory, reflex development, or reproductive capability.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of IQIRVO have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 108 IQIRVO-treated patients with PBC, 25 (23%) were 65 years of age and older, while 1 (1%) was 75 years of age and older. No overall differences in effectiveness of IQIRVO has been observed in patients 65 years of age and older compared to younger adult patients. In healthy elderly subjects (age range 75-80 years), mean systemic exposure (AUC) of elafibranor and the major active metabolite, GFT1007 was 23% and 52% higher, respectively, than those in healthy young subjects (age range 26 to 42 years).
No dosage adjustment for patients 65 years of age and older is necessary. However, because of limited clinical experience with IQIRVO in patients older than 75 years old, closer monitoring of adverse events in patients older than 75 years is recommended [see Clinical Pharmacology (12.3) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Elafibranor and its main active metabolite GFT1007 are peroxisome proliferator-activated receptor (PPAR) agonists, both of which activate PPAR-alpha, PPAR-gamma, and PPAR-delta in vitro. However, the mechanism by which elafibranor exerts its therapeutic effects in patients with PBC is not well understood. Pharmacological activity that is potentially relevant to therapeutic effects includes inhibition of bile acid synthesis through activation of PPAR-alpha and PPAR-delta.
The signaling pathway for PPAR-delta was reported to include Fibroblast Growth Factor 21 (FGF21)-dependent downregulation of CYP7A1, the key enzyme for the synthesis of bile acids from cholesterol. An in vitro PPAR functional assay showed that both elafibranor and GFT1007 produced activation of PPAR-alpha (EC 50 = 46 nM and 14 nM, respectively, and E max = 56% and 61%, respectively, relative to reference agonists). The potency of elafibranor and GFT1007 for PPAR-alpha activation exceeded the respective potencies for PPAR-gamma and PPAR-delta activation by approximately 3- to 8-fold.
Although the in vitro pharmacology studies detected PPAR-gamma activation by elafibranor and its metabolite GFT1007, toxicology studies in rats and monkeys (species with plasma metabolite profiles comparable to human) showed none of the adverse effects that are associated with PPAR-gamma activation.
12.2Pharmacodynamics In patients with PBC treated with 80 mg once daily of IQIRVO (Study 1), a greater reduction in mean alkaline phosphatase (ALP) from baseline was observed as early as 4 weeks after treatment compared to the placebo group and lower ALP was generally maintained through week 52 [see Clinical Studies (14) ] . In another study, there was no apparent dose dependent increase in the reduction of ALP from baseline observed between 80 mg and 120 mg (1.5-times the recommended dose) once daily dosing in patients with PBC.
Cardiac Electrophysiology At 3.75-times the recommended dose of 80 mg, IQIRVO did not cause clinically significant QTc interval prolongation.
12.3Pharmacokinetics Following once daily dosing, steady state of elafibranor was achieved by Day 14, while steady state of GFT1007 was achieved by Day 7. The pharmacokinetics (PK) of elafibranor and GFT1007 were time-independent after 16-day repeated administration. At steady state, mean AUC0-24h of elafibranor and GFT1007 increased 3.3-fold and 2.6-fold for a 2.5-fold dose increase from 40 mg to 100 mg and 2.9-fold and 2.2-fold, respectively from 120 mg to 300 mg.
Mean AUC 0-24 of GFT1007 was 3.2-fold higher than the elafibranor exposure in patients with PBC at steady state. Table 5: Elafibranor and GFT1007 Systemic Exposures at Steady State in Patients with PBC Following 80 mg Once Daily C max,ss (ng/mL) Day 15 following repeated elafibranor 80 mg once daily administration in patients with PBC Mean (SD) AUC 0-24 (ng ∙ h/mL) Mean (SD) AUC ratio between Day 15/Day 1 Mean (min, max) Abbreviations: AUC = area under the concentration-versus-time curve; C max = maximum concentration; SS= Steady State Elafibranor 802 (443) 3758 (1749) 2.9 (0.86- to 13) GFT1007 2058 (459) 11985 (7149) 1.3 (0.6- to 3) Absorption Following once daily dosing of 80 mg in patients with PBC, median time to peak plasma concentrations (T max ) of elafibranor and GFT1007 was 1.25 hours (range: 0.5-2 hours).
Effect of Food When administered with a high-fat and high-calorie meal, T max was delayed by 30 minutes for elafibranor and by 1-hour for GFT1007 compared to in fasted conditions. Under fed condition, mean C max and AUC of elafibranor decreased by 50% and 15% respectively and mean C max of GFT1007 decreased by 30%, but the AUC was not affected compared to fasted conditions. The difference was not clinically meaningful.
Distribution Plasma protein binding of both elafibranor and GFT1007 was approximately 99.7% (mainly to serum albumin). The mean apparent volume of distribution (Vd/F) of elafibranor… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Elafibranor and its main active metabolite GFT1007 are peroxisome proliferator-activated receptor (PPAR) agonists, both of which activate PPAR-alpha, PPAR-gamma, and PPAR-delta in vitro. However, the mechanism by which elafibranor exerts its therapeutic effects in patients with PBC is not well understood. Pharmacological activity that is potentially relevant to therapeutic effects includes inhibition of bile acid synthesis through activation of PPAR-alpha and PPAR-delta.
The signaling pathway for PPAR-delta was reported to include Fibroblast Growth Factor 21 (FGF21)-dependent downregulation of CYP7A1, the key enzyme for the synthesis of bile acids from cholesterol. An in vitro PPAR functional assay showed that both elafibranor and GFT1007 produced activation of PPAR-alpha (EC 50 = 46 nM and 14 nM, respectively, and E max = 56% and 61%, respectively, relative to reference agonists). The potency of elafibranor and GFT1007 for PPAR-alpha activation exceeded the respective potencies for PPAR-gamma and PPAR-delta activation by approximately 3- to 8-fold.
Although the in vitro pharmacology studies detected PPAR-gamma activation by elafibranor and its metabolite GFT1007, toxicology studies in rats and monkeys (species with plasma metabolite profiles comparable to human) showed none of the adverse effects that are associated with PPAR-gamma activation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied IQIRVO (elafibranor) tablets are available as 80 mg, round, orange, film-coated tablets, debossed with 'ELA 80' on one side and plain on the other side. IQIRVO is supplied in a child-resistant 30 count bottle (NDC 15054-0080-1). Storage and Handling Store at room temperature 15°C to 30°C (59°F to 86° F). Store in the original package (bottle and carton) to protect from moisture and light.
📦 Storage and Handling ▾
Storage and Handling Store at room temperature 15°C to 30°C (59°F to 86° F). Store in the original package (bottle and carton) to protect from moisture and light.
📋 Description ▾
11 DESCRIPTION Elafibranor and its main active metabolite GFT1007 are peroxisome proliferator-activated receptor (PPAR) agonists. Elafibranor is practically insoluble in aqueous media at pH in the range 1.2 to 6.8. It is very slightly soluble at pH 7.5.
It is soluble in dichloromethane, freely soluble in DMSO and sparingly soluble in 2-propanol and ethanol. Its chemical formula is C 22 H 24 O 4 S, the molecular weight is 384.49 g/mol, the chemical name is 2-(2,6-Dimethyl-4-{3-[4-(methylsulfanyl)phenyl]-3-oxoprop-1-en-1-yl}phenoxy)-2-methylpropanoic acid and it has the following structural formula: IQIRVO (elafibranor) tablets are supplied as 80 mg film-coated tablets for oral administration. Each tablet contains 80 mg elafibranor and the following inactive ingredients: colloidal silica dioxide, croscarmellose sodium, magnesium stearate, microcrystalline cellulose, and povidone.
The film coating consists of: iron oxide red, iron oxide yellow, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Myalgia, Myopathy, and Rhabdomyolysis Advise patients that IQIRVO may cause rhabdomyolysis. Inform patients to report immediately to their healthcare provider any unexplained muscle symptoms such as pain, soreness, or weakness [see Warnings and Precautions (5.1) ] .
Fractures Inform patients or their caregiver(s) that IQIRVO may increase the risk of bone fractures. Advise patients to call their healthcare provider to report any fractures [see Warnings and Precautions (5.2) ] . Adverse Effects on Fetal and Newborn Development Advise pregnant women and females of reproductive potential of the potential risk to the fetus and to inform their healthcare providers of a known, suspected, or planned pregnancy during treatment with IQIRVO.
Advise females of reproductive potential to use effective contraception during treatment and for 3 weeks after the last dose of IQIRVO [see Warning and Precautions (5.3) , Use in Specific Population (8.1 , 8.3) ] . Lactation Advise women not to breastfeed during treatment with IQIRVO and for 3 weeks after the last dose [see Use in Specific Populations (8.2) ] . Contraception Advise females of reproductive potential that use of IQIRVO may reduce the efficacy of hormonal contraceptives containing ethinyl estradiol.
Advise females of reproductive potential to avoid use of hormonal contraceptives containing ethinyl estradiol and to use alternative contraception, including progestin-only contraceptives containing levonorgestrel/norgestrel, intrauterine systems, or effective non-hormonal contraceptives during treatment with IQIRVO and for 3 weeks after the last dose [see Drug Interactions (7.1) and Use in Specific Populations (8.3) ]. Pregnancy Inform patients that there is a pregnancy safety study tracking pregnancy exposures and outcomes with IQIRVO.
Ask pregnant women to report IQIRVO exposure by contacting Ipsen Biopharmaceuticals, Inc. at 1-844-990-0239 or www.iqirvopregnancyregistry.com. Drug-Induced Liver Injury Inform patients of the risk of IQIRVO-induced liver injury. Instruct patients to report any signs or symptoms of liver injury (e.g., loss of appetite, nausea, increased fatigue, lower extremity edema, abdominal swelling, or jaundice/icterus) to their healthcare provider [see Warnings and Precautions (5.4) ] .
Hypersensitivity Reactions Advise patients to contact their healthcare provider or go to the emergency department if hypersensitivity reactions, such as rash, occur [see Warnings and Precautions (5.5) ] . Biliary Obstruction Instruct patients to immediately report any signs or symptoms of biliary obstruction (e.g., right upper quadrant pain, jaundice) to their healthcare provider so that IQIRVO treatment can be interrupted while the patient is being evaluated [see Warnings and Precautions (5.6) ] .
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration Revised: 08/2026 MEDICATION GUIDE IQIRVO® (eye-ker-vo) (elafibranor) tablets What is IQIRVO? IQIRVO is a prescription medicine used to treat primary biliary cholangitis (PBC) in combination with ursodeoxycholic acid (UDCA) in adults who have not responded well to UDCA or used alone in patients unable to tolerate UDCA.
IQIRVO is not recommended for use in people who have symptoms or signs of advanced liver disease (decompensated cirrhosis) including confusion; having fluid in the stomach-area (abdomen); black, tarry, or bloody stools; coughing up or vomiting blood, or having vomit that looks like "coffee grounds." It is not known if taking IQIRVO will improve your chance of survival or prevent liver decompensation. It is not known if IQIRVO is safe and effective in children under 18 years of age. Before taking IQIRVO, tell your healthcare provider about all of your medical conditions, including if you : have advanced liver disease. are pregnant or plan to become pregnant.
IQIRVO can harm your unborn baby. You should not become pregnant during treatment with IQIRVO. Pregnancy Registry.
There is a pregnancy registry for women who become pregnant while taking IQIRVO. If you become pregnant while receiving IQIRVO, tell your healthcare provider right away. Talk to your healthcare provider about providing information to the IQIRVO pregnancy registry.
The purpose of this study is to collect information about your health and your baby's health. You or your healthcare provider can report your pregnancy by calling 1-844-990-0239 or visiting www.iqirvopregnancyregistry.com are breastfeeding or plan to breastfeed. It is not known if IQIRVO passes into your breast milk.
Do not breastfeed while taking IQIRVO and for 3 weeks after the last dose of IQIRVO. Talk with your healthcare provider about the best way to feed your baby if you take IQIRVO. Your healthcare provider should check for muscle pain or weakness before you start taking IQIRVO.
Tell your healthcare provider right away if you have new or severe muscle pain or muscle weakness. Females who can become pregnant: You should use an effective method of birth control, such as progestin-only contraceptives containing levonorgestrel or norgestrel, or intrauterine systems, or effective non hormonal contraceptives while you are taking IQIRVO and for 3 weeks after the last dose of IQIRVO. Tell your healthcare provider right away if you become pregnant or think you may be pregnant.
Tell your healthcare provider about all of the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. IQIRVO can affect the way certain medicines work. Certain medicine may affect the way IQIRVO works.
Especially tell your healthcare provider if you use or take: a hormonal birth control method such as pills, shots, patches and implants. Hormonal birth control methods may not work as well when taken with IQIRVO. How should I take IQIRVO?
Take IQIRVO exactly as your healthcare provider tells you to. Take IQIRVO with or without food. If you take a bile acid binding resin, take IQIRVO at least 4 hours before or 4 hours after you take your bile acid binding resin.
If this is not possible, space the time between taking IQIRVO and your bile acid binding resin as far apart as possible. What are the possible side effects of IQIRVO? IQIRVO can cause serious side effects including: Muscle problems (myalgia, myopathy, rhabdomyolysis).
IQIRVO can cause muscle problems that can be severe. Treatment with IQIRVO may cause muscle pain or worsen existing pain and can increase the level of an enzyme in your blood called creatine phosphokinase (CPK) and can be a sign of muscle damage. Your healthcare provider should test for muscle weakness or pain before and during treatment.
If there is new onset or worsening of muscle pain, your healthcare provider may temporarily stop your treatment. IQIRVO may be… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following once daily dosing, steady state of elafibranor was achieved by Day 14, while steady state of GFT1007 was achieved by Day 7. The pharmacokinetics (PK) of elafibranor and GFT1007 were time-independent after 16-day repeated administration. At steady state, mean AUC0-24h of elafibranor and GFT1007 increased 3.3-fold and 2.6-fold for a 2.5-fold dose increase from 40 mg to 100 mg and 2.9-fold and 2.2-fold, respectively from 120 mg to 300 mg.
Mean AUC 0-24 of GFT1007 was 3.2-fold higher than the elafibranor exposure in patients with PBC at steady state. Table 5: Elafibranor and GFT1007 Systemic Exposures at Steady State in Patients with PBC Following 80 mg Once Daily C max,ss (ng/mL) Day 15 following repeated elafibranor 80 mg once daily administration in patients with PBC Mean (SD) AUC 0-24 (ng ∙ h/mL) Mean (SD) AUC ratio between Day 15/Day 1 Mean (min, max) Abbreviations: AUC = area under the concentration-versus-time curve; C max = maximum concentration; SS= Steady State Elafibranor 802 (443) 3758 (1749) 2.9 (0.86- to 13) GFT1007 2058 (459) 11985 (7149) 1.3 (0.6- to 3) Absorption Following once daily dosing of 80 mg in patients with PBC, median time to peak plasma concentrations (T max ) of elafibranor and GFT1007 was 1.25 hours (range: 0.5-2 hours).
Effect of Food When administered with a high-fat and high-calorie meal, T max was delayed by 30 minutes for elafibranor and by 1-hour for GFT1007 compared to in fasted conditions. Under fed condition, mean C max and AUC of elafibranor decreased by 50% and 15% respectively and mean C max of GFT1007 decreased by 30%, but the AUC was not affected compared to fasted conditions. The difference was not clinically meaningful.
Distribution Plasma protein binding of both elafibranor and GFT1007 was approximately 99.7% (mainly to serum albumin). The mean apparent volume of distribution (Vd/F) of elafibranor in healthy subjects was 4731 L, following a single dose of elafibranor at 80 mg in fasted conditions. Elimination Following a single 80 mg dose under fasted conditions, median elimination half-life was 70.2 hours (range 37.1 to 92.2 hours) for elafibranor, and 15.4 hours (range 9.39 to 21.7 hours) for major active metabolite GFT1007.
Elafibranor mean apparent total clearance (CL/F) was
50.0L/h after a single 80 mg dose under fasted conditions. Metabolism Elafibranor is extensively metabolized to form a major active metabolite, GFT1007. The mean systemic exposure (AUC) to GFT1007 was 3.2-fold higher than that of elafibranor at steady state.
Additional major inactive metabolite, an acyl glucuronide conjugate GFT3351 that consisted of four stereoisomers was formed. In vitro studies showed that elafibranor was metabolized by cytosolic enzyme, 15-ketoprostaglandin 13-Δ reductase (PTGR1), to form GFT1007. Elafibranor was also metabolized by CYP2J2, and uridine diphosphate (UDP)-glucuronosyltransferase (UGT) isoforms, UGT1A3, UGT1A4, and UGT2B7.
GFT1007 was further metabolized by CYP2C8 (27.2%), UGT1A6 (39.7%), and UGT2B7 (14.1%). Excretion Following a single 120 mg oral dose (1.5-times the recommended dose) of 14 C-radiolabelled elafibranor in healthy subjects, approximately 77.1% of the dose was recovered in feces, primarily as elafibranor (56.7% of the administered dose) and its major metabolite GFT1007 (6.08% of the administered dose). Approximately 19.3% was recovered in urine, primarily as glucuronide conjugate GFT3351 (11.8% of the administered dose).
A negligible amount of unchanged elafibranor or GFT1007 was detectable in the urine. Biliary excretion of elafibranor in humans was suggested by the excretion of 60% of orally administered elafibranor in the bile of rats. Specific Populations There was no evidence that sex and body mass index (BMI) (14.5 to 53.5 kg/m 2 ) or body weight (43 kg to 120 kg) had any clinically meaningful impact on PK of elafibranor and GFT1007.
Age Following single dose 120 mg elafibranor administration (1.5-times the recommended dos… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In patients with PBC treated with 80 mg once daily of IQIRVO (Study 1), a greater reduction in mean alkaline phosphatase (ALP) from baseline was observed as early as 4 weeks after treatment compared to the placebo group and lower ALP was generally maintained through week 52 [see Clinical Studies (14) ] . In another study, there was no apparent dose dependent increase in the reduction of ALP from baseline observed between 80 mg and 120 mg (1.5-times the recommended dose) once daily dosing in patients with PBC.
Cardiac Electrophysiology At 3.75-times the recommended dose of 80 mg, IQIRVO did not cause clinically significant QTc interval prolongation.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy of IQIRVO was evaluated in Study 1 (NCT04526665), a multi-center, randomized, double-blind, placebo-controlled study. The study included 161 adults with PBC with an inadequate response or intolerance to UDCA. Patients were randomized to receive IQIRVO 80 mg (n=108) or placebo (n=53) once daily for at least 52 weeks.
When applicable, patients continued their pre-study dose of UDCA throughout the study. Patients were included in the study if their ALP was greater than or equal to 1.67-times the ULN and TB was less than or equal to 2-times the ULN. Patients were excluded if they had other liver disease or in case of decompensated cirrhosis.
The mean age of patients in Study 1 was 57 (Range: 36, 76) years, and the mean weight was 70.8 (Range: 43, 134) kg. The study population was predominately female (96%) and White (91%). The baseline mean ALP concentration was 321.9 (Range: 151, 1398) U/L, and 39% of patients had a baseline ALP concentration greater than 3-times the ULN.
The mean baseline TB concentration was 0.56 (Range: 0.15, 1.76) mg/dL, and 96% of patients had a baseline TB concentration less than or equal to ULN. The baseline mean concentration of ALT was 50 (Range: 11 to 188) U/L and mean baseline concentration for AST was 46 (Range: 14 to 203) U/L. Most patients (95%) received study treatment (IQIRVO or placebo) in combination with UDCA.
There were 6 (6%) in the IQIRVO-treated patients and 2 (4%) in the placebo-treated patients who were unable to tolerate UDCA and received IQIRVO as monotherapy. At baseline, 12 (11%) of the IQIRVO-treated patients and 8 (15%) of the placebo-treated patients met at least one of the following criteria: serum albumin < 3.5g/dL, INR >1.3, TB > 1-time ULN, Fibroscan >16.9 kPa, or historical biopsy suggestive of cirrhosis. The primary endpoint was biochemical response at Week 52, where biochemical response was defined as achieving ALP less than 1.67-times ULN, TB less than or equal to ULN, and ALP decrease greater than or equal to 15% from baseline.
The ULN for ALP was defined as 129 U/L for males and 104 U/L for females. The ULN for TB was defined as 1.20 mg/dL. ALP normalization (i.e., ALP less than or equal to ULN) at Week 52 was a key secondary endpoint.
Table 6 presents results at Week 52 for the percentage of patients who achieved biochemical response, achieved each component of biochemical response, and achieved ALP normalization. IQIRVO demonstrated greater improvement on biochemical response and ALP normalization at Week 52 compared to placebo. Overall, 96% of patients had a baseline TB concentration less than or equal to ULN.
Therefore, improvement in ALP was the main contributor to the biochemical response rate results at Week 52. Table 6: Percentage of Adult Patients with PBC Achieving Biochemical Response and ALP Normalization at Week 52 in Study 1 Patients who prematurely stopped the study treatment or used rescue therapy for PBC prior to the Week 52 assessment were considered non-responders. For two other patients with missing data at Week 52, the closest non-missing assessment from the double-blind treatment period was used.
IQIRVO 80mg Once Daily (N=108) Placebo (N=53) Treatment Difference, % (95% CI) For biochemical response and its components: calculated using the Newcombe method stratified by (1) ALP > 3-times ULN or TB > ULN (Yes/No) and (2) 14-day baseline average PBC Worst Itch Numeric Rating Scale score ≥ 4 (Yes/No). For ALP normalization: calculated using unstratified Newcombe method. Biochemical response rate, n (%) Biochemical response is defined as ALP <1.67-times ULN and TB ≤ULN and ALP decrease from baseline ≥ 15% at Week 52.
The p-value from the exact Cochran–Mantel–Haenszel (CMH) test was <0.0001. 55 (51) 2 (4) 47 (32, 57) Components of biochemical response ALP less than 1.67-times ULN, n (%) 56 (52) 5 (9) 42 (27, 53) Decrease in ALP of at least 15%, n (%) 81 (75) 9 (17) 58 (43, 69) TB less than or equal to ULN, n (%) The mean bas… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a 2-year study in CD-1 mice, oral administration of elafibranor produced hepatocellular tumors (adenoma or carcinoma) in both sexes at doses of 1, 3, 10, and 30 mg/kg/day (0.007 to 0.14 times the recommended dose in males and 0.003 to 0.16 times the recommended dose in females based on combined AUC for elafibranor and GFT1007). In a 2-year study in Sprague-Dawley rats, oral administration of elafibranor produced hepatocellular tumors (adenoma or carcinoma) at 10 mg/kg/day and higher in males (0.36 times the recommended dose based on combined AUC for elafibranor and GFT1007) and at 30 mg/kg/day in females (2.1 times the recommended dose based on combined AUC for elafibranor and GFT1007).
In males, elafibranor also produced pancreatic acinar cell adenoma and testicular Leydig cell adenoma at 30 mg/kg/day (2.1 times the recommended dose based on combined AUC for elafibranor and GFT1007). The liver tumors in mice and rats may be attributed to the expected rodent-specific PPARα-related liver toxicity and its related consequences. Therefore, the relevance to humans is uncertain.
Mutagenesis Elafibranor was negative in the in vitro bacterial reverse mutation (Ames) assay, the in vivo rat micronucleus assay, and the in vivo rat comet assay. Elafibranor was mutagenic in L5178Y tk+/- mouse lymphoma cells in the absence or presence of metabolic activation and it induced the formation of micronuclei in this cell line in the presence of metabolic activation. The metabolites GFT1007 and racemic GFT3351 were both negative in the in vitro bacterial reverse mutation (Ames) assay.
GFT1007 tested negative in the in vitro micronucleus assay in L5178Y tk+/- mouse lymphoma cells, and GFT3351 tested negative in the in vitro micronucleus assay in human lymphocytes. The overall data and weight-of-evidence from the comprehensive battery of in vivo and in vitro genotoxicity assays conducted for elafibranor, its principal active metabolite GFT1007, and the acyl glucuronide metabolite racemic GFT3351 indicate that the parent drug and its tested metabolites are unlikely to have genotoxic potential. Impairment of Fertility Elafibranor produced no adverse effects on rat fertility or early embryonic development at oral doses up to 100 mg/kg/day (5.9 times the recommended dose in females and 7.4 times the recommended dose in males based on combined AUC for elafibranor and GFT1007).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis In a 2-year study in CD-1 mice, oral administration of elafibranor produced hepatocellular tumors (adenoma or carcinoma) in both sexes at doses of 1, 3, 10, and 30 mg/kg/day (0.007 to 0.14 times the recommended dose in males and 0.003 to 0.16 times the recommended dose in females based on combined AUC for elafibranor and GFT1007). In a 2-year study in Sprague-Dawley rats, oral administration of elafibranor produced hepatocellular tumors (adenoma or carcinoma) at 10 mg/kg/day and higher in males (0.36 times the recommended dose based on combined AUC for elafibranor and GFT1007) and at 30 mg/kg/day in females (2.1 times the recommended dose based on combined AUC for elafibranor and GFT1007).
In males, elafibranor also produced pancreatic acinar cell adenoma and testicular Leydig cell adenoma at 30 mg/kg/day (2.1 times the recommended dose based on combined AUC for elafibranor and GFT1007). The liver tumors in mice and rats may be attributed to the expected rodent-specific PPARα-related liver toxicity and its related consequences. Therefore, the relevance to humans is uncertain.
Mutagenesis Elafibranor was negative in the in vitro bacterial reverse mutation (Ames) assay, the in vivo rat micronucleus assay, and the in vivo rat comet assay. Elafibranor was mutagenic in L5178Y tk+/- mouse lymphoma cells in the absence or presence of metabolic activation and it induced the formation of micronuclei in this cell line in the presence of metabolic activation. The metabolites GFT1007 and racemic GFT3351 were both negative in the in vitro bacterial reverse mutation (Ames) assay.
GFT1007 tested negative in the in vitro micronucleus assay in L5178Y tk+/- mouse lymphoma cells, and GFT3351 tested negative in the in vitro micronucleus assay in human lymphocytes. The overall data and weight-of-evidence from the comprehensive battery of in vivo and in vitro genotoxicity assays conducted for elafibranor, its principal active metabolite GFT1007, and the acyl glucuronide metabolite racemic GFT3351 indicate that the parent drug and its tested metabolites are unlikely to have genotoxic potential. Impairment of Fertility Elafibranor produced no adverse effects on rat fertility or early embryonic development at oral doses up to 100 mg/kg/day (5.9 times the recommended dose in females and 7.4 times the recommended dose in males based on combined AUC for elafibranor and GFT1007).
📄 Recent Major Changes ▾
Warnings and Precautions (5.1 , 5.3 , 5.4 ) 08/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 80 mg Tablet Bottle Carton Rx only NDC 15054-0080-1 IQIRVO ® (elafibranor) tablets 80 mg For Oral Use 30 tablets PRINCIPAL DISPLAY PANEL - 80 mg Tablet Bottle Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |