
mycophenolate mofetil 500 mg Tablet, 500-count — NDC 16729-019-16 (Billing 16729-0019-16)
This is a package of 500 tablets of mycophenolate mofetil 500 mg Tablet from Accord Healthcare Inc., marketed since May 2009 and currently FDA-listed; retail pharmacies pay about $0.2633 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 16729-019-16 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 16729 labeler · 019 product · 16 package
- Package marketed since
- May 4, 2009
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 500 EA per package
- Barcode (UPC-A, from the NDC)
- 3 1672901916 3
- Medicaid fills, this package
- 6,861 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Mycophenolate Mofetil (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 032599
- GCN: 47561
- GPI-14 (Medi-Span): 99403030100330
- HICL (First Databank): 010012
- AHFS class code: 90:28.08.92
- RxCUI (RxNorm): 199058
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Mycophenolate is used to prevent transplant organ rejection (attack of the new organ by the immune system) in people who have received kidney, heart, or liver transplants. Mycophenolate is in a class of medications called immunosuppressive agents. It works by weakening the body's immune system so it will not attack and reject the transplanted organ.
Read the full MedlinePlus article ↗- It helps keep your body from rejecting a transplanted kidney, heart or liver. You take it together with other immunosuppressant medicines. It works by calming the immune cells that...
- It's usually taken twice a day, by mouth as a capsule, tablet or liquid, or through an IV in the hospital. Follow your prescriber's directions and your label. Don't switch it with...
- Diarrhea, nausea, vomiting and stomach pain are common. Call your doctor if you have a fever, chills or other signs of infection, unusual bruising or bleeding, black stools, severe...
- What side effects are normal, and when should I call?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mycophenolate Mofetil — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.263 | $131.65 / 500 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3299 | $164.95 / 500 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2914 | $145.70 / 500 tablets |
| Medicare Part B allowsASP · J7517 | $0.131 / J7517 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 16729-0019-01 16729-019-01 | 100 TABLET in 1 BOTTLE | $0.2633 / ea | $26.33 | 2009-05-04 | — | Active |
| 16729-0019-16 You're viewing this Main listing | 500 TABLET in 1 BOTTLE | $0.2633 / ea | $131.64 | 2009-05-04 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.2633 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 62% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 16729-0019-01?
What NDC number is used to bill for this package of mycophenolate mofetil 500 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mycophenolate Mofetil 500 mg 00054-0166-25 | Hikma | 100 tablets | $0.263 | — | Availability likely | — |
| Mycophenolate Mofetil 500 mg 00781-5175-01 | Sandoz | 100 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate mofetil 500 mg 00904-7078-61 | Major | 1 tablet | $0.263 | AB | Availability likely | — |
| mycophenolate mofetil 500 mgthis 16729-0019-16 | Accord | 500 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate mofetil 500 mg 23155-0836-01 | Heritage | 100 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate Mofetil 500 mg 31722-0879-01 | Camber | 100 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate Mofetil 500 mg 50268-0558-15 | AvPAK | 1 tablet | $0.263 | AB | Availability likely | — |
| Mycophenolate Mofetil 500 mg 59651-0638-01 | Aurobindo | 100 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate mofetil 500 mg 60687-0438-01 | American | 1 tablet | $0.263 | AB | Availability likely | — |
| Mycophenolate mofetil 500 mg 64380-0725-06 | Strides | 100 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate Mofetil 500 mg 67877-0225-01 | Ascend | 100 tablets | $0.263 | AB | Availability likely | — |
| Mycophenolate Mofetil 500 mg 72888-0185-01 | Advagen | 100 tablets | $0.263 | AB | Availability likely | — |
| CellCept 500 mg 00004-0260-01 | Genentech, | 100 tablets | $17.339 | AB | Availability likely | +6486% |
| Mycophenolate mofetil 500 mg 42543-0989-07 | Strides | 500 tablets | — | AB | FDA listed | — |
| Mycophenolate Mofetil 500 mg 50090-4275-00 | A-S | 180 tablets | — | AB | FDA listed | — |
| Mycophenolate mofetil 500 mg 55154-3571-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| mycophenolate mofetil 500 mg 63629-9582-01 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Mycophenolate mofetil 500 mg 68071-3767-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Mycophenolate Mofetil 500 mg 68254-5003-01 | CONCORD | 30 tablets | — | AB | FDA listed | — |
| Mycophenolate mofetil 500 mg 70518-2767-01 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| Mycophenolate mofetil 500 mg 70518-4377-00 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| Mycophenolate Mofetil 500 mg 71610-0033-70 | Aphena | 120 tablets | — | — | FDA listed | — |
| Mycophenolate mofetil 500 mg 73190-0010-01 | AvKARE | 100 tablets | — | AB | FDA listed | — |
| Mycophenolate mofetil 500 mg 82804-0033-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII UKE75GEA7F
Hydroxypropyl cellulose is a plant-based polymer used as a binder and thickener. It helps hold tablet ingredients together, controls how fast the medicine dissolves, and improves the texture of liquid formulations.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Accord Healthcare Inc. labeler code 16729
- simvastatin 40 mg Tablet, Film Coated NDC 16729-006-10
- simvastatin 80 mg Tablet, Film Coated NDC 16729-007-10
- Pravastatin Sodium 10 mg Tablet NDC 16729-008-15
- Pravastatin Sodium 20 mg Tablet NDC 16729-009-15
- Pravastatin Sodium 40 mg Tablet NDC 16729-010-15
- Pravastatin Sodium 80 mg Tablet NDC 16729-011-15
- Bicalutamide 50 mg Tablet NDC 16729-023-01
- Letrozole 2.5 mg Tablet, Film Coated NDC 16729-034-10
- Anastrozole 1 mg Tablet NDC 16729-035-10
- Tacrolimus .5 mg Capsule NDC 16729-041-01
- Tacrolimus 1 mg Capsule NDC 16729-042-01
- Tacrolimus 5 mg Capsule NDC 16729-043-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYOFETAL TOXICITY, MALIGNANCIES and SERIOUS INFECTIONS Use during pregnancy is associated with increased risks of first trimester pregnancy loss and congenital malformations. Avoid if safer treatment options are available. Females of reproductive potential must be counseled regarding pregnancy prevention and planning [see Warnings and Precautions (5.1) , Use in Special Populations (8.1 , 8.3) ] .
Increased risk of development of lymphoma and other malignancies, particularly of the skin [see Warnings and Precautions (5.2) ] . Increased susceptibility to bacterial, viral, fungal and protozoal infections, including opportunistic infections and viral reactivation of hepatitis B and C, which may lead to hospitalizations and fatal outcomes [see Warnings and Precautions (5.3) ] . WARNING: EMBRYOFETAL TOXICITY, MALIGNANCIES and SERIOUS INFECTIONS See full prescribing information for complete boxed warning Use during pregnancy is associated with increased risks of first trimester pregnancy loss and congenital malformations.
Avoid if safer treatment options are available. Females of reproductive potential must be counseled regarding pregnancy prevention and planning [see Warnings and Precautions (5.1) ]. Increased risk of development of lymphoma and other malignancies, particularly of the skin [see Warnings and Precautions (5.2) ] .
Increased susceptibility to infections, including opportunistic infections and severe infections with fatal outcomes [see Warnings and Precautions (5.3) ].
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mycophenolate mofetil (MMF) is indicated for the prophylaxis of organ rejection, in adult and pediatric recipients 3 months of age and older of allogeneic kidney [see Clinical Studies (14.1) ] , heart [see Clinical Studies (14.2) ] or liver transplants [see Clinical Studies (14.3) ], in combination with other immunosuppressants. Mycophenolate mofetil is an antimetabolite immunosuppressant indicated for the prophylaxis of organ rejection in adult and pediatric recipients 3 months of age and older of allogeneic kidney, heart or liver transplants, in combination with other immunosuppressants ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION ADULTS DOSAGE Kidney Transplant 1 g twice daily, orally ( 2.2 ) Heart Transplant 1.5 g twice daily orally ( 2.3 ) Liver Transplant 1.5 g twice daily orally ( 2.4 ) PEDIATRICS Kidney Transplant 600 mg/m 2 orally twice daily, up to maximum of 2 g daily ( 2.2 ) Heart Transplant 600 mg/m 2 orally twice daily, (starting dose) up to a maximum of 900 mg/m 2 twice daily (3 g) ( 2.3 ) Liver Transplant 600 mg/m 2 orally twice daily,daily (starting dose) up to a maximum of 900 mg/m 2 twice daily (3 g) ( 2.4 ) Reduce or interrupt dosing in the event of neutropenia.
( 2.5 ) See full prescribing information (FPI) for: adjustments for renal impairment and neutropenia ( 2.5 )
2.1Important Administration Instructions Mycophenolate mofetil should not be used without the supervision of a physician with experience in immunosuppressive therapy. Mycophenolate Mofetil Capsules and Tablets Mycophenolate mofetil oral dosage forms (capsules or tablets) should not be used interchangeably with mycophenolic acid delayed-release tablets without supervision of a physician with experience in immunosuppressive therapy because the rates of absorption following the administration of mycophenolate mofetil oral dosage forms and mycophenolic acid delayed-release tablets are not equivalent.
Mycophenolate mofetil tablets should not be crushed and mycophenolate mofetil capsules should not be opened or crushed. Patients should avoid inhalation or contact of the skin or mucous membranes with the powder contained in mycophenolate mofetil capsules and oral suspension. If such contact occurs, they must wash the area of contact thoroughly with soap and water.
In case of ocular contact, rinse eyes with plain water. The initial oral dose of mycophenolate mofetil should be given as soon as possible following kidney, heart or liver transplant. It is recommended that mycophenolate mofetil be administered on an empty stomach.
In stable transplant patients, however, mycophenolate mofetil may be administered with food if necessary [see Clinical Pharmacology (12.3) ] . Patients should be instructed to take a missed dose as soon as they remember, except if it is closer than 2 hours to the next scheduled dose; in this case, they should continue to take mycophenolate mofetil at the usual times.
2.2Dosage Recommendations for Kidney Transplant Patients Adults The recommended dosage for adult kidney transplant patients is 1 g orally or intravenously infused over no less than 2 hours, twice daily (total daily dose of 2 g). Pediatrics (3 months and older) Pediatric dosing is based on body surface area (BSA).The recommended dosage of mycophenolate mofetil oral suspension for pediatric kidney transplant patients 3 months and older is 600 mg/m 2 , administered twice daily (maximum total daily dose of 2 g or 10 mL of the oral suspension).
Pediatric patients with BSA ≥1.25 m 2 may be dosed with capsules or tablets as follows: Table 1 Pediatric Kidney Transplant: Dosage Using Capsules or Tablets Body Surface Area Dosage 1.25 m 2 to <1.5 m 2 Mycophenolate mofetil capsule 750 mg twice daily (1.5 g total daily dose) ≥ 1.5 m 2 Mycophenolate mofetil capsules or tablets 1 g twice daily (2 g total daily dose)
2.3Dosage Recommendations for Heart Transplant Patients Adults The recommended dosage of mycophenolate mofetil for adult heart transplant patients is 1.5 g orally twice daily (total daily dose of 3 g). Pediatric patients with BSA ≥1.25 m 2 may be started on therapy with capsules or tablets as follows: Table 2 Pediatric Heart Transplant: Pediatric Starting Dosage Using Capsules or Tablets Body Surface Area Starting Dosage Maximum maintenance dose: 3 g total daily. 1.25 m 2 to <1.5 m 2 Mycophenolate mofetil capsule 750 mg twice daily (1.5 g total daily dose) ≥ 1.5 m 2 Mycophenolate mofetil capsules or tablets 1 g twice daily (2 g total daily dose)
2.4Dosage Recommendations for Liver Transplant Patients Adults The recommended dosage of mycophenolate mofetil for adult l… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Mycophenolate Mofetil Capsules, USP are available containing 250 mg of mycophenolate mofetil, USP. The 250 mg capsules are light blue/ peach, size ‘1’ hard gelatin capsules, printed in black with ‘GC1’ on body containing white to off white powder. Mycophenolate Mofetil Tablets, USP are available containing 500 mg of mycophenolate mofetil, USP.
The 500 mg tablets are purple coloured, capsule shaped, biconvex, film coated tablets debossed ‘AHI’ on one side and ‘500’ on other side. Capsules: 250 mg Tablets: 500 mg
⛔ Contraindications ▾
4 CONTRAINDICATIONS Mycophenolate Mofetil Capsules is contraindicated in patients with a history of hypersensitivity, including anaphylaxis, to mycophenolate mofetil (MMF), mycophenolic acid (MPA) or any component of the drug product [see Warnings and Precautions (5.8) ]. History of hypersensitivity, including anaphylaxis, to mycophenolate mofetil, mycophenolic acid or any component of the drug product ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Blood Dyscrasias (Neutropenia, Red Blood Cell Aplasia): Monitor with blood tests; consider treatment interruption or dose reduction. ( 5.4 ) Gastrointestinal Complications: Monitor for complications such as bleeding, ulceration and perforations, particularly in patients with underlying gastrointestinal disorders. ( 5.5 ) Hypoxanthine-Guanine Phosphoribosyl-Transferase Deficiency: Avoid use of mycophenolate mofetil.
( 5.6 ) Acute Inflammatory Syndrome Associated with Mycophenolate Products: Monitor for this paradoxical inflammatory reaction. ( 5.7 ) Hypersensitivity Reactions: Discontinue Mycophenolate mofetil; treat and monitor until signs and symptoms resolve. (5.8) Immunizations: Avoid live attenuated vaccines.
(5.9) Blood Donation: Avoid during therapy and for 6 weeks thereafter. (5.12) Semen Donation: Avoid during therapy and for 90 days thereafter. (5.13) Potential Impairment on Driving and Use of Machinery: Mycophenolate mofetil may affect ability to drive or operate machinery.
(5.15)
5.1Embryofetal Toxicity Use of MMF during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of congenital malformations, especially external ear and other facial abnormalities including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney and nervous system. Females of reproductive potential must be made aware of these risks and must be counseled regarding pregnancy prevention and planning. Avoid use of MMF during pregnancy if safer treatment options are available [see Use in Specific Populations (8.1 , 8.3) ].
5.2Lymphoma and Other Malignancies Patients receiving immunosuppressants, including mycophenolate mofetil, are at increased risk of developing lymphomas and other malignancies, particularly of the skin [see Adverse Reactions (6.1) ] . The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. For patients with increased risk for skin cancer, exposure to sunlight and UV light should be limited by wearing protective clothing and using a broad-spectrum sunscreen with a high protection factor.
Post-transplant lymphoproliferative disorder (PTLD) developed in 0.4% to 1% of patients receiving mycophenolate mofetil (2 g or 3 g) with other immunosuppressive agents in controlled clinical trials of kidney, heart and liver transplant patients [see Adverse Reactions (6.1) ] . The majority of PTLD cases appear to be related to Epstein Barr Virus (EBV) infection. The risk of PTLD appears greatest in those individuals who are EBV seronegative, a population which includes many young children.
In pediatric patients, no other malignancies besides PTLD were observed in clinical trials [see Adverse Reactions (6.1) ].
5.3Serious Infections Patients receiving immunosuppressants, including mycophenolate mofetil, are at increased risk of developing bacterial, fungal, protozoal and new or reactivated viral infections, including opportunistic infections. The risk increases with the total immunosuppressive load. These infections may lead to serious outcomes, including hospitalizations and death [see Adverse Reactions (6.1, 6.2) ].
Serious viral infections reported include: Polyomavirus-associated nephropathy (PVAN), especially due to BK virus infection JC virus-associated progressive multifocal leukoencephalopathy (PML), and Cytomegalovirus (CMV) infections: CMV seronegative transplant patients who receive an organ from a CMV seropositive donor are at highest risk of CMV viremia and CMV disease. Viral reactivation in patients infected with Hepatitis B and C COVID-19 Consider dose reduction or discontinuation of mycophenolate mofetil in patients who develop new infections or reactivate viral infections, weighing the risk that reduced immunosuppression represents to the functioning allograft.
PVAN, especially due to BK virus infection, is associated with serious outcomes, including det… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Embryofetal Toxicity [see Warnings and Precautions (5.1) ] Lymphomas and Other Malignancies [see Warnings and Precautions 5.2) ] Serious Infections [see Warnings and Precautions (5.3) ] Blood Dyscrasias: Neutropenia, Pure Red Cell Aplasia [see Warnings and Precautions (5.4) ] Gastrointestinal Complications [see Warnings and Precautions (5.5) ] Acute Inflammatory Syndrome Associated with Mycophenolate Products s [see Warnings and Precautions (5.7) ] Hypersensitivity Reactions [see Warnings and Precautions (5.8) ] The most common adverse reactions in clinical trials (20 % or greater) include diarrhea, leukopenia, infection, vomiting, and there is evidence of a higher frequency of certain types of infections e.g., opportunistic infection.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.com
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. An estimated total of 1557 adult patients received mycophenolate mofetil during pivotal clinical trials in the prevention of acute organ rejection. Of these, 991 were included in the three renal studies, 277 were included in one hepatic study, and 289 were included in one cardiac study.
Patients in all study arms also received cyclosporine and corticosteroids. The data described below primarily derive from five randomized, active-controlled double-blind 12-month trials of mycophenolate mofetil in de novo kidney (3) heart (1) and liver (1) transplant patients [see Clinical Studies (14.1 , 14.2, and 14.3) ] . Mycophenolate Mofetil Oral The incidence of adverse reactions for mycophenolate mofetil was determined in five randomized, comparative, double-blind trials in the prevention of rejection in kidney, heart and liver transplant patients (two active- and one placebo-controlled trials, one active-controlled trial, and one active-controlled trial, respectively) [see Clinical Studies (14.1 , 14.2 and 14.3) ] .
The three de novo kidney studies with 12-month duration compared two dose levels of oral mycophenolate mofetil (1 g twice daily and 1.5 g twice daily) with azathioprine (2 studies) or placebo (1 study) when administered in combination with cyclosporine (Sandimmune ® ) and corticosteroids to prevent acute rejection episodes. One study also included anti-thymocyte globulin (ATGAM ®) induction therapy. In the de novo heart transplantation study with 12-month duration, patients received mycophenolate mofetil 1.5 g twice daily (n=289) or azathioprine 1.5 to 3 mg/kg/day (n=289), in combination with cyclosporine (Sandimmune ® or Neoral ® ) and corticosteroids as maintenance immunosuppressive therapy.
In the de novo liver transplantation study with 12-month duration, patients received mycophenolate mofetil 1 g twice daily intravenously for up to 14 days followed by mycophenolate mofetil 1.5 g twice daily orally or azathioprine 1 to 2 mg/kg/day intravenously followed by azathioprine 1 to 2 mg/kg/day orally, in combination with cyclosporine (Neoral ® ) and corticosteroids as maintenance immunosuppressive therapy. The total number of patients enrolled was 565. Approximately 53% of the kidney transplant patients, 65% of the heart transplant patients, and 48% of the liver transplant patients were treated for more than 1 year.
Adverse reactions reported in ≥ 20% of patients in the mycophenolate mofetil treatment groups are presented below. The safety data of three kidney transplantation studies are pooled together. Table 5 Adverse Reactions in Controlled Studies of De Novo Kidney, Heart or Liver Transplantation Reported in ≥20% of Patients in the Mycophenola… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS See FPI for drugs that may interfere with systemic exposure and reduce mycophenolate mofetil efficacy: antacids with magnesium or aluminum hydroxide, proton pump inhibitors, drugs that interfere with enterohepatic recirculation, telmisartan, calcium-free phosphate binders. ( 7.1 ) Mycophenolate mofetil may reduce effectiveness of oral contraceptives. Use of additional barrier contraceptive methods is recommended.
( 7.2 ) See FPI for other important drug interactions. ( 7 )
7.1Effect of Other Drugs on Mycophenolate Mofetil Table 7 Drug Interactions with Mycophenolate mofetil that Affect Mycophenolic Acid (MPA) Exposure Antacids with Magnesium or Aluminum Hydroxide Clinical Impact Concomitant use with an antacid containing magnesium or aluminum hydroxide decreases MPA systemic exposure [see Clinical Pharmacology (12.3) ] , which may reduce mycophenolate mofetil efficacy. Prevention or Management Administer magnesium or aluminum hydroxide containing antacids at least 2h after mycophenolate mofetil administration.
Proton Pump Inhibitors (PPIs) Clinical Impact Concomitant use with PPIs decreases MPA systemic exposure [see Clinical Pharmacology (12.3) ] , which may reduce mycophenolate mofetil efficacy. Prevention or Management Monitor patients for alterations in efficacy when PPIs are co-administered with mycophenolate mofetil. Examples Lansoprazole, pantoprazole Drugs that Interfere with Enterohepatic Recirculation Clinical Impact Concomitant use with drugs that directly interfere with enterohepatic recirculation, or indirectly interfere with enterohepatic recirculation by altering the gastrointestinal flora, can decrease MPA systemic exposure [see Clinical Pharmacology (12.3) ] , which may reduce mycophenolate mofetil efficacy.
Prevention or Management Monitor patients for alterations in efficacy or mycophenolate mofetil related adverse reactions when these drugs are co-administered with mycophenolate mofetil. Examples Cyclosporine A,trimethoprim/sulfamethoxazole, bile acid sequestrants (cholestyramine), rifampin as well as aminoglycoside, cephalosporin, fluoroquinolone and penicillin classes of antimicrobials Drugs Modulating Glucuronidation Clinical Impact Concomitant use with drugs inducing glucuronidation decreases MPA systemic exposure, potentially reducing mycophenolate mofetil efficacy, while use with drugs inhibiting glucuronidation increases MPA systemic exposure [see Clinical Pharmacology (12.3) ] , which may increase the risk of mycophenolate mofetil related adverse reactions.
Prevention or Management Monitor patients for alterations in efficacy or mycophenolate mofetil related adverse reactions when these drugs are co-administered with mycophenolate mofetil. Examples Telmisartan (induces glucuronidation); isavuconazole (inhibits glucuronidation). Calcium Free Phosphate Binders Clinical Impact Concomitant use with calcium free phosphate binders decrease MPA systemic exposure [see Clinical Pharmacology (12.3) ] , which may reduce mycophenolate mofetil efficacy.
Prevention or Management Administer calcium free phosphate binders at least 2 hours after mycophenolate mofetil. Examples Sevelamer
7.2Effect of Mycophenolate Mofetil on Other Drugs Table 8 Drug Interactions with Mycophenolate mofetil that Affect Other Drugs Drugs that Undergo Renal Tubular Secretion Clinical Impact When concomitantly used with mycophenolate mofetil, its metabolite MPAG, may compete with drugs eliminated by renal tubular secretion which may increase plasma concentrations and/or adverse reactions associated with these drugs. Prevention or Management Monitor for drug-related adverse reactions in patients with renal impairment. Examples Acyclovir, ganciclovir, probenecid, valacyclovir, valganciclovir Combination Oral Contraceptives Clinical Impact Concomitant use with mycophenolate mofetil decreased the systemic exposure to levonorgestrel, but did not affect the systemic exposure to ethinylestradiol [see Clinical Pharmacology (… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Male Patients: Sexually active male patients and/or their female partners are recommended to use effective contraception during treatment of the male patient and for at least 90 days after cessation of treatment ( 8.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mycophenolate during pregnancy and those becoming pregnant within 6 weeks of discontinuing mycophenolate mofetil treatment. To report a pregnancy or obtain information about the registry, visit www.mycophenolateREMS.com or call 1-800-617-8191. Risk Summary Use of mycophenolate mofetil (MMF) during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of multiple congenital malformations in multiple organ systems [see Human Data ].
Oral administration of mycophenolate to rats and rabbits during the period of organogenesis produced congenital malformations and pregnancy loss at doses less than the recommended clinical dose (0.01 to 0.05 times the recommended clinical doses in kidney and heart transplant patients) [see Animal Data ] . Consider alternative immunosuppressants with less potential for embryofetal toxicity. Risks and benefits of mycophenolate mofetil should be discussed with the pregnant woman.
The estimated background risk of pregnancy loss and congenital malformations in organ transplant populations is not clear. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data A spectrum of congenital malformations (including multiple malformations in individual newborns) has been reported in 23 to 27% of live births in MMF exposed pregnancies, based on published data from pregnancy registries.
Malformations that have been documented include external ear, eye, and other facial abnormalities including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system. Based on published data from pregnancy registries, the risk of first trimester pregnancy loss has been reported at 45 to 49% following MMF exposure. Animal Data In animal reproductive toxicology studies, there were increased rates of fetal resorptions and malformations in the absence of maternal toxicity.
Oral administration of MMF to pregnant rats from Gestational Day 7 to Day 16 produced increased embryofetal lethality and fetal malformations including anophthalmia, agnathia, and hydrocephaly at doses equivalent to 0.015 and 0.01 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA. Oral administration of MMF to pregnant rabbits from Gestational Day 7 to Day 19 produced increased embryofetal lethality and fetal malformations included ectopia cordis, ectopic kidneys, diaphragmatic hernia, and umbilical hernia at dose equivalents as low as 0.05 and 0.03 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA.
8.2Lactation Risk Summary There are no data on the presence of mycophenolate in human milk, or the effects on milk production. There are limited data in the National Transplantation Pregnancy Registry on the effects of mycophenolate on a breastfed child [see Data ] . Studies in rats treated with MMF have shown mycophenolic acid (MPA) to be present in milk.
Because available data are limited, it is not possible to exclude potential risks to a breastfeeding infant. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for mycophenolate mofetil and any potential adverse effects on the breastfed infant from mycophenolate mofetil or from the underlying maternal condition. Data Limited information is available from the National Transplantation Pregnancy Registry.
Of seven infants reported by… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mycophenolate during pregnancy and those becoming pregnant within 6 weeks of discontinuing mycophenolate mofetil treatment. To report a pregnancy or obtain information about the registry, visit www.mycophenolateREMS.com or call 1-800-617-8191. Risk Summary Use of mycophenolate mofetil (MMF) during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of multiple congenital malformations in multiple organ systems [see Human Data ].
Oral administration of mycophenolate to rats and rabbits during the period of organogenesis produced congenital malformations and pregnancy loss at doses less than the recommended clinical dose (0.01 to 0.05 times the recommended clinical doses in kidney and heart transplant patients) [see Animal Data ] . Consider alternative immunosuppressants with less potential for embryofetal toxicity. Risks and benefits of mycophenolate mofetil should be discussed with the pregnant woman.
The estimated background risk of pregnancy loss and congenital malformations in organ transplant populations is not clear. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data A spectrum of congenital malformations (including multiple malformations in individual newborns) has been reported in 23 to 27% of live births in MMF exposed pregnancies, based on published data from pregnancy registries.
Malformations that have been documented include external ear, eye, and other facial abnormalities including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system. Based on published data from pregnancy registries, the risk of first trimester pregnancy loss has been reported at 45 to 49% following MMF exposure. Animal Data In animal reproductive toxicology studies, there were increased rates of fetal resorptions and malformations in the absence of maternal toxicity.
Oral administration of MMF to pregnant rats from Gestational Day 7 to Day 16 produced increased embryofetal lethality and fetal malformations including anophthalmia, agnathia, and hydrocephaly at doses equivalent to 0.015 and 0.01 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA. Oral administration of MMF to pregnant rabbits from Gestational Day 7 to Day 19 produced increased embryofetal lethality and fetal malformations included ectopia cordis, ectopic kidneys, diaphragmatic hernia, and umbilical hernia at dose equivalents as low as 0.05 and 0.03 times the recommended human doses for renal and cardiac transplant patients, respectively, when corrected for BSA.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have been established in pediatric patients 3 months and older for the prophylaxis of organ rejection of allogenic kidney, heart or liver transplants. Kidney Transplant Use of mycophenolate mofetil in this population is supported by evidence from adequate and well-controlled studies of mycophenolate mofetil in adults with additional data from one open-label, pharmacokinetic and safety study of mycophenolate mofetil in pediatric patients after receiving allogeneic kidney transplant (100 patients, 3 months to 18 years of age) [see Dosage and Administration (2.2) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.1) ].
Heart Transplant and Liver Transplant Use of mycophenolate mofetil in pediatric heart transplant and liver transplant patients is supported by adequate and well controlled studies and pharmacokinetic data in adult heart transplant and liver transplant patients. Additional supportive data include pharmacokinetic data in pediatric kidney transplant and pediatric liver transplant patients (8 liver transplant patients, 9 months to 5 years of age, in an open-label, pharmacokinetic and safety study) and published evidence of clinical efficacy and safety in pediatric heart transplant and pediatric liver transplant patients [see Dosage and Administration (2.3,2.4) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.1) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of mycophenolate mofetil did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between geriatric and younger patients. In general, dose selection for a geriatric patient should take into consideration the presence of decreased hepatic, renal or cardiac function and of concomitant drug therapies [see Adverse Reactions (6.1) , Drug Interactions (7) ].
🆘 Overdosage ▾
10 OVERDOSAGE Possible signs and symptoms of acute overdose include hematological abnormalities such as leukopenia and neutropenia, and gastrointestinal symptoms such as abdominal pain, diarrhea, nausea, vomiting, and dyspepsia. The experience with overdose of mycophenolate mofetil in humans is limited. The reported effects associated with overdose fall within the known safety profile of the drug.
The highest dose administered to kidney transplant patients in clinical trials has been 4 g/day. In limited experience with heart and liver transplant patients in clinical trials, the highest doses used were 4 g/day or 5 g/day. At doses of 4 g/day or 5 g/day, there appears to be a higher rate, compared to the use of 3 g/day or less, of gastrointestinal intolerance (nausea, vomiting, and/or diarrhea), and occasional hematologic abnormalities, particularly neutropenia [see Warnings and Precautions (5.4) ] .
Treatment and Management MPA and the phenolic glucuronide metabolite of MPA (MPAG) are usually not removed by hemodialysis. However, at high MPAG plasma concentrations (>100 µg/mL), small amounts of MPAG are removed. By increasing excretion of the drug, MPA can be removed by bile acid sequestrants, such as cholestyramine [see Clinical Pharmacology (12.3) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Mycophenolate mofetil (MMF) is absorbed following oral administration and hydrolyzed to mycophenolic acid (MPA), the active metabolite. MPA is a selective uncompetitive inhibitor of the two isoforms (type I and type II) of inosine monophosphate dehydrogenase (IMPDH) leading to inhibition of the de novo pathway of guanosine nucleotide synthesis and blocks DNA synthesis. The mechanism of action of MPA is multifaceted and includes effects on cellular checkpoints responsible for metabolic programming of lymphocytes.
MPA shifts transcriptional activities in lymphocytes from a proliferative state to catabolic processes. In vitro studies suggest that MPA modulates transcriptional activities in human CD4+ T-lymphocytes by suppressing the Akt/mTOR and STAT5 pathways that are relevant to metabolism and survival, leading to an anergic state of T-cells whereby the cells become less responsive to antigenic stimulation. Additionally, MPA enhanced the expression of negative co-stimulators such as CD70, PD-1, CTLA-4, and transcription factor FoxP3 as well as decreased the expression of positive co-stimulators CD27 and CD28.
MPA decreases proliferative responses of T- and B-lymphocytes to both mitogenic and allo-antigenic stimulation, antibody responses, as well as the production of cytokines from lymphocytes and monocytes such as GM-CSF, IFN-ɣ, IL-17, and TNF-α. Additionally, MPA prevents the glycosylation of lymphocyte and monocyte glycoproteins that are involved in intercellular adhesion to endothelial cells and may inhibit recruitment of leukocytes into sites of inflammation and graft rejection. Overall, the effect of MPA is cytostatic and reversible.
12.2Pharmacodynamics There is a lack of information regarding the pharmacodynamic effects of MMF.
12.3Pharmacokinetics Absorption Following oral and intravenous administration, MMF undergoes complete conversion to MPA, the active metabolite. In 12 healthy volunteers, the mean absolute bioavailability of oral MMF relative to intravenous MMF was 94%. Two 500 mg mycophenolate mofetil tablets have been shown to be bioequivalent to four 250 mg mycophenolate mofetil capsules.
Five mL of the 200 mg/mL constituted mycophenolate mofetil oral suspension have been shown to be bioequivalent to four 250 mg capsules. The mean (± SD) pharmacokinetic parameters estimates for MPA following the administration of MMF given as single doses to healthy volunteers, and multiple doses to kidney, heart, and liver transplant patients, are shown in Table 10 . The area under the plasma-concentration time curve (AUC) for MPA appears to increase in a dose-proportional fashion in kidney transplant patients receiving multiple oral doses of MMF up to a daily dose of 3 g (1.5 g twice daily) (see Table 10 ).
Table 10 Pharmacokinetic Parameters for MPA [mean (±SD)] Following Administration of MMF to Healthy Volunteers (Single Dose), and Kidney, Heart, and Liver Transplant Patients (Multiple Doses) Healthy Volunteers Dose/Route T max (h) C max (mcg/mL) Total AUC (mcg∙h/mL) Single dose 1 g/oral 0.80 (±0.36) (n=129) 24.5 (±9.5) (n=129) 63.9 (±16.2) (n=117) Kidney Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route T max (h) C max (mcg/mL) Interdosing Interval AUC (0 to 12h) (mcg∙h/mL) 5 days 1 g/iv 1.58 (±0.46) (n=31) 12.0 (±3.82) (n=31) 40.8 (±11.4) (n=31) 6 days 1 g/oral 1.33 (±1.05) (n=31) 10.7 (±4.83) (n=31) 32.9 (±15.0) (n=31) Early (Less than 40 days) 1 g/oral 1.31 (±0.76) (n=25) 8.16 (±4.50) (n=25) 27.3 (±10.9) (n=25) Early (Less than 40 days) 1.5 g/oral 1.21 (±0.81) (n=27) 13.5 (±8.18) (n=27) 38.4 (±15.4) (n=27) Late (Greater than 3 months) 1.5 g/oral 0.90 (±0.24) (n=23) 24.1 (±12.1) (n=23) 65.3 (±35.4) (n=23) Heart transplant Patients (twice daily dosing) Time After Transplantation Dose/Route T max (h) C max (mcg/mL) Interdosing Interval AUC (0 to 12h) (mcg∙h/mL) Early (Day before discharge) 1.5 g/oral 1.8 (±1.3) (n=11) 11.5 (±6.8) (n=11) 43.3… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Mycophenolate mofetil (MMF) is absorbed following oral administration and hydrolyzed to mycophenolic acid (MPA), the active metabolite. MPA is a selective uncompetitive inhibitor of the two isoforms (type I and type II) of inosine monophosphate dehydrogenase (IMPDH) leading to inhibition of the de novo pathway of guanosine nucleotide synthesis and blocks DNA synthesis. The mechanism of action of MPA is multifaceted and includes effects on cellular checkpoints responsible for metabolic programming of lymphocytes.
MPA shifts transcriptional activities in lymphocytes from a proliferative state to catabolic processes. In vitro studies suggest that MPA modulates transcriptional activities in human CD4+ T-lymphocytes by suppressing the Akt/mTOR and STAT5 pathways that are relevant to metabolism and survival, leading to an anergic state of T-cells whereby the cells become less responsive to antigenic stimulation. Additionally, MPA enhanced the expression of negative co-stimulators such as CD70, PD-1, CTLA-4, and transcription factor FoxP3 as well as decreased the expression of positive co-stimulators CD27 and CD28.
MPA decreases proliferative responses of T- and B-lymphocytes to both mitogenic and allo-antigenic stimulation, antibody responses, as well as the production of cytokines from lymphocytes and monocytes such as GM-CSF, IFN-ɣ, IL-17, and TNF-α. Additionally, MPA prevents the glycosylation of lymphocyte and monocyte glycoproteins that are involved in intercellular adhesion to endothelial cells and may inhibit recruitment of leukocytes into sites of inflammation and graft rejection. Overall, the effect of MPA is cytostatic and reversible.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1Handling and Disposal Mycophenolate mofetil (MMF) has demonstrated teratogenic effects in humans [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] . Mycophenolate mofetil tablets should not be crushed and mycophenolate mofetil capsules should not be opened or crushed. Wearing disposable gloves is recommended during reconstitution and when wiping the outer surface of the bottle/cap and the table after reconstitution.
Avoid inhalation or direct contact with skin or mucous membranes of the powder contained in mycophenolate mofetil capsules. Follow applicable special handling and disposal procedures 1 .
16.2Mycophenolate Mofetil Capsules USP 250 mg Mycophenolate Mofetil Capsules, USP are available containing 250 mg of mycophenolate mofetil, USP. The 250 mg capsules are light blue/ peach, size ‘1’ hard gelatin capsules, printed in black with ‘GC1’ on body containing white to off white powder. NDC Number Size 16729-094-01 Bottle of 100’s count with a child-resistant closure 16729-094-29 Bottle of 120’s count with a child-resistant closure 16729-094-16 Bottle of 500’s count Storage Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F).
16.3Mycophenolate Mofetil Tablets USP 500 mg Mycophenolate Mofetil Tablets, USP are available containing 500 mg of mycophenolate mofetil, USP. The 500 mg tablets are purple coloured, capsule shaped, biconvex, film coated tablets debossed ‘AHI’ on one side and ‘500’ on other side. NDC Number Size 16729-019-01 Bottle of 100’s count with a child-resistant closure 16729-019-16 Bottle of 500’s count Storage and Dispensing Information Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F).
Dispense in light-resistant containers, such as the manufacturer's original containers.
📦 Storage and Handling ▾
16.1Handling and Disposal Mycophenolate mofetil (MMF) has demonstrated teratogenic effects in humans [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] . Mycophenolate mofetil tablets should not be crushed and mycophenolate mofetil capsules should not be opened or crushed. Wearing disposable gloves is recommended during reconstitution and when wiping the outer surface of the bottle/cap and the table after reconstitution.
Avoid inhalation or direct contact with skin or mucous membranes of the powder contained in mycophenolate mofetil capsules. Follow applicable special handling and disposal procedures 1 .
📋 Description ▾
11 DESCRIPTION Mycophenolate mofetil is an antimetabolite immunosuppressant. It is the 2-morpholinoethyl ester of mycophenolic acid (MPA), an immunosuppressive agent; inosine monophosphate dehydrogenase (IMPDH) inhibitor. The chemical name for mycophenolate mofetil (MMF) is 2-morpholinoethyl (E)-6-(1, 3-dihydro-4-hydroxy-6-methoxy-7-methyl-3-oxo-5-isobenzofuranyl)-4-methyl-4-hexenoate.
It has an empirical formula of C 23 H 31 NO 7 , a molecular weight of 433.50, and the following structural formula: MMF is a white to off-white crystalline powder. It is slightly soluble in water (43 µg/mL at pH 7.4); the solubility increases in acidic medium (4.27 mg/mL at pH 3.6). It is freely soluble in acetone, soluble in methanol, and sparingly soluble in ethanol.
The apparent partition coefficient in 1-octanol/water (pH 7.4) buffer solution is 238. The pKa values for MMF are 5.6 for the morpholino group and 8.5 for the phenolic group. MMF hydrochloride has a solubility of 65.8 mg/mL in 5% Dextrose Injection USP (D5W).
The pH of the reconstituted solution is 2.4 to 4.1. Mycophenolate mofetil is available for oral administration as capsules containing 250 mg of MMF, tablets containing 500 mg of MMF. Inactive ingredients in mycophenolate mofetil 250 mg capsules include croscarmellose sodium, magnesium stearate, povidone (K-90) microcrystalline cellulose, hydroxy propyl cellulose and talc.
The capsule shells contain FD&C blue #2, gelatin, red iron oxide, sodium lauryl sulfate, titanium dioxide, and yellow iron oxide. The imprinting ink contains shellac, iron oxide black and potassium hydroxide. Inactive ingredients in mycophenolate mofetil 500 mg tablets include iron oxide black, croscarmellose sodium, FD&C blue #2 aluminum Lake, hydroxypropyl cellulose, hypromellose, magnesium stearate, microcrystalline cellulose, polyethylene glycol 400, povidone (K-90), iron oxide red, talc, and titanium dioxide.
Mycophenolate Mofetil Tablets meets USP Dissolution Test 3 and Mycophenolate Mofetil Capsules meets USP Dissolution Test 2. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide and Instructions for Use ).
17.1Embryofetal Toxicity Pregnancy loss and malformations Inform females of reproductive potential and pregnant women that use of mycophenolate mofetil during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of congenital malformations. Advise that they must use an acceptable form of contraception [see Warnings and Precautions (5.1) , Use in Specific Populations (8.1 , 8.3) ] . Encourage pregnant women to enroll in the Pregnancy Exposure Registry.
This registry monitors pregnancy outcomes in women exposed to mycophenolate [see Use in Specific Populations (8.1) ]. Contraception Discuss pregnancy testing, pregnancy prevention and planning with females of reproductive potential [see Use in Specific Populations (8.3) ]. Females of reproductive potential must use an acceptable form of birth control during the entire mycophenolate mofetil therapy and for 6 weeks after stopping mycophenolate mofetil, unless the patient chooses abstinence.
Mycophenolate mofetil may reduce effectiveness of oral contraceptives. Use of additional barrier contraceptive methods is recommended [see Use in Specific Populations (8.3) ]. For patients who are considering pregnancy, discuss appropriate alternative immunosuppressants with less potential for embryofetal toxicity.
Risks and benefits of mycophenolate mofetil should be discussed with the patient. Advise sexually active male patients and/or their partners to use effective contraception during the treatment of the male patient and for at least 90 days after cessation of treatment. This recommendation is based on findings of animal studies [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] .
17.2Development of Lymphoma and Other Malignancies Inform patients that they are at increased risk of developing lymphomas and other malignancies, particularly of the skin, due to immunosuppression [see Warnings and Precautions (5.2) ] . Advise patients to limit exposure to sunlight and ultraviolet (UV) light by wearing protective clothing and use of broad-spectrum sunscreen with high protection factor.
17.3Increased Risk of Serious Infections Inform patients that they are at increased risk of developing a variety of infections due to immunosuppression. Instruct them to contact their physician if they develop any of the signs and symptoms of infection explained in the Medication Guide. [see Warnings and Precautions (5.3) ] .
17.4Blood Dyscrasias Inform patients that they are at increased risk for developing blood adverse effects such as anemia or low white blood cells. Advise patients to immediately contact their healthcare provider if they experience any evidence of infection, unexpected bruising, or bleeding, or any other manifestation of bone marrow suppression [see Warnings and Precautions (5.4) ] .
17.5Gastrointestinal Tract Complications Inform patients that mycophenolate mofetil can cause gastrointestinal tract complications including bleeding, intestinal perforations, and gastric or duodenal ulcers. Advise the patient to contact their healthcare provider if they have symptoms of gastrointestinal bleeding, or sudden onset or persistent abdominal pain [see Warnings and Precautions (5.5) ] .
17.6Acute Inflammatory Syndrome Inform patients that acute inflammatory reactions have been reported in some patients who received mycophenolate mofetil. Some reactions were severe, requiring hospitalization. Advise patients to contact their physician if they develop fever, joint stiffness, joint pain or muscle pains [see Warnings and Precautions (5.7) ] .
17.7Hypersensitivity Reactions Inform patients of the potential risk of hypersensitivity reactions. Advise patients to stop taking mycophenolate mofetil and seek immediate medical attention if signs or symptoms of hypersensitivity reaction occur (such… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
Dispense with Medication Guide available at www.accordhealthcare.us/medication-guides MEDICATION GUIDE Mycophenolate Mofetil Capsules 250 mg Mycophenolate Mofetil Tablets 500 mg (MYE koe FEN oh late MOE fe til) Read the Medication Guide that comes with mycophenolate mofetil capsules and tablets before you start taking it and each time you refill your prescription. There may be new information. This Medication Guide does not take the place of talking with your doctor about your medical condition or treatment.
What is the most important information I should know about mycophenolate mofetil capsules and tablets? Mycophenolate mofetil capsules and tablets can cause serious side effects, including: Increased risk of loss of a pregnancy (miscarriage) and higher risk of birth defects. Females who take mycophenolate mofetil during pregnancy have a higher risk of miscarriage during the first 3 months (first trimester), and a higher risk that their baby will be born with birth defects.
If you are a female who can become pregnant , your doctor must talk with you about acceptable birth control methods (contraceptive counseling) to use while taking mycophenolate mofetil. You should have 1 pregnancy test immediately before starting mycophenolate mofetil capsules and tablets and another pregnancy test 8 to 10 days later. Pregnancy tests should be repeated during routine follow-up visits with your doctor.
Talk to your doctor about the results of all of your pregnancy tests. You must use acceptable birth control during your entire mycophenolate mofetil treatment and for 6 weeks after stopping mycophenolate mofetil capsules and tablets, unless at any time you choose to avoid sexual intercourse (abstinence) with a man completely. Mycophenolate mofetil decreases blood levels of the hormones in birth control pills that you take by mouth.
Birth control pills may not work as well while you take mycophenolate mofetil, and you could become pregnant. If you take birth control pills while using mycophenolate mofetil you must also use another form of birth control. Talk to your doctor about other birth control methods that you can use while taking mycophenolate mofetil capsules and tablets.
If you are a sexually active male whose female partner can become pregnant while you are taking mycophenolate mofetil capsules and tablets, use effective contraception during treatment and for at least 90 days after stopping mycophenolate mofetil capsules and tablets. If you plan to become pregnant , talk with your doctor. Your doctor will decide if other medicines to prevent rejection may be right for you.
If you become pregnant while taking mycophenolate mofetil capsules and tablets, do not stop taking mycophenolate mofetil capsules and tablets. Call your doctor right away. You and your doctor may decide that other medicines to prevent rejection may be right for you.
You and your doctor should report your pregnancy to the Mycophenolate Pregnancy Registry either: By phone at 1-800-617-8191 or By visiting the REMS website at www.mycophenolateREMS.com The purpose of this registry is to gather information about the health of you and your baby. Increased risk of getting certain cancers. People who take mycophenolate mofetil capsules and tablets have a higher risk of getting lymphoma, and other cancers, especially skin cancer.
Tell your doctor if you have: unexplained fever, prolonged tiredness, weight loss or lymph node swelling a brown or black skin lesion with uneven borders, or one part of the lesion does not look like the other a change in the size and color of a mole a new skin lesion or bump any other changes to your health Increased risk of getting certain cancers. People who take mycophenolate mofetil capsules and tablets have a higher risk of getting lymphoma, and other cancers, especially skin cancer. Tell your doctor if you have: unexplained fever, prolonged tiredness, weight loss or lymph node swelling a brown or black skin lesion with uneven borders, or one… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following oral and intravenous administration, MMF undergoes complete conversion to MPA, the active metabolite. In 12 healthy volunteers, the mean absolute bioavailability of oral MMF relative to intravenous MMF was 94%. Two 500 mg mycophenolate mofetil tablets have been shown to be bioequivalent to four 250 mg mycophenolate mofetil capsules.
Five mL of the 200 mg/mL constituted mycophenolate mofetil oral suspension have been shown to be bioequivalent to four 250 mg capsules. The mean (± SD) pharmacokinetic parameters estimates for MPA following the administration of MMF given as single doses to healthy volunteers, and multiple doses to kidney, heart, and liver transplant patients, are shown in Table 10 . The area under the plasma-concentration time curve (AUC) for MPA appears to increase in a dose-proportional fashion in kidney transplant patients receiving multiple oral doses of MMF up to a daily dose of 3 g (1.5 g twice daily) (see Table 10 ).
Table 10 Pharmacokinetic Parameters for MPA [mean (±SD)] Following Administration of MMF to Healthy Volunteers (Single Dose), and Kidney, Heart, and Liver Transplant Patients (Multiple Doses) Healthy Volunteers Dose/Route T max (h) C max (mcg/mL) Total AUC (mcg∙h/mL) Single dose 1 g/oral 0.80 (±0.36) (n=129) 24.5 (±9.5) (n=129) 63.9 (±16.2) (n=117) Kidney Transplant Patients (twice daily dosing) Time After Transplantation Dose/Route T max (h) C max (mcg/mL) Interdosing Interval AUC (0 to 12h) (mcg∙h/mL) 5 days 1 g/iv 1.58 (±0.46) (n=31) 12.0 (±3.82) (n=31) 40.8 (±11.4) (n=31) 6 days 1 g/oral 1.33 (±1.05) (n=31) 10.7 (±4.83) (n=31) 32.9 (±15.0) (n=31) Early (Less than 40 days) 1 g/oral 1.31 (±0.76) (n=25) 8.16 (±4.50) (n=25) 27.3 (±10.9) (n=25) Early (Less than 40 days) 1.5 g/oral 1.21 (±0.81) (n=27) 13.5 (±8.18) (n=27) 38.4 (±15.4) (n=27) Late (Greater than 3 months) 1.5 g/oral 0.90 (±0.24) (n=23) 24.1 (±12.1) (n=23) 65.3 (±35.4) (n=23) Heart transplant Patients (twice daily dosing) Time After Transplantation Dose/Route T max (h) C max (mcg/mL) Interdosing Interval AUC (0 to 12h) (mcg∙h/mL) Early (Day before discharge) 1.5 g/oral 1.8 (±1.3) (n=11) 11.5 (±6.8) (n=11) 43.3 (±20.8) (n=9) Late (Greater than 6 months) 1.5 g/oral 1.1 (±0.7) (n=52) 20.0 (±9.4) (n=52)
54.1AUC (0 to 12h) values quoted are extrapolated from data from samples collected over 4 hours. (±20.4) (n=49) Liver transplant Patients (twice daily dosing) Time After Transplantation Dose/Route T max (h) C max (mcg/mL) Interdosing Interval AUC(0 to 12h) (mcg∙h/mL) 4 to 9 days 1 g/iv 1.50 (±0.517) (n=22) 17.0 (±12.7) (n=22) 34.0 (±17.4) (n=22) Early (5 to 8 days) 1.5 g/oral 1.15 (±0.432) (n=20) 13.1 (±6.76) (n=20) 29.2 (±11.9) (n=20) Late (Greater than 6 months) 1.5 g/oral 1.54 (±0.51) (n=6) 19.3 (±11.7) (n=6) 49.3 (±14.8) (n=6) In the early post-transplant period (less than 40 days post-transplant), kidney, heart, and liver transplant patients had mean MPA AUCs approximately 20% to 41% lower and mean C max approximately 32% to 44% lower compared to the late transplant period (i.e., 3 to 6 months post-transplant) (non-stationarity in MPA pharmacokinetics).
Mean MPA AUC values following administration of 1 g twice daily intravenous mycophenolate mofetil over 2 hours to kidney transplant patients for 5 days were about 24% higher than those observed after oral administration of a similar dose in the immediate post-transplant phase. In liver transplant patients, administration of 1 g twice daily intravenous mycophenolate mofetil followed by 1.5 g twice daily oral mycophenolate mofetil resulted in mean MPA AUC estimates similar to those found in kidney transplant patients administered 1 g mycophenolate mofetil twice daily.
Effect of Food Food (27 g fat, 650 calories) had no effect on the extent of absorption (MPA AUC) of MMF when administered at doses of 1.5 g twice daily to kidney transplant patients. However, MPA C max was decreased by 40% in the presence of food [see Dosage and Administration (2… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics There is a lack of information regarding the pharmacodynamic effects of MMF.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Kidney Transplantation Adults The three de novo kidney transplantation studies compared two dose levels of oral mycophenolate mofetil (1 g twice daily and 1.5 g twice daily) with azathioprine (2 studies) or placebo (1 study) to prevent acute rejection episodes. One of the two studies with azathioprine (AZA) control arm also included anti-thymocyte globulin (ATGAM ® ) induction therapy. The geographic location of the investigational sites of these studies are included in Table 13 .
In all three de novo kidney transplantation studies, the primary efficacy endpoint was the proportion of patients in each treatment group who experienced treatment failure within the first 6 months after transplantation. Treatment failure was defined as biopsy-proven acute rejection on treatment or the occurrence of death, graft loss or early termination from the study for any reason without prior biopsy-proven rejection. Mycophenolate mofetil, in combination with corticosteroids and cyclosporine, reduced (statistically significant at 0.05 level) the incidence of treatment failure within the first 6 months following transplantation ( Table 13 ).
Patients who prematurely discontinued treatment were followed for the occurrence of death or graft loss, and the cumulative incidence of graft loss and patient death combined are summarized in Table 14 . Patients who prematurely discontinued treatment were not followed for the occurrence of acute rejection after termination. Table 13 Treatment Failure in De Novo Kidney Transplantation Studies *Does not include death and graft loss as reason for early termination.
USA Study Mycophenolate mofetil 2 g/day Mycophenolate mofetil 3 g/day AZA 1 to 2 mg/kg/day (N=499 patients) (n=167 patients) (n=166 patients) (n=166 patients) All 3 groups received anti-thymocyte globulin induction, cyclosporine and corticosteroids All treatment failures 31.1% 31.3% 47.6% Early termination without prior acute rejection 9.6% 12.7% 6.0% Biopsy-proven rejection episode on treatment 19.8% 17.5% 38.0% Europe/Canada/Australia Study Mycophenolate mofetil 2 g/day Mycophenolate mofetil 3 g/day AZA 100 to 150 mg/day (N=503 patients) (n=173 patients) (n=164 patients) (n=166 patients) No induction treatment administered; all 3 groups received cyclosporine and corticosteroids All treatment failures 38.2% 34.8% 50.0% Early termination without prior acute rejection 13.9% 15.2% 10.2% Biopsy-proven rejection episode on treatment 19.7% 15.9% 35.5% Europe Study Mycophenolate mofetil 2 g/day Mycophenolate mofetil 3 g/day Placebo (N=491 patients) (n=165 patients) (n=160 patients) (n=166 patients) No induction treatment administered; all 3 groups received cyclosporine and corticosteroids.
All treatment failures 30.3% 38.8% 56.0% Early termination without prior acute rejection 11.5% 22.5% 7.2% Biopsy-proven rejection episode on treatment 17.0% 13.8% 46.4% No advantage of mycophenolate mofetil at 12 months with respect to graft loss or patient death (combined) was established ( Table 14 ). Numerically, patients receiving mycophenolate mofetil 2 g/day and 3 g/day experienced a better outcome than controls in all three studies; patients receiving mycophenolate mofetil 2 g/day experienced a better outcome than mycophenolate mofetil 3 g/day in two of the three studies.
Patients in all treatment groups who terminated treatment early were found to have a poor outcome with respect to graft loss or patient death at 1 year. Table 14 De Novo Kidney Transplantation Studies Cumulative Incidence of Combined Graft Loss or Patient Death at 12 Months Study Mycophenolate mofetil 2 g/day Mycophenolate mofetil 3 g/day Control (AZA or Placebo) USA 8.5% 11.5% 12.2% Europe/Canada/Australia 11.7% 11.0% 13.6% Europe 8.5% 10.0% 11.5% Pediatrics-De Novo Kidney transplantation PK Study with Long Term Follow-Up One open-label, safety and pharmacokinetic study of mycophenolate mofetil oral suspension 600 mg/m 2 twice daily (up to 1 g twice daily) in combination… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 104-week oral carcinogenicity study in mice, MMF in daily doses up to 180 mg/kg was not tumorigenic. The highest dose tested was 0.2 times the recommended clinical dose (2 g/day) in renal transplant patients and 0.15 times the recommended clinical dose (3 g/day) in cardiac transplant patients when corrected for differences in body surface area (BSA). In a 104-week oral carcinogenicity study in rats, MMF in daily doses up to 15 mg/kg was not tumorigenic.
The highest dose was 0.035 times the recommended clinical dose in kidney transplant patients and 0.025 times the recommended clinical dose in heart transplant patients when corrected for BSA. While these animal doses were lower than those given to patients, they were maximal in those species and were considered adequate to evaluate the potential for human risk [see Warnings and Precautions (5.2) ] . The genotoxic potential of MMF was determined in five assays.
MMF was genotoxic in the mouse lymphoma/thymidine kinase assay and the in vivo mouse micronucleus assay. MMF was not genotoxic in the bacterial mutation assay, the yeast mitotic gene conversion assay or the Chinese hamster ovary cell chromosomal aberration assay. MMF had no effect on fertility of male rats at oral doses up to 20 mg/kg/day.
This dose represents 0.05 times the recommended clinical dose in renal transplant patients and 0.03 times the recommended clinical dose in cardiac transplant patients when corrected for BSA. In a female fertility and reproduction study conducted in rats, oral doses of 4.5 mg/kg/day caused malformations (principally of the head and eyes) in the first generation offspring in the absence of maternal toxicity. This dose was 0.01 times the recommended clinical dose in renal transplant patients and 0.005 times the recommended clinical dose in cardiac transplant patients when corrected for BSA.
No effects on fertility or reproductive parameters were evident in the dams or in the subsequent generation.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 104-week oral carcinogenicity study in mice, MMF in daily doses up to 180 mg/kg was not tumorigenic. The highest dose tested was 0.2 times the recommended clinical dose (2 g/day) in renal transplant patients and 0.15 times the recommended clinical dose (3 g/day) in cardiac transplant patients when corrected for differences in body surface area (BSA). In a 104-week oral carcinogenicity study in rats, MMF in daily doses up to 15 mg/kg was not tumorigenic.
The highest dose was 0.035 times the recommended clinical dose in kidney transplant patients and 0.025 times the recommended clinical dose in heart transplant patients when corrected for BSA. While these animal doses were lower than those given to patients, they were maximal in those species and were considered adequate to evaluate the potential for human risk [see Warnings and Precautions (5.2) ] . The genotoxic potential of MMF was determined in five assays.
MMF was genotoxic in the mouse lymphoma/thymidine kinase assay and the in vivo mouse micronucleus assay. MMF was not genotoxic in the bacterial mutation assay, the yeast mitotic gene conversion assay or the Chinese hamster ovary cell chromosomal aberration assay. MMF had no effect on fertility of male rats at oral doses up to 20 mg/kg/day.
This dose represents 0.05 times the recommended clinical dose in renal transplant patients and 0.03 times the recommended clinical dose in cardiac transplant patients when corrected for BSA. In a female fertility and reproduction study conducted in rats, oral doses of 4.5 mg/kg/day caused malformations (principally of the head and eyes) in the first generation offspring in the absence of maternal toxicity. This dose was 0.01 times the recommended clinical dose in renal transplant patients and 0.005 times the recommended clinical dose in cardiac transplant patients when corrected for BSA.
No effects on fertility or reproductive parameters were evident in the dams or in the subsequent generation.
📚 References ▾
15 REFERENCES 1. "OSHA Hazardous Drugs." OSHA. http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Recent Major Changes ▾
Warnings and Precautions, Serious Infections (5.8) 05/2025
📄 Package Label / Principal Display Panel ▾
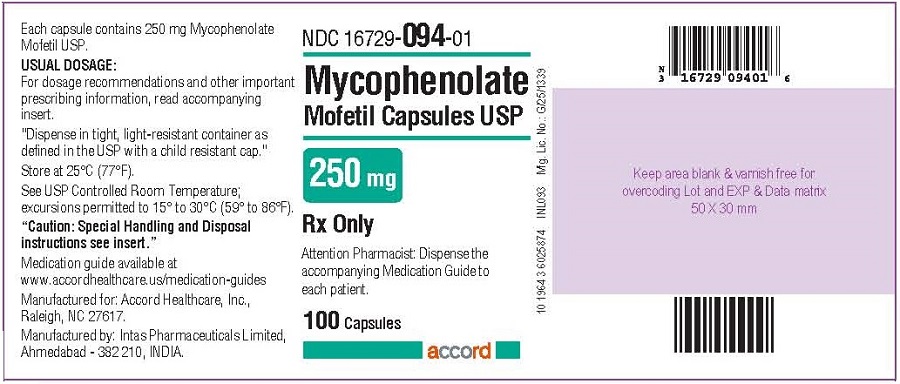
PRINCIPAL DISPLAY PANEL 250 mg : 100 Capsules Label 500 mg : 100 Tablet Label 250 mg : 100 capsules 500 mg : 100 tablets