
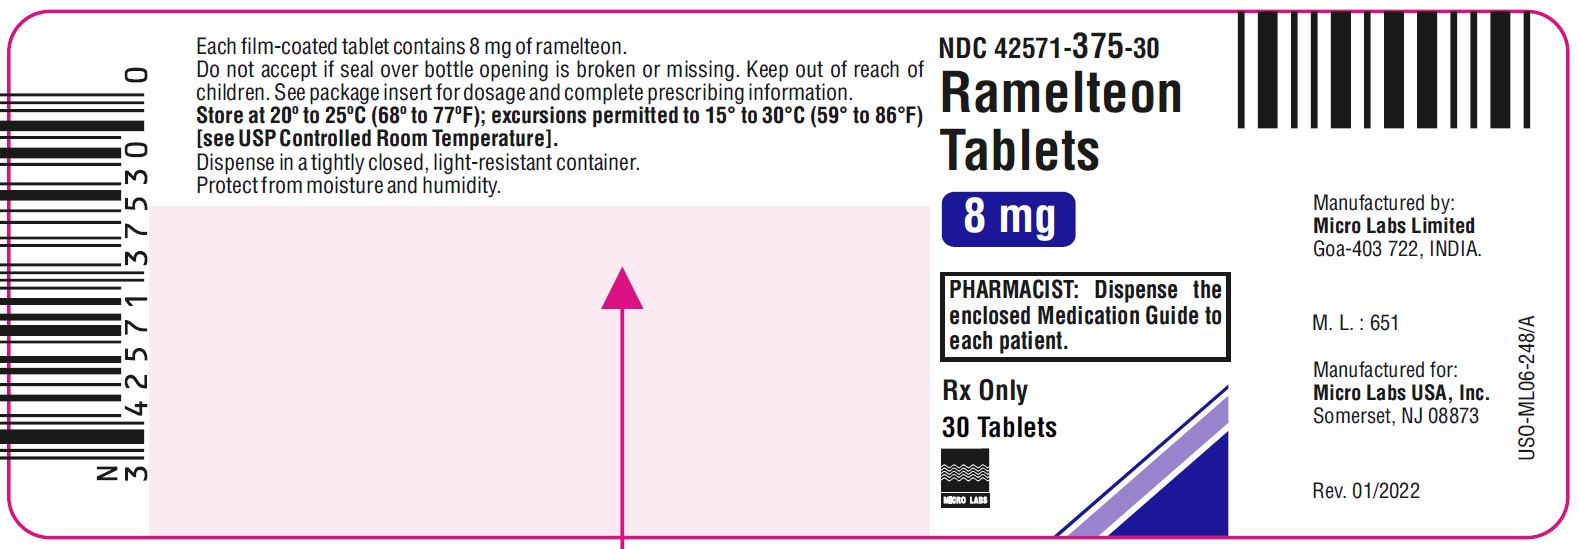
Ramelteon 8 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Melatonin Receptor Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ramelteon is used to help patients who have sleep-onset insomnia (difficulty falling asleep) fall asleep more quickly. Ramelteon is in a class of medications called melatonin receptor agonists. It works similarly to melatonin, a natural substance in the brain that is needed for sleep.
Read the full MedlinePlus article ↗- Ramelteon works differently from most other prescription sleep medications. Instead of sedating your brain with a broad chemical 'off switch,' it works the way your body's own mela...
- What exactly does ramelteon do, and is it like other sleep pills?
- Take ramelteon within 30 minutes of going to bed — not hours before. After you take it, stick to activities that prepare you for sleep and get into bed. Avoid eating a high-fat mea...
- When should I take it, and does it matter if I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ramelteon — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 5Y0974F5PW
Hydroxypropyl cellulose is a plant-derived thickener and binder made by chemically treating cellulose. In medicines, it helps hold tablets together, thickens liquids, and can form a protective coating on capsules.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.658 | $65.75 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.09 | $108.75 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.43 | $143.01 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ramelteon 8 mg 00591-2191-01 | Actavis | 100 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 00832-1250-11 | Upsher-Smith | 100 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 00904-7494-06 | Major | 50 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mgthis 42571-0375-01 | Micro | 100 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 50268-0708-15 | AvPAK | 50 tablets | $0.657 | AB | Discontinued | — |
| Ramelteon 8 mg 52817-0235-10 | TruPharma, | 100 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 59651-0505-01 | Aurobindo | 100 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 60687-0692-65 | American | 50 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 70700-0272-05 | Xiromed, | 500 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 70710-1344-01 | Zydus | 100 tablets | $0.657 | AB | Availability likely | — |
| Ramelteon 8 mg 43598-0741-01 | Dr.Reddys | 100 tablets | $0.667 | AB | Discontinued | +1% |
| Rozerem 8 mg 64764-0805-10 | Takeda | 100 tablets | $12.432 | AB | Availability likely | +1791% |
| Ramelteon 8 mg 42291-0776-30 | AvKARE | 30 tablets | — | — | FDA listed | — |
| Ramelteon 8 mg 50268-0822-15 | AvPAK | 50 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 51407-0523-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 63629-8531-01 | Bryant | 30 tablets | — | — | FDA listed | — |
| ramelteon 8 mg 70010-0028-01 | Granules | 100 tablets | — | — | FDA listed | — |
| Ramelteon 8 mg 70518-4257-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 70771-1495-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 71205-0918-00 | Proficient | 100 tablets | — | — | FDA listed | — |
| Ramelteon 8 mg 71335-1853-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 71335-2186-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 71335-2310-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 71335-2411-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 71335-2886-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72162-2161-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72162-2169-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72162-2176-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72162-2644-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72189-0153-30 | DIRECT | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72189-0369-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72189-0484-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 72319-0005-01 | i3 | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 76420-0628-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 76420-0880-01 | Asclemed | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 80425-0203-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 80425-0343-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 82804-0216-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 85742-0023-22 | Kanchan | 30 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 87063-0189-01 | ASCLEMED | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 85766-0251-01 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 10135-0838-01 | Marlex | 100 tablets | — | AB | FDA listed | — |
| Ramelteon 8 mg 80425-0593-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 42571-0375-01 You're viewing this | 100 TABLET in 1 BOTTLE (42571-375-01) | $0.6575 / ea | $65.75 | 2023-05-01 | Active |
| 42571-0375-05 | 500 TABLET in 1 BOTTLE (42571-375-05) | — | — | 2023-05-01 | Active |
| 42571-0375-30 | 30 TABLET in 1 BOTTLE (42571-375-30) | $0.6575 / ea | $19.72 | 2023-05-01 | Active |
You're viewing one of 3 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.6575 NADAC).
This pack accounts for about 12% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 42571-0375-01?
What is the difference between NDC 42571-0375-01 and NDC 42571-0375-30?
What NDC number is used to bill for this package of Ramelteon 8 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ramelteon tablets are indicated for the treatment of insomnia characterized by difficulty with sleep onset. The clinical trials performed in support of efficacy were up to six months in duration. The final formal assessments of sleep latency were performed after two days of treatment during the crossover study (elderly only), at five weeks in the six week studies (adults and elderly), and at the end of the six month study (adults and elderly) [see Clinical Studies (14)].
Ramelteon tablet is indicated for the treatment of insomnia characterized by difficulty with sleep onset. (1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult dose: 8 mg taken within 30 minutes of going to bed. (2.1) Should not be taken with or immediately after a high-fat meal. (2.1) Total daily dose should not exceed 8 mg. (2.1)
2.1Dosage in Adults The recommended dose of ramelteon tablet is 8 mg taken within 30 minutes of going to bed. It is recommended that ramelteon tablets not be taken with or immediately after a high-fat meal. The total ramelteon tablet dose should not exceed 8 mg per day.
2.2Dosing in Patients with Hepatic Impairment Ramelteon tablets are not recommended in patients with severe hepatic impairment. Ramelteon tablets should be used with caution in patients with moderate hepatic impairment [see Warnings and Precautions (5.6) , Clinical Pharmacology (12.4)] .
2.3Administration with Other Medications Ramelteon tablets should not be used in combination with fluvoxamine. Ramelteon tablets should be used with caution in patients taking other CYP1A2 inhibiting drugs [see Drug Interactions (7) , Clinical Pharmacology (12.5)].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ramelteon tablet is available in an 8 mg strength tablet for oral administration. Ramelteon tablets, 8 mg are yellow colored, circular, biconvex, film-coated tablets, debossed with "RM" on one face and plain on other face with an approximate diameter of 7.00 mm. 8 mg tablets. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Patients who develop angioedema after treatment with ramelteon tablets should not be rechallenged with the drug. Patients should not take ramelteon tablet in conjunction with fluvoxamine [see Drug Interactions (7)]. History of angioedema while taking ramelteon tablets. (4) Fluvoxamine (strong CYP1A2 inhibitor): Increases AUC for ramelteon and should not be used in combination. (7.1)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Severe anaphylactic/anaphylactoid reactions: Angioedema and anaphylaxis have been reported. Do not rechallenge if such reactions occur. ( 5.1 ) Need to evaluate for comorbid diagnoses: Reevaluate if insomnia persists after 7 to 10 days of treatment.
( 5.2 ) Abnormal thinking, behavioral changes, complex behaviors: May include “sleep-driving” and hallucinations. Immediately evaluate any new onset behavioral changes. ( 5.3 ) Depression: Worsening of depression or suicidal thinking may occur.
( 5.3 ) CNS effects: Potential impairment of activities requiring complete mental alertness such as operating machinery or driving a motor vehicle, after ingesting the drug. ( 5.4 ) Reproductive effects: Include decreased testosterone and increased prolactin levels. Effect on reproductive axis in developing humans is unknown.
( 5.5 ) Patients with severe sleep apnea: Ramelteon tablet is not recommended for use in this population. ( 5.6 )
5.1Severe Anaphylactic and Anaphylactoid Reactions Rare cases of angioedema involving the tongue, glottis or larynx have been reported in patients after taking the first or subsequent doses of ramelteon tablets. Some patients have had additional symptoms such as dyspnea, throat closing, or nausea and vomiting that suggest anaphylaxis. Some patients have required medical therapy in the emergency department.
If angioedema involves the tongue, glottis or larynx, airway obstruction may occur and be fatal. Patients who develop angioedema after treatment with ramelteon tablets should not be rechallenged with the drug.
5.2Need to Evaluate for Comorbid Diagnoses Since sleep disturbances may be the presenting manifestation of a physical and/or psychiatric disorder, symptomatic treatment of insomnia should be initiated only after a careful evaluation of the patient. The failure of insomnia to remit after 7 to 10 days of treatment may indicate the presence of a primary psychiatric and/or medical illness that should be evaluated . Worsening of insomnia, or the emergence of new cognitive or behavioral abnormalities, may be the result of an unrecognized underlying psychiatric or physical disorder and requires further evaluation of the patient.
Exacerbation of insomnia and emergence of cognitive and behavioral abnormalities were seen with ramelteon tablets during the clinical development program .
5.3Abnormal Thinking and Behavioral Changes A variety of cognitive and behavior changes have been reported to occur in association with the use of hypnotics. In primarily depressed patients, worsening of depression (including suicidal ideation and completed suicides) has been reported in association with the use of hypnotics. Hallucinations, as well as behavioral changes such as bizarre behavior, agitation and mania have been reported with ramelteon tablets use.
Amnesia, anxiety and other neuro-psychiatric symptoms may also occur unpredictably. Complex behaviors such as "sleep-driving" (i.e., driving while not fully awake after ingestion of a hypnotic) and other complex behaviors (e.g., preparing and eating food, making phone calls, or having sex), with amnesia for the event, have been reported in association with hypnotic use. The use of alcohol and other CNS depressants may increase the risk of such behaviors.
These events can occur in hypnotic-naive as well as in hypnotic-experienced persons. Complex behaviors have been reported with the use of ramelteon tablets. Discontinuation of ramelteon tablets should be strongly considered for patients who report any complex sleep behavior.
5.4CNS Effects Patients should avoid engaging in hazardous activities that require concentration (such as operating a motor vehicle or heavy machinery) after taking ramelteon tablets. After taking ramelteon tablets, patients should confine their activities to those necessary to prepare for bed. Patients should be advised not to consume alcohol in combination with ramelteon tablets as alcohol and ramelteon tablets may hav…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections: Severe anaphylactic and anaphylactoid reactions [see Warnings and Precautions (5.1)] Abnormal thinking, behavior changes, and complex behaviors [see Warnings and Precautions (5.3)] CNS effects [see Warnings and Precautions (5.4)] Most common adverse reactions (≥3% and more common than with placebo) are: somnolence, dizziness, fatigue, nausea, and exacerbated insomnia. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Micro Labs USA, Inc. at 1-855-839-8195 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Adverse Reactions Resulting in Discontinuation of Treatment The data described in this section reflect exposure to ramelteon tablets in 5373 subjects, including 722 exposed for six months or longer, and 448 subjects for one year. Six percent of the 5373 individual subjects exposed to ramelteon tablets in clinical studies discontinued treatment owing to an adverse event, compared with 2% of the 2279 subjects receiving placebo. The most frequent adverse events leading to discontinuation in subjects receiving ramelteon tablets were somnolence, dizziness, nausea, fatigue, headache, and insomnia; all of which occurred in 1% of the patients or less.
Ramelteon Tablets Most Commonly Observed Adverse Events Table 1 displays the incidence of adverse events reported by the 2861 patients with chronic insomnia who participated in placebo-controlled trials of ramelteon tablets. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in clinical trials of other drugs, and may not reflect the rates observed in practice. The adverse reaction information from clinical trials does, however, provide a basis for identifying the adverse events that appear to be related to drug use and for approximating rates.
Table 1. Incidence (% of subjects) of Treatment-Emergent Adverse Events MedDRA Preferred Term Placebo (n=1456) Ramelteon 8 mg (n=1405) Somnolence 2% 3% Fatigue 2% 3% Dizziness 3% 4% Nausea 2% 3% Insomnia exacerbated 2% 3%
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Rifampin (strong CYP enzyme inducer): Decreases exposure to and effects of ramelteon. (7.1) Ketoconazole (strong CYP3A4 inhibitor): Increases AUC for ramelteon; administer with caution. (7.1) Fluconazole (strong CYP2C9 inhibitor): Increases systemic exposure of ramelteon; administer with caution.
(7.1) Donepezil: Increases systemic exposure of ramelteon; patients should be closely monitored when ramelteon is coadministered with donepezil. (7.1) Doxepin: Increases systemic exposure of ramelteon; patients should be closely monitored when ramelteon is coadministered with doxepin. (7.1) Alcohol: Causes additive psychomotor impairment; should not be used in combination.
(7.2)
7.1Effects of Other Drugs on Ramelteon Fluvoxamine (strong CYP1A2 inhibitor) AUC 0 to inf for ramelteon increased approximately 190-fold, and the C max increased approximately 70-fold upon coadministration of fluvoxamine and ramelteon tablets, compared to ramelteon tablets administered alone. Ramelteon tablets should not be used in combination with fluvoxamine [see Contraindications (4) , Clinical Pharmacology (12.5) ] . Other less strong CYP1A2 inhibitors have not been adequately studied.
Ramelteon tablets should be administered with caution to patients taking less strong CYP1A2 inhibitors. Rifampin (strong CYP enzyme inducer) Administration of multiple doses of rifampin resulted in a mean decrease of approximately 80% in total exposure to ramelteon and metabolite M-II. Efficacy may be reduced when ramelteon tablets are used in combination with strong CYP enzyme inducers such as rifampin [see Clinical Pharmacology (12.5) ] .
Ketoconazole (strong CYP3A4 inhibitor) The AUC 0 to inf and C max of ramelteon increased by approximately 84% and 36% upon coadministration of ketoconazole with ramelteon tablets. Ramelteon tablets should be administered with caution in subjects taking strong CYP3A4 inhibitors such as ketoconazole [see Clinical Pharmacology (12.5) ] . Fluconazole (strong CYP2C9 inhibitor) The AUC 0 to inf and C max of ramelteon was increased by approximately 150% when ramelteon tablets were coadministered with fluconazole.
Ramelteon tablets should be administered with caution in subjects taking strong CYP2C9 inhibitors such as fluconazole [see Clinical Pharmacology (12.5) ] . Donepezil The AUC 0 to inf and C max of ramelteon increased by approximately 100% and 87%, respectively upon coadministration of donepezil with ramelteon tablets. Patients should be closely monitored when ramelteon tablet is coadministered with donepezil [see Clinical Pharmacology (12.5) ] .
Doxepin The AUC 0 to inf and C max of ramelteon increased by approximately 66% and 69%, respectively, upon coadministration of doxepin with ramelteon tablets. Patients should be closely monitored when ramelteon tablets were coadministered with doxepin [see Clinical Pharmacology (12.5) ] .
7.2Effect of Alcohol on Ramelteon Alcohol by itself impairs performance and can cause sleepiness. Since the intended effect of ramelteon tablets are to promote sleep, patients should be cautioned not to consume alcohol when using ramelteon tablets [see Clinical Pharmacology (12.5) ] . Use of the products in combination may have an additive effect.
7.3Drug/Laboratory Test Interactions Ramelteon tablets are not known to interfere with commonly used clinical laboratory tests. In addition, in vitro data indicate that ramelteon does not cause false-positive results for benzodiazepines, opiates, barbiturates, cocaine, cannabinoids, or amphetamines in two standard urine drug screening methods in vitro .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric use: Safety and effectiveness not established. (8.4) Geriatric use: No overall differences in safety and efficacy between elderly and younger adult subjects. (8.5) Hepatic impairment: Is not recommended in patients with severe impairment; use with caution in moderate impairment. (8.8)
8.1Pregnancy Risk Summary Available data from postmarketing reports with ramelteon tablets use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal studies, ramelteon produced evidence of developmental toxicity, including teratogenic effects, in rats at doses greater than 36 times the recommended human dose (RHD) of 8 mg/day based on body surface area (mg/m 2 ) (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Oral administration of ramelteon (10, 40, 150 or 600 mg/kg/day) to pregnant rats during the period of organogenesis was associated with increased incidences of fetal structural abnormalities (malformations and variations) at doses greater than 40 mg/kg/day.
The no-effect dose is approximately 50 times the RHD based on mg/m 2 . Treatment of pregnant rabbits during the period of organogenesis produced no evidence of embryo-fetal toxicity at oral doses of up to 300 mg/kg/day (or up to 720 times the RHD based on mg/m 2 ). When rats were orally administered ramelteon (30, 100, or 300 mg/kg/day) throughout gestation and lactation, growth retardation, developmental delay, and behavioral changes were observed in the offspring at doses greater than 30 mg/kg/day.
The no-effect dose is 36 times the RHD based on mg/m 2 . Increased incidences of malformation and death among offspring were seen at the highest dose.
8.2Lactation Risk Summary There are no data regarding the presence of ramelteon or its metabolites in human milk, the effects on the breastfed infant, or the effects on milk production. Ramelteon and/or its metabolites are present in rat milk. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
Because of the mechanism of action of ramelteon, there is a potential risk for somnolence in a breastfed infant (see Clinical Considerations) . The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ramelteon tablets and any potential adverse effects on the breastfed infant from ramelteon tablets or from the underlying maternal condition. Clinical Considerations Infants exposed to ramelteon through breastmilk should be monitored for somnolence and feeding problems.
A lactating woman may consider interrupting breastfeeding and pumping and discarding breast milk during treatment and for 25 hours (approximately 5 elimination half-lives) after ramelteon tablets administration in order to minimize drug exposure to a breastfed infant.
8.4Pediatric Use Safety and effectiveness of ramelteon tablets in pediatric patients have not been established. Further study is needed prior to determining that this product may be used safely in prepubescent and pubescent patients.
8.5Geriatric Use A total of 654 subjects in double-blind, placebo-controlled, efficacy trials who received ramelteon tablets were at least 65 years of age; of these, 199 were 75 years of age or older. No overall differences in safety or efficacy were observed between elderly and younger adult subjects. A double-blind, randomized, placebo-controlled study in elderly subjects with insomnia (n=33) evaluated the effect of a single dose of ramelteon tablets on balance, mobility, and memory functions after middle…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from postmarketing reports with ramelteon tablets use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal studies, ramelteon produced evidence of developmental toxicity, including teratogenic effects, in rats at doses greater than 36 times the recommended human dose (RHD) of 8 mg/day based on body surface area (mg/m 2 ) (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Oral administration of ramelteon (10, 40, 150 or 600 mg/kg/day) to pregnant rats during the period of organogenesis was associated with increased incidences of fetal structural abnormalities (malformations and variations) at doses greater than 40 mg/kg/day.
The no-effect dose is approximately 50 times the RHD based on mg/m 2 . Treatment of pregnant rabbits during the period of organogenesis produced no evidence of embryo-fetal toxicity at oral doses of up to 300 mg/kg/day (or up to 720 times the RHD based on mg/m 2 ). When rats were orally administered ramelteon (30, 100, or 300 mg/kg/day) throughout gestation and lactation, growth retardation, developmental delay, and behavioral changes were observed in the offspring at doses greater than 30 mg/kg/day.
The no-effect dose is 36 times the RHD based on mg/m 2 . Increased incidences of malformation and death among offspring were seen at the highest dose.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of ramelteon tablets in pediatric patients have not been established. Further study is needed prior to determining that this product may be used safely in prepubescent and pubescent patients.
🧓 Geriatric Use ▾
8.5Geriatric Use A total of 654 subjects in double-blind, placebo-controlled, efficacy trials who received ramelteon tablets were at least 65 years of age; of these, 199 were 75 years of age or older. No overall differences in safety or efficacy were observed between elderly and younger adult subjects. A double-blind, randomized, placebo-controlled study in elderly subjects with insomnia (n=33) evaluated the effect of a single dose of ramelteon tablets on balance, mobility, and memory functions after middle of the night awakening.
There is no information on the effect of multiple dosing. Night time dosing of ramelteon tablets 8 mg did not impair middle of the night balance, mobility, or memory functions relative to placebo. The effects on night balance in the elderly cannot be definitively known from this study.
🆘 Overdosage ▾
10 OVERDOSAGE General symptomatic and supportive measures should be used, along with immediate gastric lavage where appropriate. Intravenous fluids should be administered as needed. As in all cases of drug overdose, respiration, pulse, blood pressure, and other appropriate vital signs should be monitored, and general supportive measures employed.
Hemodialysis does not effectively reduce exposure to ramelteon tablets. Therefore, the use of dialysis in the treatment of overdosage is not appropriate. Poison Control Center As with the management of all overdosage, the possibility of multiple drug ingestion should be considered.
Contact a poison control center for current information on the management of overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ramelteon is a melatonin receptor agonist with both high affinity for melatonin MT 1 and MT 2 receptors and relative selectivity over the MT 3 receptor. The activity of ramelteon at the MT 1 and MT 2 receptors is believed to contribute to its sleep-promoting properties, as these receptors, acted upon by endogenous melatonin, are thought to be involved in the maintenance of the circadian rhythm underlying the normal sleep-wake cycle. Ramelteon has no appreciable affinity for the GABA receptor complex or for receptors that bind neuropeptides, cytokines, serotonin, dopamine, noradrenaline, acetylcholine, and opiates.
Ramelteon also does not interfere with the activity of a number of selected enzymes in a standard panel. The major metabolite of ramelteon, M-II, is pharmacologically active and has approximately one tenth and one fifth the binding affinity of the parent molecule for the human MT 1 and MT 2 receptors, respectively. However, M-II circulates at higher concentrations than the parent producing 20- to 100-fold greater mean systemic exposure when compared to ramelteon.
Similar to ramelteon, M-II does not interfere with the activity of a number of endogenous enzymes. All other known metabolites of ramelteon are inactive.
12.3Pharmacokinetics The pharmacokinetic profile of ramelteon tablets has been evaluated in healthy subjects as well as in subjects with hepatic or renal impairment. When administered orally to humans in doses ranging from 4 to 64 mg, ramelteon undergoes rapid, high first-pass metabolism, and exhibits linear pharmacokinetics. Maximal serum concentration (C max ) and area under the concentration-time curve (AUC) data show substantial intersubject variability, consistent with the high first-pass effect; the coefficient of variation for these values is approximately 100%.
Several metabolites have been identified in human serum and urine. Absorption Ramelteon is absorbed rapidly, with median peak concentrations occurring at approximately 0.75 hour (range, 0.5 to 1.5 hours) after fasted oral administration. Although the total absorption of ramelteon is at least 84%, the absolute oral bioavailability is only 1.8% due to extensive first-pass metabolism.
Distribution In vitro protein binding of ramelteon is approximately 82% in human serum, independent of concentration. Binding to albumin accounts for most of that binding, since 70% of the drug is bound in human serum albumin. Ramelteon is not distributed selectively to red blood cells.
Ramelteon has a mean volume of distribution after intravenous administration of
73.6L, suggesting substantial tissue distribution. Metabolism Metabolism of ramelteon consists primarily of oxidation to hydroxyl and carbonyl derivatives, with secondary metabolism producing glucuronide conjugates. CYP1A2 is the major isozyme involved in the hepatic metabolism of ramelteon; the CYP2C subfamily and CYP3A4 isozymes are also involved to a minor degree.
The rank order of the principal metabolites by prevalence in human serum is M-II, M-IV, M-I, and M-III. These metabolites are formed rapidly and exhibit a monophasic decline and rapid elimination. The overall mean systemic exposure of M-II is approximately 20- to 100-fold higher than parent drug.
Elimination Following oral administration of radiolabeled ramelteon, 84% of total radioactivity was excreted in urine and approximately 4% in feces, resulting in a mean recovery of 88%. Less than 0.1% of the dose was excreted in urine and feces as the parent compound. Elimination was essentially complete by 96 hours postdose.
Repeated once daily dosing with ramelteon tablets does not result in significant accumulation owing to the short elimination half-life of ramelteon (on average, approximately one to 2.6 hours). The half-life of M-II is two to five hours and independent of dose. Serum concentrations of the parent drug and its metabolites in humans are at or below the lower limits of quantitatio…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ramelteon is a melatonin receptor agonist with both high affinity for melatonin MT 1 and MT 2 receptors and relative selectivity over the MT 3 receptor. The activity of ramelteon at the MT 1 and MT 2 receptors is believed to contribute to its sleep-promoting properties, as these receptors, acted upon by endogenous melatonin, are thought to be involved in the maintenance of the circadian rhythm underlying the normal sleep-wake cycle. Ramelteon has no appreciable affinity for the GABA receptor complex or for receptors that bind neuropeptides, cytokines, serotonin, dopamine, noradrenaline, acetylcholine, and opiates.
Ramelteon also does not interfere with the activity of a number of selected enzymes in a standard panel. The major metabolite of ramelteon, M-II, is pharmacologically active and has approximately one tenth and one fifth the binding affinity of the parent molecule for the human MT 1 and MT 2 receptors, respectively. However, M-II circulates at higher concentrations than the parent producing 20- to 100-fold greater mean systemic exposure when compared to ramelteon.
Similar to ramelteon, M-II does not interfere with the activity of a number of endogenous enzymes. All other known metabolites of ramelteon are inactive.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ramelteon tablets are yellow colored, circular, biconvex, film-coated tablets, debossed with "RM" on one face and plain on other face with an approximate diameter of 7.00 mm. Bottle of 30: NDC 42571-375-30 Bottle of 100: NDC 42571-375-01 Bottle of 500: NDC 42571-375-05 Store at 20º to 25ºC (68º to 77ºF); excursions permitted to 15º to 30ºC (59º to 86ºF) [see USP Controlled Room Temperature]. Keep container tightly closed and protected from moisture and humidity.
📋 Description ▾
11 DESCRIPTION Ramelteon is an orally active hypnotic chemically designated as ( S )- N -[2-(1,6,7,8-tetrahydro-2 H -indeno-[5,4- b ]furan-8-yl)ethyl]propionamide and containing one chiral center. The compound is produced as the ( S )-enantiomer, with an empirical formula of C 16 H 21 NO 2 , molecular weight of 259.34, and the following chemical structure: Ramelteon is freely soluble in ethanol and benzyl alcohol, slightly soluble in acetonitrile, and practically insoluble in water. Each ramelteon tablet includes the following inactive ingredients: Copovidone, croscarmellose sodium, ferric oxide yellow, hydroxypropyl cellulose, hydroxypropyl methyl cellulose, lactose monohydrate, magnesium stearate, maize starch, polyethylene glycol 8000 and titanium dioxide. ramelteon-structure.jpg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Severe Anaphylactic and Anaphylactoid Reactions Inform patients that severe anaphylactic and anaphylactoid reactions have occurred with ramelteon. Describe the relevant signs/symptoms and advise seeking immediate medical attention if any such things occur.
Sleep-Driving and other Complex Behaviors There have been reports of people getting out of bed after taking a sleep medication and driving their cars while not fully awake, often with no memory of the event. If a patient experiences such an episode, it should be reported to his or her doctor immediately, since "sleep-driving" can be dangerous. This behavior is more likely to occur when sleep medications are taken with alcohol or other central nervous system depressants.
Other complex behaviors (e.g., preparing and eating food, making phone calls, or having sex) have been reported in patients who are not fully awake after taking a sleep medication. As with sleep-driving, patients usually do not remember these events. Endocrine Effects Patients should consult their healthcare providers if they experience one of the following: cessation of menses or galactorrhea in females, decreased libido, or problems with fertility.
Describe the relevant signs/symptoms and advise seeking medical attention if any such things occur. Administration Instructions Patients should be advised to take Ramelteon tablet within 30 minutes prior to going to bed and should confine their activities to those necessary to prepare for bed. Patients should be advised that they should not take ramelteon tablets with or immediately after a high-fat meal.
Do not break the tablet; it should be swallowed whole. Lactation Advise mothers using ramelteon tablets to monitor neonates for signs of somnolence and feeding problems. A lactating woman may consider pumping and discarding breast milk during treatment and for 25 hours after ramelteon tablets administration to minimize drug exposure to a breastfed infant [see Use in Specific Populations (8.2) ] .
Manufactured by: Micro Labs Limited Goa - 403 722, INDIA. Manufactured for: Micro Labs USA, Inc. Somerset, NJ 08873 Rev.
01/2022