
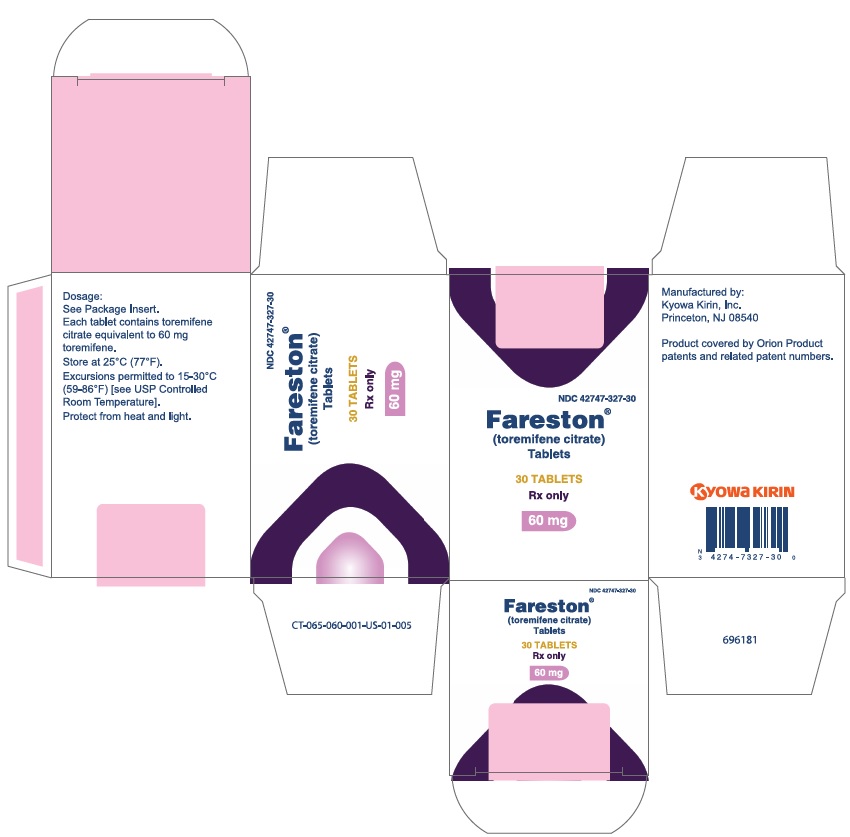
Fareston toremifene citrate 60 mg Tablet, 7-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Estrogen Agonist/Antagonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Toremifene is used to treat breast cancer that has spread to other parts of the body in women who have experienced menopause ('change of life'; end of monthly menstrual periods). Toremifene is in a class of medications called nonsteroidal antiestrogens. It works by blocking the activity of estrogen (a female hormone) in the breast. This may stop the growth of some breast tumors that need estrogen to grow.
Read the full MedlinePlus article ↗- Toremifene targets breast cancer cells that are fueled by estrogen. It works by grabbing onto the estrogen receptors on those cancer cells before estrogen can, effectively blocking...
- What exactly is toremifene treating — and how does it work against my breast cancer?
- You can take toremifene with or without food — it doesn't make a difference in how your body absorbs it. What does matter is taking it at roughly the same time each day. Keeping a...
- Do I need to take this with food, and does it matter what time of day I take it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Toremifene Citrate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII H8AV0SQX4D
A modified starch derived from potato or corn starch. It absorbs water quickly and helps tablets or capsules break apart and dissolve in the stomach, acting as a disintegrant to ensure the medicine releases its active ingredients properly.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| toremifene citrate 60 mg 64980-0404-03 | Rising | 30 tablets | $21.132 | AB | Availability likely | — |
| toremifene citrate 60 mg 72205-0050-30 | Novadoz | 30 tablets | $21.132 | AB | Availability likely | — |
| Fareston 60 mgthis 42747-0327-72 | Kyowa | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 42747-0327-30 | 30 TABLET in 1 BOTTLE (42747-327-30) | 1997-06-30 | Active |
| 42747-0327-72 You're viewing this | 7 TABLET in 1 BLISTER PACK (42747-327-72) | 1997-06-30 | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 42747-0327-72?
What is the difference between NDC 42747-0327-72 and NDC 42747-0327-30?
What NDC number is used to bill for this package of Fareston toremifene citrate 60 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: QT PROLONGATION FARESTON has been shown to prolong the QTc interval in a dose- and concentration-related manner [see Clinical Pharmacology (12.2) ] . Prolongation of the QT interval can result in a type of ventricular tachycardia called Torsade de pointes, which may result in syncope, seizure, and/or death. Toremifene should not be prescribed to patients with congenital/acquired QT prolongation, uncorrected hypokalemia or uncorrected hypomagnesemia.
Drugs known to prolong the QT interval and strong CYP3A4 inhibitors should be avoided [see Warnings and Precautions (5.1) ] . WARNING: QT PROLONGATION FARESTON has been shown to prolong the QTc interval in a dose- and concentration-related manner [see Clinical Pharmacology (12.2) ] . Prolongation of the QT interval can result in a type of ventricular tachycardia called Torsade de pointes, which may result in syncope, seizure, and/or death.
Toremifene should not be prescribed to patients with congenital/acquired QT prolongation, uncorrected hypokalemia or uncorrected hypomagnesemia. Drugs known to prolong the QT interval and strong CYP3A4 inhibitors should be avoided [see Warnings and Precautions (5.1) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE FARESTON® is an estrogen agonist/antagonist indicated for the treatment of metastatic breast cancer in postmenopausal women with estrogen-receptor positive or unknown tumors. FARESTON® is an estrogen agonist/antagonist indicated for the treatment of metastatic breast cancer in postmenopausal women with estrogen-receptor positive or unknown tumors. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The dosage of FARESTON is 60 mg, once daily, orally. Treatment is generally continued until disease progression is observed. 60 mg once daily, orally ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablet is 60 mg, round, convex, unscored, uncoated, and white, or almost white, identified with TO 60 embossed on one side. 60 mg tablet is round, convex, unscored, uncoated, and white, or almost white, identified with TO 60 embossed on one side. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to the drug ( 4.1 ) QT Prolongation, Hypokalemia, Hypomagnesemia ( 4.2 )
4.1Hypersensitivity to the Drug FARESTON is contraindicated in patients with known hypersensitivity to the drug.
4.2QT Prolongation, Hypokalemia, Hypomagnesemia Toremifene should not be prescribed to patients with congenital/acquired QT prolongation (long QT syndrome), uncorrected hypokalemia, or uncorrected hypomagnesemia.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Prolongation of the QT Interval ( 5.1 ) Heptatotoxicty ( 5.2 ) Hypercalcemia and Tumor Flare ( 5.3 ) Risk of Uterine Malignancy ( 5.4 ) General ( 5.5 ) Laboratory Tests ( 5.6 ) Pregnancy: Fetal harm may occur when administered to a pregnant woman. Women should be advised not to become pregnant when taking FARESTON. ( 5.7 , 8.1 ) Women of Childbearing Potential: Use effective nonhormonal contraception during FARESTON therapy.
( 5.8 )
5.1Prolongation of the QT Interval Toremifene has been shown to prolong the QTc interval in a dose- and concentration-related manner [see Clinical Pharmacology (12.2) ] . Prolongation of the QT interval can result in a type of ventricular tachycardia called Torsade de pointes, which may result in syncope, seizure, and/or death. Toremifene should be avoided in patients with long QT syndrome.
Caution should be exercised in patients with congestive heart failure, hepatic impairment and electrolyte abnormalities. Hypokalemia or hypomagnesemia must be corrected prior to initiating toremifene and these electrolytes should be monitored periodically during therapy. Drugs that prolong the QT interval should be avoided.
In patients at increased risk, electrocardiograms (ECGs) should be obtained at baseline and as clinically indicated [see Drug Interactions (7.2) and Clinical Pharmacology (12.2) ] .
5.2Hepatotoxicity Hepatotoxicity, both increases in the serum concentration for grade 3 and 4 transaminitis and hyperbilirubinemia, including jaundice, hepatitis, and non-alcoholic fatty liver disease, have also been reported in clinical trials and postmarketing with FARESTON. Liver function tests should be performed periodically. [ see Adverse Reactions (6.1) , Post-marketing Experience (6.2) ]
5.3Hypercalcemia and Tumor Flare As with other antiestrogens, hypercalcemia and tumor flare have been reported in some breast cancer patients with bone metastases during the first weeks of treatment with FARESTON. Tumor flare is a syndrome of diffuse musculoskeletal pain and erythema with increased size of tumor lesions that later regress. It is often accompanied by hypercalcemia.
Tumor flare does not imply failure of treatment or represent tumor progression. If hypercalcemia occurs, appropriate measures should be instituted and, if hypercalcemia is severe, FARESTON treatment should be discontinued.
5.4Risk of Uterine Malignancy Endometrial cancer, endometrial hypertrophy, hyperplasia, and uterine polyps have been reported in some patients treated with FARESTON. Endometrial hyperplasia of the uterus was observed in animals treated with toremifene [see Nonclinical Toxicology (13.1) ] . Long-term use of FARESTON has not been established in patients with pre-existing endometrial hyperplasia.
All patients should have baseline and annual gynecological examinations. In particular, patients at high risk of endometrial cancer should be closely monitored.
5.5General Patients with a history of thromboembolic diseases should generally not be treated with FARESTON. Patients with bone metastases should be monitored closely for hypercalcemia during the first weeks of treatment [see Warnings and Precautions (5.2) ] . Leukopenia and thrombocytopenia have been reported rarely; leukocyte and platelet counts should be monitored when using FARESTON in patients with leukopenia and thrombocytopenia.
5.6Laboratory Tests Periodic complete blood counts, calcium levels, and liver function tests should be obtained.
5.7Use in Pregnancy Based on its mechanism of action in humans and findings of increased pregnancy loss and fetal malformation in animal studies, FARESTON can cause fetal harm when administered to a pregnant woman. Toremifene caused embryo-fetal toxicities at maternal doses that were lower than the 60 mg daily recommended human dose on a mg/m 2 basis. There are no adequate and well-controlled studies in pregnant women using FARESTON.
If this drug is used during pregnancy, or if the patient becomes pregnan…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Most common adverse reactions are hot flashes, sweating, nausea and vaginal discharge. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Kyowa Kirin, Inc. at 1-800-305-FARESTON (1-800-305-3273) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Adverse drug reactions are principally due to the antiestrogenic actions of FARESTON and typically occur at the beginning of treatment. The incidences of the following eight clinical toxicities were prospectively assessed in the North American Study. The incidence reflects the toxicities that were considered by the investigator to be drug related or possibly drug related.
North American Study FAR60 TAM20 n = 221 n = 215 Hot Flashes 35% 30% Sweating 20% 17% Nausea 14% 15% Vaginal Discharge 13% 16% Dizziness 9% 7% Edema 5% 5% Vomiting 4% 2% Vaginal Bleeding 2% 4% Approximately 1% of patients receiving FARESTON (n = 592) in the three controlled studies discontinued treatment as a result of adverse reactions (nausea and vomiting, fatigue, thrombophlebitis, depression, lethargy, anorexia, ischemic attack, arthritis, pulmonary embolism, and myocardial infarction). Serious adverse reactions occurring in at least 1% of patients receiving FARESTON in the three major trials are listed in the table below.
Three prospective, randomized, controlled clinical studies (North American, Eastern European, and Nordic) were conducted. The patients were randomized to parallel groups receiving FARESTON 60 mg (FAR60) or tamoxifen 20 mg (TAM20) in the North American Study or tamoxifen 40 mg (TAM40) in the Eastern European and Nordic studies. The North American and Eastern European studies also included high-dose toremifene arms of 200 and 240 mg daily, respectively [see Clinical Studies (14) ] . * Most of the ocular abnormalities were observed in the North American Study in which on-study and biannual ophthalmic examinations were performed.
No cases of retinopathy were observed in any arm. ** Elevated defined as follows: North American Study: AST >100 IU/L; alkaline phosphatase >200 IU/L; bilirubin > 2 mg/dL. Eastern European and Nordic studies: AST, alkaline phosphatase, and bilirubin - WHO Grade 1 (1.25 times the upper limit of normal). Adverse Reactions North American Eastern European Nordic FAR60 TAM20 FAR60 TAM40 FAR60 TAM40 n=221(%) n=215(%) n=157(%) n=149(%) n=214(%) n=201(%) Cardiac Cardiac Failure 2 (1) 1 (<1) - 1 (<1) 2 (1) 3 (1.5) Myocardial Infarction 2 (1) 3 (1.5) 1 (<1) 2 (1) - 1 (<1) Arrhythmia - - - - 3 (1.5) 1 (<1) Angina Pectoris - - 1 (<1) - 1 (<1) 2 (1) Ocular* Cataracts 22 (10) 16 (7.5) - - - 5 (3) Dry Eyes 20 (9) 16 (7.5) - - - - Abnormal Visual Fields 8 (4) 10 (5) - - - 1 (<1) Corneal Keratopathy 4 (2) 2 (1) - - - - Glaucoma 3 (1.5) 2 (1) 1 (<1) - - 1 (<1) Abnormal Vision/Diplopia - - - - 3 (1.5) - Thromboembolic Pulmonary Embolism 4 (2) 2 (1) 1 (<1) - - 1 (<1) Thrombophlebitis - 2 (1) 1 (<1) 1 (<1) 4 (2) 3 (1.5) Thrombosis - 1 (<1) 1 (<1) - 3 (1.5) 4 (2) CVA/TIA 1 (<1) - - 1 (<1) 4 (2) 4 (2) Elevated Liver Tests** AST 11 (5) 4 (2) 30 (19) 22 (15) 32 (15) 35 (17) Alkaline Phosphatase 41 (19) 24 (11) 16 (10) 13 (9) 18 (8) 31 (15) Bilirubin 3 (1.5) 4 (2) 2 (1) 1 (<1) 2 (1) 3 (1.5) Hypercalcemia 6 (3) 6 (3) 1 (<1) - - - Other adverse reactions included leukopenia and thrombocytopenia, skin discoloration or dermatitis, constipation, dyspnea, paresis, tremor, vertigo, pruritus, anorexia, reversible corneal opacity (corneal verticulata), asthenia, alopecia, depression, jaundice, and rigors.
The incidence of AST elevations was greater in the 200 and 240 mg FARESTON dose arms than in the tamoxifen arms. Higher doses of FARESTON were also associated with an increase in nause…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs that decrease renal calcium excretion, e.g., thiazide diuretics, may increase the risk of hypercalcemia in patients receiving FARESTON. ( 7.1 ) Agents that prolong QT should be avoided. ( 7.2 ) Coadministration with a strong CYP3A4 inducer may result in a relevant decrease in FARESTON exposure and should be avoided.
( 7.3 ) Coadministration with a strong CYP3A4 inhibitor can result in a relevant increase in FARESTON exposure and should be avoided. ( 7.4 ) CYP2C9 substrates with a narrow therapeutic index such as warfarin or phenytoin with FARESTON should be used with caution and require careful monitoring. ( 7.6 )
7.1Drugs that Decrease Renal Calcium Excretion Drugs that decrease renal calcium excretion, e.g., thiazide diuretics, may increase the risk of hypercalcemia in patients receiving FARESTON.
7.2Agents that Prolong QT The administration of FARESTON with agents that have demonstrated QT prolongation as one of their pharmacodynamic effects should be avoided. Should treatment with any of these agents be required, it is recommended that therapy with FARESTON be interrupted. If interruption of treatment with FARESTON is not possible, patients who require treatment with a drug that prolongs QT should be closely monitored for prolongation of the QT interval.
Agents generally accepted to prolong QT interval include Class 1A (e.g., quinidine, procainamide, disopyramide) and Class III (e.g., amiodarone, sotalol, ibutilide, dofetilide) antiarrhythmics; certain antipsychotics (e.g., thioridazine, haloperidol); certain antidepressants (e.g., venlafaxine, amitriptyline); certain antibiotics (e.g., erythromycin, clarithromycin, levofloxacin, ofloxacin); and certain anti-emetics (e.g., ondansetron, granisetron). In patients at increased risk, electrocardiograms (ECGs) should be obtained and patients monitored as clinically indicated [see Boxed Warning and Warnings and Precautions (5.1) ] .
7.3Effect of Strong CYP3A4 Inducers on Toremifene Strong CYP3A4 enzyme inducers, such as dexamethasone, phenytoin, carbamazepine, rifampin, rifabutin, phenobarbital, St. John's Wort, lower the steady-state concentration of toremifene in serum.
7.4Effect of Strong CYP3A4 Inhibitors on Toremifene In a study of 18 healthy subjects, 80 mg toremifene once daily coadministered with 200 mg of ketoconazole twice daily increased the toremifene Cmax and AUC by 1.4- and 2.9-fold, respectively. N-demethyltoremifene Cmax and AUC were reduced by 56% and 20%, respectively. The administration of FARESTON with agents that are strong CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, clarithromycin, atazanavir, indinavir, nefazodone, nelfinavir, ritonavir, saquinavir, telithromycin, and voriconazole) increase the steady-state concentration in serum and should be avoided.
Grapefruit juice may also increase plasma concentrations of toremifene and should be avoided. Should treatment with any of these agents be required, it is recommended that therapy with FARESTON be interrupted. If interruption of treatment with FARESTON is not possible, patients who require treatment with a drug that strongly inhibits CYP3A4 should be closely monitored for prolongation of the QT interval [see Boxed Warning and Warnings and Precautions (5.1) ] .
7.5Effect of Toremifene on CYP3A4 Substrates In a study of 20 healthy subjects, 2 mg midazolam once daily (days 6 and 18) coadministered with toremifene as a 480 mg loading dose followed by 80 mg once daily for 16 days. Following coadministration on days 6 and 18 relevant increases in midazolam and α-hydroxymidazolam Cmax and AUC were not observed. Following coadministration on day 18 midazolam and α-hydroxymidazolam Cmax and AUC were reduced by less than 20%.
Clinically relevant exposure changes in sensitive substrates due to inhibition or induction of CYP3A4 by toremifene appear unlikely.
7.6Effect of Toremifene on CYP2C9 Substrates In a study of 20 healthy subjects, 500 mg tolbutamide once daily (days 7 and 1…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Nursing Mothers: Discontinue drug or nursing taking into account the importance of the drug to the mother. ( 8.2 )
8.1Pregnancy Pregnancy Category D [see Warnings and Precautions (5.7) .] Based on its mechanism of action in humans and findings of increased pregnancy loss and fetal malformation in animal studies, FARESTON can cause fetal harm when administered to a pregnant woman. Toremifene caused embryo-fetal toxicities at maternal doses that were lower than the 60 mg daily recommended human dose on a mg/m 2 basis. There are no adequate and well-controlled studies in pregnant women using FARESTON.
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus. In animal studies, toremifene crossed the placenta and accumulated in the rodent fetus. Administration of toremifene to pregnant rats during organogenesis at doses of approximately 6% the daily maximum recommended human dose of 60 mg (on a mg/m 2 basis) resulted in signs of maternal toxicity and increased preimplantation loss, increased resorptions, reduced fetal weight, and fetal anomalies.
Fetal anomalies include malformation of limbs, incomplete ossification, misshapen bones, ribs/spine anomalies, hydroureter, hydronephrosis, testicular displacement, and subcutaneous edema. Maternal toxicity may have contributed to these adverse embryo-fetal effects. Similar embryo-fetal toxicities occurred in rabbits that received toremifene at doses approximately 40% the daily recommended human dose of 60 mg (on a mg/m 2 basis).
Findings in rabbits included increased preimplantation loss, increased resorptions, and fetal anomalies, including incomplete ossification and anencephaly. Animal doses resulting in embryo-fetal toxicities were ≥1.0 mg/kg/day in rats and ≥1.25 mg/kg/day in rabbits. In rodent models of fetal reproductive tract development, toremifene produced inhibition of uterine development in female pups similar to effects seen with diethylstilbestrol (DES) and tamoxifen.
The clinical relevance of these changes is not known. Neonatal rodent studies have not been conducted to assess the potential for toremifene to cause other DES-like effects in offspring (i.e., vaginal adenosis). Vaginal adenosis in animals occurred following treatment with other drugs of this class and has been observed in women exposed to diethylstilbestrol in utero.
8.2Nursing Mothers It is not known if toremifene is excreted in human milk. Toremifene is excreted in the milk of lactating rats. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in nursing infants from FARESTON, a decision should be made to either discontinue nursing or discontinue the drug, taking into account the importance of the drug to the mother.
8.3Pediatric Use There is no indication for use of FARESTON in pediatric patients.
8.4Geriatric Use The pharmacokinetics of toremifene were studied in 10 healthy young males and 10 elderly females following a single 120 mg dose under fasting conditions. Increases in the elimination half-life (4.2 versus 7.2 days) and the volume of distribution (457 versus 627 L) of toremifene were seen in the elderly females without any change in clearance or AUC. The median ages in the three controlled studies ranged from 60 to 66 years.
No significant age-related differences in FARESTON effectiveness or safety were noted.
8.5Renal Impairment The pharmacokinetics of toremifene and N-demethyltoremifene were similar in normals and in patients with impaired kidney function.
8.6Hepatic Impairment The mean elimination half-life of toremifene was increased by less than twofold in 10 patients with hepatic impairment (cirrhosis or fibrosis) compared to subjects with normal hepatic function. The pharmacokinetics of N-demethyltoremifene were unchanged in these patients. Ten patients on anticonvulsants (phenobarbital, clonazep…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category D [see Warnings and Precautions (5.7) .] Based on its mechanism of action in humans and findings of increased pregnancy loss and fetal malformation in animal studies, FARESTON can cause fetal harm when administered to a pregnant woman. Toremifene caused embryo-fetal toxicities at maternal doses that were lower than the 60 mg daily recommended human dose on a mg/m 2 basis. There are no adequate and well-controlled studies in pregnant women using FARESTON.
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus. In animal studies, toremifene crossed the placenta and accumulated in the rodent fetus. Administration of toremifene to pregnant rats during organogenesis at doses of approximately 6% the daily maximum recommended human dose of 60 mg (on a mg/m 2 basis) resulted in signs of maternal toxicity and increased preimplantation loss, increased resorptions, reduced fetal weight, and fetal anomalies.
Fetal anomalies include malformation of limbs, incomplete ossification, misshapen bones, ribs/spine anomalies, hydroureter, hydronephrosis, testicular displacement, and subcutaneous edema. Maternal toxicity may have contributed to these adverse embryo-fetal effects. Similar embryo-fetal toxicities occurred in rabbits that received toremifene at doses approximately 40% the daily recommended human dose of 60 mg (on a mg/m 2 basis).
Findings in rabbits included increased preimplantation loss, increased resorptions, and fetal anomalies, including incomplete ossification and anencephaly. Animal doses resulting in embryo-fetal toxicities were ≥1.0 mg/kg/day in rats and ≥1.25 mg/kg/day in rabbits. In rodent models of fetal reproductive tract development, toremifene produced inhibition of uterine development in female pups similar to effects seen with diethylstilbestrol (DES) and tamoxifen.
The clinical relevance of these changes is not known. Neonatal rodent studies have not been conducted to assess the potential for toremifene to cause other DES-like effects in offspring (i.e., vaginal adenosis). Vaginal adenosis in animals occurred following treatment with other drugs of this class and has been observed in women exposed to diethylstilbestrol in utero.
🧒 Pediatric Use ▾
8.3Pediatric Use There is no indication for use of FARESTON in pediatric patients.
🧓 Geriatric Use ▾
8.4Geriatric Use The pharmacokinetics of toremifene were studied in 10 healthy young males and 10 elderly females following a single 120 mg dose under fasting conditions. Increases in the elimination half-life (4.2 versus 7.2 days) and the volume of distribution (457 versus 627 L) of toremifene were seen in the elderly females without any change in clearance or AUC. The median ages in the three controlled studies ranged from 60 to 66 years.
No significant age-related differences in FARESTON effectiveness or safety were noted.
🆘 Overdosage ▾
10 OVERDOSAGE Lethality was observed in rats following single oral doses that were ≥1000 mg/kg (about 150 times the recommended human dose on a mg/m 2 basis) and was associated with gastric atony/dilatation leading to interference with digestion and adrenal enlargement. Vertigo, headache, and dizziness were observed in healthy volunteer studies at a daily dose of 680 mg for 5 days. The symptoms occurred in two of the five subjects during the third day of the treatment and disappeared within 2 days of discontinuation of the drug.
No immediate concomitant changes in any measured clinical chemistry parameters were found. In a study in postmenopausal breast cancer patients, toremifene 400 mg/m 2 /day caused dose-limiting nausea, vomiting, and dizziness, as well as reversible hallucinations and ataxia in one patient. Theoretically, overdose may be manifested as an increase of antiestrogenic effects, such as hot flashes; estrogenic effects, such as vaginal bleeding; or nervous system disorders, such as vertigo, dizziness, ataxia, and nausea.
There is no specific antidote and the treatment is symptomatic.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Toremifene is a nonsteroidal triphenylethylene derivative. Toremifene binds to estrogen receptors and may exert estrogenic, antiestrogenic, or both activities, depending upon the duration of treatment, animal species, gender, target organ, or endpoint selected. In general, however, nonsteroidal triphenylethylene derivatives are predominantly antiestrogenic in rats and humans and estrogenic in mice.
In rats, toremifene causes regression of established dimethylbenzanthracene (DMBA)-induced mammary tumors. The antitumor effect of toremifene in breast cancer is believed to be mainly due to its antiestrogenic effects, i.e., its ability to compete with estrogen for binding sites in the cancer, blocking the growth-stimulating effects of estrogen in the tumor.
12.2Pharmacodynamics Toremifene causes a decrease in the estradiol-induced vaginal cornification index in some postmenopausal women, indicative of its antiestrogenic activity. Toremifene also has estrogenic activity as shown by decreases in serum gonadotropin concentrations (FSH and LH). Effects on Cardiac Electrophysiology The effect of 20 mg, 80 mg, and 300 mg of toremifene on QT interval was evaluated in a double-blind, randomized study in healthy male subjects aged 18 to 45 years.
The QT interval was measured at steady state of toremifene (Day 5 of dosing), including the time of peak plasma concentration (Tmax), at 13 time points (4 ECGs/time point) over 24 hours post dose in a time matched analysis. The 300 mg dose of toremifene (approximately five times the highest recommended dose 60 mg) was chosen because this dose produces exposure to toremifene that will cover the expected exposures that may result from potential drug interactions and hepatic impairment [see Drug Interactions (7.2) ] . Dose and concentration-related increases in the QTc interval and T wave changes were observed (see Table 1 ).
These effects are believed to be caused by toremifene and N-demethyltoremifene. Toremifene had no effects on heart rate, PR and QRS interval duration [see Boxed Warning and Warnings and Precautions (5.1) ] . Table 1: QTc Prolongation in Healthy Male Volunteers Treatment Arm Mean (90% CI) ΔΔQTc, ms ΔQTc > 60 ms (n, %) QTc > 500 ms (n, %) Toremifene 20 mg (N = 47) 7 (0.9, 13.6) 0 0 Toremifene 80 mg (N = 47) 26 (21.1, 31.2) 2 (4.3%) 0 Toremifene 300 mg (N = 48) 65 (60.1, 69.2) 43 (89.6%) 5 (10.4%)
12.3Pharmacokinetics Absorption - Toremifene is well absorbed after oral administration and absorption is not influenced by food. Peak plasma concentrations are obtained within 3 hours. Toremifene displays linear pharmacokinetics after single oral doses of 10 to 680 mg.
After multiple dosing, dose proportionality was observed for doses of 10 to 400 mg. Steady state concentrations were reached in about 4-6 weeks. Distribution - Toremifene has an apparent volume of distribution of 580 L and binds extensively (>99.5%) to serum proteins, mainly albumin.
Metabolism - Toremifene is extensively metabolized, principally by CYP3A4 to N-demethyltoremifene which is also antiestrogenic but with weak in vivo antitumor potency. Serum concentrations of N-demethyltoremifene are 2 to 4 times higher than toremifene at steady state. Following multiple dosing with toremifene in 20 healthy volunteers, plasma toremifene exposure was lower on Day 17 compared to Day 5 by approximately 14%.
N-demethyltoremifene exposure was higher on Day 17 compared to Day 5 by approximately 80%. Based on these data and an in vitro induction study in human hepatocytes, auto-induction of CYP3A4 by toremifene is likely. The effect of auto-induction on efficacy was likely captured following prolonged dosing in the clinical studies.
Elimination - The plasma concentration time profile of toremifene declines biexponentially after absorption with a mean distribution half-life of about 4 hours and an elimination half-life of about 5 days. Elimination half-lives of major metabolites, N-de…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Toremifene is a nonsteroidal triphenylethylene derivative. Toremifene binds to estrogen receptors and may exert estrogenic, antiestrogenic, or both activities, depending upon the duration of treatment, animal species, gender, target organ, or endpoint selected. In general, however, nonsteroidal triphenylethylene derivatives are predominantly antiestrogenic in rats and humans and estrogenic in mice.
In rats, toremifene causes regression of established dimethylbenzanthracene (DMBA)-induced mammary tumors. The antitumor effect of toremifene in breast cancer is believed to be mainly due to its antiestrogenic effects, i.e., its ability to compete with estrogen for binding sites in the cancer, blocking the growth-stimulating effects of estrogen in the tumor.
📦 How Supplied / Storage and Handling ▾
16 SUPPLIED/STORAGE AND HANDLING FARESTON Tablets, containing toremifene citrate in an amount equivalent to 60 mg of toremifene, are round, convex, unscored, uncoated, and white, or almost white. FARESTON Tablets are identified with TO 60 embossed on one side. FARESTON Tablets are available as: NDC 42747-327-30 bottles of 30 NDC 42747-327-72 samples of 7 Store at 25°C (77°F).
Excursions permitted to 15-30°C (59-86°F) [See USP Controlled Room Temperature.] Protect from heat and light.
📋 Description ▾
11 DESCRIPTION FARESTON (toremifene citrate) Tablets for oral administration each contain 88.5 mg of toremifene citrate, which is equivalent to 60 mg toremifene. FARESTON is an estrogen agonist/antagonist. The chemical name of toremifene is: 2-{p-[(Z)-4-chloro-1,2-diphenyl-1-butenyl]phenoxy}-N,N-dimethylethylamine citrate (1:1).
The structural formula is: and the molecular formula is C 26 H 28 ClNO • C 6 H 8 O 7 . The molecular weight of toremifene citrate is 598.10. The pK a is 8.0.
Water solubility at 37°C is 0.63 mg/mL and in 0.02N HCl at 37°C is 0.38 mg/mL. FARESTON is available only as tablets for oral administration. Inactive ingredients: colloidal silicon dioxide, lactose, magnesium stearate, microcrystalline cellulose, povidone, sodium starch glycolate, and starch. fareston-01
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Vaginal bleeding has been reported in patients using FARESTON. Patients should be informed about this and instructed to contact their physician if such bleeding or other gynecological symptoms (changes in vaginal discharge, pelvic pain or pressure) occur. Patients should have a gynecological examination prior to initiation of therapy and at regular intervals while on therapy.
Liver disorders including transaminits grade 3 and 4, hyperbilirubinemia with jaundice have been reported in patients using FARESTON. Patients should have liver function tests performed periodically while on therapy. FARESTON may harm the fetus and increase the risk for pregnancy loss [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1) ].
Premenopausal women using FARESTON should use nonhormonal contraception during treatment and should be apprised of the potential hazard to the fetus should pregnancy occur [see Warnings and Precautions (5.8) ] . Patients with bone metastases should be informed about the typical signs and symptoms of hypercalcemia and instructed to contact their physician for further assessment if such signs or symptoms occur. Patients who must take medications known to prolong the QT interval, or potent CYP3A4 inhibitors, should be informed of the effect of toremifene on QT interval.
Toremifene has been shown to prolong the QTc interval in a dose-related manner [see Boxed Warning , Warnings and Precautions (5.1) , and Clinical Pharmacology (12.2) ] . Specific interactions with foods that inhibit CYP3A4, including grapefruit juice, have not been studied but may increase toremifene concentrations. Patients should avoid grapefruit products and other foods that are known to inhibit CYP3A4 during FARESTON treatment.
Certain other medicines, including over-the-counter medications or herbal supplements (such as St. John's Wort) and toremifene, can reduce concentrations of co-administered drugs [see Drug Interactions (7.3) ] .