
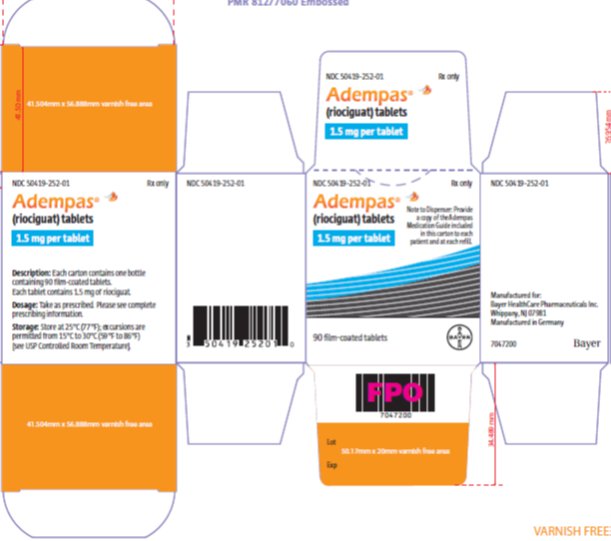
Adempas riociguat 1.5 mg Tablet, Film Coated, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Soluble Guanylate Cyclase Stimulator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Riociguat is used to treat pulmonary arterial hypertension (PAH; high blood pressure in the vessels that carry blood to the lungs). Riociguat is also used to treat chronic thromboembolic pulmonary hypertension (CTEPH; high blood pressure in the lung arteries caused by blood clots that narrow or block blood flow) in adults who cannot have surgery or for those treated with surgery who continue to have high lung blood pressure levels after surgery. Riociguat may improve the ability to exercise in people with PAH and CTEPH and may slow the worsening of symptoms in people with PAH. Riociguat is in...
Read the full MedlinePlus article ↗- Riociguat is used to treat two serious lung conditions that cause dangerously high blood pressure in the arteries going to your lungs. One is called CTEPH — where blood clots block...
- You take it three times a day, roughly evenly spaced throughout the day. The good news is that food doesn't affect how well it's absorbed, so you can take it with or without a meal...
- How do I take it — does it matter if I take it with food?
- The most common ones are headache, dizziness, an upset stomach or heartburn, nausea, and diarrhea — most of these are related to how the drug relaxes blood vessels throughout your...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Riociguat — tap one for details:
Riociguat may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $164.68 | $14,821.43 / 90 tablets |
| Medicare drug plans payPart D · Q2 2026 | $166.81 | $15,012.83 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Adempas 1.5 mgthis 50419-0252-01 | Bayer | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 12503469 ↗ | Method of use | U-2834 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2834 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2834 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2834 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2834 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2835 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2835 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2835 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2835 | Feb 18, 2034 |
| US 12503469 ↗ | Method of use | U-2835 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 10662188 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2834 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 11203593 ↗ | Drug substance | U-2835 | Feb 18, 2034 |
| US 7173037 ↗ | Drug substance | — | Dec 4, 2026 |
| US 7173037 ↗ | Drug substance | — | Dec 4, 2026 |
| US 7173037 ↗ | Drug substance | — | Dec 4, 2026 |
| US 7173037 ↗ | Drug substance | — | Dec 4, 2026 |
| US 7173037 ↗ | Drug substance | — | Dec 4, 2026 |
Is there a generic version of ADEMPAS 1.5 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 50419-0252-01 You're viewing this | 90 TABLET, FILM COATED in 1 BOTTLE (50419-252-01) | 2013-12-08 | Active |
| 50419-0252-03 | 2 BLISTER PACK in 1 PACKAGE (50419-252-03) / 21 TABLET, FILM COATED in 1 BLISTER PACK | 2013-10-08 | Active |
| 50419-0252-91 | 9 TABLET, FILM COATED in 1 BOTTLE (50419-252-91) | 2014-09-18 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 50419-0252-01?
What is the difference between NDC 50419-0252-01 and NDC 50419-0252-91?
What NDC number is used to bill for this package of Adempas riociguat 1.5 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYO-FETAL TOXICITY Adempas is contraindicated for use during pregnancy because it may cause fetal harm based on animal data [see Contraindications (4.1) , Warnings and Precautions (5.1) , and Use in Specific Populations (8.1) ]. Exclude pregnancy prior to the start of treatment with Adempas. Advise use of effective contraception prior to initiation of treatment, during treatment, and for one month after treatment with Adempas [see Dosage and Administration (2.3) , Warnings and Precautions (5.1) , and Use in Specific Populations (8.3) ].
If pregnancy is detected, discontinue Adempas as soon as possible [see Warnings and Precautions (5.1) ]. WARNING: EMBRYO-FETAL TOXICITY See full prescribing information for complete boxed warning Based on animal data, Adempas may cause fetal harm if used during pregnancy. ( 4.1 , 5.1 , 8.1 ) Exclude pregnancy before start of treatment Use effective contraception prior to initiation of treatment, during treatment, and for one month after treatment with Adempas.
( 2.3 , 5.1 , 8.6 ) When pregnancy is detected, discontinue Adempas as soon as possible. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Adempas is a soluble guanylate cyclase (sGC) stimulator indicated for the treatment of adults with: • Persistent/recurrent Chronic Thromboembolic Pulmonary Hypertension (CTEPH) (WHO Group 4) after surgical treatment or inoperable CTEPH to improve exercise capacity and WHO functional class. ( 1.1 ) • Pulmonary Arterial Hypertension (PAH) (WHO Group 1) to improve exercise capacity, improve WHO functional class and to delay clinical worsening. ( 1.2 )
1.1Chronic-Thromboembolic Pulmonary Hypertension Adempas is indicated for the treatment of adults with persistent/recurrent chronic thromboembolic pulmonary hypertension (CTEPH), (WHO Group 4) after surgical treatment, or inoperable CTEPH, to improve exercise capacity and WHO functional class [see Clinical Studies (14.1) ].
1.2Pulmonary Arterial Hypertension Adempas is indicated for the treatment of adults with pulmonary arterial hypertension (PAH), (WHO Group 1), to improve exercise capacity, WHO functional class and to delay clinical worsening. Efficacy was shown in patients on Adempas monotherapy or in combination with endothelin receptor antagonists or prostanoids. Studies establishing effectiveness included predominately patients with WHO functional class II–III and etiologies of idiopathic or heritable PAH (61%) or PAH associated with connective tissue diseases (25%) [see Clinical Studies (14.2) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Initiate treatment at 1 mg taken three times a day. ( 2.1 ) • For patients who may not tolerate the hypotensive effect of Adempas, consider a starting dose of 0.5 mg, three times a day. ( 2.1 ) • Increase dosage by 0.5 mg at intervals of no sooner than 2-weeks as tolerated to a maximum of 2.5 mg three times a day.
( 2.1 ) • Tablets may be crushed and mixed with water or soft foods for patients who have difficulty swallowing. ( 2.1 )
2.1Recommended Dosage in Adult Patients The recommended starting dosage is 1 mg taken 3 times a day. For patients who may not tolerate the hypotensive effect of Adempas, consider a starting dose of 0.5 mg taken three times a day. If systolic blood pressure remains greater than 95 mmHg and the patient has no signs or symptoms of hypotension, up-titrate the dose by 0.5 mg taken three times a day.
Dose increases should be no sooner than 2 weeks apart. The dose can be increased to the highest tolerated dosage, up to a maximum of 2.5 mg taken three times a day. If at any time, the patient has symptoms of hypotension, decrease the dosage by 0.5 mg taken three times a day.
Crushed Tablets For patients who are unable to swallow whole tablets, Adempas may be crushed and mixed with water or soft foods (such as applesauce) immediately before administration [see Clinical Pharmacology (12.3) ].
2.2Dosage Interruption If a dose is missed, advise patients to continue with the next regularly scheduled dose. In case Adempas is interrupted for 3 days or more, re-titrate Adempas.
2.3Pregnancy Testing in Females of Reproductive Potential Exclude pregnancy before initiating Adempas. [see Contraindications (4.1) , Warning and Precautions (5.1) , Use in Specific Populations (8.3) ].
2.4Use in Patients who Smoke Consider titrating to dosages higher than 2.5 mg three times a day, if tolerated, in patients who smoke. A dose decrease may be required in patients who stop smoking [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ].
2.5Strong CYP and P-gp/BCRP Inhibitors Consider a starting dose of 0.5 mg, three times a day when initiating Adempas in patients receiving strong cytochrome P450 (CYP) and P-glycoprotein/breast cancer resistance protein (P-gp/BCRP) inhibitors such as azole antimycotics (for example, ketoconazole, itraconazole) or HIV protease inhibitors (for example, ritonavir). Monitor for signs and symptoms of hypotension on initiation and on treatment with strong CYP and P-gp/BCRP inhibitors [see Warnings and Precautions (5.2) , Drug Interactions (7.2) and Clinical Pharmacology (12.3) ].
2.6Transitioning to and from Adempas • Discontinue sildenafil at least 24 hours prior to administering Adempas [see Contraindications (4.3) and Drug Interactions (7) ]. • Discontinue tadalafil at least 48 hours prior to administering Adempas [see Contraindications (4.3) and Drug Interactions (7) ]. Consider initiating Adempas at a starting dose of 0.5 mg in patients at risk of hypotension [see Dosage and Administration (2.1) ] . Monitor for signs and symptoms of hypotension on initiation. • Discontinue Adempas at least 24 hours prior to administering a PDE5-inhibitor [see Dosage and Administration (2.1) , Contraindications (4.3) , and Drug Interactions (7) ].
Monitor for signs and symptoms of hypotension on initiation.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: film-coated, round, bi-convex: • 0.5 mg, white, with "BAYER" cross on one side and "0.5" and "R" on the other side • 1 mg, pale-yellow, with "BAYER" cross on one side and "1" and "R" on the other side • 1.5 mg, yellow-orange, with "BAYER" cross on one side and "1.5" and "R" on the other side • 2 mg, pale orange, with "BAYER" cross on one side and "2" and "R" on the other side • 2.5 mg, red-orange, with "BAYER" cross on one side and "2.5" and "R" on the other side Tablets: 0.5 mg, 1 mg, 1.5 mg, 2 mg and 2.5 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Pregnancy ( 4.1 ) • Use with nitrates or nitric oxide donors in any form ( 4.2 , 7.1 ) • Use with PDE inhibitors ( 2.6 , 4.3 , 7.1 ) • Patients with concomitant use of other soluble guanylate cyclase (sGC) stimulators. ( 4.4 , 7.1 ) • Pulmonary hypertension associated with idiopathic interstitial pneumonias (PH-IIP) ( 4.5 )
4.1Pregnancy Use of Adempas is contraindicated in patients who are pregnant [see Warnings and Precautions (5.1) , Use in Specific Populations ( 8.1 )] .
4.2Nitrates and Nitric Oxide Donors Co-administration of Adempas with nitrates or nitric oxide donors (such as amyl nitrite) in any form is contraindicated [see Drug Interactions (7.1) and Clinical Pharmacology (12.2) ] .
4.3Phosphodiesterase Inhibitors Concomitant administration of Adempas with specific PDE-5 inhibitors (such as sildenafil, tadalafil, or vardenafil) or nonspecific PDE-5 inhibitors (such as dipyridamole or theophylline) is contraindicated [see Dosage and Administration (2.6), Drug Interactions ( 7.1 ) and Clinical Pharmacology ( 12.2 )]. Do not administer within 24 hours of sildenafil. Do not administer 24 hours before or within 48 hours after tadalafil.
4.4Soluble Guanylate Cyclase Stimulators Adempas is contraindicated in patients with concomitant use of other soluble guanylate cyclase (sGC) stimulators [see Drug Interactions ( 7.1 )].
4.5Pulmonary Hypertension Associated with Idiopathic Interstitial Pneumonias (PH-IIP) Adempas is contraindicated in patients with pulmonary hypertension associated with idiopathic interstitial pneumonias (PH-IIP).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Symptomatic hypotension ( 5.2 ) • Bleeding ( 5.3 ) • Pulmonary edema in patients with pulmonary veno-occlusive disease. If confirmed, discontinue treatment ( 5.4 )
5.1Embryo-Fetal Toxicity Based on data from animal reproduction studies, Adempas may cause fetal harm when administered to a pregnant patient and is contraindicated during pregnancy. The available human data for riociguat do not establish the presence or absence of major birth defects related to the use of Adempas. Counsel patients who can become pregnant on the potential risk to a fetus.
Exclude pregnancy prior to initiation of treatment with Adempas. Advise females of reproductive potential to use effective contraception prior to initiation of treatment, during treatment with Adempas and for at least one month after the last dose. When pregnancy is detected, discontinue Adempas as soon as possible [see Dosage and Administration (2.3) , Contraindications (4.1) and Use in Specific Populations (8.1 , 8.3) ] .
5.2Hypotension Adempas reduces blood pressure. Consider the potential for symptomatic hypotension or ischemia in patients with hypovolemia, severe left ventricular outflow obstruction, resting hypotension, autonomic dysfunction, or concomitant treatment with antihypertensives or strong CYP and P-gp/BCRP inhibitors [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] . Consider a dose reduction if patient develops signs or symptoms of hypotension.
5.3Bleeding In the placebo-controlled clinical trials, serious bleeding occurred in 2.4% of patients taking Adempas compared to 0% of placebo patients. Serious hemoptysis occurred in 5 (1%) patients taking Adempas compared to 0 placebo patients, including one event with fatal outcome. Serious hemorrhagic events also included 2 patients with vaginal hemorrhage, 2 with catheter site hemorrhage, and 1 each with subdural hematoma, hematemesis, and intra-abdominal hemorrhage.
5.4Pulmonary Veno-Occlusive Disease Pulmonary vasodilators may significantly worsen the cardiovascular status of patients with pulmonary veno-occlusive disease (PVOD). Therefore, administration of Adempas to such patients is not recommended. Should signs of pulmonary edema occur, the possibility of associated PVOD should be considered and, if confirmed, discontinue treatment with Adempas.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: • Embryo-Fetal Toxicity [see Warnings and Precautions (5.1) ] • Hypotension [see Warnings and Precautions (5.2) ] • Bleeding [see Warnings and Precautions (5.3) ] Adverse reactions occurring more frequently (≥3%) on Adempas compared to placebo are headache, dyspepsia/gastritis, dizziness, nausea, diarrhea, hypotension, vomiting, anemia, gastroesophageal reflux, and constipation. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Bayer HealthCare Pharmaceuticals Inc. at 1-888-842-2937 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety data described below reflect exposure to Adempas in two, randomized, double blind, placebo-controlled trials in patients with inoperable or recurrent/persistent CTEPH (CHEST-1) and treatment naive or pre-treated PAH patients (PATENT-1).
The population (Adempas: n = 490; Placebo: n = 214) was between the age of 18 and 80 years [see Clinical Studies (14.1 , 14.2) ]. The safety profile of Adempas in patients with inoperable or recurrent/persistent CTEPH (CHEST-1) and treatment naive or pre-treated PAH (PATENT-1) were similar. Therefore, adverse drug reactions (ADRs) identified from the 12 and 16 week placebo-controlled trials for PAH and CTEPH respectively were pooled, and those occurring more frequently on Adempas than placebo (≥3%) are displayed in Table 1 below.
Most adverse reactions in Table 1 can be ascribed to the vasodilatory mechanism of action of Adempas. The overall rates of discontinuation due to an adverse event in the pivotal placebo-controlled trials were 2.9% for Adempas and 5.1% for placebo (pooled data). Table 1: Adverse Reactions Occurring More Frequently (≥3%) on Adempas than Placebo (Pooled from CHEST-1 and PATENT-1) Adverse Reactions Adempas % (n=490) Placebo % (n=214) Headache 27 18 Dyspepsia and Gastritis 21 8 Dizziness 20 13 Nausea 14 11 Diarrhea 12 8 Hypotension 10 4 Vomiting 10 7 Anemia (including laboratory parameters) 7 2 Gastroesophageal reflux disease 5 2 Constipation 5 1 Other events that were seen more frequently in Adempas compared to placebo and potentially related to treatment were: palpitations, nasal congestion, epistaxis, dysphagia, abdominal distension and peripheral edema.
With longer observation in uncontrolled long-term extension studies the safety profile was similar to that observed in the placebo controlled phase 3 trials.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP and P-gp/BCRP inhibitors: For patients receiving strong CYP and P-gp/BCRP inhibitors, consider a starting dose of 0.5 mg three times a day. Monitor for hypotension. (7.2 ) • Antacids: Separate administration by at least 1 hour. ( 7.2 )
7.1Pharmacodynamic Interactions with Adempas Other Soluble Guanylate Cyclase Stimulators: Co-administration of Adempas is contraindicated in patients with use of other soluble guanylate cyclase (sGC) stimulators [see Contraindications (4.4) ] . Nitrates: Co-administration of Adempas with nitrates or nitric oxide donors (such as amyl nitrite) in any form is contraindicated because of hypotension [see Contraindications (4.2) and Clinical Pharmacology (12.2) ] . PDE Inhibitors: Co-administration of Adempas with specific PDE-5 inhibitors (such as sildenafil, tadalafil, or vardenafil) and nonspecific PDE inhibitors (such as dipyridamole or theophylline), is contraindicated because of hypotension.
Do not administer within 24 hours of sildenafil. Do not administer 24 hours before or within 48 hours after tadalafil [see Dosage and Administration (2.6) ]. Clinical experience with co-administration of Adempas and other phosphodiesterase inhibitors (for example, milrinone, cilostazole, roflumilast) is limited.
7.2Pharmacokinetic Interactions with Adempas Smoking: Plasma concentrations in smokers are reduced by 50% to 60% compared to nonsmokers. Based on pharmacokinetic modeling, for patients who are smokers, doses higher than 2.5 mg three times a day may be considered in order to match exposure seen in nonsmoking patients. Safety and effectiveness of Adempas doses higher than 2.5 mg three times a day have not been established.
A dose reduction should be considered in patients who stop smoking [see Dosage and Administration (2.4) and Clinical Pharmacology (12.3) ]. Strong CYP and P-gp/BCRP inhibitors: Concomitant use of riociguat with strong cytochrome CYP inhibitors and P-gp/BCRP inhibitors such as azole antimycotics (for example, ketoconazole, itraconazole) or HIV protease inhibitors (such as ritonavir) increase riociguat exposure and may result in hypotension. Consider a starting dose of 0.5 mg 3 times a day when initiating Adempas in patients receiving strong CYP and P-gp/BCRP inhibitors.
Monitor for signs and symptoms of hypotension on initiation and on treatment with strong CYP and P-gp/BCRP inhibitors. A dose reduction should be considered in patients who may not tolerate the hypotensive effect of riociguat [see Dosage and Administration (2.5) , Warnings and Precautions (5.2) and Clinical Pharmacology (12.3) ] . Strong CYP3A inducers: Strong inducers of CYP3A (for example, rifampin, phenytoin, carbamazepine, phenobarbital or St.
John's Wort) may significantly reduce riociguat exposure. Data are not available to guide dosing of riociguat when strong CYP3A inducers are co-administered [see Clinical Pharmacology (12.3) ]. Antacids: Antacids such as aluminum hydroxide/magnesium hydroxide decrease riociguat absorption and should not be taken within 1 hour of taking Adempas [see Clinical Pharmacology (12.3) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed. ( 8.2 ) • Renal impairment: Not recommended in patients with creatinine clearance <15 mL/min or on dialysis. ( 8.6 ) • Hepatic impairment: Not recommended in patients with severe (Child Pugh C) hepatic impairment. ( 8.7 ) • Smoking: May require dosages higher than 2.5 mg three times a day if tolerated. Dose decrease may be required in patients who stop smoking. ( 2.4 , 7.2 )
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, Adempas may cause fetal harm, including birth defects and fetal death, and miscarriage when administered to a pregnant patient and is contraindicated during pregnancy [see Contraindications (4.1) ] . Available data from published literature and post-marketing surveillance over a decade of use with riociguat have not identified an increased risk of major birth defects. However, these data are limited and do not establish the presence or absence of a drug-associated risk of major birth defects or miscarriage.
Methodological limitations of these postmarketing reports include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and missing data. These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal riociguat use. In animal reproduction studies, oral administration of riociguat to pregnant rats during organogenesis was teratogenic and embryotoxic at exposures approximately 8 times and 2 times, respectively, the human exposure.
In reproduction studies with pregnant rabbits, oral administration of riociguat during organogenesis caused abortions and fetal toxicity at exposures approximately 4 times and 13 times, respectively, the maximum recommended human dose (MRHD). Advise pregnant patients of the potential risk to a fetus [see Contraindications (4.1) ] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Animal Data In rats administered riociguat orally (1, 5, and 25 mg/kg/day) throughout organogenesis, an increased rate of cardiac ventricular-septal defect was observed at the highest dose tested.
The highest dose produced evidence of maternal toxicity (reduced body weight). Post-implantation loss was statistically significantly increased from the mid-dose of 5 mg/kg/day. Plasma exposure at the lowest dose in which no adverse effects were observed is approximately 0.4 times that in humans at the maximally recommended human dose (MRHD) of 2.5 mg three times a day based on area under the time-concentration curve (AUC) for unbound drug in rat and humans.
Plasma exposure at the highest dose (25 mg/kg/day) is approximately 8 times that in humans at the MRHD while exposure at the mid-dose (5 mg/kg/day) is approximately 2 times that in humans at the MRHD. In rabbits given doses of 0.5, 1.5 and 5 mg/kg/day, an increase in spontaneous abortions was observed starting at the middle dose of 1.5 mg/kg, and an increase in resorptions was observed at 5 mg/kg/day. Plasma exposures at these doses were 4 times and 13 times, respectively, the human exposure at the MRHD.
8.2Lactation Risk Summary There are no data on the presence of riociguat in human milk, the effects on the breastfed infant, or the effect on milk production. Riociguat is present in rat milk. Because of the potential for serious adverse reactions from Adempas, such as hypotension, in breastfed infants, advise women not to breastfeed during treatment with Adempas.
8.3Females and Males of Reproductive Potential Based on data from animal reproductive toxicity studies, Adempas may cause fetal harm, including birth defects and fetal death,…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, Adempas may cause fetal harm, including birth defects and fetal death, and miscarriage when administered to a pregnant patient and is contraindicated during pregnancy [see Contraindications (4.1) ] . Available data from published literature and post-marketing surveillance over a decade of use with riociguat have not identified an increased risk of major birth defects. However, these data are limited and do not establish the presence or absence of a drug-associated risk of major birth defects or miscarriage.
Methodological limitations of these postmarketing reports include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and missing data. These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal riociguat use. In animal reproduction studies, oral administration of riociguat to pregnant rats during organogenesis was teratogenic and embryotoxic at exposures approximately 8 times and 2 times, respectively, the human exposure.
In reproduction studies with pregnant rabbits, oral administration of riociguat during organogenesis caused abortions and fetal toxicity at exposures approximately 4 times and 13 times, respectively, the maximum recommended human dose (MRHD). Advise pregnant patients of the potential risk to a fetus [see Contraindications (4.1) ] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Animal Data In rats administered riociguat orally (1, 5, and 25 mg/kg/day) throughout organogenesis, an increased rate of cardiac ventricular-septal defect was observed at the highest dose tested.
The highest dose produced evidence of maternal toxicity (reduced body weight). Post-implantation loss was statistically significantly increased from the mid-dose of 5 mg/kg/day. Plasma exposure at the lowest dose in which no adverse effects were observed is approximately 0.4 times that in humans at the maximally recommended human dose (MRHD) of 2.5 mg three times a day based on area under the time-concentration curve (AUC) for unbound drug in rat and humans.
Plasma exposure at the highest dose (25 mg/kg/day) is approximately 8 times that in humans at the MRHD while exposure at the mid-dose (5 mg/kg/day) is approximately 2 times that in humans at the MRHD. In rabbits given doses of 0.5, 1.5 and 5 mg/kg/day, an increase in spontaneous abortions was observed starting at the middle dose of 1.5 mg/kg, and an increase in resorptions was observed at 5 mg/kg/day. Plasma exposures at these doses were 4 times and 13 times, respectively, the human exposure at the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of Adempas in pediatric patients have not been established [see Nonclinical Toxicology (13.2) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in clinical studies of Adempas, 23% were 65 and over, and 6% were 75 and over [see Clinical Studies (14) ]. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out. Elderly patients showed a higher exposure to Adempas [see Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE In cases of overdose, blood pressure should be closely monitored and supported as appropriate. Based on extensive plasma protein binding, riociguat is not expected to be dialyzable.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Riociguat is a stimulator of soluble guanylate cyclase (sGC), an enzyme in the cardiopulmonary system and the receptor for nitric oxide (NO). When NO binds to sGC, the enzyme catalyzes synthesis of the signaling molecule cyclic guanosine monophosphate (cGMP). Intracellular cGMP plays an important role in regulating processes that influence vascular tone, proliferation, fibrosis and inflammation.
Pulmonary hypertension is associated with endothelial dysfunction, impaired synthesis of nitric oxide and insufficient stimulation of the NO-sGC-cGMP pathway. Riociguat has a dual mode of action. It sensitizes sGC to endogenous NO by stabilizing the NO-sGC binding.
Riociguat also directly stimulates sGC via a different binding site, independently of NO. Riociguat stimulates the NO-sGC-cGMP pathway and leads to increased generation of cGMP with subsequent vasodilation. The active metabolite (M1) of riociguat is 1/3 to 1/10 as potent as riociguat.
12.2Pharmacodynamics There is a direct relationship between riociguat plasma concentration and hemodynamic parameters such as systemic vascular resistance, systolic blood pressure, pulmonary vascular resistance (PVR), and cardiac output [see Clinical Studies (14) ] . Hemodynamic parameters were assessed in CTEPH patients in CHEST-1 [see Clinical Studies (14.1) ] . Right heart catheterization was performed at the beginning and the end of the study period in 233 patients.
A statistically significant reduction of PVR (-246 dyn*s*cm -5 ) was shown in the Adempas group vs. placebo. Improvements in other hemodynamic parameters (not pre-specified as endpoints) are displayed in Table 2 below. Table 2: CHEST-1, Change In Hemodynamic Parameters from Baseline to Last Visit (Individual Dose Titration to Maximum 2.5 mg Three Times a Day versus placebo) Parameter (unit) Mean change LS mean difference 95% CI Adempas Placebo Pulmonary Capillary Wedge Pressure (mmHg) 0.59 0.18 0.58 –0.36 to
1.53Right Atrial Pressure (mmHg) –1.04 –0.55 –0.55 –1.72 to
0.62Pulmonary Arterial Pressure Systolic (mmHg) –6.84 0.95 –7.52 –10.88 to –4.16 Pulmonary Arterial Pressure Diastolic (mmHg) –3.05 0.67 –3.62 –5.30 to –1.95 Pulmonary Arterial Pressure Mean (mmHg) –4.31 0.76 –4.96 –6.75 to –3.16 Mean Arterial Pressure (mmHg) –9.27 –0.29 –9.15 –11.83 to –6.46 Mixed Venous Oxygen Saturation (%) 2.95 –0.44 3.85 1.46 to
6.25Cardiac Output (L/min) 0.81 –0.03 0.86 0.59 to
1.12Cardiac Index (L/min/m 2 ) 0.45 –0.01 0.47 0.33 to
0.62Pulmonary Vascular Resistance (dyn*s*cm -5 ) –226 23.1 –246 –303 to –190 Pulmonary Vascular Resistance Index (dyn*s*cm -5 *m 2 ) –397 48.3 –449 –554 to –344 Systemic Vascular Resistance (dyn*s*cm -5 ) –445 16.6 –478 –602 to –354 Systemic Vascular Resistance Index (dyn*s*cm -5 *m 2 ) –799 53.7 –914 –1141 to –687 Hemodynamic parameters were assessed in PAH patients in PATENT-1 [see Clinical Studies (14.2) ] . Right heart catheterization was performed at the beginning and the end of the study period in 339 patients.
A statistically significant reduction of PVR (-226 dyn*sec*cm -5 ) was shown in the Adempas individual titration group (to maximum dose of 2.5 mg three times a day) vs. placebo. Improvement in other relevant hemodynamic parameters (not pre-specified as endpoints) for the individual dose titration group versus placebo are displayed in Table 3. Table 3: PATENT-1, Change in Hemodynamic Parameters from Baseline to Last Visit (Individual Dose Titration to Maximum 2.5 mg Three Times a Day versus Placebo) Parameter (unit) Mean change LS mean difference 95% CI Adempas Placebo Pulmonary Capillary Wedge Pressure (mmHg) 1.08 0.46 0.41 –0.36 to
1.18Right Atrial Pressure (mmHg) –0.20 0.97 –1.01 –2.15 to
0.13Pulmonary Arterial Pressure Systolic (mmHg) –5.39 0.78 –6.73 –9.43 to –4.04 Pulmonary Arterial Pressure Diastolic (mmHg) –3.19 –1.12 –2.41 –4.15 to –0.68 Pulmonary Arterial Pressure mean (mmHg) –3.93 –0.5 –3.83 –5.61 to –2.06 Mean Arterial Pressure (mmHg)…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Riociguat is a stimulator of soluble guanylate cyclase (sGC), an enzyme in the cardiopulmonary system and the receptor for nitric oxide (NO). When NO binds to sGC, the enzyme catalyzes synthesis of the signaling molecule cyclic guanosine monophosphate (cGMP). Intracellular cGMP plays an important role in regulating processes that influence vascular tone, proliferation, fibrosis and inflammation.
Pulmonary hypertension is associated with endothelial dysfunction, impaired synthesis of nitric oxide and insufficient stimulation of the NO-sGC-cGMP pathway. Riociguat has a dual mode of action. It sensitizes sGC to endogenous NO by stabilizing the NO-sGC binding.
Riociguat also directly stimulates sGC via a different binding site, independently of NO. Riociguat stimulates the NO-sGC-cGMP pathway and leads to increased generation of cGMP with subsequent vasodilation. The active metabolite (M1) of riociguat is 1/3 to 1/10 as potent as riociguat.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Adempas (riociguat) tablets are film-coated, round, and debossed with the "Bayer cross" on one side. Color Debossing Side 2 NDC 50419-xxx-xx Bottle of 9 Bottle of 90 Blister of 42 0.5 mg White
0.5R 250-91 250-01 250-03 1 mg Pale yellow 1 R 251-91 251-01 251-03 1.5 mg Yellow-orange
1.5R 252-91 252-01 252-03 2 mg Pale orange 2 R 253-91 253-01 253-03 2.5 mg Red-orange
2.5 R 254-91 254-01 254-03
16.2Storage and Handling Store at 25°C (77°F); excursions are permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Adempas (riociguat) is a soluble guanylate cyclase stimulator tablet for oral administration. Riociguat is methyl 4,6-diamino-2-[1-(2-fluorobenzyl)-1H-pyrazolo [3,4-b]pyridin-3-yl]-5-pyrimidinyl(methyl)carbamate with the following structural formula: C 20 H 19 FN 8 O 2 Riociguat is a white to yellowish, crystalline, non-hygroscopic substance with a molecular weight of 422.42 g/mol. In solid form it is stable to temperature, light, and humidity.
The solubility at 25°C in water: 4 mg/L, in ethanol: 800 mg/L, in
0.1HCl (pH 1): 250 mg/L and in buffer (phosphate) pH 7: 3 mg/L. In the pH range of 2 to 4 the solubility showed strong pH-dependency. Solubility increases at lower pH values.
Each round film-coated tablet contains 0.5 mg (1.0, 1.5, 2.0, 2.5 mg) riociguat. The inactive ingredients are cellulose microcrystalline, crospovidone, hypromellose 5cP, lactose monohydrate, magnesium stearate, sodium laurylsulfate, hydroxypropylcellulose, hypromellose 3cP, propylene glycol, and titanium dioxide. Adempas 1, 1.5, 2, and 2.5 mg tablets contain, in addition, ferric oxide yellow.
Adempas 2 and 2.5 mg tablets contain, in addition, ferric oxide red. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Embryo-Fetal Toxicity Instruct patients on the risk of fetal harm when Adempas is used during pregnancy [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] . Educate and counsel females of reproductive potential to use effective contraception prior to initiation of treatment with Adempas, during treatment, and for one month after stopping treatment.
Instruct patients to contact their healthcare provider immediately if they suspect they may be pregnant. Educate and counsel females of reproductive potential on the use of emergency contraception in the event of unprotected sex or contraceptive failure. Advise pre-pubertal females to report any changes in their reproductive status immediately to their prescriber.
Lactation Advise women not to breastfeed during treatment with Adempas [see Use in Specific Populations (8.2) ] . Other Risks Associated with Adempas • Inform patients of the contraindication of Adempas with nitrates or nitric oxide donors or PDE-5 inhibitors. • Advise patients about the potential risks/signs of hemoptysis and to report any potential signs of hemoptysis to their physicians. • Instruct patients on the dosing, titration, and maintenance of Adempas. • Advise patients regarding activities that may impact the pharmacology of Adempas (strong multi pathway CYP inhibitors and P-gp/BCRP inhibitors and smoking).
Instruct patients to report all current medications and new medications to their physician. • Advise patients that antacids should not be taken within 1 hour of taking Adempas. • Inform patients that Adempas can cause dizziness, which can affect the ability to drive and use machines [see Adverse Reactions (6.1) ] . Advise patients to be aware of how they react to Adempas before driving or operating machinery, and if needed, consult their physician. Patients should consult their physicians if dizziness gets worse with Adempas.
💬 Medication Guide ▾
MEDICATION GUIDE Adempas (a-dem-pahs) (riociguat) tablets Read this Medication Guide before you start taking Adempas and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking to your doctor about your medical condition or your treatment.
What is the most important information I should know about Adempas? • Serious birth defects. Adempas may cause serious birth defects if taken during pregnancy. Females should not be pregnant when they start taking Adempas or become pregnant during treatment with Adempas.
Females who are able to get pregnant should have a negative pregnancy status before beginning treatment with Adempas. Females who are able to get pregnant are females who: Have entered puberty, even if they have not started their period, and Have a uterus, and Have not gone through menopause (have not had a period for at least 12 months for natural reasons, or who have had their ovaries removed) Females who are not able to get pregnant are females who: Have not yet entered puberty, or Do not have a uterus, or Have gone through menopause (have not had a period for at least 12 months for natural reasons, or who have had their ovaries removed) Females who are able to get pregnant should use effective birth control before starting treatment with Adempas, during treatment with Adempas and for 1 month after stopping Adempas because the medicine may still be in the body.
Talk with your doctor or gynecologist (a doctor who specializes in female reproduction) to find out about options for effective forms of birth control that you may use to prevent pregnancy during treatment with Adempas. If you decide that you want to change the form of birth control that you use, talk with your doctor or gynecologist to be sure that you choose another effective form of birth control. Do not have unprotected sex.
Talk to your doctor or pharmacist right away if you have unprotected sex or if you think your birth control has failed. Your doctor may talk with you about using emergency birth control. Tell your doctor right away if you miss a menstrual period or think you may be pregnant for any reason.
If you are the parent or caregiver of a female child who started taking Adempas before reaching puberty, you should check your child regularly to see if she is developing signs of puberty. Tell your doctor right away if you notice that she is developing breast buds or any pubic hair. Your doctor should decide if your child has reached puberty.
Your child may reach puberty before having her first menstrual period. If you are a female who can become pregnant, talk to your doctor to understand the benefits and risks of Adempas. What is Adempas?
Adempas is a prescription medicine used to treat adults with: • chronic thromboembolic pulmonary hypertension (CTEPH) • treated with surgery but who continue to have high pulmonary blood pressure (persistent) or it comes back after surgery (recurrent), or • that cannot be treated with surgery. • CTEPH is a type of high blood pressure in the arteries of your lungs caused by blood clots that narrow or block blood flow. Adempas can improve your ability to exercise and can help to improve some of your symptoms. • pulmonary arterial hypertension (PAH) • PAH is a type of high blood pressure in the arteries of your lungs.
Adempas can improve your ability to exercise, improve some of your symptoms, and help slow down the worsening of your physical condition. • It is unknown if Adempas is safe and effective in children. Who should not take Adempas? Do not take Adempas if: • you are pregnant, plan to become pregnant, or become pregnant during treatment with Adempas .
Adempas can cause serious birth defects. (See the Medication Guide section above called "What is the most important information I should know about Adempas?") • you take : • another medicine called a soluble guanylate cyclase stimulator (sGC). Ask your healthcare provider if you are not sure if you are taki…