
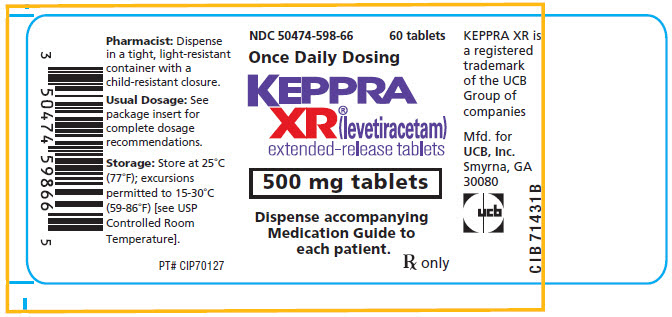
Keppra XR levetiracetam 500 mg Tablet, Film Coated, Extended Release, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Other antiepileptics class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Levetiracetam is used alone and along with other medications to control partial-onset seizures (seizures that involve only one part of the brain) in adults, children, and infants 1 month of age or older. Levetiracetam is also used in combination with other medications to treat seizure in adults and children 12 years of age or older with juvenile myoclonic epilepsy. Levetiracetam is also used in combination with other medications to treat primary generalized tonic-clonic seizures (formerly known as a grand mal seizure; seizure that involves the entire body) in adults and children 6 years of age...
Read the full MedlinePlus article ↗- Levetiracetam is an anti-seizure medicine. Depending on the product and your age, it can be used to treat partial-onset seizures (seizures starting in one part of the brain), myocl...
- What is levetiracetam actually used for?
- It can, especially when you first start taking it. Drowsiness, fatigue, and dizziness are among the most common side effects and tend to be most noticeable in the first few weeks....
- Will levetiracetam make me feel tired or foggy?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Levetiracetam — tap one for details:
Levetiracetam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Y4S76JWI15
Methyl alcohol, also called methanol, is a simple organic solvent. It helps dissolve and carry active ingredients in liquid medicines, and helps the product mix evenly.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.031 | $541.85 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $8.66 | $519.66 / 60 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levetiracetam 500 mg 43547-0345-06 | Solco | 60 tablets | $0.169 | AB | Availability likely | save 98% |
| Levetiracetam 500 mg 68001-0113-06 | BluePoint | 60 tablets | $0.169 | AB | Availability likely | save 98% |
| Levetiracetam ER 500 mg 69367-0332-60 | Westminster | 60 tablets | $0.169 | AB | Availability likely | save 98% |
| Keppra XR 500 mgthis 50474-0598-66 | UCB, | 60 tablets | $9.031 | AB | Availability likely | — |
| Levetiracetam 500 mg 13668-0272-05 | Torrent | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam Extended-Release 500 mg 50228-0189-05 | ScieGen | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam Extended-Release 500 mg 60429-0349-60 | Golden | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 60505-3280-05 | Apotex | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 63629-9847-01 | Bryant | 21 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 68180-0117-02 | Lupin | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 70518-4005-01 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam ER 500 mg 70518-4125-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam ER 500 mg 71205-0728-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam ER 500 mg 71205-0880-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam ER 500 mg 72189-0510-60 | Direct_Rx | 60 tablets | — | AB | FDA listed | — |
| LEVETIRACETAM Extended-release 500 mg 81665-0101-12 | Omnivium | 120 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7858122 ↗ | Drug product | — | Sep 17, 2028 |
| US 7858122 ↗ | Drug product | — | Sep 17, 2028 |
Is there a generic version of KEPPRA XR 500 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 50474-0598-66 You're viewing this | 60 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE, PLASTIC (50474-598-66) | 2008-09-24 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE KEPPRA XR ® is indicated for the treatment of partial-onset seizures in patients 12 years of age and older. KEPPRA XR is indicated for the treatment of partial-onset seizures in patients 12 years of age and older ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initiate treatment with a dose of 1000 mg once daily; increase by 1000 mg every 2 weeks to a maximum recommended dose of 3000 mg once daily ( 2 ) See full prescribing information for use in patients with impaired renal function ( 2.1 )
2.1Recommended Dosing For adults and adolescent patients, the recommended dosing for monotherapy and adjunctive therapy is the same; as outlined below. Adults and Adolescents 12 Years of Age and Older Weighing 50 kg or More Initiate treatment with a dose of 1000 mg once daily. The once daily dosage may be adjusted in increments of 1000 mg every 2 weeks to a maximum recommended daily dose of 3000 mg/day once daily.
Administration KEPPRA XR is administered once daily. KEPPRA XR tablets should be swallowed whole. The tablets should not be chewed, broken, or crushed.
2.2Dosage Adjustments in Adult Patients with Renal Impairment KEPPRA XR dosing must be individualized according to the patient's renal function status. Recommended dosage adjustments for adults are shown in Table 1. In order to calculate the dose recommended for patients with renal impairment, creatinine clearance adjusted for body surface area must be calculated.
To do this, an estimate of the patient's creatinine clearance (CLcr) in mL/min must first be calculated using the following formula: CLcr= [140-age (years)] × weight (kg) -------------------------------------- (× 0.85 for female patients) 72 × serum creatinine (mg/dL) Then CLcr is adjusted for body surface area (BSA) as follows: CLcr (mL/min/1.73m 2 )= CLcr (mL/min) ------------------------- ×
1.73BSA subject (m 2 ) Table 1: Dosage Adjustment Regimen for Adult Patients with Renal Impairment Group Creatinine Clearance (mL/min/1.73m 2 ) Dosage (mg) Frequency Normal > 80 1000 to 3000 Every 24 hours Mild 50 – 80 1000 to 2000 Every 24 hours Moderate 30 – 50 500 to 1500 Every 24 hours Severe < 30 500 to 1000 Every 24 hours
2.3Discontinuation of KEPPRA XR Avoid abrupt withdrawal from KEPPRA XR in order to reduce the risk of increased seizure frequency and status epilepticus [see Warnings and Precautions (5.8) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS KEPPRA XR tablets are white, oblong-shaped, film-coated extended-release tablets imprinted in red with "UCB 500XR" on one side and contain 500 mg levetiracetam. KEPPRA XR tablets are white, oblong-shaped, film-coated extended-release tablets imprinted in red with "UCB 750XR" on one side and contain 750 mg levetiracetam. 500 mg white, film-coated extended-release tablet ( 3 ) 750 mg white, film-coated extended-release tablet ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS KEPPRA XR is contraindicated in patients with a hypersensitivity to levetiracetam . Reactions have included anaphylaxis and angioedema [see Warnings and Precautions (5.4) ] . Known hypersensitivity to levetiracetam; angioedema and anaphylaxis have occurred ( 4 , 5.4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Behavioral abnormalities including psychotic symptoms, suicidal ideation, irritability, and aggressive behavior have been observed; monitor patients for psychiatric signs and symptoms ( 5.1 ) Suicidal Behavior and Ideation: Monitor patients for new or worsening depression, suicidal thoughts/behavior, and/or unusual changes in mood or behavior ( 5.2 ) Monitor for somnolence and fatigue and advise patients not to drive or operate machinery until they have gained sufficient experience on KEPPRA XR ( 5.3 ) Serious Dermatological Reactions: Discontinue KEPPRA at the first sign of rash unless clearly not drug related ( 5.5 ) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity: Discontinue if no alternative etiology ( 5.6 ) Coordination Difficulties: Monitor for ataxia, abnormal gait, and incoordination.
Advise patients to not drive or operate machinery until they have gained experience on KEPPRA ( 5.7 ) Withdrawal Seizures: KEPPRA XR must be gradually withdrawn ( 5.8 )
5.1Behavioral Abnormalities and Psychotic Symptoms KEPPRA XR may cause behavioral abnormalities and psychotic symptoms. Patients treated with KEPPRA XR should be monitored for psychiatric signs and symptoms. Behavioral abnormalities KEPPRA XR Tablets A total of 7% of KEPPRA XR-treated patients experienced non-psychotic behavioral disorders (reported as irritability and aggression) compared to 0% of placebo-treated patients.
Irritability was reported in 7% of KEPPRA XR-treated patients. Aggression was reported in 1% of KEPPRA XR-treated patients. No patient discontinued treatment or had a dose reduction as a result of these adverse reactions.
The number of patients exposed to KEPPRA XR was considerably smaller than the number of patients exposed to immediate-release KEPPRA tablets in controlled trials. Therefore, certain adverse reactions observed in the immediate-release KEPPRA controlled trials will likely occur in patients receiving KEPPRA XR. Immediate-Release KEPPRA Tablets A total of 13% of adult patients and 38% of pediatric patients (4 to 16 years of age) treated with immediate-release KEPPRA experienced non-psychotic behavioral symptoms (reported as aggression, agitation, anger, anxiety, apathy, depersonalization, depression, emotional lability, hostility, hyperkinesias, irritability, nervousness, neurosis, and personality disorder), compared to 6% and 19% of adult and pediatric patients on placebo.
A randomized, double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioral effects of immediate-release KEPPRA tablets as adjunctive therapy in pediatric patients (4 to 16 years of age). An exploratory analysis suggested a worsening in aggressive behavior in patients treated with immediate-release KEPPRA tablets in that study [see Use in Specific Populations (8.4) ] . A total of 1.7% of adult patients treated with immediate-release KEPPRA discontinued treatment due to behavioral adverse reactions, compared to 0.2% of placebo-treated patients.
The treatment dose was reduced in 0.8% of adult patients treated with immediate-release KEPPRA, compared to 0.5% of placebo-treated patients. Overall, 11% of pediatric patients treated with immediate-release KEPPRA experienced behavioral symptoms associated with discontinuation or dose reduction, compared to 6.2% of placebo-treated pediatric patients. One percent of adult patients and 2% of pediatric patients (4 to 16 years of age) treated with immediate-release KEPPRA experienced psychotic symptoms, compared to 0.2% and 2%, respectively, in adult and placebo-treated pediatric patients.
In the controlled study that assessed the neurocognitive and behavioral effects of immediate-release KEPPRA in pediatric patients 4 to 16 years of age, 1.6% KEPPRA-treated patients experienced paranoia, compared to no placebo-treated patients. There were 3.1% patients treated with immediate-release KEPPRA who experienced confusional state, comp…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more details in other sections of labeling: Behavioral abnormalities and Psychotic Symptoms [see Warnings and Precautions (5.1) ] Suicidal Behavior and Ideation [see Warnings and Precautions (5.2) ] Somnolence and Fatigue [see Warnings and Precautions (5.3) ] Anaphylaxis and Angioedema [see Warnings and Precautions (5.4) ] Serious Dermatological Reactions [see Warnings and Precautions (5.5) ] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions (5.6) ] Coordination Difficulties [see Warnings and Precautions (5.7) ] Hematologic Abnormalities [see Warnings and Precautions (5.9) ] Most common adverse reactions (incidence ≥5% more than placebo) include: somnolence and irritability ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact UCB, Inc. at (844) 599-CARE (2273) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. KEPPRA XR Tablets In the controlled clinical study in patients with partial-onset seizures [see Clinical Studies (14.1) ], the most common adverse reactions in patients receiving KEPPRA XR in combination with other AEDs, for events with rates greater than placebo, were irritability and somnolence.
Table 3 lists adverse reactions that occurred in at least 5% of epilepsy patients receiving KEPPRA XR in the placebo-controlled study and were numerically more common than in patients treated with placebo. In this study, either KEPPRA XR or placebo was added to concurrent AED therapy. Table 3: Adverse Reactions in the Placebo-Controlled, Adjunctive Study in Patients Experiencing Partial-Onset Seizures KEPPRA XR (N=77) % Placebo (N=79) % Influenza 8 4 Somnolence 8 3 Irritability 7 0 Nasopharyngitis 7 5 Dizziness 5 3 Nausea 5 3 Discontinuation or Dose Reduction in the KEPPRA XR Controlled Clinical Study In the controlled clinical study, 5% of patients receiving KEPPRA XR and 3% receiving placebo discontinued as a result of an adverse reaction.
The adverse reactions that resulted in discontinuation and that occurred more frequently in KEPPRA XR-treated patients than in placebo-treated patients were asthenia, epilepsy, mouth ulceration, rash, and respiratory failure. Each of these adverse reactions led to discontinuation in a KEPPRA XR-treated patient and no placebo-treated patients. Immediate-Release KEPPRA Tablets Table 4 lists the adverse reactions in the controlled studies of immediate-release KEPPRA tablets in adult patients experiencing partial-onset seizures [ see Clinical Studies (14.2) ].
Although the pattern of adverse reactions in the KEPPRA XR study seems somewhat different from that seen in partial-onset seizure controlled studies for immediate-release KEPPRA tablets, this is possibly due to the much smaller number of patients in this study compared to the immediate-release tablet studies. The adverse reactions for KEPPRA XR are expected to be similar to those seen with immediate-release KEPPRA tablets. Adults In controlled clinical studies of immediate-release KEPPRA tablets as adjunctive therapy to other AEDs in adults with partial-onset seizures, the most common adverse reactions, for events with rates greater than placebo, were somnolence, asthenia, infection, and dizziness.
Table 4 lists adverse reactions that occurred in at least 1% of adult epilepsy patients receiving immediate-release KEPPRA tablets in placebo-controlled studies and were numerically more common than in patients treated with placebo. In these studies, either immediate-release KEPPRA tablets or placebo was added to concurrent AED therapy. Table 4: Adverse Reactions in Pooled Placebo-Controlled, Adjunctive Studies in Adu…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Plasma levels of levetiracetam may be decreased and therefore need to be monitored closely during pregnancy. Based on animal data, may cause fetal harm ( 5.10 , 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), including KEPPRA XR, during pregnancy. Encourage women who are taking KEPPRA XR during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Prolonged experience with KEPPRA in pregnant women has not identified a drug-associated risk of major birth defects or miscarriage, based on published literature, which includes data from pregnancy registries and reflects experience over two decades [see Human Data ] .
In animal studies, levetiracetam produced developmental toxicity (increased embryofetal and offspring mortality, increased incidences of fetal structural abnormalities, decreased embryofetal and offspring growth, neurobehavioral alterations in offspring) at doses similar to human therapeutic doses [see Animal Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations KEPPRA XR levels may decrease during pregnancy [see Warnings and Precautions (5.10) ]. Physiological changes during pregnancy may affect levetiracetam concentration. Decrease in levetiracetam plasma concentrations has been observed during pregnancy.
This decrease is more pronounced during the third trimester. Dose adjustments may be necessary to maintain clinical response. Data Human Data While available studies cannot definitively establish the absence of risk, data from the published literature and pregnancy registries have not established an association with levetiracetam use during pregnancy and major birth defects or miscarriage.
Animal Data When levetiracetam (0, 400, 1200, or 3600 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, reduced fetal weights and increased incidence of fetal skeletal variations were observed at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on embryofetal developmental in rats (1200 mg/kg/day) is approximately 4 times the maximum recommended human dose (MRHD) of 3000 mg on a body surface area (mg/m 2 ) basis.
Oral administration of levetiracetam (0, 200, 600, or 1800 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality and incidence of fetal skeletal variations at the mid and high dose and decreased fetal weights and increased incidence of fetal malformations at the high dose, which was associated with maternal toxicity. The no-effect dose for adverse effects on embryofetal development in rabbits (200 mg/kg/day) is approximately equivalent to the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam (0, 70, 350, or 1800 mg/kg/day) to female rats throughout pregnancy and lactation led to an increased incidence of fetal skeletal variations, reduced fetal body weight, and decreased growth in offspring at the mid and high doses and increased pup mortality and neurobehavioral alterations in offspring at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on pre- and postnatal development in rats (70 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam to rats during the latter part of gestation and throughout lactation produced no adverse developmental or maternal effects at doses of up to 1800 mg/kg/day (6 times the MRHD on a mg/m 2 basis).
8.2 Lactation Ris…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), including KEPPRA XR, during pregnancy. Encourage women who are taking KEPPRA XR during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Prolonged experience with KEPPRA in pregnant women has not identified a drug-associated risk of major birth defects or miscarriage, based on published literature, which includes data from pregnancy registries and reflects experience over two decades [see Human Data ] .
In animal studies, levetiracetam produced developmental toxicity (increased embryofetal and offspring mortality, increased incidences of fetal structural abnormalities, decreased embryofetal and offspring growth, neurobehavioral alterations in offspring) at doses similar to human therapeutic doses [see Animal Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations KEPPRA XR levels may decrease during pregnancy [see Warnings and Precautions (5.10) ]. Physiological changes during pregnancy may affect levetiracetam concentration. Decrease in levetiracetam plasma concentrations has been observed during pregnancy.
This decrease is more pronounced during the third trimester. Dose adjustments may be necessary to maintain clinical response. Data Human Data While available studies cannot definitively establish the absence of risk, data from the published literature and pregnancy registries have not established an association with levetiracetam use during pregnancy and major birth defects or miscarriage.
Animal Data When levetiracetam (0, 400, 1200, or 3600 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, reduced fetal weights and increased incidence of fetal skeletal variations were observed at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on embryofetal developmental in rats (1200 mg/kg/day) is approximately 4 times the maximum recommended human dose (MRHD) of 3000 mg on a body surface area (mg/m 2 ) basis.
Oral administration of levetiracetam (0, 200, 600, or 1800 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality and incidence of fetal skeletal variations at the mid and high dose and decreased fetal weights and increased incidence of fetal malformations at the high dose, which was associated with maternal toxicity. The no-effect dose for adverse effects on embryofetal development in rabbits (200 mg/kg/day) is approximately equivalent to the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam (0, 70, 350, or 1800 mg/kg/day) to female rats throughout pregnancy and lactation led to an increased incidence of fetal skeletal variations, reduced fetal body weight, and decreased growth in offspring at the mid and high doses and increased pup mortality and neurobehavioral alterations in offspring at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on pre- and postnatal development in rats (70 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam to rats during the latter part of gestation and throughout lactation produced no adverse developmental or maternal effects at doses of up to 1800 mg/kg/day (6 times the MRHD on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in patients 12 years of age and older have been established based on pharmacokinetic data in adults and adolescents using KEPPRA XR and efficacy and safety data in controlled pediatric studies using immediate-release KEPPRA [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.1) ]. Safety and effectiveness in pediatric patients below the age of 12 have not been established. A 3-month, randomized, double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioral effects of immediate-release KEPPRA as adjunctive therapy in 98 pediatric patients with inadequately controlled partial seizures, ages 4 to 16 years (KEPPRA N=64; placebo N=34).
The target dose of immediate-release KEPPRA was 60 mg/kg/day. Neurocognitive effects were measured by the Leiter-R Attention and Memory (AM) Battery, which assesses various aspects of a child's memory and attention. Although no substantive differences were observed between the placebo- and KEPPRA-treated groups in the median change from baseline in this battery, the study was not adequate to assess formal statistical non-inferiority between the drug and placebo.
The Achenbach Child Behavior Checklist (CBCL/6-18), a standardized validated tool used to assess a child's competencies and behavioral/emotional problems, was also assessed in this study. An analysis of the CBCL/6-18 indicated a worsening in aggressive behavior, one of the eight syndrome scores, in patients treated with KEPPRA [see Warnings and Precautions (5.1) ] . Juvenile Animal Toxicity Data Studies of levetiracetam in juvenile rats (dosed on postnatal days 4 through 52) and dogs (dosed from postnatal weeks 3 through 7) at doses of up to 1800 mg/kg/day (approximately 7 and 24 times, respectively, the maximum recommended pediatric dose of 60 mg/kg/day on a mg/m 2 basis) did not demonstrate adverse effects on postnatal development.
🧓 Geriatric Use ▾
8.5Geriatric Use There were insufficient numbers of elderly subjects in controlled trials of epilepsy to adequately assess the effectiveness of KEPPRA XR in these patients. It is expected that the safety of KEPPRA XR in elderly patients 65 and over would be comparable to the safety observed in clinical studies of immediate-release KEPPRA tablets. There were 347 subjects in clinical studies of immediate-release KEPPRA that were 65 and over.
No overall differences in safety were observed between these subjects and younger subjects. There were insufficient numbers of elderly subjects in controlled trials of epilepsy to adequately assess the effectiveness of immediate-release KEPPRA in these patients. Levetiracetam is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs, Symptoms and Laboratory Findings of Acute Overdosage in Humans The signs and symptoms for KEPPRA XR overdose are expected to be similar to those seen with immediate-release KEPPRA tablets. The highest known dose of oral immediate-release KEPPRA received in the clinical development program was 6000 mg/day. Other than drowsiness, there were no adverse reactions in the few known cases of overdose in clinical trials.
Cases of somnolence, agitation, aggression, depressed level of consciousness, respiratory depression and coma were observed with immediate-release KEPPRA overdoses in postmarketing use.
10.2Management of Overdose There is no specific antidote for overdose with KEPPRA XR. If indicated, elimination of unabsorbed drug should be attempted by emesis or gastric lavage; usual precautions should be observed to maintain airway. General supportive care of the patient is indicated including monitoring of vital signs and observation of the patient's clinical status.
A Certified Poison Control Center should be contacted for up to date information on the management of overdose with KEPPRA XR.
10.3Hemodialysis Standard hemodialysis procedures result in significant clearance of levetiracetam (approximately 50% in 4 hours) and should be considered in cases of overdose. Although hemodialysis has not been performed in the few known cases of overdose, it may be indicated by the patient's clinical state or in patients with significant renal impairment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism(s) by which levetiracetam exerts its antiepileptic effect is unknown. A saturable and stereoselective neuronal binding site in rat brain tissue has been described for levetiracetam. Experimental data indicate that this binding site is the synaptic vesicle protein SV2A, thought to be involved in the regulation of vesicle exocytosis.
Although the molecular significance of levetiracetam binding to synaptic vesicle protein SV2A is not understood, levetiracetam and related analogs showed a rank order of affinity for SV2A which correlated with the potency of their antiseizure activity in audiogenic seizure-prone mice. These findings suggest that the interaction of levetiracetam with the SV2A protein may contribute to the antiepileptic mechanism of action of the drug.
12.2Pharmacodynamics Effects on QTc Interval The effects of KEPPRA XR on QTc prolongation is expected to be the same as that of immediate-release KEPPRA. The effect of immediate-release KEPPRA on QTc prolongation was evaluated in a randomized, double-blind, positive-controlled (moxifloxacin 400 mg) and placebo-controlled crossover study of KEPPRA (1000 mg or 5000 mg) in 52 healthy subjects. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 milliseconds.
Therefore, there was no evidence of significant QTc prolongation in this study.
12.3Pharmacokinetics Overview Bioavailability of KEPPRA XR tablets is similar to that of the immediate-release KEPPRA tablets. The pharmacokinetics (AUC and C max ) were shown to be dose proportional after single dose administration of 1000 mg, 2000 mg, and 3000 mg extended-release levetiracetam. Plasma half-life of extended-release levetiracetam is approximately 7 hours.
Levetiracetam is almost completely absorbed after oral administration. The pharmacokinetics of levetiracetam are linear and time-invariant, with low intra- and inter-subject variability. Levetiracetam is not significantly protein-bound (<10% bound) and its volume of distribution is close to the volume of intracellular and extracellular water.
Sixty-six percent (66%) of the dose is renally excreted unchanged. The major metabolic pathway of levetiracetam (24% of dose) is an enzymatic hydrolysis of the acetamide group. It is not liver cytochrome P450 dependent.
The metabolites have no known pharmacological activity and are renally excreted. Plasma half-life of levetiracetam across studies is approximately 6-8 hours. The half-life is increased in the elderly (primarily due to impaired renal clearance) and in subjects with renal impairment.
The pharmacokinetics of levetiracetam are similar when used as monotherapy or as adjunctive therapy for the treatment of partial-onset seizures. Absorption and Distribution Extended-release levetiracetam peak plasma concentrations occur in about 4 hours. The time to peak plasma concentrations is about 3 hours longer with extended-release levetiracetam than with immediate-release tablets.
Single administration of two 500 mg extended-release levetiracetam tablets once daily produced comparable maximal plasma concentrations and area under the plasma concentration versus time as did the administration of one 500 mg immediate-release tablet twice daily in fasting conditions. After multiple dose extended-release levetiracetam tablets intake, extent of exposure (AUC 0-24 ) was similar to extent of exposure after multiple dose immediate-release tablets intake. C max and C min were lower by 17% and 26% after multiple dose extended-release levetiracetam tablets intake in comparison to multiple dose immediate-release tablets intake.
Intake of a high fat, high calorie breakfast before the administration of extended-release levetiracetam tablets resulted in a higher peak concentration, and longer median time to peak. The median time to peak (T max ) was 2 hours longer in the fed state. Two 750 mg extended-release leve…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism(s) by which levetiracetam exerts its antiepileptic effect is unknown. A saturable and stereoselective neuronal binding site in rat brain tissue has been described for levetiracetam. Experimental data indicate that this binding site is the synaptic vesicle protein SV2A, thought to be involved in the regulation of vesicle exocytosis.
Although the molecular significance of levetiracetam binding to synaptic vesicle protein SV2A is not understood, levetiracetam and related analogs showed a rank order of affinity for SV2A which correlated with the potency of their antiseizure activity in audiogenic seizure-prone mice. These findings suggest that the interaction of levetiracetam with the SV2A protein may contribute to the antiepileptic mechanism of action of the drug.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied KEPPRA XR 500 mg tablets are white, oblong-shaped, film-coated tablets imprinted with "UCB 500XR" in red on one side. They are supplied in white HDPE bottles containing 60 tablets (NDC 50474-598-66). KEPPRA XR 750 mg tablets are white, oblong-shaped, film-coated tablets imprinted with "UCB 750XR" in red on one side. They are supplied in white HDPE bottles containing 60 tablets (NDC 50474-599-66).
16.2Storage Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
16.2Storage Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION KEPPRA XR is an antiepileptic drug available as 500 mg and 750 mg (white) extended-release tablets for oral administration. The chemical name of levetiracetam, a single enantiomer, is (-)-(S)-α-ethyl-2-oxo-1-pyrrolidine acetamide, its molecular formula is C 8 H 14 N 2 O 2 and its molecular weight is 170.21. Levetiracetam is chemically unrelated to existing antiepileptic drugs (AEDs).
It has the following structural formula: Levetiracetam is a white to off-white crystalline powder with a faint odor and a bitter taste. It is very soluble in water (104.0 g/100 mL). It is freely soluble in chloroform (65.3 g/100 mL) and in methanol (53.6 g/100 mL), soluble in ethanol (16.5 g/100 mL), sparingly soluble in acetonitrile (5.7 g/100 mL) and practically insoluble in n-hexane.
(Solubility limits are expressed as g/100 mL solvent.) KEPPRA XR tablets contain the labeled amount of levetiracetam. Inactive ingredients: colloidal anhydrous silica, hypromellose, magnesium stearate, polyethylene glycol 6000, polyvinyl alcohol-partially hydrolyzed, titanium dioxide (E171), Macrogol/PEG3350, and talc. The imprinting ink contains shellac, FD&C Red #40, n-butyl alcohol, propylene glycol, titanium dioxide, ethanol, and methanol.
The medication is combined with a drug release controlling polymer that provides a drug release at a controlled rate. The biologically inert components of the tablet may occasionally remain intact during GI transit and will be eliminated in the feces as a soft, hydrated mass. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). The Medication Guide accompanies the product and can also be accessed on www.keppraxr.com or by calling 1-844-599-2273. Psychiatric Reactions and Changes in Behavior Advise patients that KEPPRA XR may cause changes in behavior (e.g. irritability and aggression).
In addition, patients should be advised that they may experience changes in behavior that have been seen with other formulations of KEPPRA, which include agitation, anger, anxiety, apathy, depression, hostility, and psychotic symptoms [see Warnings and Precautions (5.1) ] . Suicidal Behavior and Ideation Counsel patients, their caregivers, and/or families that antiepileptic drugs (AEDs), including KEPPRA XR, may increase the risk of suicidal thoughts and behavior and advise patients to be alert for the emergence or worsening of symptoms of depression; unusual changes in mood or behavior; or suicidal thoughts, behavior, or thoughts about self-harm.
Advise patients, their caregivers, and/or families to immediately report behaviors of concern to a healthcare provider [see Warnings and Precautions (5.2) ] . Effects on Driving or Operating Machinery Inform patients that KEPPRA XR may cause dizziness and somnolence. Inform patients not to drive or operate machinery until they have gained sufficient experience on KEPPRA XR to gauge whether it adversely affects their ability to drive or operate machinery [see Warnings and Precautions (5.3) ] .
Anaphylaxis and Angioedema Advise patients to discontinue KEPPRA XR and seek medical care if they develop signs and symptoms of anaphylaxis or angioedema [see Warnings and Precautions (5.4) ]. Dermatological Adverse Reactions Advise patients that serious dermatological adverse reactions have occurred in patients treated with levetiracetam and instruct them to call their physician immediately if a rash develops [see Warnings and Precautions (5.5) ] . DRESS/Multiorgan Hypersensitivity Instruct patients and caregivers that a fever or rash associated with signs of other organ system involvement (e.g., lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately.
KEPPRA XR should be discontinued immediately if a serious hypersensitivity reaction is suspected [see Warnings and Precautions (5.6) ]. Dosing and Administration Patients should be instructed to only take KEPPRA XR once daily and to swallow the tablets whole. They should not be chewed, broken, or crushed.
Inform patients that they should not be concerned if they occasionally notice something that looks like swollen pieces of the original tablet in their stool. Withdrawal of KEPPRA Advise patients and caregivers not to discontinue use of KEPPRA XR without consulting with their healthcare provider. KEPPRA XR should normally be gradually withdrawn to reduce the potential of increased seizure frequency and status epilepticus [see Warnings and Precautions (5.8) ].
Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during KEPPRA therapy. Encourage patients to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry if they become pregnant [see Use in Specific Populations (8.1) ].
💬 Medication Guide ▾
MEDICATION GUIDE KEPPRA XR ® (KEPP-ruh XR ) (levetiracetam) extended-release tablets, for oral use This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 3/2024 Read this Medication Guide before you start taking KEPPRA XR and each time you get a refill.
There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment. What is the most important information I should know about KEPPRA XR?
Like other antiepileptic drugs, KEPPRA XR may cause suicidal thoughts or actions in a very small number of people, about 1 in 500 people taking it. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Do not stop KEPPRA XR without first talking to a healthcare provider .
Stopping KEPPRA XR suddenly can cause serious problems. Stopping a seizure medicine suddenly can cause seizures that will not stop (status epilepticus). Suicidal thoughts or actions can be caused by things other than medicines.
If you have suicidal thoughts or actions, your healthcare provider may check for other causes. How can I watch for early symptoms of suicidal thoughts and actions? Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings.
Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms. What is KEPPRA XR?
KEPPRA XR is a prescription medicine taken by mouth that is used to treat partial-onset seizures in people 12 years of age and older. It is not known if KEPPRA XR is safe or effective in people under 12 years of age. Before taking your medicine, make sure you have received the correct medicine.
Compare the name above with the name on your bottle and the appearance of your medicine with the description of KEPPRA XR provided below. Tell your pharmacist immediately if you think you have been given the wrong medicine. Who should not take KEPPRA XR?
Do not take KEPPRA XR if you are allergic to levetiracetam. What should I tell my healthcare provider before starting KEPPRA XR? Before taking KEPPRA XR, tell your healthcare provider about all of your medical conditions, including if you: have or have had depression, mood problems or suicidal thoughts or behavior. have kidney problems. are pregnant or planning to become pregnant.
It is not known if KEPPRA XR will harm your unborn baby. You and your healthcare provider will have to decide if you should take KEPPRA XR while you are pregnant. If you become pregnant while taking KEPPRA XR, talk to your healthcare provider about registering with the North American Antiepileptic Drug Pregnancy Registry.
You can enroll in this registry by calling 1-888-233-2334 or go to http://www.aedpregnancyregistry.org. The purpose of this registry is to collect information about the safety of KEPPRA XR and other antiepileptic medicine during pregnancy. are breastfeeding or plan to breastfeed. KEPPRA XR can pass into your breast milk.
It is not known if the KEPPRA XR that passes into your breast milk can harm your baby. Talk to your doctor about the best way to feed your baby while you receive KEPPRA. Tell your healthcare provider about all the medicines you take, including prescription and over-the counter medicines, vitamins, and herbal supplements.
Do not start a new medicine without first talking with your healthcare provider. Know the medicines you take. Keep a list of them to show your healthcare provider and pharmacist each time you…