
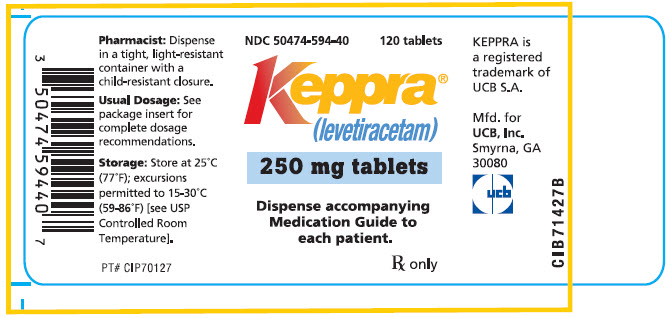
Keppra levetiracetam 250 mg Tablet, Film Coated, 120-count — NDC 50474-594-40 (Billing 50474-0594-40)
This is a package of 120 tablets of Keppra levetiracetam 250 mg Tablet, Film Coated from UCB, Inc., marketed since Apr 2000 and currently FDA-listed; retail pharmacies pay about $8.08 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 50474-594-40 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 50474 labeler · 594 product · 40 package
- Package marketed since
- Apr 24, 2000
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 120 EA per package
- Barcode (UPC)
- 0350474595404
- Medicaid fills, this package
- 1,232 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 044632
- GCN: 41587
- GPI-14 (Medi-Span): 72600043000320
- HICL (First Databank): 020952
- AHFS class code: 28:12.92.00
- RxCUI (RxNorm): 261335
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Other antiepileptics class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats seizures in epilepsy. Depending on the product, that means partial-onset seizures, and as add-on therapy, myoclonic seizures in juvenile myoclonic epilepsy and primary ge...
- Follow your prescriber and label. Tablets and solution are usually twice daily, while extended-release tablets are once daily and must be swallowed whole. Use a calibrated device f...
- Sleepiness, tiredness, dizziness and headache are common, especially early on. Children may become irritable or aggressive. Avoid driving until you know how it affects you.
- Call right away for new or worsening depression, suicidal thoughts, unusual behavior, a rash, swelling of the face or throat, or trouble walking. Get emergency help for trouble bre...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Levetiracetam — tap one for details:
Levetiracetam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $8.079 | $969.43 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $7.93 | $951.58 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $8.36 | $1,003.49 / 120 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 50474-0594-40 You're viewing this Main listing | 120 TABLET, FILM COATED in 1 BOTTLE, PLASTIC | 2000-04-24 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levetiracetam 250 mg 00904-7123-61 | Major | 1 tablet | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 16714-0034-01 | NorthStar | 120 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 27808-0263-01 | Cranbury | 120 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 31722-0536-05 | Camber | 500 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 43547-0221-15 | Solco | 120 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 50228-0470-05 | ScieGen | 500 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 67877-0768-05 | Ascend | 500 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 68001-0402-03 | BluePoint | 500 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 68084-0859-01 | American | 1 tablet | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 68180-0112-02 | Lupin | 500 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 72205-0094-92 | Novadoz | 120 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 82009-0121-05 | Quallent | 500 tablets | $0.056 | AB | Availability likely | save 99% |
| Levetiracetam 250 mg 13668-0014-05 | Torrent | 500 tablets | $0.064 | AB | FDA listed | save 99% |
| Keppra 250 mgthis 50474-0594-40 | UCB, | 120 tablets | $8.079 | AB | Availability likely | — |
| Spritam 250 mg 43485-0101-60 | Aprecia | 1 tablet | $10.272 | — | Availability likely | +27% |
| Levetiracetam 250 mg 00615-8498-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 43547-0880-15 | Solco | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 50090-7774-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 50405-0300-01 | SOHM, | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 55111-0181-01 | Dr. | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 55154-4171-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Levetiracetam 250 mg 63629-4675-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 64980-0604-01 | Rising | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 65162-0528-16 | Amneal | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 65862-0245-05 | Aurobindo | 500 tablets | — | — | FDA listed | — |
| Levetiracetam 250 mg 67046-0880-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 68788-7884-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Roweepra 250 mg 69102-0108-01 | OWP | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 70010-0521-03 | Granules | 30 tablets | — | — | FDA listed | — |
| Levetiracetam 250 mg 70518-4306-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 71335-0702-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 71335-2275-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 72189-0190-30 | DIRECT | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 72865-0187-05 | XLCare | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 76282-0246-12 | Exelan | 120 tablets | — | — | FDA listed | — |
| Levetiracetam 250 mg 76494-0528-12 | Prinston | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 87063-0190-12 | ASCLEMED | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 250 mg 66993-0100-06 | Prasco | 1 tablet | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8802142 ↗ | Drug product | — | Jun 7, 2031 |
| US 8802142 ↗ | Drug product | — | Jun 7, 2031 |
| US 8802142 ↗ | Drug product | — | Jun 7, 2031 |
| US 8802142 ↗ | Drug product | — | Jun 7, 2031 |
| US 8802142*PED ↗ | Drug product | — | Dec 7, 2031 |
| US 8802142*PED ↗ | Drug product | — | Dec 7, 2031 |
| US 8802142*PED ↗ | Drug product | — | Dec 7, 2031 |
| US 8802142*PED ↗ | Drug product | — | Dec 7, 2031 |
Is there a generic version of KEPPRA 250 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII LMI26O6933
Alumina is a white powder form of aluminum oxide. It's used as a filler to add bulk to tablets and capsules, and sometimes as a thickening or anti-caking agent in powdered formulations.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII D3741U8K7L
A blue colorant derived from indigo dye. It's added to tablets and capsules to provide color identification and improve the appearance of the medication.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from UCB, Inc. labeler code 50474
- Keppra levetiracetam 100 mg/mL Injection, Solution, Concentrate NDC 50474-002-63
- Kygevvi doxecitine and doxribtimine 2 g; 2 g Powder, For Solution NDC 50474-350-30
- Briviact brivaracetam 10 mg Tablet, Film Coated NDC 50474-370-66
- Briviact brivaracetam 25 mg Tablet, Film Coated NDC 50474-470-09
- Nayzilam midazolam 5 mg/.1mL Spray NDC 50474-500-15
- Briviact brivaracetam 50 mg Tablet, Film Coated NDC 50474-570-09
- Keppra levetiracetam 500 mg Tablet, Film Coated NDC 50474-595-40
- Keppra levetiracetam 750 mg Tablet, Film Coated NDC 50474-596-40
- Keppra levetiracetam 1000 mg Tablet, Film Coated NDC 50474-597-66
- Keppra XR levetiracetam 500 mg Tablet, Film Coated, Extended Release NDC 50474-598-66
- Keppra XR levetiracetam 750 mg Tablet, Film Coated, Extended Release NDC 50474-599-66
- Briviact brivaracetam 75 mg Tablet, Film Coated NDC 50474-670-66
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE KEPPRA is indicated for the treatment of partial-onset seizures in patients 1 month of age and older ( 1.1 ) KEPPRA is indicated for adjunctive therapy for the treatment of: Myoclonic seizures in patients 12 years of age and older with juvenile myoclonic epilepsy ( 1.2 ) Primary generalized tonic-clonic seizures in patients 6 years of age and older with idiopathic generalized epilepsy ( 1.3 )
1.1Partial-Onset Seizures KEPPRA is indicated for the treatment of partial-onset seizures in patients 1 month of age and older.
1.2Myoclonic Seizures in Patients with Juvenile Myoclonic Epilepsy KEPPRA is indicated as adjunctive therapy for the treatment of myoclonic seizures in patients 12 years of age and older with juvenile myoclonic epilepsy.
1.3Primary Generalized Tonic-Clonic Seizures KEPPRA is indicated as adjunctive therapy for the treatment of primary generalized tonic-clonic seizures in patients 6 years of age and older with idiopathic generalized epilepsy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Use the oral solution for pediatric patients with body weight ≤ 20 kg ( 2.1 ) For pediatric patients, use weight-based dosing for the oral solution with a calibrated measuring device (not a household teaspoon or tablespoon) ( 2.1 ) Partial-Onset Seizures (monotherapy or adjunctive therapy) 1 Month to < 6 Months: 7 mg/kg twice daily; increase by 7 mg/kg twice daily every 2 weeks to recommended dose of 21 mg/kg twice daily ( 2.2 ) 6 Months to < 4 Years: 10 mg/kg twice daily; increase by 10 mg/kg twice daily every 2 weeks to recommended dose of 25 mg/kg twice daily ( 2.2 ) 4 Years to < 16 Years: 10 mg/kg twice daily; increase by 10 mg/kg twice daily every 2 weeks to recommended dose of 30 mg/kg twice daily ( 2.2 ) Adults 16 Years and Older: 500 mg twice daily; increase by 500 mg twice daily every 2 weeks to a recommended dose of 1500 mg twice daily ( 2.2 ) Myoclonic Seizures in Adults and Pediatric Patients 12 Years and Older 500 mg twice daily; increase by 500 mg twice daily every 2 weeks to recommended dose of 1500 mg twice daily ( 2.3 ) Primary Generalized Tonic-Clonic Seizures 6 Years to < 16 Years: 10 mg/kg twice daily, increase in increments of 10 mg/kg twice daily every 2 weeks to recommended dose of 30 mg/kg twice daily ( 2.4 ) Adults 16 Years and Older: 500 mg twice daily, increase by 500 mg twice daily every 2 weeks to recommended dose of 1500 mg twice daily ( 2.4 ) Adult Patients with Impaired Renal Function Dose adjustment is recommended, based on the patient's estimated creatinine clearance ( 2.5 , 8.6 )
2.1Important Administration Instructions KEPPRA is given orally with or without food. The KEPPRA dosing regimen depends on the indication, age group, dosage form (tablets or oral solution), and renal function. Prescribe the oral solution for pediatric patients with body weight ≤ 20 kg.
Prescribe the oral solution or tablets for pediatric patients with body weight above 20 kg. When using the oral solution in pediatric patients, dosing is weight-based (mg per kg) using a calibrated measuring device (not a household teaspoon or tablespoon). KEPPRA tablets should be swallowed whole.
KEPPRA tablets should not be chewed or crushed.
2.2Dosing for Partial-Onset Seizures The recommended dosing for monotherapy and adjunctive therapy is the same; as outlined below. Adults 16 Years of Age and Older Initiate treatment with a daily dose of 1000 mg/day, given as twice-daily dosing (500 mg twice daily). Additional dosing increments may be given (1000 mg/day additional every 2 weeks) to a maximum recommended daily dose of 3000 mg.
There is no evidence that doses greater than 3000 mg/day confer additional benefit. Pediatric Patients 1 Month to < 6 Months Initiate treatment with a daily dose of 14 mg/kg in 2 divided doses (7 mg/kg twice daily). Increase the daily dose every 2 weeks by increments of 14 mg/kg to the recommended daily dose of 42 mg/kg (21 mg/kg twice daily).
In the clinical trial, the mean daily dose was 35 mg/kg in this age group. 6 Months to < 4 Years: Initiate treatment with a daily dose of 20 mg/kg in 2 divided doses (10 mg/kg twice daily). Increase the daily dose in 2 weeks by an increment of 20 mg/kg to the recommended daily dose of 50 mg/kg (25 mg/kg twice daily).
If a patient cannot tolerate a daily dose of 50 mg/kg, the daily dose may be reduced. In the clinical trial, the mean daily dose was 47 mg/kg in this age group. 4 Years to < 16 Years Initiate treatment with a daily dose of 20 mg/kg in 2 divided doses (10 mg/kg twice daily).
Increase the daily dose every 2 weeks by increments of 20 mg/kg to the recommended daily dose of 60 mg/kg (30 mg/kg twice daily). If a patient cannot tolerate a daily dose of 60 mg/kg, the daily dose may be reduced. In the clinical trial, the mean daily dose was 44 mg/kg.
The maximum daily dose was 3000 mg/day. For KEPPRA tablet dosing in pediatric patients weighing 20 to 40 kg, initiate treatment with a daily dose of 500 mg given as twice daily dosing (25… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 250 mg, 500 mg, 750 mg, and 1000 mg film-coated, scored tablets ( 3 ) 100 mg/mL solution ( 3 ) KEPPRA Tablets 250 mg: blue, oblong-shaped, scored, film-coated, and debossed with "ucb 250" on one side 500 mg: yellow, oblong-shaped, scored, film-coated, and debossed with "ucb 500" on one side 750 mg: orange, oblong-shaped, scored, film-coated, and debossed with "ucb 750" on one side 1000 mg: white, oblong-shaped, scored, film-coated, and debossed with "ucb 1000" on one side KEPPRA Oral Solution 100 mg/mL: a clear, colorless, grape-flavored liquid
⛔ Contraindications ▾
4 CONTRAINDICATIONS KEPPRA is contraindicated in patients with a hypersensitivity to levetiracetam . Reactions have included anaphylaxis and angioedema [see Warnings and Precautions (5.4) ] . Known hypersensitivity to levetiracetam; angioedema and anaphylaxis have occurred ( 4 , 5.4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Behavioral abnormalities including psychotic symptoms, suicidal ideation, irritability, and aggressive behavior have been observed; monitor patients for psychiatric signs and symptoms ( 5.1 ) Suicidal Behavior and Ideation: Monitor patients for new or worsening depression, suicidal thoughts/behavior, and/or unusual changes in mood or behavior ( 5.2 ) Monitor for somnolence and fatigue and advise patients not to drive or operate machinery until they have gained sufficient experience on KEPPRA ( 5.3 ) Serious Dermatological Reactions: Discontinue KEPPRA at the first sign of rash unless clearly not drug related ( 5.5 ) Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity: Discontinue if no alternative etiology ( 5.6 ) Coordination Difficulties: Monitor for ataxia, abnormal gait, and incoordination.
Advise patients to not drive or operate machinery until they have gained experience on KEPPRA ( 5.7 ) Withdrawal Seizures: KEPPRA must be gradually withdrawn ( 5.8 )
5.1Behavioral Abnormalities and Psychotic Symptoms KEPPRA may cause behavioral abnormalities and psychotic symptoms. Patients treated with KEPPRA should be monitored for psychiatric signs and symptoms. Behavioral abnormalities In clinical studies, 13% of adult KEPPRA-treated patients and 38% of pediatric KEPPRA-treated patients (4 to 16 years of age) compared to 6% and 19% of adult and pediatric placebo-treated patients, experienced non-psychotic behavioral symptoms (reported as aggression, agitation, anger, anxiety, apathy, depersonalization, depression, emotional lability, hostility, hyperkinesias, irritability, nervousness, neurosis, and personality disorder).
A randomized double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioral effects of KEPPRA as adjunctive therapy in pediatric patients (4 to 16 years of age). The results from an exploratory analysis indicated a worsening in KEPPRA-treated patients on aggressive behavior (one of eight behavior dimensions) as measured in a standardized and systematic way using a validated instrument, the Achenbach Child Behavior Checklist (CBCL/6-18). In clinical studies in pediatric patients 1 month to < 4 years of age, irritability was reported in 12% of the KEPPRA-treated patients compared to 0% of placebo-treated patients.
In clinical studies, 1.7% of adult KEPPRA-treated patients discontinued treatment due to behavioral adverse reactions, compared to 0.2% of placebo-treated patients. The treatment dose was reduced in 0.8% of adult KEPPRA-treated patients and in 0.5% of placebo-treated patients. Overall, 11% of KEPPRA-treated pediatric patients experienced behavioral symptoms associated with discontinuation or dose reduction, compared to 6% of placebo-treated patients.
Psychotic symptoms In clinical studies, 1% of KEPPRA-treated adult patients, 2% of KEPPRA-treated pediatric patients 4 to 16 years of age, and 17% of KEPPRA-treated pediatric patients 1 month to <4 years of age experienced psychotic symptoms, compared to 0.2%, 2%, and 5% in the corresponding age groups treated with placebo. In a controlled study that assessed the neurocognitive and behavioral effects of KEPPRA in pediatric patients 4 to 16 years of age, 1.6% of KEPPRA-treated patients experienced paranoia, compared to 0% of placebo-treated patients.
In the same study, 3.1% of KEPPRA-treated patients experienced confusional state, compared to 0% of placebo-treated patients [see Use in Specific Populations (8.4) ] . In clinical studies, two (0.3%) KEPPRA-treated adult patients were hospitalized and their treatment was discontinued due to psychosis. Both events, reported as psychosis, developed within the first week of treatment and resolved within 1 to 2 weeks following treatment discontinuation.
There was no difference between drug and placebo-treated patients in the incidence of the pediatric patients who discontinued treatment due to psychotic and non-psychotic… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more details in other sections of labeling: Behavior Abnormalities and Psychotic Symptoms [see Warnings and Precautions (5.1) ] Suicidal Behavior and Ideation [see Warnings and Precautions (5.2) ] Somnolence and Fatigue [see Warnings and Precautions (5.3) ] Anaphylaxis and Angioedema [see Warnings and Precautions (5.4) ] Serious Dermatological Reactions [see Warnings and Precautions (5.5) ] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions (5.6) ] Coordination Difficulties [see Warnings and Precautions (5.7) ] Hematologic Abnormalities [see Warnings and Precautions (5.9) ] Increase in Blood Pressure [see Warnings and Precautions (5.10) ] Most common adverse reactions (incidence ≥ 5% more than placebo) include: Adult patients: somnolence, asthenia, infection and dizziness ( 6.1 ) Pediatric patients: fatigue, aggression, nasal congestion, decreased appetite, and irritability ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact UCB, Inc. at 1-844-599-2273 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Partial-Onset Seizures Adults In controlled clinical studies in adults with partial-onset seizures [see Clinical Studies (14.1) ] , the most common adverse reactions in patients receiving KEPPRA in combination with other AEDs, for events with rates greater than placebo, were somnolence, asthenia, infection, and dizziness.
Of the most common adverse reactions in adults experiencing partial-onset seizures, asthenia, somnolence, and dizziness occurred predominantly during the first 4 weeks of treatment with KEPPRA. Table 3 lists adverse reactions that occurred in at least 1% of adult epilepsy patients receiving KEPPRA in placebo-controlled studies and were numerically more common than in patients treated with placebo. In these studies, either KEPPRA or placebo was added to concurrent AED therapy.
Table 3: Adverse Reactions in Pooled Placebo-Controlled, Adjunctive Studies in Adults Experiencing Partial-Onset Seizures KEPPRA (N=769) % Placebo (N=439) % Asthenia 15 9 Somnolence 15 8 Headache 14 13 Infection 13 8 Dizziness 9 4 Pain 7 6 Pharyngitis 6 4 Depression 4 2 Nervousness 4 2 Rhinitis 4 3 Anorexia 3 2 Ataxia 3 1 Vertigo 3 1 Amnesia 2 1 Anxiety 2 1 Cough Increased 2 1 Diplopia 2 1 Emotional Lability 2 0 Hostility 2 1 Paresthesia 2 1 Sinusitis 2 1 In controlled adult clinical studies, 15% of patients receiving KEPPRA and 12% receiving placebo either discontinued or had a dose reduction as a result of an adverse reaction.
Table 4 lists the most common (>1%) adverse reactions that resulted in discontinuation or dose reduction and that occurred more frequently in KEPPRA-treated patients than in placebo-treated patients. Table 4: Adverse Reactions that Resulted in Discontinuation or Dose Reduction in Placebo-Controlled Studies in Adult Patients Experiencing Partial-Onset Seizures Adverse Reaction KEPPRA (N=769) % Placebo (N=439) % Somnolence 4 2 Dizziness 1 0 Pediatric Patients 4 Years to <16 Years The adverse reaction data presented below was obtained from a pooled analysis of two controlled pediatric clinical studies in pediatric patients 4 to 16 years of age with partial-onset seizures.
The most common adverse reactions in pediatric patients receiving KEPPRA in combination with other AEDs, for events with rates greater than placebo, were fatigue, aggression, nasal congestion, decreased appetite, and irritability. Table 5 lists adverse reactions from the pooled pediatric controlled studies (4 to 16 years of age) that occurred in at least 2% of pediatric KEPPRA-treated patients and were numerically more comm… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Plasma levels of levetiracetam may be decreased and therefore need to be monitored closely during pregnancy. Based on animal data, may cause fetal harm ( 5.11 , 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), including KEPPRA, during pregnancy. Encourage women who are taking KEPPRA during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Prolonged experience with KEPPRA in pregnant women has not identified a drug-associated risk of major birth defects or miscarriage, based on published literature, which includes data from pregnancy registries and reflects experience over two decades [see Human Data ] .
In animal studies, levetiracetam produced developmental toxicity (increased embryofetal and offspring mortality, increased incidences of fetal structural abnormalities, decreased embryofetal and offspring growth, neurobehavioral alterations in offspring) at doses similar to human therapeutic doses [see Animal Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations Levetiracetam blood levels may decrease during pregnancy [see Warnings and Precautions (5.11) ] . Physiological changes during pregnancy may affect levetiracetam concentration. Decrease in levetiracetam plasma concentrations has been observed during pregnancy.
This decrease is more pronounced during the third trimester. Dose adjustments may be necessary to maintain clinical response. Data Human Data While available studies cannot definitively establish the absence of risk, data from the published literature and pregnancy registries have not established an association with levetiracetam use during pregnancy and major birth defects or miscarriage.
Animal Data When levetiracetam (0, 400, 1200, or 3600 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, reduced fetal weights and increased incidence of fetal skeletal variations were observed at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on embryofetal developmental in rats (1200 mg/kg/day) is approximately 4 times the maximum recommended human dose (MRHD) of 3000 mg on a body surface area (mg/m 2 ) basis.
Oral administration of levetiracetam (0, 200, 600, or 1800 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality and incidence of fetal skeletal variations at the mid and high dose and decreased fetal weights and increased incidence of fetal malformations at the high dose, which was associated with maternal toxicity. The no-effect dose for adverse effects on embryofetal development in rabbits (200 mg/kg/day) is approximately equivalent to the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam (0, 70, 350, or 1800 mg/kg/day) to female rats throughout pregnancy and lactation led to an increased incidence of fetal skeletal variations, reduced fetal body weight, and decreased growth in offspring at the mid and high doses and increased pup mortality and neurobehavioral alterations in offspring at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on pre- and postnatal development in rats (70 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam to rats during the latter part of gestation and throughout lactation produced no adverse developmental or maternal effects at doses of up to 1800 mg/kg/day (6 times the MRHD on a mg/m 2 basis).
8.2Lactatio… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), including KEPPRA, during pregnancy. Encourage women who are taking KEPPRA during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Prolonged experience with KEPPRA in pregnant women has not identified a drug-associated risk of major birth defects or miscarriage, based on published literature, which includes data from pregnancy registries and reflects experience over two decades [see Human Data ] .
In animal studies, levetiracetam produced developmental toxicity (increased embryofetal and offspring mortality, increased incidences of fetal structural abnormalities, decreased embryofetal and offspring growth, neurobehavioral alterations in offspring) at doses similar to human therapeutic doses [see Animal Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations Levetiracetam blood levels may decrease during pregnancy [see Warnings and Precautions (5.11) ] . Physiological changes during pregnancy may affect levetiracetam concentration. Decrease in levetiracetam plasma concentrations has been observed during pregnancy.
This decrease is more pronounced during the third trimester. Dose adjustments may be necessary to maintain clinical response. Data Human Data While available studies cannot definitively establish the absence of risk, data from the published literature and pregnancy registries have not established an association with levetiracetam use during pregnancy and major birth defects or miscarriage.
Animal Data When levetiracetam (0, 400, 1200, or 3600 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, reduced fetal weights and increased incidence of fetal skeletal variations were observed at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on embryofetal developmental in rats (1200 mg/kg/day) is approximately 4 times the maximum recommended human dose (MRHD) of 3000 mg on a body surface area (mg/m 2 ) basis.
Oral administration of levetiracetam (0, 200, 600, or 1800 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality and incidence of fetal skeletal variations at the mid and high dose and decreased fetal weights and increased incidence of fetal malformations at the high dose, which was associated with maternal toxicity. The no-effect dose for adverse effects on embryofetal development in rabbits (200 mg/kg/day) is approximately equivalent to the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam (0, 70, 350, or 1800 mg/kg/day) to female rats throughout pregnancy and lactation led to an increased incidence of fetal skeletal variations, reduced fetal body weight, and decreased growth in offspring at the mid and high doses and increased pup mortality and neurobehavioral alterations in offspring at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on pre- and postnatal development in rats (70 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam to rats during the latter part of gestation and throughout lactation produced no adverse developmental or maternal effects at doses of up to 1800 mg/kg/day (6 times the MRHD on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of KEPPRA for the treatment of partial-onset seizures in patients 1 month to 16 years of age have been established [see Clinical Pharmacology (12.3) and Clinical Studies (14.1) ] . The dosing recommendation in these pediatric patients varies according to age group and is weight-based [see Dosage and Administration (2.2) ] . The safety and effectiveness of KEPPRA as adjunctive therapy for the treatment of myoclonic seizures in adolescents 12 years of age and older with juvenile myoclonic epilepsy have been established [see Clinical Studies (14.2) ] .
The safety and effectiveness of KEPPRA as adjunctive therapy for the treatment of primary generalized tonic-clonic seizures in pediatric patients 6 years of age and older with idiopathic generalized epilepsy have been established [see Clinical Studies (14.3) ] . Safety and effectiveness for the treatment of partial-onset seizures in pediatric patients below the age of 1 month; adjunctive therapy for the treatment of myoclonic seizures in pediatric patients below the age of 12 years; and adjunctive therapy for the treatment of primary generalized tonic-clonic seizures in pediatric patients below the age of 6 years have not been established.
A 3-month, randomized, double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioral effects of KEPPRA as adjunctive therapy in 98 (KEPPRA N=64, placebo N=34) pediatric patients, ages 4 to 16 years old, with partial seizures that were inadequately controlled. The target dose was 60 mg/kg/day. Neurocognitive effects were measured by the Leiter-R Attention and Memory (AM) Battery, which measures various aspects of a child's memory and attention.
Although no substantive differences were observed between the placebo and drug treated groups in the median change from baseline in this battery, the study was not adequate to assess formal statistical non-inferiority of the drug and placebo. The Achenbach Child Behavior Checklist (CBCL/6-18), a standardized validated tool used to assess a child's competencies and behavioral/emotional problems, was also assessed in this study. An analysis of the CBCL/6-18 indicated on average a worsening in KEPPRA-treated patients in aggressive behavior, one of the eight syndrome scores [see Warnings and Precautions (5.1) ] .
Juvenile Animal Toxicity Data Studies of levetiracetam in juvenile rats (dosed on postnatal days 4 through 52) and dogs (dosed from postnatal weeks 3 through 7) at doses of up to 1800 mg/kg/day (approximately 7 and 24 times, respectively, the maximum recommended pediatric dose of 60 mg/kg/day on a mg/m 2 basis) did not demonstrate adverse effects on postnatal development.
🧓 Geriatric Use ▾
8.5Geriatric Use There were 347 subjects in clinical studies of KEPPRA that were 65 and over. No overall differences in safety were observed between these subjects and younger subjects. There were insufficient numbers of elderly subjects in controlled trials of epilepsy to adequately assess the effectiveness of KEPPRA in these patients.
Levetiracetam is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs, Symptoms and Laboratory Findings of Acute Overdosage in Humans The highest known dose of KEPPRA received in the clinical development program was 6000 mg/day. Other than drowsiness, there were no adverse reactions in the few known cases of overdose in clinical trials. Cases of somnolence, agitation, aggression, depressed level of consciousness, respiratory depression and coma were observed with KEPPRA overdoses in postmarketing use.
10.2Management of Overdose There is no specific antidote for overdose with KEPPRA. If indicated, elimination of unabsorbed drug should be attempted by emesis or gastric lavage; usual precautions should be observed to maintain airway. General supportive care of the patient is indicated including monitoring of vital signs and observation of the patient's clinical status.
A Certified Poison Control Center should be contacted for up to date information on the management of overdose with KEPPRA.
10.3Hemodialysis Standard hemodialysis procedures result in significant clearance of levetiracetam (approximately 50% in 4 hours) and should be considered in cases of overdose. Although hemodialysis has not been performed in the few known cases of overdose, it may be indicated by the patient's clinical state or in patients with significant renal impairment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism(s) by which levetiracetam exerts its antiepileptic effect is unknown. A saturable and stereoselective neuronal binding site in rat brain tissue has been described for levetiracetam. Experimental data indicate that this binding site is the synaptic vesicle protein SV2A, thought to be involved in the regulation of vesicle exocytosis.
Although the molecular significance of levetiracetam binding to SV2A is not understood, levetiracetam and related analogs showed a rank order of affinity for SV2A which correlated with the potency of their antiseizure activity in audiogenic seizure-prone mice. These findings suggest that the interaction of levetiracetam with the SV2A protein may contribute to the antiepileptic mechanism of action of the drug.
12.2Pharmacodynamics Effects on QTc Interval The effect of KEPPRA on QTc prolongation was evaluated in a randomized, double-blind, positive-controlled (moxifloxacin 400 mg) and placebo-controlled crossover study of KEPPRA (1000 mg or 5000 mg) in 52 healthy subjects. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 milliseconds. Therefore, there was no evidence of significant QTc prolongation in this study.
12.3Pharmacokinetics The pharmacokinetics of levetiracetam are similar when used as monotherapy or as adjunctive therapy for the treatment of partial-onset seizures. Absorption and Distribution Absorption of levetiracetam is rapid, with peak plasma concentrations occurring in about an hour following oral administration in fasted subjects. The oral bioavailability of levetiracetam tablets is 100% and the tablets and oral solution are bioequivalent in rate and extent of absorption.
Food does not affect the extent of absorption of levetiracetam but it decreases C max by 20% and delays T max by 1.5 hours. The pharmacokinetics of levetiracetam are linear over the dose range of 500-5000 mg. Steady state is achieved after 2 days of multiple twice-daily dosing.
Levetiracetam and its major metabolite are less than 10% bound to plasma proteins; clinically significant interactions with other drugs through competition for protein binding sites are therefore unlikely. Metabolism Levetiracetam is not extensively metabolized in humans. The major metabolic pathway is the enzymatic hydrolysis of the acetamide group, which produces the carboxylic acid metabolite, ucb L057 (24% of dose) and is not dependent on any liver cytochrome P450 isoenzymes.
The major metabolite is inactive in animal seizure models. Two minor metabolites were identified as the product of hydroxylation of the 2-oxo-pyrrolidine ring (2% of dose) and opening of the 2-oxo-pyrrolidine ring in position 5 (1% of dose). There is no enantiomeric interconversion of levetiracetam or its major metabolite.
Elimination Levetiracetam plasma half-life in adults is 7 ± 1 hour and is unaffected by either dose or repeated administration. Levetiracetam is eliminated from the systemic circulation by renal excretion as unchanged drug which represents 66% of administered dose. The total body clearance is 0.96 mL/min/kg and the renal clearance is 0.6 mL/min/kg.
The mechanism of excretion is glomerular filtration with subsequent partial tubular reabsorption. The metabolite ucb L057 is excreted by glomerular filtration and active tubular secretion with a renal clearance of 4 mL/min/kg. Levetiracetam elimination is correlated to creatinine clearance.
Levetiracetam clearance is reduced in patients with renal impairment [see Use in Specific Populations (8.6) and Dosage and Administration (2.5) ] . Specific Populations Elderly Pharmacokinetics of levetiracetam were evaluated in 16 elderly subjects (age 61-88 years) with creatinine clearance ranging from 30 to 74 mL/min. Following oral administration of twice-daily dosing for 10 days, total body clearance decreased by 38% and the half-life was 2.5 hours longer in the elderly comp… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism(s) by which levetiracetam exerts its antiepileptic effect is unknown. A saturable and stereoselective neuronal binding site in rat brain tissue has been described for levetiracetam. Experimental data indicate that this binding site is the synaptic vesicle protein SV2A, thought to be involved in the regulation of vesicle exocytosis.
Although the molecular significance of levetiracetam binding to SV2A is not understood, levetiracetam and related analogs showed a rank order of affinity for SV2A which correlated with the potency of their antiseizure activity in audiogenic seizure-prone mice. These findings suggest that the interaction of levetiracetam with the SV2A protein may contribute to the antiepileptic mechanism of action of the drug.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied KEPPRA Tablets 250 mg: blue, oblong-shaped, scored, film-coated tablets debossed with "ucb 250" on one side. They are supplied in white HDPE bottles containing 120 tablets (NDC 50474-594-40). 500 mg: yellow, oblong-shaped, scored, film-coated tablets debossed with "ucb 500" on one side.
They are supplied in white HDPE bottles containing 120 tablets (NDC 50474-595-40). 750 mg: orange, oblong-shaped, scored, film-coated tablets debossed with "ucb 750" on one side. They are supplied in white HDPE bottles containing 120 tablets (NDC 50474-596-40).
1000 mg: white, oblong-shaped, scored, film-coated tablets debossed with "ucb 1000" on one side. They are supplied in white HDPE bottles containing 60 tablets (NDC 50474-597-66). KEPPRA Oral Solution 100 mg/mL: a clear, colorless, grape-flavored liquid.
It is supplied in 16 fl. oz. white HDPE bottles (NDC 50474-001-48).
16.2Storage Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
16.2Storage Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION KEPPRA is an antiepileptic drug available as 250 mg (blue), 500 mg (yellow), 750 mg (orange), and 1000 mg (white) tablets and as a clear, colorless, grape-flavored liquid (100 mg/mL) for oral administration. The chemical name of levetiracetam, a single enantiomer, is (-)-(S)-α-ethyl-2-oxo-1-pyrrolidine acetamide, its molecular formula is C8H14N2O2 and its molecular weight is 170.21. Levetiracetam is chemically unrelated to existing antiepileptic drugs (AEDs).
It has the following structural formula: Levetiracetam is a white to off-white crystalline powder with a faint odor and a bitter taste. It is very soluble in water (104.0 g/100 mL). It is freely soluble in chloroform (65.3 g/100 mL) and in methanol (53.6 g/100 mL), soluble in ethanol (16.5 g/100 mL), sparingly soluble in acetonitrile (5.7 g/100 mL) and practically insoluble in n-hexane.
(Solubility limits are expressed as g/100 mL solvent.) KEPPRA tablets contain the labeled amount of levetiracetam. Inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, magnesium stearate, polyethylene glycol 3350, polyethylene glycol 6000, polyvinyl alcohol, talc, titanium dioxide, and additional agents listed below: 250 mg tablets: FD&C Blue #2/indigo carmine aluminum lake 500 mg tablets: iron oxide yellow 750 mg tablets: FD&C yellow #6/sunset yellow FCF aluminum lake, iron oxide red KEPPRA oral solution contains 100 mg of levetiracetam per mL.
Inactive ingredients: ammonium glycyrrhizinate, citric acid monohydrate, glycerin, maltitol solution, methylparaben, potassium acesulfame, propylparaben, purified water, sodium citrate dihydrate and natural and artificial flavor. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). The Medication Guide accompanies the product and can also be accessed on www.keppra.com or by calling 1-844-599-2273. Psychiatric Reactions and Changes in Behavior Advise patients that KEPPRA may cause changes in behavior (e.g. aggression, agitation, anger, anxiety, apathy, depression, hostility, and irritability) and psychotic symptoms [see Warnings and Precautions (5.1) ] .
Suicidal Behavior and Ideation Counsel patients, their caregivers, and/or families that antiepileptic drugs (AEDs), including KEPPRA, may increase the risk of suicidal thoughts and behavior and advise patients to be alert for the emergence or worsening of symptoms of depression; unusual changes in mood or behavior; or suicidal thoughts, behavior, or thoughts about self-harm. Advise patients, their caregivers, and/or families to immediately report behaviors of concern to a healthcare provider [see Warnings and Precautions (5.2) ] .
Effects on Driving or Operating Machinery Inform patients that KEPPRA may cause dizziness and somnolence. Inform patients not to drive or operate machinery until they have gained sufficient experience on KEPPRA to gauge whether it adversely affects their ability to drive or operate machinery [see Warnings and Precautions (5.3) ] . Anaphylaxis and Angioedema Advise patients to discontinue KEPPRA and seek medical care if they develop signs and symptoms of anaphylaxis or angioedema [see Warnings and Precautions (5.4) ].
Dermatological Adverse Reactions Advise patients that serious dermatological adverse reactions have occurred in patients treated with KEPPRA and instruct them to call their physician immediately if a rash develops [see Warnings and Precautions (5.5) ] . DRESS/Multiorgan Hypersensitivity Instruct patients and caregivers that a fever or rash associated with signs of other organ system involvement (e.g., lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately.
KEPPRA should be discontinued immediately if a serious hypersensitivity reaction is suspected [see Warnings and Precautions (5.6) ]. Withdrawal of KEPPRA Advise patients and caregivers not to discontinue use of KEPPRA without consulting with their healthcare provider. KEPPRA should normally be gradually withdrawn to reduce the potential of increased seizure frequency and status epilepticus [see Warnings and Precautions (5.8) ].
Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during KEPPRA therapy. Encourage patients to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry if they become pregnant [see Use in Specific Populations (8.1) ] .
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 3/2024 MEDICATION GUIDE KEPPRA ® (KEPP-ruh ) (levetiracetam) tablets, for oral use, and oral solution Read this Medication Guide before you start taking KEPPRA and each time you get a refill.
There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment. What is the most important information I should know about KEPPRA?
Like other antiepileptic drugs, KEPPRA may cause suicidal thoughts or actions in a very small number of people, about 1 in 500 people taking it. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Do not stop KEPPRA without first talking to a healthcare provider .
Stopping KEPPRA suddenly can cause serious problems. Stopping a seizure medicine suddenly can cause seizures that will not stop (status epilepticus). Suicidal thoughts or actions can be caused by things other than medicines.
If you have suicidal thoughts or actions, your healthcare provider may check for other causes. How can I watch for early symptoms of suicidal thoughts and actions? Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings.
Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms What is KEPPRA? KEPPRA is a prescription medicine taken by mouth that is used to treat partial-onset seizures in people 1 month of age and older.
KEPPRA is a prescription medicine taken by mouth that is used with other medicines to treat: myoclonic seizures in people 12 years of age and older with juvenile myoclonic epilepsy. primary generalized tonic-clonic seizures in people 6 years of age and older with certain types of generalized epilepsy. It is not known if KEPPRA is safe or effective in children under: 1 month of age to treat partial-onset seizures 12 years of age to treat myoclonic seizures 6 years of age to treat primary generalized tonic-clonic seizures Before taking your medicine, make sure you have received the correct medicine.
Compare the name above with the name on your bottle and the appearance of your medicine with the description of KEPPRA provided below. Tell your pharmacist immediately if you think you have been given the wrong medicine. Who should not take KEPPRA?
Do not take KEPPRA if you are allergic to levetiracetam. What should I tell my healthcare provider before starting KEPPRA? Before taking KEPPRA, tell your healthcare provider about all of your medical conditions, including if you: have or have had depression, mood problems or suicidal thoughts or behavior. have kidney problems. are pregnant or planning to become pregnant.
It is not known if KEPPRA will harm your unborn baby. You and your healthcare provider will have to decide if you should take KEPPRA while you are pregnant. If you become pregnant while taking KEPPRA, talk to your healthcare provider about registering with the North American Antiepileptic Drug Pregnancy Registry.
You can enroll in this registry by calling 1-888-233-2334 or go to http://www.aedpregnancyregistry.org. The purpose of this registry is to collect information about the safety of KEPPRA and other antiepileptic medicine during pregnancy. are breastfeeding or plan to breastfeed. KEPPRA can pass into your breast milk.
It is not known if the KEPPRA that passes into your breast milk can harm your baby. Talk to your doctor about the best way to fe… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of levetiracetam are similar when used as monotherapy or as adjunctive therapy for the treatment of partial-onset seizures. Absorption and Distribution Absorption of levetiracetam is rapid, with peak plasma concentrations occurring in about an hour following oral administration in fasted subjects. The oral bioavailability of levetiracetam tablets is 100% and the tablets and oral solution are bioequivalent in rate and extent of absorption.
Food does not affect the extent of absorption of levetiracetam but it decreases C max by 20% and delays T max by 1.5 hours. The pharmacokinetics of levetiracetam are linear over the dose range of 500-5000 mg. Steady state is achieved after 2 days of multiple twice-daily dosing.
Levetiracetam and its major metabolite are less than 10% bound to plasma proteins; clinically significant interactions with other drugs through competition for protein binding sites are therefore unlikely. Metabolism Levetiracetam is not extensively metabolized in humans. The major metabolic pathway is the enzymatic hydrolysis of the acetamide group, which produces the carboxylic acid metabolite, ucb L057 (24% of dose) and is not dependent on any liver cytochrome P450 isoenzymes.
The major metabolite is inactive in animal seizure models. Two minor metabolites were identified as the product of hydroxylation of the 2-oxo-pyrrolidine ring (2% of dose) and opening of the 2-oxo-pyrrolidine ring in position 5 (1% of dose). There is no enantiomeric interconversion of levetiracetam or its major metabolite.
Elimination Levetiracetam plasma half-life in adults is 7 ± 1 hour and is unaffected by either dose or repeated administration. Levetiracetam is eliminated from the systemic circulation by renal excretion as unchanged drug which represents 66% of administered dose. The total body clearance is 0.96 mL/min/kg and the renal clearance is 0.6 mL/min/kg.
The mechanism of excretion is glomerular filtration with subsequent partial tubular reabsorption. The metabolite ucb L057 is excreted by glomerular filtration and active tubular secretion with a renal clearance of 4 mL/min/kg. Levetiracetam elimination is correlated to creatinine clearance.
Levetiracetam clearance is reduced in patients with renal impairment [see Use in Specific Populations (8.6) and Dosage and Administration (2.5) ] . Specific Populations Elderly Pharmacokinetics of levetiracetam were evaluated in 16 elderly subjects (age 61-88 years) with creatinine clearance ranging from 30 to 74 mL/min. Following oral administration of twice-daily dosing for 10 days, total body clearance decreased by 38% and the half-life was 2.5 hours longer in the elderly compared to healthy adults.
This is most likely due to the decrease in renal function in these subjects. Pediatric Patients Pharmacokinetics of levetiracetam were evaluated in 24 pediatric patients (age 6-12 years) after single dose (20 mg/kg). The body weight adjusted apparent clearance of levetiracetam was approximately 40% higher than in adults.
A repeat dose pharmacokinetic study was conducted in pediatric patients (age 4-12 years) at doses of 20 mg/kg/day, 40 mg/kg/day, and 60 mg/kg/day. The evaluation of the pharmacokinetic profile of levetiracetam and its metabolite (ucb L057) in 14 pediatric patients demonstrated rapid absorption of levetiracetam at all doses with a T max of about 1 hour and a t 1/2 of 5 hours across the three dosing levels. The pharmacokinetics of levetiracetam in children was linear between 20 to 60 mg/kg/day.
The potential interaction of levetiracetam with other AEDs was also evaluated in these patients. Levetiracetam had no significant effect on the plasma concentrations of carbamazepine, valproic acid, topiramate or lamotrigine. However, there was about a 22% increase of apparent clearance of levetiracetam when it was co-administered with an enzyme-inducing AED (e.g. carbamazepine).
Following single dose administration (20 mg/kg) of a 10% oral solution… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effects on QTc Interval The effect of KEPPRA on QTc prolongation was evaluated in a randomized, double-blind, positive-controlled (moxifloxacin 400 mg) and placebo-controlled crossover study of KEPPRA (1000 mg or 5000 mg) in 52 healthy subjects. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 milliseconds. Therefore, there was no evidence of significant QTc prolongation in this study.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Partial-Onset Seizures Effectiveness in Partial-Onset Seizures in Adults The effectiveness of KEPPRA for the treatment of partial-onset seizures in adults was established in three multicenter, randomized, double-blind, placebo-controlled clinical studies in patients who had refractory partial-onset seizures with or without secondary generalization. The tablet formulation was used in all these studies. In these studies, 904 patients were randomized to placebo, 1000 mg, 2000 mg, or 3000 mg/day.
Patients enrolled in Study 1 or Study 2 had refractory partial-onset seizures for at least two years and had taken two or more classical AEDs. Patients enrolled in Study 3 had refractory partial-onset seizures for at least 1 year and had taken one classical AED. At the time of the study, patients were taking a stable dose regimen of at least one and could take a maximum of two AEDs.
During the baseline period, patients had to have experienced at least two partial- onset seizures during each 4-week period. Study 1 Study 1 was a double-blind, placebo-controlled, parallel-group study conducted at 41 sites in the United States comparing KEPPRA 1000 mg/day (N=97), KEPPRA 3000 mg/day (N=101), and placebo (N=95) given in equally divided doses twice daily. After a prospective baseline period of 12 weeks, patients were randomized to one of the three treatment groups described above.
The 18-week treatment period consisted of a 6-week titration period, followed by a 12-week fixed dose evaluation period, during which concomitant AED regimens were held constant. The primary measure of effectiveness was a between group comparison of the percent reduction in weekly partial seizure frequency relative to placebo over the entire randomized treatment period (titration + evaluation period). Secondary outcome variables included the responder rate (incidence of patients with ≥50% reduction from baseline in partial-onset seizure frequency).
The results of the analysis of Study 1 are displayed in Table 10. Table 10: Reduction in Mean Over Placebo in Weekly Frequency of Partial-Onset Seizures in Study 1 Placebo (N=95) KEPPRA 1000 mg/day (N=97) KEPPRA 3000 mg/day (N=101) Percent reduction in partial seizure frequency over placebo – 26.1% statistically significant versus placebo 30.1% The percentage of patients (y-axis) who achieved ≥50% reduction in weekly seizure rates from baseline in partial-onset seizure frequency over the entire randomized treatment period (titration + evaluation period) within the three treatment groups (x-axis) is presented in Figure 1.
Figure 1: Responder Rate (≥50% Reduction from Baseline) in Study 1 *statistically significant versus placebo Figure 1 Study 2 Study 2 was a double-blind, placebo-controlled, crossover study conducted at 62 centers in Europe comparing KEPPRA 1000 mg/day (N=106), KEPPRA 2000 mg/day (N=105), and placebo (N=111) given in equally divided doses twice daily. The first period of the study (Period A) was designed to be analyzed as a parallel-group study. After a prospective baseline period of up to 12 weeks, patients were randomized to one of the three treatment groups described above.
The 16-week treatment period consisted of the 4-week titration period followed by a 12-week fixed dose evaluation period, during which concomitant AED regimens were held constant. The primary measure of effectiveness was a between group comparison of the percent reduction in weekly partial seizure frequency relative to placebo over the entire randomized treatment period (titration + evaluation period). Secondary outcome variables included the responder rate (incidence of patients with ≥50% reduction from baseline in partial-onset seizure frequency).
The results of the analysis of Period A are displayed in Table 11. Table 11: Reduction in Mean Over Placebo in Weekly Frequency of Partial-Onset Seizures in Study 2: Period A Placebo (N=111) KEPPRA 1000 mg/day (N=106) KEPPRA 2000 mg/day (N=105) Percent reduction in… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Rats were dosed with levetiracetam in the diet for 104 weeks at doses of 50, 300, and 1800 mg/kg/day. Plasma exposure (AUC) at the highest dose was approximately 6 times that in humans at the maximum recommended daily human dose (MRHD) of 3000 mg. There was no evidence of carcinogenicity.
In mice, oral administration of levetiracetam for 80 weeks (doses up to 960 mg/kg/day) or 2 years (doses up to 4000 mg/kg/day, lowered to 3000 mg/kg/day after 45 weeks due to intolerability) was not associated with an increase in tumors. The highest dose tested in mice for 2 years (3000 mg/kg/day) is approximately 5 times the MRHD on a body surface area (mg/m 2 ) basis. Mutagenesis Levetiracetam was negative in in vitro (Ames, chromosomal aberration in mammalian cells) and in vivo (mouse micronucleus) assays.
The major human metabolite of levetiracetam (ucb L057) was negative in in vitro (Ames, mouse lymphoma) assays. Impairment of Fertility No adverse effects on male or female fertility or reproductive performance were observed in rats at oral doses up to 1800 mg/kg/day, which were associated with plasma exposures (AUC) up to approximately 6 times that in humans at the MRHD.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Rats were dosed with levetiracetam in the diet for 104 weeks at doses of 50, 300, and 1800 mg/kg/day. Plasma exposure (AUC) at the highest dose was approximately 6 times that in humans at the maximum recommended daily human dose (MRHD) of 3000 mg. There was no evidence of carcinogenicity.
In mice, oral administration of levetiracetam for 80 weeks (doses up to 960 mg/kg/day) or 2 years (doses up to 4000 mg/kg/day, lowered to 3000 mg/kg/day after 45 weeks due to intolerability) was not associated with an increase in tumors. The highest dose tested in mice for 2 years (3000 mg/kg/day) is approximately 5 times the MRHD on a body surface area (mg/m 2 ) basis. Mutagenesis Levetiracetam was negative in in vitro (Ames, chromosomal aberration in mammalian cells) and in vivo (mouse micronucleus) assays.
The major human metabolite of levetiracetam (ucb L057) was negative in in vitro (Ames, mouse lymphoma) assays. Impairment of Fertility No adverse effects on male or female fertility or reproductive performance were observed in rats at oral doses up to 1800 mg/kg/day, which were associated with plasma exposures (AUC) up to approximately 6 times that in humans at the MRHD.
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.6 ) 3/2024
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 250 mg Tablet Bottle Label NDC 50474-594-40 120 tablets Keppra ® (levetiracetam) 250 mg tablets Dispense accompanying Medication Guide to each patient. Rx only PRINCIPAL DISPLAY PANEL - 250 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 500 mg Tablet Bottle Label NDC 50474-595-40 120 tablets Keppra ® (levetiracetam) 500 mg tablets Dispense accompanying Medication Guide to each patient. Rx only PRINCIPAL DISPLAY PANEL - 500 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 750 mg Tablet Bottle Label NDC 50474-596-40 120 tablets Keppra ® (levetiracetam) 750 mg tablets Dispense accompanying Medication Guide to each patient. Rx only PRINCIPAL DISPLAY PANEL - 750 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 1000 mg Tablet Bottle Label NDC 50474-597-66 60 tablets Keppra ® (levetiracetam) 1000 mg tablets Dispense accompanying Medication Guide to each patient. Rx only PRINCIPAL DISPLAY PANEL - 1000 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 473 mL Bottle Label NDC 50474-001-48 Keppra ® (levetiracetam) 100 mg/mL oral solution Dispense accompanying Medication Guide to each patient. Rx only 16 fl oz (473 mL) PRINCIPAL DISPLAY PANEL - 473 mL Bottle Label