
CLONIDINE HCI 100 ug/mL Injection, Solution — NDC 51662-1346-1 (Billing 51662-1346-01)
This is a package of CLONIDINE HCI 100 ug/mL Injection, Solution from HF Acquisition Co LLC, DBA HealthFirst, marketed since Dec 2018 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 51662-1346-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 51662 labeler · 1346 product · 1 package
- Package marketed since
- Dec 23, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5166213461 0
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 884221
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Tablets, oral solutions, Nexiclon XR and patches lower high blood pressure. Certain extended-release products treat ADHD. The epidural injection is used...
- No. Stopping suddenly can cause rebound high blood pressure, with headache, a racing heart, nervousness and anxiety. Your doctor will lower the dose gradually.
- Sleepiness is common. Don't drive or use heavy equipment until you know how it affects you. Avoid alcohol, and ask me before combining it with other sedating medicines.
- No. Extended-release clonidine tablets should be swallowed whole, not crushed, chewed or broken. They can be taken with or without food.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1346-01 You're viewing this Main listing | 1 VIAL, SINGLE-USE in 1 BOX / 10 mL in 1 VIAL, SINGLE-USE | 2018-12-23 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clonidine Hydrochloride 100 ug/mL 00143-9724-01 | Hikma | 10 ml | — | AP | FDA listed | — |
| Clonidine 100 ug/mL 39822-2000-01 | XGen | 10 ml | — | AP | FDA listed | — |
| Clonidine Hci 100 ug/mLthis 51662-1346-01 | HF | 1 vial | — | AP | FDA listed | — |
| Duraclon .1 mg/mL 67457-0218-10 | Mylan | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
9 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from HF Acquisition Co LLC, DBA HealthFirst labeler code 51662
- DOBUTAMINE 12.5 mg/mL Injection, Solution, Concentrate NDC 51662-1337-1
- PROPRANOLOL HYDROCHLORIDE 1 mg/mL Injection NDC 51662-1338-1
- Nitroglycerin 20 mg/g Ointment NDC 51662-1340-1
- AMINOPHYLLINE 25 mg/mL Injection, Solution NDC 51662-1341-1
- SODIUM CHLORIDE 9 mg/mL Injection, Solution NDC 51662-1342-1
- DEXAMETHASONE SODIUM PHOSPHATE 10 mg/mL Injection NDC 51662-1343-1
- CALCIUM GLUCONATE 98 mg/mL Injection, Solution NDC 51662-1347-1
- DIPHENHYDRAMINE HYDROCHLORIDE 50 mg/mL Injection, Solution NDC 51662-1348-1
- MAGNESIUM SULFATE 40 mg/mL Injection, Solution NDC 51662-1352-1
- ROCURONIUM BROMIDE 10 mg/mL Injection, Solution NDC 51662-1354-1
- ROCURONIUM BROMIDE 10 mg/mL Injection, Solution NDC 51662-1355-1
- Aspirin Low Dose Chewable Orange Pain Reliever 81 mg Tablet, Chewable NDC 51662-1356-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Clonidine hydrochloride is indicated in combination with opiates for the treatment of severe pain in cancer patients that is not adequately relieved by opioid analgesics alone. Epidural clonidine is more likely to be effective in patients with neuropathic pain than somatic or visceral pain (see CLINICAL PHARMACOLOGY : Clinical Trials). The safety of this drug product has only been established in a highly selected group of cancer patients, and only after an adequate trial of opioid analgesia.
Other use is of unproven safety and is not recommended. In a rare patient, the potential benefits may outweigh the known risks (see WARNINGS ).
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION The recommended starting dose of clonidine hydrochloride injection for continuous epidural infusion is 30 mcg/hr. Although dosage may be titrated up or down depending on pain relief and occurrence of adverse events, experience with dosage rates above 40 mcg/hr is limited. Familiarization with the continuous epidural infusion device is essential.
Patients receiving epidural clonidine from a continuous infusion device should be closely monitored for the first few days to assess their response. The 500 mcg/mL (0.5mg/mL) strength product must be diluted prior to use in 0.9% Sodium Chloride for Injection, USP, to a final concentration of 100 mcg/mL: Renal Impairment: Dosage should be adjusted according to the degree of renal impairment, and patients should be carefully monitored. Since only a minimal amount of clonidine is removed during routine hemodialysis, there is no need to give supplemental clonidine following dialysis.
Clonidine hydrochloride injection must not be used with a preservative. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit. DOSAGE
⛔ Contraindications ▾
CONTRAINDICATIONS Clonidine hydrochloride injection is contraindicated in patients with a history of sensitization or allergic reactions to clonidine. Epidural administration is contraindicated in the presence of an injection site infection, in patients on anticoagulant therapy, and in those with a bleeding diathesis. Administration of clonidine hydrochloride injection above the C4 dermatome is contraindicated since there are no adequate safety data to support such use (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Use in Postoperative or Obstetrical Analgesia Clonidine hydrochloride injection (epidural clonidine) is not recommended for obstetrical, post-partum, or peri-operative pain management. The risk of hemodynamic instability, especially hypotension and bradycardia, from epidural clonidine may be unacceptable in these patients. Hypotension Because severe hypotension may follow the administration of clonidine, it should be used with caution in all patients.
It is not recommended in most patients with severe cardiovascular disease or in those who are otherwise hemodynamically unstable. The benefit of its administration in these patients should be carefully balanced against the potential risks resulting from hypotension. Vital signs should be monitored frequently, especially during the first few days of epidural clonidine therapy.
When clonidine is infused into the upper thoracic spinal segments, more pronounced decreases in the blood pressure may be seen. Clonidine decreases sympathetic outflow from the central nervous system resulting in decreases in peripheral resistance, renal vascular resistance, heart rate, and blood pressure. However, in the absence of profound hypotension, renal blood flow and glomerular filtration rate remain essentially unchanged.
In the pivotal double-blind, randomized study of cancer patients, where 38 subjects were administered epidural clonidine hydrochloride injection at 30 mcg/hr in addition to epidural morphine, hypotension occurred in 45% of subjects. Most episodes of hypotension occurred within the first four days after beginning epidural clonidine. However, hypotensive episodes occurred throughout the duration of the trial.
There was a tendency for these episodes to occur more commonly in women, and in those with higher serum clonidine levels. Patients experiencing hypotension also tended to weigh less than those who did not experience hypotension. The hypotension usually responded to intravenous fluids and, if necessary, parenterally-administered pressor agents.
Published reports on the use of epidural clonidine for intraoperative or postoperative analgesia also show a consistent and marked hypotensive response to clonidine. Severe hypotension may occur even if intravenous fluid pretreatment is given. Withdrawal Sudden cessation of clonidine treatment, regardless of the route of administration, has, in some cases, resulted in symptoms such as nervousness, agitation, headache, and tremor, accompanied or followed by a rapid rise in blood pressure.
The likelihood of such reactions appears to be greater after administration of higher doses or with concomitant beta-blocker treatment. Special caution is therefore advised in these situations. Rare instances of hypertensive encephalopathy, cerebrovascular accidents and death have been reported after abrupt clonidine withdrawal.
Patients with a history of hypertension and/or other underlying cardiovascular conditions may be at particular risk of the consequences of abrupt discontinuation of clonidine. In the pivotal double-blind, randomized cancer pain study, four of 38 subjects receiving 720 mcg of clonidine per day experienced rebound hypertension following abrupt withdrawal. One of these patients with rebound hypertension subsequently experienced a cerebrovascular accident.
Careful monitoring of infusion pump function and inspection of catheter tubing for obstruction or dislodgement can help reduce the risk of inadvertent abrupt withdrawal of epidural clonidine. Patients should notify their physician immediately if clonidine administration is inadvertently interrupted for any reason. Patients should also be instructed not to discontinue therapy without consulting their physician.
When discontinuing therapy with epidural clonidine, the physician should reduce the dose gradually over 2 to 4 days to avoid withdrawal symptoms. An excessive rise in blood pressure following discontinuation of epidural clonidine can be treated by administration of clo… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions seen during continuous epidural clonidine infusion are dose-dependent and typical for a compound of this pharmacologic class. The adverse events most frequently reported in the pivotal controlled clinical trial of continuous epidural clonidine administration consisted of hypotension, postural hypotension, decreased heart rate, rebound hypertension, dry mouth, nausea, confusion, dizziness, somnolence, and fever. Hypotension is the adverse event that most frequently requires treatment.
The hypotension is usually responsive to intravenous fluids and, if necessary, appropriate parenterally-administered pressor agents. Hypotension was observed more frequently in women and in lower weight patients, but no dose-related response was established. Implantable epidural catheters are associated with a risk of catheter-related infections, including meningitis and/or epidural abscess.
The risk depends on the clinical situation and the type of catheter used, but catheter related infections occur in 5%-20% of patients, depending on the kind of catheter used, catheter placement technique, quality of the catheter care, and length of catheter placement. The inadvertent intrathecal administration of clonidine has not been associated with a significantly increased risk of adverse events, but there are inadequate safety and efficacy data to support the use of intrathecal clonidine. Epidural clonidine was compared to placebo in a two week double-blind study of 85 terminal cancer patients with intractable pain receiving epidural morphine.
The following adverse events were reported in two or more patients and may be related to administration of either clonidine hydrochloride injection or morphine. Incidence of Adverse Events in the Two-Week Trial An open label long-term extension of the above trial was performed. Thirty-two subjects received epidural clonidine and morphine for up to 94 weeks with a median dosing period of 10 weeks.
The following adverse events (and percent incidence) were reported: hypotension/postural hypotension (47%); nausea (13%); anxiety/confusion (38%); somnolence (25%); urinary tract infection (22%); constipation, dyspnea, fever, infection (6% each); asthenia, hyperaesthesia, pain, skin ulcer, and vomiting (5% each). Eighteen percent of subjects discontinued this study as a result of catheter-related problems (infections, accidental dislodging, etc.), and one subject developed meningitis, possibly as a result of catheter-related infection.
In this study, rebound hypertension was not assessed, and ECG and laboratory data not systematically sought. The following adverse reactions have also been reported with the use of any dosage form of clonidine. In many cases patients were receiving concomitant medication and a causal relationship has not been established: Body as a Whole: Weakness, 10%; fatigue, 4%; headache and withdrawal syndrome, each 1%.
Also reported were pallor, a weakly positive Coomb’s test, and increased sensitivity to alcohol. Cardiovascular: Palpitations and tachycardia, and bradycardia, each 0.5%. Syncope, Raynaud’s phenomenon, congestive heart failure, and electrocardiographic abnormalities (i.e., sinus node arrest, functional bradycardia, high degree AV block) have been reported rarely.
Rare cases of sinus bradycardia and atrioventricular block have been reported, both with and without the use of concomitant digitalis. Central Nervous System: Nervousness and agitation, 3%; mental depression, 1%; insomnia, 0.5%. Cerebrovascular accidents, other behavioral changes, vivid dreams or nightmares, restlessness, and delirium have been reported rarely.
Dermatological: Rash, 1%; pruritus, 0.7%; hives, angioneurotic edema and urticaria, 0.5%; alopecia, 0.2%. Gastrointestinal: Anorexia and malaise, each 1%; mild transient abnormalities in liver function tests, 1%; hepatitis, parotitis, ileus and pseudo obstruction, and abdominal pain, rarely. Genitourinary: Decreased sexual activity, impo… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
OVERDOSAGE Hypertension may develop early and may be followed by hypotension, bradycardia, respiratory depression, hypothermia, drowsiness, decreased or absent reflexes, irritability, and miosis. With large oral overdoses, reversible cardiac conduction defects or arrhythmias, apnea, coma, and seizures have been reported. As little as 100 mcg of oral clonidine has produced signs of toxicity in pediatric patients.
There is no specific antidote for clonidine overdosage. Supportive care may include atropine sulfate for bradycardia, intravenous fluids and/or vasopressor agents for hypotension. Hypertension associated with overdosage has been treated with intravenous furosemide, diazoxide or alpha-blocking agents such as phentolamine.
Naloxone may be a useful adjunct in the treatment of clonidine-induced respiratory depression, hypotension, and/or coma; blood pressure should be monitored since the administration of naloxone has occasionally resulted in paradoxical hypertension. Tolazoline administration has yielded inconsistent results and is not recommended as first-line therapy. Dialysis is not likely to significantly enhance the elimination of clonidine.
The largest overdose reported to date involved a 28-year old white male who ingested 100 mg of clonidine hydrochloride powder. This patient developed hypertension, followed by hypotension, bradycardia, apnea, hallucinations, semi-coma, and premature ventricular contractions. The patient fully recovered after intensive treatment.
Plasma clonidine levels were 60 ng/mL after 1 hour, 190 ng/mL after 1.5 hours, 370 ng/mL after 2 hours, and 120 ng/mL after 5.5 and 6.5 hours. In mice and rats, the oral LD50 of clonidine is 206 and 465 mg/kg, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Epidurally administered clonidine produces dose-dependent analgesia not antagonized by opiate antagonists. The analgesia is limited to the body regions innervated by the spinal segments where analgesic concentrations of clonidine are present. Clonidine is thought to produce analgesia at presynaptic and postjunctional alpha-2-adrenoceptors in the spinal cord by preventing pain signal transmission to the brain.
Pharmacokinetics Following a 10 minute intravenous infusion of 300 mcg clonidine HCl to five male volunteers, plasma clonidine levels showed an initial rapid distribution phase (mean ± SD t1/2= 11 ± 9 minutes) followed by a slower elimination phase (t1/2= 9 ± 2 hours) over 24 hours. Clonidine’s total body clearance (CL) was 219 ± 92 mL/min. Following a 700 mcg clonidine HCl epidural dose given over five minutes to four male and five female volunteers, peak clonidine plasma levels (4.4 ± 1.4 ng/mL) were obtained in 19 ± 27 minutes.
The plasma elimination half-life was determined to be 22 ± 15 hours following sample collection for 24 hours. CL was 190 ± 70 mL/min. In cerebral spinal fluid (CSF), peak clonidine levels (418 ± 255 ng/mL) were achieved in 26 ± 11 minutes.
The clonidine CSF elimination half-life was 1.3 ± 0.5 hours when samples were collected for 6 hours. Compared to men, women had a lower mean plasma clearance, longer mean plasma half-life, and higher mean peak level of clonidine in both plasma and CSF. In cancer patients who received 14 days of clonidine HCl epidural infusion (rate = 30 mcg/hr) plus morphine by patient-controlled analgesia (PCA), steady state clonidine plasma concentrations of 2.2 ± 1.1 and 2.4 ± 1.4 ng/mL were obtained on dosing days 7 and 14, respectively.
CL was 279 ± 184 and 272 ± 163 mL/min on these days. CSF concentrations were not determined in these patients. Distribution Clonidine is highly lipid soluble and readily distributes into extravascular sites including the central nervous system.
Clonidine’s volume of distribution is 2.1 ±
0.4L/kg. The binding of clonidine to plasma protein is primarily to albumin and varies between 20 and 40% in vitro. Epidurally administered clonidine readily partitions into plasma via the epidural veins and attains systemic concentrations (0.5 – 2.0 ng/mL) that are associated with a hypotensive effect mediated by the central nervous system.
Excretion Following an intravenous dose of 14C-clonidine, 72% of the administered dose was excreted in urine in 96 hours of which 40 - 50% was unchanged clonidine. Renal clearance for clonidine was determined to be 133 ± 66 mL/min. In a study where 14C-clonidine was given to subjects with varying degrees of kidney function, elimination half-lives varied (17.5 to 41 hours) as a function of creatinine clearance.
In subjects undergoing hemodialysis only 5% of body clonidine stores were removed. Metabolism In humans, clonidine metabolism follows minor pathways with the major metabolite, p-hydroxy-clonidine, being present at less than 10% of the concentration of uncharged drug in urine. Special Populations The pharmacokinetics of epidurally administered clonidine has not been studied in the pediatric population or in patients with renal or hepatic disease.
Clinical Trials In a double-blind, randomized study of cancer patients with severe intractable pain below the C4 dermatome not controlled by morphine, 38 patients were randomized to an epidural infusion of clonidine hydrochloride injection plus epidural morphine, whereas 47 subjects received epidural placebo plus epidural morphine. Both groups were allowed rescue doses of epidural morphine. Successful analgesia, defined as a decrease in either morphine use or Visual Analog Score (VAS) pain, was significantly more common with epidural clonidine than placebo (45% vs 21%, p=0.016).
Only the subgroup of 36 patients with “neuropathic” pain, characterized by the investigator was well-localized, burning, shooting, or electric-like pain… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
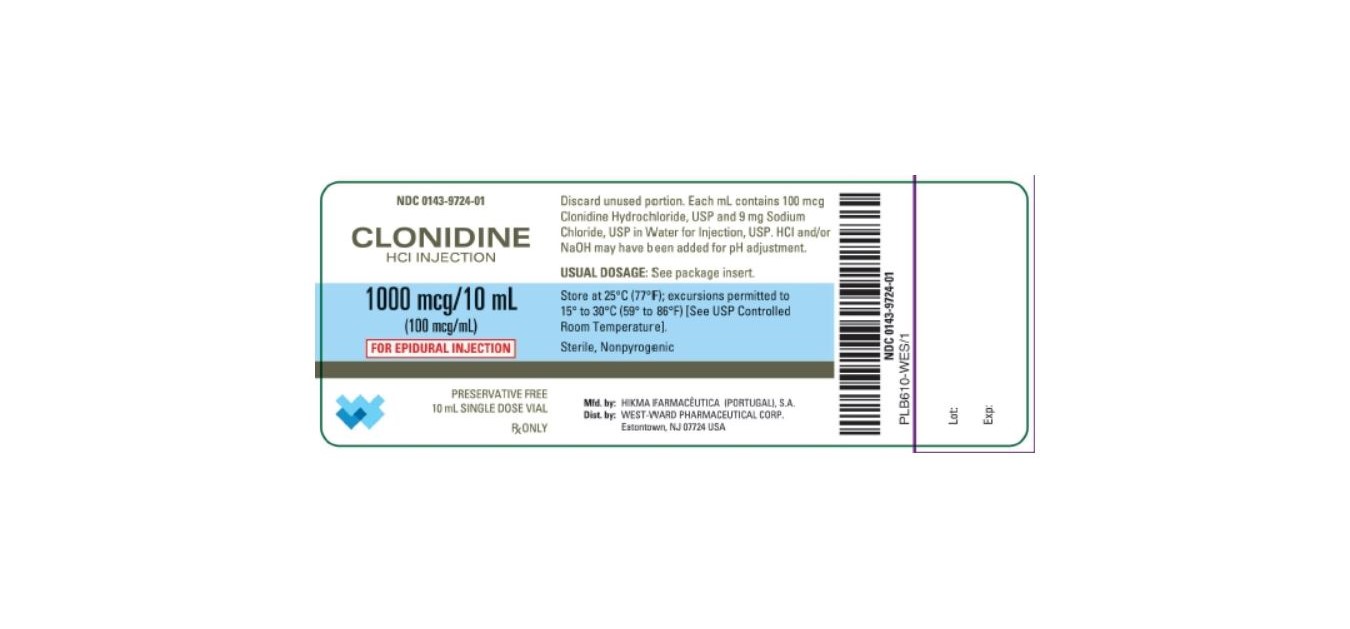
HOW SUPPLIED CLONIDINE HCI INJECTION is supplied in the following dosage forms. NDC 51662-1346-1 CLONIDINE HCI INJECTION 1000mcg/10mL (100mcg/mL) 10mL VIAL HF Acquisition Co LLC, DBA HealthFirst Mukilteo, WA 98275 Also supplied in the following manufacture supplied dosage forms NDC 0143-9724-01, 100 mcg/mL solution in 10 mL vials, packaged individually. NDC 0143-9723-01, 500 mcg/mL solution in 10 mL vials, packaged individually.
Store at 25ºC (77ºF); excursions permitted to 15º to 30ºC (59º to 86ºF) [See USP Controlled Room Temperature]. Preservative Free. Discard unused portion.
Manufactured by: HIKMA FARMACÊUTICA (PORTUGAL), S.A. Estrada do Rio da Mó, nº 8, 8A e 8B – Fervença 2705 – 906 Terrugem SNT PORTUGAL Distributed by: WEST-WARD PHARMACEUTICAL Corp. 465 Industrial Way West Eatontown, NJ 07724 USA Revised: March 2011
📋 Description ▾
DESCRIPTION Clonidine hydrochloride injection is a centrally-acting solution for use in continuous epidural infusion devices. Clonidine Hydrochloride, USP, is an imidazoline derivative and exists as a mesomeric compound. The chemical names are Benzenamine, 2, 6-dichloro-N-2-imidazolidinylidene monohydrochloride and 2-[(2,6-dichlorophenyl) imino]imidazolidine monohydrochloride.
The following is the structural formula: Clonidine hydrochloride injection is supplied as a clear, colorless, preservative-free, pyrogen-free, aqueous sterile solution (pH 5 to 7) in 10 mL single-dose vials. Each mL of the 1000 mcg/10 mL (0.1 mg/mL) concentration contains 100 mcg of Clonidine Hydrochloride, USP and 9 mg Sodium Chloride, USP in Water for Injection, USP. Hydrochloric acid and/or sodium hydroxide may have been added for pH adjustment.
Each 10 mL vial contains 1mg (1000 mcg) of clonidine hydrochloride. Each mL of the 5000 mcg/10 mL (0.5 mg/mL) concentration contains 500 mcg of Clonidine Hydrochloride, USP and 9 mg Sodium Chloride, USP in Water for Injection, USP. Hydrochloric acid and/or sodium hydroxide may have been added for pH adjustment.
Each 10 mL vial contains 5 mg (5000 mcg) of clonidine hydrochloride. STRUCTURE
⚠️ Precautions ▾
PRECAUTIONS General Cardiac Effects: Epidural clonidine frequently causes decreases in heart rate. Symptomatic bradycardia can be treated with atropine. Rarely, atrioventricular block greater than first degree has been reported.
Clonidine does not alter the hemodynamic response to exercise, but may mask the increase in heart rate associated with hypovolemia. Respiratory Depression and Sedation: Clonidine administration may result in sedation through the activation of alpha-adrenoceptors in the brainstem. High doses of clonidine cause sedation and ventilatory abnormalities that are usually mild.
Tolerance to these effects can develop with chronic administration. These effects have been reported with bolus doses that are significantly larger than the infusion rate recommended for treating cancer pain. Depression: Depression has been seen in a small percentage of patients treated with oral or transdermal clonidine.
Depression commonly occurs in cancer patients and may be exacerbated by treatment with clonidine. Patients, especially those with a known history of affective disorders, should be monitored for the signs and symptoms of depression. Pain of Visceral or Somatic Origin: In the clinical investigations, at doses tested, clonidine hydrochloride injection was most effective in well-localized, “neuropathic” pain that was characterized as electrical, burning, or shooting in nature, and which was localized to a dermatomal or peripheral nerve distribution.
Clonidine hydrochloride injection may be less effective, or possibly ineffective in the treatment of pain that is diffuse, poorly localized, or visceral in origin. Information for Patients Patients should be instructed about the risks of rebound hypertension and warned not to discontinue clonidine except under the supervision of a physician. Patients should notify their physician immediately if clonidine administration is inadvertently interrupted for any reason.
Patients who engage in potentially hazardous activities, such as operating machinery or driving, should be advised of the potential sedative and hypotensive effects of epidural clonidine. They should also be informed that sedative effects may be increased by CNS-depressing drugs such as alcohol and barbiturates, and that hypotensive effects may be increased by opiates. Drug Interactions Clonidine may potentiate the CNS-depressive effect of alcohol, barbiturates or other sedating drugs.
Narcotic analgesics may potentiate the hypotensive effects of clonidine. Tricyclic antidepressants may antagonize the hypotensive effects of clonidine. The effects of tricyclic antidepressants on clonidine’s analgesic actions are not known.
Beta-blockers may exacerbate the hypertensive response seen with clonidine withdrawal. Also, due to the potential for additive effects such as bradycardia and AV block, caution is warranted in patients receiving clonidine with agents known to affect sinus node function or AV nodal conduction, e.g., digitalis, calcium channel blockers, and beta-blockers. There is one reported case of a patient with acute delirium associated with the simultaneous use of fluphenazine and oral clonidine.
Symptoms resolved when clonidine was withdrawn and recurred when the patient was rechallenged with clonidine. Epidural clonidine may prolong the duration of pharmacologic effects of epidural local anesthetics, including both sensory and motor blockade. Carcinogenesis, Mutagenesis, Impairment of Fertility In a 132-week study in rats, clonidine hydrochloride administered as a dietary admixture at 5-8 times (based on body surface area) the 50 mcg/kg maximum recommended daily human dose (MRDHD) for hypertension did not show any carcinogenic potential.
Clonidine was inactive in the Ames test of mutagenicity. Fertility of male or female rats was unaffected by oral clonidine hydrochloride doses as high as 150 mcg/kg, or about 0.5 times the MRDHD. Fertility of female rats did, however, appear to be affected in another experiment… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL-VIAL LABEL VIAL LABEL
PRINCIPLE DISPLAY PANEL-LABELED VIAL AND BOX LABELED VIAL AND BOX
PRINCIPAL DISPLAY PANEL-SERIALIZED BOX CONTAINING VIAL SERIALIZED BOX
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |