
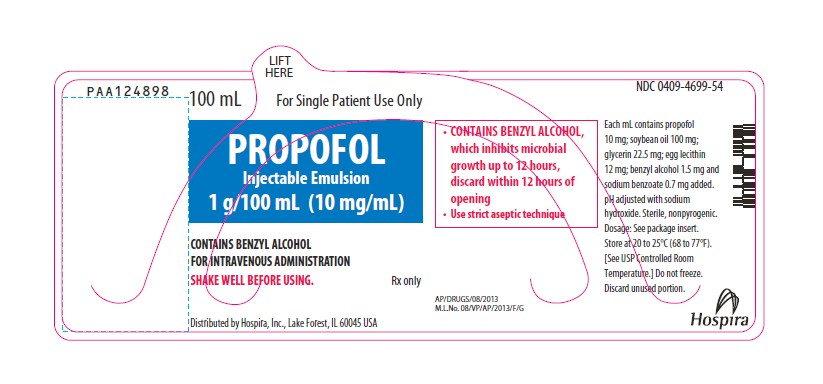
PROPOFOL 10 mg/mL Injection, Emulsion, 100 mL — NDC 51662-1470-1 (Billing 51662-1470-01)
This is a package of 100 mL of PROPOFOL 10 mg/mL Injection, Emulsion from HF Acquisition Co LLC, DBA HealthFirst, marketed since Dec 2019 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 1808217
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the General Anesthetic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Propofol is given through a vein to put you under general anesthesia or to provide sedation during procedures. It is also used to sedate adults in the ICU who are on a breathing ma...
- Some people feel burning, stinging, or pain at the IV site, and this is one of the more common effects. Your team can reduce it by using a larger vein or giving lidocaine first. An...
- Low blood pressure, a slower heart rate, and a short pause in breathing are the most common. Your team watches for these and treats them. You may also get a rash, itching, or invol...
- Yes. Tell them if you have ever had a severe allergic reaction to eggs, egg products, soybeans, or soy products, because propofol should not be used in that case. Also mention epil...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Propofol — tap one for details:
Propofol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2704 | $0.089 / J2704 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1470-01 You're viewing this Main listing | 100 mL in 1 VIAL | 2019-12-14 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| propofol 10 mg/mL 25021-0608-20 | Sagent | 25 vials | $0.171 | AB | Availability likely | — |
| propofol 10 mg/mL 71288-0730-51 | Meitheal | 10 vials | $0.171 | AB | Availability likely | — |
| Propofol 10 mg/mL 00409-6010-25 | Hospira, | 25 vials | $0.171 | AB | Availability likely | — |
| Propofol 10 mg/mL 00409-1511-98 | Hospira, | 25 vials | $0.171 | AB | Availability likely | — |
| Propofol 10 mg/mL 00069-0248-10 | Pfizer | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00409-4699-24 | Hospira, | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00641-6196-10 | Hikma | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 16714-0690-10 | NorthStar | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 23155-0345-41 | Heritage | 10 vials | — | AB | FDA listed | — |
| Propofol Injectable Emulsion 10 mg/mL 43598-0549-10 | Dr. | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mLthis 51662-1470-01 | HF | 100 ml | — | AB | FDA listed | — |
| Diprivan 10 mg/mL 63323-0269-59 | Fresenius | 20 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 71288-0731-53 | Meitheal | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 72572-0612-10 | Civica, | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 80830-2365-07 | Amneal | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 83634-0603-20 | Avenacy, | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00641-6194-10 | Hikma | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00641-6195-20 | Hikma | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 51662-1293-01 | HF | 20 ml | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00069-0234-20 | Pfizer | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 51662-1471-01 | HF | 50 ml | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00069-0209-10 | Pfizer | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 72572-0590-10 | Civica, | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 71288-0729-21 | Meitheal | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 80830-2364-08 | Amneal | 20 vials | — | AB | FDA listed | — |
| Diprivan 10 mg/mL 65219-0800-10 | Fresenius | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 80830-1188-07 | Amneal | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 16714-0977-20 | NorthStar | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 72572-0601-20 | Civica, | 20 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 16714-0528-10 | NorthStar | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 83854-0018-10 | Anthea | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00409-0501-98 | Hospira, | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00409-0010-98 | Hospira, | 10 vials | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Propofol injectable emulsion is an IV general anesthetic and sedation drug that can be used as described in the table below. TABLE 3. INDICATIONS FOR PROPOFOL INJECTABLE EMULSION Safety, effectiveness and dosing guidelines for propofol injectable emulsion have not been established for MAC Sedation in the pediatric population; therefore, it is not recommended for this use (see PRECAUTIONS , Pediatric Use).
Propofol injectable emulsion is not recommended for induction of anesthesia below the age of 3 years or for maintenance of anesthesia below the age of 2 months because its safety and effectiveness have not been established in those populations. In the Intensive Care Unit (ICU), propofol injectable emulsion can be administered to intubated, mechanically ventilated adult patients to provide continuous sedation and control of stress responses only by persons skilled in the medical management of critically ill patients and trained in cardiovascular resuscitation and airway management.
Propofol injectable emulsion is not indicated for use in Pediatric ICU sedation since the safety of this regimen has not been established (see PRECAUTIONS , Pediatric Use). Propofol injectable emulsion is not recommended for obstetrics, including Cesarean section deliveries. Propofol injectable emulsion crosses the placenta, and as with other general anesthetic agents, the administration of propofol injectable emulsion may be associated with neonatal depression (see PRECAUTIONS ).
Propofol is not recommended for use in nursing mothers because propofol injectable emulsion has been reported to be excreted in human milk, and the effects of oral absorption of small amounts of propofol are not known (see PRECAUTIONS ). INDICATIONS & USAGE
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION NOTE: CONTAINS BENZYL ALCOHOL (see PRECAUTIONS ). Propofol blood concentrations at steady-state are generally proportional to infusion rates, especially in individual patients. Undesirable effects such as cardiorespiratory depression are likely to occur at higher blood concentrations which result from bolus dosing or rapid increases in the infusion rate.
An adequate interval (3 minutes to 5 minutes) must be allowed between dose adjustments to allow for and assess the clinical effects. Shake well before use. Do not use if there is evidence of excessive creaming or aggregation, if large droplets are visible, or if there are other forms of phase separation indicating that the stability of the product has been compromised.
Slight creaming, which should disappear after shaking, may be visible upon prolonged standing. When administering propofol injectable emulsion by infusion, syringe or volumetric pumps are recommended to provide controlled infusion rates. When infusing propofol injectable emulsion to patients undergoing magnetic resonance imaging, metered control devices may be utilized if mechanical pumps are impractical.
Changes in vital signs indicating a stress response to surgical stimulation or the emergence from anesthesia may be controlled by the administration of 25 mg (2.5 mL) to 50 mg (5 mL) incremental boluses and/or by increasing the infusion rate of propofol injectable emulsion. For minor surgical procedures (e.g., body surface) nitrous oxide (60% to 70%) can be combined with a variable rate propofol injectable emulsion infusion to provide satisfactory anesthesia. With more stimulating surgical procedures (e.g., intra-abdominal), or if supplementation with nitrous oxide is not provided, administration rate(s) of propofol injectable emulsion and/or opioids should be increased in order to provide adequate anesthesia.
Infusion rates should always be titrated downward in the absence of clinical signs of light anesthesia until a mild response to surgical stimulation is obtained in order to avoid administration of propofol injectable emulsion at rates higher than are clinically necessary. Generally, rates of 50 mcg/kg/min to 100 mcg/kg/min in adults should be achieved during maintenance in order to optimize recovery times. Other drugs that cause CNS depression (e.g., sedatives, anesthetics, and opioids) can increase CNS depression induced by propofol.
Morphine premedication (0.15 mg/kg) with nitrous oxide 67% in oxygen has been shown to decrease the necessary propofol injection maintenance infusion rate and therapeutic blood concentrations when compared to non-narcotic (lorazepam) premedication. Induction of General Anesthesia Adult Patients Most adult patients under 55 years of age and classified as ASA-PS I or II require 2 mg/kg to 2.5 mg/kg of propofol injectable emulsion for induction when unpremedicated or when premedicated with oral benzodiazepines or intramuscular opioids.
For induction, propofol injectable emulsion should be titrated (approximately 40 mg every 10 seconds) against the response of the patient until the clinical signs show the onset of anesthesia. As with other general anesthetics, the amount of intravenous opioid and/or benzodiazepine premedication will influence the response of the patient to an induction dose of propofol injectable emulsion. Elderly, Debilitated, or ASA-PS III or IV Patients It is important to be familiar and experienced with the intravenous use of propofol injectable emulsion before treating elderly, debilitated, or ASA-PS III or IV patients.
Due to the reduced clearance and higher blood concentrations, most of these patients require approximately 1 mg/kg to 1.5 mg/kg (approximately 20 mg every 10 seconds) of propofol injectable emulsion for induction of anesthesia according to their condition and responses. A rapid bolus should not be used, as this will increase the likelihood of undesirable cardiorespiratory depression including hypotension, apnea, airwa…
⛔ Contraindications ▾
CONTRAINDICATIONS Propofol injectable emulsion is contraindicated in patients with a known hypersensitivity to propofol injectable emulsion or any of its components. Propofol injectable emulsion is contraindicated in patients with allergies to eggs, egg products, soybeans or soy products.
⚠️ Warnings ▾
WARNINGS Use of propofol injectable emulsion has been associated with both fatal and life-threatening anaphylactic and anaphylactoid reactions. For general anesthesia or monitored anesthesia care (MAC) sedation, propofol injectable emulsion should be administered only by persons trained in the administration of general anesthesia and not involved in the conduct of the surgical/diagnostic procedure. Sedated patients should be continuously monitored, and facilities for maintenance of a patent airway, providing artificial ventilation, administering supplemental oxygen, and instituting cardiovascular resuscitation must be immediately available.
Patients should be continuously monitored for early signs of hypotension, apnea, airway obstruction, and/or oxygen desaturation. These cardiorespiratory effects are more likely to occur following rapid bolus administration, especially in the elderly, debilitated, or ASA-PS III or IV patients. For sedation of intubated, mechanically ventilated patients in the Intensive Care Unit (ICU), propofol injectable emulsion should be administered only by persons skilled in the management of critically ill patients and trained in cardiovascular resuscitation and airway management.
Use of propofol injectable emulsion for both adult and pediatric ICU sedation has been associated with a constellation of metabolic derangements and organ system failures, referred to as Propofol Infusion Syndrome, that have resulted in death. The syndrome is characterized by severe metabolic acidosis, hyperkalemia, lipemia, rhabdomyolysis, hepatomegaly, renal failure, ECG changes1 and/or cardiac failure. The following appear to be major risk factors for the development of these events: decreased oxygen delivery to tissues; serious neurological injury and/or sepsis; high dosages of one or more of the following pharmacological agents: vasoconstrictors, steroids, inotropes and/or prolonged, high-dose infusions of propofol (greater than 5 mg/kg/h for greater than 48h).
The syndrome has also been reported following large-dose, short-term infusions during surgical anesthesia. In the setting of prolonged need for sedation, increasing propofol dose requirements to maintain a constant level of sedation, or onset of metabolic acidosis during administration of a propofol infusion, consideration should be given to using alternative means of sedation. Abrupt discontinuation of propofol injectable emulsion prior to weaning or for daily evaluation of sedation levels should be avoided.
This may result in rapid awakening with associated anxiety, agitation, and resistance to mechanical ventilation. Infusions of propofol injectable emulsion should be adjusted to maintain a light level of sedation through the weaning process or evaluation of sedation level (see PRECAUTIONS ). Propofol injectable emulsion should not be co-administered through the same IV catheter with blood or plasma because compatibility has not been established.
In vitro tests have shown that aggregates of the globular component of the emulsion vehicle have occurred with blood/plasma/serum from humans and animals. The clinical significance of these findings is not known. There have been reports in which failure to use aseptic technique when handling propofol injectable emulsion was associated with microbial contamination of the product and with fever, infection, sepsis, other life-threatening illness, and death.
Do not use if contamination is suspected. Discard unused drug product as directed within the required time limits (see DOSAGE AND ADMINISTRATION , Handling Procedures). There have been reports, in the literature and other public sources, of the transmission of bloodborne pathogens (such as Hepatitis B, Hepatitis C and HIV) from unsafe injection practices, and use of propofol vials intended for single use on multiple persons.
Propofol injectable emulsion vial is never to be accessed more than once or used on more than one person. 1 Coved ST segment elevation (similar to…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS To report SUSPECTED ADVERSE REACTIONS, contact Hospira, Inc. at 1-800-441-4100 or FDA at 1-800-FDA-1088 or www.fda.gov. General Adverse event information is derived from controlled clinical trials and worldwide marketing experience. In the description below, rates of the more common events represent US/Canadian clinical study results.
Less frequent events are also derived from publications and marketing experience in over 8 million patients; there are insufficient data to support an accurate estimate of their incidence rates. These studies were conducted using a variety of premedicants, varying lengths of surgical/diagnostic procedures, and various other anesthetic/sedative agents. Most adverse events were mild and transient.
Anesthesia and MAC Sedation in Adults The following estimates of adverse events for propofol injectable emulsion include data from clinical trials in general anesthesia/MAC sedation (N=2,889 adult patients). The adverse events listed below as probably causally related are those events in which the actual incidence rate in patients treated with propofol injectable emulsion was greater than the comparator incidence rate in these trials. Therefore, incidence rates for anesthesia and MAC sedation in adults generally represent estimates of the percentage of clinical trial patients which appeared to have probable causal relationship.
The adverse experience profile from reports of 150 patients in the MAC sedation clinical trials is similar to the profile established with propofol during anesthesia (see below). During MAC sedation clinical trials, significant respiratory events included cough, upper airway obstruction, apnea, hypoventilation, and dyspnea. Anesthesia in Pediatric Patients Generally the adverse experience profile from reports of 506 propofol injectable emulsion pediatric patients from 6 days through 16 years of age in the US/Canadian anesthesia clinical trials is similar to the profile established with propofol injectable emulsion during anesthesia in adults (see Pediatric percentages [Peds %] below).
Although not reported as an adverse event in clinical trials, apnea is frequently observed in pediatric patients. ICU Sedation in Adults The following estimates of adverse events include data from clinical trials in ICU sedation (N=159 adult patients). Probably related incidence rates for ICU sedation were determined by individual case report form review.
Probable causality was based upon an apparent dose response relationship and/or positive responses to rechallenge. In many instances the presence of concomitant disease and concomitant therapy made the causal relationship unknown. Therefore, incidence rates for ICU sedation generally represent estimates of the percentage of clinical trial patients which appeared to have a probable causal relationship.
Incidence greater than 1% - Probably Causally Related Events without an * or % had an incidence of 1% to 3% * Incidence of events 3% to 10% Incidence less than 1% - Probably Causally Related Incidence less than 1% - Causal Relationship Unknown ADVERSE 1 ADVERSE 2 ADVERSE 3
🆘 Overdosage ▾
OVERDOSAGE If overdosage occurs, propofol injectable emulsion administration should be discontinued immediately. Overdosage is likely to cause cardiorespiratory depression. Respiratory depression should be treated by artificial ventilation with oxygen.
Cardiovascular depression may require repositioning of the patient by raising the patient's legs, increasing the flow rate of intravenous fluids, and administering pressor agents and/or anticholinergic agents.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY General Propofol is an intravenous general anesthetic and sedation drug for use in the induction and maintenance of anesthesia or sedation. Intravenous injection of a therapeutic dose of propofol induces anesthesia, with minimal excitation, usually within 40 seconds from the start of injection (the time for one arm-brain circulation). As with other rapidly acting intravenous anesthetic agents, the half-time of the blood-brain equilibration is approximately 1 minute to 3 minutes, accounting for the rate of induction of anesthesia.
The mechanism of action, like all general anesthetics, is poorly understood. However, propofol is thought to produce its sedative/anesthetic effects by the positive modulation of the inhibitory function of the neurotransmitter GABA through the ligand-gated GABAA receptors. Pharmacodynamics Pharmacodynamic properties of propofol are dependent upon the therapeutic blood propofol concentrations.
Steady-state propofol blood concentrations are generally proportional to infusion rates. Undesirable side effects, such as cardiorespiratory depression, are likely to occur at higher blood concentrations which result from bolus dosing or rapid increases in infusion rates. An adequate interval (3 minutes to 5 minutes) must be allowed between dose adjustments in order to assess clinical effects.
The hemodynamic effects of propofol injectable emulsion during induction of anesthesia vary. If spontaneous ventilation is maintained, the major cardiovascular effect is arterial hypotension (sometimes greater than a 30% decrease) with little or no change in heart rate and no appreciable decrease in cardiac output. If ventilation is assisted or controlled (positive pressure ventilation), there is an increase in the incidence and the degree of depression of cardiac output.
Addition of an opioid, used as a premedicant, further decreases cardiac output and respiratory drive. If anesthesia is continued by infusion of propofol injectable emulsion, the stimulation of endotracheal intubation and surgery may return arterial pressure towards normal. However, cardiac output may remain depressed.
Comparative clinical studies have shown that the hemodynamic effects of propofol injectable emulsion during induction of anesthesia are generally more pronounced than with other intravenous (IV) induction agents. Induction of anesthesia with propofol injectable emulsion is frequently associated with apnea in both adults and pediatric patients. In adult patients who received propofol injectable emulsion (2 mg/kg to 2.5 mg/kg), apnea lasted less than 30 seconds in 7% of patients, 30 seconds to 60 seconds in 24% of patients, and more than 60 seconds in 12% of patients.
In pediatric patients from birth through 16 years of age assessable for apnea who received bolus doses of propofol injectable emulsion (1 mg/kg to 3.6 mg/kg), apnea lasted less than 30 seconds in 12% of patients, 30 seconds to 60 seconds in 10% of patients, and more than 60 seconds in 5% of patients. During maintenance of general anesthesia, propofol injectable emulsion causes a decrease in spontaneous minute ventilation usually associated with an increase in carbon dioxide tension which may be marked depending upon the rate of administration and concurrent use of other medications (e.g., opioids, sedatives, etc.).
During monitored anesthesia care (MAC) sedation, attention must be given to the cardiorespiratory effects of propofol injectable emulsion. Hypotension, oxyhemoglobin desaturation, apnea, and airway obstruction can occur, especially following a rapid bolus of propofol injectable emulsion. During initiation of MAC sedation, slow infusion or slow injection techniques are preferable over rapid bolus administration.
During maintenance of MAC sedation, a variable rate infusion is preferable over intermittent bolus administration in order to minimize undesirable cardiorespiratory effects. In the elderly, debilitated, or American Society of Anesthesiologis…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED PROPOFOL INJECTABLE EMULSION is supplied in the following dosage forms. NDC 51662-1470-1 PROPOFOL INJECTABLE EMULSION 1g/100mL (10mg/mL) 100mL VIAL HF Acquisition Co LLC, DBA HealthFirst Mukilteo, WA 98275 Also supplied in the following manufacture supplied dosage forms Propofol Injectable Emulsion, USP is supplied as follows: Propofol undergoes oxidative degradation, in the presence of oxygen, and is therefore packaged under nitrogen to eliminate this degradation path. Store at 20 to 25°C (68 to 77°F). [See USP Controlled Room Temperature].
Do not freeze. Shake well before use. Do not use if there is evidence of excessive creaming or aggregation, if large droplets are visible, or if there are other forms of phase separation indicating that the stability of the product has been compromised.
Slight creaming, which should disappear after shaking, may be visible upon prolonged standing. HOW SUPPLIED
📋 Description ▾
DESCRIPTION Propofol Injectable Emulsion, USP is a sterile, nonpyrogenic emulsion containing 10 mg/mL of propofol suitable for intravenous administration. Propofol is chemically described as 2,6-diisopropylphenol. The structural formula is: Propofol, USP is slightly soluble in water and, thus, is formulated in a white, oil-in-water emulsion.
The pKa is 11. The octanol/water partition coefficient for propofol is 6761:1 at a pH of 6 to 8.5. In addition to the active component, propofol, the formulation also contains soybean oil (100 mg/mL), glycerol (22.5 mg/mL), egg lecithin (12 mg/mL), benzyl alcohol (1.5 mg/mL) and sodium benzoate (0.7 mg/mL) added.
The pH is adjusted with sodium hydroxide. The Propofol Injectable Emulsion, USP is isotonic and has a pH of 6 to 8.5. STRUCTURE
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |