
Propofol 10 mg/mL Injection, Emulsion — NDC 72572-612-10 (Billing 72572-0612-10)
This is a package of Propofol 10 mg/mL Injection, Emulsion from Civica, Inc, marketed since Jul 2021 and currently FDA-listed. It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016796
- GCN: 14021
- HICL (First Databank): 004842
- AHFS class code: 28:04.08.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Propofol is used to begin and maintain general anesthesia (you are unconscious and unaware of what is happening) during surgery in adults and children. It is also used to provide sedation (you are relaxed, sleepy or in some cases asleep) in adults during surgical or other medical procedures. Propofol is also used to provide sedation for adults in intensive care units that are receiving mechanical ventilation (a machine that takes over the work of breathing). Propofol is in a class of medications called anesthetic agents. It works by changing the activity of certain substances in the brain.
Read the full MedlinePlus article ↗- Propofol is given through a vein to put you under general anesthesia or to provide sedation during procedures. It is also used to sedate adults in the ICU who are on a breathing ma...
- Some people feel burning, stinging, or pain at the IV site, and this is one of the more common effects. Your team can reduce it by using a larger vein or giving lidocaine first. An...
- Low blood pressure, a slower heart rate, and a short pause in breathing are the most common. Your team watches for these and treats them. You may also get a rash, itching, or invol...
- Yes. Tell them if you have ever had a severe allergic reaction to eggs, egg products, soybeans, or soy products, because propofol should not be used in that case. Also mention epil...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Propofol — tap one for details:
Propofol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2704 | $0.089 / J2704 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 72572-0612-10 You're viewing this Main listing | 10 VIAL in 1 CARTON / 100 mL in 1 VIAL | 2021-07-16 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| propofol 10 mg/mL 25021-0608-20 | Sagent | 25 vials | $0.171 | AB | Availability likely | — |
| propofol 10 mg/mL 71288-0730-51 | Meitheal | 10 vials | $0.171 | AB | Availability likely | — |
| Propofol 10 mg/mL 00409-6010-25 | Hospira, | 25 vials | $0.171 | AB | Availability likely | — |
| Propofol 10 mg/mL 00409-1511-98 | Hospira, | 25 vials | $0.171 | AB | Availability likely | — |
| Propofol 10 mg/mL 00069-0248-10 | Pfizer | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00409-4699-24 | Hospira, | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00641-6196-10 | Hikma | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 16714-0690-10 | NorthStar | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 23155-0345-41 | Heritage | 10 vials | — | AB | FDA listed | — |
| Propofol Injectable Emulsion 10 mg/mL 43598-0549-10 | Dr. | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 51662-1470-01 | HF | 100 ml | — | AB | FDA listed | — |
| Diprivan 10 mg/mL 63323-0269-59 | Fresenius | 20 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 71288-0731-53 | Meitheal | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mLthis 72572-0612-10 | Civica, | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 80830-2365-07 | Amneal | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 83634-0603-20 | Avenacy, | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00641-6194-10 | Hikma | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00641-6195-20 | Hikma | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 51662-1293-01 | HF | 20 ml | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00069-0234-20 | Pfizer | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 51662-1471-01 | HF | 50 ml | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00069-0209-10 | Pfizer | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 72572-0590-10 | Civica, | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 71288-0729-21 | Meitheal | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 80830-2364-08 | Amneal | 20 vials | — | AB | FDA listed | — |
| Diprivan 10 mg/mL 65219-0800-10 | Fresenius | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 80830-1188-07 | Amneal | 10 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 16714-0977-20 | NorthStar | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 72572-0601-20 | Civica, | 20 vials | — | AB | FDA listed | — |
| propofol 10 mg/mL 16714-0528-10 | NorthStar | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 83854-0018-10 | Anthea | 10 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00409-0501-98 | Hospira, | 20 vials | — | AB | FDA listed | — |
| Propofol 10 mg/mL 00409-0010-98 | Hospira, | 10 vials | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.05 mg / 1 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
12 mg / 1 mL
UNII 1Z74184RGV
Egg phospholipids are naturally derived fats from eggs that help mix oil and water-based ingredients together. They work as emulsifiers in medicines, keeping the formula stable and uniform.
-
22.5 mg / 1 mL
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
100 mg / 1 mL
UNII 241ATL177A
Soybean oil is a natural plant oil derived from soybean seeds. It's used in medicines as a solvent and carrier to help dissolve or suspend active ingredients and improve how the body absorbs them.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Propofol injectable emulsion is an intravenous general anesthetic and sedation drug indicated for: • Induction of General Anesthesia for Patients Greater than or Equal to 3 Years of Age • Maintenance of General Anesthesia for Patients Greater than or Equal to 2 Months of Age • Initiation and Maintenance of Monitored Anesthesia Care (MAC) Sedation in Adult Patients • Sedation for Adult Patients in Combination with Regional Anesthesia • Intensive Care Unit (ICU) Sedation of Intubated, Mechanically Ventilated Adult Patients Limitations of Use Propofol injectable emulsion is not recommended for induction of anesthesia below the age of 3 years or for maintenance of anesthesia below the age of 2 months because its safety and effectiveness have not been established in those populations [see Pediatric Use (8.4) ] .
Safety, effectiveness and dosing guidelines for propofol injectable emulsion have not been established for MAC sedation in the pediatric population; therefore, it is not recommended for this use [see Pediatric Use (8.4) ] . Propofol injectable emulsion is not indicated for use in Pediatric ICU sedation since the safety of this regimen has not been established [see Pediatric Use (8.4) ] . Propofol injectable emulsion is an intravenous general anesthetic and sedation drug indicated for: • Induction of General Anesthesia for Patients Greater than or Equal to 3 Years of Age • Maintenance of General Anesthesia for Patients Greater than or Equal to 2 Months of Age • Initiation and Maintenance of Monitored Anesthesia Care (MAC) Sedation in Adult Patients • Sedation for Adult Patients in Combination with Regional Anesthesia • Intensive Care Unit (ICU) Sedation of Intubated, Mechanically Ventilated Adult Patients Limitations of Use: Propofol injectable emulsion is not recommended for induction of anesthesia below the age of 3 years or for maintenance of anesthesia below the age of 2 months MAC sedation in the pediatric population is not recommended Propofol injectable emulsion is not indicated for use in Pediatric ICU sedation
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION See Full Prescribing Information for detailed dosing instructions.
2.1Important Dosage and Administration Information Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit. Shake well before use. Do not use if there is evidence of excessive creaming or aggregation, if large droplets are visible, or if there are other forms of phase separation indicating that the stability of the product has been compromised.
Slight creaming, which should disappear after shaking, may be visible upon prolonged standing. Do not use if there is evidence of separation of the phases of the emulsion. Propofol injectable emulsion with EDTA inhibits microbial growth for up to 12 hours, as demonstrated by test data for representative USP microorganisms.
Product is packaged under nitrogen. For general anesthesia or monitored anesthesia care (MAC) sedation, propofol injectable emulsion should be administered only by persons trained in the administration of general anesthesia and not involved in the conduct of the surgical/diagnostic procedure. Sedated patients should be continuously monitored, and equipment for maintaining a patent airway, providing artificial ventilation, administering supplemental oxygen, and instituting cardiovascular resuscitation must be immediately available.
Patients should be continuously monitored for early signs of hypotension, apnea, airway obstruction, and/or oxygen desaturation. These cardiorespiratory effects are more likely to occur following rapid bolus administration, especially in the elderly, debilitated, or ASA-PS III or IV patients. For sedation of intubated, mechanically ventilated adult patients in the Intensive Care Unit, propofol injectable emulsion should be administered only by persons skilled in the management of critically ill patients and trained in cardiovascular resuscitation and airway management.
Guidelines for Aseptic Technique for General Anesthesia/MAC Sedation Propofol injectable emulsion must be prepared for use just prior to initiation of each individual anesthetic/sedative procedure. The vial rubber stopper should be disinfected using 70% isopropyl alcohol. Propofol injectable emulsion should be drawn into a sterile syringe immediately after a vial is opened.
When withdrawing propofol injectable emulsion from vials, a sterile vent spike should be used. The syringe should be labelled with appropriate information including the date and time the vial was opened. Administration should commence promptly and be completed within 12 hours after the vial has been opened.
Propofol injectable emulsion must be prepared for single dose only. Any unused propofol injectable emulsion drug product, reservoirs, dedicated administration tubing and/or solutions containing propofol injectable emulsion must be discarded at the end of the anesthetic procedure or at 12 hours, whichever occurs sooner. The intravenous line should be flushed every 12 hours and at the end of the anesthetic procedure to remove residual propofol injectable emulsion [see Warnings and Precautions (5.2) ] .
Guidelines for Aseptic Technique for ICU Sedation Propofol injectable emulsion must be prepared for single dose only. Strict aseptic techniques must be followed. The vial rubber stopper should be disinfected using 70% isopropyl alcohol.
A sterile vent spike and sterile tubing must be used for administration of propofol injectable emulsion. As with other lipid emulsions, the number of intravenous line manipulations should be minimized. Administration should commence promptly and must be completed within 12 hours after the vial has been spiked.
The tubing and any unused propofol injectable emulsion drug product must be discarded after 12 hours. If propofol injectable emulsion is transferred to a syringe prior to administration, it should be drawn into a sterile syringe immediately after a vial is opened. When withdr… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Propofol Injectable Emulsion, USP is available in single-dose vials as follows: 200 mg of propofol per 20 mL of an oil-in-water emulsion (10 mg per mL), 20 mL vial 500 mg of propofol per 50 mL of an oil-in-water emulsion (10 mg per mL), 50 mL vial 1,000 mg of propofol per 100 mL of an oil-in-water emulsion (10 mg per mL), 100 mL vial Injectable emulsion: 200 mg per 20 mL (10 mg/mL), 500 mg per 50 mL (10 mg/mL), and 1,000 mg per 100 mL (10 mg/mL) single-dose vials ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Propofol injectable emulsion is contraindicated in patients with a known hypersensitivity to propofol or any of propofol injectable emulsion components. Propofol injectable emulsion is contraindicated in patients with a history of anaphylaxis to eggs, egg products, soybeans or soy products. Known hypersensitivity to propofol, egg or soybean ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypersensitivity Reactions : Serious and sometimes fatal reactions ( 5.1 ) Microbial Contamination : Strict aseptic technique must be maintained during handling. Propofol injectable emulsion vials are never to be accessed more than once or used on more than one person. Administration should commence promptly and be completed within 12 hours after the vial has been opened.
Discard unused drug product. Do not use if contamination is suspected ( 5.2 ) Cardiovascular Depression : Cases of bradycardia, asystole, and cardiac arrest have been reported. Pediatric patients are susceptible to this effect, particularly when fentanyl is given concomitantly ( 5.4 )
5.1Anaphylactic and Anaphylactoid Reactions Use of propofol injectable emulsion has been associated with both fatal and life threatening anaphylactic and anaphylactoid reactions. Clinical features of anaphylaxis, including angioedema, bronchospasm, erythema, and hypotension, occur rarely following propofol injectable emulsion administration.
5.2Risks of Microbial Contamination Strict aseptic technique must always be maintained during handling. Propofol injectable emulsion is a single-dose parenteral product (single patient infusion vial) which contains 0.005% disodium edetate (EDTA) to inhibit the rate of growth of microorganisms, for up to 12 hours, in the event of accidental extrinsic contamination. However, propofol injectable emulsion can still support the growth of microorganisms, as it is not an antimicrobially preserved product under USP standards.
Do not use if contamination is suspected. Discard unused drug product as directed within the required time limits. There have been reports in which failure to use aseptic technique when handling propofol injectable emulsion was associated with microbial contamination of the product and with fever, infection/sepsis, other life-threatening illness, and/or death.
Propofol injectable emulsion vials are never to be accessed more than once or used on more than one person. There have been reports, in the literature and other public sources, of the transmission of bloodborne pathogens (such as Hepatitis B, Hepatitis C, and HIV) from unsafe injection practices, and of the use of propofol vials intended for single use on multiple persons.
5.3Risks of Pediatric Neurotoxicity Published animal studies demonstrate that the administration of anesthetic and sedation drugs that block NMDA receptors and/or potentiate GABA activity increase neuronal apoptosis in the developing brain and result in long-term cognitive deficits when used for longer than 3 hours. The clinical significance of these findings is not clear. However, based on the available data, the window of vulnerability to these changes is believed to correlate with exposures in the third trimester of gestation through the first several months of life, but may extend out to approximately three years of age in humans [see Animal Toxicology and/or Pharmacology (13.2) ] .
Some published studies in children suggest that similar deficits may occur after repeated or prolonged exposures to anesthetic agents early in life and may result in adverse cognitive or behavioral effects. These studies have substantial limitations, and it is not clear if the observed effects are due to the anesthetic/sedation drug administration or other factors such as the surgery or underlying illness. Anesthetic and sedation drugs are a necessary part of the care of children needing surgery, other procedures, or tests that cannot be delayed, and no specific medications have been shown to be safer than any other.
Decisions regarding the timing of any elective procedures requiring anesthesia should take into consideration the benefits of the procedure weighed against the potential risks.
5.4Risks of Bradycardia, Asystole, and Cardiac Arrest Propofol injectable emulsion has no vagolytic activity. Reports of bradycardia, asystole, and rarely, cardiac arrest have been associated with propof… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious or otherwise important adverse reactions are discussed elsewhere in the labeling: • Hypersensitivity reaction [see Warnings and Precautions (5.1) ] • Hypotension and/or bradycardia [see Warnings and Precautions (5.4) ] • Propofol Infusion Syndrome [see Warnings and Precautions (5.9) ] In the description below, rates of the more common events represent US/Canadian clinical study results. Less frequent events are also derived from publications and marketing experience in over 8 million patients; there are insufficient data to support an accurate estimate of their incidence rates.
These studies were conducted using a variety of premedicants, varying lengths of surgical/diagnostic procedures, and various other anesthetic/sedative agents. Most adverse events were mild and transient. Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice.
Anesthesia and MAC Sedation in Adults The following estimates of adverse events for propofol injectable emulsion include data from clinical trials in general anesthesia/MAC sedation (N=2,889 adult patients). The adverse events listed below as probably causally related are those events in which the actual incidence rate in patients treated with propofol injectable emulsion was greater than the comparator incidence rate in these trials. Therefore, incidence rates for anesthesia and MAC sedation in adults generally represent estimates of the percentage of clinical trial patients which appeared to have probable causal relationship.
The adverse experience profile from reports of 150 patients in the MAC sedation clinical trials is similar to the profile established with propofol injectable emulsion during anesthesia (see Table 2 below). During MAC sedation clinical trials, significant respiratory events included cough, upper airway obstruction, apnea, hypoventilation, and dyspnea. Anesthesia in Pediatric Patients Generally, the adverse experience profile from reports of 506 propofol injectable emulsion pediatric patients from 6 days through 16 years of age in the US/Canadian anesthesia clinical trials is similar to the profile established with propofol injectable emulsion during anesthesia in adults.
Although not reported as an adverse event in clinical trials, apnea is frequently observed in pediatric patients. ICU Sedation in Adults The following estimates of adverse events include data from clinical trials in ICU sedation (N=159 adult patients). Probably related incidence rates for ICU sedation were determined by individual case report form review.
Probable causality was based upon an apparent dose response relationship and/or positive responses to rechallenge. In many instances the presence of concomitant disease and concomitant therapy made the causal relationship unknown. Therefore, incidence rates for ICU sedation generally represent estimates of the percentage of clinical trial patients which appeared to have a probable causal relationship.
Table 2. Treatment Emergent Adverse Events Observed from Clinical Trials Anesthesia/MAC Sedation ICU Sedation Body as a Whole: Anaphylaxis/Anaphylactoid reaction perinatal disorder, tachycardia, bigeminy, bradycardia, premature ventricular contractions, hemorrhage, ECG abnormal arrhythmia atrial, fever, extremities pain, anticholinergic syndrome, asthenia, awareness, chest pain, extremities pain, fever, increased drug effect, neck rigidity/stiffness, trunk pain Fever, sepsis, trunk pain, whole body weakness Cardiovascular: Premature atrial contractions Syncope, hypotension [see also Clinical Pharmacology (12) ] , tachycardia Nodal, arrhythmia Bradycardia, arrhythmia, atrial fibrillation, atrioventricular heart block, bigeminy, bleeding, bundle branch block, cardiac arrest, ECG abnormal, e… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Opioids and Sedatives The induction dose requirements of propofol injectable emulsion may be reduced in patients with intramuscular or intravenous premedication, particularly with opioids (e.g., morphine, meperidine, and fentanyl, etc.) and combinations of opioids and sedatives (e.g., benzodiazepines, barbiturates, chloral hydrate, droperidol, etc.). These agents may increase the anesthetic or sedative effects of propofol injectable emulsion and may also result in more pronounced decreases in systolic, diastolic, and mean arterial pressures and cardiac output.
In pediatric patients, administration of fentanyl concomitantly with propofol injectable emulsion may result in serious bradycardia. Analgesic Agents During maintenance of anesthesia or sedation, the rate of propofol injectable emulsion administration should be adjusted according to the desired level of anesthesia or sedation and may be reduced in the presence of supplemental analgesic agents (e.g., nitrous oxide or opioids). The concurrent administration of potent inhalational agents (e.g., isoflurane, sevoflurane, desflurane, enflurane, and halothane) during maintenance with propofol injectable emulsion are routinely used.
These inhalational agents can also be expected to increase the anesthetic or sedative and cardiorespiratory effects of propofol injectable emulsion. Valproate The concomitant use of valproate and propofol may lead to increased blood levels of propofol. Reduce the dose of propofol when co-administering with valproate.
Monitor patients closely for signs of increased sedation or cardiorespiratory depression. Common Neuromuscular Blocking Agents Propofol injectable emulsion does not cause a clinically significant change in onset, intensity or duration of action of the commonly used neuromuscular blocking agents (e.g., succinylcholine and nondepolarizing muscle relaxants). Common Drugs Used as Premedication or Drugs Used During Anesthesia or Sedation No significant adverse interactions with commonly used premedications or drugs used during anesthesia or sedation (including a range of muscle relaxants, inhalational agents, analgesic agents, and local anesthetic agents) have been observed in adults.
Opioids, Sedatives or Other Analgesic Agents : May increase the anesthetic/sedative and cardiorespiratory effects ( 7 ) Valproate : May lead to increased blood levels of propofol ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Data from randomized controlled trials, cohort studies and case series over several decades with propofol use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Most of the reported exposures to propofol describe propofol exposure at the time of cesarean delivery. There are reports of neonatal depression in infants exposed to propofol during delivery (see Clinical Considerations ) .
In animal reproduction studies, decreased pup survival concurrent with increased maternal mortality was observed with intravenous administration of propofol to pregnant rats either prior to mating and during early gestation or during late gestation and early lactation at exposures less than the human induction dose of 2.5 mg/kg. In pregnant rats administered 15 mg/kg/day intravenous propofol (equivalent to the human induction dose) from two weeks prior to mating to early in gestation (Gestation Day 7), offspring that were allowed to mate had increased post implantation losses.
The pharmacological activity (anesthesia) of the drug on the mother is probably responsible for the adverse effects seen in the offspring. Published studies in pregnant primates demonstrate that the administration of anesthetic and sedation drugs that block NMDA receptors and/or potentiate GABA activity during the period of peak brain development increases neuronal apoptosis in the developing brain of the offspring when used for longer than 3 hours. There are no data on pregnancy exposures in primates corresponding to periods prior to the third trimester in humans [see Data , Warnings and Precautions (5.3) , and Use in Specific Populations (8.4) ] .
The clinical significance of these nonclinical findings is not known, and the benefits of appropriate anesthesia in pregnant women who require procedures should be balanced with the potential risks suggested by the nonclinical data. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Fetal/neonatal Adverse Reactions Propofol injectable emulsion crosses the placenta and may be associated with neonatal depression. Monitor neonates for hypotonia and sedation following maternal exposure to propofol.
Data Animal Data Pregnant rats were administered propofol intravenously at 0, 5, 10, and 15 mg/kg/day (0.3, 0.65, and 1 times the human induction dose of 2.5 mg/kg based on body surface area) during organogenesis (Gestational Days 6–15). Propofol did not cause adverse effects to the fetus at exposures up to 1 times the human induction dose despite evidence of maternal toxicity (decreased weight gain in all groups). Pregnant rabbits were administered propofol intravenously at 0, 5, 10, and 15 mg/kg/day (0.65, 1.3, 2 times the human induction dose of 2.5 mg/kg based on body surface area comparison) during organogenesis (Gestation Days 6–18).
Propofol treatment decreased total numbers of corpora lutea in all treatment groups but did not cause fetal malformations at any dose despite maternal toxicity (one maternal death from anesthesia-related respiratory depression in the high dose group). Pregnant rats were administered propofol intravenously at 0, 10, and 15 mg/kg/day (0.65 and 1 times the human induction dose of 2.5 mg/kg based on body surface area) from late gestation through lactation (Gestation Day 16 to Lactation Day 22). Decreased pup survival was noted at all doses in the presence of maternal toxicity (deaths from anesthesia- induced respiratory depression).
This study did not evaluate neurobehavioral function including learning and memory in the pups. Preg… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Data from randomized controlled trials, cohort studies and case series over several decades with propofol use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. Most of the reported exposures to propofol describe propofol exposure at the time of cesarean delivery. There are reports of neonatal depression in infants exposed to propofol during delivery (see Clinical Considerations ) .
In animal reproduction studies, decreased pup survival concurrent with increased maternal mortality was observed with intravenous administration of propofol to pregnant rats either prior to mating and during early gestation or during late gestation and early lactation at exposures less than the human induction dose of 2.5 mg/kg. In pregnant rats administered 15 mg/kg/day intravenous propofol (equivalent to the human induction dose) from two weeks prior to mating to early in gestation (Gestation Day 7), offspring that were allowed to mate had increased post implantation losses.
The pharmacological activity (anesthesia) of the drug on the mother is probably responsible for the adverse effects seen in the offspring. Published studies in pregnant primates demonstrate that the administration of anesthetic and sedation drugs that block NMDA receptors and/or potentiate GABA activity during the period of peak brain development increases neuronal apoptosis in the developing brain of the offspring when used for longer than 3 hours. There are no data on pregnancy exposures in primates corresponding to periods prior to the third trimester in humans [see Data , Warnings and Precautions (5.3) , and Use in Specific Populations (8.4) ] .
The clinical significance of these nonclinical findings is not known, and the benefits of appropriate anesthesia in pregnant women who require procedures should be balanced with the potential risks suggested by the nonclinical data. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Fetal/neonatal Adverse Reactions Propofol injectable emulsion crosses the placenta and may be associated with neonatal depression. Monitor neonates for hypotonia and sedation following maternal exposure to propofol.
Data Animal Data Pregnant rats were administered propofol intravenously at 0, 5, 10, and 15 mg/kg/day (0.3, 0.65, and 1 times the human induction dose of 2.5 mg/kg based on body surface area) during organogenesis (Gestational Days 6–15). Propofol did not cause adverse effects to the fetus at exposures up to 1 times the human induction dose despite evidence of maternal toxicity (decreased weight gain in all groups). Pregnant rabbits were administered propofol intravenously at 0, 5, 10, and 15 mg/kg/day (0.65, 1.3, 2 times the human induction dose of 2.5 mg/kg based on body surface area comparison) during organogenesis (Gestation Days 6–18).
Propofol treatment decreased total numbers of corpora lutea in all treatment groups but did not cause fetal malformations at any dose despite maternal toxicity (one maternal death from anesthesia-related respiratory depression in the high dose group). Pregnant rats were administered propofol intravenously at 0, 10, and 15 mg/kg/day (0.65 and 1 times the human induction dose of 2.5 mg/kg based on body surface area) from late gestation through lactation (Gestation Day 16 to Lactation Day 22). Decreased pup survival was noted at all doses in the presence of maternal toxicity (deaths from anesthesia- induced respiratory depression).
This study did not evaluate neurobehavioral function including learning and memory in the pups. Pregnant rats were administered pr… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of propofol injectable emulsion have been established for induction of anesthesia in pediatric patients aged 3 years and older and for the maintenance of anesthesia aged 2 months and older. In pediatric patients, administration of fentanyl concomitantly with propofol injectable emulsion may result in serious bradycardia [see Warnings and Precautions (5.4) ] . Propofol injectable emulsion is not indicated for use in pediatric patients for ICU sedation or for MAC sedation for surgical, nonsurgical or diagnostic procedures as safety and effectiveness have not been established.
There have been anecdotal reports of serious adverse events and death in pediatric patients with upper respiratory tract infections receiving propofol injectable emulsion for ICU sedation. In one multicenter clinical trial of ICU sedation in critically ill pediatric patients that excluded patients with upper respiratory tract infections, the incidence of mortality observed in patients who received propofol injectable emulsion (n=222) was 9%, while that for patients who received standard sedative agents (n=105) was 4%.
While causality was not established in this study, propofol injectable emulsion is not indicated for ICU sedation in pediatric patients until further studies have been performed to document its safety in that population [see Clinical Pharmacology (12.3) and Dosage and Administration (2.1 and 2.2) ] . However, propofol infusions are routinely used to provide safe sedation to critically ill pediatric patients in ICUs. In pediatric patients, abrupt discontinuation of propofol injectable emulsion following prolonged infusion may result in flushing of the hands and feet, agitation, tremulousness and hyperirritability.
Increased incidences of bradycardia (5%), agitation (4%), and jitteriness (9%) have also been observed. Published juvenile animal studies demonstrate that the administration of anesthetic and sedation drugs, such as propofol injectable emulsion, that either block NMDA receptors or potentiate the activity of GABA during the period of rapid brain growth or synaptogenesis, results in widespread neuronal and oligodendrocyte cell loss in the developing brain and alterations in synaptic morphology and neurogenesis. Based on comparisons across species, the window of vulnerability to these changes is believed to correlate with exposures in the third trimester of gestation through the first several months of life, but may extend out to approximately 3 years of age in humans.
In primates, exposure to 3 hours of ketamine that produced a light surgical plane of anesthesia did not increase neuronal cell loss, however, treatment regimens of 5 hours or longer of isoflurane increased neuronal cell loss. Data from isoflurane-treated rodents and ketamine-treated primates suggest that the neuronal and oligodendrocyte cell losses are associated with prolonged cognitive deficits in learning and memory. The clinical significance of these nonclinical findings is not known, and healthcare providers should balance the benefits of appropriate anesthesia in pregnant women, neonates, and young children who require procedures with the potential risks suggested by the nonclinical data [see Warnings and Precautions (5.3) , Pregnancy (8.1) , and Animal Toxicology and/or Pharmacology (13.2) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use The effect of age on induction dose requirements for propofol was assessed in an open-label study involving 211 unpremedicated patients with approximately 30 patients in each decade between the ages of 16 and 80. The average dose to induce anesthesia was calculated for patients up to 54 years of age and for patients 55 years of age or older. The average dose to induce anesthesia in patients up to 54 years of age was 1.99 mg/kg and in patients above 54 it was 1.66 mg/kg.
Subsequent clinical studies have demonstrated lower dosing requirements for subjects greater than 60 years of age. A lower induction dose and a slower maintenance rate of administration of propofol injectable emulsion should be used in elderly patients. In this group of patients, rapid (single or repeated) bolus administration should not be used in order to minimize undesirable cardiorespiratory depression.
All dosing should be titrated according to patient condition and response [see Dosage and Administration (2) and Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Symptoms Overdosage is likely to cause cardiorespiratory depression.
10.2Treatment If overdosage occurs, propofol injectable emulsion administration should be discontinued immediately. Respiratory depression should be treated by artificial ventilation with oxygen. Cardiovascular depression may require repositioning of the patient by raising the patient's legs, increasing the flow rate of intravenous fluids, and administering pressor agents and/or anticholinergic agents.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY Propofol injectable emulsion is an intravenous general anesthetic and sedation drug for use in the induction and maintenance of anesthesia or sedation. Intravenous injection of a therapeutic dose of propofol induces anesthesia, with minimal excitation, usually within 40 seconds from the start of injection (the time for one arm-brain circulation). As with other rapidly acting intravenous anesthetic agents, the half-time of the blood-brain equilibration is approximately 1 to 3 minutes, accounting for the rate of induction of anesthesia.
12.1Mechanism of Action The mechanism of action, like all general anesthetics, is poorly understood. However, propofol is thought to produce its sedative/anesthetic effects by the positive modulation of the inhibitory function of the neurotransmitter GABA through the ligand-gated GABA A receptors.
12.2Pharmacodynamics Pharmacodynamic properties of propofol are dependent upon the therapeutic blood propofol concentrations. Steady-state propofol blood concentrations are generally proportional to infusion rates. Undesirable side effects, such as cardiorespiratory depression, are likely to occur at higher blood concentrations which result from bolus dosing or rapid increases in infusion rates.
An adequate interval (3 to 5 minutes) must be allowed between dose adjustments in order to assess clinical effects. The hemodynamic effects of propofol injectable emulsion during induction of anesthesia vary. If spontaneous ventilation is maintained, the major cardiovascular effect is arterial hypotension (sometimes greater than a 30% decrease) with little or no change in heart rate and no appreciable decrease in cardiac output.
If ventilation is assisted or controlled (positive pressure ventilation), there is an increase in the incidence and the degree of depression of cardiac output. Addition of an opioid, used as a premedicant, further decreases cardiac output and respiratory drive. If anesthesia is continued by infusion of propofol injectable emulsion, the stimulation of endotracheal intubation and surgery may return arterial pressure towards normal.
However, cardiac output may remain depressed. Comparative clinical studies have shown that the hemodynamic effects of propofol injectable emulsion during induction of anesthesia are generally more pronounced than with other intravenous induction agents. Induction of anesthesia with propofol injectable emulsion is frequently associated with apnea in both adults and pediatric patients.
In adult patients who received propofol injectable emulsion (2 mg/kg to 2.5 mg/kg), apnea lasted less than 30 seconds in 7% of patients, 30 seconds to 60 seconds in 24% of patients, and more than 60 seconds in 12% of patients. In pediatric patients from birth through 16 years of age assessable for apnea who received bolus doses of propofol injectable emulsion (1 mg/kg to 3.6 mg/kg), apnea lasted less than 30 seconds in 12% of patients, 30 seconds to 60 seconds in 10% of patients, and more than 60 seconds in 5% of patients.
During maintenance of general anesthesia, propofol injectable emulsion causes a decrease in spontaneous minute ventilation usually associated with an increase in carbon dioxide tension which may be marked depending upon the rate of administration and concurrent use of other medications (e.g., opioids, sedatives, etc.). During monitored anesthesia care (MAC) sedation, attention must be given to the cardiorespiratory effects of propofol injectable emulsion. Hypotension, oxyhemoglobin desaturation, apnea, and airway obstruction can occur, especially following a rapid bolus of propofol injectable emulsion.
During initiation of MAC sedation, slow infusion or slow injection techniques are preferable over rapid bolus administration. During maintenance of MAC sedation, a variable rate infusion is preferable over intermittent bolus administration in order to minimize undesirable cardiorespiratory effects. In the elderly, debilitated, or ASA-PS II… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action, like all general anesthetics, is poorly understood. However, propofol is thought to produce its sedative/anesthetic effects by the positive modulation of the inhibitory function of the neurotransmitter GABA through the ligand-gated GABA A receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Propofol Injectable Emulsion, USP is supplied as follows: Unit of Sale Concentration NDC 72572-590-10 Carton of 10 Single-dose infusion vials 200 mg/20 mL (10 mg/mL) NDC 72572-601-20 Carton of 20 Single-dose infusion vials 500 mg/50 mL (10 mg/mL) NDC 72572-612-10 Carton of 10 Single-dose infusion vials 1,000 mg/100 mL (10 mg/mL) Store between 4°C to 25°C (40°F to 77°F). Do not freeze. Shake well before use.
📦 Storage and Handling ▾
Store between 4°C to 25°C (40°F to 77°F). Do not freeze. Shake well before use.
📋 Description ▾
11 DESCRIPTION Propofol Injectable Emulsion, USP is an anesthetic available as a sterile, nonpyrogenic white or almost white homogeneous emulsion for intravenous administration. The structural formula is: Chemical name: 2,6-diisopropylphenol Molecular formula: C 12 H 18 O Molecular weight: 178.27 Propofol, USP is slightly soluble in water. The pKa is 11.
The octanol/water partition coefficient for propofol is 6761:1 at a pH of 6 to 8.5. Each mL of Propofol Injectable Emulsion, USP contains 10 mg of propofol, 100 mg of soybean oil (100 mg/mL), 22.5 mg of glycerin (22.5 mg/mL), 12 mg of purified egg phospholipids (12 mg/mL), 0.055 mg of disodium edetate anhydrous (equivalent to 0.055 mg of disodium edetate) (0.05 mg/mL) as microbial inhibitor, and sodium hydroxide to adjust pH, in water for injection. Propofol Injectable Emulsion, USP is isotonic and has a pH of 6 to 8.5.
Chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Impaired Mental Alertness Advise patients that performance of activities requiring mental alertness, such as operating a motor vehicle or hazardous machinery or signing legal documents may be impaired for some time after general anesthesia or sedation.
17.2Effect of Anesthetic and Sedation Drugs on Early Brain Development Studies conducted in young animals and children suggest repeated or prolonged use of general anesthetic or sedation drugs in children younger than 3 years may have negative effects on their developing brains. Discuss with parents and caregivers the benefits, risks, and timing and duration of surgery or procedures requiring anesthetic and sedation drugs. This product’s labeling may have been updated.
For the most recent prescribing information, please visit www.pfizer.com .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of propofol are well described by a three- compartment linear model with compartments representing the plasma, rapidly equilibrating tissues, and slowly equilibrating tissues. Following an intravenous bolus dose, there is rapid equilibration between the plasma and the brain, accounting for the rapid onset of anesthesia. Plasma levels initially decline rapidly as a result of both distribution and metabolic clearance.
Distribution accounts for about half of this decline following a bolus of propofol. However, distribution is not constant over time, but decreases as body tissues equilibrate with plasma and become saturated. The rate at which equilibration occurs is a function of the rate and duration of the infusion.
When equilibration occurs there is no longer a net transfer of propofol between tissues and plasma. Discontinuation of the recommended doses of propofol injectable emulsion after the maintenance of anesthesia for approximately one hour, or for sedation in the ICU for one day, results in a prompt decrease in blood propofol concentrations and rapid awakening. Longer infusions (10 days of ICU sedation) result in accumulation of significant tissue stores of propofol, such that the reduction in circulating propofol is slowed and the time to awakening is increased.
By daily titration of propofol injectable emulsion dosage to achieve only the minimum effective therapeutic concentration, rapid awakening within 10 to 15 minutes can occur even after long-term administration. If, however, higher than necessary infusion levels have been maintained for a long time, propofol redistribution from fat and muscle to the plasma can be significant and slow recovery. The figure below illustrates the fall of plasma propofol levels following infusions of various durations to provide ICU sedation.
The large contribution of distribution (about 50%) to the fall of propofol plasma levels following brief infusions means that after very long infusions a reduction in the infusion rate is appropriate by as much as half the initial infusion rate in order to maintain a constant plasma level. Therefore, failure to reduce the infusion rate in patients receiving propofol injectable emulsion for extended periods may result in excessively high blood concentrations of the drug. Thus, titration to clinical response and daily evaluation of sedation levels are important during use of propofol injectable emulsion infusion for ICU sedation.
Adults Propofol clearance ranges from 23 mL/kg/min to 50 mL/kg/min (1.6 L/min to
3.4L/min in 70 kg adults). It is chiefly eliminated by hepatic conjugation to inactive metabolites which are excreted by the kidney. A glucuronide conjugate accounts for about 50% of the administered dose.
Propofol has a steady-state volume of distribution (10-day infusion) approaching 60 L/kg in healthy adults. A difference in pharmacokinetics due to gender has not been observed. The terminal half-life of propofol after a 10-day infusion is 1 day to 3 days.
Geriatrics With increasing patient age, the dose of propofol needed to achieve a defined anesthetic end point (dose-requirement) decreases. This does not appear to be an age-related change in pharmacodynamics or brain sensitivity, as measured by EEG burst suppression. With increasing patient age, pharmacokinetic changes are such that, for a given intravenous bolus dose, higher peak plasma concentrations occur, which can explain the decreased dose requirement.
These higher peak plasma concentrations in the elderly can predispose patients to cardiorespiratory effects including hypotension, apnea, airway obstruction, and/or arterial oxygen desaturation. The higher plasma levels reflect an age-related decrease in volume of distribution and intercompartmental clearance. Lower doses are therefore recommended for initiation and maintenance of sedation and anesthesia in elderly patients [see Dosage and Administration (2) ] .
Pediatrics The pharmacokinetic… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Pharmacodynamic properties of propofol are dependent upon the therapeutic blood propofol concentrations. Steady-state propofol blood concentrations are generally proportional to infusion rates. Undesirable side effects, such as cardiorespiratory depression, are likely to occur at higher blood concentrations which result from bolus dosing or rapid increases in infusion rates.
An adequate interval (3 to 5 minutes) must be allowed between dose adjustments in order to assess clinical effects. The hemodynamic effects of propofol injectable emulsion during induction of anesthesia vary. If spontaneous ventilation is maintained, the major cardiovascular effect is arterial hypotension (sometimes greater than a 30% decrease) with little or no change in heart rate and no appreciable decrease in cardiac output.
If ventilation is assisted or controlled (positive pressure ventilation), there is an increase in the incidence and the degree of depression of cardiac output. Addition of an opioid, used as a premedicant, further decreases cardiac output and respiratory drive. If anesthesia is continued by infusion of propofol injectable emulsion, the stimulation of endotracheal intubation and surgery may return arterial pressure towards normal.
However, cardiac output may remain depressed. Comparative clinical studies have shown that the hemodynamic effects of propofol injectable emulsion during induction of anesthesia are generally more pronounced than with other intravenous induction agents. Induction of anesthesia with propofol injectable emulsion is frequently associated with apnea in both adults and pediatric patients.
In adult patients who received propofol injectable emulsion (2 mg/kg to 2.5 mg/kg), apnea lasted less than 30 seconds in 7% of patients, 30 seconds to 60 seconds in 24% of patients, and more than 60 seconds in 12% of patients. In pediatric patients from birth through 16 years of age assessable for apnea who received bolus doses of propofol injectable emulsion (1 mg/kg to 3.6 mg/kg), apnea lasted less than 30 seconds in 12% of patients, 30 seconds to 60 seconds in 10% of patients, and more than 60 seconds in 5% of patients.
During maintenance of general anesthesia, propofol injectable emulsion causes a decrease in spontaneous minute ventilation usually associated with an increase in carbon dioxide tension which may be marked depending upon the rate of administration and concurrent use of other medications (e.g., opioids, sedatives, etc.). During monitored anesthesia care (MAC) sedation, attention must be given to the cardiorespiratory effects of propofol injectable emulsion. Hypotension, oxyhemoglobin desaturation, apnea, and airway obstruction can occur, especially following a rapid bolus of propofol injectable emulsion.
During initiation of MAC sedation, slow infusion or slow injection techniques are preferable over rapid bolus administration. During maintenance of MAC sedation, a variable rate infusion is preferable over intermittent bolus administration in order to minimize undesirable cardiorespiratory effects. In the elderly, debilitated, or ASA-PS III or IV patients, rapid (single or repeated) bolus dose administration should not be used for MAC sedation [see Warnings and Precautions (5.12) ] .
Clinical and preclinical studies suggest that propofol injectable emulsion is rarely associated with elevation of plasma histamine levels. Preliminary findings in patients with normal intraocular pressure indicate that propofol injectable emulsion produces a decrease in intraocular pressure which may be associated with a concomitant decrease in systemic vascular resistance. Clinical studies indicate that propofol injectable emulsion when used in combination with hypocarbia increases cerebrovascular resistance and decreases cerebral blood flow, cerebral metabolic oxygen consumption, and intracranial pressure.
Propofol injectable emulsion does not affect cerebrovascular reactivity to changes in arterial carbon… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Pediatric Anesthesia Propofol injectable emulsion was studied in clinical trials which included cardiac surgical patients. Most patients were 3 years of age or older. The majority of the patients were healthy ASA-PS I or II patients.
The range of doses in these studies are described in Tables 3 and 4. Table 3. Pediatric Induction of Anesthesia Age Range Induction Dose Median (range) Injection Duration Median (range) ≥3 years to 16 years 2.5 mg/kg (1 mg/kg to 3.6 mg/kg) 20 sec (6 sec to 45 sec) Table 4.
Pediatric Maintenance of Anesthesia Age Range Maintenance Dosage (mcg/kg/min) Duration (minutes) 2 months to 2 years 199 (82 to 394) 65 (12 to 282) 2 to 12 years 188 (12 to 1041) 69 (23 to 374) >12 through 16 years 161 (84 to 359) 69 (26 to 251)
14.2Neuroanesthesia Propofol injectable emulsion was studied in patients undergoing craniotomy for supratentorial tumors in two clinical trials. The mean lesion size (anterior/posterior × lateral) was 31 mm × 32 mm in one trial and 55 mm × 42 mm in the other trial respectively. Anesthesia was induced with a median propofol injectable emulsion dose of 1.4 mg/kg (range: 0.9 mg/kg to 6.9 mg/kg) and maintained with a median maintenance propofol injectable emulsion dose of 146 mcg/kg/min (range: 68 mcg/kg/min to 425 mcg/kg/min).
The median duration of the propofol injectable emulsion maintenance infusion was 285 minutes (range: 48 minutes to 622 minutes). Propofol injectable emulsion was administered by infusion in a controlled clinical trial to evaluate its effect on cerebrospinal fluid pressure (CSFP). The mean arterial pressure was maintained relatively constant over 25 minutes with a change from baseline of -4% ± 17% (mean ± SD).
The change in CSFP was -46% ± 14%. As CSFP is an indirect measure of intracranial pressure (ICP), propofol injectable emulsion, when given by infusion or slow bolus in combination with hypocarbia, is capable of decreasing ICP independent of changes in arterial pressure.
14.3Cardiac Anesthesia Propofol injectable emulsion was evaluated in clinical trials involving patients undergoing coronary artery bypass graft (CABG). In post-CABG (coronary artery bypass graft) patients, the maintenance rate of propofol administration was usually low (median 11 mcg/kg/min) due to the intraoperative administration of high opioid doses. Patients receiving propofol injectable emulsion required 35% less nitroprusside than midazolam patients.
During initiation of sedation in post-CABG patients, a 15% to 20% decrease in blood pressure was seen in the first 60 minutes. It was not possible to determine cardiovascular effects in patients with severely compromised ventricular function.
14.4Intensive Care Unit (ICU) Sedation in Adult Patients Propofol injectable emulsion was compared to benzodiazepines and opioids in clinical trials involving ICU patients. Of these, 302 received propofol injectable emulsion and comprise the overall safety database for ICU sedation. Across all clinical studies, the mean infusion maintenance rate for all propofol injectable emulsion patients was 27 ± 21 mcg/kg/min.
The maintenance infusion rates required to maintain adequate sedation ranged from 2.8 mcg/kg/min to 130 mcg/kg/min. The infusion rate was lower in patients over 55 years of age (approximately 20 mcg/kg/min) compared to patients under 55 years of age (approximately 38 mcg/kg/min). Although there are reports of reduced analgesic requirements, most patients received opioids for analgesia during maintenance of ICU sedation.
In these studies, morphine or fentanyl was used as needed for analgesia. Some patients also received benzodiazepines and/or neuromuscular blocking agents. During long-term maintenance of sedation, some ICU patients were awakened once or twice every 24 hours for assessment of neurologic or respiratory function.
In Medical and Postsurgical ICU studies comparing propofol injectable emulsion to benzodiazepine infusion or bolus, there were no apparent differe… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.2Abuse There are reports of the abuse of propofol for recreational and other improper purposes, which have resulted in fatalities and other injuries. Instances of self-administration of propofol injectable emulsion by health care professionals have also been reported, which have resulted in fatalities and other injuries. Inventories of propofol injectable emulsion should be stored and managed to prevent the risk of diversion, including restriction of access and accounting procedures as appropriate to the clinical setting.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term studies in animals have not been performed to evaluate the carcinogenic potential of propofol. Mutagenesis Propofol was not mutagenic in the in vitro bacterial reverse mutation assay (Ames test) using Salmonella typhimurium strains TA98, TA100, TA1535, TA1537 and TA1538. Propofol was not mutagenic in either the gene mutation/gene conversion test using Saccharomyces cerevisiae , or in vitro cytogenetic studies in Chinese hamsters.
In the in vivo mouse micronucleus assay with Chinese Hamsters propofol administration did not produce chromosome aberrations. Impairment of Fertility Female Wistar rats were administered either 0, 10, or 15 mg/kg/day propofol intravenously from 2 weeks before pregnancy to day 7 of gestation did not show impaired fertility (0.65 and 1 times the human induction dose of 2.5 mg/kg based on body surface area). Male fertility in rats was not affected in a dominant lethal study at intravenous doses up to 15 mg/kg/day for 5 days.
13.2Animal Toxicology and/or Pharmacology Intra-arterial injection in animals did not induce local tissue effects. Intentional injection into subcutaneous or perivascular tissues of animals caused minimal tissue reaction. Published studies in animals demonstrate that the use of anesthetic agents during the period of rapid brain growth or synaptogenesis results in widespread neuronal and oligodendrocyte cell loss in the developing brain and alterations in synaptic morphology and neurogenesis.
Based on comparisons across species, the window of vulnerability to these changes is believed to correlate with exposures in the third trimester through the first several months of life, but may extend out to approximately 3 years of age in humans. In primates, exposure to 3 hours of an anesthetic regimen that produced a light surgical plane of anesthesia did not increase neuronal cell loss, however, treatment regimens of 5 hours or longer increased neuronal cell loss. Data in rodents and in primates suggest that the neuronal and oligodendrocyte cell losses are associated with subtle but prolonged cognitive deficits in learning and memory.
The clinical significance of these nonclinical findings is not known, and healthcare providers should balance the benefits of appropriate anesthesia in neonates and young children who require procedures against the potential risks suggested by the nonclinical data [see Warnings and Precautions (5.3) , Pregnancy (8.1) , and Pediatric Use (8.4) ] .
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term studies in animals have not been performed to evaluate the carcinogenic potential of propofol. Mutagenesis Propofol was not mutagenic in the in vitro bacterial reverse mutation assay (Ames test) using Salmonella typhimurium strains TA98, TA100, TA1535, TA1537 and TA1538. Propofol was not mutagenic in either the gene mutation/gene conversion test using Saccharomyces cerevisiae , or in vitro cytogenetic studies in Chinese hamsters.
In the in vivo mouse micronucleus assay with Chinese Hamsters propofol administration did not produce chromosome aberrations. Impairment of Fertility Female Wistar rats were administered either 0, 10, or 15 mg/kg/day propofol intravenously from 2 weeks before pregnancy to day 7 of gestation did not show impaired fertility (0.65 and 1 times the human induction dose of 2.5 mg/kg based on body surface area). Male fertility in rats was not affected in a dominant lethal study at intravenous doses up to 15 mg/kg/day for 5 days.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 20 mL Vial Label NDC 72572-590-01 Rx Only Propofol Injectable Emulsion, USP 200 mg/20 mL (10 mg/mL) 20 mL Single-dose vial For Intravenous Administration LOT EXP PRINCIPAL DISPLAY PANEL - 20 mL Vial Label
PRINCIPAL DISPLAY PANEL - 20 mL Vial Carton NDC 72572-590-10 Rx Only Propofol Injectable Emulsion, USP 200 mg/20 mL (10 mg/mL) Ten 20 mL Single-dose vials For Intravenous Administration SHAKE WELL BEFORE USING • Use strict aseptic technique • Contains EDTA, which inhibits microbial growth up to 12 hours, discard within 12 hours of opening CIVICA ® PRINCIPAL DISPLAY PANEL - 20 mL Vial Carton
PRINCIPAL DISPLAY PANEL - 50 mL Vial Label NDC 72572-601-01 Rx Only Propofol Injectable Emulsion, USP 500 mg/50 mL (10 mg/mL) 50 mL Single-dose vial For Intravenous Administration PRINCIPAL DISPLAY PANEL - 50 mL Vial Label
PRINCIPAL DISPLAY PANEL - 50 mL Vial Carton NDC 72572-601-20 Rx Only Propofol Injectable Emulsion, USP 500 mg/50 mL (10 mg/mL) Twenty 50 mL Single-dose vials For Intravenous Administration SHAKE WELL BEFORE USING 1. Use strict aseptic technique 2. Contains EDTA, which inhibits microbial growth up to 12 hours, discard within 12 hours of opening CIVICA ® PRINCIPAL DISPLAY PANEL - 50 mL Vial Carton
PRINCIPAL DISPLAY PANEL - 100 mL Vial Label NDC 72572-612-01 Rx Only Propofol Injectable Emulsion, USP 1,000 mg/100 mL (10 mg/mL) 100 mL Single-dose vial For Intravenous Administration SHAKE WELL BEFORE USING DISCARD DATE: ______________ DISCARD TIME: ____________ Lot: Exp.: PRINCIPAL DISPLAY PANEL - 100 mL Vial Label
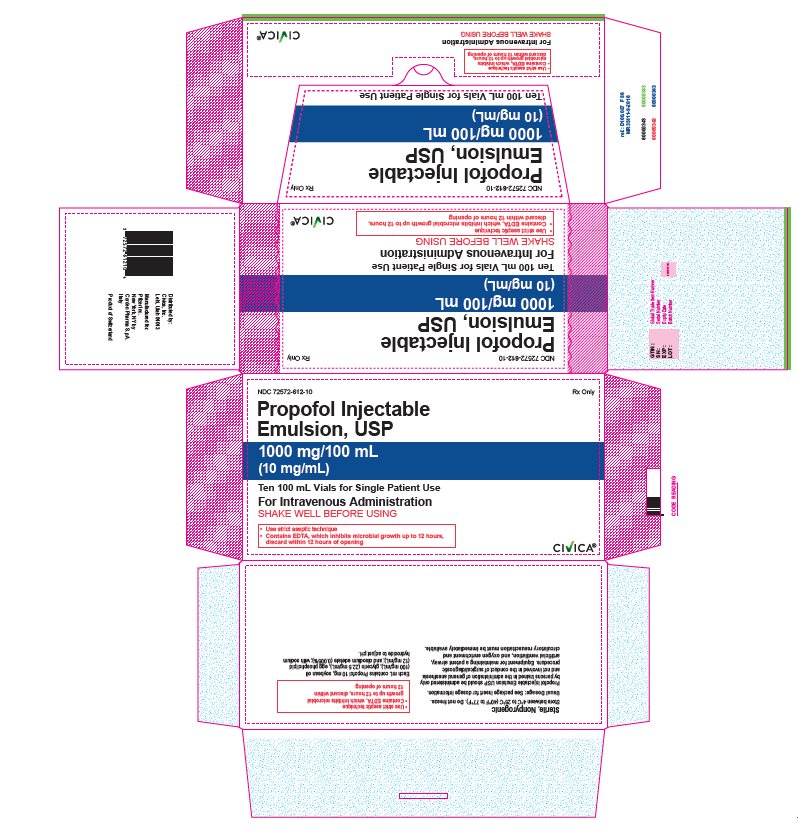
PRINCIPAL DISPLAY PANEL - 100 mL Vial Carton NDC 72572-612-10 Rx Only Propofol Injectable Emulsion, USP 1,000 mg/100 mL (10 mg/mL) Ten 100 mL Single-dose vials For Intravenous Administration SHAKE WELL BEFORE USING 1. Use strict aseptic technique 2. Contains EDTA, which inhibits microbial growth up to 12 hours, discard within 12 hours of opening CIVICA ® PRINCIPAL DISPLAY PANEL - 100 mL Vial Carton
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |