
Verapamil Hydrochloride 2.5 mg/mL Injection
Other active recalls for Verapamil Hydrochloride (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That depends on why your doctor prescribed it. Verapamil can treat three main problems: high blood pressure, angina (chest pain from the heart not getting enough blood), and certai...
- What exactly is verapamil treating in my body?
- Yes, and it depends on your specific formulation. If you have the extended-release tablets, take them in the morning with food. If you have the extended-release PM capsules, take t...
- Does it matter when I take verapamil or whether I take it with food?
Patient education
Supplement & herbal interactions
Verapamil may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $168.06 | $840.29 / 5 vials |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Verapamil Hydrochloride 2.5 mg/mL 00404-9966-02 | Henry | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 00409-1144-02 | Hospira, | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 00409-4011-01 | Hospira, | 5 ampules | — | AP | FDA listed | — |
| Verapamil hydrochloride 2.5 mg/mL 23155-0911-41 | Heritage | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 25021-0312-02 | Sagent | 25 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 42571-0313-75 | Micro | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 43066-0031-25 | Baxter | 25 vials | — | AP | FDA listed | — |
| Verapamil Hci 2.5 mg/mL 51662-1269-01 | HF | 2 ml | — | AP | FDA listed | — |
| Verapamil Hci 2.5 mg/mL 51662-1442-01 | HF | 2 ml | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 51662-1549-01 | HF | 2 ml | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 51662-1686-03 | HF | 25 pouches | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mLthis 51754-0203-02 | EXELA | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 51754-0204-02 | EXELA | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 55150-0342-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 65145-0113-25 | Caplin | 25 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 65219-0384-02 | FRESENIUS | 25 vials | — | AP | FDA listed | — |
| Verapamil hydrochloride 2.5 mg/mL 68083-0447-25 | Gland | 25 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70069-0271-05 | Somerset | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70069-0273-05 | Somerset | 5 ampules | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70121-1585-05 | Amneal | 25 vials | — | — | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70518-4453-00 | REMEDYREPACK | 25 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70710-1643-07 | Zydus | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70710-1937-07 | Zydus | 5 vials | — | AP | FDA listed | — |
| verapamil hydrochloride 2.5 mg/mL 70756-0605-25 | Lifestar | 25 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70771-1601-07 | Zydus | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 71872-7048-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 71872-7183-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 5 mg/2mL 71872-7203-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 5 mg/2mL 71872-7210-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 71872-7243-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 71872-7291-01 | Medical | 1 vial | — | AP | FDA listed | — |
| verapamil hydrochloride 2.5 mg/mL 71872-7356-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 5 mg/2mL 72485-0108-05 | Armas | 5 vials | — | AP | FDA listed | — |
| verapamil hydrochloride 2.5 mg/mL 84549-0605-25 | ProPharma | 2 ml | — | AP | FDA listed | — |
| Verapamil hydrochloride 2.5 mg/mL 68083-0448-05 | Gland | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70771-1602-05 | Zydus | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 55150-0343-01 | Eugia | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70069-0272-05 | Somerset | 5 vials | — | AP | FDA listed | — |
| verapamil hydrochloride 2.5 mg/mL 70756-0606-05 | Lifestar | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 00404-9967-04 | Henry | 1 vial | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 43066-0035-05 | Baxter | 5 vials | — | AP | FDA listed | — |
| Verapamil hydrochloride 2.5 mg/mL 23155-0912-41 | Heritage | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 65145-0114-05 | Caplin | 5 vials | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70121-1586-03 | Amneal | 5 vials | — | — | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 51662-1270-01 | HF | 1 syringe | — | — | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 00404-9968-04 | Henry | 1 syringe | — | — | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 51662-1398-01 | HF | 4 ml | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 51662-1685-01 | HF | 4 ml | — | AP | FDA listed | — |
| Verapamil Hydrochloride 2.5 mg/mL 70710-1644-05 | Zydus | 5 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
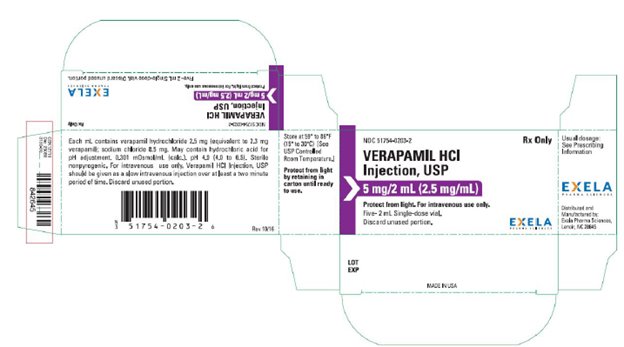
| 51754-0203-02 You're viewing this | 5 VIAL in 1 CARTON (51754-0203-2) / 2 mL in 1 VIAL | 2016-04-22 | Active |
| 51754-0203-04 | 25 VIAL in 1 CARTON (51754-0203-4) / 2 mL in 1 VIAL | 2016-12-09 | Active |
This pack accounts for about 26% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 51754-0203-02?
What NDC number is used to bill for this package of Verapamil Hydrochloride 2.5 mg/mL Injection?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Verapamil is indicated for the treatment of supraventricular tachyarrhythmias, including: • Rapid conversion to sinus rhythm of paroxysmal supraventricular tachycardias, including those associated with accessory bypass tracts (Wolff-Parkinson-White [WPW] and Lown-Ganong-Levine [LGL] syndromes). When clinically advisable, appropriate vagal maneuvers (e.g., Valsalva maneuver) should be attempted prior to Verapamil administration. • Temporary control of rapid ventricular rate in atrial flutter or atrial fibrillation, except when the atrial flutter and/or atrial fibrillation are associated with accessory bypass tracts (Wolff-Parkinson-White [WPW] and Lown-Ganong-Levine [LGL] syndromes).
In controlled studies in the U.S., about 60% of patients with supraventricular tachycardia converted to normal sinus rhythm within 10 minutes after intravenous Verapamil hydrochloride. Uncontrolled studies reported in the world literature describe a conversion rate of about 80%. About 70% of patients with atrial flutter and/or fibrillation with a fast ventricular rate respond with a decrease in heart rate of at least 20%.
Conversion of atrial flutter or fibrillation to sinus rhythm is uncommon (about 10%) after Verapamil hydrochloride and may reflect the spontaneous conversion rate, since the conversion rate after placebo was similar. The effect of a single injection lasts for 30–60 minutes when conversion to sinus rhythm does not occur. Because a small fraction (<1.0%) of patients treated with Verapamil hydrochloride respond with life-threatening adverse responses (rapid ventricular rate in atrial flutter/fibrillation with an accessory bypass tract, marked hypotension, or extreme bradycardia/asystole—see Contraindications and Warnings ), the initial use of intravenous Verapamil hydrochloride should, if possible, be in a treatment setting with monitoring and resuscitation facilities, including DC-cardioversion capability (see Suggested Treatment of Acute Cardiovascular Adverse Reactions ) .
As familiarity with the patient’s response is gained, an office setting may be acceptable. Cardioversion has been used safely and effectively after intravenous Verapamil.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION For intravenous use only. VERAPAMIL SHOULD BE GIVEN AS A SLOW INTRAVENOUS INJECTION OVER AT LEAST A TWO-MINUTE PERIOD OF TIME UNDER CONTINUOUS ECG AND BLOOD PRESSURE MONITORING. The recommended intravenous doses of Verapamil are as follows: Adult: Initial dose —5-10 mg (0.075-0.15 mg/kg body weight) given as an intravenous bolus.
Repeat dose— 10 mg (0.15 mg/kg body weight) 30 minutes after the first dose if the initial response is not adequate. Older patients— The dose should be administered over at least 3 minutes to minimize the risk of untoward drug effects. Pediatric: Initial dose 0-1 year: 0.1-0.2 mg/kg body weight (usual single dose range: 0.75-2 mg) should be administered as an intravenous bolus.
1-15 years: 0.1-0.3 mg/kg body weight (usual single dose range: 2-5 mg) should be administered as an intravenous bolus. Do not exceed 5 mg. Repeat dose 0-1 year: 0.1-0.2 mg/kg body weight (usual single dose range: 0.75-2 mg) 30 minutes after the first dose if the initial response is not adequate.
1-15 years: 0.1-0.3 mg/kg body weight (usual single dose range: 2-5 mg) 30 minutes after the first dose if the initial response is not adequate. Do not exceed 10 mg as a single dose. Note: Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Use only if solution is clear and vial seal is intact. Unused amount of solution should be discarded immediately following withdrawal of any portion of contents. For stability reasons this product is not recommended for dilution with Sodium Lactate Injection USP in polyvinyl chloride bags.
Admixing intravenous Verapamil with albumin, amphotericin B, hydralazine HCl, and trimethoprim with sulfamethoxazole should be avoided. Verapamil will precipitate in any solution with a pH above 6.0.
⛔ Contraindications ▾
CONTRAINDICATIONS Verapamil hydrochloride injection is contraindicated in: 1. Severe hypotension or cardiogenic shock 2. Second- or third-degree AV block (except in patients with a functioning artificial ventricular pacemaker) 3.
Sick sinus syndrome (except in patients with a functioning artificial ventricular pacemaker) 4. Severe congestive heart failure (unless secondary to a supraventricular tachycardia amenable to Verapamil therapy) 5. Patients receiving intravenous beta-adrenergic blocking drugs (e.g., propranolol).
Intravenous Verapamil and intravenous beta-adrenergic blocking drugs should not be administered in close proximity to each other (within a few hours), since both may have a depressant effect on myocardial contractility and AV conduction. 6. Patients with atrial flutter or atrial fibrillation and an accessory bypass tract (e.g., Wolff-Parkinson-White, Lown-Ganong-Levine syndromes).
These patients are at risk to develop ventricular tachyarrhythmia including ventricular fibrillation if Verapamil is administered. 7. Ventricular tachycardia.
Administration of intravenous Verapamil to patients with wide-complex ventricular tachycardia (QRS≥ 0.12 sec) can result in marked hemodynamic deterioration and ventricular fibrillation. Proper pretherapy diagnosis and differentiation from wide-complex supraventricular tachycardia is imperative in the emergency room setting. 8.
Known hypersensitivity to Verapamil hydrochloride
⚠️ Warnings ▾
WARNINGS VERAPAMIL SHOULD BE GIVEN AS A SLOW INTRAVENOUS INJECTION OVER AT LEAST A TWO-MINUTE PERIOD OF TIME. (See Dosage and Administration . ) Hypotension: Intravenous Verapamil often produces a decrease in blood pressure below baseline levels that is usually transient and asymptomatic but may result in dizziness. Systolic pressure less than 90 mm Hg and/or diastolic pressure less than 60 mm Hg was seen in 5%-10% of patients in controlled U.S. trials in supraventricular tachycardia and in about 10% of the patients with atrial flutter/fibrillation.
The incidence of symptomatic hypotension observed in studies conducted in the U.S. was approximately 1.5%. Three of the five symptomatic patients required pharmacologic treatment (norepinephrine bitartrate IV, metaraminol bitartrate IV, or 10% calcium gluconate IV). All recovered without sequelae.
Extreme bradycardia/asystole: Verapamil affects the AV and SA nodes and rarely may produce second- or third-degree AV block, bradycardia, and, in extreme cases, asystole. This is more likely to occur in patients with a sick sinus syndrome (SA nodal disease), which is more common in older patients. Bradycardia associated with sick sinus syndrome was reported in 0.3% of the patients treated in controlled double-blind trials in the U.S.
The total incidence of bradycardia (ventricular rate less than 60 beats/min) was 1.2% in these studies. Asystole in patients other than those with sick sinus syndrome is usually of short duration (few seconds or less), with spontaneous return to AV nodal or normal sinus rhythm. If this does not occur promptly, appropriate treatment should be initiated immediately.
(See Adverse Reactions including suggested treatment of adverse reactions.) Heart failure: When heart failure is not severe or rate related, it should be controlled with digitalis glycosides and diuretics, as appropriate, before Verapamil is used. In patients with moderately severe to severe cardiac dysfunction (pulmonary wedge pressure above 20 mm Hg, ejection fraction less than 30%), acute worsening of heart failure may be seen. Concomitant antiarrhythmic therapy: Digitalis: Intravenous Verapamil has been used concomitantly with digitalis preparations without the occurrence of serious adverse effects.
However, since both drugs slow AV conduction, patients should be monitored for AV block or excessive bradycardia. Procainamide: Intravenous Verapamil has been administered to a small number of patients receiving oral procainamide without the occurrence of serious adverse effects. Quinidine: Intravenous Verapamil has been administered to a small number of patients receiving oral quinidine without the occurrence of serious adverse effects.
However a few cases of hypotension have been reported in patients taking oral quinidine who received intravenous Verapamil. Caution should therefore be used when employing this combination of drugs. Beta-adrenergic blocking drugs: Intravenous Verapamil has been administered to patients receiving oral beta blockers without the development of serious adverse effects.
However, since both drugs may depress myocardial contractility or AV conduction, the possibility of detrimental interactions should be considered. The concomitant administration of intravenous beta blockers and intravenous Verapamil has resulted in serious adverse reactions (see Contraindications ), especially in patients with severe cardiomyopathy, congestive heart failure, or recent myocardial infarction. Disopyramide: Until data on possible interactions between Verapamil and disopyramide are obtained, disopyramide should not be administered within 48 hours before or 24 hours after Verapamil administration.
Heart block: Verapamil prolongs AV conduction time. While high-degree AV block has not been observed in controlled clinical trials in the U.S., a low percentage (less than 0.5%) has been reported in the world literature. Development of second- or third-degree AV block or unifascicular, bifascicular, o…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following reactions were reported with intravenous Verapamil use in controlled U.S. clinical trials involving 324 patients: Cardiovascular: Symptomatic hypotension (1.5%); bradycardia (1.2%); severe tachycardia (1.0%). The worldwide experience in open clinical trials in more than 7,900 patients was similar. Central nervous system effects: Dizziness (1.2%); headache (1.2%).
Although rare, cases of seizures during verapamil injection has been reported. Gastrointestinal: Nausea (0.9%); abdominal discomfort (0.6%). In rare cases of hypersensitivity, broncho/laryngeal spasm accompanied by itch and urticaria has been reported.
The following reactions were reported in a few patients: emotional depression, rotary nystagmus, sleepiness, vertigo, muscle fatigue, or diaphoresis. Suggested Treatment of Acute Cardiovascular Adverse Reactions* The frequency of these adverse reactions was quite low, and experience with their treatment has been limited. Adverse Reaction Proven Effective Treatment Supportive Treatment 1.
Symptomatic hypotenstion requiring treatment Dopamine HCl IV Calcium chloride IV Norepinephrine bitartrate IV Metaraminol bitartrate IV Isoproterenol HCl IV Intravenous fluids Trendelenburg position 2. Bradycardia, AV block, Asystole Isoproterenol HCl IV Calcium chloride IV Norepinephrine bitartrate IV Atropine sulfate IV Cardiac pacing Intravenous fluids (slow drip) 3. Rapid ventricular rate (due to antegrade con- duction in flutter/fibrilla- tion with WPW or LGL syndromes) DC-cardioversion (high energy may be required) Procainamide IV Lidocaine HCl IV Intravenous fluids (slow drip) *Actual treatment and dosage should depend on the severity of the clinical situation and the judgment and experience of the treating physician.
🆘 Overdosage ▾
OVERDOSAGE Treatment of overdosage should be supportive and individualized. Beta-adrenergic stimulation and/or parenteral administration of calcium solutions (calcium chloride) have been effectively used in treatment of deliberate overdosage with oral Verapamil. Clinically significant hypotensive reactions or high-degree AV block should be treated with vasopressor agents or cardiac pacing, respectively.
Asystole should be handled by the usual measures including isoproterenol hydrochloride, other vasopressor agents, or cardiopulmonary resuscitation (see Suggested Treatment of Acute Cardiovascular Adverse Reactions ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of action: Verapamil inhibits the calcium ion (and possibly sodium ion) influx through slow channels into conductile and contractile myocardial cells and vascular smooth muscle cells. The antiarrhythmic effect of Verapamil appears to be due to its effect on the slow channel in cells of the cardiac conductile system. Electrical activity through the SA and AV nodes depends, to a significant degree, upon calcium influx through the slow channel.
By inhibiting this influx, Verapamil slows AV conduction and prolongs the effective refractory period within the AV node in a rate-related manner. This effect results in a reduction of the ventricular rate in patients with atrial flutter and/or atrial fibrillation and a rapid ventricular response. By interrupting reentry at the AV node, Verapamil can restore normal sinus rhythm in patients with paroxysmal supraventricular tachycardias (PSVT), including Wolff-Parkinson-White (WPW) syndrome.
Verapamil has no effect on conduction across accessory bypass tracts. Verapamil does not alter the normal atrial action potential or intraventricular conduction time but depresses amplitude, velocity of depolarization, and conduction in depressed atrial fibers. In the isolated rabbit heart, concentrations of Verapamil that markedly affect SA nodal fibers or fibers in the upper and middle regions of the AV node have very little effect on fibers in the lower AV node (NH region) and no effect on atrial action potentials or His bundle fibers.
Verapamil does not induce peripheral arterial spasm. Verapamil has a local anesthetic action that is 1.6 times that of procaine on an equimolar basis. It is not known whether this action is important at the doses used in man.
Verapamil does not alter total serum calcium levels. Hemodynamics: Verapamil reduces afterload and myocardial contractility. In most patients, including those with organic cardiac disease, the negative inotropic action of Verapamil is countered by reduction of afterload, and cardiac index is usually not reduced, but in patients with moderately severe to severe cardiac dysfunction (pulmonary wedge pressure above 20 mm Hg, ejection fraction less than 30%), acute worsening of heart failure may be seen.
Peak therapeutic effects occur within 3 to 5 minutes after a bolus injection. The commonly used intravenous doses of 5-10 mg Verapamil produce transient, usually asymptomatic, reduction in normal systemic arterial pressure, systemic vascular resistance and contractility; left ventricular filling pressure is slightly increased. Pharmacokinetics: Intravenously administered Verapamil has been shown to be rapidly metabolized.
Following intravenous infusion in man, verapamil is eliminated bi-exponentially, with a rapid early distribution phase (half-life about 4 minutes) and a slower terminal elimination phase (half-life 2-5 hours). In healthy men, orally administered Verapamil undergoes extensive metabolism in the liver, with 12 metabolites having been identified, most in only trace amounts. The major metabolites have been identified as various N- and O-dealkylated products of Verapamil.
Approximately 70% of an administered dose is excreted in the urine and 16% or more in the feces within 5 days. About 3% to 4% is excreted as unchanged drug.
🧬 Mechanism of Action ▾
Mechanism of action: Verapamil inhibits the calcium ion (and possibly sodium ion) influx through slow channels into conductile and contractile myocardial cells and vascular smooth muscle cells. The antiarrhythmic effect of Verapamil appears to be due to its effect on the slow channel in cells of the cardiac conductile system. Electrical activity through the SA and AV nodes depends, to a significant degree, upon calcium influx through the slow channel.
By inhibiting this influx, Verapamil slows AV conduction and prolongs the effective refractory period within the AV node in a rate-related manner. This effect results in a reduction of the ventricular rate in patients with atrial flutter and/or atrial fibrillation and a rapid ventricular response. By interrupting reentry at the AV node, Verapamil can restore normal sinus rhythm in patients with paroxysmal supraventricular tachycardias (PSVT), including Wolff-Parkinson-White (WPW) syndrome.
Verapamil has no effect on conduction across accessory bypass tracts. Verapamil does not alter the normal atrial action potential or intraventricular conduction time but depresses amplitude, velocity of depolarization, and conduction in depressed atrial fibers. In the isolated rabbit heart, concentrations of Verapamil that markedly affect SA nodal fibers or fibers in the upper and middle regions of the AV node have very little effect on fibers in the lower AV node (NH region) and no effect on atrial action potentials or His bundle fibers.
Verapamil does not induce peripheral arterial spasm. Verapamil has a local anesthetic action that is 1.6 times that of procaine on an equimolar basis. It is not known whether this action is important at the doses used in man.
Verapamil does not alter total serum calcium levels.
📋 Description ▾
DESCRIPTION Verapamil hydrochloride is a calcium antagonist or slow-channel inhibitor available as a sterile solution for intravenous injection in 5-mg (2 ml) and 10-mg (4 ml) vials. Each form contains Verapamil HCl 2.5 mg/ml and sodium chloride 8.5 mg/ml in water for injection. Hydrochloric acid and/or sodium hydroxide is used for pH adjustment.
The pH of the solution is between 4.1 and 6.0. The structural formula of verapamil HCl is given below: Benzeneacetonitrile, α-[3-[[2-(3,4-dimethoxyphenyl)ethyl] methylamino]propyl]-3,4-dimethoxy-α-(1-methylethyl) hydrochloride Verapamil hydrochloride is an almost white, crystalline powder, practically free of odor, with a bitter taste. It is soluble in water, chloroform, and methanol.
Verapamil hydrochloride is not chemically related to other antiarrhythmic drugs. structure