
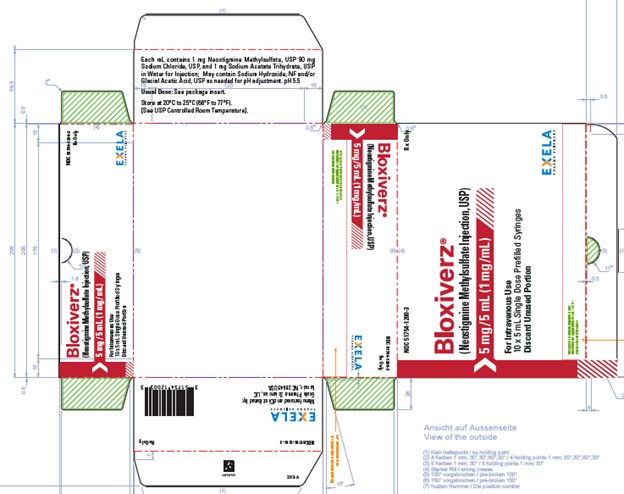
Bloxiverz Neostigmine Methylsulfate 1 mg/mL Injection
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Cholinesterase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- During surgery, you may be given a muscle relaxant to keep your muscles completely still — including your breathing muscles. When the procedure is over, the care team needs those m...
- What exactly does neostigmine methylsulfate do during or after surgery?
- Neostigmine is given directly into a vein by the anesthesia team, so you won't feel a needle stick in the usual sense. Some people experience nausea, increased saliva, or a slow or...
- Yes — it's important to tell your anesthesia team if you have heart disease, irregular heart rhythms, or had a recent heart attack, because neostigmine can affect your heart rate a...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Neostigmine Methylsulfate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $309.77 | $3,097.75 / 10 syringes |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2710 | No ASP payment limit on file for J2710 this quarter. | |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bloxiverz 1 mg/mLthis 51754-1200-03 | Exela | 10 syringes | — | — | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 00548-9602-00 | Amphastar | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 25021-0611-10 | Sagent | 10 vials | — | AP | FDA listed | — |
| neostigmine methylsulfate 1 mg/mL 31722-0995-31 | Camber | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 65145-0112-10 | Caplin | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 70069-0806-10 | Somerset | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 70594-0072-02 | Xellia | 10 vials | — | AP | FDA listed | — |
| Neostigmine methylsulfate 1 mg/mL 71839-0106-10 | BE | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 63323-0415-10 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 71872-7016-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 71872-7143-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 71872-7271-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 00641-6265-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 23155-0518-41 | Heritage | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 51662-1557-03 | HF | 10 pouches | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 00641-6277-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Neostigmine methylsulfate 1 mg/mL 68083-0384-10 | Gland | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 72572-0462-10 | Civica, | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 00641-6149-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 14445-0414-01 | Indoco | 1 vial | — | AP | FDA listed | — |
| Neostigmine methylsulfate 1 mg/mL 70700-0172-22 | Xiromed | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 65219-0811-10 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 71872-7322-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 76045-0214-30 | Fresenius | 1 syringe | — | AP | FDA listed | — |
| Neostigmine methylsulfate 1 mg/mL 84549-0172-23 | ProPharma | 10 ml | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 42023-0189-10 | Par | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 43598-0945-58 | Dr.Reddys | 1 syringe | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 55150-0349-10 | Eugia | 10 vials | — | — | FDA listed | — |
| Neostigmine methylsulfate 1 mg/mL 70121-1479-07 | Amneal | 10 vials | — | AP | FDA listed | — |
| Neostigmine Methylsulfate 1 mg/mL 76045-0383-30 | Fresenius | 1 syringe | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51754-1200-03 You're viewing this | 10 SYRINGE, PLASTIC in 1 CARTON (51754-1200-3) / 5 mL in 1 SYRINGE, PLASTIC | 2023-12-31 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BLOXIVERZ, is a cholinesterase inhibitor, indicated for the reversal of the effects of non-depolarizing neuromuscular blocking agents after surgery. BLOXIVERZ, is a cholinesterase inhibitor, indicated for the reversal of the effects of non-depolarizing neuromuscular blocking agents after surgery ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Should be administered by trained healthcare providers ( 2.1 ) • Peripheral nerve stimulator and monitoring for twitch responses should be used to determine when BLOXIVERZ should be initiated and if additional doses are needed ( 2.2 ) o For reversal of NMBAs with shorter half-lives, when first twitch response is substantially greater than 10% of baseline, or when a second twitch is present: 0.03 mg/kg by intravenous route ( 2.2 ) o For reversal of NMBAs with longer half-lives or when first twitch response is close to 10% of baseline: 0.07 mg/kg by intravenous route ( 2.2 ) • Maximum total dosage is 0.07 mg/kg or up to a total of 5 mg (whichever is less) ( 2.2 ) • An anticholinergic agent, e.g., atropine sulfate or glycopyrrolate, should be administered prior to or concomitantly with BLOXIVERZ ( 2.4 ) 2.1.
Important Dosage Information BLOXIVERZ should be administered by trained healthcare providers familiar with the use, actions, characteristics, and complications of neuromuscular blocking agents (NMBA) and neuromuscular block reversal agents. Doses of BLOXIVERZ should be individualized, and a peripheral nerve stimulator should be used to determine the time of initiation of BLOXIVERZ and should be used to determine the need for additional doses. BLOXIVERZ is for intravenous use only and should be injected slowly over a period of at least 1 minute.
The BLOXIVERZ dosage is weight-based [see Dosage and Administration ( 2.2 )] . Prior to BLOXIVERZ administration and until complete recovery of normal ventilation, the patient should be well ventilated and a patent airway maintained. Satisfactory recovery should be judged by adequacy of skeletal muscle tone and respiratory measurements in addition to the response to peripheral nerve stimulation.
An anticholinergic agent, e.g., atropine sulfate or glycopyrrolate, should be administered prior to or concomitantly with BLOXIVERZ [see Dosage and Administration ( 2.4 )]
2.2Dosage in Adults a. Peripheral nerve stimulation devices capable of delivering a train-of-four (TOF) stimulus are essential to effectively using BLOXIVERZ. b. There must be a twitch response to the first stimulus in the TOF of at least 10% of its baseline level, i.e., the response prior to NMBA administration, prior to the administration of BLOXIVERZ. c.
Prior to administration, visually inspect BLOXIVERZ for particulate matter and discoloration. d. BLOXIVERZ should be injected slowly by intravenous route over a period of at least 1 minute. e. A 0.03 mg/kg to 0.07 mg/kg dose of BLOXIVERZ will generally achieve a TOF twitch ratio of 90% (TOF 0.9 ) within 10 to 20 minutes of administration.
Dose selection should be based on the extent of spontaneous recovery that has occurred at the time of administration, the half-life of the NMBA being reversed, and whether there is a need to rapidly reverse the NMBA. 1. The 0.03 mg/kg dose is recommended for: 1.
Reversal of NMBAs with shorter half-lives, e.g., rocuronium, or 2. When the first twitch response to the TOF stimulus is substantially greater than 10% of baseline or when a second twitch is present. 2.
The 0.07 mg/kg dose is recommended for 1. NMBAs with longer half-lives, e.g., vecuronium and pancuronium, or 2. When the first twitch response is relatively weak, i.e., not substantially greater than 10% of baseline or 3.
There is need for more rapid recovery. f. TOF monitoring should continue to be used to evaluate the extent of recovery of neuromuscular function and the possible need for an additional dose of BLOXIVERZ. g. TOF monitoring alone should not be relied upon to determine the adequacy of reversal of neuromuscular blockade as related to a patient’s ability to adequately ventilate and maintain a patent airway following tracheal extubation. h.
Patients should continue to be monitored for adequacy of reversal from NMBAs for a period of time that would assure full recovery based on the patient’s medical condition and the pharmacokinetics of ne…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS BLOXIVERZ is available as • Injection: 0.5 mg/mL, 5 mg of neostigmine methylsulfate in 10 mL multiple- dose vials • Injection: 1 mg/mL, 10 mg of neostigmine methylsulfate in 10 mL multiple-dose vials • Injection: 1 mg/mL, 5 mg of neostigmine methylsulfate in 5 mL single-dose prefilled syringe. Injection: 0.5 mg/mL and 1 mg/mL in 10 mL multiple-dose vials and 1 mg/mL in 5 mL single-dose prefilled syringe ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS BLOXIVERZ is contraindicated in patients with: • known hypersensitivity to neostigmine methylsulfate (known hypersensitivity reactions have included urticaria, angioedema, erythema multiforme, generalized rash, facial swelling, peripheral edema, pyrexia, flushing, hypotension, bronchospasm, bradycardia and anaphylaxis). • peritonitis or mechanical obstruction of the intestinal or urinary tract. • Hypersensitivity to neostigmine ( 4 ) • Peritonitis or mechanical obstruction of the intestinal or urinary tract ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Bradycardia: Atropine or glycopyrrolate should be administered prior to BLOXIVERZ to lessen risk of bradycardia. ( 5.1 ) • Serious Reactions with Coexisting Conditions: Use with caution in patients with, coronary artery disease, cardiac arrhythmias, recent acute coronary syndrome or myasthenia gravis. ( 5.2 ) • Neuromuscular Dysfunction: Can occur if large doses of BLOXIVERZ are administered when neuromuscular blockade is minimal; reduce dose if recovery from neuromuscular blockade is nearly complete.
( 5.4 )
5.1Bradycardia Neostigmine has been associated with bradycardia. Atropine sulfate or glycopyrrolate should be administered prior to BLOXIVERZ to lessen the risk of bradycardia [see Dosage and Administration ( 2.4 )] .
5.2Serious Adverse Reactions in Patients with Certain Coexisting Conditions BLOXIVERZ should be used with caution in patients with coronary artery disease, cardiac arrhythmias, recent acute coronary syndrome or myasthenia gravis. Because of the known pharmacology of neostigmine methylsulfate as an acetylcholinesterase inhibitor, cardiovascular effects such as bradycardia, hypotension or dysrhythmia would be anticipated. In patients with certain cardiovascular conditions such as coronary artery disease, cardiac arrhythmias or recent acute coronary syndrome, the risk of blood pressure and heart rate complications may be increased.
Risk of these complications may also be increased in patients with myasthenia gravis. Standard antagonism with anticholinergics (e.g., atropine) is generally successful to mitigate the risk of cardiovascular complications.
5.3Hypersensitivity Because of the possibility of hypersensitivity, atropine and medications to treat anaphylaxis should be readily available.
5.4Neuromuscular Dysfunction Large doses of BLOXIVERZ administered when neuromuscular blockade is minimal can produce neuromuscular dysfunction. The dose of BLOXIVERZ should be reduced if recovery from neuromuscular blockade is nearly complete.
5.5Cholinergic Crisis It is important to differentiate between myasthenic crisis and cholinergic crisis caused by overdosage of BLOXIVERZ. Both conditions result in extreme muscle weakness but require radically different treatment [see Overdosage ( 10 )] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions during treatment: bradycardia, nausea and vomiting. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Exela Pharma Sciences, LLC at 1-888-451-4321 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse reactions to neostigmine methylsulfate are most often attributable to exaggerated pharmacological effects, in particular, at muscarinic receptor sites. The use of an anticholinergic agent, e.g., atropine sulfate or glycopyrrolate, may prevent or mitigate these reactions.
Quantitative adverse event data are available from trials of neostigmine methylsulfate in which 200 adult patients were exposed to the product. The following table lists the adverse reactions that occurred with an overall frequency of 1% or greater. System Organ Class Adverse Reaction Cardiovascular Disorders bradycardia, hypotension, tachycardia/heart rate increase Gastrointestinal Disorders dry mouth, nausea, post-procedural nausea, vomiting General Disorders and Administration Site Conditions incision site complication, pharyngolaryngeal pain, procedural complication, procedural pain Nervous System Disorders dizziness, headache, postoperative shivering, prolonged neuromuscular blockade Psychiatric Disorders insomnia Respiratory, Thoracic and Mediastinal Disorders dyspnea, oxygen desaturation <90% Skin and Subcutaneous Tissue Disorders pruritus
6.2Post Marketing Experience The following adverse reactions have been identified during parenteral use of neostigmine methylsulfate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. System Organ Class Adverse Reaction Allergic Disorders allergic reactions, anaphylaxis Nervous System Disorders convulsions, drowsiness, dysarthria, fasciculation, loss of consciousness, miosis, visual changes Cardiovascular Disorders cardiac arrest, cardiac arrhythmias (A-V block, nodal rhythm), hypotension, nonspecific EKG changes, syncope Respiratory, Thoracic and Mediastinal Disorders bronchospasm; increased oral, pharyngeal and bronchial secretions; respiratory arrest; respiratory depression Skin and Sub-cutaneous Tissue Disorders rash, urticaria Gastrointestinal Disorders bowel cramps, diarrhea, flatulence, increased peristalsis Renal and Urinary Disorders urinary frequency Musculoskeletal and Connective Tissue Disorders arthralgia, muscle cramps, spasms, weakness Miscellaneous diaphoresis, flushing
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The pharmacokinetic interaction between neostigmine methylsulfate and other drugs has not been studied. Neostigmine methylsulfate is metabolized by microsomal enzymes in the liver. Use with caution when using BLOXIVERZ with other drugs which may alter the activity of metabolizing enzymes or transporters.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Published studies and case reports over several decades about the use of neostigmine products, including neostigmine methylsulfate, in pregnant women have not identified any drug-associated risk for major birth defects and miscarriage. However, most of the available data are based on studies with exposure that occurred at the time of caesarean section or labor and delivery. These studies have not identified an adverse effect on maternal or infant outcomes.
In animal reproduction studies, no adverse developmental effects were observed after administration of neostigmine methylsulfate to pregnant rats and rabbits during organogenesis with doses up to 0.1 and 0.2 times, respectively, the maximum recommended human dose (MRHD) of 5mg/60kg/person/day based on body surface area (mg/m 2 ). The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Data Animal Data In embryofetal development studies, rats and rabbits were administered neostigmine methylsulfate at human equivalent doses (HED, on a mg/m 2 basis) of 1.6, 4 and 8.1 mcg/kg/day and 3.2, 8.1, and 13 mcg/kg/day, respectively, during the period of organogenesis (Gestation Days 6 through 17 for rats and Gestation Days 6 through 18 for rabbits).
There was no evidence for a teratogenic effect in rats and rabbits up to HED 8.1 and 13 mcg/kg/day, which are approximately 0.097 times and 0.16 times the MRHD of 5 mg/60 kg, respectively in the presence of minimal maternal toxicity (tremors, ataxia, and prostration). The studies resulted in exposures in the animals well below predicted exposures in humans. In a pre- and postnatal development study in rats, neostigmine methylsulfate was administered to pregnant female rats at human equivalent doses (HED) of 1.6, 4 and 8.1 mcg/kg/day from Day 6 of gestation through Day 20 of lactation, with weaning on Day 21.
There were no adverse effects on physical development, behavior, learning ability, or fertility in the offspring at HED doses up to 8.1 mcg/kg/day which is 0.097 times the MRHD of 5 mg/60 kg on a mg/m 2 basis in the presence of minimal maternal toxicity (tremors, ataxia, and prostration). The studies resulted in exposures in the animals well below predicted exposures in humans.
8.2Lactation Risk Summary Published data from case reports are insufficient to determine the presence of neostigmine methylsulfate in human milk or the effects on the breastfed infant. There is no information on the effects of neostigmine on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for BLOXIVERZ and any potential adverse effects on the breastfed infant from BLOXIVERZ or from the underlying maternal condition.
8.4Pediatric Use BLOXIVERZ is approved for the reversal of the effects of non-depolarizing neuromuscular blocking agents after surgery in pediatric patients of all ages. Recovery of neuromuscular activity occurs more rapidly with smaller doses of cholinesterase inhibitors in infants and children than in adults. However, infants and small children may be at greater risk of complications from incomplete reversal of neuromuscular blockade due to decreased respiratory reserve.
The risks associated with incomplete reversal outweigh any risk from giving higher doses of BLOXIVERZ (up to 0.07 mg/kg or up to a total of 5 mg, whichever is less). The dose of BLOXIVERZ required to reverse neuromuscular blockade in children varies between 0.03 mg - 0.07 mg/kg, the same dose range shown to be effective in adults, and should be selected using the same criteria as used for adult patients [see Clinical Pharmacology ( 12.3…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published studies and case reports over several decades about the use of neostigmine products, including neostigmine methylsulfate, in pregnant women have not identified any drug-associated risk for major birth defects and miscarriage. However, most of the available data are based on studies with exposure that occurred at the time of caesarean section or labor and delivery. These studies have not identified an adverse effect on maternal or infant outcomes.
In animal reproduction studies, no adverse developmental effects were observed after administration of neostigmine methylsulfate to pregnant rats and rabbits during organogenesis with doses up to 0.1 and 0.2 times, respectively, the maximum recommended human dose (MRHD) of 5mg/60kg/person/day based on body surface area (mg/m 2 ). The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20% respectively. Data Animal Data In embryofetal development studies, rats and rabbits were administered neostigmine methylsulfate at human equivalent doses (HED, on a mg/m 2 basis) of 1.6, 4 and 8.1 mcg/kg/day and 3.2, 8.1, and 13 mcg/kg/day, respectively, during the period of organogenesis (Gestation Days 6 through 17 for rats and Gestation Days 6 through 18 for rabbits).
There was no evidence for a teratogenic effect in rats and rabbits up to HED 8.1 and 13 mcg/kg/day, which are approximately 0.097 times and 0.16 times the MRHD of 5 mg/60 kg, respectively in the presence of minimal maternal toxicity (tremors, ataxia, and prostration). The studies resulted in exposures in the animals well below predicted exposures in humans. In a pre- and postnatal development study in rats, neostigmine methylsulfate was administered to pregnant female rats at human equivalent doses (HED) of 1.6, 4 and 8.1 mcg/kg/day from Day 6 of gestation through Day 20 of lactation, with weaning on Day 21.
There were no adverse effects on physical development, behavior, learning ability, or fertility in the offspring at HED doses up to 8.1 mcg/kg/day which is 0.097 times the MRHD of 5 mg/60 kg on a mg/m 2 basis in the presence of minimal maternal toxicity (tremors, ataxia, and prostration). The studies resulted in exposures in the animals well below predicted exposures in humans.
🧒 Pediatric Use ▾
8.4Pediatric Use BLOXIVERZ is approved for the reversal of the effects of non-depolarizing neuromuscular blocking agents after surgery in pediatric patients of all ages. Recovery of neuromuscular activity occurs more rapidly with smaller doses of cholinesterase inhibitors in infants and children than in adults. However, infants and small children may be at greater risk of complications from incomplete reversal of neuromuscular blockade due to decreased respiratory reserve.
The risks associated with incomplete reversal outweigh any risk from giving higher doses of BLOXIVERZ (up to 0.07 mg/kg or up to a total of 5 mg, whichever is less). The dose of BLOXIVERZ required to reverse neuromuscular blockade in children varies between 0.03 mg - 0.07 mg/kg, the same dose range shown to be effective in adults, and should be selected using the same criteria as used for adult patients [see Clinical Pharmacology ( 12.3 )] . Since the blood pressure in pediatric patients, particularly infants and neonates, is sensitive to changes in heart rate, the effects of an anticholinergic agent (e.g., atropine) should be observed prior to administration of neostigmine to lessen the probability of bradycardia and hypotension.
🧓 Geriatric Use ▾
8.5Geriatric Use Because elderly patients are more likely to have decreased renal function, BLOXIVERZ should be used with caution and monitored for a longer period in elderly patients. The duration of action of neostigmine methylsulfate is prolonged in the elderly; however, elderly patients also experience slower spontaneous recovery from neuromuscular blocking agents. Therefore, dosage adjustments are not generally needed in geriatric patients; however, they should be monitored for longer periods than younger adults to assure additional doses of BLOXIVERZ are not required.
The duration of monitoring should be predicated on the anticipated duration of action for the NMBA used on the patient [see Dosage and Administration ( 2.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE Muscarinic symptoms (nausea, vomiting, diarrhea, sweating, increased bronchial and salivary secretions, and bradycardia) may appear with overdosage of BLOXIVERZ (cholinergic crisis), but may be managed by the use of additional atropine or glycopyrrolate. The possibility of iatrogenic overdose can be lessened by carefully monitoring the muscle twitch response to peripheral nerve stimulation. Should overdosage occur, ventilation should be supported by artificial means until the adequacy of spontaneous respiration is assured, and cardiac function should be monitored.
Overdosage of BLOXIVERZ can cause cholinergic crisis, which is characterized by increasing muscle weakness, and through involvement of the muscles of respiration, may result in death. Myasthenic crisis, due to an increase in the severity of the disease, is also accompanied by extreme muscle weakness and may be difficult to distinguish from cholinergic crisis on a symptomatic basis. However, such differentiation is extremely important because increases in the dose of BLOXIVERZ or other drugs in this class, in the presence of cholinergic crisis or of a refractory or “insensitive” state, could have grave consequences.
The two types of crises may be differentiated by the use of edrophonium chloride as well as by clinical judgment. Treatment of the two conditions differs radically. Whereas the presence of myasthenic crisis requires more intensive anticholinesterase therapy, cholinergic crisis calls for the prompt withdrawal of all drugs of this type.
The immediate use of atropine in cholinergic crisis is also recommended. Atropine may also be used to lessen gastrointestinal side effects or other muscarinic reactions; but such use, by masking signs of overdosage, can lead to inadvertent induction of cholinergic crisis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Neostigmine methylsulfate is a competitive cholinesterase inhibitor. By reducing the breakdown of acetylcholine, neostigmine methylsulfate induces an increase in acetylcholine in the synaptic cleft which competes for the same binding site as nondepolarizing neuromuscular blocking agents, and reverses the neuromuscular blockade.
12.2Pharmacodynamics Neostigmine methylsulfate-induced increases in acetylcholine levels results in the potentiation of both muscarinic and nicotinic cholinergic activity. The resulting elevation of acetylcholine competes with nondepolarizing neuromuscular blocking agents to reverse neuromuscular blockade. Neostigmine methylsulfate does not readily cross the blood-brain barrier and, therefore, does not significantly affect cholinergic function in the central nervous system.
12.3Pharmacokinetics Distribution: Following intravenous injection, the observed neostigmine methylsulfate volume of distribution is reported between 0.12 and
1.4L/kg. Protein binding of neostigmine methylsulfate to human serum albumin ranges from 15 to 25%. Metabolism: Neostigmine methylsulfate is metabolized by microsomal enzymes in the liver.
Elimination: Following intravenous injection, the reported elimination half-life of neostigmine methylsulfate is between 24 and 113 minutes. Total body clearance of neostigmine methylsulfate is reported between 1.14 and 16.7 mL/min/kg. Renal impairment: Elimination half-life of neostigmine methylsulfate was prolonged in anephric patients compared to normal subjects; elimination half-life for normal, transplant and anephric patients were 79.8 ± 48.6, 104.7 ± 64 and 181 ± 54 min (mean ± SD), respectively.
Hepatic impairment: The pharmacokinetics of neostigmine methylsulfate in patients with hepatic impairment has not been studied. Pediatrics: Elimination half-life of neostigmine methylsulfate in infants (2-10 months), children (1-6 years) and adults (29-48 years) were 39 ± 5 min, 48 ± 16 min, and 67 ± 8 min (mean ± SD), respectively. Observed neostigmine methylsulfate clearance for infants, children and adults were 14 ± 3, 11 ± 3 and 10 ± 2 mL/min/kg (mean ± SD), respectively.
Drug Interaction Studies: The pharmacokinetic interaction between neostigmine methylsulfate and other drugs has not been studied.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Neostigmine methylsulfate is a competitive cholinesterase inhibitor. By reducing the breakdown of acetylcholine, neostigmine methylsulfate induces an increase in acetylcholine in the synaptic cleft which competes for the same binding site as nondepolarizing neuromuscular blocking agents, and reverses the neuromuscular blockade.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BLOXIVERZ (Neostigmine Methylsulfate Injection, USP) is available in the following: NDC No. Strength Vial Size 51754-1210-3 0.5 mg/mL 10 mL multiple-dose vials (supplied in packages of 10) 51754-1220-3 1 mg/mL 10 mL multiple-dose vials (supplied in packages of 10) 51754-1200-3 1 mg/mL 5 mL single-dose prefilled syringe (supplied in packages of 10) The vial stopper is not made with natural rubber latex. BLOXIVERZ should be stored at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) (see USP Controlled Room Temperature).
Protect from light. Store in carton until time of use. Manufactured for: Exela Pharma Sciences, LLC Lenoir, NC 28645 Logo
📦 Storage and Handling ▾
BLOXIVERZ should be stored at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) (see USP Controlled Room Temperature). Protect from light. Store in carton until time of use. Manufactured for: Exela Pharma Sciences, LLC Lenoir, NC 28645 Logo
📋 Description ▾
11 DESCRIPTION Neostigmine methylsulfate, a cholinesterase inhibitor, is ( m -hydroxyphenyl) trimethylammonium methylsulfate dimethylcarbamate. The structural formula is: Neostigmine methylsulfate is a white crystalline powder and is very soluble in water and soluble in alcohol. BLOXIVERZ is a sterile, nonpyrogenic solution intended for intravenous use.
Each mL of the 0.5 mg/mL strength contains neostigmine methylsulfate 0.5 mg, phenol 4.5 mg (used as preservative) and sodium acetate trihydrate 0.2 mg, in water for injection. The pH is adjusted, when necessary, with acetic acid/sodium hydroxide to achieve a value of 5.5. Each mL of the 1 mg/mL strength contains neostigmine methylsulfate 1 mg, phenol 4.5 mg (used as preservative), and sodium acetate trihydrate 0.2 mg, in water for injection.
The pH is adjusted, when necessary, with acetic acid/sodium hydroxide to achieve a value of 5.5. Each mL of the 5 mL single-dose prefilled syringe contains 1 mg neostigmine methylsulfate, USP, 90 mg sodium chloride, USP and 1 mg sodium acetate trihydrate, USP in water for injection. May contain sodium hydroxide, NF and/or glacial acetic acid, USP as needed for pH adjustment to achieve a value of 5.5. structure