
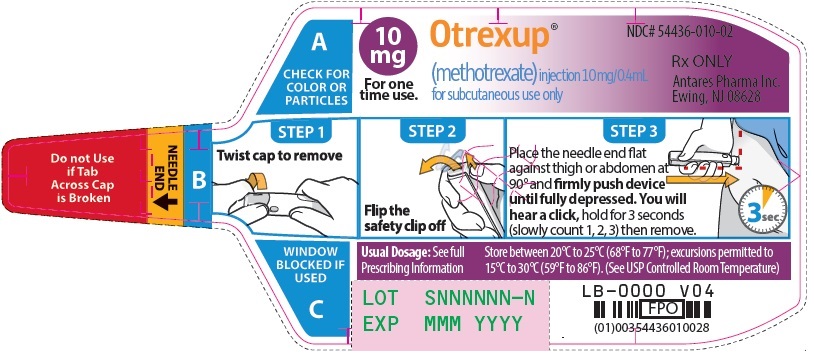
Otrexup methotrexate 20 mg/.4mL Injection, Solution, 4 syringes — NDC 54436-020-04 (Billing 54436-0020-04)
This is a package of 4 syringes of Otrexup methotrexate 20 mg/.4mL Injection, Solution from Antares Pharma, Inc., marketed since Oct 2013 and currently FDA-listed, this package's marketing is listed to end Apr 2027; retail pharmacies pay about $480.86 per mL (NADAC). It is the main listing for this product, which comes in 3 package sizes.
NDC database record
One package, one record: these facts belong to NDC 54436-020-04 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 54436 labeler · 020 product · 04 package
- Package marketed since
- Oct 11, 2013
- Package marketing ended
- Apr 30, 2027
- Sample package
- No — commercial package
- Barcode (UPC-A, from the NDC)
- 3 5443602004 1
- Medicaid fills, this package
- 218 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071563
- GCN: 35437
- GPI-14 (Medi-Span): 6625005000D525
- HICL (First Databank): 040683
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1441402
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Folate Analog Metabolic Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Methotrexate injection is used alone or in combination with other medications: to treat certain types of acute lymphocytic leukemia (ALL) in adults and children; to treat or prevent meningeal leukemia (cancer in the covering of the spinal cord and brain) in adults and children; to treat certain types of non-Hodgkin's lymphoma (types of cancer that begin in a type of white blood cells that normally fights infection) in adults and children; to treat osteosarcoma (cancer that forms in bones) after surgery to remove the tumor in adults and children; to treat cutaneous T-cell lymphoma (CTCL,...
Read the full MedlinePlus article ↗- It treats certain cancers, rheumatoid arthritis, polyarticular juvenile idiopathic arthritis and severe psoriasis. Which use applies depends on the product you were given. Otrexup...
- For many uses, such as arthritis and psoriasis, it is taken once a week, not daily. Taking it daily by mistake has caused deaths. Follow your prescriber's schedule exactly, and ask...
- Nausea, stomach upset, mouth sores, tiredness, dizziness, rash and hair loss are common. Call your doctor about a dry cough, bad diarrhea, fever, severe skin reactions or unusual b...
- NSAIDs and aspirin can raise methotrexate levels and increase toxicity, so check with your prescriber or pharmacist first. This matters most at high methotrexate doses. Also tell u...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Methotrexate — tap one for details:
Methotrexate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $480.855 | $769.37 / 1.6 ml |
| Medicaid paysCMS SDUD · 12 mo | $484.57 | $775.31 / 1.6 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Apr 15, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 54436-0020-01 54436-020-01 | 1 SYRINGE in 1 CARTON / .4 mL in 1 SYRINGE | — | — | 2013-10-11 | Apr 30, 2027 | Active |
| 54436-0020-03 54436-020-03 | 1 SYRINGE in 1 CARTON / .4 mL in 1 SYRINGE Sample | — | — | 2013-10-11 | Apr 30, 2027 | Active |
| 54436-0020-04 You're viewing this Main listing | 4 SYRINGE in 1 CARTON / .4 mL in 1 SYRINGE | $480.86 / mL | $769.37 | 2013-10-11 | Apr 30, 2027 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 54436-0020-01?
What NDC number is used to bill for this package of Otrexup methotrexate 20 mg/.4mL Injection, Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Otrexup 20 mg/.4mLthis 54436-0020-04 | Antares | 4 syringes | $480.855 | — | Availability likely | — |
| Rasuvo 20 mg/.4mL 59137-0530-01 | Medexus | 4 ml | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Apr 15, 2026
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8579865 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 9421333 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8480631 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 8945063 ↗ | Method of use | U-1442 | Mar 19, 2030 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 11497753 ↗ | Drug product | — | Mar 19, 2030 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 9629959 ↗ | Drug product | — | Jan 24, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 8562564 ↗ | Drug product | — | Jan 24, 2026 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
| US 10709844 ↗ | Drug product | — | Mar 10, 2029 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 11446441 ↗ | Drug product | — | Jan 24, 2026 |
| US 12357642 ↗ | Drug product | — | Mar 19, 2030 |
| US 9867949 ↗ | Drug product | — | Mar 10, 2029 |
| US 8021335 ↗ | Drug product | — | Oct 4, 2026 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 8814834 ↗ | Drug product | — | May 27, 2031 |
| US 9533102 ↗ | Drug product | — | Jan 24, 2026 |
| US 11684723 ↗ | Drug product | — | Mar 10, 2029 |
Is there a generic version of OTREXUP 20 MG/0.4 ML AUTO-INJ?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Methotrexate inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Antares Pharma, Inc. labeler code 54436
- Otrexup methotrexate 10 mg/.4mL Injection, Solution NDC 54436-010-01
- Otrexup methotrexate 12.5 mg/.4mL Injection, Solution NDC 54436-012-01
- Otrexup methotrexate 15 mg/.4mL Injection, Solution NDC 54436-015-01
- Otrexup methotrexate 17.5 mg/.4mL Injection, Solution NDC 54436-017-01
- Otrexup methotrexate 22.5 mg/.4mL Injection, Solution NDC 54436-022-01
- Otrexup methotrexate 25 mg/.4mL Injection, Solution NDC 54436-025-01
- XYOSTED testosterone enanthate 100 mg/.5mL Injection NDC 54436-200-01
- XYOSTED testosterone enanthate 50 mg/.5mL Injection NDC 54436-250-01
- XYOSTED testosterone enanthate 75 mg/.5mL Injection NDC 54436-275-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SEVERE TOXIC REACTIONS, INCLUDING EMBRYO-FETAL TOXICITY AND DEATH Otrexup should be used only by physicians whose knowledge and experience include the use of antimetabolite therapy. Because of the possibility of serious toxic reactions (which can be fatal), Otrexup should be used only in patients with psoriasis or rheumatoid arthritis with severe, recalcitrant, disabling disease which is not adequately responsive to other forms of therapy. Deaths have been reported with the use of methotrexate in the treatment of malignancy, psoriasis, and rheumatoid arthritis.
Patients should be closely monitored for bone marrow, liver, lung, skin, and kidney toxicities. Patients should be informed by their physician of the risks involved and be under a physician’s care throughout therapy [see Warnings and Precautions ( 5.1 )]. 1.
Methotrexate can cause embryo-fetal toxicity, including fetal death. Use is contraindicated during pregnancy. Verify the pregnancy status of females of reproductive potential prior to initiating therapy.
Advise females and males of reproductive potential to use effective contraception during and after treatment with Otrexup [see Contraindications ( 4 ), Warnings and Precautions ( 5.2 ), and Use in Specific Populations ( 8.1 , 8.3 )]. 2. Methotrexate elimination is reduced in patients with impaired renal functions, ascites, or pleural effusions.
Such patients require especially careful monitoring for toxicity, and require dose reduction or, in some cases, discontinuation of Otrexup administration [see Warnings and Precautions ( 5.6 )] . 3. Unexpectedly severe (sometimes fatal) bone marrow suppression, aplastic anemia, and gastrointestinal toxicity have been reported with concomitant administration of methotrexate (usually in high dosage) along with some nonsteroidal anti-inflammatory drugs (NSAIDs) [see Warnings and Precautions ( 5.1 ) and Drug Interactions ( 7.1 )].
4. Methotrexate causes hepatotoxicity, fibrosis and cirrhosis, but generally only after prolonged use. Acutely, liver enzyme elevations are frequently seen.
These are usually transient and asymptomatic, and also do not appear predictive of subsequent hepatic disease. Liver biopsy after sustained use often shows histologic changes, and fibrosis and cirrhosis have been reported; these latter lesions may not be preceded by symptoms or abnormal liver function tests in the psoriasis population. For this reason, periodic liver biopsies are usually recommended for psoriatic patients who are under long-term treatment.
Persistent abnormalities in liver function tests may precede appearance of fibrosis or cirrhosis in the rheumatoid arthritis population [see Warnings and Precautions ( 5.1 )]. 5. Methotrexate-induced lung disease, including acute or chronic interstitial pneumonitis, is a potentially dangerous lesion, which may occur acutely at any time during therapy and has been reported at low doses.
It is not always fully reversible and fatalities have been reported. Pulmonary symptoms (especially a dry, nonproductive cough) may require interruption of treatment and careful investigation [see Warnings and Precautions ( 5.1 )]. 6.
Diarrhea and ulcerative stomatitis require interruption of therapy: otherwise, hemorrhagic enteritis and death from intestinal perforation may occur [see Warnings and Precautions ( 5.1 )]. 7. Malignant lymphomas, which may regress following withdrawal of methotrexate, may occur in patients receiving low-dose methotrexate and, thus, may not require cytotoxic treatment.
Discontinue Otrexup first and, if the lymphoma does not regress, appropriate treatment should be instituted [see Warnings and Precautions ( 5.8 )] . 8. Like other cytotoxic drugs, methotrexate may induce “tumor lysis syndrome” in patients with rapidly growing tumors [see Warnings and Precautions ( 5.9 )] .
9. Severe, occasionally fatal, skin reactions have been reported following single or multiple doses of methotrexate. Reactions have occurred within days of oral… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Otrexup is a folate analog metabolic inhibitor indicated for the: • Management of patients with severe, active rheumatoid arthritis (RA) and polyarticular juvenile idiopathic arthritis (pJIA), who are intolerant of or had an inadequate response to first-line therapy ( 1.1 ). • Symptomatic control of severe, recalcitrant, disabling psoriasis in adults who are not adequately responsive to other forms of therapy ( 1.2 ). Limitation of Use Otrexup is not indicated for the treatment of neoplastic diseases ( 1.3 ).
1.1Rheumatoid Arthritis including Polyarticular Juvenile Idiopathic Arthritis Otrexup is indicated in the management of selected adults with severe, active rheumatoid arthritis (RA) (ACR criteria), or children with active polyarticular juvenile idiopathic arthritis (pJIA), who have had an insufficient therapeutic response to, or are intolerant of, an adequate trial of first-line therapy including full dose non-steroidal anti-inflammatory agents (NSAIDs).
1.2Psoriasis Otrexup is indicated in adults for the symptomatic control of severe, recalcitrant, disabling psoriasis that is not adequately responsive to other forms of therapy, but only when the diagnosis has been established, as by biopsy and/or after dermatologic consultation. It is important to ensure that a psoriasis “flare” is not due to an undiagnosed concomitant disease affecting immune responses.
1.3Limitation of Use Otrexup is not indicated for the treatment of neoplastic diseases.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Otrexup is for once weekly subcutaneous use only. Administer Otrexup in the abdomen or thigh. ( 2.1 ).
Use another formulation of methotrexate for patients requiring oral, intramuscular, intravenous, intra-arterial, or intrathecal dosing, doses less than 10 mg per week, doses above 25 mg per week, high-dose regimens, or dose adjustments of less than 5 mg increments ( 2.1 ). Starting doses of methotrexate: RA: 7.5 mg once weekly ( 2.2 ). pJIA: 10 mg/m 2 once weekly ( 2.2 ). Psoriasis: 10 to 25 mg once weekly of an oral, intramuscular, subcutaneous, or intravenous formulation ( 2.3 ).
Adjust dose gradually to achieve an optimal response ( 2.2 , 2.3 ).
2.1Important Dosing Information Otrexup is a single-dose auto-injector for once-weekly subcutaneous use only [see Warnings and Precautions ( 5.5 )] . Administer Otrexup in the abdomen or the thigh. Otrexup is available in the following dosage strengths: 10, 12.5, 15, 17.5, 20, 22.5 and 25 mg.
Use another formulation of methotrexate for alternative dosing in patients who require oral, intramuscular, intravenous, intra-arterial, or intrathecal dosing, doses less than 10 mg per week, doses more than 25 mg per week, high-dose regimens, or dose adjustments between the available doses.
2.2Rheumatoid Arthritis including Polyarticular Juvenile Idiopathic Arthritis Recommended starting dose of methotrexate: Adult RA: 7.5 mg once weekly. pJIA : 10 mg/m 2 once weekly. For patients switching from oral methotrexate to Otrexup, consider any differences in bioavailability between oral and subcutaneously administered methotrexate [see Clinical Pharmacology ( 12.3 )] . Dosages may be adjusted gradually to achieve an optimal response.
Limited experience shows a significant increase in the incidence and severity of serious toxic reactions, especially bone marrow suppression, at doses greater than 20 mg/wk in adults. Although there is experience with doses up to 30 mg/m 2 /wk in children, there are too few published data to assess how doses over 20 mg/m 2 /wk might affect the risk of serious toxicity in children. Experience does suggest, however, that children receiving 20 to 30 mg/m 2 /wk (0.65 to 1.0 mg/kg/wk) may have better absorption and fewer gastrointestinal side effects if methotrexate is administered either intramuscularly or subcutaneously.
Therapeutic response usually begins within 3 to 6 weeks and the patient may continue to improve for another 12 weeks or more. The optimal duration of therapy is unknown. Limited data available from long-term studies in adults indicate that the initial clinical improvement is maintained for at least two years with continued therapy.
When methotrexate is discontinued, the arthritis usually worsens within 3 to 6 weeks. The patient should be fully informed of the risks involved and should be under constant supervision of the physician. Assessment of hematologic, hepatic, renal, and pulmonary function should be made by history, physical examination, and laboratory tests before beginning, periodically during, and before reinstituting Otrexup therapy [see Warnings and Precautions ( 5.4 )] .
Females of childbearing potential should not be started on Otrexup until pregnancy is excluded [see Contraindications ( 4 ) and Warnings and Precautions ( 5.2 )] All schedules should be continually tailored to the individual patient. An initial test dose may be given prior to the regular dosing schedule to detect any extreme sensitivity to adverse effects. Maximal myelosuppression usually occurs in seven to ten days.
2.3Psoriasis Recommended starting dose of methotrexate: Psoriasis: single weekly oral, intramuscular, subcutaneous, or intravenous doses of 10-25 mg. For patients switching from oral methotrexate to Otrexup, consider any differences in bioavailability between oral and subcutaneously administered methotrexate [see Clinical Pharmacology ( 12.3 )] . Dosage may be gradually adjusted to achieve optimal clinical response; 30 mg/week shoul… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Otrexup is an injection available as an autoinjector that administers a single 0.4 mL dose of methotrexate solution in the following dosage strengths: 10 mg/0.4 mL methotrexate 12.5 mg/0.4 mL methotrexate 15 mg/0.4 mL methotrexate 17.5 mg/0.4 mL methotrexate 20 mg/0.4 mL methotrexate 22.5 mg/0.4 mL methotrexate 25 mg/0.4 mL methotrexate Injection: Single-dose auto-injector delivering 0.4 mL of methotrexate in the following dosage strengths: 10 mg, 12.5 mg, 15 mg, 17.5 mg, 20 mg, 22.5 mg and 25 mg ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Otrexup is contraindicated in the following: • Pregnancy Otrexup can cause embryo-fetal toxicity and fetal death when administered during pregnancy [see Warnings and Precautions ( 5.2 ) and Use in Specific Populations ( 8.1 )]. • Alcoholism or Liver Disease Patients with alcoholism, alcoholic liver disease or other chronic liver disease [see Warnings and Precautions ( 5.1 ) ]. • Immunodeficiency Syndromes Patients who have overt or laboratory evidence of immunodeficiency syndromes [ see Warnings and Precautions ( 5.1 ) ]. • Preexisting Blood Dyscrasias Patients who have preexisting blood dyscrasias, such as bone marrow hypoplasia, leukopenia, thrombocytopenia, or significant anemia [see Warnings and Precautions ( 5.1 )]. • Hypersensitivity Patients with a known hypersensitivity to methotrexate.
Severe hypersensitivity reactions have been observed with methotrexate use [see Warnings and Precautions ( 5.1 ) and Adverse Reactions ( 6.1 and 6.2 )]. Pregnancy ( 4 ) Alcoholism or liver disease ( 4 ) Immunodeficiency syndromes ( 4 ) Preexisting blood dyscrasias ( 4 ) Hypersensitivity to methotrexate ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Organ system toxicity: Potential for serious toxicity. Only for use by physicians experienced in antimetabolite therapy ( 5.1 ). Effects on reproduction: May cause impairment of fertility, oligospermia and menstrual dysfunction ( 5.3 , 8.3 ).
Laboratory tests: Monitor complete blood counts, renal function and liver function tests ( 5.4 ). Risks from improper dosing: Mistaken daily use has led to fatal toxicity ( 5.5 ). Patients with impaired renal function, ascites, or pleural effusions: Elimination is reduced ( 5.6 ).
Dizziness and fatigue: May impair ability to drive or operate machinery ( 5.7 ).
5.1Organ System Toxicity Otrexup should be used only by physicians whose knowledge and experience include the use of antimetabolite therapy. Because of the possibility of serious toxic reactions (which can be fatal), Otrexup should be used only in patients with psoriasis or rheumatoid arthritis with severe, recalcitrant, disabling disease which is not adequately responsive to other forms of therapy. Deaths have been reported with the use of methotrexate in the treatment of malignancy, psoriasis, and rheumatoid arthritis.
Patients should be closely monitored for bone marrow, liver, lung and kidney toxicities. Otrexup has the potential for serious toxicity. Toxic effects may be related in frequency and severity to dose or frequency of administration but have been seen at all doses.
Because they can occur at any time during therapy, it is necessary to follow patients on Otrexup closely. Most adverse reactions are reversible if detected early. When such reactions do occur, the drug should be reduced in dosage or discontinued and appropriate corrective measures should be taken.
If necessary, this could include the use of leucovorin calcium and/or acute, intermittent hemodialysis with a high-flux dialyzer [see Overdosage ( 10 )] . If Otrexup therapy is reinstituted, it should be carried out with caution, with adequate consideration of further need for the drug and increased alertness as to possible recurrence of toxicity. The clinical pharmacology of methotrexate has not been well studied in older individuals.
Due to diminished hepatic and renal function as well as decreased folate stores in this population, relatively low doses should be considered, and these patients should be closely monitored for early signs of toxicity [see Use in Specific Populations ( 8.5 )]. Gastrointestinal: Diarrhea and ulcerative stomatitis require interruption of therapy: otherwise, hemorrhagic enteritis and death from intestinal perforation may occur. If vomiting, diarrhea, or stomatitis occur, which may result in dehydration, Otrexup should be discontinued until recovery occurs.
Otrexup should be used with extreme caution in the presence of peptic ulcer disease or ulcerative colitis. Unexpectedly severe (sometimes fatal) gastrointestinal toxicity has been reported with concomitant administration of methotrexate (usually in high dosage) along with some nonsteroidal anti-inflammatory drugs (NSAIDs) [see Drug Interactions ( 7.1 )]. Hematologic: Otrexup can suppress hematopoiesis and cause anemia, aplastic anemia, pancytopenia, leukopenia, neutropenia, and/or thrombocytopenia.
In patients with preexisting hematopoietic impairment, Otrexup should be used with caution, if at all. In controlled clinical trials conducted with another formulation of methotrexate in rheumatoid arthritis (n=128), leukopenia (WBC <3000/mm 3 ) was seen in 2 patients, thrombocytopenia (platelets <100,000/mm 3 ) in 6 patients, and pancytopenia in 2 patients. Otrexup should be stopped immediately if there is a significant drop in blood counts.
Patients with profound granulocytopenia and fever should be evaluated immediately and usually require parenteral broad-spectrum antibiotic therapy. Unexpectedly severe (sometimes fatal) bone marrow suppression and aplastic anemia have been reported with concomitant administration of methotrexate (usually in high dosage) alo… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling. Organ System Toxicity [see Warnings and Precautions ( 5.1 )] Embryo-Fetal Toxicity [see Warnings and Precautions ( 5.2 )] Effects on Reproduction [see Warnings and Precautions ( 5.3 )] Malignant Lymphomas [see Warnings and Precautions ( 5.8 )] The most frequently reported adverse reactions include ulcerative stomatitis, leukopenia, nausea, and abdominal distress. Other frequently reported adverse reactions are malaise, undue fatigue, chills and fever, dizziness and decreased resistance to infection.
Common adverse reactions are: nausea, abdominal pain, dyspepsia, stomatitis/mouth sores, rash, nasopharyngitis, diarrhea, liver function test abnormalities, vomiting, headache, bronchitis, thrombocytopenia, alopecia, leucopenia, pancytopenia, dizziness, photosensitivity, and “burning of skin lesions” ( 6 ). To report SUSPECTED ADVERSE REACTIONS, contact Antares at 1-855-Otrexup (1-855-687-3987) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience This section provides a summary of adverse reactions reported in subjects in clinical studies conducted with Otrexup as well as with methotrexate injection and oral methotrexate. Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug, and may not reflect the rates observed in practice. Rheumatoid Arthritis The approximate incidences of methotrexate-attributed (i.e. placebo rate subtracted) adverse reactions in 12 to 18 week double-blind studies of patients (n=128) with rheumatoid arthritis treated with low-dose oral (7.5 to 15 mg/week) pulse methotrexate, are listed below.
Virtually all of these patients were on concomitant nonsteroidal anti-inflammatory drugs and some were also taking low dosages of corticosteroids. Hepatic histology was not examined in these short-term studies. Incidence greater than 10%: Elevated liver function tests 15%, nausea/vomiting 10%.
Incidence 3% to 10%: Stomatitis, thrombocytopenia (platelet count less than 100,000/mm 3 ). Incidence 1% to 3%: Rash/pruritis/dermatitis, diarrhea, alopecia, leukopenia (WBC less than 3000/mm 3 ), pancytopenia, dizziness. Two other controlled trials of patients (n=680) with Rheumatoid Arthritis on 7.5 mg to 15 mg/wk oral doses showed an incidence of interstitial pneumonitis of 1%.
Other less common reactions included decreased hematocrit, headache, upper respiratory infection, anorexia, arthralgias, chest pain, coughing, dysuria, eye discomfort, epistaxis, fever, infection, sweating, tinnitus, and vaginal discharge. Polyarticular Juvenile Idiopathic Arthritis The approximate incidences of adverse reactions reported in pediatric patients with pJIA treated with oral, weekly doses of methotrexate (5 to 20 mg/m 2 /wk or 0.1 to 0.65 mg/kg/wk) were as follows (virtually all patients were receiving concomitant nonsteroidal anti-inflammatory drugs, and some also were taking low doses of corticosteroids): elevated liver function tests, 14%; gastrointestinal reactions (e.g., nausea, vomiting, diarrhea), 11%; stomatitis, 2%; leukopenia, 2%; headache, 1.2%; alopecia, 0.5%; dizziness, 0.2%; and rash, 0.2%.
Although there is experience with dosing up to 30 mg/m 2 /wk in pJIA, the published data for doses above 20 mg/m 2 /wk are too limited to provide reliable estimates of adverse reaction rates. Psoriasis There are two literature reports (Roenigk, 1969, and Nyfors, 1978) describing large series (n=204, 248) of psoriasis patients treated with methotrexate. Dosages ranged up to 25 mg per week and treatment was administered for up to four years.
With the exception of alopecia, photosensitivity, and “burning of skin lesions” (each 3% to 10%), the adverse reaction rates in these reports were very similar to those in the rheumatoid arthritis studies. Rarel… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Aspirin, NSAIDs, and steroids: concomitant use may elevate and prolong serum methotrexate levels and cause increased toxicity ( 7.1 ). Proton pump inhibitors : concomitant use may elevate and prolong serum methotrexate levels and cause increased toxicity ( 7.2 ).
7.1Aspirin, Nonsteroidal Anti-Inflammatory Drugs, and Steroids Nonsteroidal anti-inflammatory drugs (NSAIDs) should not be administered prior to or concomitantly with the high doses of methotrexate, such as used in the treatment of osteosarcoma. Concomitant administration of some NSAIDs with high dose methotrexate therapy has been reported to elevate and prolong serum methotrexate levels, resulting in deaths from severe hematologic and gastrointestinal toxicity [see Warnings and Precautions ( 5.1 )]. Caution should be used when NSAIDs and salicylates are administered concomitantly with lower doses of methotrexate, including Otrexup.
These drugs have been reported to reduce the tubular secretion of methotrexate in an animal model and may enhance its toxicity. Despite the potential interactions, studies of methotrexate in patients with rheumatoid arthritis have usually included concurrent use of constant dosage regimens of NSAIDs, without apparent problems. It should be appreciated, however, that the doses used in rheumatoid arthritis (7.5 to 15 mg/week) are somewhat lower than those used in psoriasis and that larger doses could lead to unexpected toxicity.
Aspirin, NSAIDs, and/or low dose steroids may be continued, although the possibility of increased toxicity with concomitant use of NSAIDs including salicylates has not been fully explored. Steroids may be reduced gradually in patients who respond to methotrexate.
7.2Proton Pump Inhibitors (PPIs) Use caution if high-dose methotrexate is administered to patients receiving proton pump inhibitor (PPI) therapy. Case reports and published population pharmacokinetic studies suggest that concomitant use of some PPIs, such as omeprazole, esomeprazole, and pantoprazole, with methotrexate (primarily at high dose), may elevate and prolong serum levels of methotrexate and/or its metabolite hydroxymethotrexate, possibly leading to methotrexate toxicities. In two of these cases, delayed methotrexate elimination was observed when high-dose methotrexate was co-administered with PPIs, but was not observed when methotrexate was co-administered with ranitidine.
However, no formal drug interaction studies of methotrexate with ranitidine have been conducted.
7.3Oral Antibiotics Oral antibiotics such as tetracycline, chloramphenicol, and nonabsorbable broad spectrum antibiotics, may decrease intestinal absorption of methotrexate or interfere with the enterohepatic circulation by inhibiting bowel flora and suppressing metabolism of the drug by bacteria. Penicillins may reduce the renal clearance of methotrexate; increased serum concentrations of methotrexate with concomitant hematologic and gastrointestinal toxicity have been observed with high and low dose methotrexate.
Use of Otrexup with penicillins should be carefully monitored. Trimethoprim/sulfamethoxazole has been reported rarely to increase bone marrow suppression in patients receiving methotrexate, probably by decreased tubular secretion and/or an additive antifolate effect.
7.4Hepatotoxins The potential for increased hepatotoxicity when methotrexate is administered with other hepatotoxic agents has not been evaluated. However, hepatotoxicity has been reported in such cases. Therefore, patients receiving concomitant therapy with Otrexup and other potential hepatotoxins (e.g., azathioprine, retinoids, and sulfasalazine) should be closely monitored for possible increased risk of hepatotoxicity.
7.5Theophylline Methotrexate may decrease the clearance of theophylline; theophylline levels should be monitored when used concurrently with Otrexup.
7.6Folic Acid and Antifolates Vitamin preparations containing folic acid or its derivatives may decrease responses to… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric use: Safety and efficacy of methotrexate, including Otrexup, have not been established in pediatric patients with psoriasis. Safety and efficacy of Otrexup have not been established in pediatric patients with malignancy ( 8.4 ). Geriatric use: Use caution in dose selection ( 8.5 ). Lactation: Advise women not to breastfeed ( 8.2 ).
8.1Pregnancy Risk Summary Based on published reports and methotrexate’s mechanism of action, methotrexate can cause embryo-fetal toxicity and fetal death when administered to a pregnant woman [see Data and Clinical Pharmacology ( 12.1 )] . In pregnant women with non-malignant disease, Otrexup is contraindicated. Consider the benefits and risks of Otrexup and risks to the fetus when prescribing Otrexup to a pregnant patient.
There are no animal data that meet current standards for nonclinical developmental toxicity studies. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Human Data Published data from cases, literature reviews, and observational studies report that methotrexate exposure during pregnancy is associated with an increased risk of embryo-fetal toxicity and fetal death. Methotrexate exposure during the first trimester of pregnancy is associated with an increased incidence of spontaneous abortions and multiple adverse developmental outcomes, including skull anomalies, facial dysmorphism, central nervous system abnormalities, limb abnormalities, and sometimes cardiac anomalies and intellectual impairment.
Adverse outcomes associated with exposure during second and third trimesters of pregnancy include intrauterine growth restriction and functional abnormalities. Because methotrexate is widely distributed and persists in the body for a prolonged period, there is a potential risk to the fetus from preconception methotrexate exposure. A prospective multicenter study evaluated pregnancy outcomes in women taking methotrexate less than or equal to 30 mg/week after conception.
The rate of miscarriage in pregnant women exposed to methotrexate was 42.5% (95% confidence interval [95% CI] 29.2-58.7), which was higher than in unexposed patients with autoimmune disease (22.5%, 95% CI 16.8-29.7) and unexposed patients with non-autoimmune disease (17.3%, 95% CI 13-22.8). Of the live births, the rate of major birth defects in pregnant women exposed to methotrexate after conception was higher than in unexposed patients with autoimmune disease (adjusted odds ratio (OR) 1.8 [95% CI 0.6-5.7]) and unexposed patients with non-autoimmune disease (adjusted OR 3.1 [95% CI 1.03-9.5]).
Major birth defects associated with pregnancies exposed to methotrexate after conception were not always consistent with methotrexate-associated adverse developmental outcomes.
8.2Lactation Risk Summary Limited published literature report the presence of methotrexate in human milk in low amounts following oral methotrexate administration, with the highest breast milk to plasma concentration ratio reported to be 0.08:1. No information is available on the effects of methotrexate on a breastfed infant or on milk production. Because of the potential for serious adverse reactions including myelosuppression, from methotrexate in breastfed infants, advise women not to breastfeed during treatment with Otrexup and for one week after the final dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating Otrexup. Contraception Females Otrexup can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations ( 8.1 )] . Advise females of reproductive potential to u… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on published reports and methotrexate’s mechanism of action, methotrexate can cause embryo-fetal toxicity and fetal death when administered to a pregnant woman [see Data and Clinical Pharmacology ( 12.1 )] . In pregnant women with non-malignant disease, Otrexup is contraindicated. Consider the benefits and risks of Otrexup and risks to the fetus when prescribing Otrexup to a pregnant patient.
There are no animal data that meet current standards for nonclinical developmental toxicity studies. The estimated background risk of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Human Data Published data from cases, literature reviews, and observational studies report that methotrexate exposure during pregnancy is associated with an increased risk of embryo-fetal toxicity and fetal death. Methotrexate exposure during the first trimester of pregnancy is associated with an increased incidence of spontaneous abortions and multiple adverse developmental outcomes, including skull anomalies, facial dysmorphism, central nervous system abnormalities, limb abnormalities, and sometimes cardiac anomalies and intellectual impairment.
Adverse outcomes associated with exposure during second and third trimesters of pregnancy include intrauterine growth restriction and functional abnormalities. Because methotrexate is widely distributed and persists in the body for a prolonged period, there is a potential risk to the fetus from preconception methotrexate exposure. A prospective multicenter study evaluated pregnancy outcomes in women taking methotrexate less than or equal to 30 mg/week after conception.
The rate of miscarriage in pregnant women exposed to methotrexate was 42.5% (95% confidence interval [95% CI] 29.2-58.7), which was higher than in unexposed patients with autoimmune disease (22.5%, 95% CI 16.8-29.7) and unexposed patients with non-autoimmune disease (17.3%, 95% CI 13-22.8). Of the live births, the rate of major birth defects in pregnant women exposed to methotrexate after conception was higher than in unexposed patients with autoimmune disease (adjusted odds ratio (OR) 1.8 [95% CI 0.6-5.7]) and unexposed patients with non-autoimmune disease (adjusted OR 3.1 [95% CI 1.03-9.5]).
Major birth defects associated with pregnancies exposed to methotrexate after conception were not always consistent with methotrexate-associated adverse developmental outcomes.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of methotrexate, including Otrexup, have not been established in pediatric patients with psoriasis. The safety and effectiveness of Otrexup have not been established in pediatric patients with neoplastic diseases. The safety and effectiveness of methotrexate have been established in pediatric patients with polyarticular juvenile idiopathic arthritis [see Clinical Studies ( 14.2 )] .
Published clinical studies evaluating the use of methotrexate in children and adolescents (i.e., patients 2 to 16 years of age) with pJIA demonstrated safety comparable to that observed in adults with rheumatoid arthritis [ see Adverse Reactions ( 6.1 ) ]. Otrexup does not contain a preservative. However, methotrexate injectable formulations containing the preservative benzyl alcohol are not recommended for use in neonates.
There have been reports of fatal ‘gasping syndrome’ in neonates (children less than one month of age) following the administrations of intravenous solutions containing the preservative benzyl alcohol. Symptoms include a striking onset of gasping respiration, hypotension, bradycardia, and cardiovascular collapse. Serious neurotoxicity, frequently manifested as generalized or focal seizures, has been reported with unexpectedly increased frequency among pediatric patients with acute lymphoblastic leukemia who were treated with intermediate-dose intravenous methotrexate (1 gm/m 2 ) [see Warnings and Precautions ( 5.1 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of methotrexate did not include sufficient numbers of subjects age 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious reflecting the greater frequency of decreased hepatic and renal function, decreased folate stores, concomitant disease or other drug therapy (i.e., that interfere with renal function, methotrexate or folate metabolism) in this population [see Warnings and Precautions ( 5.1 ), Drug Interactions ( 7.7 ) and Use in Specific Populations ( 8.6 )].
Since decline in renal function may be associated with increases in adverse reactions and serum creatinine measurements may over estimate renal function in the elderly, more accurate methods (i.e., creatinine clearance) should be considered. Serum methotrexate levels may also be helpful. Elderly patients should be closely monitored for early signs of hepatic, bone marrow and renal toxicity.
In chronic use situations, certain toxicities may be reduced by folate supplementation. Post-marketing experience suggests that the occurrence of bone marrow suppression, thrombocytopenia, and pneumonitis may increase with age [see Warnings and Precautions ( 5.1 )].
🆘 Overdosage ▾
10 OVERDOSAGE Leucovorin is indicated to diminish the toxicity and counteract the effect of inadvertently administered overdosages of methotrexate. Leucovorin administration should begin as promptly as possible. As the time interval between methotrexate administration and leucovorin initiation increases, the effectiveness of leucovorin in counteracting toxicity decreases.
Monitoring of the serum methotrexate concentration is essential in determining the optimal dose and duration of treatment with leucovorin. In cases of massive overdosage, hydration and urinary alkalinization may be necessary to prevent the precipitation of methotrexate and/or its metabolites in the renal tubules. Generally speaking, neither hemodialysis nor peritoneal dialysis has been shown to improve methotrexate elimination.
However, effective clearance of methotrexate has been reported with acute, intermittent hemodialysis using a high-flux dialyzer (Wall, SM et al: Am J Kidney Dis 28 (6): 846-854, 1996). Accidental intrathecal overdosage may require intensive systemic support, high-dose systemic leucovorin, alkaline diuresis and rapid CSF drainage and ventriculolumbar perfusion. In postmarketing experience, overdose with methotrexate has generally occurred with oral and intrathecal administration, although intravenous and intramuscular overdose have also been reported.
Reports of oral overdose often indicate accidental daily administration instead of weekly (single or divided doses). Symptoms commonly reported following oral overdose include those symptoms and signs reported at pharmacologic doses, particularly hematologic and gastrointestinal reaction. For example, leukopenia, thrombocytopenia, anemia, pancytopenia, bone marrow suppression, mucositis, stomatitis, oral ulceration, nausea, vomiting, gastrointestinal ulceration, gastrointestinal bleeding.
In some cases, no symptoms were reported. There have been reports of death following overdose. In these cases, events such as sepsis or septic shock, renal failure, and aplastic anemia were also reported.
Symptoms of intrathecal overdose are generally central nervous system (CNS) symptoms, including headache, nausea and vomiting, seizure or convulsion, and acute toxic encephalopathy. In some cases, no symptoms were reported. There have been reports of death following intrathecal overdose.
In these cases, cerebellar herniation associated with increased intracranial pressure, and acute toxic encephalopathy have also been reported. There are published case reports of intravenous and intrathecal carboxypeptidase G2 treatment to hasten clearance of methotrexate in cases of overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Methotrexate inhibits dihydrofolic acid reductase. Dihydrofolates must be reduced to tetrahydrofolates by this enzyme before they can be utilized as carriers of one-carbon groups in the synthesis of purine nucleotides and thymidylate. Therefore, methotrexate interferes with DNA synthesis, repair, and cellular replication.
Actively proliferating tissues such as malignant cells, bone marrow, fetal cells, buccal and intestinal mucosa, and cells of the urinary bladder are in general more sensitive to this effect of methotrexate. The mechanism of action in rheumatoid arthritis is unknown; it may affect immune function.
12.2Pharmacodynamics Two reports describe in vitro methotrexate inhibition of DNA precursor uptake by stimulated mononuclear cells, and another describes in animal polyarthritis partial correction by methotrexate of spleen cell hyporesponsiveness and suppressed IL 2 production. Other laboratories, however, have been unable to demonstrate similar effects. Clarification of methotrexate’s effect on immune activity and its relation to rheumatoid immunopathogenesis await further studies.
In psoriasis, the rate of production of epithelial cells in the skin is greatly increased over normal skin. This differential in proliferation rates is the basis for the use of methotrexate to control the psoriatic process. Methotrexate in high doses, followed by leucovorin rescue, is used as a part of the treatment of patients with non-metastatic osteosarcoma.
The original rationale for high dose methotrexate therapy was based on the concept of selective rescue of normal tissues by leucovorin. More recent evidence suggests that high dose methotrexate may also overcome methotrexate resistance caused by impaired active transport, decreased affinity of dihydrofolic acid reductase for methotrexate, increased levels of dihydrofolic acid reductase resulting from gene amplification, or decreased polyglutamation of methotrexate. The actual mechanism of action is unknown.
12.3Pharmacokinetics Absorption In adults, oral absorption appears to be dose dependent. Peak serum levels are reached within one to two hours. At doses of 30 mg/m 2 or less, methotrexate is generally well absorbed with a mean bioavailability of about 60%.
The absorption of doses greater than 80 mg/m 2 is significantly less, possibly due to a saturation effect. In relative bioavailability studies in rheumatoid arthritis patients, systemic exposure of methotrexate was found to be similar between Otrexup and intramuscular or subcutaneous administration of methotrexate injection at the same doses, however systemic exposure of methotrexate was higher with Otrexup as compared to oral administration of methotrexate at the same dose. Bioavailability following oral dosing showed a plateau effect at doses of 15 mg and greater.
The systemic exposure of methotrexate from Otrexup at doses of 10, 15, 20, and 25 mg was higher than that of oral methotrexate by 17, 13, 31, and 36%, respectively. Methotrexate systemic absorption from Otrexup was similar when administered into the abdomen or thigh. In leukemic pediatric patients, oral absorption of methotrexate also appears to be dose dependent and has been reported to vary widely (23% to 95%).
A twenty fold difference between highest and lowest peak levels (Cmax: 0.11 to 2.3 micromolar after a 20 mg/m 2 dose) has been reported. Significant interindividual variability has also been noted in time to peak concentration (Tmax: 0.67 to 4 hrs after a 15 mg/m 2 dose) and fraction of dose absorbed. The absorption of doses greater than 40 mg/m 2 has been reported to be significantly less than that of lower doses.
Food has been shown to delay absorption and reduce peak concentration. Methotrexate is generally completely absorbed from parenteral routes of injection. After intramuscular injection, peak serum concentrations occur in 30 to 60 minutes.
As in leukemic pediatric patients, a wide interindividual… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Methotrexate inhibits dihydrofolic acid reductase. Dihydrofolates must be reduced to tetrahydrofolates by this enzyme before they can be utilized as carriers of one-carbon groups in the synthesis of purine nucleotides and thymidylate. Therefore, methotrexate interferes with DNA synthesis, repair, and cellular replication.
Actively proliferating tissues such as malignant cells, bone marrow, fetal cells, buccal and intestinal mucosa, and cells of the urinary bladder are in general more sensitive to this effect of methotrexate. The mechanism of action in rheumatoid arthritis is unknown; it may affect immune function.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Otrexup contains methotrexate in a preservative-free sterile solution for a single subcutaneous injection. Otrexup is available in the following strengths and configurations. Otrexup (methotrexate) injection 10 mg/0.4 mL Carton of 1 NDC 54436-010-01 Carton of 4 NDC 54436-010-04 Otrexup NDC 54436-010-02 Otrexup (methotrexate) injection 12.5 mg/0.4 mL Carton of 1 NDC 54436-012-01 Carton of 4 NDC 54436-012-04 Otrexup NDC 54436-012-02 Otrexup (methotrexate) injection 15 mg/0.4 mL Carton of 1 NDC 54436-015-01 Carton of 4 NDC 54436-015-04 Otrexup NDC 54436-015-02 Otrexup (methotrexate) injection 17.5 mg/0.4 mL Carton of 1 NDC 54436-017-01 Carton of 4 NDC 54436-017-04 Otrexup NDC 54436-017-02 Otrexup (methotrexate) injection 20 mg/0.4 mL Carton of 1 NDC 54436-020-01 Carton of 4 NDC 54436-020-04 Otrexup NDC 54436-020-02 Otrexup (methotrexate) injection 22.5 mg/0.4 mL Carton of 1 NDC 54436-022-01 Carton of 4 NDC 54436-022-04 Otrexup NDC 54436-022-02 Otrexup (methotrexate) injection 25 mg/0.4 mL Carton of 1 NDC 54436-025-01 Carton of 4 NDC 54436-025-04 Otrexup NDC 54436-025-02 Store at controlled room temperature, 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F).
PROTECT FROM LIGHT. Handling and Disposal Handle and dispose of Otrexup consistent with recommendations for handling and disposal of cytotoxic drugs. 1
📋 Description ▾
11 DESCRIPTION Otrexup contains methotrexate, a folate analog metabolic inhibitor. Chemically, methotrexate is [N-[4-[[(2,4-diamino-6-pteridinyl)methyl]methylamino]benzoyl]-Lglutamic acid. The structural formula is: C 20 H 22 N 8 O 5 M.W.= 454.45 Otrexup contains methotrexate in a sterile, preservative-free, unbuffered solution with a 27 gauge ½ inch needle for a single subcutaneous injection.
Otrexup solution is yellow in color. Inactive ingredients include sodium chloride and water for injection, USP. The amounts of sodium chloride vary with the amount of methotrexate.
Amount of methotrexate (mg) per 0.4 mL 10 12.5 15 17.5 20 22.5 25 Amount of sodium chloride (mg) per 0.4 mL 1.96 2.04 1.60 1.48 1.28 0.92
0.56Hydrochloric acid and additional sodium hydroxide may have been added, if necessary, to adjust the pH to 8.0. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling ( Patient Information and Instructions for Use ) Risk of Organ Toxicity Inform patients of the risks of organ toxicity, including gastrointestinal, hematologic, hepatic, infections, neurologic, pulmonary, renal and skin as well as possible signs and symptoms for which they should contact their healthcare provider. Advise patients of the need for close follow-up, including periodic laboratory tests to monitor toxicity [see Warnings and Precautions ( 5.1 and 5.4 )] .
Importance of Proper Dosing and Administration Both the physician and pharmacist should emphasize to the patient that the recommended dose is taken weekly and that mistaken daily use of the recommended dose has led to fatal toxicity [see Dosing and Administration ( 2 )] . Otrexup is intended for use under the guidance and supervision of a physician. Patients should not self-administer until they receive training from a healthcare professional.
The patient’s or caregiver’s ability to administer Otrexup should be assessed. A trainer device is available for training purposes. Patients should be instructed to use administration sites on the abdomen or the thigh.
Administration should not be made within 2 inches of the navel. Instruct patients not to administer Otrexup to the arms or any other areas of the body, as delineated in the Otrexup Instructions for Use [see Instructions for Use ] . Embryo-Fetal Toxicity Advise females of reproductive potential that Otrexup can cause fetal harm and is contraindicated in pregnancy.
Advise women of childbearing potential that Otrexup should not be started until pregnancy is excluded. Women should be fully counseled on the serious risk to the fetus should they become pregnant while undergoing treatment. Inform patients to contact their physician if they suspect that they are pregnant [see Boxed Warning , Contraindications ( 4 ), Warnings and Precautions ( 5.2 ), Use in Specific Populations ( 8.1 )] .
Advise females of reproductive potential to use effective contraception during Otrexup therapy and for 6 months after the final dose [see Use in Specific Populations ( 8.3 )] . Advise males of reproductive potential to use effective contraception during Otrexup therapy and for 3 months after the final dose [see Use in Specific Populations ( 8.3 )] . Infertility Advise patients of reproductive potential that Otrexup may cause impairment of fertility, oligospermia, and menstrual dysfunction [see Warnings and Precautions ( 5.2 ), Use in Specific Populations ( 8.3 )] .
Lactation Advise females not to breastfeed during treatment with Otrexup and for one week after the final dose [see Use in Specific Populations ( 8.3 )] . Ability to Drive or Operate Machinery Inform patients that adverse reactions such as dizziness and fatigue may affect their ability to drive or operate machinery. Proper Storage and Disposal Advise patients to store Otrexup at room temperature (68 to 77°F or 20 to 25°C).
Inform patients and caregivers of the need for proper disposal after use, including the use of a sharps disposal container. Address Medical Inquiries to: Antares Pharma, Inc. Medical Communications 100 Princeton South, Suite 300 Ewing, NJ 08628 1-855-Otrexup (1-855-687-3987) Manufactured for: Antares Pharma, Inc.
100 Princeton South, Suite 300 Ewing, NJ 08628 USA Otrexup™ is the subject of US Patent Nos. 8,021,335, 6,746,429, 8,480,631, 8,562,564, 8,579,865, and 8,945,063. ©2019 Antares Pharma, Inc., Ewing, NJ 08628 Antares Pharma Logo
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption In adults, oral absorption appears to be dose dependent. Peak serum levels are reached within one to two hours. At doses of 30 mg/m 2 or less, methotrexate is generally well absorbed with a mean bioavailability of about 60%.
The absorption of doses greater than 80 mg/m 2 is significantly less, possibly due to a saturation effect. In relative bioavailability studies in rheumatoid arthritis patients, systemic exposure of methotrexate was found to be similar between Otrexup and intramuscular or subcutaneous administration of methotrexate injection at the same doses, however systemic exposure of methotrexate was higher with Otrexup as compared to oral administration of methotrexate at the same dose. Bioavailability following oral dosing showed a plateau effect at doses of 15 mg and greater.
The systemic exposure of methotrexate from Otrexup at doses of 10, 15, 20, and 25 mg was higher than that of oral methotrexate by 17, 13, 31, and 36%, respectively. Methotrexate systemic absorption from Otrexup was similar when administered into the abdomen or thigh. In leukemic pediatric patients, oral absorption of methotrexate also appears to be dose dependent and has been reported to vary widely (23% to 95%).
A twenty fold difference between highest and lowest peak levels (Cmax: 0.11 to 2.3 micromolar after a 20 mg/m 2 dose) has been reported. Significant interindividual variability has also been noted in time to peak concentration (Tmax: 0.67 to 4 hrs after a 15 mg/m 2 dose) and fraction of dose absorbed. The absorption of doses greater than 40 mg/m 2 has been reported to be significantly less than that of lower doses.
Food has been shown to delay absorption and reduce peak concentration. Methotrexate is generally completely absorbed from parenteral routes of injection. After intramuscular injection, peak serum concentrations occur in 30 to 60 minutes.
As in leukemic pediatric patients, a wide interindividual variability in the plasma concentrations of methotrexate has been reported in pediatric patients with JIA. Following oral administration of methotrexate in doses of 6.4 to 11.2 mg/m 2 /week in pediatric patients with JIA, mean serum concentrations were 0.59 micromolar (range, 0.03 to 1.40) at 1 hour, 0.44 micromolar (range, 0.01 to 1.00) at 2 hours, and 0.29 micromolar (range, 0.06 to 0.58) at 3 hours. Distribution After intravenous administration, the initial volume of distribution is approximately
0.18L/kg (18% of body weight) and steady-state volume of distribution is approximately 0.4 to
0.8L/kg (40 to 80% of body weight). Methotrexate competes with reduced folates for active transport across cell membranes by means of a single carrier-mediated active transport process. At serum concentrations greater than 100 micromolar, passive diffusion becomes a major pathway by which effective intracellular concentrations can be achieved.
Methotrexate in serum is approximately 50% protein bound. Laboratory studies demonstrate that it may be displaced from plasma albumin by various compounds including sulfonamides, salicylates, tetracyclines, chloramphenicol, and phenytoin. Methotrexate does not penetrate the blood-cerebrospinal fluid barrier in therapeutic amounts when given orally or parenterally.
High CSF concentrations of the drug may be attained by intrathecal administration of other parenteral forms of methotrexate. In dogs, synovial fluid concentrations after oral dosing were higher in inflamed than uninflamed joints. Although salicylates did not interfere with this penetration, prior prednisone treatment reduced penetration into inflamed joints to the level of normal joints.
Metabolism After absorption, methotrexate undergoes hepatic and intracellular metabolism to polyglutamated forms which can be converted back to methotrexate by hydrolase enzymes. These polyglutamates act as inhibitors of dihydrofolate reductase and thymidylate synthetase. Small amounts of methotrexate polyglutamates may remain in… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Two reports describe in vitro methotrexate inhibition of DNA precursor uptake by stimulated mononuclear cells, and another describes in animal polyarthritis partial correction by methotrexate of spleen cell hyporesponsiveness and suppressed IL 2 production. Other laboratories, however, have been unable to demonstrate similar effects. Clarification of methotrexate’s effect on immune activity and its relation to rheumatoid immunopathogenesis await further studies.
In psoriasis, the rate of production of epithelial cells in the skin is greatly increased over normal skin. This differential in proliferation rates is the basis for the use of methotrexate to control the psoriatic process. Methotrexate in high doses, followed by leucovorin rescue, is used as a part of the treatment of patients with non-metastatic osteosarcoma.
The original rationale for high dose methotrexate therapy was based on the concept of selective rescue of normal tissues by leucovorin. More recent evidence suggests that high dose methotrexate may also overcome methotrexate resistance caused by impaired active transport, decreased affinity of dihydrofolic acid reductase for methotrexate, increased levels of dihydrofolic acid reductase resulting from gene amplification, or decreased polyglutamation of methotrexate. The actual mechanism of action is unknown.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Rheumatoid Arthritis Clinical trials in patients with rheumatoid arthritis were performed using other formulations of methotrexate. In patients with rheumatoid arthritis, effects of methotrexate on articular swelling and tenderness can be seen as early as 3 to 6 weeks. Most studies of methotrexate in patients with rheumatoid arthritis are relatively short term (3 to 6 months).
Limited data from long-term studies indicate that an initial clinical improvement is maintained for at least two years with continued therapy.
14.2Polyarticular Juvenile Idiopathic Arthritis Clinical trials in patients with polyarticular juvenile idiopathic arthritis were performed using other formulations of methotrexate. In a 6-month double-blind, placebo-controlled trial of 127 pediatric patients with pJIA (mean age, 10.1 years; age range, 2.5 to 18 years; mean duration of disease, 5.1 years) on background nonsteroidal anti-inflammatory drugs and/or prednisone, methotrexate given weekly at an oral dose of 10 mg/m 2 provided significant clinical improvement compared to placebo as measured by either the physician’s global assessment, or by a patient composite (25% reduction in the articular-severity score plus improvement in parent and physician global assessments of disease activity).
Over two-thirds of the patients in this trial had polyarticular-course JIA, and the numerically greatest response was seen in this subgroup treated with 10 mg/m 2 /wk methotrexate. The overwhelming majority of the remaining patients had systemic-course JIA. All patients were unresponsive to NSAIDs; approximately one-third were using low dose corticosteroids.
Weekly methotrexate at a dose of 5 mg/m 2 was not significantly more effective than placebo in this trial.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Methotrexate has been evaluated in a number of animal studies for carcinogenic potential with inconclusive results. Although there is evidence that methotrexate causes chromosomal damage to animal somatic cells and human bone marrow cells, the clinical significance remains uncertain. Data are available regarding the risks for pregnancy and for fertility in humans [see Use in Specific Populations ( 8.1 and 8.3 )].
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Methotrexate has been evaluated in a number of animal studies for carcinogenic potential with inconclusive results. Although there is evidence that methotrexate causes chromosomal damage to animal somatic cells and human bone marrow cells, the clinical significance remains uncertain. Data are available regarding the risks for pregnancy and for fertility in humans [see Use in Specific Populations ( 8.1 and 8.3 )].
📚 References ▾
15 REFERENCES 1. “Hazardous Drugs”. OSHA . http://www.osha.gov/SLTC/hazardousdrugs/index.html
📄 Patient Package Insert ▾
Patient Package Insert PATIENT INFORMATION Otrexup™ (oh-TREKS-up) (methotrexate) injection, for subcutaneous use What is Otrexup? Otrexup is a single-dose auto-injector containing a prescription medicine, methotrexate. Methotrexate is used to: treat certain adults with severe, active rheumatoid arthritis (RA), and children with active polyarticular juvenile idiopathic arthritis (pJIA), after treatment with other medicines including non-steroidal anti-inflammatory (NSAIDS) have been used and did not work well. control the symptoms of severe, resistant, disabling psoriasis in adults when other types of treatment have been used and did not work well.
Otrexup is available in doses of 10, 12.5, 15, 17.5, 20, 22.5 and 25 mg. Your doctor will prescribe a different way to take methotrexate if you need to take methotrexate by mouth or in some other way. Your doctor may also change your prescription if your dose does not match the available Otrexup doses, such as doses of less than 10 mg, more than 25 mg, or doses in between the available Otrexup doses.
Otrexup should not be used for the treatment of cancer. Otrexup should not be used for the treatment of children with psoriasis. What is the most important information I should know about Otrexup ?
Otrexup can cause serious side effects that can lead to death, including: 1. Organ system toxicity. People who use methotrexate for the treatment of cancer, psoriasis, or rheumatoid arthritis, have an increased risk of death from organ toxicity.
Types of organ toxicity can include: o gastrointestinal o bone marrow o liver o immune system o nerve o lung o kidneys o skin Your doctor will do blood tests and other types of tests before you take and while you are taking Otrexup to check for signs and symptoms of organ toxicity. Call your doctor right away if you have any of the following symptoms of organ toxicity: o vomiting o diarrhea o mouth sores o fever o confusion o weakness o temporary blindness o seizures o headache o back pain o neck stiffness o paralysis o irritability o sleepiness o problems with coordination o dry cough o trouble breathing o severe skin rash 2.
Women who are pregnant are at increased risk for death of the baby and birth defects. Women who are pregnant or who plan to become pregnant must not take Otrexup. A pregnancy test should be performed before starting Otrexup.
Contraception should be used by both females and males while taking Otrexup. Pregnancy should be avoided if either partner is receiving Otrexup: for a minimum of 3 months after treatment with Otrexup for males. during and for 6 months after treatment with Otrexup for females. Who should not take Otrexup?
Do not take Otrexup if you: are pregnant or planning to become pregnant. See “What is the most important information I should know about Otrexup?" are breastfeeding. Otrexup can pass into your breast milk and may harm your baby.
Do not breastfeed while taking Otrexup. Talk to your doctor about the best way to feed your baby if you take Otrexup. have alcohol problems (alcoholism). have liver problems. have problems fighting infection (immunodeficiency syndrome). have been told you have (or think you have) a blood disorder such as low levels of white blood cells, red blood cells (anemia), or platelets. have had an allergy to methotrexate or any of the ingredients in Otrexup. See the end of this leaflet for a complete list of ingredients in Otrexup.
Talk to your doctor before taking this medicine if you have any of these conditions. What should I tell my doctor before taking Otrexup? Before you take Otrexup , tell your doctor if you have any other medical conditions.
Tell your doctor about all of the medicines you take , including prescription, over-the-counter medicines, vitamins, and herbal supplements. Otrexup may affect how other medicines work, and other medicines may affect how Otrexup works causing side effects. Ask your doctor or pharmacist for a list of medicines if you are not sure.
Know the medicines… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use Read this Instructions for Use before using Otrexup™ (oh-TREKS-up) (methotrexate) injection, for subcutaneous use Prepare to Use Otrexup Do not remove cap (marked 1) or safety clip (marked 2) until you are ready to inject Otrexup. Wash your hands well with soap and warm water. Check the expiration date on the label.
Do not use if expired. Check the seal. Do not use Otrexup if the seal is broken ( See Figure B ).
In addition to Otrexup, you will need the following items: 1 alcohol swab and 1 cotton ball or gauze. Check the Liquid Look at the viewing window ( See Figure C ). The liquid should be yellow in color and should not have any lumps or particles in it.
You may see an air bubble. This is normal. Choose an Injection Site Otrexup should be injected into the stomach (abdomen) or thigh.
Do not inject Otrexup within 2 inches of the belly button (navel) ( See Figure D ). Do not inject Otrexup in the arms or any other areas of the body. Do not inject Otrexup in areas where the skin is tender, bruised, red, scaly, hard, or has scars or stretch marks.
Wipe the area with an alcohol swab. Allow the skin to dry and do not touch this area again before giving Otrexup. Do not fan or blow on the clean area.
Give your Injection Step 1: Remove Cap (marked 1) Twist cap marked 1 to remove ( See Figure E ). This will break the seal. You may notice 1 or 2 drops of medicine.
This is normal. Do not touch the needle end with your hands or fingers. This could inject the medicine into your hand.
Do not replace the cap after it has been removed. After the cap is removed Otrexup must be used or disposed of safely (See step 5). STEP 2: Remove the Safety Clip (marked 2) Flip the Safety Clip marked 2 ( See Figure F ).
STEP 3: Inject Otrexup Place needle end of Otrexup flat against thigh or stomach (abdomen) at a 90° and firmly push device against the injection site until fully depressed. You will hear a click, hold for 3 seconds (slowly count 1,2,3) ( See Figure G ). After counting to 3, remove Otrexup from the injection site.
You may notice a small amount of blood or liquid at the administration site, which is normal. Press a cotton ball or gauze on the area for 10 seconds. Do not rub the area.
Step 4: Check the Viewing Window Check the viewing window ( See Figure H ). The viewing window will be half blocked with a red flag to show that the full dose was delivered. ( See Figure H ).
Dispose of Otrexup in a puncture-proof disposable container (See Step 5) . If the viewing window is not half blocked with a red flag , call your doctor or pharmacist, or call 1-855-Otrexup (1-855-687-3987) for help. Do not use another Otrexup without talking to your doctor.
Step 5: Dispose of Otrexup Do not throw away in the household trash . Put used Otrexup in a FDA-cleared sharps disposal container right away after use. If you do not have a FDA-cleared sharps disposal container, you may use a household container that is: made of a heavy-duty plastic can be closed with a tight-fitting, puncture-resistant lid, without sharps being able to come out upright and stable during use leak-resistant properly labeled to warn of hazardous waste inside the container When your sharps disposal container is almost full, you will need to follow your community guidelines for the right way to dispose of your sharps disposal container.
There may be state or local laws about how you should throw away used needles and syringes. For more information about the safe sharps disposal, and for specific information about sharps disposal in the state that you live in, go to the FDA’s website at: http://www.fda.gov/safesharpsdisposal. Do not dispose of your used sharps disposal container in your household trash unless your community guidelines permit this.
Do not recycle your used sharps disposal container. Safely dispose of Otrexup that is out of date or no longer needed. How should I store Otrexup?
Store Otrexup at room temperature between 68°F to 77°F (20°C to 25°C). Do not fre… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - Autoinjector 10 mg label
12.5 mg label
15 mg label
17.5 mg label
20 mg label
22.5 mg label
25 mg label
PRINCIPAL DISPLAY PANEL - Carton of 4 10 mg 4-pack carton label