
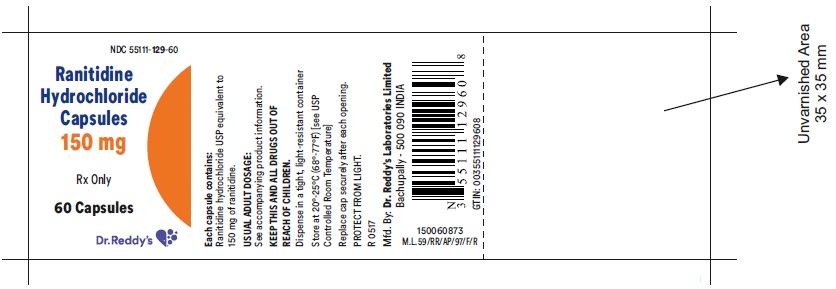
Ranitidine Hydrochloride 150 mg Capsule, 60-count — NDC 55111-129-60 (Billing 55111-0129-60)
This is a package of 60 capsules of Ranitidine Hydrochloride 150 mg Capsule from Dr. Reddy's Laboratories Limited, marketed since Jan 2001 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016223
- GCN: 19551
- GPI-14 (Medi-Span): 49200020100105
- HICL (First Databank): 004520
- AHFS class code: 56:28.12.00
- RxCUI (RxNorm): 198190
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Histamine-2 Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Ranitidine is used to reduce the amount of acid your stomach makes. Prescription versions treat ulcers in the stomach or small intestine, acid reflux disease (GERD), and acid damag...
- No, food doesn't significantly affect how ranitidine works, so you can take it with or without a meal. For prescription forms, your doctor will tell you how often to take it — usua...
- How should I take ranitidine — does it matter if I eat first?
- Most people do fine on ranitidine. The most common complaints are headache, constipation, diarrhea, nausea, or an upset stomach. Dizziness or trouble sleeping can also happen. Thes...
Patient education
Supplement & herbal interactions
Ranitidine may be associated with lower levels of 6 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 55111-0129-05 55111-129-05 Main listing | 500 CAPSULE in 1 BOTTLE | 2001-01-12 | — | Active |
| 55111-0129-60 You're viewing this | 60 CAPSULE in 1 BOTTLE | 2001-01-12 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 55111-0129-05?
What NDC number is used to bill for this package of Ranitidine Hydrochloride 150 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ranitidine Hydrochloride 150 mgthis 55111-0129-60 | Dr. | 60 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Ranitidine is indicated in: 1. Short-term treatment of active duodenal ulcer. Most patients heal within 4 weeks.
Studies available to date have not assessed the safety of ranitidine in uncomplicated duodenal ulcer for periods of more than 8 weeks. 2. Maintenance therapy for duodenal ulcer patients at reduced dosage after healing of acute ulcers.
No placebo-controlled comparative studies have been carried out for periods of longer than 1 year. 3.The treatment of pathological hypersecretory conditions (e.g., Zollinger-Ellison syndrome and systemic mastocytosis). 4.
Short-term treatment of active, benign gastric ulcer. Most patients heal within 6 weeks and the usefulness of further treatment has not been demonstrated. Studies available to date have not assessed the safety of ranitidine in uncomplicated, benign gastric ulcer for periods of more than 6 weeks.
5.Maintenance therapy for gastric ulcer patients at reduced dosage after healing of acute ulcers. Placebo-controlled studies have been carried out for 1 year. 6.Treatment of GERD.
Symptomatic relief commonly occurs within 24 hours after starting therapy with ranitidine 150 mg two times a day. 7. Treatment of endoscopically diagnosed erosive esophagitis.
Symptomatic relief of heartburn commonly occurs within 24 hours of therapy initiation with ranitidine 150 mg 4 times daily. 8. Maintenance of healing of erosive esophagitis.
Placebo-controlled trials have been carried out for 48 weeks. Concomitant antacids should be given as needed for pain relief to patients with active duodenal ulcer; active, benign gastric ulcer; hypersecretory states; GERD; and erosive esophagitis.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Active Duodenal Ulcer: The current recommended adult oral dosage of ranitidine for duodenal ulcer is 150 mg twice daily. An alternative dosage of 300 mg once daily after the evening meal or at bedtime can be used for patients in whom dosing convenience is important. The advantages of one treatment regimen compared to the other in a particular patient population have yet to be demonstrated (see CLINICAL PHARMACOLOGY : Clinical Trials : Active Duodenal Ulcer ).
Smaller doses have been shown to be equally effective in inhibiting gastric acid secretion in US studies, and several foreign trials have shown that 100 mg twice daily is as effective as the 150 mg dose. Antacid should be given as needed for relief of pain (see CLINICAL PHARMACOLOGY : Pharmacokinetics ) . Maintenance of Healing Duodenal Ulcers The current recommended adult oral dosage is 150 mg at bedtime.
Pathological Hypersecretory Conditions (such as Zollinger-Ellison syndrome) The current recommended adult oral dosage is 150 mg twice a day. In some patients it may be necessary to administer ranitidine 150 mg doses more frequently. Dosages should be adjusted to individual patient needs, and should continue as long as clinically indicated.
Dosages up to 6 g/day have been employed in patients with severe disease. Benign Gastric Ulcer The current recommended adult oral dosage is 150 mg twice a day. Maintenance of Healing of Gastric Ulcers The current recommended adult oral dosage is 150 mg at bedtime.
GERD The current recommended adult oral dosage is 150 mg twice a day. Erosive Esophagitis The current recommended adult oral dosage is 150 mg four times a day. Maintenance of Healing of Erosive Esophagitis The current recommended adult oral dosage is 150 mg twice a day.
Pediatric Use The safety and effectiveness of ranitidine has been established in the age-group of 1 month to 16 years. There is insufficient information about the pharmacokinetics of ranitidine in neonatal patients (less than 1 month of age) to make dosing recommendations. The following 3 subsections provide dosing information for each of the pediatric indications.
Treatment of Duodenal and Gastric Ulcers The recommended oral dose for the treatment of active duodenal and gastric ulcers is 2 to 4 mg/kg twice daily to a maximum of 300 mg/day. This recommendation is derived from adult clinical studies and pharmacokinetic data in pediatric patients. Maintenance of Healing of Duodenal and Gastric Ulcers The recommended oral dose for the maintenance of healing of duodenal and gastric ulcers is 2 to 4 mg/kg once daily to a maximum of 150 mg/day.
This recommendation is derived from adult clinical studies and pharmacokinetic data in pediatric patients. Treatment of GERD and Erosive Esophagitis Although limited data exist for these conditions in pediatric patients, published literature supports a dosage of 5 to 10 mg/kg per day, usually given as two divided doses. Dosage Adjustment for Patients with Impaired Renal Function On the basis of experience with a group of subjects with severely impaired renal function treated with ranitidine, the recommended dosage in patients with a creatinine clearance <50 mL/min is 150 mg every 24 hours.
Should the patient’s condition require, the frequency of dosing may beincreased to every 12 hours or even further with caution. Hemodialysis reduces the level of circulating ranitidine. Ideally, the dosing schedule should be adjusted so that the timing of a scheduled dose coincides with the end of hemodialysis.
Elderly patients are more likely to have decreased renal function, therefore caution should be exercised in dose selection, and it may be useful to monitor renal function (see CLINICAL PHARMACOLOGY : Pharmacokinetics : Geriatric Use and PRECAUTIONS : Geriatric Use ).
⛔ Contraindications ▾
CONTRAINDICATIONS Ranitidine is contraindicated for patients known to have hypersensitivity to the drug or any of the ingredients (see PRECAUTIONS ).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following have been reported as events in clinical trials or in the routine management of patients treated with ranitidine. The relationship to therapy with ranitidine has been unclear in many cases. Headache, sometimes severe, seems to be related to administration of ranitidine.
Central Nervous System Rarely, malaise, dizziness, somnolence, insomnia, and vertigo. Rare cases of reversible mental confusion, agitation, depression, and hallucinations have been reported, predominantly in severely ill elderly patients. Rare cases of reversible blurred vision suggestive of a change in accommodation have been reported.
Rare reports of reversible involuntary motor disturbances have been received. Cardiovascular As with other H 2 -blockers, rare reports of arrhythmias such as tachycardia, bradycardia, atrioventricular block, and premature ventricular beats. Gastrointestinal Constipation, diarrhea, nausea/vomiting, abdominal discomfort/pain, and rare reports of pancreatitis.
Hepatic There have been occasional reports of hepatocellular, cholestatic, or mixed hepatitis, with or without jaundice. In such circumstances, ranitidine should be immediately discontinued. These events are usually reversible, but in rare circumstances death has occurred.
Rare cases of hepatic failure have also been reported. In normal volunteers, SGPT values were increased to at least twice the pretreatment levels in 6 of 12 subjects receiving 100 mg 4 times daily intravenously for 7 days, and in 4 of 24 subjects receiving 50 mg 4 times daily for 5 days. Musculoskeletal Rare reports of arthralgias and myalgias.
Hematologic Blood count changes (leukopenia, granulocytopenia, and thrombocytopenia) have occurred in a few patients. These were usually reversible. Rare cases of agranulocytosis, pancytopenia, sometimes with marrow hypoplasia, and aplastic anemia and exceedingly rare cases of acquired immune hemolytic anemia have been reported.
Endocrine Controlled studies in animals and man have shown no stimulation of any pituitary hormone by ranitidine and no antiandrogenic activity, and cimetidine-induced gynecomastia and impotence in hypersecretory patients have resolved when ranitidine has been substituted. However, occasional cases of impotence and loss of libido have been reported in male patients receiving ranitidine, but the incidence did not differ from that in the general population. Rare cases of breast symptoms and conditions, including galactorrhea and gynecomastia, have been reported in both males and females.
Integumentary Rash, including rare cases of erythema multiforme. Rare cases of alopecia and vasculitis. Respiratory A large epidemiological study suggested an increased risk of developing pneumonia in current users of histamine-2-receptor antagonists (H 2 RAs) compared to patients who had stopped H 2 RA treatment, with an observed adjusted relative risk of 1.63 (95% CI, 1.07-2.48).
However, a causal relationship between use of H 2 RAs and pneumonia has not been established. Other Rare cases of hypersensitivity reactions (e.g., bronchospasm, fever, rash, eosinophilia), anaphylaxis, angioneurotic edema, acute interstitial nephritis, and small increases in serum creatinine.
🔄 Drug Interactions ▾
Drug Interactions Ranitidine has been reported to affect the bioavailability of other drugs through several different mechanisms such as competition for renal tubular secretion, alteration of gastric pH, and inhibition of cytochrome P450 enzymes. Procainamide: Ranitidine, a substrate of the renal organic cation transport system, may affect the clearance of other drugs eliminated by this route. High doses of ranitidine (e.g., such as those used in the treatment of Zollinger-Ellison syndrome) have been shown to reduce the renal excretion of procainamide and N-acetylprocainamide resulting in increased plasma levels of these drugs.
Although this interaction is unlikely to be clinically relevant at usual ranitidine doses, it may be prudent to monitor for procainamide toxicity when administered with oral ranitidine at a dose exceeding 300 mg per day. Warfarin: There have been reports of altered prothrombin time among patients on concomitant warfarin and ranitidine therapy. Due to the narrow therapeutic index, close monitoring of increased or decreased prothrombin time is recommended during concurrent treatment with ranitidine.
Ranitidine may alter the absorption of drugs in which gastric pH is an important determinant of bioavailability. This can result in either an increase in absorption (e.g., triazolam, midazolam, glipizide) or a decrease in absorption (e.g., ketoconazole, atazanavir, delavirdine, gefitinib). Appropriate clinical monitoring is recommended.
Atazanavir: Atazanavir absorption may be impaired based on known interactions with other agents that increase gastric pH. Use with caution. See atazanavir label for specific recommendations.
Delavirdine: Delavirdine absorption may be impaired based on known interactions with other agents that increase gastric pH. Chronic use of H2-receptor antagonists with delavirdine is not recommended. Gefitinib: Gefitinib exposure was reduced by 44% with the coadministration of ranitidine and sodium bicarbonate (dosed to maintain gastric pH above 5.0).
Use with caution. Glipizide: In diabetic patients, glipizide exposure was increased by 34% following a single 150-mg dose of oral ranitidine. Use appropriate clinical monitoring when initiating or discontinuing ranitidine.
Ketoconazole: Oral ketoconazole exposure was reduced by up to 95% when oral ranitidine was coadministered in a regimen to maintain a gastric pH of 6 or above. The degree of interaction with usual dose of ranitidine (150 mg twice daily) is unknown. Midazolam: Oral midazolam exposure in 5 healthy volunteers was increased by up to 65% when administered with oral ranitidine at a dose of 150 mg twice daily.
However, in another interaction study in 8 volunteers receiving IV midazolam, a 300 mg oral dose of ranitidine increased midazolam exposure by about 9%. Monitor patients for excessive or prolonged sedation when ranitidine is coadministered with oral midazolam. Triazolam: Triazolam exposure in healthy volunteers was increased by approximately 30% when administered with oral ranitidine at a dose of 150 mg twice daily.
Monitor patients for excessive or prolonged sedation.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects: Pregnancy Category B: Reproduction studies have been performed in rats and rabbits at doses up to 160 times the human dose and have revealed no evidence of impaired fertility or harm to the fetus due to ranitidine. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧓 Geriatric Use ▾
Geriatric Use Of the total number of subjects enrolled in US and foreign controlled clinical trials of oral formulations of ranitidine, for which there were subgroup analyses, 4,197 were 65 and over, while 899 were 75 and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in response between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
This drug is known to be substantially excreted by the kidney and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, caution should be exercised in dose selection, and it may be useful to monitor renal function (see CLINICAL PHARMACOLOGY : Pharmacokinetics : Geriatrics and DOSAGE AND ADMINISTRATION : Dosage Adjustments for Patients with impaired Renal Function ).
🆘 Overdosage ▾
OVERDOSAGE There has been limited experience with overdosage. Reported acute ingestions of up to 18 g orally have been associated with transient adverse effects similar to those encountered in normal clinical experience (see ADVERSE REACTIONS ). In addition, abnormalities of gait and hypotension have been reported.
When overdosage occurs, the usual measures to remove unabsorbed material from the gastrointestinal tract, clinical monitoring, and supportive therapy should be employed. Studies in dogs receiving dosages of ranitidine in excess of 225 mg/kg per day have shown muscular tremors, vomiting, and rapid respiration. Single oral doses of 1000 mg/kg in mice and rats were not lethal.
Intravenous LD 50 values in mice and rats were 77 and 83 mg/kg, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Ranitidine is a competitive, reversible inhibitor of the action of histamine at the histamine H 2 -receptors, including receptors on the gastric cells. Ranitidine does not lower serum Ca ++ in hypercalcemic states. Ranitidine is not an anticholinergic agent.
Pharmacokinetics Absorption: Ranitidine capsules are 50% absorbed after oral administration, compared to an intravenous (IV) injection with mean peak levels of 440 to 545 ng/mL occurring 2 to 3 hours after a 150 mg dose. Absorption is not significantly impaired by the administration of food or antacids. Propantheline slightly delays and increases peak blood levels of ranitidine, probably by delaying gastric emptying and transit time.
In one study, simultaneous administration of high-potency antacid (150 mmol) in fasting subjects has been reported to decrease the absorption of ranitidine. Distribution: The volume of distribution is about
1.4L/kg. Serum protein binding averages 15%. Metabolism: In humans, the N-oxide is the principal metabolite in the urine; however, this amounts to <4% of the dose.
Other metabolites are the S-oxide (1%) and the desmethyl ranitidine (1%). The remainder of the administered dose is found in the stool. Studies in patients with hepatic dysfunction (compensated cirrhosis) indicate that there are minor, but clinically insignificant, alterations in ranitidine half-life, distribution, clearance, and bioavailability.
Excretion: The principal route of excretion is the urine, with approximately 30% of the orally administered dose collected in the urine as unchanged drug in 24 hours. Renal clearance is about 410 mL/min, indicating active tubular excretion. The elimination half-life is 2.5 to 3 hours.
Four patients with clinically significant renal function impairment (creatinine clearance 25 to 35 mL/min) administered 50 mg of ranitidine intravenously had an average plasma half-life of 4.8 hours, a ranitidine clearance of 29 mL/min, and a volume of distribution of
1.76L/kg. In general, these parameters appear to be altered in proportion to creatinine clearance (see DOSAGE AND ADMINISTRATION ). Geriatrics The plasma half-life is prolonged and total clearance is reduced in the elderly population due to a decrease in renal function.
The elimination half-life is 3 to 4 hours. Peak levels average 526 ng/mL following a 150 mg twice daily dose and occur in about 3 hours (see PRECAUTIONS : Geriatric Use and DOSAGE AND ADMINISTRATION : Dosage Adjustment for Patients with Impaired Renal Function). Pediatrics There are no significant differences in the pharmacokinetic parameter values for ranitidine in pediatric patients (from 1 month up to 16 years of age) and healthy adults when correction is made for body weight.
The average bioavailability of ranitidine given orally to pediatric patients is 48% which is comparable to the bioavailability of ranitidine in the adult population. All other pharmacokinetic parameter values (t 1/2 , Vd, and CL) are similar to those observed with intravenous ranitidine use in pediatric patients. Estimates of C max and T max are displayed in Table 1.
Table 1. Ranitidine Pharmacokinetics in Pediatric Patients Following Oral Dosing Population(age) n Dosage Form (dose) C max (ng/mL) T max (hours) Gastric or duodenal ulcer (3.5 to 16 years) 12 Tablets (1 to 2 mg/kg) 54 to 492 2 Otherwise healthy requiring Ranitidine (0.7 to 14 years, Single dose) 10 Syrup (2mg/kg) 244
1.61Otherwise healthy requiring Ranitidine (0.7 to 14 years, Multiple dose) 10 Syrup (2 mg/kg) 320
1.66Plasma clearance measured in two neonatal patients (less than 1 month of age) was considerably lower (3 mL/min/kg) than children or adults and is likely due to reduced renal function observed in this population (see PRECAUTIONS : Pediatric Use and DOSAGE AND ADMINISTRATION : Pediatric Use ). Pharmacodynamics Serum concentrations necessary to inhibit 50% of stimulated gastric acid secretion are estimated to be 36 to 94 ng/mL. Following a single oral… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Ranitidine Hydrochloride Capsules 150 mg White to pale yellow powder filled in size '3', hard gelatin capsules with opaque light brown colored cap and opaque light brown colored body, imprinted 'CD' on cap and '129' on body, with black ink. The capsules are supplied in bottles of 60's and 500's. Bottles of 60 NDC 55111-129-60 Bottles of 500 NDC 55111-129-05 Ranitidine Hydrochloride Capsules 300 mg White to pale yellow powder filled in size '1', hard gelatin capsules with opaque light brown colored cap and opaque light brown colored body, imprinted 'CD' on cap and '130' on body, with black ink.
The capsules are supplied in bottles of 30's and 100's. Bottles of 30 NDC55111-130-30 Bottles of 100 NDC 55111-130-01 Store at 20°-25°C (68°-77°F) [see USP Controlled Room Temperature] in a dry place. Protect from light.
Dispense in a tight, light resistant container. Rx Only Manufactured by: Dr. Reddy’s Laboratories Limited Bachupally – 500 090 INDIA Revised: 0517
📋 Description ▾
DESCRIPTION Ranitidine hydrochloride (HCl) USP, is a histamine H 2 -receptor antagonist. Chemically it is N-[2-[[[5-[(dimethylamino)methyl]-2-furanyl]methyl]thio]ethyl]-N’-methyl-2-nitro-1,1-ethenediamine, HCl. It has the following structural formula: The molecular formula is C 13 H 22 N 4 O 3 S•HCl, representing a molecular weight of 350.87.
Ranitidine hydrochloride USP is a white to pale yellow, crystalline practically odorless powder, is sensitive to light and moisture. It is very soluble in water and sparingly soluble in alcohol. Each Ranitidine Hydrochloride capsule, for oral administration, contains 167.4 mg or 334.8 mg of ranitidine hydrochloride equivalent to 150 mg or 300 mg of ranitidine, respectively.
In addition, each capsule contains the following inactive ingredients: Microcrystalline Cellulose, Sodium Starch Glycolate, Magnesium Stearate. The capsule shells contain Black Iron Oxide, Red Iron Oxide T3469, Yellow Iron Oxide T3506, Titanium Dioxide and Gelatin. The capsule shells are imprinted with edible ink.
⚠️ Precautions ▾
PRECAUTIONS General Symptomatic response to therapy with ranitidine does not preclude the presence of gastric malignancy. Since ranitidine is excreted primarily by the kidney, dosage should be adjusted in patients with impaired renal function (see DOSAGE AND ADMINISTRATION ). Caution should be observed in patients with hepatic dysfunction since ranitidine is metabolized in the liver.
Rare reports suggest that ranitidine may precipitate acute porphyric attacks in patients with acute porphyria. Ranitidine should therefore be avoided in patients with a history of acute porphyria Laboratory Tests False-positive tests for urine protein with Multistix ® may occur during ranitidine therapy, and therefore testing with sulfosalicylic acid is recommended. Drug Interactions Ranitidine has been reported to affect the bioavailability of other drugs through several different mechanisms such as competition for renal tubular secretion, alteration of gastric pH, and inhibition of cytochrome P450 enzymes.
Procainamide: Ranitidine, a substrate of the renal organic cation transport system, may affect the clearance of other drugs eliminated by this route. High doses of ranitidine (e.g., such as those used in the treatment of Zollinger-Ellison syndrome) have been shown to reduce the renal excretion of procainamide and N-acetylprocainamide resulting in increased plasma levels of these drugs. Although this interaction is unlikely to be clinically relevant at usual ranitidine doses, it may be prudent to monitor for procainamide toxicity when administered with oral ranitidine at a dose exceeding 300 mg per day.
Warfarin: There have been reports of altered prothrombin time among patients on concomitant warfarin and ranitidine therapy. Due to the narrow therapeutic index, close monitoring of increased or decreased prothrombin time is recommended during concurrent treatment with ranitidine. Ranitidine may alter the absorption of drugs in which gastric pH is an important determinant of bioavailability.
This can result in either an increase in absorption (e.g., triazolam, midazolam, glipizide) or a decrease in absorption (e.g., ketoconazole, atazanavir, delavirdine, gefitinib). Appropriate clinical monitoring is recommended. Atazanavir: Atazanavir absorption may be impaired based on known interactions with other agents that increase gastric pH.
Use with caution. See atazanavir label for specific recommendations. Delavirdine: Delavirdine absorption may be impaired based on known interactions with other agents that increase gastric pH.
Chronic use of H2-receptor antagonists with delavirdine is not recommended. Gefitinib: Gefitinib exposure was reduced by 44% with the coadministration of ranitidine and sodium bicarbonate (dosed to maintain gastric pH above 5.0). Use with caution.
Glipizide: In diabetic patients, glipizide exposure was increased by 34% following a single 150-mg dose of oral ranitidine. Use appropriate clinical monitoring when initiating or discontinuing ranitidine. Ketoconazole: Oral ketoconazole exposure was reduced by up to 95% when oral ranitidine was coadministered in a regimen to maintain a gastric pH of 6 or above.
The degree of interaction with usual dose of ranitidine (150 mg twice daily) is unknown. Midazolam: Oral midazolam exposure in 5 healthy volunteers was increased by up to 65% when administered with oral ranitidine at a dose of 150 mg twice daily. However, in another interaction study in 8 volunteers receiving IV midazolam, a 300 mg oral dose of ranitidine increased midazolam exposure by about 9%.
Monitor patients for excessive or prolonged sedation when ranitidine is coadministered with oral midazolam. Triazolam: Triazolam exposure in healthy volunteers was increased by approximately 30% when administered with oral ranitidine at a dose of 150 mg twice daily. Monitor patients for excessive or prolonged sedation.
Carcinogenesis, Mutagenesis, Impairment of Fertility There was no indication of tumorigenic or carcinogenic effects in… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Ranitidine is secreted in human milk. Caution should be exercised when ranitidine is administered to a nursing mother.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility There was no indication of tumorigenic or carcinogenic effects in life-span studies in mice and rats at dosages up to 2,000 mg/kg per day. Ranitidine was not mutagenic in standard bacterial tests (Salmonella, Escherichia coli) for mutagenicity at concentrations up to the maximum recommended for these assays. In a dominant lethal assay, a single oral dose of 1,000 mg/kg to male rats was without effect on the outcome of two matings per week for the next 9 weeks.
📄 Package Label / Principal Display Panel ▾
Package Label. Principal Display Panel Unvarnished Area Consists of: 2D Barcode, Lot Number, Expiry Date and Serial Number 150 mg - 60's Container Label
300 mg - 30's Container Label
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |