
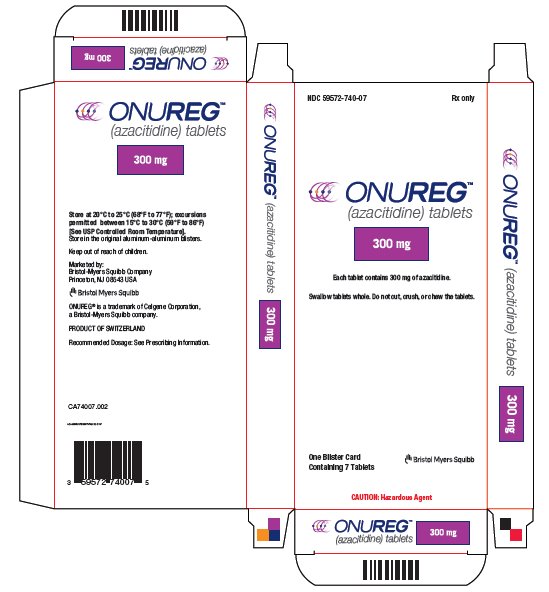
ONUREG azacitidine 300 mg Tablet, Film Coated, 7-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nucleoside Metabolic Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Azacitidine is used to treat acute myeloid leukemia (AML; cancer of the white blood cells) in adults who improved after chemotherapy, but who are unable to complete intensive curative therapy. Azacitidine is in a class of medications called demethylation agents. It works by helping the bone marrow to produce normal blood cells and by killing abnormal cells.
Read the full MedlinePlus article ↗- Yes, azacitidine is a type of cancer treatment, though it works a bit differently from traditional chemotherapy. Instead of just killing cancer cells outright, it also reprograms h...
- What exactly is azacitidine treating — is it chemotherapy?
- They contain the same active ingredient, but you absolutely cannot swap one for the other. Onureg tablets and the injectable forms are approved for completely different conditions,...
- Can I take the Onureg tablet instead of getting injections — they're the same drug, right?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Azacitidine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $1,854.23 | $12,979.63 / 7 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1,875.36 | $13,127.49 / 7 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Onureg 300 mgthis 59572-0740-07 | Celgene | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8846628 ↗ | Method of use | U-2950 | Jun 3, 2030 |
| US 8846628 ↗ | Method of use | U-2950 | Jun 3, 2030 |
| US 12053482 ↗ | Method of use | U-2950 | May 14, 2029 |
| US 12053482 ↗ | Method of use | U-2950 | May 14, 2029 |
| US 11571436 ↗ | Drug product | — | May 14, 2029 |
| US 11571436 ↗ | Drug product | — | May 14, 2029 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-320 | Orphan Drug Exclusivity (7-year) | Sep 1, 2027 |
| ODE-320 | Orphan Drug Exclusivity (7-year) | Sep 1, 2027 |
Is there a generic version of ONUREG 300 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59572-0740-07 You're viewing this | 7 TABLET, FILM COATED in 1 BLISTER PACK (59572-740-07) | 2020-12-18 | Active |
| 59572-0740-14 | 14 TABLET, FILM COATED in 1 BOTTLE (59572-740-14) | 2020-09-01 | Discontinued by firm |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 59572-0740-07?
What is the difference between NDC 59572-0740-07 and NDC 59572-0740-14?
What NDC number is used to bill for this package of ONUREG azacitidine 300 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ONUREG is indicated for continued treatment of adult patients with acute myeloid leukemia who achieved first complete remission (CR) or complete remission with incomplete blood count recovery (CRi) following intensive induction chemotherapy and are not able to complete intensive curative therapy. ONUREG is a nucleoside metabolic inhibitor indicated for continued treatment of adult patients with acute myeloid leukemia who achieved first complete remission (CR) or complete remission with incomplete blood count recovery (CRi) following intensive induction chemotherapy and are not able to complete intensive curative therapy ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Do not substitute ONUREG for intravenous or subcutaneous azacitidine. The indications and dosing regimen for ONUREG differ from that of intravenous or subcutaneous azacitidine ( 2.1 , 5.1 ). • Administer ONUREG 300 mg orally once daily on Days 1 through 14 of each 28-day cycle ( 2.2 ). • Administer an antiemetic before each dose for at least the first 2 cycles ( 2.2 ).
2.1Important Administration Information Do not substitute ONUREG for intravenous or subcutaneous azacitidine. The indications and dosing regimen for ONUREG differ from that of intravenous or subcutaneous azacitidine [see Warnings and Precautions (5.1) ].
2.2Recommended Dosage The recommended dosage of ONUREG is 300 mg orally once daily with or without food on Days 1 through 14 of each 28-day cycle. Continue ONUREG until disease progression or unacceptable toxicity. Administer an antiemetic 30 minutes prior to each dose of ONUREG for the first 2 cycles. Antiemetic prophylaxis may be omitted after 2 cycles if there has been no nausea and vomiting. If the absolute neutrophil count (ANC) is less than
0.5Gi/L on Day 1 of a cycle, do not administer ONUREG. Delay the start of the cycle until the ANC is
0.5Gi/L or more. Instruct patients on the following: • Swallow tablets whole. Do not cut, crush, or chew the tablets. • Take a dose about the same time each day. • If a dose of ONUREG is missed, or not taken at the usual time, take the dose as soon as possible on the same day, and resume the normal schedule the following day.
Do not take 2 doses on the same day. • If a dose is vomited, do not take another dose on the same day. Resume the normal schedule the following day. ONUREG is a hazardous drug.
Follow applicable special handling and disposal procedures. 1
2.3Monitoring and Dosage Modifications for Adverse Reactions Monitor complete blood count every other week for the first 2 cycles and prior to the start of each cycle thereafter. Increase monitoring to every other week for the 2 cycles after any dose reduction for myelosuppression. The recommended dosage modifications for adverse reactions are provided in Table 1.
Table 1: Recommended Dosage Modifications for Adverse Reactions Adverse Reaction Severity Recommended Dosage Modification Myelosuppression [see Warnings and Precautions (5.2) ] Neutrophils less than
0.5Gi/L on Cycle Day 1 • Interrupt treatment. Resume at the same dose once neutrophils return to
0.5Gi/L or higher. Neutrophils less than 1 Gi/L with fever at anytime First Occurrence • Interrupt treatment. Resume at the same dose once neutrophils return to 1 Gi/L or higher.
Occurrence in 2 Consecutive Cycles • Interrupt treatment. After neutrophils return to 1 Gi/L or higher, resume at reduced dose of 200 mg. • If a patient continues to experience febrile neutropenia after dose reduction, reduce the treatment duration by 7 days. • If febrile neutropenia reoccurs after dose and schedule reduction, discontinue ONUREG. Platelets less than 50 Gi/L with bleeding First Occurrence • Interrupt dose.
Resume at the same dose once platelets return to 50 Gi/L or higher. Occurrence in 2 Consecutive Cycles • Interrupt dose. After platelets return to 50 Gi/L or higher, resume at reduced dose of 200 mg. • If a patient continues to experience thrombocytopenia with bleeding after dose reduction, reduce the treatment duration by 7 days. • If thrombocytopenia with bleeding reoccurs after dose and schedule reduction, discontinue ONUREG.
Gastrointestinal Toxicity [see Adverse Reactions (6.1) ] Grade 3 or 4 Nausea or Vomiting • Interrupt dose. Resume at the same dose once toxicity has resolved to Grade 1 or lower. • If toxicity reoccurs, interrupt dose until resolved to Grade 1 or lower. Resume at reduced dose of 200 mg. • If a patient continues to experience the toxicity after dose reduction, reduce the treatment duration by 7 days. • If the toxicity continues or reoccurs after dose and schedule reduction, discontinue ONUREG.
Grade 3 or 4 Diarr…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: • 200 mg, pink, oval, film-coated tablet with debossed "200" on one side and "ONU" on the other side. • 300 mg, brown, oval, film-coated tablet with debossed "300" on one side and "ONU" on the other side. Tablets: 200 mg and 300 mg ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS ONUREG is contraindicated in patients with known severe hypersensitivity to azacitidine or its components [see Adverse Reactions (6.2) , Description (11) ] . History of severe hypersensitivity to azacitidine or its components ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Risks of Substitution with Other Azacitidine Products : Do not substitute ONUREG for intravenous or subcutaneous azacitidine ( 2.1 , 5.1 ). • Myelosuppression : Monitor complete blood counts every other week for the first 2 cycles and prior to the start of each cycle thereafter. Increase monitoring to every other week for the 2 cycles after any dose reduction. Withhold and then resume at same or reduced dose or discontinue ONUREG based on severity ( 2.3 , 5.2 ). • Embryo-Fetal Toxicity : Can cause fetal harm.
Advise patients of the potential risk to a fetus and use of effective contraception ( 5.4 , 8.1 , 8.3 ).
5.1Risks of Substitution with Other Azacitidine Products Due to substantial differences in the pharmacokinetic parameters [see Clinical Pharmacology (12.3) ] , the recommended dose and schedule for ONUREG are different from those for the intravenous or subcutaneous azacitidine products. Treatment of patients using intravenous or subcutaneous azacitidine at the recommended dosage of ONUREG may result in a fatal adverse reaction. Treatment of patients using ONUREG at the doses recommended for intravenous or subcutaneous azacitidine may not be effective.
Do not substitute ONUREG for intravenous or subcutaneous azacitidine [see Dosage and Administration (2.1) ] .
5.2Myelosuppression New or worsening Grade 3 or 4 neutropenia and thrombocytopenia occurred in 49% and 22% of patients who received ONUREG, respectively. Febrile neutropenia occurred in 12% , and sepsis was reported in 6%, including 1 fatal case . A dose reduction was required for 7% and 2% of patients due to neutropenia and thrombocytopenia, respectively.
Less than 1% of patients discontinued ONUREG due to either neutropenia or thrombocytopenia. Monitor complete blood counts and modify the dosage as recommended [see Dosage and Administration (2.2 , 2.3) ]. Provide standard supportive care, including hematopoietic growth factors, if myelosuppression occurs.
5.3Increased Early Mortality in Patients with Myelodysplastic Syndromes In AZA-MDS-003 (NCT01566695), 216 patients with red blood cell transfusion-dependent anemia and thrombocytopenia due to myelodysplastic syndromes were randomized to ONUREG or placebo. One-hundred and seven patients received a median of 5 cycles of ONUREG 300 mg daily for 21 days of a 28-day cycle. Enrollment was discontinued early due to a higher incidence of early fatal and/or serious adverse reactions in patients who received ONUREG compared with placebo.
The most frequent fatal adverse reaction was sepsis. The safety and effectiveness of ONUREG for treatment of myelodysplastic syndromes have not been established. Treatment of patients with myelodysplastic syndromes with ONUREG is not recommended outside of controlled trials.
5.4Embryo-Fetal Toxicity Based on the mechanism of action and findings in animals, ONUREG can cause fetal harm when administered to a pregnant woman. Azacitidine administered to pregnant rats via a single intraperitoneal dose less than the recommended human daily dose of oral azacitidine on a mg/m 2 basis caused fetal death and anomalies. Advise pregnant women of the potential risk to a fetus.
Advise females of reproductive potential to use effective contraception during treatment with ONUREG and for at least 6 months after the last dose. Advise males with female partners of reproductive potential to use effective contraception during treatment with ONUREG and for at least 3 months after the last dose [see Use in Specific Populations (8.1 , 8.3) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Myelosuppression [see Warnings and Precautions (5.2) ] The most common adverse reactions (≥ 10%) are nausea, vomiting, diarrhea, fatigue/asthenia, constipation, upper respiratory tract infection, pneumonia, abdominal pain, arthralgia, decreased appetite, febrile neutropenia, dizziness, skin infection, and pain in extremity. To report SUSPECTED ADVERSE REACTIONS, contact Bristol-Myers Squibb Company at 1-800-721-5072 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Acute Myeloid Leukemia The safety of ONUREG was evaluated in QUAZAR [see Clinical Studies (14) ] . Patients received ONUREG 300 mg (N=236) or placebo (N=233) orally once daily on Days 1 through 14 of each 28-day cycle.
Among patients who received ONUREG, 71% were exposed for 6 months or longer, and 49% were exposed for greater than one year. The median duration of exposure to ONUREG was 11.6 months (range: 0.5 to 74.3 months) and the median number of cycles was 12 (range: 1 to 82 cycles). Serious adverse reactions occurred in 15% of patients who received ONUREG.
Serious adverse reactions in ≥ 2% of patients who received ONUREG were pneumonia (8%) and febrile neutropenia (7%). One fatal adverse reaction (sepsis) occurred in a patient who received ONUREG. Permanent discontinuation of ONUREG due to an adverse reaction occurred in 8% of patients.
Adverse reactions which resulted in permanent discontinuation of ONUREG in > 1% of patients included nausea (2.1%), diarrhea (1.7%), and vomiting (1.3%). Interruptions of ONUREG due to an adverse reaction occurred in 35% of patients. Adverse reactions which required an interruption of ONUREG in > 5% of patients included neutropenia (20%), thrombocytopenia (8%), and nausea (6%).
Dose reductions of ONUREG due to an adverse reaction occurred in 14% of patients. Adverse reactions which required a dose reduction in > 1% of patients included neutropenia (6%), diarrhea (3.4%), thrombocytopenia (1.7%), and nausea (1.7%). The most common (≥ 10%) adverse reactions were nausea, vomiting, diarrhea, fatigue/asthenia, constipation, upper respiratory tract infection, pneumonia, abdominal pain, arthralgia, decreased appetite, febrile neutropenia, dizziness, skin infection, and pain in extremity.
Table 2 summarizes the adverse reactions in QUAZAR. Table 2: Adverse Reactions (≥ 5%) in Patients with AML Who Received ONUREG with a Difference Between Arms of > 2% Compared to Placebo in QUAZAR Adverse Reaction ONUREG (N=236) Placebo (N=233) All Grades (%) Grade 3 or 4 (%) All Grades (%) Grade 3 or 4 (%) a Grouped term includes abdominal pain, abdominal pain upper, abdominal discomfort, and gastrointestinal pain. b Grouped term includes fatigue and asthenia. c Broad scope term includes acute sinusitis, adenoviral upper respiratory infection, chronic tonsillitis, influenza, nasopharyngitis, pharyngitis, rhinitis, sinusitis, sinusitis fungal, tonsillitis, tracheitis, upper respiratory tract infection, upper respiratory tract infection bacterial, viral pharyngitis, viral rhinitis, viral upper respiratory tract infection. d Broad scope term includes influenza, pneumonia, respiratory tract infection, respiratory tract infection viral, bronchopulmonary aspergillosis, lung infection, Staphylococcal infection, atypical pneumonia, lower respiratory tract infection, lung abscess, Pneumocystis jirovecii pneumonia, pneumonia bacterial, pneumonia fungal, Pseudomonas infection, hemoptysis, productive cough, pleural effusion, atelectasis, pleuritic pain, rales, Enterobacter test positive, and Hemophilus test positive.
Gastrointestinal disorders Nausea 65 3 24…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Advise not to breastfeed ( 8.2 ).
8.1Pregnancy Risk Summary Based on its mechanism of action [see Clinical Pharmacology (12.1) ] and findings in animals, ONUREG can cause fetal harm when administered to a pregnant woman. There are no available data on ONUREG use in pregnant women to evaluate for a drug-associated risk. Azacitidine was teratogenic and caused embryo-fetal lethality in animals at doses less than the recommended human daily dose of oral azacitidine on a mg/m 2 basis (see Data ) .
Advise pregnant women of the potential risk to the fetus. The estimated background of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data No reproductive or developmental toxicity studies have been conducted with oral azacitidine. Early embryotoxicity studies in mice revealed a 44% frequency of intrauterine embryonal death (increased resorption) after a single intraperitoneal injection of 6 mg/m 2 azacitidine (at doses less than the recommended human daily dose of oral azacitidine on a mg/m 2 basis) on gestation Day 10.
Developmental abnormalities in the brain have been detected in mice given azacitidine on or before gestation Day 15 at doses of approximately 3 to 12 mg/m 2 (at doses less than the recommended human daily dose on a mg/m 2 basis). In rats, azacitidine was clearly embryotoxic when given an intraperitoneal injection on gestation Days 4 to 8 (postimplantation) at a dose of 6 mg/m 2 (at doses less than the recommended human daily dose on a mg/m 2 basis), although treatment in the preimplantation period (on gestation Days 1 to 3) had no adverse effect on the embryos.
Azacitidine caused multiple fetal abnormalities in rats after a single intraperitoneal dose of 3 to 12 mg/m 2 (at doses less than the recommended human daily dose on a mg/m 2 basis) given on gestation Days 9, 10, 11, or 12. In this study, azacitidine caused fetal death when administered at 3 to 12 mg/m 2 on gestation Days 9 and 10; average live animals per litter was reduced to 9% of control at the highest dose on gestation Day 9. Fetal anomalies included: CNS anomalies (exencephaly/encephalocele), limb anomalies (micromelia, club foot, syndactyly, oligodactyly), and others (micrognathia, gastroschisis, edema, and rib abnormalities).
8.2Lactation Risk Summary There are no data regarding the presence of azacitidine in human milk or the effects on the breastfed child or milk production. Because of the potential for serious adverse reactions in the breastfed child, advise women not to breastfeed during treatment with ONUREG and for 1 week after the last dose.
8.3Females and Males of Reproductive Potential ONUREG can cause embryo-fetal harm when administered to pregnant women [see Use in Specific Populations (8.1) ] . Pregnancy Testing Pregnancy testing is recommended for females of reproductive potential before starting ONUREG. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with ONUREG and for at least 6 months after the last dose.
Males Advise males with female partners of reproductive potential to use effective contraception during treatment with ONUREG and for at least 3 months after the last dose. Infertility Based on animal data, ONUREG may impair male or female fertility [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use The safety and effectiveness of ONUREG in pediatric patients have not been established.
8.5Geriatric Use Of the 238 patients in QUAZAR who received ONUREG, 72% were 65 years of age or older, while 12% were 75 years of age or older. No overall differences in safety or effectiveness of ONUREG were observed between these patients…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action [see Clinical Pharmacology (12.1) ] and findings in animals, ONUREG can cause fetal harm when administered to a pregnant woman. There are no available data on ONUREG use in pregnant women to evaluate for a drug-associated risk. Azacitidine was teratogenic and caused embryo-fetal lethality in animals at doses less than the recommended human daily dose of oral azacitidine on a mg/m 2 basis (see Data ) .
Advise pregnant women of the potential risk to the fetus. The estimated background of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data No reproductive or developmental toxicity studies have been conducted with oral azacitidine. Early embryotoxicity studies in mice revealed a 44% frequency of intrauterine embryonal death (increased resorption) after a single intraperitoneal injection of 6 mg/m 2 azacitidine (at doses less than the recommended human daily dose of oral azacitidine on a mg/m 2 basis) on gestation Day 10.
Developmental abnormalities in the brain have been detected in mice given azacitidine on or before gestation Day 15 at doses of approximately 3 to 12 mg/m 2 (at doses less than the recommended human daily dose on a mg/m 2 basis). In rats, azacitidine was clearly embryotoxic when given an intraperitoneal injection on gestation Days 4 to 8 (postimplantation) at a dose of 6 mg/m 2 (at doses less than the recommended human daily dose on a mg/m 2 basis), although treatment in the preimplantation period (on gestation Days 1 to 3) had no adverse effect on the embryos.
Azacitidine caused multiple fetal abnormalities in rats after a single intraperitoneal dose of 3 to 12 mg/m 2 (at doses less than the recommended human daily dose on a mg/m 2 basis) given on gestation Days 9, 10, 11, or 12. In this study, azacitidine caused fetal death when administered at 3 to 12 mg/m 2 on gestation Days 9 and 10; average live animals per litter was reduced to 9% of control at the highest dose on gestation Day 9. Fetal anomalies included: CNS anomalies (exencephaly/encephalocele), limb anomalies (micromelia, club foot, syndactyly, oligodactyly), and others (micrognathia, gastroschisis, edema, and rib abnormalities).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ONUREG in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 238 patients in QUAZAR who received ONUREG, 72% were 65 years of age or older, while 12% were 75 years of age or older. No overall differences in safety or effectiveness of ONUREG were observed between these patients and younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Azacitidine is a pyrimidine nucleoside analog of cytidine that inhibits DNA/RNA methyltransferases. Azacitidine is incorporated into DNA and RNA following cellular uptake and enzymatic biotransformation to nucleotide triphosphates. Incorporation of azacitidine into the DNA of cancer cells in vitro, including acute myeloid leukemia cells, inhibited DNA methyltransferases, reduced DNA methylation and altered gene expression, including re-expression of genes regulating tumor suppression and cell differentiation.
Incorporation of azacitidine into the RNA of cancer cells, including leukemic cells, inhibited RNA methyltransferases, reduced RNA methylation, decreased RNA stability and decreased protein synthesis. Antileukemic activity of azacitidine was demonstrated by reduction of cell viability and induction of apoptosis in AML cell lines in vitro. Azacitidine decreased tumor burden and increased survival in leukemic tumor models in vivo.
12.2Pharmacodynamics Greater reduction in global DNA methylation was observed with higher azacitidine plasma exposure in patients with AML administered ONUREG for 14 days of a 28-day cycle.
12.3Pharmacokinetics The systemic exposure of azacitidine is approximately dose proportional over the dose range of 120 mg to 600 mg once daily of ONUREG (0.4 to 2 times the recommended dosage). Following a single 300 mg dose of ONUREG, the mean (coefficient of variation [CV%]) C max of azacitidine was 145 ng/mL (64%) and the mean AUC of azacitidine was 242 ng h/mL (65%). No accumulation was observed following ONUREG 300 mg once daily.
Absorption The mean oral bioavailability is approximately 11% relative to subcutaneous administration. The median time to peak plasma concentration of azacitidine is 1 hour. Effect of Food A high-fat, high-calorie meal (approximately 800 to 1000 calories, 50% fat) did not affect AUC 0-INF and decreased C max by 21%.
Distribution The mean (CV%) apparent volume of distribution (V z /F) of azacitidine is 881 L (67%). The in vitro serum protein binding of azacitidine is approximately 6% to 12%. The blood-to-plasma ratio is approximately 0.3.
Elimination The mean (CV%) terminal half-life is approximately 0.5 hours (27%) and the apparent clearance (CL/F) is 1240 L/hour (64%). Metabolism Azacitidine undergoes spontaneous hydrolysis and deamination mediated by cytidine deaminase. Excretion Following the administration of ONUREG 300 mg orally once daily, < 2% of the dose was recovered unchanged in the urine.
Specific Populations Age (46 years to 93 years), sex, body weight (39.3 kg to 129 kg), mild to moderate hepatic impairment (total bilirubin ≤ ULN and AST > ULN, or total bilirubin 1 to 3 × ULN and any AST), and mild to moderate renal impairment (CLcr 30 to 89 mL/min) have no clinically meaningful effect on the pharmacokinetics of oral azacitidine. The effects of race/ethnicity, severe hepatic impairment (total bilirubin > 3 × ULN and any AST), and severe renal impairment (CLcr 15 to 29 mL/min) on the pharmacokinetics of oral azacitidine is unknown.
Severe renal impairment increased azacitidine exposure by approximately 70% after a single or 41% after multiple subcutaneous daily administration. Drug Interaction Studies Effect of Gastric Acid Reducing Agents on Azacitidine: Coadministration of omeprazole (a proton pump inhibitor) with ONUREG increased azacitidine AUC 0-INF by 19% and had no effect on C max . In Vitro Studies Cytochrome P450 (CYP) Enzymes: Azacitidine does not inhibit CYP1A2, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, CYP3A4, or CYP2E1 at clinically relevant concentrations.
Azacitidine is not an inducer of CYP1A2, CYP2C19, or CYP3A. Transporter Systems: Azacitidine is not a substrate of P-glycoprotein (P-gp). Azacitidine does not inhibit P-gp, breast cancer resistance protein (BCRP), organic anion transporters (OAT) OAT1 and OAT3, organic anion transporting polypeptides (OATP) OATP1B1 and OATP1B3, or organic cation transp…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Azacitidine is a pyrimidine nucleoside analog of cytidine that inhibits DNA/RNA methyltransferases. Azacitidine is incorporated into DNA and RNA following cellular uptake and enzymatic biotransformation to nucleotide triphosphates. Incorporation of azacitidine into the DNA of cancer cells in vitro, including acute myeloid leukemia cells, inhibited DNA methyltransferases, reduced DNA methylation and altered gene expression, including re-expression of genes regulating tumor suppression and cell differentiation.
Incorporation of azacitidine into the RNA of cancer cells, including leukemic cells, inhibited RNA methyltransferases, reduced RNA methylation, decreased RNA stability and decreased protein synthesis. Antileukemic activity of azacitidine was demonstrated by reduction of cell viability and induction of apoptosis in AML cell lines in vitro. Azacitidine decreased tumor burden and increased survival in leukemic tumor models in vivo.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied ONUREG tablets are available as: • 200 mg: pink, oval, film-coated tablets with debossed "200" on one side and "ONU" on the other side. • 300 mg: brown, oval, film-coated tablets with debossed "300" on one side and "ONU" on the other side. Table 6 lists the package configurations and strengths. Table 6: ONUREG Package Configurations and NDC Numbers Package Configuration Tablet Strength NDC Number One blister card containing 7 tablets 200 mg 59572-730-07 One blister card containing 7 tablets 300 mg 59572-740-07 Storage • Store blisters at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Store in the original aluminum-aluminum blisters. Handling and Disposal ONUREG is a hazardous drug. Follow applicable special handling and disposal procedures.
1 If powder comes in contact with skin, immediately and thoroughly wash with soap and water. If powder comes in contact with mucous membranes, immediately flush the area with water.
📦 Storage and Handling ▾
Storage • Store blisters at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Store in the original aluminum-aluminum blisters.
Handling and Disposal ONUREG is a hazardous drug. Follow applicable special handling and disposal procedures. 1 If powder comes in contact with skin, immediately and thoroughly wash with soap and water. If powder comes in contact with mucous membranes, immediately flush the area with water.
📋 Description ▾
11 DESCRIPTION Azacitidine is a nucleoside metabolic inhibitor with a molecular formula of C 8 H 12 N 4 O 5 and a molecular weight of 244 g/mol. The chemical name is: 4-amino-1-β-D-ribofuranosyl-s-triazin-2(1H)-one and the chemical structural is: Azacitidine is a white to off-white solid. Azacitidine was found to be soluble in aqueous media across a pH range from 1.0 to 7.0.
ONUREG (azacitidine) is supplied as film-coated tablets containing 200 mg or 300 mg of azacitidine for oral use. Each core tablet contains the following inactive ingredients: croscarmellose sodium, magnesium stearate, mannitol, and silicified microcrystalline cellulose. The 200 and 300 mg tablet coating contains hypromellose, lactose monohydrate, polyethylene glycol, titanium dioxide, and triacetin.
In addition, the 200 mg tablet coating contains iron oxide red and the 300 mg tablet coating contains black iron oxide, iron oxide red, and iron oxide yellow. onureg-chem-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myelosuppression Advise patients of the risk of myelosuppression with ONUREG and of the need to monitor complete blood counts before and during treatment [see Warnings and Precautions (5.2) ] . Infection Advise patients of the risk of infections, including sepsis, with ONUREG and to report any symptoms of infection to their healthcare provider as soon as possible [see Adverse Reactions (6.1) ] .
Gastrointestinal Toxicity Advise patients of the risk of gastrointestinal toxicity with ONUREG and of the potential need to use anti-emetic or anti-diarrheal medications during treatment [see Adverse Reactions (6.1) ]. Embryo-Fetal Toxicity Advise pregnant women of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.4) , Use in Specific Populations (8.1) ] .
Advise females of reproductive potential to use effective contraception during treatment with ONUREG and for at least 6 months after the last dose [see Use in Specific Populations (8.3) ] . Advise males with female partners of reproductive potential to use effective contraception during treatment with ONUREG and for at least 3 months after the last dose [see Use in Specific Populations (8.3) ] . Lactation Advise women not to breastfeed during treatment with ONUREG and for 1 week after the last dose [see Use in Specific Populations (8.2) ] .
Administration Advise patients to take ONUREG with or without food at about the same time each day and how to make up a missed or vomited dose. Advise patients to swallow tablets whole. Advise patients not to cut, crush, or chew the tablets [see Dosage and Administration (2.2) ] .
Storage Instructions Advise patients to keep ONUREG in the original container (blisters).