
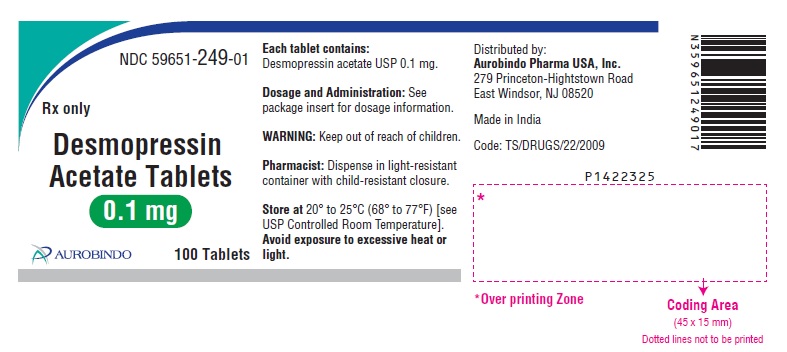
Desmopressin Acetate .1 mg Tablet, 100-count — NDC 59651-249-01 (Billing 59651-0249-01)
This is a package of 100 tablets of Desmopressin Acetate .1 mg Tablet from Aurobindo Pharma Limited, marketed since Mar 2024 and currently FDA-listed; retail pharmacies pay about $0.2429 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 019596
- GCN: 26171
- GPI-14 (Medi-Span): 30201010100310
- HICL (First Databank): 002841
- AHFS class code: 20:28.16.00
- RxCUI (RxNorm): 833008
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Vasopressin Analog class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Desmopressin is used to treat diabetes insipidus ('water diabetes'; condition in which the body produces an abnormally large amount of urine) excessive thirst and urination that may occur after a head injury or after pituitary (a small gland in the brain) surgery, and bedwetting Desmopressin is in a class of medications called hormones. It works by replacing vasopressin, a hormone that is normally produced in the body to help balance the amount of water and salt.
Read the full MedlinePlus article ↗- It depends on the product. It replaces the hormone that helps your body hold on to water in central diabetes insipidus. Some forms also treat hemophilia A and von Willebrand’s dise...
- Desmopressin makes your body hold on to water. Drinking too much can dilute the sodium in your blood, which can be dangerous. Ask your prescriber exactly how much fluid is right fo...
- Why do I need to limit how much I drink?
- Headache, nausea, stomach cramps, and flushing are possible. Nasal forms can cause a stuffy or runny nose or nosebleeds. Call right away for severe headache, confusion, vomiting, q...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Desmopressin Acetate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.243 | $24.29 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4148 | $41.48 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.6671 | $66.71 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59651-0249-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 2024-03-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Desmopressin Acetate .1 mg 23155-0489-01 | Heritage | 100 tablets | $0.243 | AB | Availability likely | — |
| Desmopressin Acetate .1 mgthis 59651-0249-01 | Aurobindo | 100 tablets | $0.243 | AB | Availability likely | — |
| Desmopressin Acetate .1 mg 60505-0257-01 | Apotex | 100 tablets | $0.243 | AB | Availability likely | — |
| Desmopressin Acetate .1 mg 60687-0721-21 | American | 30 tablets | $0.243 | AB | Availability likely | — |
| Desmopressin Acetate .1 mg 68001-0574-00 | BluePoint | 100 tablets | $0.243 | AB | Availability likely | — |
| Desmopressin Acetate .1 mg 69918-0101-01 | Nordic | 100 tablets | $0.243 | AB | Availability likely | — |
| Desmopressin Acetate .1 mg 10702-0169-01 | KVK-TECH, | 100 tablets | $0.373 | AB | FDA listed | +53% |
| Desmopressin Acetate .1 mg 68462-0275-01 | Glenmark | 100 tablets | $0.385 | — | FDA listed | +58% |
| Ddavp .1 mg 55566-2600-00 | Ferring | 100 tablets | $7.478 | AB | FDA listed | +2978% |
| Desmopressin Acetate .1 mg 70518-4612-00 | REMEDYREPACK | 50 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Central Diabetes Insipidus: Desmopressin acetate tablets are indicated as antidiuretic replacement therapy in the management of central diabetes insipidus and for the management of the temporary polyuria and polydipsia following head trauma or surgery in the pituitary region. Desmopressin acetate is ineffective for the treatment of nephrogenic diabetes insipidus. Patients were selected for therapy based on the diagnosis by means of the water deprivation test, the hypertonic saline infusion test, and/or response to antidiuretic hormone.
Continued response to desmopressin acetate can be monitored by measuring urine volume and osmolality. Primary Nocturnal Enuresis: Desmopressin acetate tablets are indicated for the management of primary nocturnal enuresis. Desmopressin acetate may be used alone or as an adjunct to behavioral conditioning or other non-pharmacologic intervention.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Central Diabetes Insipidus: The dosage of desmopressin acetate tablets must be determined for each individual patient and adjusted according to the diurnal pattern of response. Response should be estimated by two parameters: adequate duration of sleep and adequate, not excessive, water turnover. Patients previously on intranasal desmopressin acetate therapy should begin tablet therapy twelve hours after the last intranasal dose.
During the initial dose titration period, patients should be observed closely and appropriate safety parameters measured to assure adequate response. Patients should be monitored at regular intervals during the course of desmopressin acetate tablets therapy to assure adequate antidiuretic response. Modifications in dosage regimen should be implemented as necessary to assure adequate water turnover.
Fluid restriction should be observed. (See WARNINGS , PRECAUTIONS , Pediatric Use and Geriatric Use .) Adults and Children: It is recommended that patients be started on doses of 0.05 mg (1/2 of the 0.1 mg tablet) two times a day and individually adjusted to their optimum therapeutic dose. Most patients in clinical trials found that the optimal dosage range is 0.1 mg to 0.8 mg daily, administered in divided doses.
Each dose should be separately adjusted for an adequate diurnal rhythm of water turnover. Total daily dosage should be increased or decreased in the range of 0.1 mg to 1.2 mg divided into two or three daily doses as needed to obtain adequate antidiuresis. See Pediatric Use subsection for special considerations when administering desmopressin acetate to pediatric diabetes insipidus patients.
Geriatric Use: This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. (See CLINICAL PHARMACOLOGY , Human Pharmacokinetics , CONTRAINDICATIONS , and PRECAUTIONS , Geriatric Use .) Primary Nocturnal Enuresis: The dosage of desmopressin acetate tablets must be determined for each individual patient and adjusted according to response.
Patients previously on intranasal desmopressin acetate therapy can begin tablet therapy the night following (24 hours after) the last intranasal dose. The recommended initial dose for patients age 6 years and older is 0.2 mg at bedtime. The dose may be titrated up to 0.6 mg to achieve the desired response.
Fluid restriction should be observed, and fluid intake should be limited to a minimum from 1 hour before desmopressin administration, until the next morning, or at least 8 hours after administration. (See WARNINGS , PRECAUTIONS , Pediatric Use and Geriatric Use .)
⛔ Contraindications ▾
CONTRAINDICATIONS Desmopressin acetate tablets are contraindicated in individuals with known hypersensitivity to desmopressin acetate or to any of the components of desmopressin acetate tablets. Desmopressin acetate tablets are contraindicated in patients with moderate to severe renal impairment (defined as a creatinine clearance below 50 mL/min). Desmopressin acetate tablets are contraindicated in patients with hyponatremia or a history of hyponatremia.
⚠️ Warnings ▾
WARNINGS 1. Very rare cases of hyponatremia have been reported from world-wide postmarketing experience in patients treated with desmopressin acetate. Desmopressin acetate is a potent antidiuretic which, when administered, may lead to water intoxication and/or hyponatremia.
Unless properly diagnosed and treated hyponatremia can be fatal. Therefore, fluid restriction is recommended and should be discussed with the patient and/or guardian. Careful medical supervision is required.
2. When desmopressin acetate tablets are administered, in particular in pediatric and geriatric patients, fluid intake should be adjusted downward to decrease the potential occurrence of water intoxication and hyponatremia. (See PRECAUTIONS , Pediatric Use and Geriatric Use .) All patients receiving desmopressin acetate therapy should be observed for the following signs of symptoms associated with hyponatremia: headache, nausea/vomiting, decreased serum sodium, weight gain, restlessness, fatigue, lethargy, disorientation, depressed reflexes, loss of appetite, irritability, muscle weakness, muscle spasms or cramps and abnormal mental status such as hallucinations, decreased consciousness and confusion.
Severe symptoms may include one or a combination of the following: seizure, coma and/or respiratory arrest. Particular attention should be paid to the possibility of the rare occurrence of an extreme decrease in plasma osmolality that may result in seizures which could lead to coma. 3.
Desmopressin acetate should be used with caution in patients with habitual or psychogenic polydipsia who may be more likely to drink excessive amounts of water, putting them at greater risk of hyponatremia.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Infrequently, large doses of the intranasal formulations of Desmopressin Acetate Tablets and Desmopressin Acetate Injection have produced transient headache, nausea, flushing and mild abdominal cramps. These symptoms have disappeared with reduction in dosage. Central Diabetes Insipidus: In long-term clinical studies in which patients with diabetes insipidus were followed for periods up to 44 months of desmopressin acetate tablets therapy, transient increases in AST (SGOT) no higher than 1.5 times the upper limit of normal were occasionally observed.
Elevated AST (SGOT) returned to the normal range despite continued use of desmopressin acetate tablets. Primary Nocturnal Enuresis: The only adverse event occurring in ≥3% of patients in controlled clinical trials with desmopressin acetate tablets that was probably, possibly, or remotely related to study drug was headache (4% desmopressin acetate, 3% placebo). Other: The following adverse events have been reported; however their relationship to desmopressin acetate has not been established: abnormal thinking, diarrhea, and edema-weight gain.
See WARNINGS for the possibility of water intoxication and hyponatremia. Post Marketing: There have been rare reports of hyponatremic convulsions associated with concomitant use with the following medications: oxybutinin and imipramine.
🔄 Drug Interactions ▾
Drug Interactions: Although the pressor activity of desmopressin acetate is very low compared to its antidiuretic activity, large doses of desmopressin acetate tablets should be used with other pressor agents only with careful patient monitoring. The concomitant administration of drugs that may increase the risk of water intoxication with hyponatremia, (e.g. tricyclic antidepressants, selective serotonin re-uptake inhibitors, chlorpromazine, opiate analgesics, NSAIDs, lamotrigine and carbamazepine) should be performed with caution.
🤰 Pregnancy ▾
Pregnancy: Category B: Fertility studies have not been done. Teratology studies in rats and rabbits at doses from 0.05 to 10 mcg/kg/day (approximately 0.1 times the maximum systemic human exposure in rats and up to 38 times the maximum systemic human exposure in rabbits based on surface area, mg/m 2 ) revealed no harm to the fetus due to desmopressin acetate. There are, however, no adequate and well-controlled studies in pregnant women.
Because animal studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Several publications where desmopressin acetate was used in the management of diabetes insipidus during pregnancy are available; these include a few anecdotal reports of congenital anomalies and low birth weight babies. However, no causal connection between these events and desmopressin acetate has been established.
A fifteen year Swedish epidemiologic study of the use of desmopressin acetate in pregnant women with diabetes insipidus found the rate of birth defects to be no greater than that in the general population; however, the statistical power of this study is low. As opposed to preparations containing natural hormones, desmopressin acetate in antidiuretic doses has no uterotonic action and the physician will have to weigh the possible therapeutic advantages against the possible risks in each case.
🧒 Pediatric Use ▾
Pediatric Use: Central Diabetes Insipidus: Desmopressin acetate tablets have been used safely in pediatric patients, age 4 years and older, with diabetes insipidus for periods up to 44 months. In younger pediatric patients the dose must be individually adjusted in order to prevent an excessive decrease in plasma osmolality leading to hyponatremia and possible convulsions; dosing should start at 0.05 mg (1/2 of the 0.1 mg tablet). Use of desmopressin acetate tablets in pediatric patients requires careful fluid intake restrictions to prevent possible hyponatremia and water intoxication.
Fluid restriction should be discussed with the patient and/or guardian. (See WARNINGS .) Primary Nocturnal Enuresis: Desmopressin acetate tablets have been safely used in pediatric patients age 6 years and older with primary nocturnal enuresis for up to 6 months. Some patients respond to a dose of 0.2 mg; however, increasing responses are seen at doses of 0.4 mg and 0.6 mg.
No increase in the frequency or severity of adverse reactions or decrease in efficacy was seen with an increased dose or duration. The dose should be individually adjusted to achieve the best results. Treatment with desmopressin for primary nocturnal enuresis should be interrupted during acute intercurrent illness characterized by fluid and/or electrolyte imbalance (e.g., systemic infections, fever, recurrent vomiting or diarrhea) or under conditions of extremely hot weather, vigorous exercise or other conditions associated with increased water intake.
🧓 Geriatric Use ▾
Geriatric Use: Clinical studies of desmopressin acetate tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function. Desmopressin acetate is contraindicated in patients with moderate to severe renal impairment (defined as a creatinine clearance below 50 mL/min).
(See CLINICAL PHARMACOLOGY , Human Pharmacokinetics and CONTRAINDICATIONS .) Use of desmopressin acetate tablets in geriatric patients requires careful fluid intake restrictions to prevent possible hyponatremia and water intoxication. Fluid restriction should be discussed with the patient. (See WARNINGS .)
🆘 Overdosage ▾
OVERDOSAGE Signs of overdose may include confusion, drowsiness, continuing headache, problems with passing urine and rapid weight gain due to fluid retention. (See WARNINGS .) In case of overdose, the dose should be reduced, frequency of administration decreased, or the drug withdrawn according to the severity of the condition. There is no known specific antidote for desmopressin acetate.
The patient should be observed and treated with appropriate symptomatic therapy. An oral LD 50 has not been established. Oral doses up to 0.2 mg/kg/day have been administered to dogs and rats for 6 months without any significant drug-related toxicities reported.
An intravenous dose of 2 mg/kg in mice demonstrated no effect.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Desmopressin acetate tablets contain as active substance, desmopressin acetate, a synthetic analogue of the natural hormone arginine vasopressin. Central Diabetes Insipidus: Dose response studies in patients with diabetes insipidus have demonstrated that oral doses of 0.025 mg to 0.4 mg produced clinically significant antidiuretic effects. In most patients, doses of 0.1 mg to 0.2 mg produced optimal antidiuretic effects lasting up to eight hours.
With doses of 0.4 mg, antidiuretic effects were observed for up to 12 hours; measurements beyond 12 hours were not recorded. Increasing oral doses produced dose dependent increases in the plasma levels of desmopressin acetate. The plasma half-life of desmopressin acetate followed a monoexponential time course with t 1/2 values of 1.5 to 2.5 hours which was independent of dose.
The bioavailability of desmopressin acetate oral tablets are about 5% compared to intranasal desmopressin acetate, and about 0.16% compared to intravenous desmopressin acetate. The time to reach maximum plasma desmopressin acetate levels ranged from 0.9 to 1.5 hours following oral or intranasal administration, respectively. Following administration of desmopressin acetate tablets, the onset of antidiuretic effect occurs at around 1 hour, and it reaches a maximum at about 4 to 7 hours based on the measurement of increased urine osmolality.
The use of desmopressin acetate tablets in patients with an established diagnosis will result in a reduction in urinary output with an accompanying increase in urine osmolality. These effects usually will allow resumption of a more normal life style, with a decrease in urinary frequency and nocturia. There are reports of an occasional change in response to the intranasal formulations of desmopressin acetate (Desmopressin Acetate Nasal Spray and Desmopressin Acetate Rhinal Tube).
Usually, the change occurred over a period of time greater than six months. This change may be due to decreased responsiveness, or to shortened duration of effect. There is no evidence that this effect is due to the development of binding antibodies, but may be due to a local inactivation of the peptide.
No lessening of effect was observed in the 46 patients who were treated with desmopressin acetate tablets for 12 to 44 months and no serum antibodies to desmopressin were detected. The change in structure of arginine vasopressin to desmopressin acetate resulted in less vasopressor activity and decreased action on visceral smooth muscle relative to enhanced antidiuretic activity. Consequently, clinically effective antidiuretic doses are usually below the threshold for effects on vascular or visceral smooth muscle.
In the four long-term studies of desmopressin acetate tablets, no increases in blood pressure in 46 patients receiving desmopressin acetate tablets for periods of 12 to 44 months were reported. In one study, the pharmacodynamic characteristics of desmopressin acetate tablets and intranasal formulation were compared during an 8-hour dosing interval at steady state. The doses administered to 36 hydrated (water loaded) healthy male adult volunteers every 8 hours were 0.1, 0.2, 0.4 mg orally and 0.01 mg intranasally by rhinal tube.
The results are shown in the following table: Mean Changes from Baseline (SE) in Pharmacodynamic Parameters in Normal Healthy Adult Volunteers Treatment Total Urine Volume in mL Maximum Urine Osmolality in mOsm/kg 0.1 mg PO q8h -3689.3 (149.6) 514.8 (21.9) 0.2 mg PO q8h -4429.9 (149.6) 686.3 (21.9) 0.4 mg PO q8h -4998.8 (149.6) 769.3 (21.9) 0.01 mg IN q8h -4844.9 (149.6) 754.1 (21.9) (SE) = Standard error of the mean With respect to the mean values of total urine volume decrease and maximum urine osmolality increase from baseline, the 90% confidence limits estimated that the 0.4 mg and 0.2 mg oral dose produced between 95% and 110% and 84% to 99% of pharmacodynamic activity, respectively, when compared to the 0.01 mg intranasal dose.
While both the… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Desmopressin Acetate Tablets 0.1 mg are white to off-white, oval, biconvex tablets, debossed with S and 71 on either side of score line (functional) on one side and plain on the other side. Bottles of 100 NDC 59651-249-01 Desmopressin Acetate Tablets 0.2 mg are white to off-white, round, biconvex tablets, debossed with S and 72 on either side of score line (functional) on one side and plain on the other side. Bottles of 100 NDC 59651-250-01 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Avoid exposure to excessive heat or light. This product should be dispensed in a container with a child-resistant cap. Keep out of the reach of children.
Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Issued: May 2023
📋 Description ▾
DESCRIPTION Desmopressin acetate is a synthetic analogue of the natural pituitary hormone 8-arginine vasopressin (ADH), an antidiuretic hormone affecting renal water conservation. It is chemically defined as follows: Mol. Wt.
1183.34 Molecular Formula: C 46 H 64 N 14 O 12 S 2 • C 2 H 4 O 2 • 3H 2 O 1-(3-mercaptopropionic acid)-8-D-arginine vasopressin monoacetate (salt) trihydrate. Desmopressin acetate tablets contain either 0.1 or 0.2 mg desmopressin acetate USP. Inactive ingredients include: corn starch, lactose monohydrate, magnesium stearate and povidone.
Structure
⚠️ Precautions ▾
PRECAUTIONS General: Intranasal formulations of desmopressin acetate at high doses and Desmopressin Acetate Injection have infrequently produced a slight elevation of blood pressure which disappears with a reduction of dosage. Although this effect has not been observed when single oral doses up to 0.6 mg have been administered, the drug should be used with caution in patients with coronary artery insufficiency and/or hypertensive cardiovascular disease, because of a possible rise in blood pressure. Desmopressin acetate should be used with caution in patients with conditions associated with fluid and electrolyte imbalance, such as cystic fibrosis, heart failure and renal disorders because these patients are prone to hyponatremia.
Rare severe allergic reactions have been reported with desmopressin acetate. Anaphylaxis has been reported rarely with intravenous and intranasal administration of desmopressin acetate but not with desmopressin acetate tablets. Laboratory Tests: Central Diabetes Insipidus: Laboratory tests for monitoring the patient with central diabetes insipidus or post-surgical or head trauma-related polyuria and polydipsia include urine volume and osmolality.
In some cases, measurements of plasma osmolality may be useful. Drug Interactions: Although the pressor activity of desmopressin acetate is very low compared to its antidiuretic activity, large doses of desmopressin acetate tablets should be used with other pressor agents only with careful patient monitoring. The concomitant administration of drugs that may increase the risk of water intoxication with hyponatremia, (e.g. tricyclic antidepressants, selective serotonin re-uptake inhibitors, chlorpromazine, opiate analgesics, NSAIDs, lamotrigine and carbamazepine) should be performed with caution.
Carcinogenicity, Mutagenicity, Impairment of Fertility: Studies with desmopressin acetate have not been performed to evaluate carcinogenic potential, mutagenic potential or effects on fertility. Pregnancy: Category B: Fertility studies have not been done. Teratology studies in rats and rabbits at doses from 0.05 to 10 mcg/kg/day (approximately 0.1 times the maximum systemic human exposure in rats and up to 38 times the maximum systemic human exposure in rabbits based on surface area, mg/m 2 ) revealed no harm to the fetus due to desmopressin acetate.
There are, however, no adequate and well-controlled studies in pregnant women. Because animal studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Several publications where desmopressin acetate was used in the management of diabetes insipidus during pregnancy are available; these include a few anecdotal reports of congenital anomalies and low birth weight babies.
However, no causal connection between these events and desmopressin acetate has been established. A fifteen year Swedish epidemiologic study of the use of desmopressin acetate in pregnant women with diabetes insipidus found the rate of birth defects to be no greater than that in the general population; however, the statistical power of this study is low. As opposed to preparations containing natural hormones, desmopressin acetate in antidiuretic doses has no uterotonic action and the physician will have to weigh the possible therapeutic advantages against the possible risks in each case.
Nursing Mothers: There have been no controlled studies in nursing mothers. A single study in postpartum women demonstrated a marked change in plasma, but little if any change in assayable desmopressin acetate in breast milk following an intranasal dose of 0.01 mg. It is not known whether the drug is excreted in human milk.
Because many drugs are excreted in human milk, caution should be exercised when desmopressin acetate is administered to nursing mothers. Pediatric Use: Central Diabetes Insipidus: Desmopressin acetate tablets have been used safely in pediatric patients, age 4 years and older, with diabetes insipid… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers: There have been no controlled studies in nursing mothers. A single study in postpartum women demonstrated a marked change in plasma, but little if any change in assayable desmopressin acetate in breast milk following an intranasal dose of 0.01 mg. It is not known whether the drug is excreted in human milk.
Because many drugs are excreted in human milk, caution should be exercised when desmopressin acetate is administered to nursing mothers.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenicity, Mutagenicity, Impairment of Fertility: Studies with desmopressin acetate have not been performed to evaluate carcinogenic potential, mutagenic potential or effects on fertility.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.1 mg (100 Tablets Bottle) NDC 59651-249-01 Rx only Desmopressin Acetate Tablets 0.1 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.1 mg (100 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 0.2 mg (100 Tablets Bottle) NDC 59651-250-01 Rx only Desmopressin Acetate Tablets 0.2 mg AUROBINDO 100 Tablets fig2