
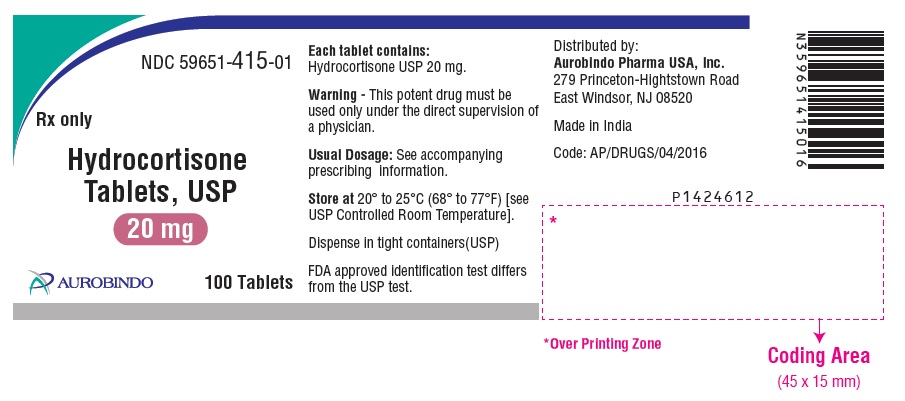
Hydrocortisone 20 mg Tablet, 100-count — NDC 59651-415-01 (Billing 59651-0415-01)
This is a package of 100 tablets of Hydrocortisone 20 mg Tablet from Aurobindo Pharma Limited, marketed since Jul 2023 and currently FDA-listed; retail pharmacies pay about $0.3006 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 006704
- GCN: 26782
- GPI-14 (Medi-Span): 22100025000310
- HICL (First Databank): 002867
- AHFS class code: 52:08.08.00
- RxCUI (RxNorm): 197782
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Tablets and oral granules are used for adrenal insufficiency, among other conditions. Injections are used for severe allergic states and skin diseases. R...
- Don't stop it suddenly if you take it for adrenal insufficiency. Stopping abruptly can cause adrenal crisis, which can be fatal. Talk to your prescriber before making any changes.
- Common ones are fluid retention, higher blood pressure, changes in blood sugar, mood changes, bigger appetite and weight gain. Call your doctor for signs of infection, vision chang...
- Grapefruit juice and some antifungals and antibiotics can raise hydrocortisone levels. Some seizure medicines and rifampicin can lower them. Tell me about any diabetes medicines, w...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Hydrocortisone — tap one for details:
Hydrocortisone may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.301 | $30.06 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4946 | $49.46 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.5873 | $58.73 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59651-0415-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 2023-07-17 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Hydrocortisone 20 mg 00115-1700-01 | Amneal | 100 tablets | $0.301 | AB | Availability likely | — |
| Hydrocortisone 20 mg 50268-0407-15 | AvPAK | 50 tablets | $0.301 | AB | Availability likely | — |
| Hydrocortisone 20 mgthis 59651-0415-01 | Aurobindo | 100 tablets | $0.301 | AB | Availability likely | — |
| Hydrocortisone 20 mg 59762-0075-01 | Mylan | 100 tablets | $0.301 | AB | Availability likely | — |
| Hydrocortisone 20 mg 62135-0186-60 | Chartwell | 60 tablets | $0.301 | — | Availability likely | — |
| Hydrocortisone 20 mg 64380-0972-06 | Strides | 100 tablets | $0.301 | AB | Availability likely | — |
| Hydrocortisone 20 mg 70954-0054-10 | ANI | 100 tablets | $0.301 | AB | Availability likely | — |
| hydrocortisone 20 mg 71930-0080-12 | Eywa | 100 tablets | $0.301 | AB | Availability likely | — |
| Cortef 20 mg 00009-0044-01 | Pharmacia | 100 tablets | — | AB | FDA listed | — |
| Hydrocortisone 20 mg 42543-0972-06 | Strides | 100 tablets | — | AB | FDA listed | — |
| Hydrocortisone 20 mg 71335-2044-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Hydrocortisone 20 mg 72162-2018-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Hydrocortisone 20 mg 72789-0229-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Hydrocortisone 20 mg 43547-0894-10 | Solco | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hydrocortisone tablets are indicated in the following conditions. 1. Endocrine Disorders Primary or secondary adrenocortical insufficiency (hydrocortisone or cortisone is the first choice; synthetic analogs may be used in conjunction with mineralocorticoids where applicable; in infancy mineralocorticoid supplementation is of particular importance) Congenital adrenal hyperplasia Non suppurative thyroiditis Hypercalcemia associated with cancer 2.
Rheumatic Disorders As adjunctive therapy for short-term administration (to tide the patient over an acute episode or exacerbation) in: Psoriatic arthritis Rheumatoid arthritis, including juvenile rheumatoid arthritis (selected cases may require low-dose maintenance therapy) Ankylosing spondylitis Acute and subacute bursitis Acute nonspecific tenosynovitis Acute gouty arthritis Post-traumatic osteoarthritis Synovitis of osteoarthritis Epicondylitis 3. Collagen Diseases During an exacerbation or as maintenance therapy in selected cases of: Systemic lupus erythematosus Systemic dermatomyositis (polymyositis) Acute rheumatic carditis 4.
Dermatologic Diseases Pemphigus Bullous dermatitis herpetiformis Severe erythema multiforme (Stevens-Johnson syndrome) Exfoliative dermatitis Mycosis fungoides Severe psoriasis Severe seborrheic dermatitis 5. Allergic States Control of severe or incapacitating allergic conditions intractable to adequate trials of conventional treatment: Seasonal or perennial allergic rhinitis Serum sickness Bronchial asthma Contact dermatitis Atopic dermatitis Drug hypersensitivity reactions 6. Ophthalmic Diseases Severe acute and chronic allergic and inflammatory processes involving the eye and its adnexa such as: Allergic conjunctivitis Keratitis Allergic corneal marginal ulcers Herpes zoster ophthalmicus Iritis and iridocyclitis Chorioretinitis Anterior segment inflammation Diffuse posterior uveitis and choroiditis Optic neuritis Sympathetic ophthalmia 7.
Respiratory Diseases Symptomatic sarcoidosis Loeffler’s syndrome not manageable by other means Berylliosis Fulminating or disseminated pulmonary tuberculosis when used concurrently with appropriate antituberculous chemotherapy Aspiration pneumonitis 8. Hematologic Disorders Idiopathic thrombocytopenic purpura in adults Secondary thrombocytopenia in adults Acquired (autoimmune) hemolytic anemia Erythroblastopenia (RBC anemia) Congenital (erythroid) hypoplastic anemia 9. Neoplastic Diseases For palliative management of: Leukemias and lymphomas in adults Acute leukemia of childhood 10.
Edematous States To induce a diuresis or remission of proteinuria in the nephrotic syndrome, without uremia, of the idiopathic type or that due to lupus erythematosus. 11. Gastrointestinal Diseases To tide the patient over a critical period of the disease in: Ulcerative colitis Regional enteritis 12.
Miscellaneous Tuberculous meningitis with subarachnoid block or impending block when used concurrently with appropriate antituberculous chemotherapy Trichinosis with neurologic or myocardial involvement
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The initial dosage of hydrocortisone tablets may vary from 20 mg to 240 mg of hydrocortisone per day depending on the specific disease entity being treated. In situations of less severity lower doses will generally suffice while in selected patients higher initial doses may be required. The initial dosage should be maintained or adjusted until a satisfactory response is noted.
If after a reasonable period of time there is a lack of satisfactory clinical response, hydrocortisone tablets should be discontinued and the patient transferred to other appropriate therapy. IT SHOULD BE EMPHASIZED THAT DOSAGE REQUIREMENTS ARE VARIABLE AND MUST BE INDIVIDUALIZED ON THE BASIS OF THE DISEASE UNDER TREATMENT AND THE RESPONSE OF THE PATIENT. After a favorable response is noted, the proper maintenance dosage should be determined by decreasing the initial drug dosage in small decrements at appropriate time intervals until the lowest dosage which will maintain an adequate clinical response is reached.
It should be kept in mind that constant monitoring is needed in regard to drug dosage. Included in the situations which may make dosage adjustments necessary are changes in clinical status secondary to remissions or exacerbations in the disease process, the patient’s individual drug responsiveness, and the effect of patient exposure to stressful situations not directly related to the disease entity under treatment; in this latter situation it may be necessary to increase the dosage of hydrocortisone tablets for a period of time consistent with the patient’s condition.
If after long-term therapy the drug is to be stopped, it is recommended that it be withdrawn gradually, rather than abruptly.
⛔ Contraindications ▾
CONTRAINDICATIONS Systemic fungal infections and known hypersensitivity to components
⚠️ Warnings ▾
WARNINGS In patients on corticosteroid therapy subjected to unusual stress, increased dosage of rapidly acting corticosteroids before, during, and after the stressful situation is indicated. Immunosuppression and Increased Risk of Infection Corticosteroids, including hydrocortisone, suppress the immune system and increase the risk of infection with any pathogen, including viral, bacterial, fungal, protozoan, or helminthic pathogens. Corticosteroids can: Reduce resistance to new infections Exacerbate existing infections Increase the risk of disseminated infections Increase the risk of reactivation or exacerbation of latent infections Mask some signs of infection Corticosteroid-associated infections can be mild but can be severe and at times fatal.
The rate of infectious complications increases with increasing corticosteroid dosages. Monitor for the development of infection and consider hydrocortisone withdrawal or dosage reduction as needed. Tuberculosis If hydrocortisone is used to treat a condition in patients with latent tuberculosis or tuberculin reactivity, reactivation of tuberculosis may occur.
Closely monitor such patients for reactivation. During prolonged hydrocortisone therapy, patients with latent tuberculosis or tuberculin reactivity should receive chemoprophylaxis. Varicella Zoster and Measles Viral Infections Varicella and measles can have a serious or even fatal course in non-immune patients taking corticosteroids, including hydrocortisone.
In corticosteroid-treated patients who have not had these diseases or are non-immune, particular care should be taken to avoid exposure to varicella and measles: If a hydrocortisone-treated patient is exposed to varicella, prophylaxis with varicella zoster immune globulin may be indicated. If varicella develops, treatment with antiviral agents may be considered. If a hydrocortisone-treated patient is exposed to measles, prophylaxis with immunoglobulin may be indicated.
Hepatitis B Virus Reactivation Hepatitis B virus reactivation can occur in patients who are hepatitis B carriers treated with immunosuppressive dosages of corticosteroids, including hydrocortisone. Reactivation can also occur infrequently in corticosteroid-treated patients who appear to have resolved hepatitis B infection. Screen patients for hepatitis B infection before initiating immunosuppressive (e.g., prolonged) treatment with hydrocortisone.
For patients who show evidence of hepatitis B infection, recommend consultation with physicians with expertise in managing hepatitis B regarding monitoring and consideration for hepatitis B antiviral therapy. Fungal Infections Corticosteroids, including hydrocortisone, may exacerbate systemic fungal infections; therefore, avoid hydrocortisone use in the presence of such infections unless hydrocortisone is needed to control drug reactions. For patients on chronic hydrocortisone therapy who develop systemic fungal infections, hydrocortisone withdrawal or dosage reduction is recommended.
Amebiasis Corticosteroids, including hydrocortisone, may activate latent amebiasis. Therefore, it is recommended that latent amebiasis or active amebiasis be ruled out before initiating hydrocortisone in patients who have spent time in the tropics or patients with unexplained diarrhea. Strongyloides Infestation Corticosteroids, including hydrocortisone, should be used with great care in patients with known or suspected Strongyloides (threadworm) infestation.
In such patients, corticosteroid-induced immunosuppression may lead to Strongyloides hyperinfection and dissemination with widespread larval migration, often accompanied by severe enterocolitis and potentially fatal gram-negative septicemia. Cerebral Malaria Avoid corticosteroids, including hydrocortisone, in patients with cerebral malaria. Ophthalmic Effects Prolonged use of corticosteroids may produce posterior subcapsular cataracts, glaucoma with possible damage to the optic nerves, and may enhance the establishment of secondary o… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Fluid and Electrolyte Disturbances Sodium retention Fluid retention Congestive heart failure in susceptible patients Potassium loss Hypokalemic alkalosis Hypertension Musculoskeletal Muscle weakness Steroid myopathy Loss of muscle mass Osteoporosis Tendon rupture, particularly of the Achilles tendon Vertebral compression fractures Aseptic necrosis of femoral and humeral heads Pathologic fracture of long bones Gastrointestinal Peptic ulcer with possible perforation and hemorrhage Pancreatitis Abdominal distention Ulcerative esophagitis Increases in alanine transaminase (ALT, SGPT), aspartate transaminase (AST, SGOT) and alkaline phosphatase have been observed following corticosteroid treatment.
These changes are usually small, not associated with any clinical syndrome and are reversible upon discontinuation. Dermatologic Impaired wound healing Thin fragile skin Petechiae and ecchymoses Facial erythema Increased sweating May suppress reactions to skin tests Neurological Increased intracranial pressure with papilledema (pseudotumor cerebri) usually after treatment Convulsions Vertigo Headache Epidural lipomatosis Endocrine Development of Cushingoid state Suppression of growth in children Secondary adrenocortical and pituitary unresponsiveness, particularly in times of stress, as in trauma, surgery or illness Menstrual irregularities Decreased carbohydrate tolerance Manifestations of latent diabetes mellitus Increased requirements for insulin or oral hypoglycemic agents in diabetics Ophthalmic Central serous chorioretinopathy Posterior subcapsular cataracts Increased intraocular pressure Glaucoma Exophthalmos Metabolic Negative nitrogen balance due to protein catabolism Blood and lymphatic system disorders Leukocytosis
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Hydrocortisone Tablets USP are available in the following strengths and package sizes: Hydrocortisone Tablets USP, 5 mg are white to off-white, round shaped tablets, with score line on one side and debossed with ‘HC5’ on other side. Bottles of 50 NDC 59651-413-50 Hydrocortisone Tablets USP, 10 mg are white to off-white, round shaped tablets, with score line on one side and debossed with ‘HC10’ on other side. Bottles of 100 NDC 59651-414-01 Hydrocortisone Tablets USP, 20 mg are white to off-white, round shaped tablets, with score line on one side and debossed with ‘HC20’ on other side.
Bottles of 100 NDC 59651-415-01 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
DESCRIPTION Hydrocortisone Tablets USP contain hydrocortisone which is a glucocorticoid. Glucocorticoids are adrenocortical steroids, both naturally occurring and synthetic, which are readily absorbed from the gastrointestinal tract. Hydrocortisone USP is white to practically white, odorless, crystalline powder with a melting point of about 215°C.
It is sparingly soluble in acetone and in alcohol; slightly soluble in chloroform; practically insoluble in water and in ether. The chemical name for hydrocortisone is pregn-4-ene-3,20-dione,11,17,21-trihydroxy-, (11β)-. Its molecular weight is 362.46 and the structural formula is as outlined below.
Hydrocortisone tablets USP are available for oral administration in three strengths: each tablet contains either 5 mg, 10 mg, or 20 mg of hydrocortisone USP. Inactive ingredients: colloidal silicon dioxide, copovidone, lactose monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch (maize) and sodium starch glycolate. FDA approved identification test differs from the USP test.
ACTIONS Naturally occurring glucocorticoids (hydrocortisone and cortisone), which also have salt-retaining properties, are used as replacement therapy in adrenocortical deficiency states. Their synthetic analogs are primarily used for their potent anti-inflammatory effects in disorders of many organ systems. Glucocorticoids cause profound and varied metabolic effects.
In addition, they modify the body’s immune responses to diverse stimuli. str
💬 Information for Patients ▾
Drug Interactions The pharmacokinetic interactions listed below are potentially clinically important. Drugs that induce hepatic enzymes such as phenobarbital, phenytoin and rifampin may increase the clearance of corticosteroids and may require increases in corticosteroid dose to achieve the desired response. Drugs such as troleandomycin and ketoconazole may inhibit the metabolism of corticosteroids and thus decrease their clearance.
Therefore, the dose of corticosteroid should be titrated to avoid steroid toxicity. Corticosteroids may increase the clearance of chronic high dose aspirin. This could lead to decreased salicylate serum levels or increase the risk of salicylate toxicity when corticosteroid is withdrawn.
Aspirin should be used cautiously in conjunction with corticosteroids in patients suffering from hypoprothrombinemia. The effect of corticosteroids on oral anticoagulants is variable. There are reports of enhanced as well as diminished effects of anticoagulants when given concurrently with corticosteroids.
Therefore, coagulation indices should be monitored to maintain the desired anticoagulant effect.
⚠️ Precautions ▾
PRECAUTIONS General Precautions Drug-induced secondary adrenocortical insufficiency may be minimized by gradual reduction of dosage. This type of relative insufficiency may persist for months after discontinuation of therapy; therefore, in any situation of stress occurring during that period, hormone therapy should be reinstituted. There is an enhanced effect of corticosteroids on patients with hypothyroidism and in those with cirrhosis.
Corticosteroids should be used cautiously in patients with ocular herpes simplex because of possible corneal perforation. The lowest possible dose of corticosteroid should be used to control the condition under treatment, and when reduction in dosage is possible, the reduction should be gradual. Psychic derangements may appear when corticosteroids are used, ranging from euphoria, insomnia, mood swings, personality changes, and severe depression, to frank psychotic manifestations.
Also, existing emotional instability or psychotic tendencies may be aggravated by corticosteroids. Steroids should be used with caution in nonspecific ulcerative colitis, if there is a probability of impending perforation, abscess or other pyogenic infection; diverticulitis; fresh intestinal anastomoses; active or latent peptic ulcer; renal insufficiency; hypertension; osteoporosis; and myasthenia gravis. Growth and development of infants and children on prolonged corticosteroid therapy should be carefully observed.
Since complications of treatment with glucocorticoids are dependent on the size of the dose and the duration of treatment, a risk/benefit decision must be made in each individual case as to dose and duration of treatment and as to whether daily or intermittent therapy should be used. Pheochromocytoma crisis, which can be fatal, has been reported after administration of systemic corticosteroids. In patients with suspected pheochromocytoma, consider the risk of pheochromocytoma crisis prior to administering corticosteroids.
In post marketing experience tumor lysis syndrome (TLS) has been reported in patients with malignancies, including hematological malignancies and solid tumors, following the use of systemic corticosteroids alone or in combination with other chemotherapeutic agents. Patients at high risk of TLS, such as patients with tumors that have a high proliferative rate, high tumor burden and high sensitivity to cytotoxic agents, should be monitored closely and appropriate precautions should be taken. Drug Interactions The pharmacokinetic interactions listed below are potentially clinically important.
Drugs that induce hepatic enzymes such as phenobarbital, phenytoin and rifampin may increase the clearance of corticosteroids and may require increases in corticosteroid dose to achieve the desired response. Drugs such as troleandomycin and ketoconazole may inhibit the metabolism of corticosteroids and thus decrease their clearance. Therefore, the dose of corticosteroid should be titrated to avoid steroid toxicity.
Corticosteroids may increase the clearance of chronic high dose aspirin. This could lead to decreased salicylate serum levels or increase the risk of salicylate toxicity when corticosteroid is withdrawn. Aspirin should be used cautiously in conjunction with corticosteroids in patients suffering from hypoprothrombinemia.
The effect of corticosteroids on oral anticoagulants is variable. There are reports of enhanced as well as diminished effects of anticoagulants when given concurrently with corticosteroids. Therefore, coagulation indices should be monitored to maintain the desired anticoagulant effect.
Information for the Patient Persons who are on immunosuppressant doses of corticosteroids should be warned to avoid exposure to chicken pox or measles. Patients should also be advised that if they are exposed, medical advice should be sought without delay.
📚 References ▾
REFERENCES 1 Fekety R. Infections associated with corticosteroids and immunosuppressive therapy. In: Gorbach SL, Bartlett JG, Blacklow NR, eds.
Infectious Diseases. Philadelphia: WB Saunders Company 1992:1050-1. 2 Stuck AE, Minder CE, Frey FJ.
Risk of infectious complications in patients taking glucocorticoids. Rev Infect Dis 1989:11(6):954-63. Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 06/2024
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 5 mg (50 Tablets Bottle) NDC 59651-413-50 Rx only Hydrocortisone Tablets, USP 5 mg AUROBINDO 50 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 5 mg (50 Tablet Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg (100 Tablets Bottle) NDC 59651-414-01 Rx only Hydrocortisone Tablets, USP 10 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg (100 Tablet Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 20 mg (100 Tablets Bottle) NDC 59651-415-01 Rx only Hydrocortisone Tablets, USP 20 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 20 mg (100 Tablet Bottle)