
DICLOXACILLIN SODIUM 500 mg Capsule, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Penicillin-class Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Dicloxacillin is used to treat infections caused by certain types of bacteria. Dicloxacillin is in a class of medications called penicillins. It works by killing bacteria. Antibiotics such as dicloxacillin will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Dicloxacillin is used specifically for staph (staphylococcal) infections caused by bacteria that have developed resistance to regular penicillin. These resistant staph bacteria pro...
- What kind of infections does dicloxacillin actually treat?
- Yes, it does matter. Food slows down how quickly your body absorbs dicloxacillin, which means the medicine may not work as well. Try to take it on an empty stomach — about 30 to 60...
- Please don't stop early, even if you feel much better. With staph infections, stopping too soon can leave behind bacteria that come back stronger or harder to treat. For severe inf...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Dicloxacillin Sodium — tap one for details:
Dicloxacillin Sodium may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.927 | $92.74 / 100 capsules |
| Medicaid paysCMS SDUD · 12 mo | $1.08 | $107.86 / 100 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.6362 | $63.62 / 100 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dicloxacillin Sodium 500 mg 00093-3125-01 | Teva | 100 capsules | $0.927 | AB | Availability likely | — |
| Dicloxacillin Sodium 500 mgthis 59651-0566-01 | Aurobindo | 100 capsules | $0.927 | AB | Availability likely | — |
| Dicloxacillin Sodium 500 mg 43063-0473-20 | PD-Rx | 20 capsules | — | AB | FDA listed | — |
| Dicloxacillin Sodium 500 mg 63629-4256-01 | Bryant | 20 capsules | — | AB | FDA listed | — |
| Dicloxacillin Sodium 500 mg 76420-0183-20 | Asclemed | 20 capsules | — | AB | FDA listed | — |
| Dicloxacillin Sodium 500 mg 62135-0097-01 | Chartwell | 100 capsules | — | AB | FDA listed | — |
| Dicloxacillin Sodium 500 mg 67296-2307-04 | Redpharm | 40 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59651-0566-01 You're viewing this | 100 CAPSULE in 1 BOTTLE (59651-566-01) | 2022-09-23 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE To reduce the development of drug-resistant bacteria and maintain the effectiveness of dicloxacillin sodium capsules and other antibacterial drugs, dicloxacillin sodium capsules should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Dicloxacillin sodium capsules are indicated in the treatment of infections caused by penicillinase-producing staphylococci which have demonstrated susceptibility to the drug. Cultures and susceptibility tests should be performed initially to determine the causative organisms and their sensitivity to the drug (see CLINICAL PHARMACOLOGY – Susceptibility Testing ) . Dicloxacillin sodium capsules may be used to initiate therapy in suspected cases of resistant staphylococcal infections prior to the availability of laboratory test results.
The penicillinase-resistant penicillins should not be used in infections caused by organisms susceptible to penicillin G. If the susceptibility tests indicate that the infection is due to an organism other than a resistant staphylococcus, therapy should not be continued with a penicillinase-resistant penicillin.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Concurrent administration of the penicillinase-resistant penicillins and probenecid increases and prolongs serum penicillin levels. Probenecid decreases the apparent volume of distribution and slows the rate of excretion by competitively inhibiting renal tubular secretion of penicillin. Penicillin-probenecid therapy is generally limited to those infections where very high serum levels of penicillin are necessary.
Oral preparations of the penicillinase-resistant penicillins should not be used as initial therapy in serious, life-threatening infections (see PRECAUTIONS - General ). Oral therapy with the penicillinase-resistant penicillins may be used to follow up the previous use of a parenteral agent as soon as the clinical condition warrants. RECOMMENDED DOSAGES FOR DICLOXACILLIN SODIUM IN MILD TO MODERATE AND SEVERE INFECTIONS 1.
Patients weighing less than 40 kg (88 lbs) DRUG ADULTS CHILDREN Mild to Moderate Severe Mild to Moderate Severe Dicloxacillin 125 mg every 6 hours 250 mg every 6 hours 12.5 mg/kg/day 1 in equally divided doses every 6 hours 25 mg/kg/day 1 in equally divided doses every 6 hours Dicloxacillin is best absorbed when taken on an empty stomach, and should be administered at least 1 hour before or 2 hours after meals. Dicloxacillin sodium capsules should be taken with at least 4 fluid ounces (120 mL) of water and should not be taken in the supine position or immediately before going to bed (see PRECAUTIONS ).
⛔ Contraindications ▾
CONTRAINDICATIONS Dicloxacillin sodium capsules are contraindicated in persons who have shown hypersensitivity to any of the penicillins or any component of the formulations.
⚠️ Warnings ▾
WARNINGS Serious and occasionally fatal hypersensitivity (anaphylactic shock with collapse) reactions have occurred in patients receiving penicillin. The incidence of anaphylactic shock in all penicillin-treated patients is between 0.015% and 0.04%. Anaphylactic shock resulting in death has occurred in approximately 0.002% of the patients treated.
Although anaphylaxis is more frequent following a parenteral administration, it has occurred in patients receiving oral penicillins. When penicillin therapy is indicated, it should be initiated only after a comprehensive patient drug and allergy history has been obtained. If an allergic reaction occurs, dicloxacillin should be discontinued and appropriate therapy instituted.
Individuals with a history of penicillin hypersensitivity may also experience allergic reactions when treated with a cephalosporin. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including dicloxacillin sodium, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Hypersensitive Reactions The reported incidence of allergic reactions to penicillin ranges from 0.7% to 10% (see WARNINGS ). Sensitization is usually the result of treatment, but some individuals have had immediate reactions to penicillin when first treated. In such cases, it is thought that the patients may have had prior exposure to the drug via trace amounts present in milk and vaccines.
Two types of allergic reactions to penicillin are noted clinically, immediate and delayed. Immediate reactions usually occur within 20 minutes of administration and range in severity from urticaria and pruritus to angioneurotic edema, laryngospasm, bronchospasm, hypotension, vascular collapse and death. Such immediate anaphylactic reactions are very rare (see WARNINGS ) and usually occur after parenteral therapy, but have occurred in patients receiving oral therapy.
Another type of immediate reaction, an accelerated reaction, may occur between 20 minutes and 48 hours after administration and may include urticaria, pruritus and fever. Although laryngeal edema, laryngospasm and hypotension occasionally occur, fatality is uncommon. Delayed allergic reactions to penicillin therapy usually occur after 48 hours and sometimes as late as two to four weeks after initiation of therapy.
Manifestations of this type of reaction include serum sicknesslike symptoms (i.e., fever, malaise, urticaria, myalgia, arthralgia, abdominal pain) and various skin rashes. Gastrointestinal Reactions Nausea, vomiting, diarrhea, stomatitis, black or hairy tongue and other symptoms of gastrointestinal irritation may occur, especially during oral penicillin therapy. Pseudomembranous colitis has been reported with the use of dicloxacillin.
Therefore, it is important to consider its diagnosis in patients who develop diarrhea in association with dicloxacillin use. Reports have been received during postmarketing surveillance of esophageal burning, esophagitis, and esophageal ulceration, particularly after ingestion of dicloxacillin capsules with an insufficient quantity of water and/or before going to bed (see PRECAUTIONS and DOSAGE AND ADMINISTRATION ). Nervous System Reactions Neurotoxic reactions similar to those observed with penicillin G (e.g., lethargy, confusion, twitching, multifocal myoclonus, localized or generalized epileptiform seizures) may occur with large intravenous doses of the penicillinase-resistant penicillins, especially with patients with renal insufficiency.
Renal Reactions Renal tubular damage and interstitial nephritis have been associated with the administration of methicillin sodium and, infrequently, with the administration of nafcillin and oxacillin. Manifestations of this reaction may include rash, fever, eosinophilia, hematuria, proteinuria and renal insufficiency. Methicillininduced nephropathy does not appear to be dose-related and is generally reversible upon prompt discontinuation of therapy.
Hematologic Reactions Eosinophilia, hemolytic anemia, agranulocytosis, neutropenia, leukopenia, granulocytopenia, thrombocytopenia, and bone marrow depression have been associated with the use of penicillinaseresistant penicillins. Hepatic Reactions Hepatotoxicity, characterized by fever, nausea and vomiting associated with abnormal liver function tests, mainly elevated AST (SGOT) levels, has been associated with the use of oxacillin and cloxacillin. Chloestatic hepatitis has been reported rarely.
Asymptomatic, transient increases in serum concentrations of alkaline phosphatase, AST (SGOT), and ALT (SGPT) have been reported.
🔄 Drug Interactions ▾
Drug Interactions Tetracycline, a bacteriostatic antibiotic, may antagonize the bactericidal effect of penicillin and concurrent use of these drugs should be avoided. Probenecid administered concomitantly with penicillins increases and prolongs serum penicillin levels (see DOSAGE AND ADMINISTRATION ). Penicillinase-resistant penicillins, like other penicillins, are physically and/or chemically incompatible with aminoglycosides and can inactivate the drugs in vitro.
In vitro mixing of penicillins and aminoglycosides should be avoided during concomitant therapy and the drugs should be administered separately. Penicillins can inactivate aminoglycosides in vitro in serum samples from patients receiving both drugs, which could produce falsely decreased results in serum aminoglycoside assays of the serum samples. Dicloxacillin may reduce the anticoagulant response to dicumarol and warfarin.
Careful monitoring of prothrombin times is suggested during concomitant therapy, and dosage of the anticoagulant should be adjusted as required. The mechanism of this possible interaction is unclear, but may be due to hepatic enzyme induction.
🤰 Pregnancy ▾
Pregnancy Reproduction studies performed in the mouse, rat and rabbit have revealed no evidence of impaired fertility or harm to the fetus due to the penicillinase-resistant penicillins. Human experience with the penicillins during pregnancy has not shown any positive evidence of adverse effects on the fetus. There are, however, no adequate or well-controlled studies in pregnant women showing conclusively that harmful effects of these drugs on the fetus can be excluded.
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Because of incompletely developed renal function in newborns, penicillinase-resistant penicillins (especially methicillin) may not be completely excreted, with abnormally high blood levels resulting. Frequent monitoring of blood levels is advisable in this group, with dosage adjustments when necessary. All newborns treated with penicillins should be monitored closely for clinical and laboratory evidence of toxic or adverse effects (see DOSAGE AND ADMINISTRATION ).
Experience in the neonatal period is limited. Therefore a dose for the newborn is not recommended.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of dicloxacillin sodium capsules did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Microbiology Mechanism of Action Penicillinase-resistant penicillins exert a bactericidal action against penicillin-susceptible microorganisms during the state of active multiplication. All penicillins inhibit the biosynthesis of the bacterial cell wall. Antibacterial Activity Dicloxacillin sodium has been shown to be active against most isolates of the following microorganisms, both in vitro and in clinical infections as described in the INDICATIONS AND USAGE section.
Gram-positive Bacteria Staphylococcus spp. Susceptibility Testing For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC. Pharmacokinetics Dicloxacillin sodium is resistant to destruction by acid.
Absorption of dicloxacillin sodium after oral administration is rapid but incomplete; peak blood levels are achieved in 1 to 1.5 hours. In one study, after ingestion of a single 500 mg oral dose, peak serum concentrations range from 10 to 17 mcg/mL for dicloxacillin. Oral absorption of dicloxacillin is delayed when the drugs are administered after meals.
Once absorbed, dicloxacillin sodium is 97.9 ± 0.6 percent bound to serum protein, mainly albumin. Dicloxacillin sodium vary in the extent to which they are distributed in the body fluids. With normal doses, insignificant concentrations are found in the cerebrospinal fluid and aqueous humor.
Dicloxacillin sodium is found in therapeutic concentrations in the pleural, bile and amniotic fluids. Dicloxacillin sodium is rapidly excreted, primarily as unchanged drug in the urine by glomerular filtration and active tubular secretion. The elimination half-life for dicloxacillin is about 0.7 hour.
Nonrenal elimination includes hepatic inactivation and excretion in bile. Dicloxacillin is not dialyzable. Only minimal amounts are removed by hemodialysis or peritoneal dialysis.
📦 How Supplied / Storage and Handling ▾
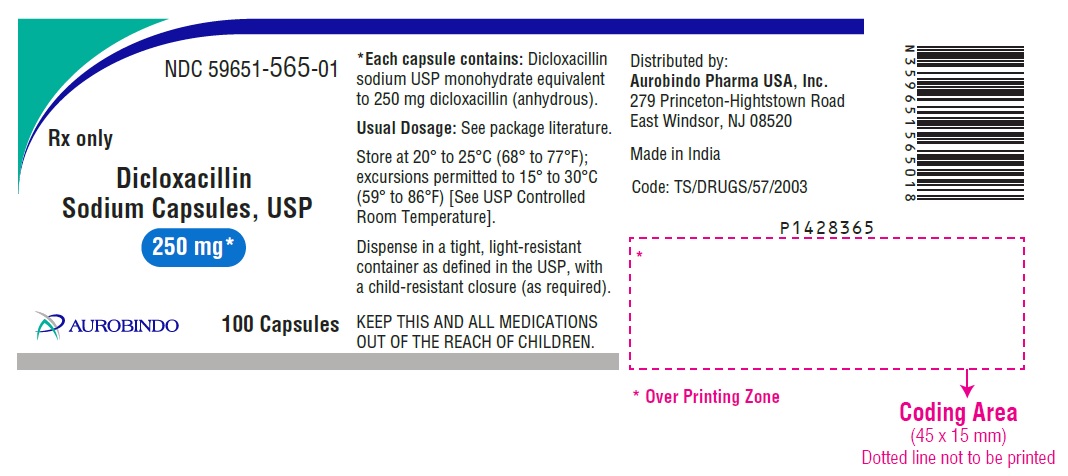
HOW SUPPLIED Dicloxacillin Sodium Capsules USP are available as follows: 250 mg: Each capsule contains dicloxacillin sodium USP monohydrate equivalent to 250 mg dicloxacillin (anhydrous), with blue opaque colored cap and body, hard gelatin capsule filled with white to off-white granular powder, imprinted with "DCS" on cap and “250” on body with black ink. They are supplied as follows: Bottles of 100 NDC 59651-565-01 500 mg: Each capsule contains dicloxacillin sodium USP monohydrate equivalent to 500 mg dicloxacillin (anhydrous), with blue opaque colored cap and body, hard gelatin capsule filled with white to off-white granular powder, imprinted with "DCS" on cap and “500” on body with black ink.
They are supplied as follows: Bottles of 100 NDC 59651-566-01 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required). KEEP THIS AND ALL MEDICATIONS OUT OF THE REACH OF CHILDREN.
Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Issued: August 2022
📋 Description ▾
DESCRIPTION Dicloxacillin sodium, USP is an antibacterial agent of the isoxazolyl penicillin series. It is a penicillinase resistant, acid resistant semisynthetic penicillin suitable for oral administration. It is monosodium (2 S ,5 R ,6 R )-6-[3-(2,6-dichlorophenyl)-5-methyl-4-isoxazolecarboxamido]-3,3-dimethyl-7-oxo-4-thia-1-azabicyclo [3.2.0]heptane-2-carboxylate monohydrate, and has following structural formula: C 19 H 16 Cl 2 N 3 NaO 5 S·H 2 O MW 510.32 Each capsule for oral administration contains dicloxacillin sodium USP monohydrate equivalent to 250 mg or 500 mg dicloxacillin (anhydrous).
The inactive ingredient is magnesium stearate. The capsule shells contain FD&C Blue 1, gelatin, sodium lauryl sulfate and titanium dioxide. The imprinting ink contains black iron oxide, potassium hydroxide and shellac. structure
💬 Information for Patients ▾
Information for the Patient Patients should be counselled that antibacterial drugs including dicloxacillin sodium capsules should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When dicloxacillin sodium capsules are prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by dicloxacillin sodium capsules or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible. Patients receiving penicillins should be given the following information and instructions by the physician: Patients should be told that penicillin is an antibacterial agent which will work with the body’s natural defenses to control certain types of infections. They should be told that the drug should not be taken if they have had an allergic reaction to any form of penicillin previously, and to inform the physician of any allergies or previous allergic reactions to any drugs they may have had (see WARNINGS ).
Patients who have previously experienced an anaphylactic reaction to penicillin should be instructed to wear a medical identification tag or bracelet. Because most antibacterial drugs taken by mouth are best absorbed on an empty stomach, patients should be directed, unless circumstances warrant otherwise, to take penicillin one hour before meals or two hours after eating (see CLINICAL PHARMACOLOGY - Pharmacokinetics ). Patients should be told to take the entire course of therapy prescribed, even if fever and other symptoms have stopped (see PRECAUTIONS - General ).
If any of the following reactions occur, stop taking your prescription and notify the physician: shortness of breath, wheezing, skin rash, mouth irritation, black tongue, sore throat, nausea, vomiting, diarrhea, fever, swollen joints or any unusual bleeding or bruising (see ADVERSE REACTIONS ). Do not take any additional medications without physician approval, including nonprescription drugs such as antacids, laxatives or vitamins.