
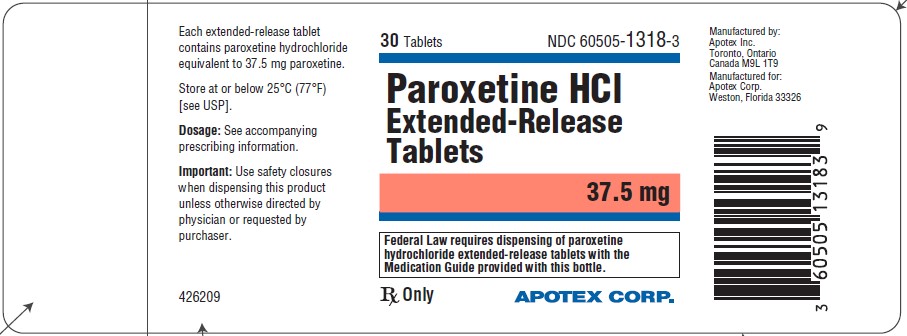
PAROXETINE HYDROCHLORIDE 37.5 mg Tablet, Film Coated, Extended Release, 30-count
Other active recalls for Paroxetine Hydrochloride (different manufacturers) — 5 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin Reuptake Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Paroxetine is used to treat depression, panic disorder (sudden, unexpected attacks of extreme fear and worry about these attacks), social anxiety disorder (extreme fear of interacting with others or performing in front of others that interferes with normal life), obsessive-compulsive disorder (bothersome thoughts that won't go away and the need to perform certain actions over and over), generalized anxiety disorder (GAD; excessive worrying that is difficult to control), and posttraumatic stress disorder (disturbing psychological symptoms that develop after a frightening experience). Paroxetine...
Read the full MedlinePlus article ↗- It usually takes a few weeks before you notice the full benefit — that's completely normal for this type of medication. Some people notice small improvements in sleep or energy wit...
- How long before I start feeling better on paroxetine?
- Please don't stop suddenly — paroxetine is one of the antidepressants most likely to cause discontinuation symptoms if you quit cold turkey. These can include dizziness, nausea, ir...
- Can I just stop taking paroxetine if I feel better or if it bothers me?
Patient education
Supplement & herbal interactions
Paroxetine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII R8WTH25YS2
Glyceryl dibehenate is a wax-like substance made from behenate fatty acids and glycerol. It functions as a binder and release-control agent in tablets and capsules, helping hold ingredients together and regulate how quickly the medicine dissolves and releases in your body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII NX76LV5T8J
A synthetic plastic polymer made from methacrylic acid and ethyl acrylate. It's used as a coating or binder to control how and where the medicine dissolves in your digestive system.
-
UNII H57W405143
Polyethylene glycol 10000 is a synthetic polymer made from ethylene oxide. It acts as a binder and lubricant in medicines, helping ingredients stick together and allowing tablets or capsules to move smoothly during manufacturing.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.400 | $11.99 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.7785 | $23.36 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.09 | $32.56 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Paroxetine Hydrochloride 37.5 mgthis 60505-1318-03 | Apotex | 30 tablets | $0.400 | AB | Availability likely | — |
| Paroxetine 37.5 mg 62135-0427-30 | Chartwell | 30 tablets | $0.400 | AB | Availability likely | — |
| Paroxetine Hydrochloride 37.5 mg 62175-0472-32 | Lannett | 30 tablets | $0.400 | AB | Availability likely | — |
| Paroxetine 37.5 mg 69367-0337-30 | Westminster | 30 tablets | $0.400 | AB | Availability likely | — |
| Paroxetine 37.5 mg 42858-0707-03 | Rhodes | 30 tablets | $0.409 | AB | Discontinued | +2% |
| Paroxetine 37.5 mg 46708-0768-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Paxil Cr 37.5 mg 60505-4379-03 | Apotex | 30 tablets | — | AB | FDA listed | — |
| Paroxetine 37.5 mg 62332-0768-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Paroxetine 37.5 mg 63629-9500-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Paroxetine 37.5 mg 68180-0645-01 | Lupin | 100 tablets | — | — | FDA listed | — |
| Paroxetine 37.5 mg 71209-0096-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Paroxetine 37.5 mg 72241-0031-10 | Modavar | 500 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 60505-1318-03 You're viewing this | 30 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (60505-1318-3) | 2019-08-09 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behaviors in pediatric and young adult patients in short-term studies. Closely monitor all antidepressant-treated patients for clinical worsening, and for emergence of suicidal thoughts and behaviors [see Warnings and Precautions (5.1 )]. Paroxetine HCL CR is not approved for use in pediatric patients [see Use in Specific Populations (8.4 )].
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning. Increased risk of suicidal thoughts and behavior in pediatric and young adult patients taking antidepressants. Closely monitor all antidepressant-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors.
Paroxetine HCL CR is not approved for use in pediatric patients. ( 5.1 , 8.4 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Paroxetine HCL CR is indicated in adults for the treatment of: Major depressive disorder (MDD) Panic disorder (PD) Social anxiety disorder (SAD) Premenstrual dysphoric disorder (PMDD) Paroxetine HCL CR is a selective serotonin reuptake inhibitor (SSRI) indicated in adults for the treatment of ( 1 ): Major Depressive Disorder (MDD) Panic Disorder (PD) Social Anxiety Disorder (SAD) Premenstrual Dysphoric Disorder (PMDD)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Swallow tablet whole; do not chew or crush. ( 2.1 ) Recommended starting and maximum daily dosage: ( 2.2 , 2.3 ) Indication Starting Dose Maximum Dose MDD 25 mg/day 62.5 mg/day PD 12.5 mg/day 75 mg/day SAD 12.5 mg/day 37.5 mg/day PMDD 12.5 mg/day 25 mg/day For PMDD, dose continuously or intermittently (luteal phase only). ( 2.3 ) If inadequate response to starting dosage, titrate in 12.5 mg per day increments once weekly.
( 2.2 , 2.3 ) Elderly patients, patients with severe renal impairment or severe hepatic impairment: Starting dose is 12.5 mg per day. Do not exceed 50 mg per day for treatment of MDD and PD and 37.5 mg per day for treatment of SAD. ( 2.5 ) When discontinuing Paroxetine HCL CR, reduce dose gradually.
( 2.7 )
2.1Important Administration Instructions Administer Paroxetine HCL CR as a single daily dose in the morning, with or without food. Swallow tablets whole and do not chew or crush.
2.2Dosage in Patients with Major Depressive Disorder, Panic Disorder, and Social Anxiety Disorder The recommended initial dosage and maximum dosage of Paroxetine HCL CR in patients with MDD, PD, and SAD are presented in Table 1. In patients with an inadequate response, dosage may be increased in increments of 12.5 mg per day at intervals of at least 1 week, depending on tolerability. Table 1: Recommended Daily Dosage of Paroxetine HCL CR in Patients with MDD, PD, and SAD Indication Starting Dose Maximum Dose MDD 25 mg 62.5 mg PD 12.5 mg 75 mg SAD 12.5 mg 37.5 mg
2.3Dosage in Patients with Premenstrual Dysphoric Disorder The recommended starting dosage in women with PMDD is 12.5 mg per day. Paroxetine HCL CR may be administered either continuously (every day throughout the menstrual cycle) or intermittently (only during the luteal phase of the menstrual cycle, i.e., starting the daily dosage 14 days prior to the anticipated onset of menstruation and continuing through the onset of menses). Intermittent dosing is repeated with each new cycle.
In patients with an inadequate response, the dosage may be increased to the maximum recommended dosage of 25 mg per day, depending on tolerability. Institute dosage adjustments at intervals of at least 1 week.
2.4Screen for Bipolar Disorder Prior to Starting Paroxetine HCL CR Prior to initiating treatment with Paroxetine HCL CR or another antidepressant, screen patients for a personal or family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions ( 5.6 )].
2.5Dosage Modifications for Elderly Patients, Patients with Severe Renal Impairment and Patients with Severe Hepatic Impairment The recommended initial dose of Paroxetine HCL CR is 12.5 mg per day for elderly patients, patients with severe renal impairment, and patients with severe hepatic impairment. Reduce initial dose and increase up-titration intervals if necessary. Dosage should not exceed 50 mg per day for MDD or PD and should not exceed 37.5 mg per day for SAD [see Use in Specific Populations ( 8.5 , 8.6 )].
2.6Switching Patients to or from a Monoamine Oxidase Inhibitor Antidepressant At least 14 days must elapse between discontinuation of an monoamine oxidase inhibitor (MAOI) antidepressant and initiation of Paroxetine HCL CR. In addition, at least 14 days must elapse after stopping Paroxetine HCL CR before starting an MAOI antidepressant [see Contraindications ( 4 ), Warnings and Precautions ( 5.2 )].
2.7Discontinuation of Treatment with Paroxetine HCL CR Adverse reactions may occur upon discontinuation of Paroxetine HCL CR [see Warnings and Precautions ( 5.7 )] .Gradually reduce the dosage rather than stopping Paroxetine HCL CR abruptly whenever possible.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Paroxetine HCL CR extended‑release tablets, USP are available as: • 12.5 mg yellow, round tablets, one face is plain and the other face is engraved with “12.5”. • 25 mg pink, round tablets, one face is plain and the other face is engraved with “25”. • 37.5 mg blue, round tablets, one face is plain and the other face is engraved with “37.5”. Extended-release tablets:12.5 mg, 25 mg, and 37.5 mg tablets. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Paroxetine HCL CR is contraindicated in patients: Taking, or within 14 days of stopping, MAOIs (including the MAOIs linezolid and intravenous methylene blue) because of an increased risk of serotonin syndrome [See Warnings and Precautions ( 5.2 ), Drug Interactions (7)]. Paroxetine HCL CR should not be used in patients receiving medications that can prolong QT interval and are also metabolized by CYP450 2D6,such as thioridazine or pimozide [see Drug Interactions (7),Warnings and Precautions (5.3)].
With known hypersensitivity (e.g., anaphylaxis, angioedema, Stevens-Johnson syndrome) to paroxetine or to any of the inactive ingredients in Paroxetine HCL CR [see Adverse Reactions ( 6.1 , 6.2 )]. Concomitant use of monoamine oxidase inhibitors (MAOIs) or use within 14 days of discontinuing a MAOIs. ( 4 , 5.2 , 7 ) Concomitant use of pimozide or thioridazine.
( 4 , 5.3 , 7 ) Known hypersensitivity to paroxetine or to any of the inactive ingredients in Paroxetine HCL CR. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome: Increased risk when co-administered with other serotonergic agents, but also when taken alone. If occurs, discontinue Paroxetine HCL CR and serotonergic agents and initiate supportive measures. ( 5.2 ) Embryofetal Toxicity : May cause fetal harm.
Meta-analysis of epidemiological studies have shown increased risk (less than 2-fold) of cardiovascular malformations with exposure during the first trimester.( 5.4 , 8. 1) Increased Risk of Bleeding: Concomitant use of aspirin, nonsteroidal anti-inflammatory drugs, other antiplatelet drugs, warfarin, and other anticoagulant drugs may increase risk. ( 5.5 ) Activation of Mania/Hypomania : Screen patients for bipolar disorder.
( 5.6 ) Seizures : Use with caution in patients with seizure disorders. ( 5.8 ) Angle-Closure Glaucoma: Angle-closure glaucoma has occurred in patients with untreated anatomically narrow angles, treated with antidepressants (5.9 ) Sexual Dysfunction: Paroxetine HCL CR may cause symptoms of sexual dysfunction. ( 5.13 )
5.1Suicidal Thoughts and Behaviors in Adolescents and Young Adults In pooled analyses of placebo-controlled trials of antidepressant drugs (SSRIs and other antidepressant classes) that included approximately 77,000 adult patients and 4,500 pediatric patients, the incidence of suicidal thoughts and behaviors in antidepressant-treated patients age 24 years and younger was greater than in placebo-treated patients. There was considerable variation in risk of suicidal thoughts and behaviors among drugs, but there was an increased risk identified in young patients for most drugs studied.
There were differences in absolute risk of suicidal thoughts and behaviors across the different indications, with the highest incidence in patients with MDD. The drug-placebo differences in the number of cases of suicidal thoughts and behaviors per 1,000 patients treated are provided in Table 2. Table 2: Risk Differences of the Number of Patients of Suicidal Thoughts and Behaviors in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range Drug-Placebo Difference in Number of Patients of Suicidal Thoughts and Behaviors per 1,000 Patients Treated I ncreases Compared to Placebo <18 years old 14 additional patients 18 to 24 years old 5 additional patients Decreases Compared to Placebo 25 to 64 years old 1 fewer patient ≥65 years old 6 fewer patients It is unknown whether the risk of suicidal thoughts and behaviors in children, adolescents, and young adults extends to longer-term use, i.e., beyond four months.
However, there is substantial evidence from placebo-controlled maintenance trials in adults with MDD that antidepressants delay the recurrence of depression and that depression itself is a risk factor for suicidal thoughts and behaviors. Monitor all antidepressant-treated patients for any indication for clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes. Counsel family members or caregivers of patients to monitor for changes in behavior and to alert the healthcare provider.
Consider changing the therapeutic regimen, including possibly discontinuing Paroxetine HCL CR, in patients whose depression is persistently worse, or who are experiencing emergent suicidal thoughts or behaviors.
5.2Serotonin Syndrome Serotonin-norepinephrine reuptake inhibitors (SNRIs) and SSRIs, including Paroxetine HCL CR, can precipitate serotonin syndrome, a potentially life-threatening condition. The risk is increased with concomitant use of other serotonergic drugs (including triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, meperidine, methadone, tryptophan, buspirone, amphetamines, and St. John's Wort) and with drugs that impair metabolism of serotonin, i.e., MAOIs [see Contraindications ( 4 ), Drug Interactions ( 7.1 )].
Serotonin syndrome can also occur when these drugs are used al…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are included in more detail in other sections of the prescribing information: Hypersensitivity reactions to paroxetine [see Contraindications ( 4 )] Suicidal Thoughts and Behaviors [see Warnings and Precautions ( 5.1 )] Serotonin Syndrome [see Warnings and Precautions ( 5.2 )] Embryofetal and Neonatal Toxicity [see Warnings and Precautions ( 5.4 )] Increased Risk of Bleeding [see Warnings and Precautions ( 5.5 )] Activation of Mania/Hypomania [see Warnings and Precautions ( 5.6 )] Discontinuation Syndrome [see Warnings and Precautions ( 5.7 )] Seizures [see Warnings and Precautions ( 5.8 )] Angle-closure Glaucoma [see Warnings and Precautions ( 5.9 )] Hyponatremia [see Warnings and Precautions ( 5.10 )] Bone Fracture [see Warnings and Precautions ( 5.12 )] Sexual Dysfunction [see Warnings and Precautions ( 5.13 )] Most common adverse reactions (≥5% and at least twice placebo) in placebo-controlled MDD, PD, SAD, and PMDD clinical trials: abnormal ejaculation, abnormal vision, asthenia, constipation, decreased appetite, diarrhea, dizziness, dry mouth, female genital disorder, impotence, insomnia, libido decreased, nausea, somnolence, sweating, tremor.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Safety data for Paroxetine HCL CR is from 11 short-term, placebo‑controlled clinical trials including 3 studies in patients with major depressive disorder (MDD) (Studies 1, 2, and 3), 3 studies in patients with panic disorder (PD) (Studies 4, 5, and 6), 1 study in patients with social anxiety disorder (SAD) (Study 7), and 4 studies in female patients with premenstrual dysphoric disorder (PMDD) (Studies 8, 9, 10, and 11) [see Clinical Studies ( 14 )].
These 11 trials included 1627 patients treated with Paroxetine HCL CR. Studies 1 and 2 were 12-week studies that enrolled patients 18 to 65 years old who received Paroxetine HCL CR at doses ranging from 25 mg to 62.5 mg once daily. Study 3 was a 12-week study in patients 60 to 88 years old who received Paroxetine HCL CR at doses ranging from 12.5 mg to 50 mg once daily.
Studies 4, 5, and 6 were 10-week studies in patients 19 to 72 years old who received Paroxetine HCL CR at doses ranging from 12.5 mg to 75 mg once daily. Study 7 was a 12-week study that enrolled adult patients who received Paroxetine HCL CR at doses ranging from 12.5 mg to 37.5 mg once daily. Studies 8, 9, and 10 were 12‑week, placebo‑controlled trials in female patients 18 to 46 years old who received Paroxetine HCL CR at doses of 12.5 mg or 25 mg once daily.
Study 11 was a 12-week placebo‑controlled trial in patients 18 to 46 years old who received Paroxetine HCL CR 2 weeks prior to the onset of menses (luteal phase dosing) at doses of 12.5 mg or 25 mg once daily. Adverse Reactions Leading to Discontinuation in Patients with MDD, PD, SAD, and PMDD In pooled studies in patients with MDD, PD and SAD, the most common adverse reactions leading to study withdrawal were: nausea (up to 4% of patients), asthenia, headache, depression, insomnia, and abnormal liver function tests (each occurring in up to 2% of patients), and dizziness, somnolence, and diarrhea (each occurring in up to 1% of patients).
In pooled studies for PMDD, the most common adverse reactions leading to study withdrawal were: nausea (occurring in up to 6% of patients), asthenia (occurring in up to 5% of patients), somnolence (occurring in up to 4% of patients), insomnia (occurring in approximately 2% of patients); and impaired concentration, dry mouth, dizziness, decreased appetite, sweating, tremor, yawn and diarrhea (occurring in…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drugs Highly Bound to Plasma Protein: Monitor for adverse reactions and reduce dosage of Paroxetine HCL CR or other protein-bound drugs (e.g., warfarin) as warranted. ( 7 ) Drugs Metabolized by CYP2D6: Reduce dosage of drugs metabolized by CYP2D6 as warranted. ( 7 ) Concomitant use with Tamoxifen: Consider use of an alternative antidepressant with little or no CYP2D6 inhibition. ( 5.11 , 7 )
7.1Clinically Significant Drug Interactions with Paroxetine HCL CR Table 6 includes clinically significant drug interactions with Paroxetine HCL CR. Table 6: Clinically Significant Drug Interactions with Paroxetine HCL CR Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact The concomitant use of SSRIs, including Paroxetine HCL CR, and MAOIs increases the risk of serotonin syndrome. Intervention Paroxetine HCL CR is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Dosage and Administration ( 2.6 ), Contraindications ( 4 ), Warnings and Precautions ( 5.2 )].
Examples selegiline, tranylcypromine, isocarboxazid, phenelzine, linezolid, methylene blue Pimozide and Thioridazine Clinical Impact Paroxetine HCL CR should not be used in patients receiving medications that can prolong QT interval and are metabolized by CYP450 2D6 such as thioridazine or pimozide (see Contraindications and Warnings and Precautions ) Intervention Paroxetine HCL CR is contraindicated in patients taking pimozide or thioridazine [see Contraindications ( 4 )]. Other Serotonergic Drugs Clinical Impact The concomitant use of serotonergic drugs with Paroxetine HCL CR increases the risk of serotonin syndrome.
Intervention Monitor patients for signs and symptoms of serotonin syndrome, particularly during treatment initiation and dosage increases. If serotonin syndrome occurs, consider discontinuation of Paroxetine HCL CR and/or concomitant serotonergic drugs [see Warnings and Precautions ( 5.2 )]. Examples Other SSRIs, SNRIs, triptans, tricyclic antidepressants, opioids, lithium, tryptophan, buspirone, St.
John’s Wort Drugs that Interfere with Hemostasis (antiplatelet agents and anticoagulants) Clinical Impact The concurrent use of an antiplatelet agent or anticoagulant with Paroxetine HCL CR may potentiate the risk of bleeding. Intervention Inform patients of the increased risk of bleeding associated with the concomitant use of Paroxetine HCL CR and antiplatelet agents and anticoagulants. For patients taking warfarin, carefully monitor the international normalized ratio [see Warnings and Precautions ( 5.5 )].
Examples aspirin, clopidogrel, heparin, warfarin Drugs Highly Bound to Plasma Protein Clinical Impact Paroxetine HCL CR is highly bound to plasma protein. The concomitant use of Paroxetine HCL CR with another drug that is highly bound to plasma protein may increase free concentrations of Paroxetine HCL CR or other tightly-bound drugs in plasma. Intervention Monitor for adverse reactions and reduce dosage of Paroxetine HCL CR or other protein-bound drugs as warranted.
Examples warfarin Drugs Metabolized by CYP2D6 Clinical Impact Paroxetine HCL CR is a CYP2D6 inhibitor [see Clinical Pharmacology ( 12.3 )]. The concomitant use of Paroxetine HCL CR with a CYP2D6 substrate may increase the exposure of the CYP2D6 substrate. Intervention Decrease the dosage of a CYP2D6 substrate if needed with concomitant Paroxetine HCL CR use.
Conversely, an increase in dosage of a CYP2D6 substrate may be needed if Paroxetine HCL CR is discontinued. Examples propafenone, flecainide, atomoxetine, desipramine, dextromethorphan, metoprolol, nebivolol, perphenazine, tolterodine, venlafaxine, risperidone. Tamoxifen Clinical Impact Concomitant use of tamoxifen with Paroxetine HCL CR may lead to reduced plasma concentrations of the active metabolite (endoxifen) and reduced efficacy of tamoxifen Intervention Consider use of an alternative antidepressant little or no CYP2D6 inhibition [see Warnings and Precautions ( 5.11…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: SSRI use, particularly later in pregnancy, may increase the risk of persistent pulmonary hypertension and symptoms of poor adaptation (respiratory distress, temperature instability, feeding difficulty, hypotonia, irritability) in the neonate. ( 5.4, 8.1 ) Nursing Mothers : Discontinue drug or nursing taking into consideration importance of drug to mother. ( 8.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and-researchprograms/ pregnancy registry/antidepressants/. Risk Summary Based on data from published observational studies, exposure to SSRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions (5.5) and Clinical Considerations].
Paroxetine HCL CR is associated with a less than 2-fold increase in cardiovascular malformations when administered to a pregnant woman during the first trimester. While individual epidemiological studies on the association between paroxetine use and cardiovascular malformations have reported inconsistent findings, some meta-analyses of epidemiological studies have identified an increased risk of cardiovascular malformations (see Data). There are risks of persistent pulmonary hypertension of the newborn (PPHN) (see Data) and/or poor neonatal adaptation with exposure to selective serotonin reuptake inhibitors (SSRIs), including Paroxetine HCL CR, during pregnancy.
There also are risks associated with untreated depression in pregnancy (see Clinical Considerations). For women who intend to become pregnant or who are in their first trimester of pregnancy, paroxetine should be initiated only after consideration of the other available treatment options. No evidence of treatment related malformations was observed in animal reproduction studies, when paroxetine was administered during the period of organogenesis at doses up to 50 mg/kg/day in rats and 6 mg/kg/day in rabbits.
These doses are approximately 6 (rat) and less than 2 (rabbit) times the maximum recommended human dose (MRHD -75 mg) on an mg/m 2 basis. When paroxetine was administered to female rats during the last trimester of gestation and continued through lactation, there was an increase in the number of pup deaths during the first four days of lactation. This effect occurred at a dose of 1 mg/kg/day which is less than the MRHD on an mg/m 2 basis (see Data).
The estimated background risks of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Women who discontinue antidepressants during pregnancy are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective longitudinal study of 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy. Consider the risks of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum.
Maternal Adverse Reactions Use of Paroxetine HCL CR in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions (5.5)]. Fetal/Neonatal adverse reactions Neonates exposed to Paroxetine HCL CR and other SSRIs late in the third…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-866-961-2388 or visiting online at https://womensmentalhealth.org/clinical-and-researchprograms/ pregnancy registry/antidepressants/. Risk Summary Based on data from published observational studies, exposure to SSRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions (5.5) and Clinical Considerations].
Paroxetine HCL CR is associated with a less than 2-fold increase in cardiovascular malformations when administered to a pregnant woman during the first trimester. While individual epidemiological studies on the association between paroxetine use and cardiovascular malformations have reported inconsistent findings, some meta-analyses of epidemiological studies have identified an increased risk of cardiovascular malformations (see Data). There are risks of persistent pulmonary hypertension of the newborn (PPHN) (see Data) and/or poor neonatal adaptation with exposure to selective serotonin reuptake inhibitors (SSRIs), including Paroxetine HCL CR, during pregnancy.
There also are risks associated with untreated depression in pregnancy (see Clinical Considerations). For women who intend to become pregnant or who are in their first trimester of pregnancy, paroxetine should be initiated only after consideration of the other available treatment options. No evidence of treatment related malformations was observed in animal reproduction studies, when paroxetine was administered during the period of organogenesis at doses up to 50 mg/kg/day in rats and 6 mg/kg/day in rabbits.
These doses are approximately 6 (rat) and less than 2 (rabbit) times the maximum recommended human dose (MRHD -75 mg) on an mg/m 2 basis. When paroxetine was administered to female rats during the last trimester of gestation and continued through lactation, there was an increase in the number of pup deaths during the first four days of lactation. This effect occurred at a dose of 1 mg/kg/day which is less than the MRHD on an mg/m 2 basis (see Data).
The estimated background risks of major birth defects and miscarriage for the indicated populations are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the US general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Women who discontinue antidepressants during pregnancy are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective longitudinal study of 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy. Consider the risks of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum.
Maternal Adverse Reactions Use of Paroxetine HCL CR in the month before delivery may be associated with an increased risk of postpartum hemorrhage [see Warnings and Precautions (5.5)]. Fetal/Neonatal adverse reactions Neonates exposed to Paroxetine HCL CR and other SSRIs late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Such complications can arise immediately upon delivery.
Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremors, jitteriness, irritability, an…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Paroxetine HCL CR in pediatric patients have not been established [see Boxed Warning, Warnings and Precautions ( 5.1 )]. Three placebo-controlled trials in 752 pediatric patients with MDD have been conducted with immediate-release paroxetine, and effectiveness was not established in pediatric patients. Decreased appetite and weight loss have been observed in association with the use of SSRIs.
In placebo-controlled clinical trials conducted with pediatric patients, the following adverse reactions were reported in at least 2% of pediatric patients treated with immediate-release paroxetine hydrochloride and at a rate at least twice that for pediatric patients receiving placebo: emotional lability (including self-harm, suicidal thoughts, attempted suicide, crying, and mood fluctuations), hostility, decreased appetite, tremor, sweating, hyperkinesia, and agitation. Adverse reactions upon discontinuation of treatment with immediate-release paroxetine hydrochloride in the pediatric clinical trials that included a taper phase regimen, which occurred in at least 2% of patients and at a rate at least twice that of placebo, were: emotional lability (including suicidal ideation, suicide attempt, mood changes, and tearfulness), nervousness, dizziness, nausea, and abdominal pain.
🧓 Geriatric Use ▾
8.5Geriatric Use SSRIs and SNRIs, including Paroxetine HCL CR, have been associated with cases of clinically significant hyponatremia in elderly patients, who may be at greater risk for this adverse reaction [see Warnings and Precautions ( 5.9 )]. In premarketing clinical trials with immediate‑release paroxetine hydrochloride, 17% of paroxetine treated patients (approximately 700) were 65 years or older. Pharmacokinetic studies revealed a decreased clearance in the elderly, and a lower starting dose is recommended; however, no overall differences in safety or effectiveness were observed between these subjects and younger subjects [see Dosage and Administration (2.5), Clinical Pharmacology (12.3)].
🆘 Overdosage ▾
10 OVERDOSAGE The following have been reported with paroxetine tablet overdosage: Seizures, which may be delayed, and altered mental status including coma. Cardiovascular toxicity, which may be delayed, including QRS and QTc interval prolongation. Hypertension most commonly seen, but rarely can see hypotension alone or with co-ingestants including alcohol.
Serotonin syndrome (patients with a multiple drug overdosage with other proserotonergic drugs may have a higher risk). Gastrointestinal decontamination with activated charcoal should be considered in patients who present early after a paroxetine overdose. Consider contacting a Poison Center (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of paroxetine in the treatment of major depressive disorder (MDD), panic disorder (PD), social anxiety disorder (SAD), and premenstrual dysphoric disorder (PMDD) is unknown, but is presumed to be linked to potentiation of serotonergic activity in the central nervous system resulting from inhibition of neuronal reuptake of serotonin (5-HT).
12.2Pharmacodynamics Studies at clinically relevant doses in humans have demonstrated that paroxetine blocks the uptake of serotonin into human platelets. In vitro studies in animals also suggest that paroxetine is a potent and highly selective inhibitor of neuronal serotonin reuptake (SSRI) and has only very weak effects on norepinephrine and dopamine neuronal reuptake.
12.3Pharmacokinetics Absorption Tablets of Paroxetine HCL CR contain a degradable polymeric matrix designed to control the dissolution rate of paroxetine over a period of approximately 4 to 5 hours. In addition to controlling the rate of drug release in vivo , an enteric coat delays the start of drug release until tablets of Paroxetine HCL CR have left the stomach. Paroxetine extended-release tablets are completely absorbed after oral dosing of a solution of the hydrochloride salt.
In a study in which normal male and female subjects (n = 23) received single oral doses of Paroxetine HCL CR at 4 dosage strengths (12.5 mg, 25 mg, 37.5 mg, and 50 mg), paroxetine C max and AUC 0-inf increased disproportionately with dose (as seen also with immediate‑release formulations). Mean C max and AUC 0-inf values at these doses were 2, 5.5, 9, and 12.5 ng/mL, and 121, 261, 338, and 540 ng·hr. /mL, respectively. T max was observed typically between 6 and 10 hours post‑dose, reflecting a reduction in absorption rate compared with immediate‑release formulations.
The bioavailability of 25 mg Paroxetine HCL CR is not affected by food. Distribution Paroxetine distributes throughout the body, including the CNS, with only 1% remaining in the plasma. Approximately 95% and 93% of paroxetine is bound to plasma protein at 100 ng/mL and 400 ng/mL, respectively.
Under clinical conditions, paroxetine concentrations would normally be less than 400 ng/mL. Paroxetine does not alter the in vitro protein binding of phenytoin or warfarin. Elimination Metabolism The mean elimination half-life of paroxetine was 15 to 20 hours throughout a range of single doses of Paroxetine HCL CR (12.5 mg, 25 mg, 37.5 mg, and 50 mg).
During repeated administration of Paroxetine HCL CR (25 mg once daily), steady state was reached within 2 weeks (i.e., comparable to immediate‑release formulations). In a repeat‑dose study in which normal male and female subjects (n = 23) received Paroxetine HCL CR (25 mg daily), mean steady state C max , C min , and AUC 0-24 values were 30 ng/mL, 20 ng/mL, and 550 ng·hr./mL, respectively. Based on studies using immediate‑release formulations, steady‑state drug exposure based on AUC 0-24 was several‑fold greater than would have been predicted from single‑dose data.
The excess accumulation is a consequence of the fact that 1 of the enzymes that metabolizes paroxetine is readily saturable. In steady‑state dose proportionality studies involving elderly and nonelderly patients, at doses of the immediate‑release formulation of 20 mg to 40 mg daily for the elderly and 20 mg to 50 mg daily for the nonelderly, some nonlinearity was observed in both populations, again reflecting a saturable metabolic pathway (Figure 3). Paroxetine is extensively metabolized after oral administration.
The principal metabolites are polar and conjugated products of oxidation and methylation, which are readily cleared. Conjugates with glucuronic acid and sulfate predominate, and major metabolites have been isolated and identified. Data indicate that the metabolites have no more than 1/50 the potency of the parent compound at inhibiting serotonin uptake.
The metabolism of paroxetine is accomplished in pa…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of paroxetine in the treatment of major depressive disorder (MDD), panic disorder (PD), social anxiety disorder (SAD), and premenstrual dysphoric disorder (PMDD) is unknown, but is presumed to be linked to potentiation of serotonergic activity in the central nervous system resulting from inhibition of neuronal reuptake of serotonin (5-HT).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Paroxetine HCL CR extended‑release tablets, USP are available as: 12.5 mg yellow, round tablets, one face is plain and the other face is engraved with “12.5”. Bottles of 30 NDC 60505-1316-3 25 mg pink, round tablets, one face is plain and the other face is engraved with “25”. Bottles of 30 NDC 60505-1317-3 37.5 mg blue, round tablets, one face is plain and the other face is engraved with “37.5”.
Bottles of 30 NDC 60505-1318-3 Store at or below 25°C (77°F); [see USP].
📋 Description ▾
11 DESCRIPTION Paroxetine HCL CR USP, contains paroxetine hydrochloride, an SSRI. It is the hydrochloride salt of a phenylpiperidine compound identified chemically as (-)-trans-4R-(4'-fluorophenyl)-3S-[(3',4'-methylenedioxyphenoxy) methyl] piperidine hydrochloride hemihydrate and has the empirical formula of C 19 H 20 FNO 3 ·HCl·1/2H 2 O. The molecular weight is 374.8 g/mol (329.4 g/mol as free base).
The structural formula of paroxetine hydrochloride is: Paroxetine hydrochloride is an odorless, off‑white powder, having a melting point range of 120°C to 138°C and a solubility of 5.4 mg/mL in water. Paroxetine HCL CR tablets, USP are intended for oral administration. Each extended‑release tablet contains 12.5 mg, 25 mg, or 37.5 mg paroxetine equivalent to 14.25 mg, 28.51 mg, or 42.76 mg of paroxetine hydrochloride, respectively.
One layer of the tablet consists of a degradable barrier layer and the other contains the active material in a hydrophilic matrix. Inactive ingredients consist of glyceryl behenate, hypromellose, lactose monohydrate, magnesium stearate, methacrylic acid copolymer type C, polyethylene glycols, polysorbate 80, polyvinylpyrrolidone, silicon dioxide, sodium lauryl sulfate, talc, titanium dioxide, triethyl citrate and the following colorants: D&C Red No. 30 aluminum lake (25 mg), D&C Yellow No.
10 aluminum lake (12.5 mg), FD&C Blue No. 2 aluminum lake (37.5 mg), FD&C Yellow No. 6 aluminum lake (12.5 mg), red ferric oxide (25 mg) and Yellow ferric oxide (12.5 mg and 37.5 mg).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Suicidal Thoughts and Behaviors Advise patients and caregivers to look for the emergence of suicidality, especially early during treatment and when the dosage is adjusted up or down, and instruct them to report such symptoms to the healthcare provider [see Boxed Warning and Warnings and Precautions ( 5.1 )]. Important Administration Instructions Instruct patients to swallow Paroxetine HCL CR whole and to not chew or crush the tablets [see Dosage and Administration ( 2.1 )].
Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the concomitant use of Paroxetine HCL CR with other serotonergic drugs including triptans, tricyclic antidepressants, opioids, lithium, tryptophan, buspirone, amphetamines, St. John’s Wort, and with drugs that impair metabolism of serotonin (in particular, MAOIs, both those intended to treat psychiatric disorders and also others, such as linezolid). Instruct patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome [see Warnings and Precautions ( 5.2 ), Drug Interactions ( 7.1 )].
Concomitant Medications Advise patients to inform their physician if they are taking, or plan to take, any prescription or over‑the‑counter drugs, since there is a potential for drug-drug interactions [see Warning and Precautions ( 5.3 ), Drug Interactions ( 7 )]. Increased Risk of Bleeding Inform patients about the concomitant use of Paroxetine HCL CR with aspirin, NSAIDs, other antiplatelet drugs, warfarin, or other anticoagulants because the combined use has been associated with an increased risk of bleeding. Advise patients to inform their health care providers if they are taking or planning to take any prescription or over-the counter medications that increase the risk of bleeding [see Warnings and Precautions ( 5.5 )].
Activation of Mania/Hypomania Advise patients and their caregivers to observe for signs of activation of mania/hypomania and instruct them to report such symptoms to the healthcare provider [see Warnings and Precautions ( 5.6 )]. Discontinuation Syndrome Advise patients not to abruptly discontinue Paroxetine HCL CR and to discuss any tapering regimen with their healthcare provider. Inform patients that adverse reactions can occur when Paroxetine HCL CR is discontinued [See Warnings and Precautions ( 5.7 )].
Sexual Dysfunction Advise patients that use of Paroxetine HCL CR may cause symptoms of sexual dysfunction in both male and female patients. Inform patients that they should discuss any changes in sexual function and potential management strategies with their healthcare provider [see Warnings and Precautions ( 5.13 )]. Embryo-Fetal Toxicity Advise women to notify their healthcare provider if they become pregnant or intend to become pregnant during treatment with Paroxetine HCL CR.
Advise women of risks associated with first trimester use of Paroxetine HCL CR and that use later in pregnancy may lead to an increased risk for neonatal complications requiring prolonged hospitalization, respiratory support, tube feeding, and/or persistent pulmonary hypertension of the newborn (PPHN) [see Warnings and Precautions (5.4), Use in Specific Populations (8.1)]. Advise women that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to Paroxetine HCL CR during pregnancy [see Warnings and Precautions (5.4), Use in Specific Populations (8.1)].
Lactation Advise breastfeeding women using Paroxetine HCL CR to monitor infants for agitation, irritability, poor feeding and poor weight gain and to seek medical care if they notice these signs [see Use in Specific Populations ( 8.2 )]. Females and Males of Reproduct ive Potential Advise men that Paroxetine HCL CR may affect sperm quality, which may impair fertility; it is unknown if this effect is reversible [see Use…
💬 Medication Guide ▾
Medication Guide Paroxetine HCL CR ( PA-rox-eh-tine HY-dro-chlo-ride ) extended-release tablets,USP What is the most important information I should know about Paroxetine HCL CR ? Paroxetine HCL CR can cause serious side effects, including: Increased risk of suicidal thoughts or actions. Antidepressant medicines may increase suicidal thoughts and actions in some children and young adults within the first few months of treatment or when the dose is changed.
Paroxetine HCL CR is not for use in people younger than 18 years of age. How can I watch for and try to prevent suicidal thoughts and actions? Depression or other serious mental illnesses are the most important causes of suicidal thoughts and actions.
Pay close attention to any changes, especially sudden changes in mood, behavior, thoughts or feelings or if you develop suicidal thoughts or actions. This is very important when an antidepressant medicine is started or when the dose is changed. Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts or feelings or if you develop suicidal thoughts or actions.
Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you have concerns about symptoms. Call your healthcare provider or get emergency medical help right away if you have any of the following symptoms, especially if they are new, worse, or worry you: attempts to commit suicide acting aggressive or violent new or worse depression feeling agitated, restless, angry, or irritable an increase in activity and talking more than what is normal for you acting on dangerous impulses thoughts about suicide or dying new or worse anxiety or panic attacks trouble sleeping other unusual changes in behavior or mood What is Paroxetine HCL CR ?
Paroxetine HCL CR is a prescription medicine used in adults to treat: A certain type of depression called Major Depressive Disorder (MDD) Panic Disorder Social Anxiety Disorder (SAD) Premenstrual Dysphoric Disorder (PMDD) Do not take Paroxetine HCL CR if you: take a monoamine oxidase inhibitor (MAOI) have stopped taking an MAOI in the last 14 days are being treated with the antibiotic linezolid or intravenous methylene blue are taking thioridazine are taking pimozide are allergic to paroxetine or any of the ingredients in Paroxetine HCL CR.
See the end of this Medication Guide for a complete list of ingredients in Paroxetine HCL CR. Ask your healthcare provider or pharmacist if you are not sure if you take an MAOI or one of these medicines, including intravenous methylene blue. Do not start taking an MAOI for at least 14 days after you stop treatment with Paroxetine HCL CR .
Before taking Paroxetine HCL CR , tell your healthcare provider about all your medical conditions, including if you: have heart problems have a heart tracing (electrocardiogram/ECG) has an abnormality known as prolonged QT interval or you are taking medicines that may affect the QT interval in the ECG. have or had bleeding problems have, or have a family history of bipolar disorder, mania or hypomania have or had seizures or convulsions have glaucoma (high pressure in the eye) have low sodium levels in your blood have bone problems have kidney or liver problems are pregnant or plan to become pregnant.
Paroxetine HCL CR may harm your unborn baby. Taking Paroxetine HCL CR during your first trimester of pregnancy may cause your baby to be at an increased risk of having a heart problem (cardiac malformations) at birth. Taking Paroxetine HCL CR during your third trimester of pregnancy may cause your baby to have breathing, temperature, and feeding problems, low muscle tone (floppy baby syndrome), and irritability after birth and may cause your baby to be at an increased risk of a serious lung problem at birth.
Talk to your healthcare provider about the risk to your unborn baby if you take Paroxetine HCL CR during pregnancy. Tell your healthcare provider right…