
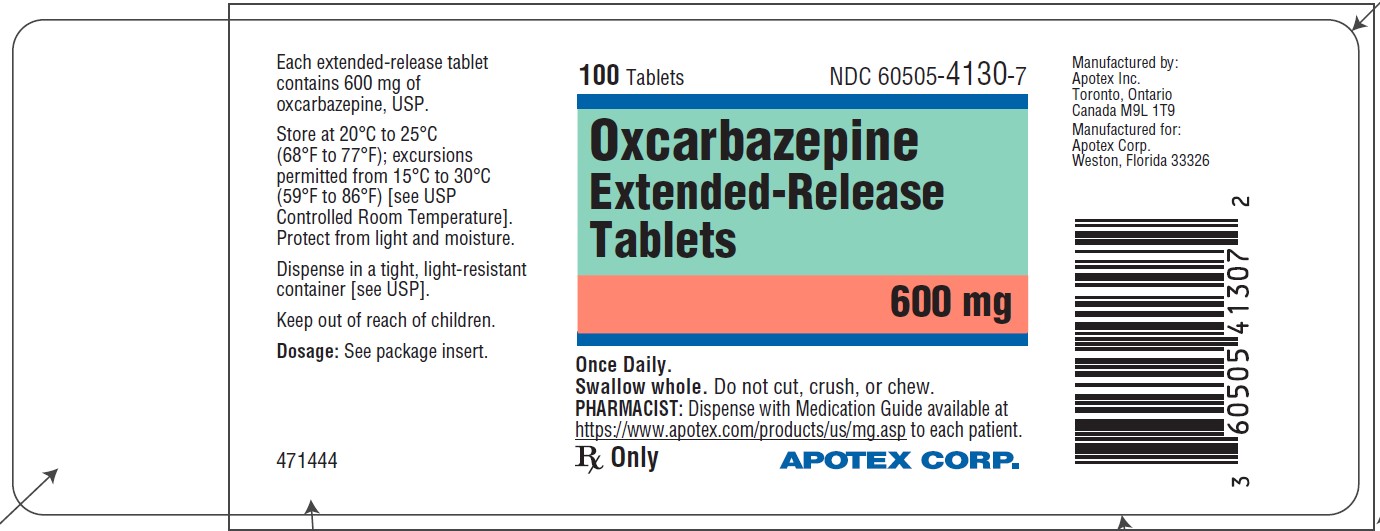
OXCARBAZEPINE 600 mg Tablet, Extended Release, 100-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Oxcarbazepine is used to treat partial-onset seizures — seizures that start in one part of the brain. It can be used on its own or together with other seizure medicines, depending...
- What is oxcarbazepine actually used for?
- Good news: the tablets and oral suspension can be taken with or without food, so you don't need to plan around meals. The extended-release tablet is taken once a day, while the reg...
- How should I take it — does it matter if I take it with food?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Oxcarbazepine — tap one for details:
Oxcarbazepine may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII B1QE5P712K
Hypromellose 2208 is a plant-derived thickening agent that dissolves in water. It's used as a binder to help hold tablet ingredients together and as a coating on pills to control how quickly the medicine releases in your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.478 | $947.84 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $15.35 | $1,534.50 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $19.18 | $1,918.00 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Oxcarbazepine 600 mg 27241-0239-01 | Ajanta | 100 tablets | $9.478 | AB | Availability likely | — |
| Oxcarbazepine 600 mg 50742-0613-01 | Ingenus | 100 tablets | $9.478 | AB | Availability likely | — |
| Oxcarbazepine 600 mgthis 60505-4130-07 | Apotex | 100 tablets | $9.478 | AB | Availability likely | — |
| Oxtellar Xr 600 mg 17772-0123-01 | Supernus | 100 tablets | $23.203 | AB | Availability likely | +145% |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 60505-4130-05 | 500 TABLET, EXTENDED RELEASE in 1 BOTTLE (60505-4130-5) | — | — | 2024-09-03 | Active |
| 60505-4130-07 You're viewing this | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (60505-4130-7) | $9.48 / ea | $947.84 | 2024-09-03 | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 60505-4130-07?
What is the difference between NDC 60505-4130-07 and NDC 60505-4130-05?
What NDC number is used to bill for this package of OXCARBAZEPINE 600 mg Tablet, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Oxcarbazepine extended-release tablets are indicated for the treatment of partial-onset seizures in patients 6 years of age and older. Oxcarbazepine extended-release tablets are indicated for the treatment of partial-onset seizures in patients 6 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult Patients: The recommended initial dosage is 600 mg once per day. Increase the dosage in weekly increments of 600 mg once per day, based on clinical response and tolerability, to a recommended maintenance dosage of 1,200 mg to 2,400 mg once per day. ( 2.2 ) In adult patients with a creatinine clearance <30 mL/min, initiate at one-half the usual starting dosage and increase slowly.
( 2.3 ) Pediatric Patients: The recommended dosage is based on body weight and is administered orally once per day. Increase the dosage in weekly intervals based on clinical response and tolerability, to the recommended dosage. ( 2.2 ) Geriatric Patients: Start at lower dosage (300 mg or 450 mg/day) and increase slowly.
( 2.4 ) In conversion of oxcarbazepine immediate-release to oxcarbazepine extended-release tablets, higher dosages of oxcarbazepine extended-release tablets may be necessary. ( 2.7 , 12.3 )
2.1Important Administration Instructions Administer oxcarbazepine extended-release tablets as a single daily dose taken on an empty stomach (at least 1 hour before or at least 2 hours after meals) [see Clinical Pharmacology ( 12.3 )] . If oxcarbazepine extended-release tablets are taken with food, adverse reactions are more likely to occur because of increased peak levels [see Clinical Pharmacology ( 12.3 )]. Swallow oxcarbazepine extended-release tablets whole.
Do not cut, crush, or chew the tablets. For ease of swallowing in pediatric patients or patients with difficulty swallowing, achieve daily dosages with multiples of appropriate lower strength tablets (e.g., 150 mg tablets).
2.2General Dosing Recommendations Monotherapy or Adjunctive Therapy Adult Patients Initiate treatment at a dosage of 600 mg/day given orally once daily for one week. Subsequent dosage increases can be made at weekly intervals in 600 mg/day increments to achieve the recommended daily dosage. The recommended daily dosage of oxcarbazepine extended-release tablets is 1,200 mg to 2,400 mg/day, given once daily.
The dosage of 2,400 mg/day showed slightly greater efficacy than 1,200 mg/day, but was associated with an increase in adverse reactions [see Adverse Reactions ( 6.1 ) and Clinical Studies ( 14.1 )] . Dosage adjustment is recommended with concomitant use of strong CYP3A4 enzyme inducers or UGT inducers, which include certain antiepileptic drugs (AEDs) [see Drug Interactions ( 7.1 , 7.2 )]. Pediatric Patients (6 to Less than 17 Years of Age) In pediatric patients 6 to less than 17 years of age, initiate treatment at a daily dosage of 8 mg/kg to 10 mg/kg orally once daily, not to exceed 600 mg per day in the first week.
Subsequent dosage increases can be made at weekly intervals in 8 mg/kg to 10 mg/kg increments once daily, not to exceed 600 mg, to achieve the target daily dosage. The target maintenance dosage, achieved over two to three weeks, is displayed in Table 1. Table 1: Target Daily Dosage in Pediatric Patients (6 to Less Than 17 Years of Age) Weight Target Daily Dosage 20 kg to 29 kg 900 mg/day 29.1 kg to 39 kg 1,200 mg/day Greater than 39 kg 1,800 mg/day Dosage adjustment is recommended with concomitant use of strong CYP3A4 enzyme inducers or UGT inducers, which include certain antiepileptic drugs (AEDs) [see Drug Interactions ( 7.1 , 7.2 )].
2.3Dosage Modifications in Adult Patients with Renal Impairment In adult patients with severe renal impairment (creatinine clearance less than 30 mL/minute), initiate oxcarbazepine extended-release tablets at one-half the usual starting dosage (300 mg/day). Subsequent dosage increases can be made at weekly intervals in increments of 300 mg to 450 mg/day to achieve the desired clinical response [see Use in Specific Populations ( 8.6 )].
2.4Dosage Modifications in Geriatric Patients In geriatric patients, consider starting at a lower dosage (300 mg or 450 mg/day). Subsequent dosage increases can be made at weekly intervals in increments of 300 mg to 450 mg/day to achieve the desired clinic…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Extended-release tablets : 150 mg: Yellow, oval, biconvex film-coated tablet. Engraved “OX150” on one side, “APO” on the other side. 300 mg: Brown, oval, biconvex film-coated tablet. Engraved “OX300” on one side, “APO” on the other side. 600 mg: Brownish red, oval, biconvex film-coated tablet. Engraved “OX600” on one side, “APO” on the other side. Extended-release tablets: 150 mg, 300 mg and 600 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Oxcarbazepine extended-release tablets are contraindicated in patients with a known hypersensitivity to oxcarbazepine, to any of the components of oxcarbazepine extended-release tablets, or to eslicarbazepine acetate. Reactions have included anaphylaxis and angioedema [see Warnings and Precautions ( 5.2 , 5.3 )]. Known hypersensitivity to oxcarbazepine, any of the components of oxcarbazepine extended-release tablets, or to eslicarbazepine acetate.
( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hyponatremia : Monitor sodium as recommended. ( 5.1 ) Cross Hypersensitivity Reaction to Carbamazepine: Discontinue immediately if hypersensitivity occurs. ( 5.3 ) Serious Dermatological Reactions: Discontinue if observed.
( 5.4 ) Suicidal Behavior and Ideation: Monitor for symptoms. ( 5.5 ) Withdrawal of oxcarbazepine extended-release tablets: Withdrawal gradually. ( 5.6 ) Drug Reaction with Eosinophilia and Systemic symptoms (DRESS)/Multi-Organ Hypersensitivity: Discontinue if suspected.
( 5.7 ) Hematologic Reactions: Discontinue if suspected. ( 5.8 ) Risk of Seizure Aggravation: Discontinue if occurs. ( 5.10 )
5.1Hyponatremia Clinically significant hyponatremia (sodium <125 mmol/L) may develop during oxcarbazepine extended-release tablets use. Serum sodium levels less than 125 mmol/L have occurred in immediate-release oxcarbazepine-treated patients generally in the first three months of treatment. However, clinically significant hyponatremia may develop more than a year after initiating therapy.
Most immediate-release oxcarbazepine-treated patients who developed hyponatremia were asymptomatic in clinical trials. However, some of these patients had their dosage reduced, discontinued, or had their fluid intake restricted for hyponatremia. Serum sodium levels returned toward normal when the dosage was reduced or discontinued, or when the patient was treated conservatively (e.g., fluid restriction).
Cases of symptomatic hyponatremia and syndrome of inappropriate antidiuretic hormone secretion (SIADH) have been reported during post-marketing use of immediate-release oxcarbazepine. Among treated patients in a controlled trial of adjunctive therapy with oxcarbazepine extended-release tablets in 366 adults with complex partial seizures, 1 patient receiving 2,400 mg experienced a severe reduction in serum sodium (117 mEq/L) requiring discontinuation from treatment, while 2 other patients receiving 1,200 mg experienced serum sodium concentrations low enough (125 and 126 mEq/L) to require discontinuation from treatment.
The overall incidence of clinically significant hyponatremia in patients treated with oxcarbazepine extended-release tablets was 1.2%, although slight shifts in serum sodium concentrations from Normal to Low (<135 mEq/L) were observed for the 2,400 mg (6.5%) and 1,200 mg (9.8%) groups compared to placebo (1.7%). Measure serum sodium concentrations if patients develop symptoms of hyponatremia (e.g., nausea, malaise, headache, lethargy, confusion, obtunded consciousness, or increase in seizure frequency or severity). Consider measurement of serum sodium concentrations during treatment with oxcarbazepine extended-release tablets, particularly if the patient receives concomitant medications known to decrease serum sodium levels (for example, drugs associated with inappropriate ADH secretion).
5.2Anaphylactic Reactions and Angioedema Rare cases of anaphylaxis and angioedema involving the larynx, glottis, lips and eyelids have been reported in patients after taking the first or subsequent doses of immediate-release oxcarbazepine. Angioedema associated with laryngeal edema can be fatal. If a patient develops any of these reactions after treatment with oxcarbazepine extended-release tablets, discontinue the drug and initiate an alternative treatment.
Do not rechallenge these patients with oxcarbazepine extended-release tablets.
5.3Cross Hypersensitivity Reaction to Carbamazepine Approximately 25% to 30% of patients who have had hypersensitivity reactions to carbamazepine will experience hypersensitivity reactions with oxcarbazepine extended-release tablets. For this reason, patients should be specifically questioned about any prior experience with carbamazepine, and patients with a history of hypersensitivity reactions to carbamazepine should ordinarily be treated with oxcarbazepine extended-release tablets only if the potential benefit justifies the potential risk.
Discontinue oxcarbazepine exten…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described in other sections of the labeling: Hyponatremia [see Warnings and Precautions ( 5.1 )] Anaphylactic Reactions and Angioedema [see Warnings and Precautions ( 5.2 )] Cross Hypersensitivity Reaction to Carbamazepine [see Warnings and Precautions ( 5.3 )] Serious Dermatological Reactions [see Warnings and Precautions ( 5.4 )] Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.5 )] Withdrawal of AEDs [see Warnings and Precautions ( 5.6 )] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multi-Organ Hypersensitivity [see Warnings and Precautions ( 5.7 )] Hematologic Reactions [see Warnings and Precautions ( 5.8 )] Risk of Seizures in the Pregnant Patient [see Warnings and Precautions ( 5.9 )] Most commonly observed (≥5% and more frequent than placebo) adverse reactions in adults were dizziness, somnolence, headache, balance disorder, tremor, vomiting, diplopia, asthenia, and fatigue.
( 6.1 ) Adverse reactions in pediatric patients are similar to those seen in adult patients. To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or contact FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The safety data presented below are from 384 patients with partial-onset seizures who received oxcarbazepine extended-release tablets (366 adults and 18 pediatric patients) with concomitant AEDs. In addition, safety data presented below are from a total of 2,288 patients with seizure disorders treated with immediate-release oxcarbazepine; 1,832 were adults and 456 were pediatric patients.
Most Common Adverse Reactions Reported by Adult Patients Receiving Concomitant AEDs in Oxcarbazepine Extended-Release Tablets Clinical Studies Table 3 lists adverse reactions that occurred in at least 2% of adult patients with epilepsy treated with oxcarbazepine extended-release tablets or placebo and concomitant AEDs and that were numerically more common in the patients treated with any dosage of oxcarbazepine extended-release tablets than in patients receiving placebo. Table 3: Adverse Reaction Incidence in a Controlled Clinical Study of Oxcarbazepine Extended-Release Tablets with Concomitant AEDs in Adults* Oxcarbazepine extended-release tablets 2,400 mg/day N=123 % Oxcarbazepine extended-release tablets 1,200 mg/day N=122 % Placebo N=121 % Any System / Any Term 69 57 55 Nervous System Disorders Dizziness 41 20 15 Somnolence 14 12 9 Headache 15 8 7 Balance Disorder 7 5 5 Tremor 1 5 2 Nystagmus 3 3 1 Ataxia 1 3 1 Gastrointestinal Disorders Vomiting 15 6 9 Abdominal Pain Upper 0 3 1 Dyspepsia 0 3 1 Gastritis 0 3 2 Eye Disorders Diplopia 13 10 4 Vision Blurred 1 4 3 Visual Impairment 1 3 0 General Disorders and Administration Site Conditions Asthenia 7 3 1 Fatigue 3 6 1 Gait Disturbance 0 3 1 Drug Intolerance 2 0 0 Infections and Infestations Nasopharyngitis 0 3 0 Sinusitis 0 3 2 * Reported by ≥ 2% of patients treated with oxcarbazepine extended-release tablets and numerically more frequent than in the placebo group The overall incidence of adverse reactions appeared to be dose related, particularly during the titration period.
The most commonly observed (≥5%) adverse reactions seen in association with oxcarbazepine extended-release tablets and more frequent than in placebo-treated patients were: dizziness, somnolence, headache, balance disorder, tremor, vomiting, diplopia, and asthenia. Adverse Reactions Associated with Discontinuation of Oxcarbazepine Extended-Release Tablets Treatment: Approximately 23.3% of the 366 adult patients receiving oxcarbazepine extended-release tablets in clinical studies discontinued treatment because of an adverse re…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Phenytoin, Carbamazepine, and Phenobarbital: Coadministration decreased blood levels of an active metabolite of oxcarbazepine extended-release tablets: Greater dosage of oxcarbazepine extended-release tablets may be required. ( 2.5 , 7.2 ) Oral Contraceptives: Advise patients that oxcarbazepine extended-release tablets may decrease the effectiveness of hormonal contraceptives. Additional non-hormonal forms of contraception are recommended.
( 7.3 )
7.1Effect of Oxcarbazepine Extended-Release Tablets on Other Drugs It is recommended that the plasma levels of phenytoin be monitored during the period of oxcarbazepine extended-release tablets titration and dosage modification [see Clinical Pharmacology ( 12.3 )] . A decrease in the dosage of phenytoin may be required.
7.2Effect of Other Drugs on Oxcarbazepine Extended-Release Tablets If oxcarbazepine extended-release tablets and strong CYP3A4 inducers or UGT inducers (e.g., rifampin, carbamazepine, phenytoin and phenobarbital) are administered concurrently, it is recommended that the plasma levels of MHD be monitored during the period of oxcarbazepine extended-release tablets titration [see Clinical Pharmacology ( 12.3 )] . Dosage adjustment of oxcarbazepine extended-release tablets may be required after initiation, dosage modification, or discontinuation of such inducers [see Dosage and Administration ( 2.5 )].
7.3Hormonal Contraceptives Concurrent use of immediate-release oxcarbazepine with hormonal contraceptives may render these contraceptives less effective [see Clinical Pharmacology ( 12.3 )] . Studies with other oral or implant contraceptives have not been conducted.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: May cause fetal harm. ( 5.9 , 8.1 ) Severe Hepatic Impairment: Not recommended. ( 8.7 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as oxcarbazepine extended-release tablets, during pregnancy. Encourage women who are taking oxcarbazepine extended-release tablets during pregnancy to enroll in the North American Antiepileptic Drug (NAAED Pregnancy Registry) by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/ . Risk Summary There are no adequate data on the developmental risks associated with the use of oxcarbazepine extended-release tablets in pregnant women; however, oxcarbazepine extended-release tablets are closely related structurally to carbamazepine, which is considered to be teratogenic in humans.
Data on a limited number of pregnancies from pregnancy registries suggest that oxcarbazepine monotherapy use is associated with congenital malformations (e.g., craniofacial defects such as oral clefts, and cardiac malformations such as ventricular septal defects). Increased incidences of fetal structural abnormalities and other manifestations of developmental toxicity (embryolethality, growth retardation) were observed in the offspring of animals treated with either oxcarbazepine or its active 10-hydroxy metabolite (MHD) during pregnancy at doses similar to the maximum recommended human dose (MRHD).
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Clinical Considerations An increase in seizure frequency may occur during pregnancy because of altered levels of the active metabolite of oxcarbazepine.
Monitor patients carefully during pregnancy and through the postpartum period [see Warnings and Precautions ( 5.9 )] Data Human Data Data from published registries have reported craniofacial defects such as oral clefts and cardiac malformations such as ventricular septal defects in children with prenatal oxcarbazepine exposure. Animal Data When pregnant rats were given oxcarbazepine (30, 300, or 1,000 mg/kg/day) orally throughout the period of organogenesis, increased incidences of fetal malformations (craniofacial, cardiovascular, and skeletal) and variations were observed at the intermediate and high doses (approximately 1.2 and 4 times, respectively, the MRHD on a mg/m 2 basis).
Increased embryofetal death and decreased fetal body weights were seen at the high dose. Doses ≥ 300 mg/kg were also maternally toxic (decreased body weight gain, clinical signs), but there is no evidence to suggest that teratogenicity was secondary to the maternal effects. In a study in which pregnant rabbits were orally administered MHD (20, 100, or 200 mg/kg/day) during organogenesis, embryofetal mortality was increased at the highest dose (1.5 times the MRHD on a mg/m 2 basis).
This dose produced only minimal maternal toxicity. In a study in which female rats were dosed orally with oxcarbazepine (25, 50, or 150 mg/kg/day) during the latter part of gestation and throughout the lactation period, a persistent reduction in body weights and altered behavior (decreased activity) were observed in offspring exposed to the highest dose (0.6 times the MRHD on a mg/m 2 basis). Oral administration of MHD (25, 75, or 250 mg/kg/day) to rats during gestation and lactation resulted in a persistent reduction in offspring weights at the highest dose (equivalent to the MRHD on a mg/m 2 basis).
8.2Lactation Risk Summary Oxcarbazepine and its active metabolite (MHD) are present in human milk after oxcarbazepine administration. The effects of oxcarbazepine and its active metabolite (MHD) on the breastfed infant or on milk production are unknown. The developmental and health benefits of br…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as oxcarbazepine extended-release tablets, during pregnancy. Encourage women who are taking oxcarbazepine extended-release tablets during pregnancy to enroll in the North American Antiepileptic Drug (NAAED Pregnancy Registry) by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/ . Risk Summary There are no adequate data on the developmental risks associated with the use of oxcarbazepine extended-release tablets in pregnant women; however, oxcarbazepine extended-release tablets are closely related structurally to carbamazepine, which is considered to be teratogenic in humans.
Data on a limited number of pregnancies from pregnancy registries suggest that oxcarbazepine monotherapy use is associated with congenital malformations (e.g., craniofacial defects such as oral clefts, and cardiac malformations such as ventricular septal defects). Increased incidences of fetal structural abnormalities and other manifestations of developmental toxicity (embryolethality, growth retardation) were observed in the offspring of animals treated with either oxcarbazepine or its active 10-hydroxy metabolite (MHD) during pregnancy at doses similar to the maximum recommended human dose (MRHD).
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown. Clinical Considerations An increase in seizure frequency may occur during pregnancy because of altered levels of the active metabolite of oxcarbazepine.
Monitor patients carefully during pregnancy and through the postpartum period [see Warnings and Precautions ( 5.9 )] Data Human Data Data from published registries have reported craniofacial defects such as oral clefts and cardiac malformations such as ventricular septal defects in children with prenatal oxcarbazepine exposure. Animal Data When pregnant rats were given oxcarbazepine (30, 300, or 1,000 mg/kg/day) orally throughout the period of organogenesis, increased incidences of fetal malformations (craniofacial, cardiovascular, and skeletal) and variations were observed at the intermediate and high doses (approximately 1.2 and 4 times, respectively, the MRHD on a mg/m 2 basis).
Increased embryofetal death and decreased fetal body weights were seen at the high dose. Doses ≥ 300 mg/kg were also maternally toxic (decreased body weight gain, clinical signs), but there is no evidence to suggest that teratogenicity was secondary to the maternal effects. In a study in which pregnant rabbits were orally administered MHD (20, 100, or 200 mg/kg/day) during organogenesis, embryofetal mortality was increased at the highest dose (1.5 times the MRHD on a mg/m 2 basis).
This dose produced only minimal maternal toxicity. In a study in which female rats were dosed orally with oxcarbazepine (25, 50, or 150 mg/kg/day) during the latter part of gestation and throughout the lactation period, a persistent reduction in body weights and altered behavior (decreased activity) were observed in offspring exposed to the highest dose (0.6 times the MRHD on a mg/m 2 basis). Oral administration of MHD (25, 75, or 250 mg/kg/day) to rats during gestation and lactation resulted in a persistent reduction in offspring weights at the highest dose (equivalent to the MRHD on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of oxcarbazepine extended-release tablets in pediatric patients 6 years of age and older for the treatment of partial-onset seizures is supported by: 1) An adequate and well-controlled safety and efficacy study of oxcarbazepine extended-release tablets in adults that included pharmacokinetic sampling [see Clinical Studies ( 14.1 )] , 2) A pharmacokinetic study of oxcarbazepine extended-release tablets in pediatric patients, which included patients 6 to less than 17 years of age [see Clinical Pharmacology ( 12.3 )] , 3) Safety and efficacy studies with the immediate-release formulation in adults and pediatric patients [see Clinical Studies ( 14.2 ) and Adverse Reactions ( 6.1 )] .
Oxcarbazepine extended-release tablets is not approved for pediatric patients less than 6 years of age because the size of the tablets are inappropriate for younger children.
🧓 Geriatric Use ▾
8.5Geriatric Use Following administration of single (300 mg) and multiple (600 mg/day) doses of immediate-release oxcarbazepine to elderly volunteers (60 to 82 years of age), the maximum plasma concentrations and AUC values of MHD were 30% to 60% higher than in younger volunteers (18 to 32 years of age). Comparisons of creatinine clearance in young and elderly volunteers indicate that the difference was due to age-related reductions in creatinine clearance. Consider starting at a lower dosage and lower titration [see Dosage and Administration ( 2.4 )] .
Close monitoring of sodium levels is required in elderly patients at risk for hyponatremia [see Warnings and Precautions ( 5.1 )] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Overdose Experience Isolated cases of overdose with immediate-release oxcarbazepine have been reported. The maximum dose taken was approximately 48,000 mg. All patients recovered with symptomatic treatment.
Nausea, vomiting, somnolence, aggression, agitation, hypotension, and tremor each occurred in more than one patient. Coma, confusional state, convulsion, dyscoordination, depressed level of consciousness, diplopia, dizziness, dyskinesia, dyspnea, QT prolongation, headache, miosis, nystagmus, overdose, decreased urine output, and blurred vision also occurred.
10.2Treatment and Management There is no specific antidote for oxcarbazepine extended-release tablets overdose. Administer symptomatic and supportive treatment as appropriate. Options include removal of the drug by gastric lavage and/or inactivation by administering activated charcoal.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The pharmacological activity of oxcarbazepine extended-release tablets are primarily exerted through the 10-monohydroxy metabolite (MHD) of oxcarbazepine [see Clinical Pharmacology ( 12.3 )] . The precise mechanism by which oxcarbazepine and MHD exert their antiseizure effect is unknown; however, in vitro electrophysiological studies indicate that they produce blockade of voltage-sensitive sodium channels, resulting in stabilization of hyperexcited neural membranes, inhibition of repetitive neuronal firing, and diminution of propagation of synaptic impulses.
These actions are thought to be important in the prevention of seizure spread in the intact brain. In addition, increased potassium conductance and modulation of high-voltage activated calcium channels may contribute to the anticonvulsant effects of the drug. No significant interactions of oxcarbazepine or MHD with brain neurotransmitter or modulator receptor sites have been demonstrated.
12.2Pharmacodynamics Oxcarbazepine and its active metabolite (MHD) exhibit anticonvulsant properties in animal seizure models. They protected rodents against electrically induced tonic extension seizures and, to a lesser degree, chemically induced clonic seizures, and abolished or reduced the frequency of chronically recurring focal seizures in Rhesus monkeys with aluminum implants. No development of tolerance (i.e., attenuation of anticonvulsive activity) was observed in the maximal electroshock test when mice and rats were treated daily for five days and four weeks, respectively, with oxcarbazepine or MHD.
12.3Pharmacokinetics Following oral administration, oxcarbazepine is absorbed and extensively metabolized to its pharmacologically active 10-monohydroxy metabolite (MHD), which is responsible for most antiepileptic activity. In clinical studies of oxcarbazepine extended-release tablets, the elimination half-life of oxcarbazepine was between 7 and 11 hours; the elimination half-life of MHD is between 9 and 11 hours. In a mass balance study in humans, only 2% of total radioactivity in plasma after administration of immediate-release oxcarbazepine was due to unchanged oxcarbazepine, with approximately 70% present as MHD, and the remainder attributable to minor metabolites.
Absorption Oxcarbazepine extended-release tablets administered as a once daily dosage is not bioequivalent to the same total dosage of the immediate-release formulation given twice daily at steady state. Steady state plasma concentrations of MHD are reached within 5 days when oxcarbazepine extended-release tablets are given once daily. At steady state, when 1,200 mg oxcarbazepine extended-release tablets were given once daily, MHD C max occurred 7 hours post-dose.
At steady state, oxcarbazepine extended-release tablets given once daily produced MHD exposures (AUC and C max ) about 19% lower and MHD minimum concentrations (C min ) about 16% lower than the immediate-release oxcarbazepine given twice daily when administered at the same 1,200 mg total daily dosage. When oxcarbazepine extended-release tablets were administered at an equivalent 600 mg single dose (4 x 150 mg tablets, 2 x 300 mg tablets, or 1 x 600 mg tablet), equivalent MHD exposures (AUC) were observed. Following a single dose of oxcarbazepine extended-release tablets (1 x 150 mg tablets, 1 x 300 mg tablets, or 1 x 600 mg tablet), the pharmacokinetics of MHD are not linear and show greater than dose proportional increase in AUC and less than proportional increase in C max : AUC increases 2.4-fold and C max increases 1.9-fold with a 2-fold increase in dose.
Effect of Food : Single dose administration of 600 mg oxcarbazepine extended-release tablets following a high fat meal (800 to 1,000 calories) produced MHD exposure (AUC) equivalent to that produced under fasting conditions. Peak MHD concentration (C max ) was about 60% higher and occurred 2 hours earlier under fed conditions than under fasting condition…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The pharmacological activity of oxcarbazepine extended-release tablets are primarily exerted through the 10-monohydroxy metabolite (MHD) of oxcarbazepine [see Clinical Pharmacology ( 12.3 )] . The precise mechanism by which oxcarbazepine and MHD exert their antiseizure effect is unknown; however, in vitro electrophysiological studies indicate that they produce blockade of voltage-sensitive sodium channels, resulting in stabilization of hyperexcited neural membranes, inhibition of repetitive neuronal firing, and diminution of propagation of synaptic impulses.
These actions are thought to be important in the prevention of seizure spread in the intact brain. In addition, increased potassium conductance and modulation of high-voltage activated calcium channels may contribute to the anticonvulsant effects of the drug. No significant interactions of oxcarbazepine or MHD with brain neurotransmitter or modulator receptor sites have been demonstrated.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied 150 mg: Yellow, oval, biconvex film-coated tablet. Engraved “OX150” on one side, “APO” on the other side. Bottles of 100 tablets with child-resistant closure..…………………… NDC 60505-4128-7 Bottles of 500 tablets……………………………………………………NDC 60505-4128-5 300 mg: Brown, oval, biconvex film-coated tablet.
Engraved “OX300” on one side, “APO” on the other side. Bottles of 100 tablets with child-resistant closure ………………….. NDC 60505-4129-7 Bottles of 500 tablets………………………………………………….
NDC 60505-4129-5 600 mg: Brownish red, oval, biconvex film-coated tablet. Engraved “OX600” on one side, “APO” on the other side. Bottles of 100 tablets with child-resistant closure………………… NDC 60505-4130-7 Bottles of 500 tablets……………………………………………….
NDC 60505-4130-5
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [See USP controlled room temperature]. Protect from light and moisture. Dispense in a tight, light-resistant container.
📋 Description ▾
11 DESCRIPTION Oxcarbazepine extended-release tablet is an antiepileptic drug (AED). Oxcarbazepine extended-release tablets contain oxcarbazepine, USP for once-a-day oral administration. Oxcarbazepine, USP is 10,11-Dihydro-10-oxo- 5H -dibenz[ b,f ]azepine-5-carboxamide, and its structural formula is Oxcarbazepine is light orange to creamish white or off-white powder.
Oxcarbazepine is soluble in acetic acid, sparingly soluble in chloroform and practically insoluble in water. The molecular formula is C 15 H 12 N 2 O 2 and its molecular weight is 252.27 g/mol. Oxcarbazepine extended-release tablets contain the following inactive ingredients: colloidal silicon dioxide, ferric oxide red (300 mg, 600 mg tablets only), ferric oxide yellow (150 mg, 300 mg tablets only), hydroxypropyl methyl cellulose, iron oxide black (300 mg tablet only), magnesium stearate, polyethylene glycol, polyvinyl alcohol, sorbitol, talc, titanium dioxide (300 mg, 600 mg tablets only).
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-Approved patient labeling (Medication Guide). Administration Information Advise patients to take the tablet whole. Do not cut, chew, or crush the tablet.
Advise patients to take oxcarbazepine extended-release tablets on an empty stomach. This means they should take oxcarbazepine extended-release tablets at least one hour before food or at least two hours after food [see Dosage and Administration (2.1) and Clinical Pharmacology (12.3)]. Hyponatremia Advise patients that oxcarbazepine extended-release tablets may reduce serum sodium concentrations especially if they are taking other medications that can lower sodium.
Advise patients to report symptoms of low sodium like nausea, tiredness, lack of energy, confusion, and more frequent or more severe seizures [see Warnings and Precautions (5.1)]. Anaphylactic Reactions and Angioedema Anaphylactic reactions and angioedema may occur during treatment with oxcarbazepine extended-release tablets. Advise patients to immediately report signs and symptoms suggesting angioedema (swelling of the face, eyes, lips, tongue, or difficulty in swallowing or breathing) and to stop taking the drug until they have consulted with their physician [see Warnings and Precautions (5.2)].
Cross Hypersensitivity Reaction to Carbamazepine Inform patients who have exhibited hypersensitivity reactions to carbamazepine that approximately 25% to 30% of these patients may also experience hypersensitivity reactions with oxcarbazepine extended-release tablets. If patients experience a hypersensitivity reaction while taking oxcarbazepine extended-release tablets, advise them to consult with their physician immediately [see Warnings and Precautions (5.3)] . Serious Dermatological Reactions Advise patients that serious skin reactions have been reported in association with immediate-release oxcarbazepine.
If patients experience a skin reaction while taking oxcarbazepine extended-release tablets, advise patients to consult with their physician immediately [see Warnings and Precautions (5.4)]. Suicidal Behavior and Ideation Counsel patients, their caregivers, and families that AEDs, including oxcarbazepine extended-release tablets, may increase the risk of suicidal thoughts and behavior and that they need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm.
Advise them to immediately report behaviors of concern to healthcare providers [see Warnings and Precautions (5.5)]. DRESS/Multi-Organ Hypersensitivity Instruct patients that a fever associated with signs of other organ system involvement (e.g., rash, lymphadenopathy, hepatic dysfunction, etc.) occurring during treatment with oxcarbazepine extended-release tablets may be drug-related, and advise them to consult their physician immediately [see Warnings and Precautions (5.7)]. Hematologic Reactions Advise patients that there have been rare reports of blood disorders reported in patients treated with immediate-release oxcarbazepine.
Instruct patients to immediately consult with their physician if they experience symptoms suggestive of blood disorders during treatment with oxcarbazepine extended-release tablets [see Warnings and Precautions (5.8)]. Drug Interactions Warn female patients of childbearing age that the concurrent use of oxcarbazepine extended-release tablets with hormonal contraceptives may render this method of contraception less effective [see Drug Interactions (7.3) and Use in Specific Populations (8.1)]. Additional non-hormonal forms of contraception are recommended when using oxcarbazepine extended-release tablets.
Pregnancy Registry Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during oxcarbazepine extended-release tablets therapy. Encourage patients to enroll in the North American Antiepilepti…
💬 Medication Guide ▾
MEDICATION GUIDE Oxcarbazepine (ox’’ kar baz’ e peen) extended-release tablets, for oral use Medication Guide available at https://www.apotex.com/products/us/mg.asp What is the most important information I should know about oxcarbazepine extended-release tablets? Do not stop taking oxcarbazepine extended-release tablets without first talking to your healthcare provider. Stopping oxcarbazepine extended-release tablets suddenly can cause serious problems.
Oxcarbazepine extended-release tablets can cause serious side effects, including: 1. Oxcarbazepine extended-release tablets may cause the level of sodium in your blood to be low. Symptoms of low blood sodium include: nausea tiredness, lack of energy headache confusion more frequent or more severe seizures Similar symptoms that are not related to low sodium may occur from taking oxcarbazepine extended-release tablets.
You should tell your healthcare provider if you have any of these side effects and if they bother you or they do not go away. Some other medicines can also cause low sodium in your blood. Be sure to tell your healthcare provider about all the other medicines that you are taking.
Your healthcare provider may do blood tests to check your sodium levels during your treatment with oxcarbazepine extended-release tablets . 2. Oxcarbazepine extended-release tablets may also cause allergic reactions or serious problems which may affect organs and other parts of your body like the liver or blood cells.
You may or may not have a rash with these types of reactions. Call your healthcare provider right away if you have any of the following: swelling of your face, eyes, lips, or tongue trouble swallowing or breathing a skin rash hives fever, swollen glands, or sore throat that does not go away or comes and goes painful sores in the mouth or around your eyes yellowing of your skin or eyes unusual bruising or bleeding severe fatigue or weakness severe muscle pain frequent infections that do not go away Many people who are allergic to carbamazepine are also allergic to oxcarbazepine extended-release tablets.
Tell your healthcare provider if you are allergic to carbamazepine. 3. Like other antiepileptic drugs, oxcarbazepine extended-release tablets may cause suicidal thoughts or actions in a very small number of people, about 1 in 500.
Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Do not stop taking oxcarbazepine extended-release tablets without first talking to a healthcare provider. Stopping oxcarbazepine extended-release tablets suddenly can cause serious problems. Stopping a seizure medicine suddenly in a patient who has epilepsy may cause seizures that will not stop (status epilepticus).
Suicidal thoughts or actions may be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes. What is oxcarbazepine extended-release tablets?
Oxcarbazepine extended-release tablets are a prescription medicine used to treat partial onset seizures in adults and children 6 years of age and older. Oxcarbazepine extended-release tablets are not for use in children under 6 years of age. It is not known if oxcarbazepine extended-release tablets are safe an…