
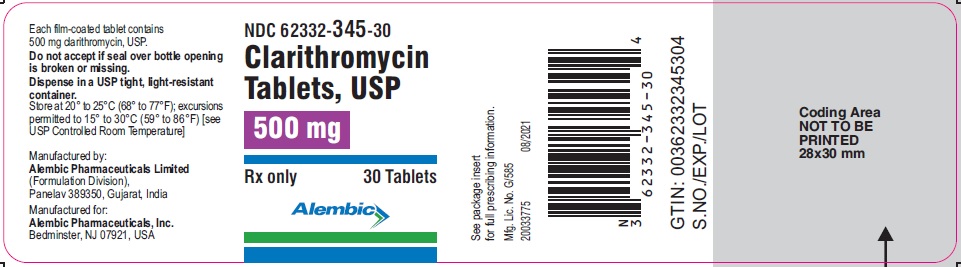
Clarithromycin 500 mg Tablet, Film Coated, 30-count — NDC 62332-345-30 (Billing 62332-0345-30)
This is a package of 30 tablets of Clarithromycin 500 mg Tablet, Film Coated from Alembic Pharmaceuticals Inc., marketed since Feb 2022 and currently FDA-listed.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 016368
- GCN: 48851
- GPI-14 (Medi-Span): 03500010000320
- HICL (First Databank): 006228
- AHFS class code: 08:12.12.08
- RxCUI (RxNorm): 197516
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Macrolide Antimicrobial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Clarithromycin is used to treat certain bacterial infections. treat and prevent disseminated Mycobacterium avium complex (MAC) infection [a type of lung infection that affects people with a weakened immune system. eliminate H. pylori, a bacterium that causes ulcers. Clarithromycin is in a class of medications called macrolide antibiotics. It works by stopping the growth of bacteria. Antibiotics such as clarithromycin will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibioti...
Read the full MedlinePlus article ↗- It is an antibiotic for mild to moderate bacterial infections, such as bronchitis flare-ups, sinus infections, pneumonia, throat, skin and ear infections. Some forms are also used...
- Take it by mouth exactly as your prescriber directed. Tablets can be taken with or without food. Extended-release tablets should be taken with food and swallowed whole. Finish the...
- Stomach upset, nausea, vomiting, diarrhea, belly pain, headache and a strange taste in your mouth are the most common. Call your doctor if you get a severe rash, yellow skin or eye...
- It interacts with many drugs, so give me your full list. Some, like simvastatin, lovastatin, colchicine in certain people, and pimozide, should not be combined with it. Blood thinn...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Clarithromycin — tap one for details:
Clarithromycin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.6937 | $20.81 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 62332-0345-30 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE | — | — | 2022-02-01 | — | Active |
| 62332-0345-60 62332-345-60 Main listing | 60 TABLET, FILM COATED in 1 BOTTLE | $0.4658 / ea | $27.95 | 2022-02-01 | — | Active |
| 62332-0345-91 62332-345-91 | 1000 TABLET, FILM COATED in 1 BOTTLE | — | — | 2022-02-01 | — | Active |
You're viewing the smallest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 62332-0345-60?
What NDC number is used to bill for this package of Clarithromycin 500 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clarithromycin 500 mg 00527-1932-06 | Lannett | 60 tablets | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 00904-6872-04 | Major | 1 tablet | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 50268-0179-13 | AvPAK | 1 tablet | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 57237-0045-60 | Rising | 60 tablets | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 60687-0435-21 | American | 1 tablet | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 62135-0615-60 | Chartwell | 60 tablets | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 68002-0104-04 | American | 1 tablet | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 73473-0910-60 | Solaris | 60 tablets | $0.466 | AB | Availability likely | — |
| Clarithromycin 500 mg 00781-1962-60 | Sandoz | 60 tablets | $0.488 | AB | Availability likely | — |
| Clarithromycin 500 mg 43063-0530-14 | PD-Rx | 14 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 43063-0752-14 | PD-Rx | 14 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 43063-0823-20 | PD-Rx | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 46708-0345-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 50090-1830-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 50090-5282-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 51655-0668-20 | Northwind | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mgthis 62332-0345-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 63187-0376-20 | Proficient | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 63187-0625-14 | Proficient | 14 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 65862-0226-10 | Aurobindo | 10 tablets | — | — | FDA listed | — |
| Clarithromycin 500 mg 67046-1515-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 68071-3116-02 | NuCare | 20 tablets | — | AB | Discontinued | — |
| Clarithromycin 500 mg 68071-5045-02 | NuCare | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 68788-8480-02 | Preferred | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 70518-0204-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 71335-0017-01 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 71335-1493-01 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 72189-0299-20 | DirectRx | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 72189-0639-10 | Direct_Rx | 10 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 76420-0051-14 | Asclemed | 14 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 82804-0069-20 | Proficient | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 82804-0141-14 | Proficient | 14 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 82868-0085-20 | Northwind | 20 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 85766-0198-01 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
| Clarithromycin 500 mg 85766-0203-01 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII CQ3XH3DET6
D&C Yellow No. 10 Aluminum Lake is a yellow colorant made by combining a dye with aluminum salts. It's used in medicines to add color for product identification and visual appeal.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII CHI530446X
Vanillin is a natural or synthetic aromatic compound that gives vanilla flavor. It's used in medicines as a flavoring agent to mask bitter tastes and improve how the medicine tastes.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Clarithromycin tablets are a macrolide antimicrobial indicated for mild to moderate infections caused by designated, susceptible bacteria in the following: • Acute Bacterial Exacerbation of Chronic Bronchitis in Adults (1.1) • Acute Maxillary Sinusitis (1.2) • Community-Acquired Pneumonia (1.3) • Pharyngitis/Tonsillitis (1.4) • Uncomplicated Skin and Skin Structure Infections (1.5) • Acute Otitis Media in Pediatric Patients (1.6) • Treatment and Prophylaxis of Disseminated Mycobacterial Infections (1.7) • Helicobacter pylori Infection and Duodenal Ulcer Disease in Adults (1.8) Limitations of Use To reduce the development of drug-resistant bacteria and maintain the effectiveness of clarithromycin tablets and other antibacterial drugs, clarithromycin tablets should be used only to treat or prevent infections that are proven or strongly suspected to be caused by bacteria.
(1.9)
1.1Acute Bacterial Exacerbation of Chronic Bronchitis Clarithromycin tablets, USP are indicated in adults for the treatment of mild to moderate infections caused by susceptible isolates due to Haemophilus influenzae , Haemophilus parainfluenzae , Moraxella catarrhalis , or Streptococcus pneumoniae [see Indications and Usage (1.9)] .
1.2Acute Maxillary Sinusitis Clarithromycin tablets, USP are indicated for the treatment of mild to moderate infections caused by susceptible isolates due to Haemophilus influenzae , Moraxella catarrhalis , or Streptococcus pneumoniae [see Indications and Usage (1.9)] .
1.3Community-Acquired Pneumonia Clarithromycin tablets, USP are indicated [see Indications and Usage (1.9)] for the treatment of mild to moderate infections caused by susceptible isolates due to: · Haemophilus influenzae (in adults) · Mycoplasma pneumoniae , Streptococcus pneumoniae , Chlamydophila pneumoniae
1.4Pharyngitis/Tonsillitis Clarithromycin tablets, USP are indicated for the treatment of mild to moderate infections caused by susceptible isolates due to Streptococcus pyogenes as an alternative in individuals who cannot use first line therapy.
1.5Uncomplicated Skin and Skin Structure Infections Clarithromycin tablets, USP are indicated for the treatment of mild to moderate infections caused by susceptible isolates due to Staphylococcus aureus , or Streptococcus pyogenes .
1.6Acute Otitis Media Clarithromycin tablets, USP are indicated in pediatric patients for the treatment of mild to moderate infections caused by susceptible isolates due to Haemophilus influenzae , Moraxella catarrhalis , or Streptococcus pneumoniae [see Clinical Studies (14.2)] .
1.7Treatment and Prophylaxis of Disseminated Mycobacterial Infections Clarithromycin tablets, USP are indicated for the treatment of mild to moderate infections caused by susceptible isolates due to Mycobacterium avium or Mycobacterium intracellulare in patients with advanced HIV infection [see Clinical Studies (14.1)] .
1.8Helicobacter pylori Infection and Duodenal Ulcer Disease Clarithromycin tablets, USP are given in combination with other drugs in adults as described below to eradicate H. pylori . The eradication of H. pylori has been demonstrated to reduce the risk of duodenal ulcer recurrence [see Clinical Studies (14.3)] . · Clarithromycin tablets, USP in combination with amoxicillin and PREVACID (lansoprazole) or PRILOSEC (omeprazole) Delayed-Release Capsules, as triple therapy, are indicated for the treatment of patients with H. pylori infection and duodenal ulcer disease (active or five-year history of duodenal ulcer) to eradicate H. pylori . · Clarithromycin tablets, USP in combination with PRILOSEC (omeprazole) capsules are indicated for the treatment of patients with an active duodenal ulcer associated with H. pylori infection.
Regimens which contain clarithromycin tablets, USP as the single antibacterial agent are more likely to be associated with the development of clarithromycin resistance among patients who fail therapy. Clarithromycin-containing regimens should… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Adults : Clarithromycin tablets 250 mg or 500 mg every 12 hours for 7 to 14 days (2.2) • H. pylori eradication (in combination with lansoprazole/amoxicillin, omeprazole/amoxicillin, or omeprazole): Clarithromycin tablets 500 mg every 8 or 12 hours for 10 to 14 days. See full prescribing information (FPI) for additional information. (2.3) • Pediatric Patients : Clarithromycin tablets 15 mg/kg/day divided every 12 hours for 10 days (2.4) • Mycobacterial Infections : Clarithromycin tablets 500 mg every 12 hours; clarithromycin tablets 7.5 mg/kg up to 500 mg every 12 hours in pediatric patients (2.5) • Reduce dose in moderate renal impairment with concomitant atazanavir or ritonavir-containing regimens and in severe renal impairment (2.6)
2.1Important Administration Instructions Clarithromycin tablets may be given with or without food.
2.2Adult Dosage The recommended dosages clarithromycin tablets for the treatment of mild to moderate infections in adults are listed in Table 1. Table 1. Adult Dosage Guidelines Clarithromycin Tablets Infection Dosage (every 12 hours) Duration (days) Acute bacterial exacerbation of chronic bronchitis 250 to 500 mg a 7 b to 14 Acute maxillary sinusitis 500 mg 14 Community-acquired pneumonia 250 mg c 7 d to 14 Pharyngitis/Tonsillitis 250 mg 10 Uncomplicated skin and skin structure infections 250 mg 7 to 14 Treatment and prophylaxis of disseminated Mycobacterium avium disease [see Dosage and Administration (2.5)] 500 mg e - H.pylori eradication to reduce the risk of duodenal ulcer recurrence with amoxicillin and omeprazole or lansoprazole [see Dosage and Administration (2.3)] 500 mg 10 to 14 H.pylori eradication to reduce the risk of duodenal ulcer recurrence with omeprazole [see Dosage and Administration (2.3)] 500 mg every 8 hours 14 a For M. catarrhalis and S. pneumoniae use 250 mg.
For H. influenzae and H. parainfluenzae , use 500 mg. b For H parainfluenzae , the duration of therapy is 7 days. d For H. influenzae , the duration of therapy is 7 days. e Clarithromycin tablets therapy should continue if clinical response is observed. Clarithromycin tablets can be discontinued when the patient is considered at low risk of disseminated infection.
2.3Combination Dosing Regimens for H. pylori Infection · Triple therapy: Clarithromycin /lansoprazole/amoxicillin The recommended adult dosage is 500 mg clarithromycin, 30 mg lansoprazole, and 1 gram amoxicillin, all given every 12 hours for 10 or 14 days [see Indications and Usage (1.8) and Clinical Studies (14.3)] . · Triple therapy: Clarithromycin/omeprazole/amoxicillin The recommended adult dosage is 500 mg clarithromycin, 20 mg omeprazole, and 1 gram amoxicillin; all given every 12 hours for 10 days. In patients with an ulcer present at the time of initiation of therapy, an additional 18 days of omeprazole 20 mg once daily is recommended for ulcer healing and symptom relief [see Indications and Usage (1.8) and Clinical Studies (14.3)] . · Dual therapy: Clarithromycin/omeprazole The recommended adult dosage is 500 mg clarithromycin given every 8 hours and 40 mg omeprazole given once every morning for 14 days.
An additional 14 days of omeprazole 20 mg once daily is recommended for ulcer healing and symptom relief [see Indications and Usage (1.8) and Clinical Studies (14.3)] .
2.4Pediatric Dosage The recommended daily dosage is 15 mg/kg/day divided every 12 hours for 10 days (up to the adult dose). Refer to dosage regimens for mycobacterial infections in pediatric patients for additional dosage information [see Dosage and Administration (2.5)] .
2.5Dosage Regimens for Mycobacterial Infections For the treatment of disseminated infection due to Mycobacterium avium complex (MAC), clarithromycin tablets are recommended as the primary agents. Clarithromycin tablets should be used in combination with other antimycobacterial drugs (e.g. ethambutol) that have shown in vitro activity against MAC or clinical benefit in MAC treatment [… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Clarithromycin tablets are available as: · 250 mg: Yellow oval film-coated tablets debossed with ‘L139’ on one side and plain on the other side. · 500 mg: Yellow oval film-coated tablets debossed with ‘L140’ on one side and plain on the other side. • Tablets : 250 mg and 500 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to clarithromycin or any macrolide drug (4.1) Cisapride, pimozide (4.2) History of cholestatic jaundice/hepatic dysfunction with use of clarithromycin (4.3) Colchicine in renal or hepatic impairment (4.4) Lomitapide, lovastatin, and simvastatin (4.5) Ergot alkaloids (ergotamine or dihydroergotamine) (4.6) Lurasidone (4.7)
4.1Hypersensitivity Clarithromycin tablets are contraindicated in patients with a known hypersensitivity to clarithromycin, erythromycin, or any of the macrolide antibacterial drugs [see Warnings and Precautions (5.1)] .
4.2Cisapride and Pimozide Concomitant administration of Clarithromycin tablets with cisapride and pimozide is contraindicated [see Drug Interactions (7)] . There have been postmarketing reports of drug interactions when clarithromycin is co administered with cisapride or pimozide, resulting in cardiac arrhythmias (QT prolongation, ventricular tachycardia, ventricular fibrillation, and torsades de pointes ) most likely due to inhibition of metabolism of these drugs by clarithromycin tablets. Fatalities have been reported.
4.3Cholestatic Jaundice/Hepatic Dysfunction Clarithromycin tablets are contraindicated in patients with a history of cholestatic jaundice or hepatic dysfunction associated with prior use of clarithromycin.
4.4Colchicine Concomitant administration of clarithromycin tablets and colchicine is contraindicated in patients with renal or hepatic impairment.
4.5Lomitapide, Lovastatin, and Simvastatin Concomitant administration of clarithromycin tablets with lomitapide is contraindicated due to potential for markedly increased transaminases [see Warnings and Precautions (5.4) and Drug Interactions (7)] . Concomitant administration of clarithromycin tablets with HMG-CoA reductase inhibitors (statins) that are extensively metabolized by CYP3A4 (lovastatin or simvastatin) is contraindicated, due to the increased risk of myopathy, including rhabdomyolysis [see Warnings and Precautions (5.4) and Drug Interactions (7)].
4.6Ergot Alkaloids Concomitant administration of clarithromycin and ergotamine or dihydroergotamine is contraindicated [see Drug Interactions (7)] .
4.7Lurasidone Concomitant administration of clarithromycin and lurasidone is contraindicated since it may result in an increase in lurasidone exposure and the potential for serious adverse reactions [see Drug Interactions (7)].
4.8Contraindications for Co-administered Drugs For information about contraindications of other drugs indicated in combination with clarithromycin tablets, refer to their full prescribing information (contraindications section).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Severe Acute Hypersensitivity Reactions : Discontinue clarithromycin tablets if occurs (5.1) QT Prolongation : Avoid clarithromycin tablets in patients with known QT prolongation or receiving drugs known to prolong the QT interval, ventricular arrhythmia ( torsades de pointes ), hypokalemia/hypomagnesemia, significant bradycardia, or taking Class IA or III antiarrhythmics (5.2) Hepatotoxicity : Discontinue if signs and symptoms of hepatitis occur (5.3) Serious adverse reactions can occur due to drug interactions of clarithromycin tablets with colchicine, some lipid-lowering agents, some calcium channel blockers, and other drugs (5.4) Risk of all-cause mortality one year or more after the end of treatment in patients with coronary artery disease.
Balance this potential risk with the treatment benefits when prescribing clarithromycin tablets in these patients. (5.5) Clostridium difficile associated diarrhea (CDAD) : Evaluate if diarrhea occurs (5.6) Embryo-Fetal Toxicity : Based on animal findings, clarithromycin tablet is not recommended for use in pregnant women except in clinical circumstances where no alternative therapy is appropriate (5.7) Exacerbation of myasthenia gravishas been reported in patients receiving clarithromycin tablets therapy.(5.8)
5.1Severe Acute Hypersensitivity Reactions In the event of severe acute hypersensitivity reactions, such as anaphylaxis, Stevens-Johnson Syndrome, toxic epidermal necrolysis, drug rash with eosinophilia and systemic symptoms (DRESS), Henoch-Schonlein purpura, and acute generalized exanthematous pustulosis, discontinue clarithromycin tablets therapy immediately and institute appropriate treatment.
5.2QT Prolongation Clarithromycin tablets have been associated with prolongation of the QT interval and infrequent cases of arrhythmia. Cases of torsades de pointes have been spontaneously reported during postmarketing surveillance in patients receiving clarithromycin tablets. Fatalities have been reported.
Avoid clarithromycin tablets in the following patients: · patients with known prolongation of the QT interval, ventricular cardiac arrhythmia, including torsades de pointes · patients receiving drugs known to prolong the QT interval [see also Contraindications (4.2)] · patients with ongoing proarrhythmic conditions such as uncorrected hypokalemia or hypomagnesemia, clinically significant bradycardia and in patients receiving Class IA (e.g., quinidine, procainamide, disopyramide) or Class III (e.g., dofetilide, amiodarone, sotalol) antiarrhythmic agents.
Elderly patients may be more susceptible to drug-associated effects on the QT interval [see Use in Specific Populations (8.5)] .
5.3Hepatotoxicity Hepatic dysfunction, including increased liver enzymes, and hepatocellular and/or cholestatic hepatitis, with or without jaundice, has been reported with clarithromycin. This hepatic dysfunction may be severe and is usually reversible. In some instances, hepatic failure with fatal outcome has been reported and generally has been associated with serious underlying diseases and/or concomitant medications.
Symptoms of hepatitis can include anorexia, jaundice, dark urine, pruritus, or tender abdomen. Discontinue clarithromycin tablets immediately if signs and symptoms of hepatitis occur.
5.4Serious Adverse Reactions Due to Concomitant Use with Other Drugs Drugs metabolized by CYP3A4 : Serious adverse reactions have been reported in patients taking clarithromycin tablets concomitantly with CYP3A4 substrates. These include colchicine toxicity with colchicine; markedly increased transaminases with lomitapide; rhabdomyolysis with simvastatin, lovastatin, and atorvastatin; hypoglycemia and cardiac arrhythmias (e.g., torsades de pointes) with disopyramide; and hypotension and acute kidney injury with calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem, nifedipine).
Most reports of acute kidney injury with calcium channel blockers metabo… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: · Acute Hypersensitivity Reactions [see Warnings and Precautions (5.1)] · QT Prolongation [see Warnings and Precautions (5.2)] · Hepatotoxicity [see Warnings and Precautions (5.3)] · Serious Adverse Reactions Due to Concomitant Use with Other Drugs [see Warnings and Precautions (5.4)] · Clostridium difficile Associated Diarrhea [see Warnings and Precautions (5.6)] · Exacerbation of Myasthenia Gravis [see Warnings and Precautions (5.8)] Most frequent adverse reactions for both adult and pediatric populations in clinical trials: abdominal pain, diarrhea, nausea, vomiting, dysgeusia (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Alembic Pharmaceuticals Limited at 1-866-210-9797 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Based on pooled data across all indications, the most frequent adverse reactions for both adult and pediatric populations observed in clinical trials are abdominal pain, diarrhea, nausea, vomiting and dysgeusia. Also reported were dyspepsia, liver function test abnormal, anaphylactic reaction, candidiasis, headache, insomnia, and rash.
The subsequent subsections list the most common adverse reactions for prophylaxis and treatment of mycobacterial infections and duodenal ulcer associated with H. pylori infection. In general, these profiles are consistent with the pooled data described above. Prophylaxis of Mycobacterial Infections In AIDS patients treated with clarithromycin tablets over long periods of time for prophylaxis against M. avium , it was often difficult to distinguish adverse reactions possibly associated with clarithromycin tablets administration from underlying HIV disease or intercurrent illness.
Median duration of treatment was 10.6 months for the clarithromycin tablets group and 8.2 months for the placebo group. Table 4. Incidence Rates (%) of Selected Adverse Reactions a in Immunocompromised Adult Patients Receiving Prophylaxis Against M. avium Complex Body System b Adverse Reaction Clarithromycin Tablets (n=339) % Placebo (n=339) % Body as a Whole Abdominal pain 5% 4% Headache 3% 1% Digestive Diarrhea 8% 4% Dyspepsia 4% 3% Flatulence 2% 1% Nausea 11% 7% Vomiting 6% 3% Skin & Appendages Rash 3% 4% Special Senses Taste Perversion 8% c 0.3% a Includes those events possibly or probably related to study drug and excludes concurrent conditions b 2% or greater Adverse Reaction Incidence Rates for either treatment group c Significant higher incidence compared to the placebo-treated group Discontinuation due to adverse reactions occurred in 18% of patients receiving clarithromycin tablets compared to 17% of patients receiving placebo in this trial.
Primary reasons for discontinuation in clarithromycin tablets treated patients include headache, nausea, vomiting, depression, and taste perversion. Changes in Laboratory Values Selected laboratory adverse experiences that were reported during therapy in greater than 2 % of adult patients treated with clarithromycin tablets in a randomized double-blind clinical trial involving 682 patients are presented in Table 5. In immunocompromised patients receiving prophylaxis against M. avium , evaluations of laboratory values were made by analyzing those values outside the seriously abnormal value (i.e., the extreme high or low limit) for the specified test.
Table 5. Percentage of Patients a Exceeding Extreme Laboratory Values in Patients Receiving Prophylaxis Against M. avium Complex Clarithromycin Tablets 500 mg twice a day Placebo WBC Count <1 x 10 9 /L 2/103 (4%) 0/95 SGOT >5 x ULN b 7/196 (4%) 5/208 (2%) SGPT >5 x ULN b 6/217 (3%) 4/232 (2%) a Include… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Co-administration of clarithromycin tablet is known to inhibit CYP3A, and a drug primarily metabolized by CYP3A may be associated with elevations in drug concentrations that could increase or prolong both therapeutic and adverse effects of the concomitant drug. Clarithromycin tablets should be used with caution in patients receiving treatment with other drugs known to be CYP3A enzyme substrates, especially if the CYP3A substrate has a narrow safety margin (e.g., carbamazepine) and/or the substrate is extensively metabolized by this enzyme.
Adjust dosage when appropriate and monitor serum concentrations of drugs primarily metabolized by CYP3A closely in patients concurrently receiving clarithromycin. Table 8: Clinically Significant Drug Interactions with Clarithromycin Tablets Drugs That Are Affected By Clarithromycin Tablets Drug(s) with Pharmacokinetics Affected by Clarithromycin Tablets Recommendation Comments Antiarrhythmics: Disopyramide Quinidine Dofetilide Amiodarone Sotalol Procainamide Not Recommended Disopyramide, Quinidine: There have been postmarketing reports of torsades de pointes occurring with concurrent use of clarithromycin and quinidine or disopyramide.
Electrocardiograms should be monitored for QTc prolongation during coadministration of clarithromycin with these drugs [see Warnings and Precautions (5.2)] . Serum concentrations of these medications should also be monitored. There have been spontaneous or published reports of CYP3A based interactions of clarithromycin with disopyramide and quinidine.
There have been postmarketing reports of hypoglycemia with the concomitant administration of clarithromycin and disopyramide. Therefore, blood glucose levels should be monitored during concomitant administration of clarithromycin and disopyramide. Digoxin Use With Caution Digoxin: Digoxin is a substrate for P-glycoprotein (Pgp) and clarithromycin is known to inhibit Pgp.
When clarithromycin and digoxin are co-administered, inhibition of Pgp by clarithromycin may lead to increased exposure of digoxin. Elevated digoxin serum concentrations in patients receiving clarithromycin and digoxin concomitantly have been reported in postmarketing surveillance. Some patients have shown clinical signs consistent with digoxin toxicity, including potentially fatal arrhythmias.
Monitoring of serum digoxin concentrations should be considered, especially for patients with digoxin concentrations in the upper therapeutic range. Oral Anticoagulants: Warfarin Use With Caution Oral anticoagulants: Spontaneous reports in the postmarketing period suggest that concomitant administration of clarithromycin and oral anticoagulants may potentiate the effects of the oral anticoagulants. Prothrombin times should be carefully monitored while patients are receiving clarithromycin and oral anticoagulants simultaneously [see Warnings and Precautions (5.4)] .
Antiepileptics: Carbamazepine Use With Caution Carbamazepine: Concomitant administration of single doses of clarithromycin and carbamazepine has been shown to result in increased plasma concentrations of carbamazepine. Blood level monitoring of carbamazepine may be considered. Increased serum concentrations of carbamazepine were observed in clinical trials with clarithromycin.
There have been spontaneous or published reports of CYP3A based interactions of clarithromycin with carbamazepine. Antifungals: Itraconazole Fluconazole Use With Caution No Dose Adjustment Itraconazole: Both clarithromycin and itraconazole are substrates and inhibitors of CYP3A, potentially leading to a bi-directional drug interaction when administered concomitantly (see also Itraconazole under “Drugs That Affect Clarithromycin Tablets” in the table below). Clarithromycin may increase the plasma concentrations of itraconazole.
Patients taking itraconazole and clarithromycin concomitantly should be monitored closely for signs or symptoms of increased or prolonged adverse reactions. Fluconazole: [see Pha… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric : Increased risk of torsades de pointes (8.5)
8.1Pregnancy Risk Summary Based on findings from animal studies, clarithromycin is not recommended for use in pregnant women except in clinical circumstances where no alternative therapy is appropriate. If pregnancy occurs while taking clarithromycin, the patient should be apprised of the potential hazard to the fetus [see Warnings and Precautions (5.7)] . Limited data from a small number of published human studies, with clarithromycin use during pregnancy are insufficient to inform drug-associated risks of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In animal reproduction studies, administration of oral clarithromycin to pregnant mice, rats, rabbits, and monkeys during the period of organogenesis produced malformations in rats (cardiovascular anomalies) and mice (cleft palate) at clinically relevant doses based on body surface area comparison. Fetal effects in mice, rats, and monkeys (e.g., reduced fetal survival, body weight, body weight gain) and implantation losses in rabbits were generally considered to be secondary to maternal toxicity (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Animal reproduction studies were conducted in mice, rats, rabbits, and monkeys with oral and intravenously administered clarithromycin.
In pregnant mice, clarithromycin was administered during organogenesis (gestation day [GD] 6 to 15) at oral doses of 15, 60, 250, 500, or 1000 mg/kg/day. Reduced body weight observed in dams at 1000 mg/kg/day (3 times the maximum recommended human dose [MRHD] based on body surface area comparison) resulted in reduced survival and body weight of the fetuses. At ≥ 500 mg/kg/day, increases in the incidence of post implantation loss and cleft palate in the fetuses were observed.
No adverse developmental effects were observed in mice at ≤ 250 mg/kg/day (≤ 1 times MRHD based on body surface area comparison). In pregnant Sprague Dawley rats, clarithromycin was administered during organogenesis (GD 6 to 15) at oral doses of 15, 50, or 150 mg/kg/day. Reductions in body weight and food consumption was observed in dams at 150 mg/kg/day.
Increased resorptions and reduced body weight of the fetuses at this dose were considered secondary to maternal toxicity. Additionally, at 150 mg/kg/day (1 times MRHD based on body surface area comparison), a low incidence of cardiovascular anomalies (complete situs inversus, undivided truncus, IV septal defect) was observed in the fetuses. Clarithromycin did not cause adverse developmental effects in rats at 50 mg/kg/day (0.3 times MRHD based on body surface area comparison).
Intravenous dosing of clarithromycin during organogenesis in rats (GD 6 to 15) at 15, 50, or 160 mg/kg/day was associated with maternal toxicity (reduced body weight, body-weight gain, and food consumption) at 160 mg/kg/day but no evidence of adverse developmental effects at any dose (≤ 1 times MRHD based on body surface area comparison). In pregnant Wistar rat, clarithromycin was administered during organogenesis (GD 7 to 17) at oral doses of 10, 40, or 160 mg/kg/day. Reduced body weight and food consumption were observed in dams at 160 mg/kg/day but there was no evidence of adverse developmental effects at any dose (≤ 1 times MRHD based on body surface area comparison).
In pregnant rabbits, clarithromycin administered during organogenesis (GD 6 to 18) at oral doses of 10, 35, or 125 mg/kg/day resulted in reduced maternal food consumption and decreased body weight at the highest dose, with no evidence of any adverse developmental effects at any do… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies, clarithromycin is not recommended for use in pregnant women except in clinical circumstances where no alternative therapy is appropriate. If pregnancy occurs while taking clarithromycin, the patient should be apprised of the potential hazard to the fetus [see Warnings and Precautions (5.7)] . Limited data from a small number of published human studies, with clarithromycin use during pregnancy are insufficient to inform drug-associated risks of major birth defects, miscarriage, or adverse maternal or fetal outcomes.
In animal reproduction studies, administration of oral clarithromycin to pregnant mice, rats, rabbits, and monkeys during the period of organogenesis produced malformations in rats (cardiovascular anomalies) and mice (cleft palate) at clinically relevant doses based on body surface area comparison. Fetal effects in mice, rats, and monkeys (e.g., reduced fetal survival, body weight, body weight gain) and implantation losses in rabbits were generally considered to be secondary to maternal toxicity (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Animal reproduction studies were conducted in mice, rats, rabbits, and monkeys with oral and intravenously administered clarithromycin.
In pregnant mice, clarithromycin was administered during organogenesis (gestation day [GD] 6 to 15) at oral doses of 15, 60, 250, 500, or 1000 mg/kg/day. Reduced body weight observed in dams at 1000 mg/kg/day (3 times the maximum recommended human dose [MRHD] based on body surface area comparison) resulted in reduced survival and body weight of the fetuses. At ≥ 500 mg/kg/day, increases in the incidence of post implantation loss and cleft palate in the fetuses were observed.
No adverse developmental effects were observed in mice at ≤ 250 mg/kg/day (≤ 1 times MRHD based on body surface area comparison). In pregnant Sprague Dawley rats, clarithromycin was administered during organogenesis (GD 6 to 15) at oral doses of 15, 50, or 150 mg/kg/day. Reductions in body weight and food consumption was observed in dams at 150 mg/kg/day.
Increased resorptions and reduced body weight of the fetuses at this dose were considered secondary to maternal toxicity. Additionally, at 150 mg/kg/day (1 times MRHD based on body surface area comparison), a low incidence of cardiovascular anomalies (complete situs inversus, undivided truncus, IV septal defect) was observed in the fetuses. Clarithromycin did not cause adverse developmental effects in rats at 50 mg/kg/day (0.3 times MRHD based on body surface area comparison).
Intravenous dosing of clarithromycin during organogenesis in rats (GD 6 to 15) at 15, 50, or 160 mg/kg/day was associated with maternal toxicity (reduced body weight, body-weight gain, and food consumption) at 160 mg/kg/day but no evidence of adverse developmental effects at any dose (≤ 1 times MRHD based on body surface area comparison). In pregnant Wistar rat, clarithromycin was administered during organogenesis (GD 7 to 17) at oral doses of 10, 40, or 160 mg/kg/day. Reduced body weight and food consumption were observed in dams at 160 mg/kg/day but there was no evidence of adverse developmental effects at any dose (≤ 1 times MRHD based on body surface area comparison).
In pregnant rabbits, clarithromycin administered during organogenesis (GD 6 to 18) at oral doses of 10, 35, or 125 mg/kg/day resulted in reduced maternal food consumption and decreased body weight at the highest dose, with no evidence of any adverse developmental effects at any dose (≤ 2 times MRHD based on body surface area comparison). Intravenously administered… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of clarithromycin tablets have been established for the treatment of the following conditions or diseases in pediatric patients 6 months and older. Use in these indications is based on clinical trials in pediatric patients or adequate and well-controlled studies in adults with additional pharmacokinetic and safety data in pediatric patients: · Pharyngitis/Tonsillitis · Community-Acquired Pneumonia · Acute maxillary sinusitis · Acute otitis media [see Clinical Studies (14.2)] · Uncomplicated skin and skin structure infections The safety and effectiveness of clarithromycin tablets have been established for the prevention of disseminated Mycobacterium avium complex (MAC) disease in pediatric patients 20 months and older with advanced HIV infection.
No studies of clarithromycin tablets for MAC prophylaxis have been performed in pediatric populations and the doses recommended for prophylaxis are derived from MAC pediatric treatment studies. Safety and effectiveness of clarithromycin tablets in pediatric patients under 6 months of age have not been established. The safety of clarithromycin tablets has not been studied in MAC patients under the age of 20 months.
🧓 Geriatric Use ▾
8.5Geriatric Use In a steady-state study in which healthy elderly subjects (65 years to 81 years of age) were given 500 mg of clarithromycin tablets every 12 hours, the maximum serum concentrations and area under the curves of clarithromycin and 14-OH clarithromycin were increased compared to those achieved in healthy young adults. These changes in pharmacokinetics parallel known age-related decreases in renal function. In clinical trials, elderly patients did not have an increased incidence of adverse reactions when compared to younger patients.
Consider dosage adjustment in elderly patients with severe renal impairment. Elderly patients may be more susceptible to development of torsades de pointes arrhythmias than younger patients [see Warnings and Precautions (5.3)] . Most reports of acute kidney injury with calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem, nifedipine) involved elderly patients 65 years of age or older [see Warnings and Precautions (5.4)] .
Especially in elderly patients, there have been reports of colchicine toxicity with concomitant use of clarithromycin and colchicine, some of which occurred in patients with renal insufficiency. Deaths have been reported in some patients [see Contraindications (4.4) and Warnings and Precautions (5.4)] .
🆘 Overdosage ▾
10 OVERDOSAGE Overdosage of clarithromycin tablets can cause gastrointestinal symptoms such as abdominal pain, vomiting, nausea, and diarrhea. Treat adverse reactions accompanying overdosage by the prompt elimination of unabsorbed drug and supportive measures. As with other macrolides, clarithromycin tablets serum concentrations are not expected to be appreciably affected by hemodialysis or peritoneal dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Clarithromycin is a macrolide antimicrobial drug [see Microbiology (12.4)] .
12.3Pharmacokinetics Absorption Clarithromycin Immediate-Release Tablets The absolute bioavailability of 250 mg clarithromycin tablets was approximately 50%. For a single 500 mg dose of clarithromycin, food slightly delays the onset of clarithromycin absorption, increasing the peak time from approximately 2 to 2.5 hours. Food also increases the clarithromycin peak plasma concentration by about 24%, but does not affect the extent of clarithromycin bioavailability.
Food does not affect the onset of formation of the active metabolite, 14-OH clarithromycin or its peak plasma concentration but does slightly decrease the extent of metabolite formation, indicated by an 11% decrease in area under the plasma concentration-time curve (AUC). Therefore, clarithromycin tablets may be given without regard to food. In non-fasting healthy human subjects (males and females), peak plasma concentrations were attained within 2 to 3 hours after oral dosing.
Clarithromycin Extended-Release Tablets Clarithromycin extended-release tablets provide extended absorption of clarithromycin from the gastrointestinal tract after oral administration. Relative to an equal total daily dose of immediate- release clarithromycin tablets, clarithromycin extended-release tablets provide lower and later steady-state peak plasma concentrations but equivalent 24-hour AUCs for both clarithromycin and its microbiologically-active metabolite, 14-OH clarithromycin. While the extent of formation of 14-OH clarithromycin following administration of clarithromycin extended-release tablets (2 x 500 mg tablets once daily) is not affected by food, administration under fasting conditions is associated with approximately 30% lower clarithromycin AUC relative to administration with food.
Therefore, clarithromycin extended-release tablets should be taken with food. Figure 2: Steady-State Clarithromycin Plasma Concentration-Time Profiles Clarithromycin Granules For Oral Suspension When 250 mg doses of clarithromycin as clarithromycin granules as an oral suspension were administered to fasting healthy adult subjects, peak plasma concentrations were attained around 3 hours after dosing. For adult patients, the bioavailability of 10 mL of the 125 mg/5 mL suspension or 10 mL of the 250 mg/5 mL suspension is similar to a 250 mg or 500 mg tablet, respectively.
In adults given 250 mg clarithromycin as suspension (n = 22), food appeared to decrease mean peak plasma clarithromycin concentrations from 1.2 (± 0.4) mcg/mL to 1(± 0.4) mcg/mL and the extent of absorption from 7.2 (± 2.5) hr•mcg/mL to 6.5 (± 3.7) hr•mcg/mL. Distribution Clarithromycin and the 14-OH clarithromycin metabolite distribute readily into body tissues and fluids. There are no data available on cerebrospinal fluid penetration.
Because of high intracellular concentrations, tissue concentrations are higher than serum concentrations. Examples of tissue and serum concentrations are presented below. Table 9.
Tissue and Serum Concentrations of Clarithromycin CONCENTRATION (after 250 mg every 12 hours) Tissue Type Tissue (mcg/g) Serum (mcg/mL) Tonsil 1.6
0.8Lung 8.8
1.7Metabolism and Elimination Clarithromycin Immediate-Release Tablets Steady-state peak plasma clarithromycin concentrations were attained within 3 days and were approximately 1 mcg/mL to 2 mcg/mL with a 250 mg dose administered every 12 hours and 3 mcg/mL to 4 mcg/mL with a 500 mg dose administered every 8 hours to 12 hours. The elimination half-life of clarithromycin was about 3 hours to 4 hours with 250 mg administered every 12 hours but increased to 5 hours to 7 hours with 500 mg administered every 8 hours to 12 hours.
The nonlinearity of clarithromycin pharmacokinetics is slight at the recommended doses of 250 mg and 500 mg administered every 8 hours to 12 hours. With a 250 mg every 12 hours dosing, the principal metabolite, 14-OH clari… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Clarithromycin is a macrolide antimicrobial drug [see Microbiology (12.4)] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Clarithromycin tablets USP, 250 mg are yellow oval film-coated tablets debossed with ‘L139’ on one side and plain on the other side. NDC 62332-344-30 Bottle of 30 tablets NDC 62332-344-60 Bottle of 60 tablets NDC 62332-344-91 Bottle of 1000 tablets Clarithromycin tablets USP, 500 mg are yellow oval film-coated tablets debossed with ‘L140’ on one side and plain on the other side. NDC 62332-345-30 Bottle of 30 tablets NDC 62332-345-60 Bottle of 60 tablets NDC 62332-345-91 Bottle of 1000 tablets Store 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Clarithromycin is a semi-synthetic macrolide antimicrobial for oral use. Chemically, it is 6- 0 methylerythromycin. The molecular formula is C38H69NO13, and the molecular weight is 747.95.
The structural formula is: Figure 1: Structure of Clarithromycin Clarithromycin is a white to off-white crystalline powder. It is soluble in acetone, slightly soluble in dehydrated alcohol, in methanol, in acetonitrile and in phosphate buffer at pH values of 2 to 5. Practically insoluble in water.
Clarithromycin tablets, USP are available as immediate-release tablets. Each yellow oval film-coated immediate-release clarithromycin tablet, USP contains 250 mg or 500 mg of clarithromycin USP and the following inactive ingredients: 250 mg tablets: microcrystalline cellulose, croscarmellose sodium, pregelatinized starch, colloidal silicon dioxide, povidone K-30, stearic acid, magnesium stearate, hypromellose, hydroxypropyl cellulose, propylene glycol, talc, vanillin, titanium dioxide, and D&C Yellow No. 10 Aluminium Lake.
500 mg tablets: microcrystalline cellulose, croscarmellose sodium, colloidal silicon dioxide, povidone K-30, magnesium stearate, hypromellose, hydroxypropyl cellulose, propylene glycol, talc, vanillin, titanium dioxide, and D&C Yellow No. 10 Aluminium Lake. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Provide the following instructions or information about clarithromycin tablets to patients: Important Administration Instructions Advise patients that clarithromycin tablets and oral suspension can be taken with or without food and can be taken with milk; however, clarithromycin extended-release tablets should be taken with food. Do not refrigerate the suspension. Drug Interactions Advise patients that clarithromycin tablet may interact with some drugs; therefore, advise patients to report to their healthcare provider the use of any other medications.
Diarrhea Advise patients that diarrhea is a common problem caused by antibacterials including clarithromycin tablets which usually ends when the antibacterial is discontinued. Sometimes after starting treatment with antibacterials, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial. If this occurs, instruct patients to contact their healthcare provider as soon as possible.
Embryo-Fetal Toxicity Advise females of reproductive potential that if pregnancy occurs while taking this drug, there is a potential hazard to the fetus [see Warnings and Precautions (5.7) and Use in Specific Populations (8.1)] . Antibacterial Resistance Counsel patients that antibacterial drugs including clarithromycin tablets should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold).
When clarithromycin tablets are prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by clarithromycin tablets or other antibacterial drugs in the future. Potential for Dizziness, Vertigo and Confusion There are no data on the effect of clarithromycin tablets on the ability to drive or use machines.
However, counsel patients regarding the potential for dizziness, vertigo, confusion and disorientation, which may occur with the clarithromycin tablets. The potential for these adverse reactions should be taken into account before patients drive or use machines. Risk of Mortality in Patients with Coronary Disease Years After Clarithromycin Tablets Treatment Advise patients who have coronary artery disease to continue medications and lifestyle modifications for their coronary artery disease because clarithromycin tablets may be associated with increased risk for mortality years after the end of clarithromycin tablets treatment.
Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088. For more information, call Alembic Pharmaceutical Limited at 1-866-210-9797.
Manufactured by: Alembic Pharmaceuticals Limited (Formulation Division), Panelav 389350, Gujarat, India Manufactured for: Alembic Pharmaceuticals, Inc. Bedminster, NJ 07921, USA Revised: 05/2023
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Clarithromycin Immediate-Release Tablets The absolute bioavailability of 250 mg clarithromycin tablets was approximately 50%. For a single 500 mg dose of clarithromycin, food slightly delays the onset of clarithromycin absorption, increasing the peak time from approximately 2 to 2.5 hours. Food also increases the clarithromycin peak plasma concentration by about 24%, but does not affect the extent of clarithromycin bioavailability.
Food does not affect the onset of formation of the active metabolite, 14-OH clarithromycin or its peak plasma concentration but does slightly decrease the extent of metabolite formation, indicated by an 11% decrease in area under the plasma concentration-time curve (AUC). Therefore, clarithromycin tablets may be given without regard to food. In non-fasting healthy human subjects (males and females), peak plasma concentrations were attained within 2 to 3 hours after oral dosing.
Clarithromycin Extended-Release Tablets Clarithromycin extended-release tablets provide extended absorption of clarithromycin from the gastrointestinal tract after oral administration. Relative to an equal total daily dose of immediate- release clarithromycin tablets, clarithromycin extended-release tablets provide lower and later steady-state peak plasma concentrations but equivalent 24-hour AUCs for both clarithromycin and its microbiologically-active metabolite, 14-OH clarithromycin. While the extent of formation of 14-OH clarithromycin following administration of clarithromycin extended-release tablets (2 x 500 mg tablets once daily) is not affected by food, administration under fasting conditions is associated with approximately 30% lower clarithromycin AUC relative to administration with food.
Therefore, clarithromycin extended-release tablets should be taken with food. Figure 2: Steady-State Clarithromycin Plasma Concentration-Time Profiles Clarithromycin Granules For Oral Suspension When 250 mg doses of clarithromycin as clarithromycin granules as an oral suspension were administered to fasting healthy adult subjects, peak plasma concentrations were attained around 3 hours after dosing. For adult patients, the bioavailability of 10 mL of the 125 mg/5 mL suspension or 10 mL of the 250 mg/5 mL suspension is similar to a 250 mg or 500 mg tablet, respectively.
In adults given 250 mg clarithromycin as suspension (n = 22), food appeared to decrease mean peak plasma clarithromycin concentrations from 1.2 (± 0.4) mcg/mL to 1(± 0.4) mcg/mL and the extent of absorption from 7.2 (± 2.5) hr•mcg/mL to 6.5 (± 3.7) hr•mcg/mL. Distribution Clarithromycin and the 14-OH clarithromycin metabolite distribute readily into body tissues and fluids. There are no data available on cerebrospinal fluid penetration.
Because of high intracellular concentrations, tissue concentrations are higher than serum concentrations. Examples of tissue and serum concentrations are presented below. Table 9.
Tissue and Serum Concentrations of Clarithromycin CONCENTRATION (after 250 mg every 12 hours) Tissue Type Tissue (mcg/g) Serum (mcg/mL) Tonsil 1.6
0.8Lung 8.8
1.7Metabolism and Elimination Clarithromycin Immediate-Release Tablets Steady-state peak plasma clarithromycin concentrations were attained within 3 days and were approximately 1 mcg/mL to 2 mcg/mL with a 250 mg dose administered every 12 hours and 3 mcg/mL to 4 mcg/mL with a 500 mg dose administered every 8 hours to 12 hours. The elimination half-life of clarithromycin was about 3 hours to 4 hours with 250 mg administered every 12 hours but increased to 5 hours to 7 hours with 500 mg administered every 8 hours to 12 hours.
The nonlinearity of clarithromycin pharmacokinetics is slight at the recommended doses of 250 mg and 500 mg administered every 8 hours to 12 hours. With a 250 mg every 12 hours dosing, the principal metabolite, 14-OH clarithromycin, attains a peak steady-state concentration of about 0.6 mcg/mL and has an elimination half-life of 5 hours to 6 hours… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Mycobacterial Infections Prophylaxis of Mycobacterial Infections A randomized, double-blind clinical trial (trial 3) compared clarithromycin 500 mg twice a day to placebo in patients with CDC-defined AIDS and CD 4 counts less than 100 cells/µL. This trial accrued 682 patients from November 1992 to January 1994, with a median CD 4 cell count at entry of 30 cells/mcL. Median duration of clarithromycin was 10.6 months vs.
8.2months for placebo. More patients in the placebo arm than the clarithromycin arm discontinued prematurely from the trial (75.6% and 67.4%, respectively). However, if premature discontinuations due to Mycobacterium avium complex (MAC) or death are excluded, approximately equal percentages of patients on each arm (54.8%) on clarithromycin and 52.5% on placebo) discontinued study drug early for other reasons.
The trial was designed to evaluate the following endpoints: 1. MAC bacteremia, defined as at least one positive culture for Mycobacterium avium complex bacteria from blood or another normally sterile site 2. Survival 3.
Clinically significant disseminated MAC disease, defined as MAC bacteremia accompanied by signs or symptoms of serious MAC infection, including fever, night sweats, weight loss, anemia, or elevations in liver function tests MAC Bacteremia In patients randomized to clarithromycin, the risk of MAC bacteremia was reduced by 69% compared to placebo. The difference between groups was statistically significant (p < 0.001). On an intent- to-treat basis, the one-year cumulative incidence of MAC bacteremia was 5% for patients randomized to clarithromycin and 19.4% for patients randomized to placebo.
While only 19 of the 341 patients randomized to clarithromycin developed MAC, 11 of these cases were resistant to clarithromycin. The patients with resistant MAC bacteremia had a median baseline CD 4 count of 10 cells/mm 3 (range 2 cells/mm 3 to 25 cells/mm 3 ). Information regarding the clinical course and response to treatment of the patients with resistant MAC bacteremia is limited.
The 8 patients who received clarithromycin and developed susceptible MAC bacteremia had a median baseline CD 4 count of 25 cells/mm 3 (range 10 cells/mm 3 to 80 cells/mm 3 ). Comparatively, 53 of the 341 placebo patients developed MAC; none of these isolates were resistant to clarithromycin. The median baseline CD 4 count was 15 cells/mm 3 (range 2 cells/mm 3 to 130 cells/mm 3 ) for placebo patients that developed MAC.
Survival A statistically significant survival benefit of clarithromycin compared to placebo was observed (see Figure 3 and Table 11). Since the analysis at 18 months includes patients no longer receiving prophylaxis the survival benefit of clarithromycin may be underestimated. Figure 3.
Survival of All Randomized AIDS Patients Over Time in Trial 3 Table 11. Mortality Rates at 18 months in Trial 3 M ortality Rates Re duction in Mortality Rates on Clarithromycin P lacebo Clarithromycin 6 month 9.4% 6.5% 31% 12 month 29.7% 20.5% 31% 18 month 46.4% 37.5% 20% Clinically Significant Disseminated MAC Disease In association with the decreased incidence of MAC bacteremia, patients in the group randomized to clarithromycin showed reductions in the signs and symptoms of disseminated MAC disease, including fever, night sweats, weight loss, and anemia.
Treatment of Mycobacterial Infections Dose-Ranging Monotherapy Trials in Adult AIDS Patients with MAC Two randomized clinical trials (Trials 1 and 2) compared different dosages of clarithromycin in patients with CDC-defined AIDS and CD 4 counts less than100 cells/mcL. These trials accrued patients from May 1991 to March 1992. Trial 500 was a randomized, double-blind trial; trial 577 was an open-label compassionate use trial.
Both trials used 500 mg and 1000 mg twice daily dosing of clarithromycin tablets; trial 1 also had a 2000 mg twice daily clarithromycin tablets group. Trial 1 enrolled 154 adult patients and trial 2 enrolled 469 adult patients.… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Mutagenesis The following in vitro mutagenicity tests have been conducted with clarithromycin: · Salmonella /Mammalian Microsomes Test · Bacterial Induced Mutation Frequency Test · In Vitro Chromosome Aberration Test · Rat Hepatocyte DNA Synthesis Assay · Mouse Lymphoma Assay · Mouse Dominant Lethal Study · Mouse Micronucleus Test All tests had negative results except the in vitro chromosome aberration test which was positive in one test and negative in another.
In addition, a bacterial reverse-mutation test (Ames test) has been performed on clarithromycin metabolites with negative results. Impairment of Fertility Fertility and reproduction studies have shown that daily doses of up to 160 mg/kg/day to male and female rats caused no adverse effects on the estrous cycle, fertility, parturition, or number and viability of offspring. Plasma levels in rats after 150 mg/kg/day were twice the human serum levels.
Testicular atrophy occurred in rats at doses 7 times, in dogs at doses 3 times, and in monkeys at doses 8 times greater than the maximum human daily dose (on a body surface area basis).
13.2Animal Toxicology and/or Pharmacology Corneal opacity occurred in dogs at doses 12 times and in monkeys at doses 8 times greater than the maximum human daily dose (on a body surface area basis). Lymphoid depletion occurred in dogs at doses 3 times greater than and in monkeys at doses 2 times greater than the maximum human daily dose (on a body surface area basis).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Mutagenesis The following in vitro mutagenicity tests have been conducted with clarithromycin: · Salmonella /Mammalian Microsomes Test · Bacterial Induced Mutation Frequency Test · In Vitro Chromosome Aberration Test · Rat Hepatocyte DNA Synthesis Assay · Mouse Lymphoma Assay · Mouse Dominant Lethal Study · Mouse Micronucleus Test All tests had negative results except the in vitro chromosome aberration test which was positive in one test and negative in another.
In addition, a bacterial reverse-mutation test (Ames test) has been performed on clarithromycin metabolites with negative results. Impairment of Fertility Fertility and reproduction studies have shown that daily doses of up to 160 mg/kg/day to male and female rats caused no adverse effects on the estrous cycle, fertility, parturition, or number and viability of offspring. Plasma levels in rats after 150 mg/kg/day were twice the human serum levels.
Testicular atrophy occurred in rats at doses 7 times, in dogs at doses 3 times, and in monkeys at doses 8 times greater than the maximum human daily dose (on a body surface area basis).
📚 References ▾
15 REFERENCES 1. Winkel P, Hilden J, Hansen JF, Kastrup J, Kolmos HJ, Kjøller E, et al. Clarithromycin for stable coronary heart disease increases all-cause and cardiovascular mortality and cerebrovascular morbidity over 10 years in the CLARICOR randomised, blinded clinical trial. Int J Cardiol 2015;182:459-65. 2. Kemper CA, et al. Treatment of Mycobacterium avium Complex Bacteremia in AIDS with a Four-Drug Oral Regimen. Ann Intern Med . 1992;116:466-472.
📄 Recent Major Changes ▾
Contraindications (4) 5/2023 Drug Interactions (7) 5/2023
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 250 mg NDC 62332-344-30 Clarithromycin Tablets, USP 250 mg Rx only 30 Tablets Alembic clarithromycin-250-mg.jpg
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL 500 mg NDC 62332-345-30 Clarithromycin Tablets, USP 500 mg Rx only 30 Tablets Alembic clarithromycin-500-mg.jpg
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |