
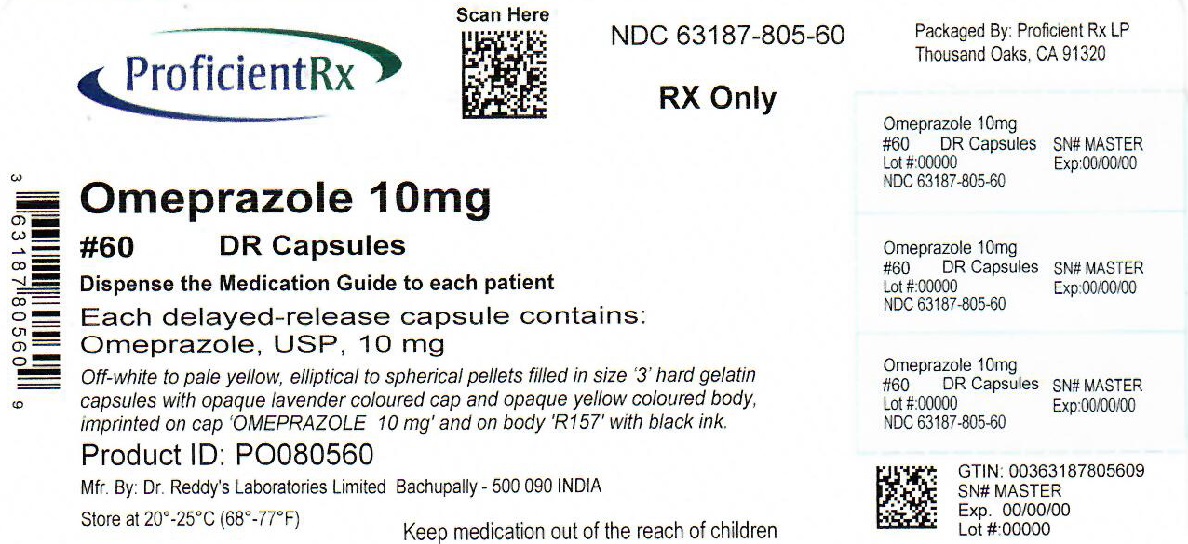
Omeprazole 10 mg Capsule, Delayed Release, 30-count
Other active recalls for Omeprazole (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Proton Pump Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Omeprazole turns down your stomach's acid production by blocking the pump that makes acid in the first place. Depending on why you're taking it, that can mean relief from heartburn...
- What exactly is omeprazole supposed to do for me?
- Take it about 30 minutes before a meal, ideally before breakfast. Taking it before eating gives it the best chance to be absorbed and ready to work when your stomach starts produci...
- When should I take it — before or after eating?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Omeprazole — tap one for details:
Omeprazole may be associated with lower levels of 9 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 767IP0Y5NH
A synthetic red colorant used to give medicines their color. It helps patients identify their medication and makes the product visually appealing.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 6HG8UB2MUY
Meglumine is a sugar-alcohol compound used as a solubilizer and pH buffer in medicines. It helps dissolve drugs that don't mix well in water and maintains stable acidity levels in the formulation.
-
UNII T967IEU43C
A synthetic polymer made from methacrylic acid and ethyl acrylate. It forms a protective coating on tablets and capsules to control how and where the medicine dissolves in the digestive system.
-
UNII TUF2IVW3M2
Poloxamer 407 is a synthetic polymer made from ethylene oxide and propylene oxide. In medicines, it acts as a thickener, emulsifier, and solubilizer to help mix ingredients and create the right texture.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
21 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Omeprazole 10 mg 00781-2859-01 | Sandoz | 100 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 16714-0630-01 | NorthStar | 30 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 16714-0714-01 | NorthStar | 30 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 55111-0157-01 | Dr. | 100 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 55111-0643-01 | Dr. | 100 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 59651-0001-01 | Aurobindo | 100 capsules | $0.082 | — | Availability likely | — |
| Omeprazole 10 mg 60505-0145-00 | Apotex | 30 capsules | $0.082 | AB | Discontinued | — |
| Omeprazole 10 mg 62135-0530-30 | Chartwell | 30 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 62135-0559-30 | Chartwell | 30 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 68382-0411-01 | Zydus | 100 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 68462-0395-01 | Glenmark | 100 capsules | $0.082 | AB | Availability likely | — |
| Omeprazole 10 mg 62175-0114-32 | Lannett | 30 capsules | $0.090 | AB | FDA listed | — |
| Omeprazole 10 mg 00781-2785-01 | Sandoz | 100 capsules | — | AB | FDA listed | — |
| omeprazole 10 mg 31722-0527-01 | Camber | 100 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 42708-0158-14 | QPharma, | 14 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 57237-0160-01 | Rising | 100 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 63187-0061-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mgthis 63187-0805-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 65841-0759-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 70700-0149-01 | Xiromed, | 100 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 71205-0501-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 76420-0878-00 | Asclemed | 1000 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 82804-0166-60 | Proficient | 60 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 82804-0280-60 | Proficient | 60 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 85534-0064-00 | HAWAII | 30 capsules | — | AB | FDA listed | — |
| Omeprazole 10 mg 82804-0310-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63187-0805-30 You're viewing this | 30 CAPSULE, DELAYED RELEASE in 1 BOTTLE (63187-805-30) | 2017-01-02 | Active |
| 63187-0805-60 | 60 CAPSULE, DELAYED RELEASE in 1 BOTTLE (63187-805-60) | 2017-01-02 | Active |
| 63187-0805-90 | 90 CAPSULE, DELAYED RELEASE in 1 BOTTLE (63187-805-90) | 2017-01-02 | Active |
You're viewing the smallest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 63187-0805-30?
What is the difference between NDC 63187-0805-30 and NDC 63187-0805-60?
What NDC number is used to bill for this package of Omeprazole 10 mg Capsule, Delayed Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Omeprazole is a proton pump inhibitor indicated for: 1. Treatment in adults of duodenal ulcer (1.1) and gastric ulcer (1.2) 2. Treatment in adults and children of gastroesophageal reflux disease (GERD) (1.3) and maintenance of healing of erosive esophagitis (1.4) The safety and effectiveness of omeprazole in pediatric patients < 1 year of age have not been established. (8.4)
1.1Duodenal Ulcer (adults) Omeprazole delayed-release capsules are indicated for short-term treatment of active duodenal ulcer in adults. Most patients heal within four weeks. Some patients may require an additional four weeks of therapy.
Omeprazole delayed-release capsules, in combination with clarithromycin and amoxicillin, are indicated for treatment of patients with H. pylori infection and duodenal ulcer disease (active or up to 1-year history) to eradicate H. pylori in adults. Omeprazole delayed-release capsules, in combination with clarithromycin are indicated for treatment of patients with H. pylori infection and duodenal ulcer disease to eradicate H. pylori in adults. Eradication of H. pylori has been shown to reduce the risk of duodenal ulcer recurrence [see Clinical Studies (14.1) and Dosage and Administration (2 ) ].
Among patients who fail therapy, Omeprazole delayed-release capsules with clarithromycin are more likely to be associated with the development of clarithromycin resistance as compared with triple therapy. In patients who fail therapy, susceptibility testing should be done. If resistance to clarithromycin is demonstrated or susceptibility testing is not possible, alternative antimicrobial therapy should be instituted. [See Microbiology section (12.4) ] , and the clarithromycin package insert, Microbiology section.)
1.2Gastric Ulcer (adults) Omeprazole delayed-release capsules are indicated for short-term treatment (4 to 8 weeks) of active benign gastric ulcer in adults for upto 4 weeks. [See Clinical Studies (14.2) ]
1.3Treatment of Gastroesophageal Reflux Disease (GERD) (adults and pediatric patients) Symptomatic GERD Omeprazole delayed-release capsules are indicated for the treatment of heartburn and other symptoms associated with GERD in pediatric patients and adults. Erosive Esophagitis Omeprazole delayed-release capsules are indicated for the short-term treatment (4 to 8 weeks) of erosive esophagitis that has been diagnosed by endoscopy in pediatric patients and adults. [See Clinical Studies (14.4) ] The efficacy of omeprazole delayed-release capsules used for longer than 8 weeks in these patients has not been established.
If a patient does not respond to 8 weeks of treatment, an additional 4 weeks of treatment may be given. If there is recurrence of erosive esophagitis or GERD symptoms (e.g., heartburn), additional 4 to 8 week courses of omeprazole may be considered.
1.4Maintenance of Healing of Erosive Esophagitis (adults and pediatric patients) Omeprazole delayed-release capsules are indicated to maintain healing of erosive esophagitis in pediatric patients and adults. Controlled studies do not extend beyond 12 months. [See Clinical Studies (14.4) ]
1.5Pathological Hypersecretory Conditions (adults) Omeprazole delayed-release capsules are indicated for the long-term treatment of pathological hypersecretory conditions (e.g., Zollinger-Ellison syndrome, multiple endocrine adenomas and systemic mastocytosis) in adults.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Omeprazole delayed-release capsules should be taken before eating. In the clinical trials, antacids were used concomitantly with omeprazole. Patients should be informed that the omeprazole delayed-release capsule should be swallowed whole.
For patients unable to swallow an intact capsule, alternative administration options are available [See Dosage and Administration (2.8) ]. Indication Omeprazole Dose Frequency Treatment of ActiveDuodenal Ulcer (2.1) 20 mg Once daily for 4 weeks. Some patients may require an additional 4 weeks H. pylori Eradication to Reduce the Risk of Duodenal Ulcer Recurrence (2.2) Triple Therapy: Omeprazole 20 mg Each drug twice daily for 10 days Amoxicillin 1000 mg Clarithromycin 500 mg Dual Therapy: Omeprazole 40 mg Once daily for 14 days Clarithromycin 500 mg Three times daily for 14 days Gastric Ulcer (2.3) 40 mg Once daily for 4 to 8 weeks GERD (2.4) 20 mg Once daily for 4 to 8 weeks Maintenance of Healing of Erosive Esophagitis (2.5) 20 mg Once daily Pathological Hypersecretory Conditions (2.6) 60 mg (varies with individual patient) Once daily Pediatric Patients (2 to 16 years of age) (2.7) Weight Dose GERD 10 < 20 kg 10 mg Once daily And Maintenance of ≥ 20 kg 20 mg Healing of Erosive Esophagitis
2.1Short-Term Treatment of Active Duodenal Ulcer The recommended adult oral dose of omeprazole delayed-release capsules is 20 mg once daily. Most patients heal within four weeks. Some patients may require an additional four weeks of therapy.
2.2H. pylori Eradication for the Reduction of the Risk of Duodenal Ulcer Recurrence Triple Therapy (omeprazole/clarithromycin/amoxicillin) — The recommended adult oral regimen is omeprazole delayed-release capsules 20 mg plus clarithromycin 500 mg plus amoxicillin 1000 mg each given twice daily for 10 days. In patients with an ulcer present at the time of initiation of therapy, an additional 18 days of omeprazole delayed-release capsules 20 mg once daily is recommended for ulcer healing and symptom relief. Dual Therapy (omeprazole/clarithromycin) — The recommended adult oral regimen is omeprazole delayed-release capsuels 40 mg once daily plus clarithromycin 500 mg three times daily for 14 days.
In patients with an ulcer present at the time of initiation of therapy, an additional 14 days of omeprazole delayed-release capsules 20 mg once daily is recommended for ulcer healing and symptom relief.
2.3Gastric Ulcer The recommended adult oral dose is 40 mg once daily for 4 to 8 weeks.
2.4Gastroesophageal Reflux Disease (GERD) The recommended adult oral dose for the treatment of patients with symptomatic GERD and no esophageal lesions is 20 mg daily for up to 4 weeks. The recommended adult oral dose for the treatment of patients with erosive esophagitis and accompanying symptoms due to GERD is 20 mg daily for 4 to 8 weeks.
2.5Maintenance of Healing of Erosive Esophagitis The recommended adult oral dose is 20 mg daily. Controlled studies do not extend beyond 12 months. [See Clinical Studies (14.4) ]
2.6Pathological Hypersecretory Conditions The dosage of omeprazole delayed-release capsules in patients with pathological hypersecretory conditions varies with the individual patient. The recommended adult oral starting dose is 60 mg once daily. Doses should be adjusted to individual patient needs and should continue for as long as clinically indicated.
Doses up to 120 mg three times daily have been administered. Daily dosages of greater than 80 mg should be administered in divided doses. Some patients with Zollinger-Ellison syndrome have been treated continuously with omeprazole delayed-release capsules for more than 5 years.
2.7Pediatric Patients For the treatment of GERD and maintenance of healing of erosive esophagitis, the recommended daily dose for pediatric patients 2 to 16 years of age is as follows: Patient Weight Omeprazole Daily Dose 10 < 20 kg 10 mg ≥ 20 kg 20 mg On a per kg basis, the doses of omeprazole required to heal erosive esoph…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Omeprazole delayed-release capsules, USP 10 mg are off-white to pale yellow, elliptical to spherical pellets filled in size ‘3’ hard gelatin capsules with opaque lavender coloured cap and opaque yellow coloured body, imprinted on cap ‘OMEPRAZOLE’ 10 mg and on body ‘R157’ with black ink. Omeprazole delayed-release capsules, USP 20 mg are off-white to pale yellow, elliptical to spherical pellets filled in size ‘2’ hard gelatin capsules with opaque lavender coloured cap and opaque iron grey coloured body, imprinted on cap ‘OMEPRAZOLE’ 20 mg and on body ‘R158’ with black ink.
Omeprazole delayed-release capsules, USP 40 mg are off-white to pale yellow, elliptical to spherical pellets filled in size ‘O el ’ hard gelatin capsules with opaque yellow coloured cap and opaque lavender coloured body, imprinted on cap ‘OMEPRAZOLE’ 40 mg and on body ‘R159’ with black ink. 2. Omeprazole delayed-release capsules, 10 mg, 20 mg and 40 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Omeprazole delayed-release capsules are contraindicated in patients with known hypersensitivity to substituted benzimidazoles or to any component of the formulation. Hypersensitivity reactions may include anaphylaxis, anaphylactic shock, angioedema, bronchospasm, acute interstitial nephritis, and urticaria [see Adverse Reactions (6) ]. For information about contraindications of antibacterial agents (clarithromycin and amoxicillin) indicated in combination with omeprazole, refer to the CONTRAINDICATIONS section of their package inserts.
Known hypersensitivity to any component of the formulation or substituted benzimidazoles (angioedema and anaphylaxis have occurred) (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS 1. Symptomatic response does not preclude the presence of gastric malignancy (5.1) 2. Atrophic gastritis: has been noted with long-term therapy (5.2 ) 3.
Acute interstitial nephritis has been observed in patients taking PPIs. ( 5.3) 4. Cyanocobalamin (vitamin B-12) Deficiency: Daily long-term use (e.g., longer than 3 years) may lead to malabsorption or a deficiency of cyanocobalamin.
( 5.4 ) 5. PPI therapy may be associated with increased risk of Clostridium difficile associated diarrhea. ( 5.5 ) 6.
Avoid concomitant use of omeprazole with clopidogrel. ( 5.6 ) 7. Bone Fracture: Long-term and multiple daily dose PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist or spine.
( 5.7 ) 8. Hypomagnesemia has been reported rarely with prolonged treatment with PPIs. ( 5.8 ) 9.
Avoid concomitant use of omeprazole with St.John’s Wort or rifampin due to the potential reduction in omeprazole concentrations. ( 5.9, 7.3 ) 10. Interactions with diagnostic investigations for Neuroendocrine Tumors: Increases in intragastric pH may result in hypergastrinemia and enterochromaffin-like cell hyperplasia and increased Choromogranin A levels which may interfere with diagnostic investigations for neuroendocrine tumors.
( 5.10 , 12.2 )
5.1Concomitant Gastric Malignancy Symptomatic response to therapy with omeprazole does not preclude the presence of gastric malignancy.
5.2Atrophic Gastritis Atrophic gastritis has been noted occasionally in gastric corpus biopsies from patients treated long-term with omeprazole.
5.3Acute Interstitial Nephritis Acute interstitial nephritis has been observed in patients taking PPIs including omeprazole. Acute interstitial nephritis may occur at any point during PPI therapy and is generally attributed to an idiopathic hypersensitivity reaction. Discontinue omeperazole if acute interstitial nephritis develops [see Contraindications ( 4 ) ].
5.4Cyanocobalamin (vitamin B-12) Deficiency Daily treatment with any acid-suppressing medications over a long period of time (e.g., longer than 3 years) may lead to malabsorption of cyanocobalamin (vitamin B-12) caused by hypo-or achlorhydria. Rare reports of cyanocobalamin deficiency occurring with acidsuppressing therapy have been reported in the literature. This diagnosis should be considered if clinical symptoms consistent with cyanocobalamin deficiency are observed.
5.5Clostridium difficile associated diarrhea Published observational studies suggest that PPI therapy like omeprazole may be associated with an increased risk of Clostridium difficile associated diarrhea, especially in hospitalized patients. This diagnosis should be considered for diarrhea that does not improve [see Adverse Reactions (6.2) ]. Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
Clostridium diffficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents. For more information specific to antibacterial agents (clarithromycin and amoxicillin) indicated for use in combination with omeprazole, refer to WARNINGS and PRECAUTIONS sections of those package inserts.
5.6Interaction with Clopidogrel Avoid concomitant use of omeprazole with clopidogrel. Clopidogrel is a prodrug. Inhibition of platelet aggregation by clopidogrel is entirely due to an active metabolite.
The metabolism of clopidogrel to its active metabolite can be impaired by use with concomitant medications, such as omeprazole, that inhibit CYP2C19 activity. Concomitant use of clopidogrel with 80 mg omeprazole reduces the pharmacological activity of clopidogrel, even when administered 12 hours apart. When using omeprazole, consider alternative anti-platelet therapy [see Drug Interactions (7.3 ) and Pharmacokinetics ( 12.3 ) ].
5.7Bone Fracture Several published observational studies suggest that proton pump inhibitor (PPI) therapy may be associated with an increased r…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Adults: Most common adverse reactions (incidence >2%) are 2. Headache, abdominal pain, nausea, diarrhea, vomiting, and flatulence. (6) Pediatric patients (2 to 16 years of age): Safety profile similar to that in adults, except that respiratory system events and fever were the most frequently reported reactions in pediatric studies.
(8.4) To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience with Omeprazole Monotherapy Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety data described below reflects exposure to omeprazole delayed-release capsules in 3096 patients from worldwide clinical trials (465 patients from US studies and 2,631 patients from international studies).
Indications clinically studied in US trials included duodenal ulcer, resistant ulcer, and Zollinger-Ellison syndrome. The international clinical trials were double blind and open-label in design. The most common adverse reactions reported (i.e., with an incidence rate ≥ 2%) from omeprazole-treated patients enrolled in these studies included headache (6.9%), abdominal pain (5.2%), nausea (4%), diarrhea (3.7%), vomiting (3.2%), and flatulence (2.7%).
Additional adverse reactions that were reported with an incidence ≥1% included acid regurgitation (1.9%), upper respiratory infection (1.9%), constipation (1.5%), dizziness (1.5%), rash (1.5%), asthenia (1.3%), back pain (1.1%), and cough (1.1%). The clinical trial safety profile in patients greater than 65 years of age was similar to that in patients 65 years of age or less. The clinical trial safety profile in pediatric patients who received omeprazole delayed-release capsules was similar to that in adult patients.
Unique to the pediatric population, however, adverse reactions of the respiratory system were most frequently reported in the 2 to 16 year age group (18.5%). Similarly, accidental injuries were reported frequently in the 2 to 16 year age group (3.8%). [See Use in Specific Populations (8.4) ]
6.2Clinical Trials Experience with Omeprazole in Combination Therapy for H. pylori Eradication In clinical trials using either dual therapy with omeprazole and clarithromycin, or triple therapy with omeprazole, clarithromycin, and amoxicillin, no adverse reactions unique to these drug combinations were observed. Adverse reactions observed were limited to those previously reported with omeprazole, clarithromycin, or amoxicillin alone. Dual Therapy (omeprazole/clarithromycin) Adverse reactions observed in controlled clinical trials using combination therapy with omeprazole and clarithromycin (n = 346) that differed from those previously described for omeprazole alone were taste perversion (15%), tongue discoloration (2%), rhinitis (2%), pharyngitis (1%) and flu-syndrome (1%).
(For more information on clarithromycin, refer to the clarithromycin prescribing information, Adverse Reactions section). Triple Therapy (omeprazole/clarithromycin/amoxicillin) The most frequent adverse reactions observed in clinical trials using combination therapy with omeprazole, clarithromycin, and amoxicillin (n = 274) were diarrhea (14%), taste perversion (10%), and headache (7%). None of these occurred at a higher frequency than that reported by patients taking antimicrobial agents alone.
(For more information on clarithromycin or amoxicillin, refer to the respective prescribing information, Adverse Reactions sections).
6.3Post-marketing Experience The following adverse reactions have been identified during post-approval use of omeprazole delayed-release capsules. Because these reactions are voluntarily reported from a population of uncertain size, it is not always possible to rel…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS 1. Atazanavir and nelfinavir: omeprazole reduces plasma levels of atazanavir and nelfinavir. Concomitant use is not recommended (7.1) 2.
Saquinavir: omeprazole increases plasma levels of saquinavir. Monitor for toxicity and consider dose reduction of saquinavir (7.1) 3. May interfere with drugs for which gastric pH affects bioavailability (e.g., ketoconazole, iron salts, erlotinib, ampicillin esters, digoxin and mycophenolate mofetil).
Patients treated with omeprazole and digoxin may need to be monitored for increases in digoxin toxicity. (7.2 ) 4. Clopidogrel: omeprazole decreases exposure to the active metabolite of clopidogrel.
(7.3 , 12.3 ) 5. Clopidogrel: Omeprazole decreases exposure to the active metabolite of clopidogrel. (7.3 , 12.3 ) 6.
Cilostazol: omeprazole increases systemic exposure of cilostazol and one of its active metabolites. Consider dose reduction of cilostazol. (7.3 ) 7.
Drugs metabolized by cytochrome P450 (e.g., diazepam, warfarin, phenytoin, cyclosporine, disulfiram, benzodiazepines): omeprazole can prolong their elimination. Monitor and determine need for dose adjustments (7.3) 8. Patients treated with proton pump inhibitors and warfarin may need to be monitored for increases in INR and prothrombin time (7.3) 9.
Combined inhibitor of CYP2C19 and 3A4 (e.g. voriconazole) may raise omeprazole levels (7.3) 10. Tacrolimus: omeprazole may increase serum levels of tacrolimus (7.4) 11. Methotrexate: Omeprazole may increase serum levels of methotrexate ( 7.7 )
7.1Interference with Antiretroviral Therapy Concomitant use of atazanavir and nelfinavir with proton pump inhibitors is not recommended. Co-administration of atazanavir with proton pump inhibitors is expected to substantially decrease atazanavir plasma concentrations and may result in a loss of therapeutic effect and the development of drug resistance. Co-administration of saquinavir with proton pump inhibitors is expected to increase saquinavir concentrations, which may increase toxicity and require dose reduction.
Omeprazole has been reported to interact with some antiretroviral drugs. The clinical importance and the mechanisms behind these interactions are not always known. Increased gastric pH during omeprazole treatment may change the absorption of the antiretroviral drug.
Other possible interaction mechanisms are via CYP 2C19. Reduced concentrations of atazanavir and nelfinavir For some antiretroviral drugs, such as atazanavir and nelfinavir, decreased serum levels have been reported when given together with omeprazole. Following multiple doses of nelfinavir (1250 mg, twice daily) and omeprazole (40 mg daily), AUC was decreased by 36% and 92%, C max by 37% and 89% and C min by 39% and 75% respectively for nelfinavir and M8.
Following multiple doses of atazanavir (400 mg, daily) and omeprazole (40 mg, daily, 2 hr before atazanavir), AUC was decreased by 94%, C max by 96%, and C min by 95%. Concomitant administration with omeprazole and drugs such as atazanavir and nelfinavir is therefore not recommended. Increased concentrations of saquinavir For other antiretroviral drugs, such as saquinavir, elevated serum levels have been reported, with an increase in AUC by 82%, in C max by 75%, and in C min by 106%, following multiple dosing of saquinavir/ritonavir (1000/100 mg) twice daily for 15 days with omeprazole 40 mg daily co-administered days 11 to 15.
Therefore, clinical and laboratory monitoring for saquinavir toxicity is recommended during concurrent use with omeprazole. Dose reduction of saquinavir should be considered from the safety perspective for individual patients. There are also some antiretroviral drugs of which unchanged serum levels have been reported when given with omeprazole.
7.2Drugs for which Gastric pH can affect Bioavailability Due to its effects on gastric acid secretion, omeprazole can reduce the absorption of drugs where gastric pH is an important determinant of theirbioavailability. Like with other drugs th…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS 1. Pregnancy: Based on animal data may cause fetal harm (8.1) 2. Patients with hepatic impairment: Consider dose reduction, particularly for maintenance of healing erosive esophagitis (12.3)
8.1Pregnancy Pregnancy Category C Risk Summary There are no adequate and well-controlled studies with omeprazole in pregnant women. Available epidemiologic data fail to demonstrate an increased risk of major congenital malformations or other adverse pregnancy outcomes with first trimester omeprazole use. Teratogenicity was not observed in animal reproduction studies with administration of oral esomeprazole magnesium in rats and rabbits with doses about 68 times and 42 times, respectively, an oral human dose of 40 mg (based on a body surface area basis for a 60 kg person).
However, changes in bone morphology were observed in offspring of rats dosed through most of pregnancy and lactation at doses equal to or greater than approximately 34 times an oral human dose of 40 mg (see Animal Data). Because of the observed effect at high doses of esomeprazole magnesium on developing bone in rat studies, omeprazole should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Human Data Four published epidemiological studies compared the frequency of congenital abnormalities among infants born to women who used omeprazole during pregnancy with the frequency of abnormalities among infants of women exposed to H 2 -receptor antagonists or other controls.
A population-based retrospective cohort epidemiological study from the Swedish Medical Birth Registry, covering approximately 99% of pregnancies, from 1995-99, reported on 955 infants (824 exposed during the first trimester with 39 of these exposed beyond first trimester, and 131 exposed after the first trimester) whose mothers used omeprazole during pregnancy. The number of infants exposed in utero to omeprazole that had any malformation, low birth weight, low Apgar score, or hospitalization was similar to the number observed in this population.
The number of infants born with ventricular septal defects and the number of stillborn infants was slightly higher in the omeprazole-exposed infants than the expected number in this population. A population-based retrospective cohort study covering all live births in Denmark from 1996-2009, reported on 1,800 live births whose mothers used omeprazole during the first trimester of pregnancy and 837,317 live births whose mothers did not use any proton pump inhibitor. The overall rate of birth defects in infants born to mothers with first trimester exposure to omeprazole was 2.9% and 2.6% in infants born to mothers not exposed to any proton pump inhibitor during the first trimester.
A retrospective cohort study reported on 689 pregnant women exposed to either H 2 -blockers or omeprazole in the first trimester (134 exposed to omeprazole) and 1,572 pregnant women unexposed to either during the first trimester. The overall malformation rate in offspring born to mothers with first trimester exposure to omeprazole, an H 2 -blocker, or were unexposed was 3.6%, 5.5% and 4.1% respectively. A small prospective observational cohort study followed 113 women exposed to omeprazole during pregnancy (89% first trimester exposures).
The reported rates of major congenital malformations was 4% for the omeprazole group, 2% for controls exposed to non-teratogens, and 2.8% in disease-paired controls. Rates of spontaneous and elective abortions, preterm deliveries, gestational age at delivery, and mean birth weight were similar among the groups. Several studies have reported no apparent adverse short-term effects on the infant when single dose oral or intravenous omeprazole was administered to over 200 pregnant women as premedication for cesarean section under general anesthesia.
Animal Data Reproductive studies conducted with omeprazole in rats at oral doses up to 138 mg/kg/day (about 34 times an oral human dose o…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C Risk Summary There are no adequate and well-controlled studies with omeprazole in pregnant women. Available epidemiologic data fail to demonstrate an increased risk of major congenital malformations or other adverse pregnancy outcomes with first trimester omeprazole use. Teratogenicity was not observed in animal reproduction studies with administration of oral esomeprazole magnesium in rats and rabbits with doses about 68 times and 42 times, respectively, an oral human dose of 40 mg (based on a body surface area basis for a 60 kg person).
However, changes in bone morphology were observed in offspring of rats dosed through most of pregnancy and lactation at doses equal to or greater than approximately 34 times an oral human dose of 40 mg (see Animal Data). Because of the observed effect at high doses of esomeprazole magnesium on developing bone in rat studies, omeprazole should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Human Data Four published epidemiological studies compared the frequency of congenital abnormalities among infants born to women who used omeprazole during pregnancy with the frequency of abnormalities among infants of women exposed to H 2 -receptor antagonists or other controls.
A population-based retrospective cohort epidemiological study from the Swedish Medical Birth Registry, covering approximately 99% of pregnancies, from 1995-99, reported on 955 infants (824 exposed during the first trimester with 39 of these exposed beyond first trimester, and 131 exposed after the first trimester) whose mothers used omeprazole during pregnancy. The number of infants exposed in utero to omeprazole that had any malformation, low birth weight, low Apgar score, or hospitalization was similar to the number observed in this population.
The number of infants born with ventricular septal defects and the number of stillborn infants was slightly higher in the omeprazole-exposed infants than the expected number in this population. A population-based retrospective cohort study covering all live births in Denmark from 1996-2009, reported on 1,800 live births whose mothers used omeprazole during the first trimester of pregnancy and 837,317 live births whose mothers did not use any proton pump inhibitor. The overall rate of birth defects in infants born to mothers with first trimester exposure to omeprazole was 2.9% and 2.6% in infants born to mothers not exposed to any proton pump inhibitor during the first trimester.
A retrospective cohort study reported on 689 pregnant women exposed to either H 2 -blockers or omeprazole in the first trimester (134 exposed to omeprazole) and 1,572 pregnant women unexposed to either during the first trimester. The overall malformation rate in offspring born to mothers with first trimester exposure to omeprazole, an H 2 -blocker, or were unexposed was 3.6%, 5.5% and 4.1% respectively. A small prospective observational cohort study followed 113 women exposed to omeprazole during pregnancy (89% first trimester exposures).
The reported rates of major congenital malformations was 4% for the omeprazole group, 2% for controls exposed to non-teratogens, and 2.8% in disease-paired controls. Rates of spontaneous and elective abortions, preterm deliveries, gestational age at delivery, and mean birth weight were similar among the groups. Several studies have reported no apparent adverse short-term effects on the infant when single dose oral or intravenous omeprazole was administered to over 200 pregnant women as premedication for cesarean section under general anesthesia.
Animal Data Reproductive studies conducted with omeprazole in rats at oral doses up to 138 mg/kg/day (about 34 times an oral human dose of 40 mg on a body surface area basis) and in rabbits at doses up to 69 mg/kg/day (about 34 times an oral human dose of 40 mg on a body surface area basis) did not disclose any evidence for a teratogenic potential of omepr…
🧒 Pediatric Use ▾
8.4Pediatric Use Use of omeprazole in pediatric and adolescent patients 2 to 16 years of age for the treatment of GERD and maintenance of healing of erosive esophagitis is supported by a) extrapolation of results from adequate and well-controlled studies that supported the approval of omeprazole for adults, and b) safety and pharmacokinetic studies performed in pediatric and adolescent patients. [See Clinical Pharmacology, Pharmacokinetics, Pediatric for pharmacokinetic information (12.3) and Dosage and Administration (2) .
Adverse Reactions (6.1) and Clinical Studies (14.6) ]. The safety and effectiveness of omeprazole for the treatment of GERD in patients < 1 year of age have not been established. The safety and effectiveness of omeprazole for other pediatric uses have not been established.
Juvenile Animal Data In a juvenile rat toxicity study, esomeprazole was administered with both magnesium and strontium salts at oral doses about 34 to 57 times a daily human dose of 40 mg based on body surface area. Increases in death were seen at the high dose, and at all doses of esomeprazole, there were decreases in body weight, body weight gain, femur weight and femur length, and decreases in overall growth [see Nonclinical Toxicology ( 13.2 ) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Omeprazole was administered to over 2000 elderly individuals (≥ 65 years of age) in clinical trials in the U.S. and Europe. There were no differences in safety and effectiveness between the elderly and younger subjects. Other reported clinical experience has not identified differences in response between the elderly and younger subjects, but greater sensitivity of some older individuals cannot be ruled out.
Pharmacokinetic studies have shown the elimination rate was somewhat decreased in the elderly and bioavailability was increased. The plasma clearance of omeprazole was 250 mL/min (about half that of young volunteers) and its plasma half-life averaged one hour, about twice that of young healthy volunteers. However, no dosage adjustment is necessary in the elderly. [See Clinical Pharmacology (12.3) ]
🆘 Overdosage ▾
10 OVERDOSAGE Reports have been received of overdosage with omeprazole in humans. Doses ranged up to 2400 mg (120 times the usual recommended clinical dose). Manifestations were variable, but included confusion, drowsiness, blurred vision, tachycardia, nausea, vomiting, diaphoresis, flushing, headache, dry mouth, and other adverse reactions similar to those seen in normal clinical experience. [See Adverse Reactions (6) ] Symptoms were transient, and no serious clinical outcome has been reported when omeprazole was taken alone.
No specific antidote for omeprazole overdosage is known. Omeprazole is extensively protein bound and is, therefore, not readily dialyzable. In the event of overdosage, treatment should be symptomatic and supportive.
As with the management of any overdose, the possibility of multiple drug ingestion should be considered. For current information on treatment of any drug overdose, contact your local Poison Control Center. Single oral doses of omeprazole at 1350, 1339, and 1200 mg/kg were lethal to mice, rats, and dogs, respectively.
Animals given these doses showed sedation, ptosis, tremors, convulsions, and decreased activity, body temperature, and respiratory rate and increased depth of respiration.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Omeprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that suppress gastric acid secretion by specific inhibition of the H+/K+ ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the gastric mucosa, omeprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production. This effect is dose-related and leads to inhibition of both basal and stimulated acid secretion irrespective of the stimulus.
Animal studies indicate that after rapid disappearance from plasma, omeprazole can be found within the gastric mucosa for a day or more.
12.2Pharmacodynamics Antisecretory Activity After oral administration, the onset of the antisecretory effect of omeprazole occurs within one hour, with the maximum effect occurring within two hours. Inhibition of secretion is about 50% of maximum at 24 hours and the duration of inhibition lasts up to 72 hours. The antisecretory effect thus lasts far longer than would be expected from the very short (less than one hour) plasma half-life, apparently due to prolonged binding to the parietal H+/K+ ATPase enzyme.
When the drug is discontinued, secretory activity returns gradually, over 3 to 5 days. The inhibitory effect of omeprazole on acid secretion increases with repeated once-daily dosing, reaching a plateau after four days. Results from numerous studies of the antisecretory effect of multiple doses of 20 mg and 40 mg of omeprazole in normal volunteers and patients are shown below.
The “max” value represents determinations at a time of maximum effect (2 to 6 hours after dosing), while “min” values are those 24 hours after the last dose of omeprazole. Table 1 Range of Mean Values from Multiple Studies of the Mean Antisecretory Effects of Omeprazole After Multiple Daily Dosing Omeprazole 20 mg Omeprazole 40 mg Parameter Max Min Max Min % Decrease in Basal Acid Output 78* 58 to 80 94* 80 to 93 % Decrease in Peak Acid Output 79* 50 to 59 88* 62 to 68 % Decrease in 24–hr Intragastric Acidity 80 to 97 92 to 94 * Single Studies Single daily oral doses of omeprazole ranging from a dose of 10 mg to 40 mg have produced 100% inhibition of 24-hour intragastric acidity in some patients.
Serum Gastrin Effects In studies involving more than 200 patients, serum gastrin levels increased during the first 1 to 2 weeks of once-daily administration of therapeutic doses of omeprazole in parallel with inhibition of acid secretion. No further increase in serum gastrin occurred with continued treatment. In comparison with histamine H2-receptor antagonists, the median increases produced by 20 mg doses of omeprazole were higher (1.3 to 3.6 fold vs.
1.1to 1.8 fold increase). Gastrin values returned to pretreatment levels, usually within 1 to 2 weeks after discontinuation of therapy. Increased gastrin causes enterochromaffin-like cell hyperplasia and increased serum Chromogranin A (CgA) levels.
The increased CgA levels may cause false positive results in diagnostic investigations for neuroendocrine tumors. Enterochromaffin-like (ECL) Cell Effects Human gastric biopsy specimens have been obtained from more than 3000 patients treated with omeprazole in long-term clinical trials. The incidence of ECL cell hyperplasia in these studies increased with time; however, no case of ECL cell carcinoids, dysplasia, or neoplasia has been found in these patients. [See Clinical Pharmacology (12) ] However, these studies are of insufficient duration and size to rule out the possible influence of long-term administration of omeprazole on the development of any premalignant or malignant conditions.
Other Effects Systemic effects of omeprazole in the CNS, cardiovascular and respiratory systems have not been found to date. Omeprazole, given in oral doses of 30 or 40 mg for 2 to 4 weeks, had no effect on thyroid function, car…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Omeprazole belongs to a class of antisecretory compounds, the substituted benzimidazoles, that suppress gastric acid secretion by specific inhibition of the H+/K+ ATPase enzyme system at the secretory surface of the gastric parietal cell. Because this enzyme system is regarded as the acid (proton) pump within the gastric mucosa, omeprazole has been characterized as a gastric acid-pump inhibitor, in that it blocks the final step of acid production. This effect is dose-related and leads to inhibition of both basal and stimulated acid secretion irrespective of the stimulus.
Animal studies indicate that after rapid disappearance from plasma, omeprazole can be found within the gastric mucosa for a day or more.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Omeprazole delayed-release capsules, USP 10 mg are off-white to pale yellow, elliptical to spherical pellets filled in size ‘3’ hard gelatin capsules with opaque lavender coloured cap and opaque yellow coloured body, imprinted on cap ‘OMEPRAZOLE 10 mg’ and on body ‘R157’ with black ink. The capsules are supplied in bottles of 30, 60 and 90. Bottles of 60 NDC 63187-805-60 Bottles of 90 NDC 63187-805-90 Storage Store omeprazole delayed-release capsules in a tight container protected from light and moisture.
Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION The active ingredient in omeprazole delayed-release capsules is a substituted benzimidazole, 5-methoxy-2-[[(4-methoxy-3, 5-dimethyl-2-pyridinyl) methyl] sulfinyl]-1H-benzimidazole, a compound that inhibits gastric acid secretion. Its empirical formula is C 17 H 19 N 3 O 3 S, with a molecular weight of 345.42. The structural formula is: Omeprazole is a white to off-white powder.
Melts between 150°C and 160°C with decomposition. It is soluble in dichloromethane, sparingly soluble in methanol and in alcohol. Omeprazole delayed-release capsules meets USP Dissolution Test 2 .
Omeprazole is supplied as delayed-release capsules for oral administration. Each delayed-release capsule contains either 10 mg, 20 mg or 40 mg of omeprazole in the form of enteric-coated granules with the following inactive ingredients: crospovidone, hypromellose, magnesium stearate, mannitol, meglumine, methacrylic acid copolymer, poloxamer, povidone and triethyl citrate. The capsule shells contains: D&C Red No.
28, FD&C Blue No. 1, FD&C Red No. 40, FD&C Yellow No.
6, yellow iron oxide, gelatin, silicon dioxide, sodium lauryl sulphate and titanium dioxide. Imprinting ink contains: D&C Yellow No. 10 aluminum lake, FD&C Blue No.
1 aluminum lake, FD&C Blue No. 2 aluminum lake, FD&C Red No. 40 aluminum lake, n-butyl alcohol, pharmaceutical glaze, propylene glycol, SDA-3A alcohol and synthetic black iron oxide. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-Approved Medication Guide Omeprazole delayed-release capsules should be taken before eating. Patients should be informed that the omeprazole delayed-release capsules should be swallowed whole. For patients who have difficulty swallowing capsules, the contents of an omeprazole delayed-release capsule can be added to applesauce.
One tablespoon of applesauce should be added to an empty bowl and the capsule should be opened. All of the pellets inside the capsule should be carefully emptied on the applesauce. The pellets should be mixed with the applesauce and then swallowed immediately with a glass of cool water to ensure complete swallowing of the pellets.
The applesauce used should not be hot and should be soft enough to be swallowed without chewing. The pellets should not be chewed or crushed. The pellets/applesauce mixture should not be stored for future use.
Advise patients to immediately report and seek care for diarrhea that does not improve. This may be a sign of Clostridium difficile associated diarrhea [see Warnings and Precautions ( 5.5) ]. Advise patients to immediately report and seek care for any cardiovascular or neurological symptoms including palpitations, dizziness, seizures, and tetany as these may be signs of hypomagnesemia [see Warnings and Precautions ( 5.8) ]
💬 Medication Guide ▾
MEDICATION GUIDE OMEPRAZOLE DELAYED-RELEASE CAPSULES, USP Read this Medication Guide before you start taking omeprazole delayed-release capsules and each time you get a refill. There may be new information. This information does not take the place of talking with your doctor about your medical condition or your treatment.
What is the most important information I should know about omeprazole delayed-release capsules? Omeprazole delayed-release capsules may help your acid-related symptoms, but you could still have serious stomach problems. Talk with your doctor.
Omeprazole delayed-release capsules can cause serious side effects, including: 1. Diarrhea . Omeprazole delayed-release capsules may increase your risk of getting severe diarrhea.
This diarrhea may be caused by an infection (Clostridium difficile) in your intestines. Call your doctor right away if you have watery stool, stomach pain, and fever that does not go away. 1.
Bone fractures . People who take multiple daily doses of proton pump inhibitor medicines for a long period of time (a year or longer) may have an increased risk of fractures of the hip, wrist, or spine. You should take omeprazole delayed-release capsules exactly as prescribed, at the lowest dose possible for your treatment and for the shortest time needed.
Talk to your doctor about your risk of bone fracture if you take omeprazole delayed-release capsules. Omeprazole delayed-release capsules can have other serious side effects. See “What are the possible side effects of omeprazole delayed-release capsules?” What is omeprazole delayed-release capsule?
Omeprazole delayed-release capsule is a prescription medicine called a proton pump inhibitor (PPI). Omeprazole delayed-release capsules reduces the amount of acid in your stomach. Omeprazole delayed-release capsules are used in adults: 1. for up to 8 weeks for the healing of duodenal ulcers.
The duodenal area is the area where food passes when it leaves the stomach. 2. with certain antibiotics for 10 to 14 days to treat an infection caused by bacteria called H. pylori. If needed, your doctor may decide to prescribe another 14 to 18 days of omeprazole delayed-release capsules by itself after the antibiotics.
Sometimes H. pylori bacteria can cause duodenal ulcers. The infection needs to be treated to prevent the ulcers from coming back. 3. for up to 8 weeks for healing stomach ulcers 4. for up to 4 weeks to treat heartburn and other symptoms that happen with gastroesophageal reflux disease (GERD).
5. GERD happens when acid in your stomach backs up into the tube (esophagus) that connects your mouth to your stomach. This may cause a burning feeling in your chest or throat, sour taste, or burping.
6. for up to 8 weeks to heal acid-related damage to the lining of the esophagus (called erosive esophagitis or EE). If needed, your doctor may decide to prescribe another 4 weeks of omeprazole delayed-release capsules. 7. to maintain healing of the esophagus.
It is not known if omeprazole delayed-release capsules are safe and effective when used for longer than 12 months (1 year) for this purpose. 8. for the long-term treatment of conditions where your stomach makes too much acid. This includes a rare condition called Zollinger-Ellison Syndrome.
For children 1 to 16 years of age, omeprazole delayed-release capsules are used: 1. for up to 4 weeks to treat heartburn and other symptoms that happen with gastroesophageal reflux disease (GERD). 2. for up to 8 weeks to treat gastroesophageal reflux disease (GERD) with acid-related damage to the lining of the esophagus [called erosive esophagitis (or EE) due to acid-mediated GERD]. 3. to maintain healing of the esophagus.
It is not known if omeprazole delayed-release capsules are safe and effective when used longer than 12 months (1 year) for this purpose. For children 1 month to less than 12 months (1 year) of age, omeprazole delayed-release capsules are used: 1. for up to 6 weeks to treat gastroesophageal reflux disease (GERD)…