
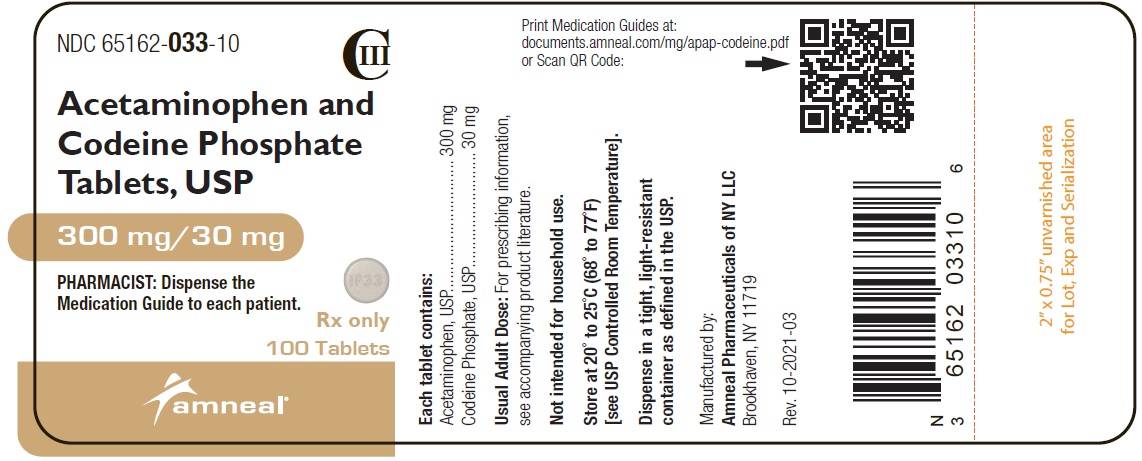
Acetaminophen and Codeine 300 mg; 30 mg Tablet, 500-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anilides class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of acetaminophen and codeine is used to relieve pain. Acetaminophen is in a class of medications called analgesics (pain relievers) and antipyretics (fever reducers). It works by changing the way the body senses pain and by cooling the body. Codeine belongs to a class of medications called opiate (narcotic) analgesics. When codeine is used to treat pain, it works by changing the way the brain and nervous system respond to pain.
Read the full MedlinePlus article ↗- This combination is used to treat mild to moderate pain — things like post-surgical pain or musculoskeletal injuries — when other options like ibuprofen or acetaminophen alone have...
- What exactly is this medication for, and is it really necessary for me to take an opioid?
- The oral solution needs to be measured very carefully, because errors between milligrams and milliliters — or mixing it up with a different strength — can be dangerous. Always use...
- How should I take the liquid version without making a dosing mistake?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.5009 | $250.45 / 500 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 00406-0484-01 | SpecGx | 100 tablets | $0.243 | AA | Availability likely | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 13107-0059-01 | Aurolife | 100 tablets | $0.243 | AA | Availability likely | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 64380-0446-01 | Strides | 100 tablets | $0.243 | AA | Availability likely | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 71930-0055-12 | Eywa | 100 tablets | $0.243 | AA | Availability likely | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 49999-0060-30 | Quality | 30 tablets | — | AA | Discontinued | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 50090-4610-00 | A-S | 10 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 50090-4611-01 | A-S | 16 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 58118-4484-08 | Clinical | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 60760-0581-30 | St. | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 60760-0938-30 | ST. | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine 300 mg/1; 30 mg 61919-0484-18 | Direct_Rx | 18 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 63187-0106-15 | Proficient | 15 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 63187-0491-20 | Proficient | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 63187-0815-15 | Proficient | 15 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 63629-5666-01 | Bryant | 10 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 64850-0642-12 | Elite | 120 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mgthis 65162-0033-50 | Amneal | 500 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 67296-1772-06 | RedPharm | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 67296-2239-02 | Redpharm | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 67544-0002-09 | Aphena | 9 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-3651-06 | NuCare | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-3658-02 | NuCare | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-3798-06 | NuCare | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-3824-06 | NuCare | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-4475-02 | NuCare | 12 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-4533-02 | NuCare | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-4673-02 | NuCare | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-5010-04 | NuCare | 4 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68788-7835-01 | Preferred | 15 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 70518-2628-00 | REMEDYREPACK | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 70518-3705-00 | REMEDYREPACK | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 70518-4104-00 | REMEDYREPACK | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 71335-0256-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 71335-0545-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 71335-1522-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 71335-1818-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 71335-2916-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 72162-2001-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 76420-0103-03 | Asclemed | 3 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 76420-0821-00 | Asclemed | 100 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 80425-0527-01 | Advanced | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 80425-0529-01 | Advanced | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 82804-0181-30 | Proficient | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 82804-0283-20 | Proficient | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 87441-0009-01 | Unit | 30 tablets | — | AA | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65162-0033-10 | 100 TABLET in 1 BOTTLE (65162-033-10) | $0.2432 / ea | $24.32 | 2008-05-29 | Active |
| 65162-0033-11 | 1000 TABLET in 1 BOTTLE (65162-033-11) | — | — | 2008-05-29 | Active |
| 65162-0033-50 You're viewing this | 500 TABLET in 1 BOTTLE (65162-033-50) | — | — | 2008-05-29 | Active |
You're viewing one of 3 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 100 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 65162-0033-50?
What is the difference between NDC 65162-0033-50 and NDC 65162-0033-10?
What NDC number is used to bill for this package of Acetaminophen and Codeine 300 mg; 30 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF ACETAMINOPHEN AND CODEINE PHOSPHATE TABLETS Addiction, Abuse and Misuse Because the use of acetaminophen and codeine phosphate tablets exposes patients and other users to the risks of opioid addiction, abuse and misuse, which can lead to overdose and death, assess each patient’s risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions (see WARNINGS ). Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of acetaminophen and codeine phosphate tablets, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of acetaminophen and codeine phosphate tablets are essential (see WARNINGS ). Accidental Ingestion Accidental ingestion of even one dose of acetaminophen and codeine phosphate tablets, especially by children, can result in a fatal overdose of acetaminophen and codeine phosphate (see WARNINGS ). Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death.
Reserve concomitant prescribing of acetaminophen and codeine phosphate tablets and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate (see WARNINGS , Drug Interactions ). Neonatal Opioid Withdrawal Syndrome (NOWS) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome , which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery (see WARNINGS ).
Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS) Healthcare providers are strongly encouraged to complete a REMS-compliant education program and to counsel patients and caregivers on serious risks, safe use, and the importance of reading the Medication Guide with each prescription (see WARNINGS ). Ultra-Rapid Metabolism of Codeine and Other Risk Factors for Life-Threatening Respiratory Depression in Children Life-threatening respiratory depression and death have occurred in children who received codeine.
Most of the reported cases occurred following tonsillectomy and/or adenoidectomy and many of the children had evidence of being ultra-rapid metabolizers of codeine due to a CYP2D6 polymorphism (see WARNINGS , PRECAUTIONS; Information for Patients/Caregivers , Nursing Mothers ). Acetaminophen and codeine phosphate tablets are contraindicated in children younger than 12 years of age and in children younger than 18 years of age following tonsillectomy and/or adenoidectomy (see CONTRAINDICATIONS ). Avoid the use of acetaminophen and codeine phosphate tablets in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of codeine.
Interactions with Drugs Affecting Cytochrome P450 Isoenzymes The effects of concomitant use or discontinuation of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with codeine are complex. Use of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with acetaminophen and codeine phosphate tablets requires careful consideration of the effects on the parent drug, codeine, and the active metabolite, morphine (see WARNINGS , PRECAUTIONS : Drug Interactions ). Hepatotoxicity Acetaminophen has been associated with cases of acute liver failure, at times resulting in liver transplant and death.
Most of the cases of liver injury are associated with the use of acetaminophen at doses that exceed 4,000 milligrams per day, and often involve more than one acetaminophen-containing product (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Acetaminophen and codeine phosphate tablets are indicated for the management of mild to moderate pain, where treatment with an opioid is appropriate and for which alternative treatments are inadequate. Limitations of Use Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy (see WARNINGS ), reserve opioid analgesics, including acetaminophen and codeine phosphate tablets, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Important Dosage and Administration Instructions Acetaminophen and codeine phosphate tablets should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals (see WARNINGS ). Because the risk of overdose increases as opioid doses increase, reserve titration to higher doses of acetaminophen and codeine phosphate tablets for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks.
Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic. Clinical guidelines on opioid prescribing for some acute pain conditions are available. There is variability in the opioid analgesic dose and duration needed to adequately manage pain due both to the cause of pain and to individual patient factors.
Initiate the dosing regimen for each patient individually, taking into account the patient’s underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse (see WARNINGS ). Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with acetaminophen and codeine phosphate tablets. Consider this risk when selecting an initial dose and when making dose adjustments (see WARNINGS ).
Patient Access to an Opioid Overdose Reversal Agent for the Emergency Treatment of Opioid Overdose Inform patients and caregivers about opioid overdose reversal agents (e.g., naloxone, nalmefene). Discuss the importance of having access to an opioid overdose reversal agent, especially if the patient has risk factors for overdose (e.g., concomitant use of CNS depressants, a history of opioid use disorder, or prior opioid overdose) or if there are household members (including children) or other close contacts at risk for accidental ingestion or opioid overdose.
The presence of risk factors for overdose should not prevent the management of pain in any patient (see WARNINGS; Addiction, Abuse, and Misuse ; Life-Threatening Respiratory Depression ; Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants ). Discuss the options for obtaining an opioid overdose reversal agent (e.g., prescription, over-the-counter, or as part of a community-based program). There are important differences among the opioid overdose reversal agents, such as route of administration, product strength, approved patient age range, and pharmacokinetics.
Be familiar with these differences, as outlined in the approved labeling for those products, prior to recommending or prescribing such an agent. Initial Dosage Use of Acetaminophen and Codeine Phosphate Tablets as the First Opioid Analgesic Initiate treatment with acetaminophen and codeine phosphate tablets in a dosing range of 300 mg to 600 mg of acetaminophen and 30 mg to 60 mg of codeine phosphate every 4 hours as needed for pain, at the lowest dose necessary to achieve adequate analgesia. Titrate the dose based upon the individual patient’s response to their initial dose of acetaminophen and codeine phosphate tablets.
The usual adult dosage is: Acetaminophen and Codeine Phosphate Tablets (codeine 30 mg and acetaminophen 300 mg): Take 1 to 2 tablets every 4 hours as needed for pain. Single Doses (Range) Maximum 24-Hour Dose Codeine Phosphate 30 mg to 60 mg 360 mg Acetaminophen 300 mg to 1,000 mg 4,000 mg The prescriber must determine the number of tablets per dose, and the maximum number of tablets per 24 hours, based upon the above dosage guidance. This information should be conveyed in the prescription.
Conversion from Other Opioids to Acetaminophen and Codeine Phosph…
⛔ Contraindications ▾
CONTRAINDICATIONS Acetaminophen and codeine phosphate tablets are contraindicated for: All children younger than 12 years of age (see WARNINGS ). Post-operative management in children younger than 18 years of age following tonsillectomy and/or adenoidectomy (see WARNINGS ). Acetaminophen and codeine phosphate tablets are contraindicated in patients with: significant respiratory depression (see WARNINGS ). acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment (see WARNINGS ). concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days (see WARNINGS ). known or suspected gastrointestinal obstruction, including paralytic ileus (see WARNINGS ). hypersensitivity to codeine, acetaminophen, or any of the formulation excipients (e.g., anaphylaxis) (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Addiction, Abuse, and Misuse Acetaminophen and codeine phosphate tablets contain codeine. Codeine in combination with acetaminophen, is a Schedule III controlled substance. As an opioid, acetaminophen and codeine phosphate tablets expose users to the risks of addiction, abuse, and misuse (see DRUG ABUSE AND DEPENDENCE ).
Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed acetaminophen and codeine phosphate tablets. Addiction can occur at recommended dosages and if the drug is misused or abused. The risk of opioid-related overdose or overdose-related death is increased with higher opioid doses, and this risk persists over the course of therapy.
In postmarketing studies, addiction, abuse, misuse, and fatal and non-fatal opioid overdose were observed in patients with long-term opioid use (see ADVERSE REACTIONS ). Assess each patient’s risk for opioid addiction, abuse, or misuse prior to prescribing acetaminophen and codeine phosphate tablets, and reassess all patients receiving acetaminophen and codeine phosphate tablets for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression).
The potential for these risks should not, however, prevent the proper management of pain in any given patient. Patients at increased risk may be prescribed opioids such as acetaminophen and codeine phosphate tablets, but use in such patients necessitates intensive counseling about the risks and proper use of acetaminophen and codeine phosphate tablets along with frequent reevaluation for signs of addiction, abuse, and misuse. Consider recommending or prescribing an opioid overdose reversal agent (see WARNINGS ; DOSAGE AND ADMINISTRATION ).
Opioids are sought for nonmedical use and are subject to diversion from legitimate prescribed use. Consider these risks when prescribing or dispensing acetaminophen and codeine phosphate tablets. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity and advising the patient on careful storage of the drug during the course of treatment and proper disposal of unused drug (see PRECAUTIONS; Information for Patients/Caregivers ).
Contact local state professional licensing board or state-controlled substances authority for information on how to prevent and detect abuse or diversion of this product. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death.
Management of respiratory depression may include close observation, supportive measures, and use of opioid overdose reversal agents (e.g., naloxone, nalmefene), depending on the patient’s clinical status (see OVERDOSAGE ). Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids. While serious, life-threatening, or fatal respiratory depression can occur at any time during the use of acetaminophen and codeine phosphate tablets, the risk is greatest during the initiation of therapy or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of acetaminophen and codeine phosphate tablets are essential (see DOSAGE AND ADMINISTRATION ). Overestimating the acetaminophen and codeine phosphate tablets dosage when converting patients from another opioid product can result in a fatal overdose with the first dose. Accidental ingestion of acetaminophen and codeine phosphate tablets, especially by children, can result in respiratory depression and death due to an overdose of codeine.
Educate patients and caregivers on how to recognize respiratory depression and emphasize the im…
🆘 Overdosage ▾
OVERDOSAGE Following an acute overdosage, toxicity may result from codeine or acetaminophen. Clinical Presentation Codeine Acute overdose with codeine can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations (see CLINICAL PHARMACOLOGY ).
Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication. Acetaminophen Dose-dependent, potentially fatal hepatic necrosis is the most serious adverse effect of acetaminophen overdose. Renal tubular necrosis, hypoglycemic coma, and coagulation defects may also occur.
Early symptoms following a potentially hepatotoxic overdose may include; anorexia, nausea, vomiting, diaphoresis, pallor and general malaise. Clinical and laboratory evidence of hepatic toxicity may not be apparent until 48 to 72 hours post-ingestion. Treatment of Overdose Codeine In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed.
Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or serious arrhythmias will require advanced life-support measures. For clinically significant respiratory or circulatory depression secondary to opioid overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene.
Because the duration of opioid reversal is expected to be less than the duration of action of codeine in acetaminophen and codeine phosphate tablets, frequently evaluate the patient until spontaneous respiration is reliably reestablished. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product’s prescribing information. In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome.
The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the reversal agent should be begun with care and by titration with smaller than usual doses of the reversal agent. Acetaminophen Gastric decontamination with activated charcoal should be administered just prior to N-acetylcysteine (NAC) to decrease systemic absorption if acetaminophen ingestion is known or suspected to have occurred within a few hours of presentation.
Serum acetaminophen levels should be obtained immediately if the patient presents 4 hours or more after ingestion to assess potential risk of hepatotoxicity; acetaminophen levels drawn less than 4 hours post-ingestion may be misleading. To obtain the best possible outcome, (NAC) should be administered as soon as possible where impending or evolving liver injury is suspected. Intravenous NAC may be administered when circumstances preclude oral administration.
Vigorous supportive therapy is required in severe intoxication. Procedures to limit the continuing absorption of the drug must be readily performed since the hepatic injury is dose-dependent and occurs early in the course of intoxication.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Codeine is an opioid agonist relatively selective for the mu-opioid receptor, but with a much weaker affinity than morphine. The analgesic properties of codeine have been speculated to come from its conversion to morphine, although the exact mechanism of analgesic action remains unknown. The precise mechanism of the analgesic properties of acetaminophen is not established but is thought to involve central actions.
Pharmacodynamics Effects on the Central Nervous System Codeine produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Codeine causes miosis, even in total darkness.
Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Codeine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum.
Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects on the Cardiovascular System Codeine produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, sweating, and/or orthostatic hypotension. Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans (see ADVERSE REACTIONS ).
They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date (see ADVERSE REACTIONS ).
Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of codeine for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome, and/or the development of analgesic tolerance (see DOSAGE AND ADMINISTRATION ). Concentration–Adverse Reaction Relationships There is a relationship between increasing codeine plasma concentration and increasing frequency of dose-related opioid adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression.
In opioid-tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions (see DOSAGE AND ADMINISTRATION ). Pharmacokinetics The behavior of the individual components is described below. Codei…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Acetaminophen and Codeine Phosphate Tablets, USP, 300 mg/30 mg are white, round, flat, beveled edged tablets debossed “IP 33” on obverse and “3” on reverse. They are available as follows: Bottles of 100: NDC 65162-033-10 Bottles of 500: NDC 65162-033-50 Bottles of 1,000: NDC 65162-033-11 Store Acetaminophen and Codeine Phosphate Tablets, USP 300 mg/30 mg between 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Dispense in tight, light-resistant container as defined in the USP.
Store acetaminophen and codeine phosphate tablets securely and dispose of properly (see PRECAUTIONS; Information for Patients/ Caregivers ). Manufactured by: Amneal Pharmaceuticals of NY, LLC Brookhaven, NY 11719 Rev. 12-2025-14
📋 Description ▾
DESCRIPTION Acetaminophen and codeine phosphate tablets, USP are supplied in tablet form for oral administration. Acetaminophen, USP, 4'-hydroxyacetanilide, a slightly bitter, white, odorless, crystalline powder, is a non-opiate, non-salicylate analgesic and antipyretic. It has the following structural formula: Codeine phosphate, USP, 7,8-didehydro-4, 5α-epoxy-3-methoxy-17-methylmorphinan-6α-ol phosphate (1:1) (salt) hemihydrate, a white crystalline powder, is a narcotic analgesic and antitussive.
It has the following structural formula: Each Acetaminophen and Codeine Phosphate Tablet, USP (300 mg/30 mg) contains: Acetaminophen, USP .................................................. 300 mg Codeine Phosphate, USP .............................................. 30 mg In addition, each acetaminophen and codeine phosphate tablet, USP contains the following inactive ingredients: croscarmellose sodium, crospovidone, lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone, pregelatinized starch and stearic acid.
1 2
💬 Medication Guide ▾
Medication Guide Acetaminophen and Codeine Phosphate (a seet’ a min’ oh fen and koe’ deen fos’ fate) Tablets CIII Acetaminophen and Codeine Phosphate Tablets are: A strong prescription pain medicine that contains an opioid (narcotic) that is used to manage mild to moderate pain, when other pain treatments such as non-opioid pain medicines do not treat your pain well enough or you cannot tolerate them. An opioid pain medicine that can put you at risk for overdose and death. Even if you take your dose correctly as prescribed, you are at risk for opioid addiction, abuse, and misuse that can lead to death.
Important information about Acetaminophen and Codeine Phosphate Tablets: Get emergency help or call 911 right away if you take too much acetaminophen and codeine phosphate tablets (overdose) . When you first start taking acetaminophen and codeine phosphate tablets, when your dose is changed, or if you take too much (overdose), serious or life-threatening breathing problems that can lead to death may occur. Ask your healthcare provider about medicines like naloxone or nalmefene that can be used in an emergency to reverse an opioid overdose.
Taking acetaminophen and codeine phosphate tablets with other opioid medicines, benzodiazepines, gabapentinoids (gabapentin or pregabalin), alcohol, or other central nervous system depressants (including street drugs) can cause severe drowsiness, decreased awareness, breathing problems coma and death. Never give anyone else your acetaminophen and codeine phosphate tablets. They could die from taking it.
Selling or giving away acetaminophen and codeine phosphate tablets is against the law. Store acetaminophen and codeine phosphate tablets securely, out of sight and reach of children and in a location not accessible by others, including visitors to the home. Important Information Guiding Use in Pediatric Patients: Do not give acetaminophen and codeine phosphate tablets to a child younger than 12 years of age.
Do not give acetaminophen and codeine phosphate tablets to a child younger than 18 years of age after surgery to remove the tonsils and/or adenoids. Avoid giving acetaminophen and codeine phosphate tablets to children between 12 to 18 years of age who have risk factors for breathing problems such as obstructive sleep apnea, obesity, or underlying lung problems. Do not take Acetaminophen and Codeine Phosphate Tablets if you have: severe asthma, trouble breathing, or other lung problems. a bowel blockage or narrowing of the stomach or intestines. previously had an allergic reaction to codeine or acetaminophen.
Before taking Acetaminophen and Codeine Phosphate Tablets, tell your healthcare provider if you have a history of: head injury, seizures liver, kidney, thyroid problems problems urinating pancreas or gallbladder problems abuse of street or prescription drugs, alcohol addiction, opioid overdose, or mental health problems. Have been told by your healthcare provider that you are a “rapid metabolizer” of certain medicines. Tell your healthcare provider if you are: noticing your pain getting worse.
If your pain gets worse after you take acetaminophen and codeine phosphate tablets, do not take more of acetaminophen and codeine phosphate tablets without first talking to your healthcare provider. Talk to your healthcare provider if the pain you have increases, if you feel more sensitive to pain, or if you have new pain after taking acetaminophen and codeine phosphate tablets. pregnant or planning to become pregnant. Use of acetaminophen and codeine phosphate tablets for an extended period of time during pregnancy can cause withdrawal symptoms in your newborn baby that could be life-threatening if not recognized and treated. breastfeeding.
Not recommended; may harm your baby. living in a household where there are small children or someone who has abused street or prescription drugs taking prescription or over-the-counter medicines, vitamins, or herbal supplements. Acetaminophen and codeine phosp…