
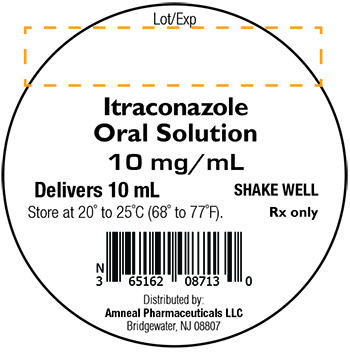
Itraconazole 10 mg/mL Solution, 150 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Azole Antifungal class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- These are genuinely different products, not just different forms of the same thing. The oral solution is absorbed differently — your body actually gets more drug from it at the sam...
- Why can't I just swap my Sporanox capsules for the oral solution if I run out?
- It matters a lot — and the answer is different depending on which form you have. If you're taking capsules (Sporanox, Tolsura, or generic itraconazole capsules), always take them w...
- Does it matter if I take itraconazole with food or not?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Itraconazole — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.125 | $168.80 / 150 ml |
| Medicaid paysCMS SDUD · 12 mo | $1.01 | $150.96 / 150 ml |
| Medicare drug plans payPart D · Q2 2026 | $1.21 | $181.89 / 150 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Itraconazole 10 mg/mL 31722-0006-31 | Camber | 1 bottle | $1.125 | AA | Availability likely | — |
| Itraconazole 10 mg/mLthis 65162-0087-74 | Amneal | 150 ml | $1.125 | AA | Availability likely | — |
| Itraconazole Oral 10 mg/mL 69339-0159-17 | Natco | 40 cups | — | AA | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65162-0087-34 | 10 CUP, UNIT-DOSE in 1 TRAY (65162-087-34) / 10 mL in 1 CUP, UNIT-DOSE (65162-087-13) | — | — | 2014-04-30 | Active |
| 65162-0087-74 You're viewing this | 150 mL in 1 BOTTLE, GLASS (65162-087-74) | $1.13 / mL | $168.80 | 2014-04-30 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 65162-0087-74?
What NDC number is used to bill for this package of Itraconazole 10 mg/mL Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING Congestive Heart Failure, Cardiac Effects and Drug Interactions Congestive Heart Failure and Cardiac Effects: If signs or symptoms of congestive heart failure occur during administration of itraconazole oral solution, continued itraconazole use should be reassessed . When itraconazole was administered intravenously to dogs and healthy human volunteers, negative inotropic effects were seen (see CONTRAINDICATIONS , WARNINGS , PRECAUTIONS: Drug Interactions , ADVERSE REACTIONS: Postmarketing Experience , and CLINICAL PHARMACOLOGY: Special Populations for more information).
Drug Interactions: Co-administration of a number of CYP3A4 substrates are contraindicated with itraconazole oral solution. Some examples of drugs that are contraindicated for co-administration with itraconazole oral solution are: methadone, disopyramide, dofetilide, dronedarone, quinidine, isavuconazole, ergot alkaloids (such as dihydroergotamine, ergometrine (ergonovine), ergotamine, methylergometrine (methylergonovine)), irinotecan, lurasidone, oral midazolam, pimozide, triazolam, felodipine, nisoldipine, ivabradine, ranolazine, eplerenone, cisapride, naloxegol, lomitapide, lovastatin, simvastatin, avanafil, ticagrelor, finerenone, voclosporin.
Co-administration with colchicine, fesoterodine and solifenacin is contraindicated in subjects with varying degrees of renal or hepatic impairment. Co-administration with eliglustat is contraindicated in subjects that are poor or intermediate metabolizers of CYP2D6 and in subjects taking strong or moderate CYP2D6 inhibitors. Co-administration with venetoclax is contraindicated in patients with chronic lymphocytic leukemia (CLL)/small lymphocytic lymphoma (SLL) during the dose initiation and ramp-up phase of venetoclax (see PRECAUTIONS: Drug Interactions Section for specific examples).
Co-administration with itraconazole can cause elevated plasma concentrations of these drugs and may increase or prolong both the pharmacologic effects and/or adverse reactions to these drugs. For example, increased plasma concentrations of some of these drugs can lead to QT prolongation and ventricular tachyarrhythmias including occurrences of torsade de pointes, a potentially fatal arrhythmia (see CONTRAINDICATIONS and WARNINGS Sections, and PRECAUTIONS: Drug Interactions Section for specific examples).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Itraconazole oral solution is indicated for the treatment of oropharyngeal and esophageal candidiasis. (see CLINICAL PHARMACOLOGY: Special Populations , WARNINGS , and ADVERSE REACTIONS: Postmarketing Experience for more information).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Treatment of Oropharyngeal and Esophageal Candidiasis: The solution should be vigorously swished in the mouth (10 mL at a time) for several seconds and swallowed. The recommended dosage of itraconazole oral solution for oropharyngeal candidiasis is 200 mg (20 mL) daily for 1 to 2 weeks. Clinical signs and symptoms of oropharyngeal candidiasis generally resolve within several days.
For patients with oropharyngeal candidiasis unresponsive/refractory to treatment with fluconazole tablets, the recommended dose is 100 mg (10 mL) b.i.d. For patients responding to therapy, clinical response will be seen in 2 to 4 weeks. Patients may be expected to relapse shortly after discontinuing therapy.
Limited data on the safety of long-term use (> 6 months) of itraconazole oral solution are available at this time. The recommended dosage of itraconazole oral solution for esophageal candidiasis is 100 mg (10 mL) daily for a minimum treatment of three weeks. Treatment should continue for 2 weeks following resolution of symptoms.
Doses up to 200 mg (20 mL) per day may be used based on medical judgment of the patient’s response to therapy. Itraconazole oral solution and itraconazole capsules should not be used interchangeably. Patients should be instructed to take itraconazole oral solution without food, if possible.
Only itraconazole oral solution has been demonstrated effective for oral and/or esophageal candidiasis. Use in Patients with Renal Impairment: Limited data are available on the use of oral itraconazole in patients with renal impairment. Caution should be exercised when this drug is administered in this patient population (see CLINICAL PHARMACOLOGY: Special Populations and PRECAUTIONS ).
Use in Patients with Hepatic Impairment: Limited data are available on the use of oral itraconazole in patients with hepatic impairment. Caution should be exercised when this drug is administered in this patient population (see CLINICAL PHARMACOLOGY: Special Populations , WARNINGS, and PRECAUTIONS ).
⛔ Contraindications ▾
CONTRAINDICATIONS Congestive Heart Failure: Itraconazole oral solution should not be administered to patients with evidence of ventricular dysfunction such as congestive heart failure (CHF) or a history of CHF except for the treatment of life-threatening or other serious infections (see BOXED WARNING , WARNINGS , PRECAUTIONS: Drug Interactions -Calcium Channel Blockers, ADVERSE REACTIONS: Postmarketing Experience , and CLINICAL PHARMACOLOGY: Special Populations ). Drug Interactions: Co-administration of a number of CYP3A4 substrates are contraindicated with itraconazole.
Some examples of drugs for which plasma concentrations increase are: methadone, disopyramide, dofetilide, dronedarone, quinidine, isavuconazole, ergot alkaloids (such as dihydroergotamine, ergometrine (ergonovine), ergotamine, methylergometrine (methylergonovine)), irinotecan, lurasidone, oral midazolam, pimozide, triazolam, felodipine, nisoldipine, ivabradine, ranolazine, eplerenone, cisapride, naloxegol, lomitapide, lovastatin, simvastatin, avanafil, ticagrelor, finerenone, voclosporin. In addition, co-administration with colchicine, fesoterodine, and solifenacin is contraindicated in subjects with varying degrees of renal or hepatic impairment, and co-administration with eliglustat is contraindicated in subjects that are poor or intermediate metabolizers of CYP2D6 and in subjects taking strong or moderate CYP2D6 inhibitors (see PRECAUTIONS: Drug Interactions Section for specific examples).
This increase in drug concentrations caused by co-administration with itraconazole may increase or prolong both the pharmacologic effects and/or adverse reactions to these drugs. For example, increased plasma concentrations of some of these drugs can lead to QT prolongation and ventricular tachyarrhythmias including occurrences of torsade de pointes, a potentially fatal arrhythmia. Some specific examples are listed in PRECAUTIONS: Drug Interactions .
Co-administration with venetoclax is contraindicated in patients with CLL/SLL during the dose initiation and ramp-up phase of venetoclax due to the potential for an increased risk of tumor lysis syndrome. Itraconazole oral solution is contraindicated for patients who have shown hypersensitivity to itraconazole. There is limited information regarding cross-hypersensitivity between itraconazole and other azole antifungal agents.
Caution should be used when prescribing itraconazole to patients with hypersensitivity to other azoles.
⚠️ Warnings ▾
WARNINGS Hepatic Effects: Itraconazole has been associated with rare cases of serious hepatotoxicity, including liver failure and death. Some of these cases had neither pre-existing liver disease nor a serious underlying medical condition, and some of these cases developed within the first week of treatment. If clinical signs or symptoms develop that are consistent with liver disease, treatment should be discontinued and liver function testing performed.
Continued itraconazole use or reinstitution of treatment with itraconazole is strongly discouraged unless there is a serious or life-threatening situation where the expected benefit exceeds the risk (see PRECAUTIONS : Information for Patients and ADVERSE REACTIONS ). Cardiac Dysrhythmias: Life-threatening cardiac dysrhythmias and/or sudden death have occurred in patients using drugs such as cisapride, pimozide, methadone, or quinidine concomitantly with itraconazole and/or other CYP3A4 inhibitors. Concomitant administration of these drugs with itraconazole is contraindicated (see BOXED WARNING , CONTRAINDICATIONS, and PRECAUTIONS: Drug Interactions ).
Cardiac Disease: Itraconazole oral solution should not be used in patients with evidence of ventricular dysfunction unless the benefit clearly outweighs the risk. For patients with risk factors for congestive heart failure, physicians should carefully review the risks and benefits of itraconazole therapy. These risk factors include cardiac disease such as ischemic and valvular disease; significant pulmonary disease such as chronic obstructive pulmonary disease; and renal failure and other edematous disorders.
Such patients should be informed of the signs and symptoms of CHF, should be treated with caution, and should be monitored for signs and symptoms of CHF during treatment. If signs or symptoms of CHF appear during administration of itraconazole oral solution, monitor carefully and consider other treatment alternatives which may include discontinuation of itraconazole oral solution administration. Itraconazole has been shown to have a negative inotropic effect.
When itraconazole was administered intravenously to anesthetized dogs, a dose-related negative inotropic effect was documented. In a healthy volunteer study of itraconazole intravenous infusion, transient, asymptomatic decreases in left ventricular ejection fraction were observed using gated SPECT imaging; these resolved before the next infusion, 12 hours later. Itraconazole has been associated with reports of congestive heart failure.
In postmarketing experience, heart failure was more frequently reported in patients receiving a total daily dose of 400 mg although there were also cases reported among those receiving lower total daily doses. Calcium channel blockers can have negative inotropic effects which may be additive to those of itraconazole. In addition, itraconazole can inhibit the metabolism of calcium channel blockers.
Therefore, caution should be used when co-administering itraconazole and calcium channel blockers due to an increased risk of CHF. Concomitant administration of itraconazole and felodipine or nisoldipine is contraindicated. Cases of CHF, peripheral edema, and pulmonary edema have been reported in the postmarketing period among patients being treated for onychomycosis and/or systemic fungal infections (see CONTRAINDICATIONS , CLINICAL PHARMACOLOGY: Special Populations , PRECAUTIONS: Drug Interactions , and ADVERSE REACTIONS: Postmarketing Experience for more information).
Pseudoaldosteronism: Pseudoaldosteronism, manifested by the onset of hypertension or worsening of hypertension, and abnormal laboratory findings (hypokalemia, low serum renin and aldosterone, and elevated 11-deoxycortisol), has been reported with itraconazole use in the postmarketing setting. Monitor blood pressure and potassium levels and manage as necessary. Management of pseudoaldosteronism may include discontinuation of itraconazole, substitution with an appropriate antifun…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Itraconazole has been associated with rare cases of serious hepatotoxicity, including liver failure and death. Some of these cases had neither pre-existing liver disease nor a serious underlying medical condition.
If clinical signs or symptoms develop that are consistent with liver disease, treatment should be discontinued and liver function testing performed. The risks and benefits of itraconazole use should be reassessed (see WARNINGS: Hepatic Effects and PRECAUTIONS: Hepatotoxicity and Information for Patients ). Adverse Events Reported in Oropharyngeal or Esophageal Candidiasis Trials U.S. adverse experience data are derived from 350 immunocompromised patients (332 HIV seropositive/AIDS) treated for oropharyngeal or esophageal candidiasis.
Table 3 below lists adverse events reported by at least 2% of patients treated with itraconazole oral solution in U.S. clinical trials. Data on patients receiving comparator agents in these trials are included for comparison. Table 3: Summary of Adverse Events Reported by ≥ 2% of Itraconazole Treated Patients in U.S.
Clinical Trials (Total) Body System/ Adverse Event Itraconazole Total (n = 350 * ) % All controlled studies (n = 272) % Fluconazole (n = 125 † ) % Clotrimazole (n = 81 ‡ ) % Gastrointestinal disorders Nausea 11 10 11 5 Diarrhea 11 10 10 4 Vomiting 7 6 8 1 Abdominal pain 6 4 7 7 Constipation 2 2 1 0 Body as a whole Fever 7 6 8 5 Chest pain 3 3 2 0 Pain 2 2 4 0 Fatigue 2 1 2 0 Respiratory disorders Coughing 4 4 10 0 Dyspnea 2 3 5 1 Pneumonia 2 2 0 0 Sinusitis 2 2 4 0 Sputum increased 2 3 3 1 Skin and appendages disorders Rash 4 5 4 6 Increased sweating 3 4 6 1 Skin disorder unspecified 2 2 2 1 Central/peripheral nervous system Headache 4 4 6 6 Dizziness 2 2 4 1 Resistance mechanism disorders Pneumocystis carinii infection 2 2 2 0 Psychiatric disorders Depression 2 1 0 1 * Of the 350 patients, 209 were treated for oropharyngeal candidiasis in controlled studies, 63 were treated for esophageal candidiasis in controlled studies and 78 were treated for oropharyngeal candidiasis in an open study. † Of the 125 patients, 62 were treated for oropharyngeal candidiasis and 63 were treated for esophageal candidiasis. ‡ All 81 patients were treated for oropharyngeal candidiasis.
Adverse events reported by less than 2% of patients in U.S. clinical trials with itraconazole included: adrenal insufficiency, asthenia, back pain, dehydration, dyspepsia, dysphagia, flatulence, gynecomastia, hematuria, hemorrhoids, hot flushes, implantation complication, infection unspecified, injury, insomnia, male breast pain, myalgia, pharyngitis, pruritus, rhinitis, rigors, stomatitis ulcerative, taste perversion, tinnitus, upper respiratory tract infection, vision abnormal, and weight decrease. Edema, hypokalemia and menstrual disorders have been reported in clinical trials with itraconazole capsules.
Adverse Events Reported from Other Clinical Trials A comparative clinical trial in patients who received intravenous itraconazole followed by itraconazole oral solution or received Amphotericin B reported the following adverse events in the itraconazole intravenous/ itraconazole oral solution treatment arm which are not listed above in the subsection “Adverse Events Reported in Oropharyngeal or Esophageal Candidiasis Trials” or listed below as postmarketing reports of adverse drug reactions: serum creatinine increased, blood urea nitrogen increased, renal function abnormal, hypocalcemia, hypomagnesemia, hypophosphatemia, hypotension, tachycardia and pulmonary infiltration.
In addition, the following adverse drug reactions were reported in patients who participated in itraconazole oral solution clinical trials: Cardiac Disorde…
🔄 Drug Interactions ▾
Drug Interactions: Co-administration of a number of CYP3A4 substrates are contraindicated with itraconazole. Some examples of drugs for which plasma concentrations increase are: methadone, disopyramide, dofetilide, dronedarone, quinidine, isavuconazole, ergot alkaloids (such as dihydroergotamine, ergometrine (ergonovine), ergotamine, methylergometrine (methylergonovine)), irinotecan, lurasidone, oral midazolam, pimozide, triazolam, felodipine, nisoldipine, ivabradine, ranolazine, eplerenone, cisapride, naloxegol, lomitapide, lovastatin, simvastatin, avanafil, ticagrelor, finerenone, voclosporin.
In addition, co-administration with colchicine, fesoterodine, and solifenacin is contraindicated in subjects with varying degrees of renal or hepatic impairment, and co-administration with eliglustat is contraindicated in subjects that are poor or intermediate metabolizers of CYP2D6 and in subjects taking strong or moderate CYP2D6 inhibitors (see PRECAUTIONS: Drug Interactions Section for specific examples). This increase in drug concentrations caused by co-administration with itraconazole may increase or prolong both the pharmacologic effects and/or adverse reactions to these drugs.
For example, increased plasma concentrations of some of these drugs can lead to QT prolongation and ventricular tachyarrhythmias including occurrences of torsade de pointes, a potentially fatal arrhythmia. Some specific examples are listed in PRECAUTIONS: Drug Interactions . Co-administration with venetoclax is contraindicated in patients with CLL/SLL during the dose initiation and ramp-up phase of venetoclax due to the potential for an increased risk of tumor lysis syndrome.
Itraconazole oral solution is contraindicated for patients who have shown hypersensitivity to itraconazole. There is limited information regarding cross-hypersensitivity between itraconazole and other azole antifungal agents. Caution should be used when prescribing itraconazole to patients with hypersensitivity to other azoles.
Drug Interactions: Effect of Itraconazole on Other Drugs Itraconazole and its major metabolite, hydroxy-itraconazole, are potent CYP3A4 inhibitors. Itraconazole is an inhibitor of the drug transporters P-glycoprotein and breast cancer resistance protein (BCRP). Consequently, itraconazole has the potential to interact with many concomitant drugs resulting in either increased or sometimes decreased concentrations of the concomitant drugs.
Increased concentrations may increase the risk of adverse reactions associated with the concomitant drug which can be severe or life-threatening in some cases (e.g., QT prolongation, torsade de pointes, respiratory depression, hepatic adverse reactions, hypersensitivity reactions, myelosuppression, hypotension, seizures, angioedema, atrial fibrillation, bradycardia, priapism). Reduced concentrations of concomitant drugs may reduce their efficacy. The table below lists examples of drugs that may have their concentrations affected by itraconazole, but it is not a comprehensive list.
Refer to the approved product labeling to become familiar with the interaction pathways, risk potential and specific actions to be taken with regards to each concomitant drug prior to initiating therapy with itraconazole. Although many of the clinical drug interactions in Table 1 below are based on information with a similar azole antifungal, ketoconazole, these interactions are expected to occur with itraconazole. Table 1: Drug Interactions with Itraconazole that Affect Concomitant Drug Concentrations Examples of Concomitant Drugs Within Class Prevention or Management Drug Interactions with Itraconazole that Increase Concomitant Drug Concentrations and May Increase Risk of Adverse Reactions Associated with the Concomitant Drug Alpha Blockers Alfuzosin Silodosin Tamsulosin Not recommended during and 2 weeks after itraconazole treatment.
Analgesics Methadone Contraindicated during and 2 weeks after itraconazole treatment. Fentanyl Not recommended durin…
🧒 Pediatric Use ▾
Pregnancy: Teratogenic Effects: Itraconazole was found to cause a dose-related increase in maternal toxicity, embryotoxicity, and teratogenicity in rats at dosage levels of approximately 40 to 160 mg/kg/day (1 to 4 times the MRHD based on body surface area comparisons), and in mice at dosage levels of approximately 80 mg/kg/day (1 time the MRHD based on body surface area comparisons). Itraconazole has been shown to cross the placenta in a rat model. In rats, the teratogenicity consisted of major skeletal defects; in mice, it consisted of encephaloceles and/or macroglossia.
Itraconazole oral solution contains the excipient hydroxypropyl-β-cyclodextrin (HP-β-CD). HP-β-CD has no direct embryotoxic and no teratogenic effect. There are no studies in pregnant women.
Itraconazole should be used in pregnancy only if the benefit outweighs the potential risk. Highly effective contraception should be continued throughout Itraconazole therapy and for 2 months following the end of treatment. During postmarketing experience, cases of congenital abnormalities have been reported (see ADVERSE REACTIONS: Postmarketing Experience ).
🧓 Geriatric Use ▾
Nursing Mothers: Itraconazole is excreted in human milk; therefore, the expected benefits of itraconazole therapy for the mother should be weighed against the potential risk from exposure of itraconazole to the infant. The U.S. Public Health Service Centers for Disease Control and Prevention advises HIV-infected women not to breast-feed to avoid potential transmission of HIV to uninfected infants.
🆘 Overdosage ▾
OVERDOSAGE Itraconazole is not removed by dialysis. In the event of accidental overdosage, supportive measures should be employed. Contact a certified poison control center for the most up to date information on the management of Itraconazole Oral Solution overdosage (1-800-222-1222 or www.poison.org ).
In general, adverse events reported with overdose have been consistent with adverse drug reactions already listed in this package insert for itraconazole (see ADVERSE REACTIONS ).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacokinetics and Metabolism: Itraconazole General Pharmacokinetic Characteristics Peak plasma concentrations are reached within 2.5 hours following administration of the oral solution. As a consequence of non-linear pharmacokinetics, itraconazole accumulates in plasma during multiple dosing. Steady-state concentrations are generally reached within about 15 days, with C max and AUC values 4 to 7-fold higher than those seen after a single dose.
Steady-state C max values of about 2 mcg/mL are reached after oral administration of 200 mg once daily. The terminal half-life of itraconazole generally ranges from 16 to 28 hours after single dose and increases to 34 to 42 hours with repeated dosing. Once treatment is stopped, itraconazole plasma concentrations decrease to an almost undetectable concentration within 7 to 14 days, depending on the dose and duration of treatment.
Itraconazole mean total plasma clearance following intravenous administration is 278 mL/min. Itraconazole clearance decreases at higher doses due to saturable hepatic metabolism. Absorption Itraconazole is rapidly absorbed after administration of the oral solution.
Peak plasma concentrations of itraconazole are reached within 2.5 hours following administration of the oral solution under fasting conditions. The observed absolute bioavailability of itraconazole under fed conditions is about 55% and increases by 30% when the oral solution is taken in fasting conditions. Itraconazole exposure is greater with the oral solution than with the capsule formulation when the same dose of drug is given (see WARNINGS ).
Distribution Most of the itraconazole in plasma is bound to protein (99.8%), with albumin being the main binding component (99.6% for the hydroxy-metabolite). It has also a marked affinity for lipids. Only 0.2% of the itraconazole in plasma is present as free drug.
Itraconazole is distributed in a large apparent volume in the body (> 700 L), suggesting extensive distribution into tissues. Concentrations in lung, kidney, liver, bone, stomach, spleen and muscle were found to be two to three times higher than corresponding concentrations in plasma, and the uptake into keratinous tissues, skin in particular, up to four times higher. Concentrations in the cerebrospinal fluid are much lower than in plasma.
Metabolism Itraconazole is extensively metabolized by the liver into a large number of metabolites. In vitro studies have shown that CYP3A4 is the major enzyme involved in the metabolism of itraconazole. The main metabolite is hydroxy-itraconazole, which has in vitro antifungal activity comparable to itraconazole; trough plasma concentrations of this metabolite are about twice those of itraconazole.
Excretion Itraconazole is excreted mainly as inactive metabolites in urine (35%) and in feces (54%) within one week of an oral solution dose. Renal excretion of itraconazole and the active metabolite hydroxy-itraconazole account for less than 1% of an intravenous dose. Based on an oral radiolabeled dose, fecal excretion of unchanged drug ranges from 3% to 18% of the dose.
Special Populations: Renal Impairment : Limited data are available on the use of oral itraconazole in patients with renal impairment. A pharmacokinetic study using a single 200 mg oral dose of itraconazole was conducted in three groups of patients with renal impairment (uremia: n=7; hemodialysis: n=7; and continuous ambulatory peritoneal dialysis: n=5). In uremic subjects with a mean creatinine clearance of 13 mL/min. × 1.73 m 2 , the exposure, based on AUC, was slightly reduced compared with normal population parameters.
This study did not demonstrate any significant effect of hemodialysis or continuous ambulatory peritoneal dialysis on the pharmacokinetics of itraconazole (T max , C max , and AUC 0-8h ). Plasma concentration-versus-time profiles showed wide intersubject variation in all three groups. After a single intravenous dose, the mean terminal half-lives of itraconazo…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Itraconazole Oral Solution, 10 mg/mL, is available in 150 mL amber glass bottles (NDC 65162-087-74) containing 10 mg of itraconazole, USP per mL. It is also available as: 10 mL unit dose cup NDC 65162-087-13 10 unit dose cups in a tray NDC 65162-087-34 Store at or below 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Do not freeze. Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 08-2026-11
📋 Description ▾
DESCRIPTION Itraconazole, USP is an azole antifungal agent. Itraconazole, USP is a 1:1:1:1 racemic mixture of four diastereomers (two enantiomeric pairs), each possessing three chiral centers. It may be represented by the following structural formula and nomenclature: (±)-1-[(R*)-sec-butyl]-4-[p-[4-[p-[[(2R*,4S*)-2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1-ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1-piperazinyl]phenyl]-Δ 2 -1,2,4-triazolin-5-one mixture with (±)-1-[(R*)-sec-butyl]-4-[p-[4-[p-[[(2S*,4R*)-2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1-ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1-piperazinyl]phenyl]-Δ 2 -1,2,4-triazolin-5-one or (±)-1-[(RS)-sec-butyl]-4-[p-[4-[p-[[(2R,4S)-2-(2,4-dichlorophenyl)-2-(1H-1,2,4-triazol-1-ylmethyl)-1,3-dioxolan-4-yl]methoxy]phenyl]-1-piperazinyl]phenyl]-Δ 2 -1,2,4-triazolin-5-one.
Itraconazole, USP has a molecular formula of C 35 H 38 Cl 2 N 8 O 4 and a molecular weight of 705.64. It is a white to slightly yellowish powder. It is insoluble in water, very slightly soluble in alcohols, and freely soluble in dichloromethane.
It has a pKa of 3.70 (based on extrapolation of values obtained from methanolic solutions) and a log (n-octanol/water) partition coefficient of 5.66 at pH 8.1. Itraconazole oral solution contains 10 mg of itraconazole, USP per mL, solubilized by hydroxypropyl-β-cyclodextrin (400 mg/mL) as a molecular inclusion complex. Itraconazole oral solution is clear and yellowish in color with a target pH of 2.
Other ingredients are caramel flavor, cherry flavor, hydrochloric acid, propylene glycol, purified water, sodium hydroxide, sodium saccharin, and sorbitol. Hydrochloric acid solution or sodium hydroxide solution may be added for adjustment of pH. 4
💬 Information for Patients ▾
Information for Patients: Only itraconazole oral solution has been demonstrated effective for oral and/or esophageal candidiasis. Itraconazole oral solution contains the excipient hydroxypropyl-β-cyclodextrin which produced adenocarcinomas in the large intestine and exocrine pancreatic adenocarcinomas in a rat carcinogenicity study. These findings were not observed in a similar mouse carcinogenicity study.
The clinical relevance of these adenocarcinomas is unknown (see PRECAUTIONS: Carcinogenesis, Mutagenesis, and Impairment of Fertility ). Taking itraconazole oral solution under fasted conditions improves the systemic availability of itraconazole. Instruct patients to take itraconazole oral solution without food, if possible.
Itraconazole oral solution should not be used interchangeably with itraconazole capsules. Instruct patients about the signs and symptoms of congestive heart failure, and if these signs or symptoms occur during itraconazole administration, they should discontinue itraconazole and contact their healthcare provider immediately. Instruct patients to stop itraconazole treatment immediately and contact their healthcare provider if any signs and symptoms suggestive of liver dysfunction develop.
Such signs and symptoms may include unusual fatigue, anorexia, nausea and/or vomiting, jaundice, dark urine, or pale stools. Instruct patients to contact their physician before taking any concomitant medications with itraconazole to ensure there are no potential drug interactions. Instruct patients that hearing loss can occur with the use of itraconazole.
The hearing loss usually resolves when treatment is stopped, but can persist in some patients. Advise patients to discontinue therapy and inform their physicians if any hearing loss symptoms occur. Instruct patients that dizziness or blurred/double vision can sometimes occur with itraconazole.
Advise patients that if they experience these events, they should not drive or use machines.