
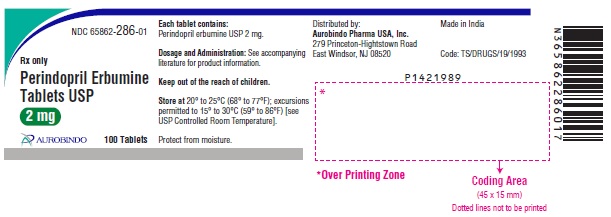
Perindopril Erbumine 2 mg Tablet, 12,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Perindopril is used alone or in combination with other medications to treat high blood pressure. Perindopril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It makes blood flow more smoothly by preventing the production of certain natural chemicals that tighten the blood vessels. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood vessels, kidneys, and other parts of the body. Damage to these organs may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss of vision, and other...
Read the full MedlinePlus article ↗- Perindopril is mainly used for two things: lowering high blood pressure and — if you have stable coronary artery disease — reducing your chances of a heart attack or dying from a h...
- Yes, a dry, persistent cough is the most common side effect with perindopril — it happened in about 12% of patients in clinical trials, compared to about 4.5% with placebo. It's no...
- I've heard ACE inhibitors cause a cough. Is that really common?
- No — this is one of the most important warnings with perindopril. This drug can cause serious kidney damage and even death in an unborn baby, particularly in the second and third t...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Perindopril Erbumine — tap one for details:
Perindopril Erbumine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Perindopril Erbumine 2 mgthis 65862-0286-53 | Aurobindo | 12000 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0286-01 | 100 TABLET in 1 BOTTLE (65862-286-01) | $0.4188 / ea | $41.88 | 2009-11-10 | Active |
| 65862-0286-53 You're viewing this | 12000 TABLET in 1 BAG (65862-286-53) | — | — | — | Active |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 65862-0286-53?
What is the difference between NDC 65862-0286-53 and NDC 65862-0286-01?
What NDC number is used to bill for this package of Perindopril Erbumine 2 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue perindopril erbumine as soon as possible [see Warnings and Precautions (5.4) ]. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions (5.4) ] . WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue perindopril erbumine as soon as possible [see Warnings and Precautions (5.4) ] . Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [ see Warnings and Precautions (5.4) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Perindopril erbumine tablets are indicated for the treatment of patients with essential hypertension. (1.1) Perindopril erbumine tablets are indicated for treatment of patients with stable coronary artery disease to reduce the risk of cardiovascular mortality or nonfatal myocardial infarction. (1.2)
1.1Hypertension Perindopril erbumine tablets are indicated for the treatment of patients with essential hypertension. Perindopril erbumine tablets may be used alone or given with other classes of antihypertensives, especially thiazide diuretics.
1.2Stable Coronary Artery Disease Perindopril erbumine tablets are indicated for treatment of patients with stable coronary artery disease to reduce the risk of cardiovascular mortality or nonfatal myocardial infarction. Perindopril erbumine tablets can be used with conventional treatment for management of coronary artery disease, such as antiplatelet, antihypertensive or lipid-lowering therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension The recommended initial dose is 4 mg once a day. The dosage may be titrated upward until blood pressure, when measured just before the next dose, is controlled or to a maximum of 16 mg per day. (2.1) Stable Coronary Artery Disease Perindopril erbumine tablets should be given at an initial dose of 4 mg once daily for 2 weeks, and then increased, as tolerated, to a maintenance dose of 8 mg once daily. (2.2)
2.1Hypertension Use in Uncomplicated Hypertensive Patients: In patients with essential hypertension, the recommended initial dose is 4 mg once a day. The dose may be titrated, as needed to a maximum of 16 mg per day. The usual maintenance dose range is 4 mg to 8 mg administered as a single daily dose or in two divided doses.
Use in Elderly Patients: The recommended initial daily dosage of perindopril erbumine tablets for the elderly is 4 mg daily, given in one or two divided doses. Experience with perindopril erbumine tablets is limited in the elderly at doses exceeding 8 mg. Dosages above 8 mg should be administered with careful blood pressure monitoring and dose titration [see Use in Specific Populations (8.5) ] .
Use with Diuretics: In patients who are currently being treated with a diuretic, symptomatic hypotension can occur following the initial dose of perindopril erbumine tablets. Consider reducing the dose of diuretic prior to starting perindopril erbumine tablets [see Drug Interactions (7.1) ] .
2.2Stable Coronary Artery Disease In patients with stable coronary artery disease, perindopril erbumine tablets should be given at an initial dose of 4 mg once daily for 2 weeks, and then increased as tolerated, to a maintenance dose of 8 mg once daily. In elderly patients (greater than 70 years), perindopril erbumine tablets should be given as a 2 mg dose once daily in the first week, followed by 4 mg once daily in the second week and 8 mg once daily for maintenance dose if tolerated.
2.3Dose Adjustment in Renal Impairment and Dialysis Perindoprilat elimination is decreased in renally impaired patients. Perindopril erbumine tablets are not recommended in patients with creatinine clearance <30 mL/min. For patients with lesser degrees of impairment, the initial dosage should be 2 mg/day and dosage should not exceed 8 mg/day. During dialysis, perindopril is removed with the same clearance as in patients with normal renal function.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 2 mg tablet is white to off-white colored round biconvex, uncoated tablets, with debossing “D” on one side and “5” & “7” on either side of the breakline on another side. 4 mg tablet is white to off-white colored capsule shaped uncoated tablets, with debossing “D” on one side and “5” & “8” on either side of the breakline on another side. 8 mg tablet is white to off-white colored round biconvex uncoated tablets, with debossing “D” on one side and “5” & “9” on either side of breakline on another side.
Tablets: 2 mg, 4 mg and 8 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Perindopril erbumine tablets are contraindicated in patients known to be hypersensitive (including angioedema) to this product or to any other ACE inhibitor. Perindopril erbumine tablets are also contraindicated in patients with hereditary or idiopathic angioedema. Do not co-administer aliskiren with perindopril erbumine tablets in patients with diabetes. [see Drug Interactions (7.8) ] Perindopril erbumine tablets are contraindicated in combination with neprilysin inhibitor (e.g., sacubitril).
Do not administer perindopril erbumine tablets within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor [see Warnings and Precautions (5.1) ]. Angioedema related to previous treatment with an ACE inhibitor, or a history of hereditary or idiopathic angioedema. ( 4 , 5.1 ) Do not co-administer aliskiren with perindopril erbumine tablets in patients with diabetes ( 4 , 7.8 ) Do not take a neprilysin inhibitor with perindopril erbumine tablets ( 4 ).
Do not administer perindopril erbumine tablets within 36 hours of switching to or from sacubitril/valsartan ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Watch for anaphylactoid reactions, including angioedema. (5.1) Monitor renal function during therapy. (5.5) Assess for hypotension and hyperkalemia. (5.2 , 5.6)
5.1Anaphylactoid and Possibly Related Reactions Presumably because angiotensin-converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors (including perindopril erbumine) may be subject to a variety of adverse events, some of them serious. Black patients receiving ACE inhibitors have a higher incidence of angioedema compared to nonblacks. Head and Neck Angioedema: Angioedema of the face, extremities, lips, tongue, glottis, or larynx has been reported in patients treated with ACE inhibitors, including perindopril erbumine (0.1% of patients treated with perindopril erbumine in U.S. clinical trials).
Angioedema associated with involvement of the tongue, glottis or larynx may be fatal. In such cases, discontinue perindopril erbumine treatment immediately and observe until the swelling disappears. When involvement of the tongue, glottis, or larynx appears likely to cause airway obstruction, administer appropriate therapy, such as subcutaneous epinephrine solution 1:1000 (0.3 to 0.5 mL), promptly.
Patients taking concomitant mTOR inhibitor (e.g., temsirolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema [see Drug Interactions (7.9 ; 7.10) ]. Intestinal Angioedema: Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal.
The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor. Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain.
5.2Hypotension Perindopril erbumine can cause symptomatic hypotension. Perindopril erbumine has been associated with hypotension in 0.3% of uncomplicated hypertensive patients in U.S. placebo-controlled trials. Symptoms related to orthostatic hypotension were reported in another 0.8% of patients.
Symptomatic hypotension is most likely to occur in patients who have been volume or salt-depleted as a result of prolonged diuretic therapy, dietary salt restriction, dialysis, diarrhea or vomiting [see Dosage and Administration (2.1) ] . ACE inhibitors may cause excessive hypotension, and may be associated with oliguria or azotemia, and rarely with acute renal failure and death. In patients with ischemic heart disease or cerebrovascular disease, an excessive fall in blood pressure could result in a myocardial infarction or a cerebrovascular accident.
In patients at risk of excessive hypotension, perindopril erbumine therapy should be started under very close medical supervision. Patients should be followed closely for the first two weeks of treatment and whenever the dose of perindopril erbumine and/or diuretic is increased. If excessive hypotension occurs, the patient should be placed immediately in a supine position and, if necessary, treated with an intravenous infusion of physiological saline.
Perindopril erbumine treatment can usually be continued following restoration of volume and blood pressure.
5.3Neutropenia/Agranulocytosis ACE inhibitors have been associated with agranulocytosis and bone marrow depression, most frequently in patients with renal impairment, especially patients with a collagen vascular disease such as systemic lupus erythematosus or scleroderma.
5.4Fetal Toxicity Pregnancy Category D Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be as…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse event rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Hypertension: Most common adverse events (incidence greater than or equal to 5%) are cough, dizziness and back pain. (6.1) Stable Coronary Artery Disease: Most common adverse events leading to discontinuation were cough, drug intolerance, and hypotension.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience The following adverse reactions are discussed elsewhere in labeling: Anaphylactoid reactions, including angioedema [see Warnings and Precautions (5.1) ] Hypotension [see Warnings and Precautions (5.2) ] Neutropenia and agranulocytosis [see Warnings and Precautions (5.3) ] Impaired renal function [see Warnings and Precautions (5.5) ] Hyperkalemia [see Warnings and Precautions (5.6) ] Cough [see Warnings and Precautions (5.7) ] Hypertension Perindopril erbumine has been evaluated for safety in approximately 3,400 patients with hypertension in U.S. and foreign clinical trials.
The data presented here are based on results from the 1,417 perindopril erbumine-treated patients who participated in the U.S. clinical trials. Over 220 of these patients were treated with perindopril erbumine for at least one year. In placebo-controlled U.S. clinical trials, the incidence of premature discontinuation of therapy due to adverse events was 6.5% in patients treated with perindopril erbumine and 6.7% in patients treated with placebo.
The most common causes were cough, headache, asthenia and dizziness. Among 1,012 patients in placebo-controlled U.S. trials, the overall frequency of reported adverse events was similar in patients treated with perindopril erbumine and in those treated with placebo (approximately 75% in each group). The only adverse events whose incidence on perindopril erbumine was at least 2% greater than on placebo were cough (12% vs.
4.5%) and back pain (5.8% vs. 3.1%). Dizziness was not reported more frequently in the perindopril group (8.2%) than in the placebo group (8.5%), but its likelihood increased with dose, suggesting a causal relationship with perindopril.
Stable Coronary Artery Disease Perindopril has been evaluated for safety in EUROPA, a double-blind, placebo-controlled study in 12,218 patients with stable coronary artery disease. The overall rate of discontinuation was about 22% on drug and placebo. The most common medical reasons for discontinuation that were more frequent on perindopril than placebo were cough, drug intolerance and hypotension.
6.2Postmarketing Experience Voluntary reports of adverse events in patients taking perindopril erbumine that have been received since market introduction and are of unknown causal relationship to perindopril erbumine include: cardiac arrest, eosinophilic pneumonitis, neutropenia/agranulocytosis, pancytopenia, anemia (including hemolytic and aplastic), thrombocytopenia, acute renal failure, nephritis, hepatic failure, jaundice (hepatocellular or cholestatic), symptomatic hyponatremia, bullous pemphigoid, pemphigus, acute pancreatitis, falls, psoriasis, exfoliative dermatitis and a syndrome which may include: arthralgia/arthritis, vasculitis, serositis, myalgia, fever, rash or other dermatologic manifestations, a positive antinuclear antibody (ANA), leukocytosis, eosinophilia or an elevated erythrocyte sedimentation rate (ESR).
6.3Clinical Laboratory Test Findings Hematology: Small decreases in hemoglobin and hematocrit occur frequently in hypertensive patients treated with perindopril erbumine, but are rarely of clinical importance. In controlled clinical trials, no patient was discontinued from therapy due to the development of anemia. Leukopenia (including neutropeni…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Diuretics: Excessive drop in blood pressure. (7.1) Potassium-Sparing Diuretics/Potassium Supplements: Hyperkalemia. (7.2) Lithium: Increase serum lithium levels, symptoms of lithium toxicity.
(7.3) Injectable Gold: Nitritoid reactions (facial flushing, nausea, vomiting, and hypotension). (7.4) NSAID use may lead to increased risk of renal impairment and loss of antihypertensive effect. (7.7) Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia.
( 7.8 ) Neprilysin Inhibitor: risk of angioedema ( 7 ).
7.1Diuretics Patients on diuretics, and especially those started recently, may occasionally experience an excessive reduction of blood pressure after initiation of perindopril erbumine therapy. The possibility of hypotensive effects can be minimized by either decreasing the dose of or discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with perindopril. If diuretic therapy cannot be altered, provide close medical supervision with the first dose of perindopril erbumine, for at least two hours and until blood pressure has stabilized for another hour [see Warnings and Precautions (5.2) ] .
The rate and extent of perindopril absorption and elimination are not affected by concomitant diuretics. The bioavailability of perindoprilat was reduced by diuretics, however, and this was associated with a decrease in plasma ACE inhibition.
7.2Potassium Supplements and Potassium-Sparing Diuretics Perindopril erbumine may increase serum potassium because of its potential to decrease aldosterone production. Use of potassium-sparing diuretics (spironolactone, amiloride, triamterene and others), potassium supplements or other drugs capable of increasing serum potassium (indomethacin, heparin, cyclosporine and others) can increase the risk of hyperkalemia. Therefore, if concomitant use of such agents is indicated, monitor the patient’s serum potassium frequently.
7.3Lithium Increased serum lithium and symptoms of lithium toxicity have been reported in patients receiving concomitant lithium and ACE inhibitor therapy. Frequent monitoring of serum lithium concentration is recommended. Use of a diuretic may further increase the risk of lithium toxicity.
7.4Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE Inhibitor therapy including perindopril erbumine.
7.5Digoxin A controlled pharmacokinetic study has shown no effect on plasma digoxin concentrations when coadministered with perindopril erbumine, but an effect of digoxin on the plasma concentration of perindopril/perindoprilat has not been excluded.
7.6Gentamicin Animal data have suggested the possibility of interaction between perindopril and gentamicin. However, this has not been investigated in human studies.
7.7Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including perindopril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving perindopril and NSAID therapy.
The antihypertensive effect of ACE inhibitors, including perindopril, may be attenuated by NSAIDs including selective COX-2 inhibitors.
7.8Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of tw…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatrics: Start at low daily dose (4 mg or less) and titrate slowly as needed. Experience with doses exceeding 8 mg is limited. (8.5) Dosage adjustment may be necessary in renally impaired patients. (8.6)
8.1Pregnancy Pregnancy Category D [see Boxed Warning and Warnings and Precautions (5.4) ] . Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue perindopril erbumine as soon as possible. These adverse outcomes are usually associated with use of these drugs in the second and third trimester of pregnancy.
Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents. Appropriate management of maternal hypertension during pregnancy is important to optimize outcomes for both mother and fetus. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue perindopril erbumine, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of pregnancy.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to perindopril erbumine for hypotension, oliguria, and hyperkalemia [see Use in Specific Populations (8.4) ] . Radioactivity was detectable in fetuses after administration of 14 C-perindopril to pregnant rats.
8.3Nursing Mothers Milk of lactating rats contained radioactivity following administration of 14 C-perindopril. It is not known whether perindopril is secreted in human milk. Because many drugs are secreted in human milk, caution should be exercised when perindopril erbumine is given to nursing mothers.
8.4Pediatric Use Neonates With a History of in utero Exposure to Perindopril Erbumine: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Perindopril, which crosses the placenta, can theoretically be removed from the neonatal circulation by these means, but limited experience has not shown that such removal is central to the treatment of these infants.
Safety and effectiveness of perindopril erbumine in pediatric patients have not been established.
8.5Geriatric Use The mean blood pressure effect of perindopril was somewhat smaller in patients over 60 than in younger patients, although the difference was not significant. Plasma concentrations of both perindopril and perindoprilat were increased in elderly patients compared to concentrations in younger patients. No adverse effects were clearly increased in older patients with the exception of dizziness and possibly rash.
Start at a low dose and titrate slowly as needed. Monitor for dizziness because of potential for falls. Experience with perindopril erbumine in elderly patients at daily doses exceeding 8 mg is limited.
8.6Renal Impairment Dosage adjustment may be necessary in renally impaired patients [see Dosage and Administration (2.3) and Clinical Pharmacology (12.3) ] .
8.7Hepatic Impairment The bioavailability of perindoprilat is increased in patients with impaired hep…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category D [see Boxed Warning and Warnings and Precautions (5.4) ] . Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue perindopril erbumine as soon as possible. These adverse outcomes are usually associated with use of these drugs in the second and third trimester of pregnancy.
Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents. Appropriate management of maternal hypertension during pregnancy is important to optimize outcomes for both mother and fetus. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue perindopril erbumine, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of pregnancy.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to perindopril erbumine for hypotension, oliguria, and hyperkalemia [see Use in Specific Populations (8.4) ] . Radioactivity was detectable in fetuses after administration of 14 C-perindopril to pregnant rats.
🧒 Pediatric Use ▾
8.4Pediatric Use Neonates With a History of in utero Exposure to Perindopril Erbumine: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Perindopril, which crosses the placenta, can theoretically be removed from the neonatal circulation by these means, but limited experience has not shown that such removal is central to the treatment of these infants.
Safety and effectiveness of perindopril erbumine in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The mean blood pressure effect of perindopril was somewhat smaller in patients over 60 than in younger patients, although the difference was not significant. Plasma concentrations of both perindopril and perindoprilat were increased in elderly patients compared to concentrations in younger patients. No adverse effects were clearly increased in older patients with the exception of dizziness and possibly rash.
Start at a low dose and titrate slowly as needed. Monitor for dizziness because of potential for falls. Experience with perindopril erbumine in elderly patients at daily doses exceeding 8 mg is limited.
🆘 Overdosage ▾
10 OVERDOSAGE In animals, doses of perindopril up to 2,500 mg/kg in mice, 3,000 mg/kg in rats and 1,600 mg/kg in dogs were non-lethal. Past experiences were scant but suggested that overdosage with other ACE inhibitors was also fairly well tolerated by humans. The most likely manifestation is hypotension, and treatment should be symptomatic and supportive.
Therapy with the ACE inhibitor should be discontinued, and the patient should be observed. Dehydration, electrolyte imbalance and hypotension should be treated by established procedures. Among the reported cases of perindopril overdosage, patients who were known to have ingested a dose of 80 mg to 120 mg required assisted ventilation and circulatory support.
One additional patient developed hypothermia, circulatory arrest and died following ingestion of up to 180 mg of perindopril. The intervention for perindopril overdose may require vigorous support. Laboratory determinations of serum levels of perindopril and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of perindopril overdose.
No data are available to suggest physiological maneuvers ( e.g., maneuvers to change the pH of the urine) that might accelerate elimination of perindopril and its metabolites. Perindopril can be removed by hemodialysis, with clearance of 52 mL/min for perindopril and 67 mL/min for perindoprilat. Angiotensin II could presumably serve as a specific antagonist-antidote in the settling of perindopril overdose, but angiotensin II is essentially unavailable outside of scattered research facilities.
Because the hypotensive effect of perindopril is achieved through vasodilation and effective hypovolemia, it is reasonable to treat perindopril overdose by infusion of normal saline solution.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Perindopril erbumine is a pro-drug for perindoprilat, which inhibits ACE in human subjects and animals. The mechanism through which perindoprilat lowers blood pressure is believed to be primarily inhibition of ACE activity. ACE is a peptidyl dipeptidase that catalyzes conversion of the inactive decapeptide, angiotensin I, to the vasoconstrictor, angiotensin II.
Angiotensin II is a potent peripheral vasoconstrictor, which stimulates aldosterone secretion by the adrenal cortex, and provides negative feedback on renin secretion. Inhibition of ACE results in decreased plasma angiotensin II, leading to decreased vasoconstriction, increased plasma renin activity and decreased aldosterone secretion. The latter results in diuresis and natriuresis and may be associated with a small increase of serum potassium.
ACE is identical to kininase II, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of perindopril erbumine remains to be elucidated. While the principal mechanism of perindopril in blood pressure reduction is believed to be through the renin-angiotensin-aldosterone system, ACE inhibitors have some effect even in apparent low-renin hypertension.
Perindopril has been studied in relatively few black patients, usually a low-renin population, and the average response of diastolic blood pressure to perindopril was about half the response seen in nonblack patients, a finding consistent with previous experience of other ACE inhibitors.
12.2Pharmacodynamics After administration of perindopril, ACE is inhibited in a dose and blood concentration-related fashion, with the maximal inhibition of 80 to 90% attained by 8 mg persisting for 10 to 12 hours. Twenty-four hour ACE inhibition is about 60% after these doses. The degree of ACE inhibition achieved by a given dose appears to diminish over time (the ID 50 increases).
The pressor response to an angiotensin I infusion is reduced by perindopril, but this effect is not as persistent as the effect on ACE; there is about 35% inhibition at 24 hours after a 12 mg dose.
12.3Pharmacokinetics Absorption: Oral administration of perindopril erbumine results in peak plasma concentrations that occur at approximately 1 hour. The absolute oral bioavailability of perindopril is about 75%. Following absorption, approximately 30 to 50% of systemically available perindopril is hydrolyzed to its active metabolite, perindoprilat, which has a mean bioavailability of about 25%.
Peak plasma concentrations of perindoprilat are attained 3 to 7 hours after perindopril administration. Oral administration of perindopril erbumine with food does not significantly lower the rate or extent of perindopril absorption relative to the fasted state. However, the extent of biotransformation of perindopril to the active metabolite, perindoprilat, is reduced approximately 43%, resulting in a reduction in the plasma ACE inhibition curve of approximately 20%, probably clinically insignificant.
In clinical trials, perindopril was generally administered in a non-fasting state. With 4 mg, 8 mg and 16 mg doses of perindopril erbumine, C max and AUC of perindopril and perindoprilat increase in a dose-proportional manner following both single oral dosing and at steady state during a once-a-day multiple dosing regimen. Distribution: Approximately 60% of circulating perindopril is bound to plasma proteins, and only 10 to 20% of perindoprilat is bound.
Therefore, drug interactions mediated through effects on protein binding are not anticipated. Metabolism and Elimination: Following oral administration perindopril exhibits multicompartment pharmacokinetics including a deep tissue compartment (ACE binding sites). The mean half-life of perindopril associated with most of its elimination is approximately 0.8 to 1 hours.
Perindopril is extensively metabolized following oral administration, with only 4…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Perindopril erbumine is a pro-drug for perindoprilat, which inhibits ACE in human subjects and animals. The mechanism through which perindoprilat lowers blood pressure is believed to be primarily inhibition of ACE activity. ACE is a peptidyl dipeptidase that catalyzes conversion of the inactive decapeptide, angiotensin I, to the vasoconstrictor, angiotensin II.
Angiotensin II is a potent peripheral vasoconstrictor, which stimulates aldosterone secretion by the adrenal cortex, and provides negative feedback on renin secretion. Inhibition of ACE results in decreased plasma angiotensin II, leading to decreased vasoconstriction, increased plasma renin activity and decreased aldosterone secretion. The latter results in diuresis and natriuresis and may be associated with a small increase of serum potassium.
ACE is identical to kininase II, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of perindopril erbumine remains to be elucidated. While the principal mechanism of perindopril in blood pressure reduction is believed to be through the renin-angiotensin-aldosterone system, ACE inhibitors have some effect even in apparent low-renin hypertension.
Perindopril has been studied in relatively few black patients, usually a low-renin population, and the average response of diastolic blood pressure to perindopril was about half the response seen in nonblack patients, a finding consistent with previous experience of other ACE inhibitors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Perindopril Erbumine T ablets USP, 2 mg are white to off-white colored round biconvex, uncoated tablets, with debossing “D” on one side and “5” & “7” on either side of the breakline on another side. Bottles of 100 NDC 65862-286-01 Perindopril Erbumine T ablets USP, 4 mg are white to off-white colored capsule shaped uncoated tablets, with debossing “D” on one side and “5” & “8” on either side of the breakline on another side. Bottles of 100 NDC 65862-287-01 Perindopril Erbumine T ablets USP, 8 mg are white to off-white colored round biconvex uncoated tablets, with debossing “D” on one side and “5” & “9” on either side of breakline on another side.
Bottles of 100 NDC 65862-288-01 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from moisture. Keep out of the reach of children.
For further information, please call Aurobindo Pharma USA, Inc. at 1-866-850-2876.
📋 Description ▾
11 DESCRIPTION Perindopril erbumine tablets USP contain the tert-butylamine salt of perindopril, the ethyl ester of a non-sulfhydryl angiotensin-converting enzyme (ACE) inhibitor. Perindopril erbumine is chemically described as (2S,3DS,7DS)-1-[(S)-N-[(S)-1-Carboxy-butyl]alanyl]hexahydro-2-indolinecarboxylic acid, 1-ethyl ester, compound with tert-butylamine (1:1). Its molecular formula is C 19 H 32 N 2 O 5 C 4 H 11 N.
Its structural formula is: Perindopril erbumine USP is a white or almost white, crystalline powder, slightly hygroscopic with a molecular weight of 368.47 (free acid) or 441.61 (salt form). It is freely soluble in water (60% w/w), alcohol and chloroform. Perindopril is the free acid form of perindopril erbumine, is a pro-drug and metabolized in vivo by hydrolysis of the ester group to form perindoprilat, the biologically active metabolite.
Perindopril erbumine tablets USP are available in 2 mg, 4 mg and 8 mg strengths for oral administration. In addition to perindopril erbumine, each tablet contains the following inactive ingredients: anhydrous lactose, silica hydrophobic colloidal anhydrous, microcrystalline cellulose, and magnesium stearate. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Female patients of childbearing age should be told about the consequences of exposure to perindopril erbumine during pregnancy. Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible.
Tell patients to report promptly any indication of infection ( e.g., sore throat, fever) which could be a sign of neutropenia. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 03/2024