
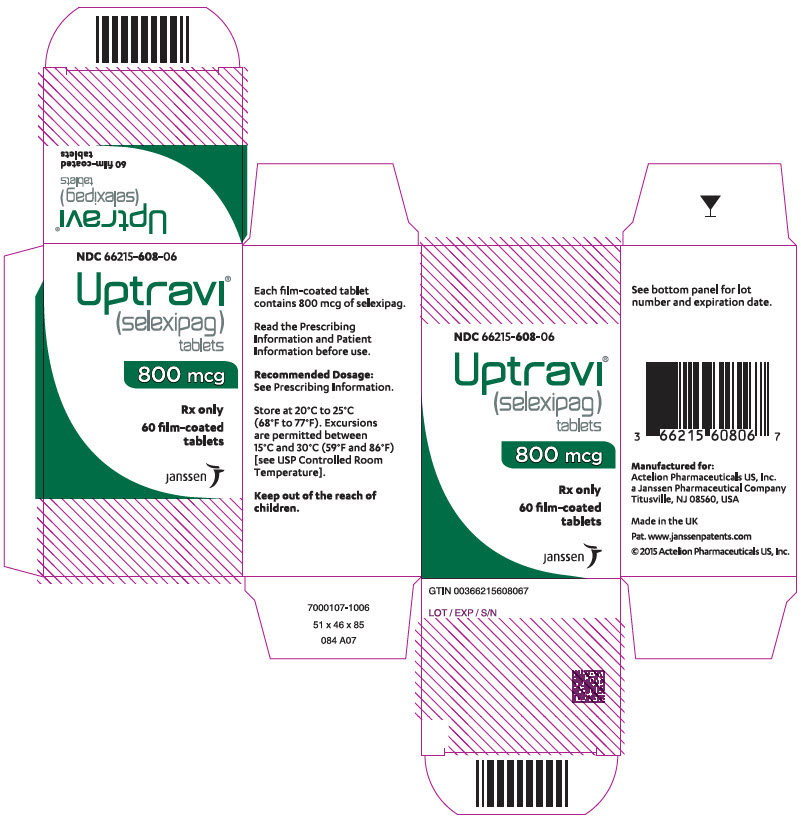
UPTRAVI Selexipag 800 ug Tablet, Coated, 60-count — NDC 66215-608-06 (Billing 66215-0608-06)
This is a package of 60 tablets of UPTRAVI Selexipag 800 ug Tablet, Coated from Actelion Pharmaceuticals US, Inc., marketed since Dec 2015 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 66215-608-06 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 66215 labeler · 608 product · 06 package
- Package marketed since
- Dec 21, 2015
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 60 EA per package
- Barcode (UPC)
- 0366215612064, 0366215610060, 0366215604069, 0366215910146 +3 more
- Medicaid fills, this package
- 1,224 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 075315
- GCN: 40358
- GPI-14 (Medi-Span): 40120070000325
- HICL (First Databank): 042922
- AHFS class code: 24:12.92.00
- RxCUI (RxNorm): 1729007
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Prostacyclin Receptor Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Selexipag is used in adults to treat pulmonary arterial hypertension (PAH, high blood pressure in the vessels that carry blood to the lungs) to slow down the worsening of symptoms and reduce the chance of being hospitalized for PAH. Selexipag is in a class of medications called selective nonprostanoid IP prostacyclin receptor agonists. It works by relaxing the blood vessels in the lungs to allow blood to flow easily.
Read the full MedlinePlus article ↗- Selexipag treats pulmonary arterial hypertension, a type of high blood pressure in the arteries of your lungs. It helps delay the disease getting worse and lowers the chance you'll...
- Tablets are taken by mouth twice a day and swallowed whole, so don't split or crush them. Taking them with food may help you tolerate them. Your doctor will raise your dose slowly,...
- Headache, diarrhea, nausea, jaw pain and muscle aches are common, especially while your dose is going up. Tell your doctor or pharmacist if they become hard to handle, since the do...
- Call right away if you have new or worsening shortness of breath, which could be fluid in the lungs. Also report symptoms that might suggest an overactive thyroid, or signs of an a...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Selexipag — tap one for details:
Selexipag may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $390.36 | $23,421.89 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $405.21 | $24,312.47 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 66215-0608-06 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 60 TABLET, COATED in 1 BOTTLE | 2015-12-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Uptravi 800 ugthis 66215-0608-06 | Actelion | 60 tablets | — | AB | FDA listed | — |
| Selexipag 800 ug 70710-1554-06 | Zydus | 60 tablets | — | — | FDA listed | — |
| Selexipag 800 ug 70771-1796-06 | Zydus | 60 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 10828298 ↗ | Method of use | U-2991 | Dec 1, 2036 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 9173881 ↗ | Method of use | U-1798 | Aug 12, 2029 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 7205302 ↗ | Drug substance | U-1797 | Oct 31, 2026 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 9284280 ↗ | Method of use | U-1831 | Jun 25, 2030 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 10821108 ↗ | Method of use | U-2992 | Dec 1, 2036 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 8791122 ↗ | Drug substance | — | Aug 1, 2030 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 8791122*PED ↗ | Drug product | — | Feb 1, 2031 |
| US 9173881*PED ↗ | Drug product | — | Feb 12, 2030 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 7205302*PED ↗ | Drug product | — | Apr 30, 2027 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 9284280*PED ↗ | Drug product | — | Dec 25, 2030 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10821108*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| US 10828298*PED ↗ | Drug product | — | Jun 1, 2037 |
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NPP | New Patient Population | May 23, 2029 |
| NS | New Strength | May 23, 2029 |
| NS | New Strength | May 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Nov 23, 2029 |
Is there a generic version of UPTRAVI 800 MCG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Selexipag inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII U3JF91U133
Hydroxypropyl cellulose is a plant-derived polymer that acts as a binder, thickener, and film-former in medications. It helps hold tablet ingredients together, control how quickly the drug dissolves, and create protective coatings on pills.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 2165RE0K14
A plant-based thickener made from cellulose that helps control how quickly the medicine dissolves and releases its active ingredient. It also binds ingredients together and improves the tablet's texture and handling during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Actelion Pharmaceuticals US, Inc. labeler code 66215
- Veletri epoprostenol 1.5 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 66215-402-01
- Veletri epoprostenol .5 mg/10mL Injection, Powder, Lyophilized, For Solution NDC 66215-403-01
- Opsumit macitentan 10 mg Tablet, Film Coated NDC 66215-501-15
- UPTRAVI Selexipag 200 ug Tablet, Coated NDC 66215-602-06
- UPTRAVI Selexipag 400 ug Tablet, Coated NDC 66215-604-06
- UPTRAVI Selexipag 600 ug Tablet, Coated NDC 66215-606-06
- UPTRAVI Selexipag 1000 ug Tablet, Coated NDC 66215-610-06
- UPTRAVI Selexipag 1200 ug Tablet, Coated NDC 66215-612-06
- UPTRAVI Selexipag 1400 ug Tablet, Coated NDC 66215-614-06
- UPTRAVI Selexipag 1600 ug Tablet, Coated NDC 66215-616-06
- UPTRAVI Titration Pack Selexipag Kit NDC 66215-628-20
- UPTRAVI Selexipag 1800 ug/10mL Injection, Powder, For Solution NDC 66215-718-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE UPTRAVI is a prostacyclin receptor agonist indicated for the treatment of pulmonary arterial hypertension (PAH, WHO Group I): In adults to delay disease progression and reduce the risk of hospitalization for PAH. ( 1.1 ) In pediatric patients aged 2 years and older. UPTRAVI reduces NT-proBNP and is expected to delay disease progression and reduce the risk of hospitalization for PAH. ( 1.1 )
1.1Pulmonary Arterial Hypertension Adult Patients UPTRAVI is indicated for the treatment of pulmonary arterial hypertension in adults (PAH, WHO Group I) to delay disease progression and reduce the risk of hospitalization for PAH. Effectiveness of UPTRAVI tablets was established in a long-term study in adult PAH patients with WHO Functional Class II–III symptoms. Patients had idiopathic and heritable PAH (58%), PAH associated with connective tissue disease (29%), PAH associated with congenital heart disease with repaired shunts (10%) [see Clinical Studies (14.1) ] .
Pediatric Patients UPTRAVI is indicated for the treatment of PAH (WHO Group I) in pediatric patients aged two years and older. UPTRAVI reduces NT-proBNP and is expected to delay disease progression and reduce the risk of hospitalization for PAH.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult patients: UPTRAVI tablets starting dose: 200 mcg orally twice daily. Increase the dose by 200 mcg orally twice daily at weekly intervals to the highest tolerated dose up to 1,600 mcg orally twice daily. ( 2.1 ) Pediatric patients: See Full Prescribing Information for recommended starting dose, titration increments, and maximum allowed dose based on body weight category.
( 2.1 ) Maintenance dose is determined by tolerability. ( 2.1 ) Moderate hepatic impairment: Starting dose once daily, increase in increments of the starting dose once daily at weekly intervals to the maximum allowed or highest tolerated dose. ( 2.6 ) Adult patients: UPTRAVI for injection dose is determined by the patient's current dose of UPTRAVI tablets.
Administer UPTRAVI for injection by intravenous infusion, twice daily. ( 2.2 ) See Full Prescribing Information for instructions on preparation and administration. ( 2.3 , 2.4 )
2.1Recommended Dosage and Administration for UPTRAVI Film-coated Tablets Adult Patients The recommended starting dosage of UPTRAVI tablets is 200 mcg given orally twice daily. Tolerability may be improved when taken with food [see Clinical Pharmacology (12.3) ] . Increase the dose in increments of 200 mcg orally twice daily, usually at weekly intervals, to the highest tolerated dose up to 1,600 mcg orally twice daily.
If a patient reaches a dose that cannot be tolerated, the dose should be reduced to the previous tolerated dose. Swallow the UPTRAVI tablets whole. Do not split or crush the tablets.
Pediatric Patients Two Years and Older The recommended starting dose of UPTRAVI is determined based on the patient's body weight and is given orally twice daily. The recommended UPTRAVI starting doses, titration increments, and maximum allowed doses based on body weight categories in pediatric patients are shown in Table 1. Table 1: Pediatric Dosing Regimen Body weight (kg) Recommended starting dose Recommended titration increments Maximum dose allowed 9 kg to less than 25 kg 100 mcg orally twice daily 100 mcg orally twice daily 800 mcg orally twice daily 25 kg to less than 40 kg 150 mcg orally twice daily 150 mcg orally twice daily 1,200 mcg orally twice daily 40 kg to less than 50 kg 150 mcg orally twice daily 150 mcg orally twice daily 1,600 mcg orally twice daily For pediatric patients with a body weight ≥40 kg to <50 kg multiple tablet dose strengths may be needed to reach the doses up to 1,600 mcg twice daily.
50 kg and greater 200 mcg orally twice daily 200 mcg orally twice daily 1,600 mcg orally twice daily Increase the dose in increments equivalent to the starting dose (i.e., 100 mcg, 150 mcg or 200 mcg given orally twice daily), at weekly intervals, to the highest tolerated dose up to the maximum dose allowed for the patient's body weight (see Table 1 ). If a patient reaches a dose that cannot be tolerated or medically managed, the dose should be reduced to the previous tolerated dose. Re-evaluate further dose titration based on changes in body weight category over time.
Tolerability may be improved when taken with food [see Clinical Pharmacology (12.3) ] . Swallow the UPTRAVI tablets whole. Do not split or crush the tablets.
Alternate Methods of Administration of 100 mcg and 150 mcg UPTRAVI Film-coated Tablets For patients who cannot swallow the tablets whole, 100 mcg or 150 mcg UPTRAVI tablets can be dispersed and administered in apple or orange juice. Do not disperse the tablet(s) in water or milk. Do not crush or split the tablet(s).
At least 1 mL of juice per tablet is recommended. Add the juice to the required number of tablet(s) per dosing schedule (see Table 1 ). Wait for 5 min and then stir until the tablets are dispersed.
Administer the mixture immediately after dispersion. Do not store tablets that are mixed with juice for later use. Alternatively, 100 mcg and 150 mcg UPTRAVI tablets can also be administered with soft foods such as yogurt, applesauce, or mashed banana.
Cover the require… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS UPTRAVI is available in the following presentations: Film-Coated Tablets 100 mcg selexipag [Light yellow tablet debossed with 1, 3 mm diameter] 150 mcg selexipag [Red tablet with no debossing, 3 mm diameter] 200 mcg selexipag [Light yellow tablet debossed with 2, 7 mm diameter] 400 mcg selexipag [Red tablet debossed with 4, 7 mm diameter] 600 mcg selexipag [Light violet tablet debossed with 6, 7 mm diameter] 800 mcg selexipag [Green tablet debossed with 8, 7 mm diameter] 1,000 mcg selexipag [Orange tablet debossed with 10, 7 mm diameter] 1,200 mcg selexipag [Dark violet tablet debossed with 12, 7 mm diameter] 1,400 mcg selexipag [Dark yellow tablet debossed with 14, 7 mm diameter] 1,600 mcg selexipag [Brown tablet debossed with 16, 7 mm diameter] UPTRAVI for Injection 1,800 mcg selexipag [Lyophilized powder white to almost white broken cake or powdered material, supplied in a 10 mL single-dose glass vial] Tablets: 100 mcg, 150 mcg, 200 mcg, 400 mcg, 600 mcg, 800 mcg, 1,000 mcg, 1,200 mcg, 1,400 mcg, 1,600 mcg.
( 3 ) For Injection: 1,800 mcg of selexipag as a lyophilized powder in a single-dose vial for reconstitution and dilution. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to the active substance or to any of the excipients. Concomitant use of strong inhibitors of CYP2C8 (e.g., gemfibrozil) [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ] . Concomitant use with strong CYP2C8 inhibitors. ( 4 , 7.1 , 12.3 ) Hypersensitivity to the active substance or to any of the excipients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Pulmonary edema in patients with pulmonary veno-occlusive disease. If confirmed, discontinue treatment. ( 5.1 )
5.1Pulmonary Edema with Pulmonary Veno-Occlusive Disease Should signs of pulmonary edema occur, consider the possibility of associated pulmonary veno-occlusive disease. If confirmed, discontinue UPTRAVI.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Adverse reactions in adult and pediatric patients occurring more frequently (≥5%) on UPTRAVI compared to placebo are headache, diarrhea, jaw pain, nausea, myalgia, vomiting, pain in extremity, and flushing. Additional adverse reaction occurring in pediatric patients more frequently (≥5%) on UPTRAVI compared to placebo is abdominal pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Actelion at 1-800-526-7736 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. UPTRAVI Tablets Adult Patients The safety of UPTRAVI tablets has been evaluated in a long-term, placebo-controlled study enrolling 1,156 adult patients with symptomatic PAH (GRIPHON study) [see Clinical Studies (14.1) ] . The exposure to UPTRAVI in this trial was up to 4.2 years with median duration of exposure of 1.4 years.
Table 3 presents adverse reactions more frequent on UPTRAVI tablets than on placebo by ≥3%. Table 3: Adverse Reactions UPTRAVI Placebo Adverse Reaction N=575 N=577 Headache 65% 32% Diarrhea 42% 18% Jaw pain 26% 6% Nausea 33% 18% Myalgia 16% 6% Vomiting 18% 9% Pain in extremity 17% 8% Flushing 12% 5% Arthralgia 11% 8% Anemia 8% 5% Decreased appetite 6% 3% Rash 11% 8% These adverse reactions are more frequent during the dose titration phase. Hyperthyroidism was observed in 1% (n=8) of patients on UPTRAVI tablets and in none of the patients on placebo.
Pediatric Patients Two Years and Older The safety of UPTRAVI tablets has been evaluated in a long-term, Phase 3, double-blind, placebo-controlled study (SALTO), where a total of 138 pediatric patients with symptomatic PAH ≥2 to <18 years of age were randomized 1:1 to receive either UPTRAVI or placebo [see Clinical Studies (14.2) ] . The exposure to UPTRAVI in this study was up to 4.1 years with a median duration of exposure of 1.5 years. The safety profile in pediatric patients was consistent with that observed in adults with PAH.
Compared to adults, a higher frequency of vomiting was observed (39% on UPTRAVI versus 19% on placebo). In addition, abdominal pain was observed in 15% of pediatric patients on UPTRAVI and in 6% on placebo. UPTRAVI-treated pediatric patients experienced a smaller mean increase in body weight and height compared to the placebo group.
The mean change in weight Z-score from baseline at 48 weeks in UPTRAVI-treated pediatric patients (n=54) was –0.31 compared to –0.09 in the placebo group (n=61); and at 96 weeks in UPTRAVI-treated pediatric patients (n=32) was –0.46 compared to –0.12 in the placebo group (n=35). The mean change in height Z-score from baseline at 48 weeks in UPTRAVI-treated pediatric patients (n=54) was –0.16 compared to –0.04 in the placebo group (n=61); and at 96 weeks in the UPTRAVI-treated pediatric patients (n=32) was –0.30 compared to –0.05 in the placebo group (n=35).
When treating pediatric patients with UPTRAVI, monitor growth. UPTRAVI for Injection Infusion-site reactions (infusion site erythema/redness, pain and swelling) were reported with UPTRAVI for Injection in adult patients. Laboratory Test Abnormalities Hemoglobin In a Phase 3 placebo-controlled study in adult patients with PAH, mean absolute changes in hemoglobin at regular visits compared to baseline ranged from −0.34 to −0.02 g/dL in the UPTRAVI group compared to −0.05 to 0.25 g/dL in the placebo group.
A decrease in hemoglobin concentration to below 10 g/dL was reported in 8.6% of patients treated with UPTRAVI tablets and 5.0% of placebo-treated patients. Thyroid Function Tests In a Phase 3 placebo-controlled study in adult patients with PAH, a reduction (up to −0.3 MU/L from a baseline median of
2.5MU/L) in median thyroid-stimulating hormone (TSH) was observed at most visits in th… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Moderate CYP2C8 inhibitors (e.g., clopidogrel, deferasirox and teriflunomide) increase exposure to the active metabolite of UPTRAVI. Reduce the dosing of UPTRAVI to once daily. ( 2.7 , 7.1 , 12.3 ) CYP2C8 inducers (e.g., rifampin) decrease exposure to the active metabolite. Increase up to twice the dose of UPTRAVI. ( 7.2 , 12.3 )
7.1CYP2C8 Inhibitors Concomitant administration with gemfibrozil, a strong inhibitor of CYP2C8, doubled the exposure to selexipag and increased exposure to the active metabolite by approximately 11-fold. Concomitant administration of UPTRAVI with strong inhibitors of CYP2C8 (e.g., gemfibrozil) is contraindicated [see Contraindications (4) and Clinical Pharmacology (12.3) ] . Concomitant administration of UPTRAVI tablets with clopidogrel, a moderate inhibitor of CYP2C8, had no relevant effect on the exposure to selexipag and increased the exposure to the active metabolite by approximately 2.7-fold [see Clinical Pharmacology (12.3) ] .
Reduce the dosing of UPTRAVI to once daily in adult and pediatric patients on a moderate CYP2C8 inhibitor [see Dosage and Administration (2.7) ] .
7.2CYP2C8 Inducers Concomitant administration with an inducer of CYP2C8 and UGT 1A3 and 2B7 enzymes (rifampin) halved exposure to the active metabolite. Increase UPTRAVI up to twice the dose when co-administered with rifampin. Reduce UPTRAVI when rifampin is stopped [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Nursing mothers: Discontinue UPTRAVI or breastfeeding. ( 8.2 ) Severe hepatic impairment: Avoid use. ( 8.6 )
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies with UPTRAVI in pregnant women. Animal reproduction studies performed with selexipag showed no clinically relevant effects on embryofetal development and survival. A slight reduction in maternal as well as in fetal body weight was observed when pregnant rats were administered selexipag during organogenesis at a dose producing an exposure to the active metabolite approximately 47 times that in humans at the maximum recommended human dose.
No adverse developmental outcomes were observed with oral administration of selexipag to pregnant rabbits during organogenesis at exposures to the active metabolite up to 50 times the human exposure at the maximum recommended human dose. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk In patients with pulmonary arterial hypertension, pregnancy is associated with an increased rate of maternal and fetal morbidity and mortality, including heart failure, stroke, spontaneous abortion, intrauterine growth restriction, premature labor, and preterm birth. Data Animal Data Pregnant rats were treated with selexipag using oral doses of 2, 6, and 20 mg/kg/day (up to 47 times the exposure to the active metabolite at the maximum recommended human oral dose of 1,600 mcg twice daily on an area under the curve [AUC] basis) during the period of organogenesis (gestation days 7 to 17).
Selexipag did not cause adverse developmental effects to the fetus in this study. A slight reduction in fetal body weight was observed in parallel with a slight reduction in maternal body weight at the high dose. Pregnant rabbits were treated with selexipag using oral doses of 3, 10, and 30 mg/kg (up to 50 times the exposure to the active metabolite at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis) during the period of organogenesis (gestation days 6 to 18).
Selexipag did not cause adverse developmental effects to the fetus in this study. In a pre- and post-natal development study, pregnant rats were treated with selexipag from gestation day 7 through lactation day 20 at oral doses of 2, 6, and 20 mg/kg/day (up to 35 times the exposure to the active metabolite at the maximum recommended human dose of 1,600 mcg twice daily on an AUC basis). Treatment with selexipag did not cause adverse developmental effects in this study at any dose.
8.2Lactation It is not known if UPTRAVI is present in human milk. Selexipag or its metabolites were present in the milk of rats. Because many drugs are present in the human milk and because of the potential for serious adverse reactions in nursing infants, discontinue nursing or discontinue UPTRAVI.
8.4Pediatric Use Safety and effectiveness of UPTRAVI have been established for the treatment of PAH in pediatric patients aged 2 years and older. Use of UPTRAVI for this indication is supported by evidence from an adequate and well-controlled study in adults with additional pharmacokinetic, pharmacodynamic, and safety data in pediatric patients aged 2 years and older (N=132) [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) and Clinical Studies (14.2) ]. The safety profile observed in pediatric patients was consistent with that of adults.
A higher frequency of vomiting and abdominal pain was observed in UPTRAVI-treated pediatric patients compared to UPTRAVI-treated adults. UPTRAVI-treated pediatric patients experienced a smaller mean increase in body weight and height compared to placebo. When treating pediatric patients with UPTRAVI, monitor g… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies with UPTRAVI in pregnant women. Animal reproduction studies performed with selexipag showed no clinically relevant effects on embryofetal development and survival. A slight reduction in maternal as well as in fetal body weight was observed when pregnant rats were administered selexipag during organogenesis at a dose producing an exposure to the active metabolite approximately 47 times that in humans at the maximum recommended human dose.
No adverse developmental outcomes were observed with oral administration of selexipag to pregnant rabbits during organogenesis at exposures to the active metabolite up to 50 times the human exposure at the maximum recommended human dose. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk In patients with pulmonary arterial hypertension, pregnancy is associated with an increased rate of maternal and fetal morbidity and mortality, including heart failure, stroke, spontaneous abortion, intrauterine growth restriction, premature labor, and preterm birth. Data Animal Data Pregnant rats were treated with selexipag using oral doses of 2, 6, and 20 mg/kg/day (up to 47 times the exposure to the active metabolite at the maximum recommended human oral dose of 1,600 mcg twice daily on an area under the curve [AUC] basis) during the period of organogenesis (gestation days 7 to 17).
Selexipag did not cause adverse developmental effects to the fetus in this study. A slight reduction in fetal body weight was observed in parallel with a slight reduction in maternal body weight at the high dose. Pregnant rabbits were treated with selexipag using oral doses of 3, 10, and 30 mg/kg (up to 50 times the exposure to the active metabolite at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis) during the period of organogenesis (gestation days 6 to 18).
Selexipag did not cause adverse developmental effects to the fetus in this study. In a pre- and post-natal development study, pregnant rats were treated with selexipag from gestation day 7 through lactation day 20 at oral doses of 2, 6, and 20 mg/kg/day (up to 35 times the exposure to the active metabolite at the maximum recommended human dose of 1,600 mcg twice daily on an AUC basis). Treatment with selexipag did not cause adverse developmental effects in this study at any dose.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of UPTRAVI have been established for the treatment of PAH in pediatric patients aged 2 years and older. Use of UPTRAVI for this indication is supported by evidence from an adequate and well-controlled study in adults with additional pharmacokinetic, pharmacodynamic, and safety data in pediatric patients aged 2 years and older (N=132) [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) and Clinical Studies (14.2) ]. The safety profile observed in pediatric patients was consistent with that of adults.
A higher frequency of vomiting and abdominal pain was observed in UPTRAVI-treated pediatric patients compared to UPTRAVI-treated adults. UPTRAVI-treated pediatric patients experienced a smaller mean increase in body weight and height compared to placebo. When treating pediatric patients with UPTRAVI, monitor growth [see Adverse Reactions (6.1) ] .
The safety and effectiveness of UPTRAVI have not been established in pediatric patients younger than 2 years. Due to nonclinical studies demonstrating a risk of intussusception in juvenile dogs and known susceptibility to gastrointestinal intussusception in young children, treatment with UPTRAVI in pediatric patients younger than 2 years of age was not studied. Juvenile Animal Toxicity Data In juvenile dogs, intussusception due to prostacyclin-related effects on intestinal motility was observed sporadically.
Safety margins adapted for prostacyclin receptor potency for the active metabolite were 2-fold (based on total exposure) in relation to human therapeutic exposure. The finding did not occur in mouse or rat toxicity studies.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 1,368 subjects in clinical studies of UPTRAVI tablets, 248 subjects were 65 years of age and older, while 19 were 75 and older. No overall differences were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Isolated cases of overdose in adults with UPTRAVI tablets up to 3,200 mcg were reported. Mild, transient nausea was the only reported consequence. In the event of overdose, supportive measures must be taken as required. Dialysis is unlikely to be effective because selexipag and its active metabolite are highly protein-bound.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Selexipag is a prostacyclin receptor (IP receptor) agonist that is structurally distinct from prostacyclin. Selexipag is hydrolyzed by carboxylesterase 1 to yield its active metabolite, which is approximately 37-fold as potent as selexipag. Selexipag and the active metabolite are selective for the IP receptor versus other prostanoid receptors (EP 1–4 , DP, FP, and TP).
12.2Pharmacodynamics Cardiac Electrophysiology At the maximum tolerated dose of 1,600 mcg UPTRAVI tablets twice daily, UPTRAVI does not prolong the QT interval to any clinically relevant extent. Platelet Aggregation Both selexipag and its active metabolite caused concentration-dependent inhibition of platelet aggregation in vitro with an IC 50 of 5.5 µM and 0.21 µM, respectively. However, at clinically relevant concentrations, there was no effect on platelet aggregation test parameters as seen following multiple-dose administrations of UPTRAVI tablets in healthy subjects from 400 to 1,800 mcg twice daily.
Pulmonary Hemodynamics A Phase 2 clinical study NS-304/-02 assessed hemodynamic variables after 17 weeks of oral treatment in adult patients with PAH WHO Functional Class II–III and concomitantly receiving endothelin receptor antagonists (ERAs) and/or phosphodiesterase type 5 (PDE-5) inhibitors. Patients titrating UPTRAVI tablets to an individually tolerated dose (200 mcg twice daily increments up to 800 mcg twice daily) (N=33) achieved a statistically-significant mean reduction in pulmonary vascular resistance of 30.3% (95% confidence interval [CI] −44.7%, −12.2%) and an increase in cardiac index (median treatment effect) of
0.41L/min/m 2 (95% CI 0.10, 0.71) compared to placebo (N=10). A Phase 2 clinical study NS304P-P2-1 assessed hemodynamic variables in 6 Japanese pediatric patients with PAH WHO Functional Class II–III. The mean age was 9.2 years (range 3–13 years).
Five patients had idiopathic PAH, and 1 patient had postoperative congenital heart disease. Three patients were treatment-naïve, while 3 patients received background combination therapy. UPTRAVI was titrated and dosed the same as in the SALTO study [see Clinical Studies (14.2) ] .
A mean reduction of
5.55Wood units∙m 2 (95% CI −12.76, 1.67) in pulmonary vascular resistance index at week 16 was achieved. Drug Interaction In a study in healthy adult subjects, UPTRAVI tablets (400 mcg twice a day) did not influence the pharmacodynamic effect of warfarin on the international normalized ratio.
12.3Pharmacokinetics The pharmacokinetics of selexipag and its active metabolite have been studied primarily in healthy subjects. The pharmacokinetics of selexipag and the active metabolite, after both single- and multiple-dose oral administration, were dose-proportional up to a single dose of 800 mcg and multiple doses of up to 1,800 mcg twice daily. The pharmacokinetics of selexipag and the active metabolite, after multiple-dose intravenous administration, were dose-proportional in the tested dose range from 450 to 1,800 mcg twice a day.
In healthy subjects, inter-subject variability in exposure (area under the curve over a dosing interval, AUC) at steady-state following oral administration was 43% and 39% for selexipag and the active metabolite, respectively. Intra-subject variability in exposure was 24% and 19% for selexipag and the active metabolite, respectively. Exposures to selexipag and the active metabolite at steady-state in PAH patients and healthy subjects were similar.
The pharmacokinetics of selexipag and the active metabolite in PAH patients were not influenced by the severity of the disease and did not change with time. The corresponding UPTRAVI tablets and UPTRAVI for injection doses (Table 2) provide similar exposure to the active metabolite in PAH patients at steady-state, whereas the exposure to selexipag is approximately twice as high after intravenous administration compared to oral administration. Both in healthy subjects and PAH patie… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Selexipag is a prostacyclin receptor (IP receptor) agonist that is structurally distinct from prostacyclin. Selexipag is hydrolyzed by carboxylesterase 1 to yield its active metabolite, which is approximately 37-fold as potent as selexipag. Selexipag and the active metabolite are selective for the IP receptor versus other prostanoid receptors (EP 1–4 , DP, FP, and TP).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING UPTRAVI ® (selexipag) film-coated, round tablets are supplied in the following configurations: Strength (mcg) Color Debossing NDC-XXX Bottle of 60 NDC-XXX Bottle of 140 100 Light yellow 1 Not Available 66215-910-14 150 Red No debossing is present on the 150 mcg tablets. Not Available 66215-915-14 200 Light yellow 2 66215-602-06 66215-602-14 400 Red 4 66215-604-06 Not Available 600 Light violet 6 66215-606-06 Not Available 800 Green 8 66215-608-06 Not Available 1,000 Orange 10 66215-610-06 Not Available 1,200 Dark violet 12 66215-612-06 Not Available 1,400 Dark yellow 14 66215-614-06 Not Available 1,600 Brown 16 66215-616-06 Not Available UPTRAVI ® (selexipag) tablets are also supplied in a Titration Pack [NDC 66215-628-20] that includes a 140-count bottle of 200-mcg tablets and a 60-count bottle of 800-mcg tablets.
Store at 20 °C to 25 °C (68 °F to 77 °F). Excursions are permitted between 15 °C and 30 °C (59 °F and 86 °F) [see USP Controlled Room Temperature]. Recommended storage for UPTRAVI 100 mcg and 150 mcg tablets: Store and dispense in the original package to protect from moisture.
Keep out of reach of children. UPTRAVI ® (selexipag) for injection, for intravenous use, is supplied in a 10 mL Type I glass vial closed by a stopper and sealed with an aluminum flip-off button, containing 1,800 mcg of selexipag [NDC 66215-718-01]. UPTRAVI ® (selexipag) for injection is available in cartons containing 1 single-dose vial.
Storage conditions for UPTRAVI for injection: Store the original carton containing glass vial in a refrigerator at 2 °C to 8 °C (36 ºF to 46 ºF) until use in order to protect from light.
📦 Storage and Handling ▾
Store at 20 °C to 25 °C (68 °F to 77 °F). Excursions are permitted between 15 °C and 30 °C (59 °F and 86 °F) [see USP Controlled Room Temperature]. Recommended storage for UPTRAVI 100 mcg and 150 mcg tablets: Store and dispense in the original package to protect from moisture.
Keep out of reach of children. UPTRAVI ® (selexipag) for injection, for intravenous use, is supplied in a 10 mL Type I glass vial closed by a stopper and sealed with an aluminum flip-off button, containing 1,800 mcg of selexipag [NDC 66215-718-01]. UPTRAVI ® (selexipag) for injection is available in cartons containing 1 single-dose vial.
Storage conditions for UPTRAVI for injection: Store the original carton containing glass vial in a refrigerator at 2 °C to 8 °C (36 ºF to 46 ºF) until use in order to protect from light.
📋 Description ▾
11 DESCRIPTION UPTRAVI contains selexipag, a prostacyclin receptor agonist. The chemical name of selexipag is 2-{4-[(5,6-diphenylpyrazin-2-yl)(isopropyl)amino]butoxy}- N -(methylsulfonyl) acetamide. It has a molecular formula of C 26 H 32 N 4 O 4 S and a molecular weight of 496.62.
Selexipag has the following structural formula: Selexipag is a pale yellow crystalline powder that is practically insoluble in water. In the solid state selexipag is very stable, is not hygroscopic, and is not light sensitive. UPTRAVI ® (selexipag) tablets: depending on the dose strength, each round film-coated tablet for oral administration contains 100, 150, 200, 400, 600, 800, 1,000, 1,200, 1,400, or 1,600 mcg of selexipag.
The tablets include the following inactive ingredients: corn starch, D-mannitol, hydroxypropyl cellulose, low substituted hydroxypropyl cellulose, and magnesium stearate. The tablets are film coated with a coating material containing carnauba wax, hypromellose, propylene glycol, titanium dioxide, along with mixtures of iron oxide black, iron oxide red and/or iron oxide yellow. The coating material of the 100 mcg and 150 mcg tablets also contains talc.
UPTRAVI ® (selexipag) for injection: contains 1,800 mcg of selexipag per vial. UPTRAVI for injection includes the following inactive ingredients: glycine (180 mg), phosphoric acid (3.53 mg), polysorbate 20 (10.8 mg) and sodium hydroxide (for pH adjustment). UPTRAVI for injection is provided in 10 mL Type I clear glass vials closed by a stopper and tear-off aluminum seal.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Inform Patients To take a missed dose as soon as possible, unless the next dose is within the next 6 hours. Not to split or crush tablets. To follow the instructions for alternate methods of administration for patients who cannot swallow tablets whole [see Dosage and Administration (2.1) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of selexipag and its active metabolite have been studied primarily in healthy subjects. The pharmacokinetics of selexipag and the active metabolite, after both single- and multiple-dose oral administration, were dose-proportional up to a single dose of 800 mcg and multiple doses of up to 1,800 mcg twice daily. The pharmacokinetics of selexipag and the active metabolite, after multiple-dose intravenous administration, were dose-proportional in the tested dose range from 450 to 1,800 mcg twice a day.
In healthy subjects, inter-subject variability in exposure (area under the curve over a dosing interval, AUC) at steady-state following oral administration was 43% and 39% for selexipag and the active metabolite, respectively. Intra-subject variability in exposure was 24% and 19% for selexipag and the active metabolite, respectively. Exposures to selexipag and the active metabolite at steady-state in PAH patients and healthy subjects were similar.
The pharmacokinetics of selexipag and the active metabolite in PAH patients were not influenced by the severity of the disease and did not change with time. The corresponding UPTRAVI tablets and UPTRAVI for injection doses (Table 2) provide similar exposure to the active metabolite in PAH patients at steady-state, whereas the exposure to selexipag is approximately twice as high after intravenous administration compared to oral administration. Both in healthy subjects and PAH patients, after oral administration, exposure at steady-state to the active metabolite is approximately 3- to 4-fold that of selexipag.
Absorption The absolute bioavailability of orally administered selexipag is approximately 49%. Upon oral administration, maximum observed plasma concentrations of selexipag and its active metabolite are reached within about 1–3 hours and 3–4 hours, respectively. Similar exposures were observed in pediatric study patients after taking whole tablets with water, taking with soft food, and dispersing in apple or orange juice.
Effect of Food In the presence of food, the absorption of selexipag was prolonged resulting in a delayed time to peak concentration (T max ) and ~30% lower peak plasma concentration (C max ). The exposure to selexipag and the active metabolite (AUC) did not significantly change in the presence of food. Distribution The volume of distribution of selexipag at steady-state is
11.7L. Selexipag and its active metabolite are highly bound to plasma proteins (approximately 99% in total and to the same extent to albumin and alpha1-acid glycoprotein). Metabolism Selexipag is hydrolyzed to its active metabolite, (free carboxylic acid) in the liver and intestine by carboxylesterases.
Oxidative metabolism, catalyzed mainly by CYP2C8 and to a smaller extent by CYP3A4, leads to the formation of hydroxylated and dealkylated products. UGT1A3 and UGT2B7 are involved in the glucuronidation of the active metabolite. Except for the active metabolite, none of the circulating metabolites in human plasma exceeds 3% of the total drug-related material.
Elimination Elimination of selexipag is predominately via metabolism with a mean terminal half-life of 0.8–2.5 hours. The terminal half-life of the active metabolite is 6.2–13.5 hours. Selexipag does not accumulate following twice daily repeat administration.
There is minimal accumulation of the active metabolite upon twice daily repeat administration suggesting that the effective half-life is in the range of 3–4 hours. The total body clearance of selexipag is
17.9L/hour. Excretion In a study in healthy subjects with radiolabeled selexipag, approximately 93% of radioactive drug material was eliminated in feces and only 12% in urine. Neither selexipag nor its active metabolite were found in urine.
Specific Populations No clinically relevant effects of sex, race, age or body weight on the pharmacokinetics of selexipag and its active metabolite have been observed in healthy subjects or PAH patients. Pedi… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology At the maximum tolerated dose of 1,600 mcg UPTRAVI tablets twice daily, UPTRAVI does not prolong the QT interval to any clinically relevant extent. Platelet Aggregation Both selexipag and its active metabolite caused concentration-dependent inhibition of platelet aggregation in vitro with an IC 50 of 5.5 µM and 0.21 µM, respectively. However, at clinically relevant concentrations, there was no effect on platelet aggregation test parameters as seen following multiple-dose administrations of UPTRAVI tablets in healthy subjects from 400 to 1,800 mcg twice daily.
Pulmonary Hemodynamics A Phase 2 clinical study NS-304/-02 assessed hemodynamic variables after 17 weeks of oral treatment in adult patients with PAH WHO Functional Class II–III and concomitantly receiving endothelin receptor antagonists (ERAs) and/or phosphodiesterase type 5 (PDE-5) inhibitors. Patients titrating UPTRAVI tablets to an individually tolerated dose (200 mcg twice daily increments up to 800 mcg twice daily) (N=33) achieved a statistically-significant mean reduction in pulmonary vascular resistance of 30.3% (95% confidence interval [CI] −44.7%, −12.2%) and an increase in cardiac index (median treatment effect) of
0.41L/min/m 2 (95% CI 0.10, 0.71) compared to placebo (N=10). A Phase 2 clinical study NS304P-P2-1 assessed hemodynamic variables in 6 Japanese pediatric patients with PAH WHO Functional Class II–III. The mean age was 9.2 years (range 3–13 years).
Five patients had idiopathic PAH, and 1 patient had postoperative congenital heart disease. Three patients were treatment-naïve, while 3 patients received background combination therapy. UPTRAVI was titrated and dosed the same as in the SALTO study [see Clinical Studies (14.2) ] .
A mean reduction of
5.55Wood units∙m 2 (95% CI −12.76, 1.67) in pulmonary vascular resistance index at week 16 was achieved. Drug Interaction In a study in healthy adult subjects, UPTRAVI tablets (400 mcg twice a day) did not influence the pharmacodynamic effect of warfarin on the international normalized ratio.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Efficacy of UPTRAVI Tablets in Adult Patients with Pulmonary Arterial Hypertension The effect of UPTRAVI tablets on progression of PAH was demonstrated in a multi-center, double-blind, placebo-controlled, parallel group, event-driven study (GRIPHON) in 1,156 adult patients with symptomatic (WHO Functional Class I [0.8%], II [46%], III [53%], and IV [1%]) PAH. Patients were randomized to either placebo (N=582), or UPTRAVI tablets (N=574). The dose was increased in weekly intervals by increments of 200 mcg twice a day to the highest tolerated dose up to 1,600 mcg twice a day.
The primary study endpoint was the time to first occurrence up to end-of-treatment of: a) death, b) hospitalization for PAH, c) PAH worsening resulting in need for lung transplantation, or balloon atrial septostomy, d) initiation of parenteral prostanoid therapy or chronic oxygen therapy, or e) other disease progression based on a 15% decrease from baseline in 6-minute walk distance (6MWD) plus worsening of Functional Class or need for additional PAH-specific therapy. The mean age was 48 years, the majority of patients were white (65%) and female (80%).
Nearly all patients were in WHO Functional Class II and III at baseline. Idiopathic or heritable PAH was the most common etiology in the study population (58%) followed by PAH associated with connective tissue disease (29%), PAH associated with congenital heart disease with repaired shunts (10%), drugs and toxins (2%), and HIV (1%). At baseline, the majority of enrolled patients (80%) were being treated with a stable dose of an endothelin receptor antagonist (15%), a PDE-5 inhibitor (32%), or both (33%).
Patients on UPTRAVI tablets achieved doses within the following groups: 200–400 mcg (23%), 600–1,000 mcg (31%) and 1,200–1,600 mcg (43%). Treatment with UPTRAVI tablets resulted in a 40% reduction (99% CI: 22 to 54%; two-sided log-rank p-value <0.0001) of the occurrence of primary endpoint events compared to placebo (Table 4; Figure 3). The beneficial effect of UPTRAVI was primarily attributable to a reduction in hospitalization for PAH and a reduction in other disease progression events (Table 4).
The observed benefit of UPTRAVI was similar regardless of the dose achieved when patients were titrated to their highest tolerated dose [see Dosage and Administration (2.1) ] . Figure 3 Kaplan-Meier Estimates of the First Morbidity-Mortality Event in GRIPHON Table 4: Primary Endpoints and Related Components in GRIPHON UPTRAVI N=574 Placebo N=582 Hazard Ratio (99% CI) p-value n % n % Primary endpoint events up to the end of treatment All primary endpoint events As first event: 155 27.0 242 41.6 0.60 [0.46, 0.78] <0.0001 Hospitalization for PAH 78 13.6 109
18.7Other disease progression (Decrease in 6MWD plus worsening functional class or need for other therapy) 38 6.6 100
17.2Death 28 4.9 18
3.1Parenteral prostanoid or chronic oxygen therapy 10 1.7 13
2.2PAH worsening resulting in need for lung transplantation or balloon atrial septostomy 1 0.2 2
0.3It is not known if the excess number of deaths in the UPTRAVI group is drug-related because there were so few deaths and the imbalance was not observed until 18 months into GRIPHON. Figures 4A, B, and C show time to first event analyses for primary endpoint components of hospitalization for PAH (A), other disease progression (B), and death (C) all censored 7 days after any primary end point event (because many patients on placebo transitioned to open-label UPTRAVI at this point). Figure 4A Hospitalization for PAH as the First Endpoint in GRIPHON Figure 4B Disease Progression as the First Endpoint in GRIPHON Figure 4C Death as the First Endpoint in GRIPHON The treatment effect of UPTRAVI on time to first primary event was consistent irrespective of background PAH therapy (i.e., in combination with an ERA, PDE-5i, both, or without background therapy) (Figure 5).
Figure 5 Subgroup Analyses of the Primary Endpoint in GRIPHON Note: Race group "Ot… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis: In the 2-year carcinogenicity studies, chronic oral administration of selexipag revealed no evidence of carcinogenic potential in rats at 100 mg/kg/day and mice at 500 mg/kg/day which resulted in the exposures to the active metabolite more than 25 times the human exposure at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis. Mutagenesis: Selexipag and the active metabolite are not genotoxic on the basis of the overall evidence of conducted genotoxicity studies.
Fertility: In rats administered with selexipag orally, the no effect dose for effects on fertility was 60 mg/kg/day which resulted in the exposure to the active metabolite approximately 175 times the human exposure at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis: In the 2-year carcinogenicity studies, chronic oral administration of selexipag revealed no evidence of carcinogenic potential in rats at 100 mg/kg/day and mice at 500 mg/kg/day which resulted in the exposures to the active metabolite more than 25 times the human exposure at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis. Mutagenesis: Selexipag and the active metabolite are not genotoxic on the basis of the overall evidence of conducted genotoxicity studies.
Fertility: In rats administered with selexipag orally, the no effect dose for effects on fertility was 60 mg/kg/day which resulted in the exposure to the active metabolite approximately 175 times the human exposure at the maximum recommended human oral dose of 1,600 mcg twice daily on an AUC basis.
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 5/2026 PATIENT INFORMATION UPTRAVI ® (up-TRA-vee) (selexipag) tablets UPTRAVI ® (up-TRA-vee) (selexipag) for injection What is UPTRAVI?
UPTRAVI is a prescription medicine used to treat adults and children 2 years of age and older with pulmonary arterial hypertension (PAH) which is high blood pressure in the arteries of your lungs. UPTRAVI can help slow down the progression of your disease and lower your risk of being hospitalized for PAH. It is not known if UPTRAVI is safe and effective in children younger than 2 years of age.
Do not take UPTRAVI if you or your child : are allergic to selexipag or any of the other ingredients in UPTRAVI (see the end of the Patient Information leaflet for a complete list of ingredients). take gemfibrozil because this medicine may affect how UPTRAVI works and cause side effects. Before you or your child take UPTRAVI, tell your healthcare provider about all of your medical conditions, including if you: have liver problems. have narrowing of the pulmonary veins, a condition called pulmonary veno-occlusive disease. are pregnant or plan to become pregnant.
It is not known if UPTRAVI will harm your unborn baby. are breastfeeding or plan to breastfeed. It is not known if UPTRAVI passes into your breast milk. You and your healthcare provider should decide if you will take UPTRAVI or breastfeed.
You should not do both. Tell your healthcare provider about all the medicines you or your child take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. UPTRAVI and other medicines may affect each other causing side effects.
Do not start any new medicine until you check with your healthcare provider. How should you or your child take UPTRAVI? UPTRAVI tablets Take or give UPTRAVI exactly as your healthcare provider tells you to take it.
Do not stop taking UPTRAVI unless your healthcare provider tells you to stop. Your child's healthcare provider will prescribe an UPTRAVI starting dose based on your child's body weight. Your healthcare provider will slowly increase your or your child's dose to find the dose of UPTRAVI that is right.
If you or your child have side effects, your healthcare provider may tell you to change the dose of UPTRAVI. UPTRAVI can be taken with or without food. Taking UPTRAVI with food may help you or your child tolerate UPTRAVI better.
UPTRAVI is usually taken 2 times each day. Swallow UPTRAVI tablets whole. Do not split or crush UPTRAVI tablets.
If you or your child cannot swallow the tablets: Dissolve (disperse) the 100 mcg or 150 mcg tablet(s) in apple or orange juice. Do not disperse the tablet(s) in water or milk. Place the required number of tablet(s) for the prescribed dose in a cup.
Do not crush or split the tablet(s). Add 1 or 2 teaspoons of apple or orange juice to the prescribed number of tablets. Wait for 5 minutes, then stir the juice and the tablet(s) until the tablets are dispersed.
Take or give the mixture right away. UPTRAVI tablets can also be given with soft foods as follows: Cover the prescribed number of 100 mcg or 150 mcg tablets with a small amount of soft food, such as yogurt, applesauce or mashed banana. Take or give the mixture right away.
Make sure no remaining medicine is left in the container by adding more soft food and take or give the mixture right away. Do not store UPTRAVI tablets that are already mixed with juice or soft food for later use. If you or your child miss a dose of UPTRAVI, take it as soon as you remember.
If the next scheduled dose is due within 6 hours, skip the missed dose. Take the next dose at the regular time. If you or your child miss 3 or more days of UPTRAVI, call your healthcare provider to see if the dose needs to be changed.
If you or your child take too much UPTRAVI, call your healthcare provider or go to the nearest hospital emergency room right away. UPTRAVI given by intravenous (IV) injection Your heal… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 5/2026 Dosage and Administration ( 2.1 , 2.6 , 2.7 ) 5/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 200 mcg Tablet Bottle Carton NDC 66215-602-06 Uptravi ® (selexipag) tablets 200 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 200 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 400 mcg Tablet Bottle Carton NDC 66215-604-06 Uptravi ® (selexipag) tablets 400 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 400 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 600 mcg Tablet Bottle Carton NDC 66215-606-06 Uptravi ® (selexipag) tablets 600 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 600 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 800 mcg Tablet Bottle Carton NDC 66215-608-06 Uptravi ® (selexipag) tablets 800 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 800 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 1000 mcg Tablet Bottle Carton NDC 66215-610-06 Uptravi ® (selexipag) tablets 1000 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 1000 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 1200 mcg Tablet Bottle Carton NDC 66215-612-06 Uptravi ® (selexipag) tablets 1200 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 1200 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 1400 mcg Tablet Bottle Carton NDC 66215-614-06 Uptravi ® (selexipag) tablets 1400 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 1400 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 1600 mcg Tablet Bottle Carton NDC 66215-616-06 Uptravi ® (selexipag) tablets 1600 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 1600 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - Kit Carton NDC 66215-628-20 TITRATION PACK Uptravi ® (selexipag) tablets 200 mcg Rx only 140 film-coated tablets Uptravi ® (selexipag) tablets 800 mcg Rx only 60 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - Kit Carton
PRINCIPAL DISPLAY PANEL - 1,800 mcg Vial Carton NDC 66215-718-01 Uptravi ® (selexipag) for injection 1,800 mcg/vial FOR INTRAVENOUS INFUSION ONLY Reconstitute and Dilute Prior to Use. Single-dose vial. Discard unused portion. Rx only Sterile One Vial OPEN HERE PRINCIPAL DISPLAY PANEL - 1,800 mcg Vial Carton
PRINCIPAL DISPLAY PANEL - 100 mcg Tablet Bottle Carton NDC 66215-910-14 Uptravi ® (selexipag) tablets 100 mcg Rx only 140 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 100 mcg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 150 mcg Tablet Bottle Carton NDC 66215-915-14 Uptravi ® (selexipag) tablets 150 mcg Rx only 140 film-coated tablets Johnson &Johnson PRINCIPAL DISPLAY PANEL - 150 mcg Tablet Bottle Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |