
Nifedipine 60 mg Tablet, Extended Release, 100-count — NDC 68382-689-01 (Billing 68382-0689-01)
This is a package of 100 tablets of Nifedipine 60 mg Tablet, Extended Release from Zydus Pharmaceuticals (USA) Inc., marketed since Aug 2018 and currently FDA-listed. It is the main listing for this product, which comes in 5 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 198034
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Nifedipine is used to treat high blood pressure and to control angina (chest pain). Nifedipine is in a class of medications called calcium-channel blockers. It lowers blood pressure by relaxing the blood vessels so the heart does not have to pump as hard. It controls chest pain by increasing the supply of blood and oxygen to the heart. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood vessels, kidneys and other parts of the body. Damage to these organs may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss...
Read the full MedlinePlus article ↗- It treats angina, which is chest pain from the heart, and the extended-release tablets also treat high blood pressure. Your prescriber chose the form that fits your condition, so t...
- Swallow it whole. Don't bite or split extended-release tablets. They are usually taken once a day, while capsules are taken several times a day. Follow your label and prescriber.
- No. Grapefruit can raise nifedipine levels in your body and increase side effects. It's best to avoid grapefruit and its juice entirely.
- Swelling in your ankles or legs, headache, dizziness, flushing, tiredness and nausea are the most common. Many are mild. Call your doctor if they bother you or don't ease.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nifedipine — tap one for details:
Nifedipine may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3961 | $39.61 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68382-0689-01 You're viewing this Main listing | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2018-08-18 | — | Active |
| 68382-0689-10 68382-689-10 | 1000 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2018-08-18 | — | Active |
| 68382-0689-16 68382-689-16 | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2018-08-18 | — | Active |
| 68382-0689-77 68382-689-77 | 10 BLISTER PACK in 1 CARTON / 10 TABLET, EXTENDED RELEASE in 1 BLISTER PACK | 2018-08-18 | — | Active |
| 68382-0689-95 68382-689-95 | 300 TABLET, EXTENDED RELEASE in 1 BOTTLE | 2018-08-18 | — | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 68382-0689-16?
What NDC number is used to bill for this package of Nifedipine 60 mg Tablet, Extended Release?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nifedipine 60 mg 68682-0106-10 | Oceanside | 100 tablets | $0.128 | AB1 | FDA listed | — |
| Nifedipine 60 mg 50742-0621-01 | Ingenus | 100 tablets | $0.163 | AB1 | Availability likely | — |
| Nifedipine 60 mg 59651-0296-01 | Aurobindo | 100 tablets | $0.163 | AB1 | Availability likely | — |
| Nifedipine 60 mg 62175-0261-37 | Lannett | 100 tablets | $0.168 | AB2 | Availability likely | — |
| Nifedipine ER 60 mg 50268-0598-15 | AvPAK | 1 tablet | $0.168 | AB2 | Availability likely | — |
| Nifedipine 60 mg 50742-0261-01 | Ingenus | 100 tablets | $0.168 | AB2 | Availability likely | — |
| Nifedipine 60 mg 00904-7081-06 | Major | 1 tablet | $0.168 | AB2 | Availability likely | — |
| Nifedipine 60 mg 24979-0010-12 | Upsher-Smith | 300 tablets | $0.168 | AB2 | Availability likely | — |
| Nifedipine 60 mg 62135-0522-90 | Chartwell | 90 tablets | $0.168 | AB2 | Availability likely | — |
| Nifedipine 60 mg 68084-0598-01 | American | 1 tablet | $0.168 | AB2 | Availability likely | — |
| Nifedipine 60 mg 67877-0758-01 | Ascend | 100 tablets | $0.168 | AB2 | Availability likely | — |
| nifedipine 60 mg 68682-0109-10 | Oceanside | 100 tablets | $0.170 | AB2 | FDA listed | — |
| Nifedipine 60 mg 51407-0623-01 | Golden | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mg 51655-0780-52 | Northwind | 30 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mgthis 68382-0689-01 | Zydus | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mg 70771-1366-00 | Zydus | 1000 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mg 71610-0012-16 | Aphena | 6000 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mg 72162-2260-01 | Bryant | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mg 72162-2535-01 | Bryant | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 60 mg 62332-0733-31 | Alembic | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 71205-0412-30 | Proficient | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 71205-0964-00 | Proficient | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 46708-0733-31 | Alembic | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 50090-6767-00 | A-S | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 50090-6201-00 | A-S | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 51655-0386-52 | Northwind | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 55154-4157-00 | Cardinal | 1 tablet | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 60429-0048-01 | Golden | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 70518-3520-00 | REMEDYREPACK | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 70771-1191-00 | Zydus | 1000 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 68788-8164-01 | Preferred | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 71335-1721-01 | Bryant | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 00615-8549-39 | NCS | 30 tablets | — | AB2 | FDA listed | — |
| nifedipine 60 mg 71335-0744-01 | Bryant | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 72789-0494-90 | PD-Rx | 90 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 72789-0485-01 | PD-Rx | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 55154-8177-00 | Cardinal | 1 tablet | — | AB2 | FDA listed | — |
| Procardia XL 60 mg 00069-2660-41 | Pfizer | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 60760-0859-90 | St. | 90 tablets | — | AB2 | FDA listed | — |
| Nifedipine 60 mg 68382-0686-01 | Zydus | 100 tablets | — | AB2 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII U3JF91U133
Hydroxypropyl cellulose is a plant-derived polymer that acts as a binder, thickener, and film-former in medications. It helps hold tablet ingredients together, control how quickly the drug dissolves, and create protective coatings on pills.
-
UNII UKE75GEA7F
Hydroxypropyl cellulose is a plant-based polymer used as a binder and thickener. It helps hold tablet ingredients together, controls how fast the medicine dissolves, and improves the texture of liquid formulations.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Nifedipine extended-release tablets are indicated for the treatment of hypertension. It may be used alone or in combination with other antihypertensive agents.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Dosage should be adjusted according to each patient's needs. It is recommended that nifedipine extended-release tablets be administered orally once daily on an empty stomach. Nifedipine extended-release tablets are an extended release dosage form and tablets should be swallowed whole, not bitten or divided.
In general, titration should proceed over a 7-14 day period starting with 30 mg once daily. Upward titration should be based on therapeutic efficacy and safety. The usual maintenance dose is 30 mg to 60 mg once daily.
Titration to doses above 90 mg daily is not recommended. If discontinuation of nifedipine extended-release tablets is necessary, sound clinical practice suggests that the dosage should be decreased gradually with close physician supervision. Co-administration of nifedipine with grapefruit juice is to be avoided (See CLINICAL PHARMACOLOGY and PRECAUTIONS ).
Care should be taken when dispensing nifedipine extended-release tablets to assure that the extended release dosage form has been prescribed.
⛔ Contraindications ▾
CONTRAINDICATIONS Concomitant administration with strong P450 inducers, such as rifampin, are contraindicated since the efficacy of nifedipine tablets could be significantly reduced. (See PRECAUTIONS, Drug Interactions . ) Nifedipine must not be used in cases of cardiogenic shock. Nifedipine is contraindicated in patients with a known hypersensitivity to any component of the tablet.
⚠️ Warnings ▾
WARNINGS Excessive Hypotension Although in most patients the hypotensive effect of nifedipine is modest and well tolerated, occasional patients have had excessive and poorly tolerated hypotension. These responses have usually occurred during initial titration or at the time of subsequent upward dosage adjustment, and may be more likely in patients using concomitant beta-blockers. Severe hypotension and/or increased fluid volume requirements have been reported in patients who received immediate release capsules together with a beta-blocking agent and who underwent coronary artery bypass surgery using high dose fentanyl anesthesia.
The interaction with high dose fentanyl appears to be due to the combination of nifedipine and a beta-blocker, but the possibility that it may occur with nifedipine alone, with low doses of fentanyl, in other surgical procedures, or with other narcotic analgesics cannot be ruled out. In nifedipine-treated patients where surgery using high dose fentanyl anesthesia is contemplated, the physician should be aware of these potential problems and, if the patient's condition permits, sufficient time (at least 36 hours) should be allowed for nifedipine to be washed out of the body prior to surgery.
Increased Angina and/or Myocardial Infarction Rarely, patients, particularly those who have severe obstructive coronary artery disease, have developed well-documented increased frequency, duration and/or severity of angina or acute myocardial infarction upon starting nifedipine or at the time of dosage increase. The mechanism of this effect is not established. Beta-Blocker Withdrawal When discontinuing a beta-blocker it is important to taper its dose, if possible, rather than stopping abruptly before beginning nifedipine.
Patients recently withdrawn from beta blockers may develop a withdrawal syndrome with increased angina, probably related to increased sensitivity to catecholamines. Initiation of nifedipine treatment will not prevent this occurrence and on occasion has been reported to increase it. Congestive Heart Failure Rarely, patients (usually while receiving a beta-blocker) have developed heart failure after beginning nifedipine.
Patients with tight aortic stenosis may be at greater risk for such an event, as the unloading effect of nifedipine would be expected to be of less benefit to these patients, owing to their fixed impedance to flow across the aortic valve.
🤒 Adverse Reactions ▾
ADVERSE EXPERIENCES The incidence of adverse events during treatment with nifedipine extended-release tablets in doses up to 90 mg daily were derived from multi-center placebo-controlled clinical trials in 370 hypertensive patients. Atenolol 50 mg once daily was used concomitantly in 187 of the 370 patients on nifedipine extended-release tablets and in 64 of the 126 patients on placebo. All adverse events reported during nifedipine extended-release tablets therapy were tabulated independently of their causal relationship to medication.
The most common adverse event reported with nifedipine extended-release tablets was peripheral edema. This was dose related and the frequency was 18% on nifedipine extended-release tablets 30 mg daily, 22% on nifedipine extended-release tablets 60 mg daily and 29% on nifedipine extended-release tablets 90 mg daily versus 10% on placebo. Other common adverse events reported in the above placebo-controlled trials include: Adverse Event Nifedipine extended - release tablets (%) ( n = 370 ) PLACEBO (%) ( n = 126 ) Headache 19 13 Flushing/heat sensation Dizziness 4 4 0 2 Fatigue/asthenia Nausea 4 2 4 1 Constipation 1 0 Where the frequency of adverse events with nifedipine extended-release tablets and placebo is similar, causal relationship cannot be established.
The following adverse events were reported with an incidence of 3% or less in daily doses up to 90 mg: Body as a Whole/Systemic: chest pain, leg pain Central Nervous System: paresthesia, vertigo Dermatologic: rash Gastrointestinal: constipation Musculoskeletal: leg cramps Respiratory: epistaxis, rhinitis Urogenital: impotence, urinary frequency Other adverse events reported with an incidence of less than 1.0% were: Body as a Whole/Systemic: allergic reaction, asthenia, cellulitis, substernal chest pain, chills, facial edema, lab test abnormal, malaise, neck pain, pelvic pain, pain, photosensitivity reaction Cardiovascular: atrial fibrillation, bradycardia, cardiac arrest, extrasystole, hypotension, migraine, palpitations, phlebitis, postural hypotension, tachycardia, cutaneous angiectases Central Nervous System: anxiety, confusion, decreased libido, depression, hypertonia, hypesthesia, insomnia, somnolence Dermatologic: angioedema, petechial rash, pruritus, sweating Gastrointestinal: abdominal pain, diarrhea, dry mouth, dysphagia, dyspepsia, eructation, esophagitis, flatulence, gastrointestinal disorder, gastrointestinal hemorrhage, GGT increased, gum disorder, gum hemorrhage, vomiting Hematologic: eosinophilia, lymphadenopathy Metabolic: gout, weight loss Musculoskeletal: arthralgia, arthritis, joint disorder, myalgia, myasthenia Respiratory: dyspnea, increased cough, rales, pharyngitis, stridor Special Senses: abnormal vision, amblyopia, conjunctivitis, diplopia, eye disorder, eye hemorrhage, tinnitus Urogenital/Reproductive: dysuria, kidney calculus, nocturia, breast engorgement, polyuria, urogenital disorder, erectile dysfunction (ED) The following adverse events have been reported rarely in patients given nifedipine in coat core or other formulations: allergenic hepatitis, alopecia, anaphylactic reaction, anemia, arthritis with ANA (+), depression, erythromelalgia, exfoliative dermatitis, fever, gingival hyperplasia, gynecomastia, hyperglycemia, jaundice, leukopenia, mood changes, muscle cramps, nervousness, paranoid syndrome, purpura, shakiness, sleep disturbances, Stevens-Johnson syndrome, syncope, taste perversion, thrombocytopenia, toxic epidermal necrolysis, transient blindness at the peak of plasma level, tremor and urticaria.
🔄 Drug Interactions ▾
Drug Interactions Nifedipine is mainly eliminated by metabolism and is a substrate of CYP3A. Inhibitors and inducers of CYP3A can impact the exposure to nifedipine and consequently its desirable and undesirable effects. In vitro and in vivo data indicate that nifedipine can inhibit the metabolism of drugs that are substrates of CYP3A, thereby increasing the exposure to other drugs.
Nifedipine is a vasodilator, and co-administration of other drugs affecting blood pressure may result in pharmacodynamic interactions. CYP3A inhibitors CYP3A inhibitors such as ketoconazole, fluconazole, itraconazole, clarithromycin, erythromycin (Azithromycin, although structurally related to the class of macrolide antibiotic is void of clinically relevant CYP3A4 inhibition), grapefruit, nefazodone, fluoxetine, saquinavir, indinavir, nelfinavir, and ritonavir may result in increased exposure to nifedipine when co-administered.
Careful monitoring and dose adjustment may be necessary; consider initiating nifedipine at the lowest dose available if given concomitantly with these medications. Strong CYP3A inducers Strong CYP3A inducers, such as rifampin, rifabutin, phenobarbital, phenytoin, carbamazepine, and St. John's Wort reduce the bioavailability and efficacy of nifedipine; therefore nifedipine should not be used in combination with strong CYP3A inducers such as rifampin (See CONTRAINDICATIONS ).
Cardiovascular Drugs Antiarrhythmics Quinidine: Quinidine is a substrate of CYP3A and has been shown to inhibit CYP3A in vitro . Co-administration of multiple doses of quinidine sulfate, 200 mg t.i.d., and nifedipine, 20 mg t.i.d., increased C max and AUC of nifedipine in healthy volunteers by factors of 2.30 and 1.37, respectively. The heart rate in the initial interval after drug administration was increased by up to 17.9 beats/minute.
The exposure to quinidine was not importantly changed in the presence of nifedipine. Monitoring of heart rate and adjustment of the nifedipine dose, if necessary, are recommended when quinidine is added to a treatment with nifedipine. Flecainide: There has been too little experience with the co-administration of Tambocor with nifedipine to recommend concomitant use.
Calcium Channel Blockers Diltiazem: Pre-treatment of healthy volunteers with 30 mg or 90 mg t.i.d. diltiazem p.o. increased the AUC of nifedipine after a single dose of 20 mg nifedipine by factors of 2.2 and 3.1, respectively. The corresponding Cmax values of nifedipine increased by factors of 2.0 and 1.7, respectively. Caution should be exercised when co-administering diltiazem and nifedipine and a reduction of the dose of nifedipine should be considered.
Verapamil: Verapamil, a CYP3A inhibitor, can inhibit the metabolism of nifedipine and increase the exposure to nifedipine during concomitant therapy. Blood pressure should be monitored and reduction of the dose of nifedipine considered. ACE Inhibitors Benazepril: In healthy volunteers receiving single dose of 20 mg nifedipine ER and benazepril 10 mg, the plasma concentrations of benazeprilat and nifedipine in the presence and absence of each other were not statistically significantly different.
A hypotensive effect was only seen after co-administration of the two drugs. The tachycardic effect of nifedipine was attenuated in the presence of benazepril. Angiotensin-II Blockers Irbesartan: In vitro studies show significant inhibition of the formation of oxidized irbesartan metabolites by nifedipine.
However, in clinical studies, concomitant nifedipine had no effect on irbesartan pharmacokinetics. Candesartan: No significant drug interaction has been reported in studies with candesartan cilexitil given together with nifedipine. Because candesartan is not significantly metabolized by the cytochrome P450 system and at therapeutic concentrations has no effect on cytochrome P450 enzymes, interactions with drugs that inhibit or are metabolized by those enzymes would not be expected.
Beta-blockers Nifedipine extended-r… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Pregnancy Category C. In rodents, rabbits and monkeys, nifedipine has been shown to have a variety of embryotoxic, placentotoxic, teratogenic and fetotoxic effects, including stunted fetuses (rats, mice and rabbits), digital anomalies (rats and rabbits), rib deformities (mice), cleft palate (mice), small placentas and underdeveloped chorionic villi (monkeys), embryonic and fetal deaths (rats, mice and rabbits), prolonged pregnancy (rats; not evaluated in other species), and decreased neonatal survival (rats; not evaluated in other species).
On a mg/kg or mg/m2 basis, some of the doses associated with these various effects are higher than the maximum recommended human dose and some are lower, but all are within an order of magnitude of it. The digital anomalies seen in nifedipine-exposed rabbit pups are strikingly similar to those seen in pups exposed to phenytoin, and these are in turn similar to the phalangeal deformities that are the most common malformation seen in human children with in utero exposure to phenytoin. From the clinical evidence available, a specific prenatal risk has not been identified.
However, an increase in perinatal asphyxia, caesarean delivery, prematurity and intrauterine growth retardation have been reported. Careful monitoring of blood pressure must be exercised in pregnant women, when administering nifedipine in combination with IV magnesium sulfate due to the possibility of an excessive fall in blood pressure which could harm the mother and fetus. There are no adequate and well-controlled studies in pregnant women.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of nifedipine extended-release tablets in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Although small pharmacokinetic studies have identified an increased half-life and increased Cmax and AUC (See CLINICAL PHARMACOLOGY: Pharmacokinetics and Metabolism ), clinical studies of nifedipine did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE Experience with nifedipine overdosage is limited. Symptoms associated with severe nifedipine overdosage include loss of consciousness, drop in blood pressure, heart rhythm disturbances, metabolic acidosis, hypoxia, cardiogenic shock with pulmonary edema. Generally, overdosage with nifedipine leading to pronounced hypotension calls for active cardiovascular support including monitoring of cardiovascular and respiratory function, elevation of extremities, judicious use of calcium infusion, pressor agents and fluids.
After oral ingestion, thorough gastric lavage is indicated, if necessary in combination with irrigation of the small intestine. In cases involving overdosage of a slow-release product like nifedipine, elimination must be as complete as possible, including from the small intestine, to prevent the subsequent absorption of the active substance. Additional liquid or volume must be administered with caution because of the risk of fluid overload.
Clearance of nifedipine would be expected to be prolonged in patients with impaired liver function. Since nifedipine is highly protein bound, dialysis is not likely to be of any benefit; however, plasmapheresis may be beneficial. There has been one reported case of massive overdosage with tablets of another extended release formulation of nifedipine.
The main effects of ingestion of approximately 4800 mg of nifedipine in a young man attempting suicide as a result of cocaine-induced depression was initial dizziness, palpitations, flushing, and nervousness. Within several hours of ingestion, nausea, vomiting, and generalized edema developed. No significant hypotension was apparent at presentation, 18 hours post ingestion.
Blood chemistry abnormalities consisted of a mild, transient elevation of serum creatinine, and modest elevations of LDH and CPK, but normal SGOT. Vital signs remained stable, no electrocardiographic abnormalities were noted and renal function returned to normal within 24 to 48 hours with routine supportive measures alone. No prolonged sequelae were observed.
The effect of a single 900 mg ingestion of nifedipine capsules in a depressed anginal patient on tricyclic antidepressants was loss of consciousness within 30 minutes of ingestion, and profound hypotension, which responded to calcium infusion, pressor agents, and fluid replacement. A variety of ECG abnormalities were seen in this patient with a history of bundle branch block, including sinus bradycardia and varying degrees of AV block. These dictated the prophylactic placement of a temporary ventricular pacemaker, but otherwise resolved spontaneously.
Significant hyperglycemia was seen initially in this patient, but plasma glucose levels rapidly normalized without further treatment. A young hypertensive patient with advanced renal failure ingested 280 mg of nifedipine capsules at one time, with resulting marked hypotension responding to calcium infusion and fluids. No AV conduction abnormalities, arrhythmias, or pronounced changes in heart rate were noted, nor was there any further deterioration in renal function.
Bradycardiac heart rhythm disturbances may be treated symptomatically with β-sympathomimetics, and in life-threatening bradycardiac disturbances of heart rhythm temporary pacemaker therapy can be advisable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Nifedipine is a calcium ion influx inhibitor (slow-channel blocker or calcium ion antagonist) which inhibits the transmembrane influx of calcium ions into vascular smooth muscle and cardiac muscle. The contractile processes of vascular smooth muscle and cardiac muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Nifedipine selectively inhibits calcium ion influx across the cell membrane of vascular smooth muscle and cardiac muscle without altering serum calcium concentrations.
Mechanism of Action The mechanism by which nifedipine reduces arterial blood pressure involves peripheral arterial vasodilatation and, consequently, a reduction in peripheral vascular resistance. The increased peripheral vascular resistance, an underlying cause of hypertension, results from an increase in active tension in the vascular smooth muscle. Studies have demonstrated that the increase in active tension reflects an increase in cytosolic free calcium.
Nifedipine is a peripheral arterial vasodilator which acts directly on vascular smooth muscle. The binding of nifedipine to voltage-dependent and possibly receptor-operated channels in vascular smooth muscle results in an inhibition of calcium influx through these channels. Stores of intracellular calcium in vascular smooth muscle are limited and thus dependent upon the influx of extracellular calcium for contraction to occur.
The reduction in calcium influx by nifedipine causes arterial vasodilation and decreased peripheral vascular resistance which results in reduced arterial blood pressure. Pharmacokinetics and Metabolism Nifedipine is completely absorbed after oral administration. The bioavailability of nifedipine as nifedipine extended-release tablets relative to immediate release nifedipine is in the range of 84%-89%.
After ingestion of nifedipine extended-release tablets under fasting conditions, plasma concentrations peak at about 2.5-5 hours with a second small peak or shoulder evident at approximately 6-12 hours post dose. The elimination half-life of nifedipine administered as nifedipine extended-release tablets is approximately 7 hours in contrast to the known 2 hour elimination half-life of nifedipine administered as an immediate release capsule. When nifedipine extended-release tablets are administered as multiples of 30 mg tablets over a dose range of 30 mg to 90 mg, the area under the curve (AUC) is dose proportional; however, the peak plasma concentration for the 90 mg dose given as 3 × 30 mg is 29% greater than predicted from the 30 mg and 60 mg doses.
Two 30 mg nifedipine extended-release tablets may be interchanged with a 60 mg nifedipine extended-release tablets. Three 30 mg nifedipine extended-release tablets, however, result in substantially higher C max values than those after a single 90 mg nifedipine extended-release tablets. Three 30 mg tablets should, therefore, not be considered interchangeable with a 90 mg tablet.
Once daily dosing of nifedipine extended-release tablets under fasting conditions results in decreased fluctuations in the plasma concentration of nifedipine when compared to t.i.d. dosing with immediate release nifedipine capsules. The mean peak plasma concentration of nifedipine following a 90 mg nifedipine extended-release tablet, administered under fasting conditions, is approximately115 ng/mL. When nifedipine extended-release tablets are given immediately after a high fat meal in healthy volunteers, there is an average increase of 60% in the peak plasma nifedipine concentration, a prolongation in the time to peak concentration, but no significant change in the AUC.
Plasma concentrations of nifedipine when nifedipine extended-release tablets are taken after a fatty meal result in slightly lower peaks compared to the same daily dose of the immediate release formulation administered in three divided doses. This may be, in part, because nifedipine extended-release tablets ar… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action The mechanism by which nifedipine reduces arterial blood pressure involves peripheral arterial vasodilatation and, consequently, a reduction in peripheral vascular resistance. The increased peripheral vascular resistance, an underlying cause of hypertension, results from an increase in active tension in the vascular smooth muscle. Studies have demonstrated that the increase in active tension reflects an increase in cytosolic free calcium.
Nifedipine is a peripheral arterial vasodilator which acts directly on vascular smooth muscle. The binding of nifedipine to voltage-dependent and possibly receptor-operated channels in vascular smooth muscle results in an inhibition of calcium influx through these channels. Stores of intracellular calcium in vascular smooth muscle are limited and thus dependent upon the influx of extracellular calcium for contraction to occur.
The reduction in calcium influx by nifedipine causes arterial vasodilation and decreased peripheral vascular resistance which results in reduced arterial blood pressure.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Nifedipine Extended-Release Tablets, USP 30 mg are Light pink to pink, round, biconvex, film-coated tablets debossed with '688' on one side and plain on the other side and are supplied as follows: NDC 68382-688-16 in bottle of 90 tablets NDC 68382-688-01 in bottle of 100 tablets NDC 68382-688-95 in bottle of 300 tablets NDC 68382-688-05 in bottle of 500 tablets NDC 68382-688-10 in bottle of 1000 tablets NDC 68382-688-77 in unit-dose blister cartons of 100 tablets (10 X 10 Unit-dose) Nifedipine Extended-Release Tablets, USP 60 mg are Light yellow to yellow, round, biconvex, film- coated tablets debossed with '689' on one side and plain on the other side and are supplied as follows: NDC 68382-689-16 in bottle of 90 tablets NDC 68382-689-01 in bottle of 100 tablets NDC 68382-689-95 in bottle of 300 tablets NDC 68382-689-10 in bottle of 1000 tablets NDC 68382-689-77 in unit-dose blister cartons of 100 tablets (10 X 10 Unit-dose) Nifedipine Extended-Release Tablets, USP 90 mg are Light brown to brown, round, biconvex, film-coated tablets debossed with '690' on one side and plain on the other side and are supplied as follows: NDC 68382-690-16 in bottle of 90 tablets NDC 68382-690-01 in bottle of 100 tablets NDC 68382-690-95 in bottle of 300 tablets NDC 68382-690-10 in bottle of 1000 tablets NDC 68382-690-77 in unit-dose blister cartons of 100 tablets (10 X 10 Unit-dose) The tablets should be protected from light and moisture and Store at 20° to 25°C (68° to 77°F).
Dispense in tight, light-resistant containers. Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088.
📋 Description ▾
DESCRIPTION Nifedipine extended-release tablet, USP is an extended release tablet dosage form of the calcium channel blocker nifedipine. Nifedipine is 3,5-pyridinedicarboxylic acid, 1,4-dihydro-2,6-dimethyl-4-(2-nitrophenyl)-dimethyl ester, C 17 H 18 N 2 O 6 , and has the structural formula: Nifedipine USP is a yellow crystalline substance, practically insoluble in water but soluble in ethanol. It has a molecular weight of 346.3.
Nifedipine extended-release tablets consist of an external coat and an internal core. Both contain nifedipine, the coat as a slow release formulation and the core as a fast release formulation. Nifedipine extended-release tablets contain either: 30, 60, or 90 mg of nifedipine for once-a-day oral administration.
Inert ingredients in the formulation are hydroxypropylcellulose, lactose monohydrate, pregelatinized Starch, crospovidone, microcrystalline cellulose, colloidal silicon dioxide, magnesium stearate. The inert ingredients in the film coating for nifedipine extended-release tablets 30 mg and 60 mg are: hypromellose, titanium dioxide, polyethylene glycol, iron oxide yellow and iron oxide red. The inert ingredients in the film coating for nifedipine extended-release tablets 90 mg are hypromellose, titanium dioxide, polyethylene glycol, iron oxide yellow, iron oxide red and ferrosoferic oxide.
USP Dissolution Test pending. structure
💬 Information for Patients ▾
Information for Patients Nifedipine extended-release tablets are extended release tablet and should be swallowed whole and taken on an empty stomach. It should not be administered with food. Do not chew, divide or crush tablets.
⚠️ Precautions ▾
PRECAUTIONS General Hypotension Because nifedipine decreases peripheral vascular resistance, careful monitoring of blood pressure during the initial administration and titration of nifedipine extended-release tablets is suggested. Close observation is especially recommended for patients already taking medications that are known to lower blood pressure (See WARNINGS ). Peripheral Edema Mild to moderate peripheral edema occurs in a dose-dependent manner with nifedipine extended-release tablets.
The placebo subtracted rate is approximately 8% at 30 mg, 12% at 60 mg and 19% at 90 mg daily. This edema is a localized phenomenon, thought to be associated with vasodilation of dependent arterioles and small blood vessels and not due to left ventricular dysfunction or generalized fluid retention. With patients whose hypertension is complicated by congestive heart failure, care should be taken to differentiate this peripheral edema from the effects of increasing left ventricular dysfunction.
Use in Cirrhotic Patients Clearance of nifedipine is reduced and systemic exposure increased in patients with cirrhosis. It is unknown how systemic exposure may be altered in patients with moderate or severe liver impairment. Careful monitoring and dose reduction may be necessary; consider initiating therapy with the lowest dose available.
Information for Patients Nifedipine extended-release tablets are extended release tablet and should be swallowed whole and taken on an empty stomach. It should not be administered with food. Do not chew, divide or crush tablets.
Laboratory Tests Rare, usually transient, but occasionally significant elevations of enzymes such as alkaline phosphatase, CPK, LDH, SGOT, and SGPT have been noted. The relationship to nifedipine therapy is uncertain in most cases, but probable in some. These laboratory abnormalities have rarely been associated with clinical symptoms; however, cholestasis with or without jaundice has been reported.
A small increase (<5%) in mean alkaline phosphatase was noted in patients treated with nifedipine extended-release tablets. This was an isolated finding and it rarely resulted in values which fell outside the normal range. Rare instances of allergic hepatitis have been reported with nifedipine treatment.
In controlled studies, nifedipine extended-release tablets did not adversely affect serum uric acid, glucose, cholesterol or potassium. Nifedipine, like other calcium channel blockers, decreases platelet aggregation in vitro . Limited clinical studies have demonstrated a moderate but statistically significant decrease in platelet aggregation and increase in bleeding time in some nifedipine patients.
This is thought to be a function of inhibition of calcium transport across the platelet membrane. No clinical significance for these findings has been demonstrated. Positive direct Coombs' test with or without hemolytic anemia has been reported but a causal relationship between nifedipine administration and positivity of this laboratory test, including hemolysis, could not be determined.
Although nifedipine has been used safely in patients with renal dysfunction and has been reported to exert a beneficial effect in certain cases, rare reversible elevations in BUN and serum creatinine have been reported in patients with pre-existing chronic renal insufficiency. The relationship to nifedipine therapy is uncertain in most cases but probable in some. Drug Interactions Nifedipine is mainly eliminated by metabolism and is a substrate of CYP3A.
Inhibitors and inducers of CYP3A can impact the exposure to nifedipine and consequently its desirable and undesirable effects. In vitro and in vivo data indicate that nifedipine can inhibit the metabolism of drugs that are substrates of CYP3A, thereby increasing the exposure to other drugs. Nifedipine is a vasodilator, and co-administration of other drugs affecting blood pressure may result in pharmacodynamic interactions.
CYP3A inhibitors CYP3A inhibitors such as ket… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Nifedipine is excreted in human milk. Nursing mothers are advised not to breastfeed their babies when taking the drug.
🔬 Clinical Studies ▾
Clinical Studies Nifedipine extended-release tablets produced dose-related decreases in systolic and diastolic blood pressure as demonstrated in two double-blind, randomized, placebo-controlled trials in which over 350 patients were treated with nifedipine extended-release tablets 30, 60 or 90 mg once daily for 6 weeks. In the first study, nifedipine extended-release tablets were given as monotherapy and in the second study, nifedipine extended-release tablets were added to a beta-blocker in patients not controlled on a beta-blocker alone.
The mean trough (24 hours post-dose) blood pressure results from these studies are shown below: MEAN REDUCTIONS IN TROUGH SUPINE BLOOD PRESSURE (mmHg) * Placebo response subtracted. SYSTOLIC / DIASTOLIC STUDY 1 Nifedipine extended-release tablets N MEAN TROUGH DOSE REDUCTION * 30 MG 60 5.3/2.9 60 MG 57 8.0/4.1 90 MG 55 12.5/8.1 STUDY 2 Nifedipine extended-release tablets N MEAN TROUGH DOSE REDUCTION * 30 MG 58 7.6/3.8 60 MG 63 10.1/5.3 90 MG 52 10.2/5.8 The trough/peak ratios estimated from 24 hour blood pressure monitoring ranged from 41%-78% for diastolic and 46%-91% for systolic blood pressure.
Hemodynamics Like other slow-channel blockers, nifedipine exerts a negative inotropic effect on isolated myocardial tissue. This is rarely, if ever, seen in intact animals or man, probably because of reflex responses to its vasodilating effects. In man, nifedipine decreases peripheral vascular resistance which leads to a fall in systolic and diastolic pressures, usually minimal in normotensive volunteers (less than 5-10 mm Hg systolic), but sometimes larger.
With nifedipine extended-release tablets, these decreases in blood pressure are not accompanied by any significant change in heart rate. Hemodynamic studies of the immediate release nifedipine formulation in patients with normal ventricular function have generally found a small increase in cardiac index without major effects on ejection fraction, left ventricular end-diastolic pressure (LVEDP) or volume (LVEDV). In patients with impaired ventricular function, most acute studies have shown some increase in ejection fraction and reduction in left ventricular filling pressure.
Electrophysiologic Effects Although, like other members of its class, nifedipine causes a slight depression of sinoatrial node function and atrioventricular conduction in isolated myocardial preparations, such effects have not been seen in studies in intact animals or in man. In formal electrophysiologic studies, predominantly in patients with normal conduction systems, nifedipine administered as the immediate release capsule has had no tendency to prolong atrioventricular conduction or sinus node recovery time, or to slow sinus rate.
📄 Package Label / Principal Display Panel ▾
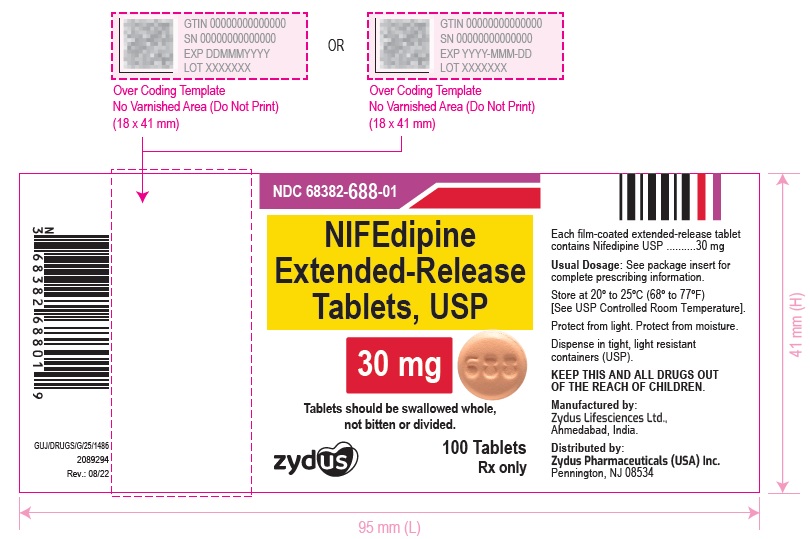
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 68382-688-01 in bottles of 100 tablets Nifedipine Extended-Release Tablets, USP 30 mg 100 Tablets Zydus Rx only NDC 68382-688-77 in carton of 100 Tablets (10 X 10 Unit-dose) Nifedipine Extended-Release Tablets, USP 30 mg 100 Tablets Zydus Rx only NDC 68382-689-01 in bottles of 100 tablets Nifedipine Extended-Release Tablets, USP 60 mg 100 Tablets Zydus Rx only NDC 68382-689-77 in carton of 100 Tablets (10 X 10 Unit-dose) Nifedipine Extended-Release Tablets, USP 60 mg 100 Tablets Zydus Rx only NDC 68382-690-01 in bottles of 100 tablets Nifedipine Extended-Release Tablets, USP 90 mg 100 Tablets Zydus Rx only NDC 68382-690-77 in carton of 100 Tablets (10 X 10 Unit-dose) Nifedipine Extended-Release Tablets, USP 90 mg 100 Tablets Zydus Rx only Container Label 30 mg Carton Label 30 mg Container Label 60 mg Carton Label 60 mg Container Label 90 mg Carton Label 90 mg
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |