
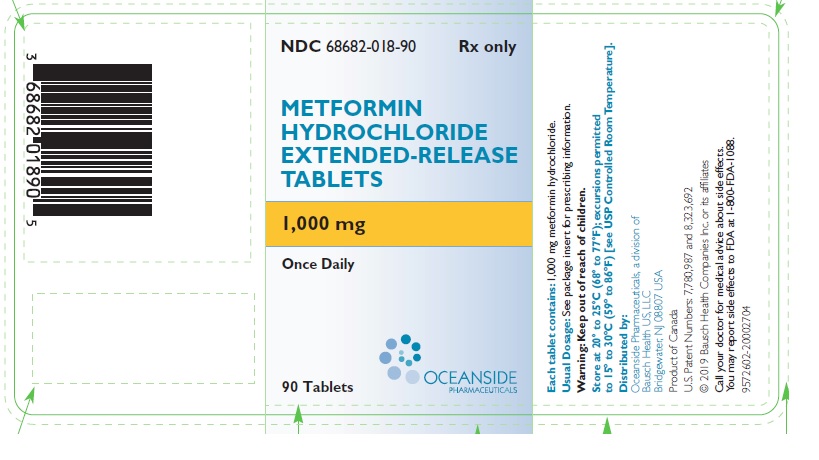
Metformin hydrochloride 1000 mg Tablet, Film Coated, Extended Release, 90-count
Other active recalls for Metformin Hydrochloride (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Biguanide class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Metformin is used alone or with other medications, including insulin, to treat type 2 diabetes (condition in which the body does not use insulin normally and, therefore, cannot control the amount of sugar in the blood). Metformin is in a class of drugs called biguanides. Metformin helps to control the amount of glucose (sugar) in your blood. It decreases the amount of glucose you absorb from your food and the amount of glucose made by your liver. Metformin also increases your body's response to insulin, a natural substance that controls the amount of glucose in the blood. Metformin is not used...
Read the full MedlinePlus article ↗- Metformin works in three ways: it lowers the amount of sugar your liver dumps into your bloodstream, slows how much sugar your gut absorbs from food, and helps your body respond to...
- What exactly is metformin doing for my diabetes?
- Yes, this is very common — diarrhea, nausea, and stomach discomfort are the most frequently reported side effects, and they're often worst when you first start or when your dose go...
- My stomach has been a mess since I started metformin. Is that normal? Will it get better?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Metformin Hydrochloride — tap one for details:
Metformin Hydrochloride may be associated with lower levels of 4 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII R8WTH25YS2
Glyceryl dibehenate is a wax-like substance made from behenate fatty acids and glycerol. It functions as a binder and release-control agent in tablets and capsules, helping hold ingredients together and regulate how quickly the medicine dissolves and releases in your body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.193 | $197.38 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.53 | $407.63 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Metformin hydrochloride 1000 mg 27241-0189-60 | Ajanta | 60 tablets | $0.326 | AB2 | Availability likely | save 85% |
| Metformin Hydrochloride 1000 mg 59651-0043-60 | Aurobindo | 60 tablets | $0.326 | AB2 | Availability likely | save 85% |
| Metformin Hydrochloride 1000 mg 69367-0413-60 | Westminster | 60 tablets | $0.326 | AB2 | Availability likely | save 85% |
| Metformin hydrochloride 1000 mg 27241-0241-90 | Ajanta | 90 tablets | $0.334 | AB3 | Availability likely | save 85% |
| Metformin Hydrochloride 1000 mg 70010-0497-09 | Granules | 90 tablets | $0.334 | AB3 | Availability likely | save 85% |
| Metformin hydrochloride 1000 mgthis 68682-0018-90 | Oceanside | 90 tablets | $2.193 | — | FDA listed | — |
| Metformin Hydrochloride 1000 mg 33342-0378-10 | Macleods | 90 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 1000 mg 42571-0334-01 | Micro | 100 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 43547-0504-09 | Solco | 90 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 47335-0306-18 | Sun | 1000 tablets | — | — | Discontinued | — |
| Metformin Hydrochloride 1000 mg 50228-0446-05 | ScieGen | 500 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 62207-0497-47 | Granules | 500 tablets | — | AB3 | FDA listed | — |
| Glumetza 1000 mg 68012-0003-16 | Santarus, | 90 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 1000 mg 68180-0339-01 | Lupin | 100 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 68462-0521-01 | GLENMARK | 100 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 70518-4677-00 | REMEDYREPACK | 90 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 72664-0228-90 | VGYAAN | 90 tablets | — | — | FDA listed | — |
| Metformin hydrochloride 1000 mg 70518-4652-00 | REMEDYREPACK | 1 tablet | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 51407-0059-60 | Golden | 60 tablets | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 68180-0337-01 | Lupin | 100 tablets | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 63629-5934-01 | Bryant | 30 tablets | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 68788-8520-06 | Preferred | 60 tablets | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 70518-4369-00 | REMEDYREPACK | 1 tablet | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 1000 mg 70518-4710-00 | REMEDYREPACK | 1 tablet | — | AB2 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68682-0018-90 You're viewing this | 90 TABLET, FILM COATED, EXTENDED RELEASE in 1 BOTTLE (68682-018-90) | 2008-06-17 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LACTIC ACIDOSIS Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. The onset of metformin-associated lactic acidosis is often subtle, accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Metformin-associated lactic acidosis was characterized by elevated blood lactate levels (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), an increased lactate/pyruvate ratio, and metformin plasma levels generally >5 mcg/mL [see Warnings and Precautions ( 5.1 )] .
Risk factors for metformin-associated lactic acidosis include renal impairment, concomitant use of certain drugs (e.g., carbonic anhydrase inhibitors such as topiramate), age 65 years old or greater, having a radiological study with contrast, surgery and other procedures, hypoxic states (e.g., acute congestive heart failure), excessive alcohol intake, and hepatic impairment. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the full prescribing information [see Dosage and Administration ( 2.2 ), Contraindications ( 4 ), Warnings and Precautions ( 5.1 ), and Drug Interactions ( 7 )] .
If metformin-associated lactic acidosis is suspected, immediately discontinue Metformin Hydrochloride Extended-Release Tablets and institute general supportive measures in a hospital setting. Prompt hemodialysis is recommended [see Warnings and Precautions ( 5.1 ) ] . WARNING: LACTIC ACIDOSIS See full prescribing information for complete boxed warning.
Postmarketing cases of metformin-associated lactic acidosis have resulted in death, hypothermia, hypotension, and resistant bradyarrhythmias. Symptoms included malaise, myalgias, respiratory distress, somnolence, and abdominal pain. Laboratory abnormalities included elevated blood lactate levels, anion gap acidosis, increased lactate/pyruvate ratio; and metformin plasma levels generally >5 mcg/mL.
( 5.1 ) Risk factors include renal impairment, concomitant use of certain drugs, age ≥65 years old, radiological studies with contrast, surgery and other procedures, hypoxic states, excessive alcohol intake, and hepatic impairment. Steps to reduce the risk of and manage metformin-associated lactic acidosis in these high risk groups are provided in the Full Prescribing Information. ( 5.1 ) If lactic acidosis is suspected, discontinue Metformin Hydrochloride Extended-Release Tablets and institute general supportive measures in a hospital setting.
Prompt hemodialysis is recommended. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Metformin Hydrochloride Extended-Release Tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. Metformin Hydrochloride Extended-Release Tablets are a biguanide indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting dose: 500 mg orally once daily with the evening meal ( 2.1 ) Increase the dose in increments of 500 mg every 1 to 2 weeks, up to a maximum of 2,000 mg once daily with the evening meal. ( 2.1 ) Patients receiving metformin hydrochloride (HCl) tablets may be switched to Metformin Hydrochloride Extended-Release Tablets once daily at the same total daily dose, up to 2,000 mg once daily. ( 2.1 ) Swallow Metformin Hydrochloride Extended-Release Tablets whole and never crush, cut or chew.
( 2.1 ) Renal Impairment: Prior to initiation, assess renal function with estimated glomerular filtration rate (eGFR). ( 2.2 ) Do not use in patients with eGFR below 30 mL/minute/1.73 m 2 . Initiation is not recommended in patients with eGFR between 30 to 45 mL/minute/1.73 m 2 .
Assess risk/benefit of continuing Metformin Hydrochloride Extended-Release Tablets if eGFR falls below 45 mL/minute/1.73 m 2 . Discontinue if eGFR falls below 30 mL/minute/1.73 m 2 . Discontinuation for Iodinated Contrast Imaging Procedures: Metformin Hydrochloride Extended-Release Tablets may need to be discontinued at time of, or prior to, iodinated contrast imaging procedures.
( 2.3 )
2.1Adult Dosage and Administration The recommended starting dose of Metformin Hydrochloride Extended-Release Tablets is 500 mg orally once daily with the evening meal. Increase the dose in increments of 500 mg every 1 to 2 weeks on the basis of glycemic control and tolerability, up to a maximum of 2,000 mg once daily with the evening meal. Patients receiving metformin hydrochloride (HCl) may be switched to Metformin Hydrochloride Extended-Release Tablets once daily at the same total daily dose, up to 2,000 mg once daily.
Swallow Metformin Hydrochloride Extended-Release Tablets whole and never crush, cut or chew. If a dose of Metformin Hydrochloride Extended-Release Tablets is missed, instruct patients not to take two doses the same day and to resume their usual dose of Metformin Hydrochloride Extended-Release Tablets with the next schedule dose.
2.2Recommendations for Use in Renal Impairment Assess renal function prior to initiation of Metformin Hydrochloride Extended-Release Tablets and periodically thereafter. Metformin Hydrochloride Extended-Release Tablets are contraindicated in patients with an estimated glomerular filtration rate (eGFR) below 30 mL/minute/1.73 m 2 . Initiation of Metformin Hydrochloride Extended-Release Tablets in patients with an eGFR between 30 to 45 mL/minute/1.73 m 2 is not recommended.
In patients taking Metformin Hydrochloride Extended-Release Tablets whose eGFR later falls below 45 mL/minute/1.73 m 2 , assess the benefit risk of continuing therapy. Discontinue Metformin Hydrochloride Extended-Release Tablets if the patient’s eGFR later falls below 30 mL/minute/1.73 m 2 [see Contraindications ( 4 ) and Warnings and Precautions ( 5.1 )] .
2.3Discontinuation for Iodinated Contrast Imaging Procedures Discontinue Metformin Hydrochloride Extended-Release Tablets at the time of, or prior to, an iodinated contrast imaging procedure in patients with an eGFR between 30 and 60 mL/minute/1.73 m2; in patients with a history of liver disease, alcoholism or heart failure; or in patients who will be administered intra-arterial iodinated contrast. Re-evaluate eGFR 48 hours after the imaging procedure; restart Metformin Hydrochloride Extended-Release Tablets if renal function is stable [see Warnings and Precautions ( 5.1 )].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Metformin Hydrochloride Extended-Release Tablets are available as: Extended-release tablets: 500 mg white, film-coated, oval-shaped tablets with “M500” on one side. Extended-release tablets : 1,000 mg white, film-coated, oval-shaped tablets with “M1000” on one side. Metformin Hydrochloride Extended-Release Tablets: 500 mg and 1,000 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Metformin Hydrochloride Extended-Release Tablets are contraindicated in patients with: Severe renal impairment (eGFR below 30 mL/minute/1.73 m 2 ) [see Warnings and Precautions ( 5.1 )] . Known hypersensitivity to metformin. Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma.
Severe renal impairment: (eGFR below 30 mL/minute/1.73 m 2 ) ( 4 , 5.1 ) Known hypersensitivity to metformin ( 4 ) Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Lactic Acidosis : See boxed warning. ( 5.1 ) Vitamin B 12 Deficiency : Metformin may lower vitamin B 12 levels. Monitor hematological parameters annually and vitamin B 12 at 2 to 3 year intervals and manage any abnormalities.
( 5.2 ) Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues : Increased risk of hypoglycemia when used in combination with insulin and/or an insulin secretagogue. Lower dose of insulin or insulin secretagogue may be required. ( 5.3 )
5.1Lactic Acidosis There have been postmarketing cases of metformin-associated lactic acidosis, including fatal cases. These cases had a subtle onset and were accompanied by nonspecific symptoms such as malaise, myalgias, abdominal pain, respiratory distress, or increased somnolence; however, hypothermia, hypotension and resistant bradyarrhythmias have occurred with severe acidosis. Metformin-associated lactic acidosis was characterized by elevated blood lactate concentrations (>5 mmol/Liter), anion gap acidosis (without evidence of ketonuria or ketonemia), and an increased lactate/pyruvate ratio; metformin plasma levels were generally >5 mcg/mL.
Metformin decreases liver uptake of lactate increasing lactate blood levels which may increase the risk of lactic acidosis, especially in patients at risk. If metformin-associated lactic acidosis is suspected, general supportive measures should be instituted promptly in a hospital setting, along with immediate discontinuation of Metformin Hydrochloride Extended-Release Tablets. In Metformin Hydrochloride Extended-Release Tablets-treated patients with a diagnosis or strong suspicion of lactic acidosis, prompt hemodialysis is recommended to correct the acidosis and remove accumulated metformin (metformin HCl is dialyzable, with a clearance of up to 170 mL/minute under good hemodynamic conditions).
Hemodialysis has often resulted in reversal of symptoms and recovery. Educate patients and their families about the symptoms of lactic acidosis and if these symptoms occur, instruct them to discontinue Metformin Hydrochloride Extended-Release Tablets and report these symptoms to their healthcare provider. For each of the known and possible risk factors for metformin-associated lactic acidosis, recommendations to reduce the risk of and manage metformin-associated lactic acidosis are provided below: Renal Impairment: The postmarketing metformin-associated lactic acidosis cases primarily occurred in patients with significant renal impairment.
The risk of metformin accumulation and metformin-associated lactic acidosis increases with the severity of renal impairment because metformin is substantially excreted by the kidney. Clinical recommendations based upon the patient’s renal function include [see Dosage and Administration ( 2.2 ) and Clinical Pharmacology ( 12.3 )]: Before initiating Metformin Hydrochloride Extended-Release Tablets, obtain an estimated glomerular filtration rate (eGFR). Metformin Hydrochloride Extended-Release Tablets are contraindicated in patients with an eGFR less than 30 mL/minute/1.73 m 2 [see Contraindications ( 4 )].
Initiation of Metformin Hydrochloride Extended-Release Tablets is not recommended in patients with eGFR between 30 to 45 mL/minute/1.73 m 2 . Obtain an eGFR at least annually in all patients taking Metformin Hydrochloride Extended-Release Tablets. In patients at increased risk for the development of renal impairment (e.g., the elderly), renal function should be assessed more frequently.
In patients taking Metformin Hydrochloride Extended-Release Tablets whose eGFR later falls below 45 mL/minute/1.73 m 2 , assess the benefit and risk of continuing therapy. Drug Interactions: The concomitant use of Metformin Hydrochloride Extended-Release Tablets with specific drugs may increase the risk of metformin-associated lactic acidosis: those that impair renal function, result in significant hemodynamic change, interfere with acid-base balance or increase metformin accu…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: Lactic Acidosis [see Boxed Warning and Warnings and Precautions ( 5.1 )] Vitamin B 12 Deficiency [see Warnings and Precautions ( 5.2 )] Hypoglycemia [see Warnings and Precautions ( 5.3 )] Adverse reactions occurring >5% in Metformin Hydrochloride Extended-Release Tablets clinical trials: hypoglycemia, diarrhea, and nausea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Oceanside Pharmaceuticals at 1-800-321-4576 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In clinical trials conducted in the U.S., over 1,000 patients with type 2 diabetes mellitus have been treated with Metformin Hydrochloride Extended-Release Tablets 1,500 to 2,000 mg/day in active-controlled and placebo-controlled studies with the 500 mg dosage form.
In the add-on to sulfonylurea study, patients receiving background glyburide therapy were randomized to receive add-on treatment of either one of three different regimens of Metformin Hydrochloride Extended-Release Tablets or placebo. In total, 431 patients received Metformin Hydrochloride Extended-Release Tablets and glyburide and 144 patients received placebo and glyburide. Adverse reactions reported in greater than 5% of patients treated with Metformin Hydrochloride Extended-Release Tablets that were more common in the combined Metformin Hydrochloride Extended-Release Tablets and glyburide group than in the placebo and glyburide group are shown in Table 1.
In 0.7% of patients treated with Metformin Hydrochloride Extended-Release Tablets and glyburide, diarrhea was responsible for discontinuation of study medication compared to no patients in the placebo and glyburide group. Table 1: Adverse Reactions Reported by >5% Adverse reactions that were more common in the Metformin Hydrochloride Extended-Release Tablets-treated than in the placebo-treated patients. of Patients for the Combined Metformin Hydrochloride Extended-Release Tablets Groups Versus Placebo Group Adverse Reaction Metformin Hydrochloride Extended-Release Tablets + Glyburide (n=431) Placebo + Glyburide (n=144) Hypoglycemia 14% 5% Diarrhea 13% 6% Nausea 7% 4% Laboratory Tests Vitamin B 12 Concentrations In clinical trials of 29-week duration with metformin HCl tablets, a decrease to subnormal levels of previously normal serum vitamin B 12 levels was observed in approximately 7% of patients.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of Metformin Hydrochloride Extended-Release Tablets. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Cholestatic, hepatocellular, and mixed hepatocellular liver injury have been reported with postmarketing use of metformin.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 2 presents clinically significant drug interactions with Metformin Hydrochloride Extended-Release Tablets. Table 2: Clinically Significant Drug Interactions with Metformin Hydrochloride Extended-Release Tablets Carbonic Anhydrase Inhibitors Clinical Impact: Carbonic anhydrase inhibitors frequently cause a decrease in serum bicarbonate and induce non-anion gap, hyperchloremic metabolic acidosis. Concomitant use of these drugs with Metformin Hydrochloride Extended-Release Tablets may increase the risk for lactic acidosis.
Intervention: Consider more frequent monitoring of these patients. Examples: Topiramate, zonisamide, acetazolamide or dichlorphenamide. Drugs that Reduce Metformin Hydrochloride Extended-Release Tablets Clearance Clinical Impact: Concomitant use of drugs that interfere with common renal tubular transport systems involved in the renal elimination of metformin (e.g., organic cationic transporter-2 [OCT2] / multidrug and toxin extrusion [MATE] inhibitors) could increase systemic exposure to metformin and may increase the risk for lactic acidosis [see Clinical Pharmacology ( 12.3 )].
Intervention: Consider the benefits and risks of concomitant use with Metformin Hydrochloride Extended-Release Tablets. Examples: Ranolazine, vandetanib, dolutegravir, and cimetidine. Alcohol Clinical Impact: Alcohol is known to potentiate the effect of metformin on lactate metabolism.
Intervention: Warn patients against excessive alcohol intake while receiving Metformin Hydrochloride Extended-Release Tablets. Insulin Secretagogues or Insulin Clinical Impact: Coadministration of Metformin Hydrochloride Extended-Release Tablets with an insulin secretagogue (e.g., sulfonylurea) or insulin may increase the risk of hypoglycemia. Intervention: Patients receiving an insulin secretagogue or insulin may require lower doses of the insulin secretagogue or insulin.
Drugs Affecting Glycemic Control Clinical Impact: Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control. Intervention: When such drugs are administered to a patient receiving Metformin Hydrochloride Extended-Release Tablets, observe the patient closely for loss of blood glucose control. When such drugs are withdrawn from a patient receiving Metformin Hydrochloride Extended-Release Tablets, observe the patient closely for hypoglycemia.
Examples: Thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blockers, and isoniazid. Carbonic anhydrase inhibitors may increase risk of lactic acidosis. Consider more frequent monitoring.
( 7 ) Drugs that reduce metformin clearance (such as ranolazine, vandetanib, dolutegravir, and cimetidine) may increase the accumulation of metformin. Consider the benefits and risks of concomitant use. ( 7 ) Alcohol can potentiate the effect of metformin on lactate metabolism.
Warn patients against excessive alcohol intake. ( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Females and Males of Reproductive Potential: Advise premenopausal females of the potential for an unintended pregnancy. ( 8.3 ) Geriatric Use: Assess renal function more frequently. ( 8.5 ) Hepatic Impairment: Avoid use in patients with hepatic impairment. ( 8.7 )
8.1Pregnancy Risk Summary Limited data with Metformin Hydrochloride Extended-Release Tablets in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data]. There are risks to the mother and fetus associated with poorly controlled diabetes mellitus in pregnancy [see Clinical Considerations] .
No adverse developmental effects were observed when metformin was administered to pregnant Sprague Dawley rats and rabbits during the period of organogenesis at doses up to 3 and 1 times, respectively, a 2,000 mg clinical dose, based on body surface area [see Data] . The estimated background risk of major birth defects is 6–10% in women with pregestational diabetes mellitus with an HbA1c >7 and has been reported to be as high as 20–25% in women with an HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes mellitus in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, stillbirth and delivery complications. Poorly controlled diabetes mellitus increases the fetal risk for major birth defects, stillbirth, and macrosomia-related morbidity.
Data Human Data Published data from postmarketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy. However, these studies cannot definitely establish the absence of any metformin-associated risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Metformin HCl was not teratogenic or embyrolethal when administered to rats prior to pregnancy through the period of organogenesis at doses up to 900 mg/kg, or when administered to rabbits during the period of organogenesis at doses up to 90 mg/kg.
8.2Lactation Risk Summary Limited published studies report that metformin is present in human milk [see Data] . However, there is insufficient information to determine the effects of metformin on the breastfed infant and no available information on the effects of metformin on milk production. Therefore, the developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for Metformin Hydrochloride Extended-Release Tablets and any potential adverse effects on the breastfed child from Metformin Hydrochloride Extended-Release Tablets or from the underlying maternal condition.
Data Published clinical lactation studies report that metformin is present in human milk which resulted in infant doses approximately 0.11% to 1% of the maternal weight-adjusted dosage and a milk/plasma ratio ranging between 0.13 and 1. However, the studies were not designed to definitely establish the risk of use of metformin during lactation because of small sample size and limited adverse event data collected in infants.
8.3Females and Males of Reproductive Potential Discuss the potential for unintended pregnancy with premenopausal women as therapy with Metformin Hydrochloride Extended-Release Tablets may result in ovulation in some anovulatory women.
8.4 Pediatric Use Safety and effectiveness of Metformin Hydrochloride Extended-Releas…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited data with Metformin Hydrochloride Extended-Release Tablets in pregnant women are not sufficient to determine a drug-associated risk for major birth defects or miscarriage. Published studies with metformin use during pregnancy have not reported a clear association with metformin and major birth defect or miscarriage risk [see Data]. There are risks to the mother and fetus associated with poorly controlled diabetes mellitus in pregnancy [see Clinical Considerations] .
No adverse developmental effects were observed when metformin was administered to pregnant Sprague Dawley rats and rabbits during the period of organogenesis at doses up to 3 and 1 times, respectively, a 2,000 mg clinical dose, based on body surface area [see Data] . The estimated background risk of major birth defects is 6–10% in women with pregestational diabetes mellitus with an HbA1c >7 and has been reported to be as high as 20–25% in women with an HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes mellitus in pregnancy increases the maternal risk for diabetic ketoacidosis, pre-eclampsia, spontaneous abortions, preterm delivery, stillbirth and delivery complications. Poorly controlled diabetes mellitus increases the fetal risk for major birth defects, stillbirth, and macrosomia-related morbidity.
Data Human Data Published data from postmarketing studies have not reported a clear association with metformin and major birth defects, miscarriage, or adverse maternal or fetal outcomes when metformin was used during pregnancy. However, these studies cannot definitely establish the absence of any metformin-associated risk because of methodological limitations, including small sample size and inconsistent comparator groups. Animal Data Metformin HCl was not teratogenic or embyrolethal when administered to rats prior to pregnancy through the period of organogenesis at doses up to 900 mg/kg, or when administered to rabbits during the period of organogenesis at doses up to 90 mg/kg.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of Metformin Hydrochloride Extended-Release Tablets in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of Metformin Hydrochloride Extended-Release Tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy and the higher risk of lactic acidosis. Assess renal function more frequently in elderly patients. [see Dosage and Administration ( 2.2 ) and Warnings and Precautions ( 5.1 ).]
🆘 Overdosage ▾
10 OVERDOSAGE Overdose of metformin HCl has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases. [see Warnings and Precautions ( 5.1 ).] Metformin is dialyzable with a clearance of up to 170 mL/minute under good hemodynamic conditions.
Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Metformin is a biguanide that improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may decrease.
12.3Pharmacokinetics Absorption Following a single oral dose of 1,000 mg (2x500 mg tablets) Metformin Hydrochloride Extended-Release Tablets after a meal, the time to reach maximum plasma metformin concentration (T max ) is achieved at approximately 7-8 hours. In both single- and multiple-dose studies in healthy subjects, once daily 1,000 mg (2x500 mg tablets) dosing provides equivalent systemic exposure, as measured by area under the curve (AUC), and up to 35% higher C max , of metformin relative to the immediate-release given as 500 mg twice daily.
At usual clinical doses and dosing schedules of metformin, steady state plasma concentrations of metformin are reached within 24-48 hours and are generally <1 mcg/mL. In a two-way, single-dose, crossover study in healthy volunteers, the 1,000 mg tablet was found to be similar to two 500 mg tablets under fed conditions based on equivalent C max and AUCs for the two formulations. Single oral doses of Metformin Hydrochloride Extended-Release Tablets from 500 mg to 2,500 mg resulted in less than proportional increase in both AUC and C max .
Effect of food: Low-fat and high-fat meals increased the systemic exposure (as measured by AUC) from Metformin Hydrochloride Extended-Release Tablets by about 38% and 73%, respectively, relative to fasting. Both meals prolonged metformin T max by approximately 3 hours but C max was not affected. Distribution The apparent volume of distribution (V/F) of metformin following single oral doses of 850 mg metformin HCl averaged 654±358 L.
Metformin is negligibly bound to plasma proteins. Metformin partitions into erythrocytes, most likely as a function of time. Metabolism Intravenous, single-dose studies in healthy subjects demonstrate that metformin is excreted unchanged in the urine and does not undergo hepatic metabolism (no metabolites have been identified in humans), nor biliary excretion.
Excretion Renal clearance is approximately 3.5 times greater than creatinine clearance, which indicates that tubular secretion is the major route of metformin elimination. Following oral administration, approximately 90% of the absorbed drug is eliminated via the renal route within the first 24 hours, with a plasma elimination half-life of approximately 6.2 hours. In blood, the elimination half-life is approximately 17.6 hours, suggesting that the erythrocyte mass may be a compartment of distribution.
Special Populations Renal Impairment Following a single-dose administration of Metformin Hydrochloride Extended-Release Tablets 500 mg in subjects with mild and moderate renal impairment, the oral and renal clearance of metformin were decreased by 33% and 50% and 16% and 53%, respectively . Metformin peak and systemic exposure was 27% and 61% greater, respectively in subjects with mild renal impairment and 74% and 2.36-fold greater in subjects with moderate renal impairment as compared to healthy subjects. [see Dosage and Administration ( 2.2 ), Contraindications ( 4 ), and Warnings and Precautions ( 5.1 ).] Hepatic Impairment No pharmacokinetic studies of Metformin Hydrochloride Extended-Release Tablets have been conducted in subjects with hepatic impairment, [see Warnings and Precautions ( 5.1 ) and Use in Specific Populations ( 8.7 )] Geriatrics Limited data from controlled pharmacokinetic studies of metformin HCl in healthy elderly subjects suggest that total plasma clearance of metformin is decreased by 35%, the half-life is prolonged by 64% and C max is…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Metformin is a biguanide that improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may decrease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Metformin Hydrochloride Extended-Release Tablets are supplied as: 500 mg Bottles of 100 NDC 68682-021-50 white, film-coated, oval-shaped, extended-release tablets with “M500” on one side. 1,000 mg Bottles of 90 NDC 68682-018-90 white, film-coated, oval-shaped, extended-release tablets with “M1000” on one side. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Metformin Hydrochloride Extended-Release Tablets contain the biguanide antihyperglycemic agent metformin in the form of monohydrochloride salt. The chemical name of metformin hydrochloride is N,N-dimethylimidodicarbonimidic diamide hydrochloride. The structural formula is as shown: Metformin hydrochloride is a white to off-white crystalline compound with a molecular formula of C 4 H 11 N 5 •HCl and a molecular weight of 165.63.
Metformin hydrochloride is freely soluble in water and is practically insoluble in acetone, ether, and chloroform. The pKa of metformin is 12.4. The pH of a 1% aqueous solution of metformin hydrochloride is 6.68.
Metformin Hydrochloride Extended-Release Tablets contain 500 mg or 1,000 mg of metformin hydrochloride, which is equivalent to 389.93 mg or 779.86 mg metformin, respectively. Each 500 mg tablet contains coloring, hypromellose, magnesium stearate, microcrystalline cellulose and polyethylene oxide. Each 1,000 mg tablet contains colloidal silicon dioxide, polyvinyl alcohol, crospovidone, glyceryl behenate, polyacrylate dispersion, hypromellose, talc, polyethylene glycol, eudragit, titanium dioxide, simethicone emulsion, polysorbate and coloring.
Chemical Structure-Glumetza
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Lactic Acidosis : Explain the risks of lactic acidosis, its symptoms, and conditions that predispose to its development. Advise patients to discontinue Metformin Hydrochloride Extended-Release Tablets immediately and to promptly notify their healthcare provider if unexplained hyperventilation, myalgias, malaise, unusual somnolence or other nonspecific symptoms occur.
Counsel patients against excessive alcohol intake and inform patients about importance of regular testing of renal function while receiving Metformin Hydrochloride Extended-Release Tablets. Instruct patients to inform their doctor that they are taking Metformin Hydrochloride Extended-Release Tablets prior to any surgical or radiological procedure, as temporary discontinuation may be required [see Warnings and Precautions ( 5.1 )] . Hypoglycemia Inform patients that hypoglycemia may occur when Metformin Hydrochloride Extended-Release Tablets are coadministered with oral sulfonylureas and insulin.
Explain to patients receiving concomitant therapy the risks of hypoglycemia, its symptoms and treatment, and conditions that predispose to its development [see Warnings and Precautions ( 5.3 )] . Vitamin B12 Deficiency: Inform patients about importance of regular hematological parameters while receiving Metformin Hydrochloride Extended-Release Tablets [see Warnings and Precautions ( 5.2 )] . Females of Reproductive Age: Inform females that treatment with Metformin Hydrochloride Extended-Release Tablets may result in ovulation in some premenopausal anovulatory women which may lead to unintended pregnancy [see Use in Specific Populations ( 8.3 )] .
Administration Information: Inform patients that Metformin Hydrochloride Extended-Release Tablets must be swallowed whole and not crushed, cut, or chewed, and that the inactive ingredients may occasionally be eliminated in the feces as a soft mass that may resemble the original tablet. Distributed by: Oceanside Pharmaceuticals, a division of Bausch Health US, LLC Bridgewater, NJ 08807 USA Manufactured by: Bausch Health Companies Inc. Steinbach, MB R5G 1Z7, Canada U.S.
Patent Numbers: 6,488,962; 6,723,340; 7,780,987 and 8,323,692 © 2019 Bausch Health Companies Inc. or its affiliates 9619003 20002705