
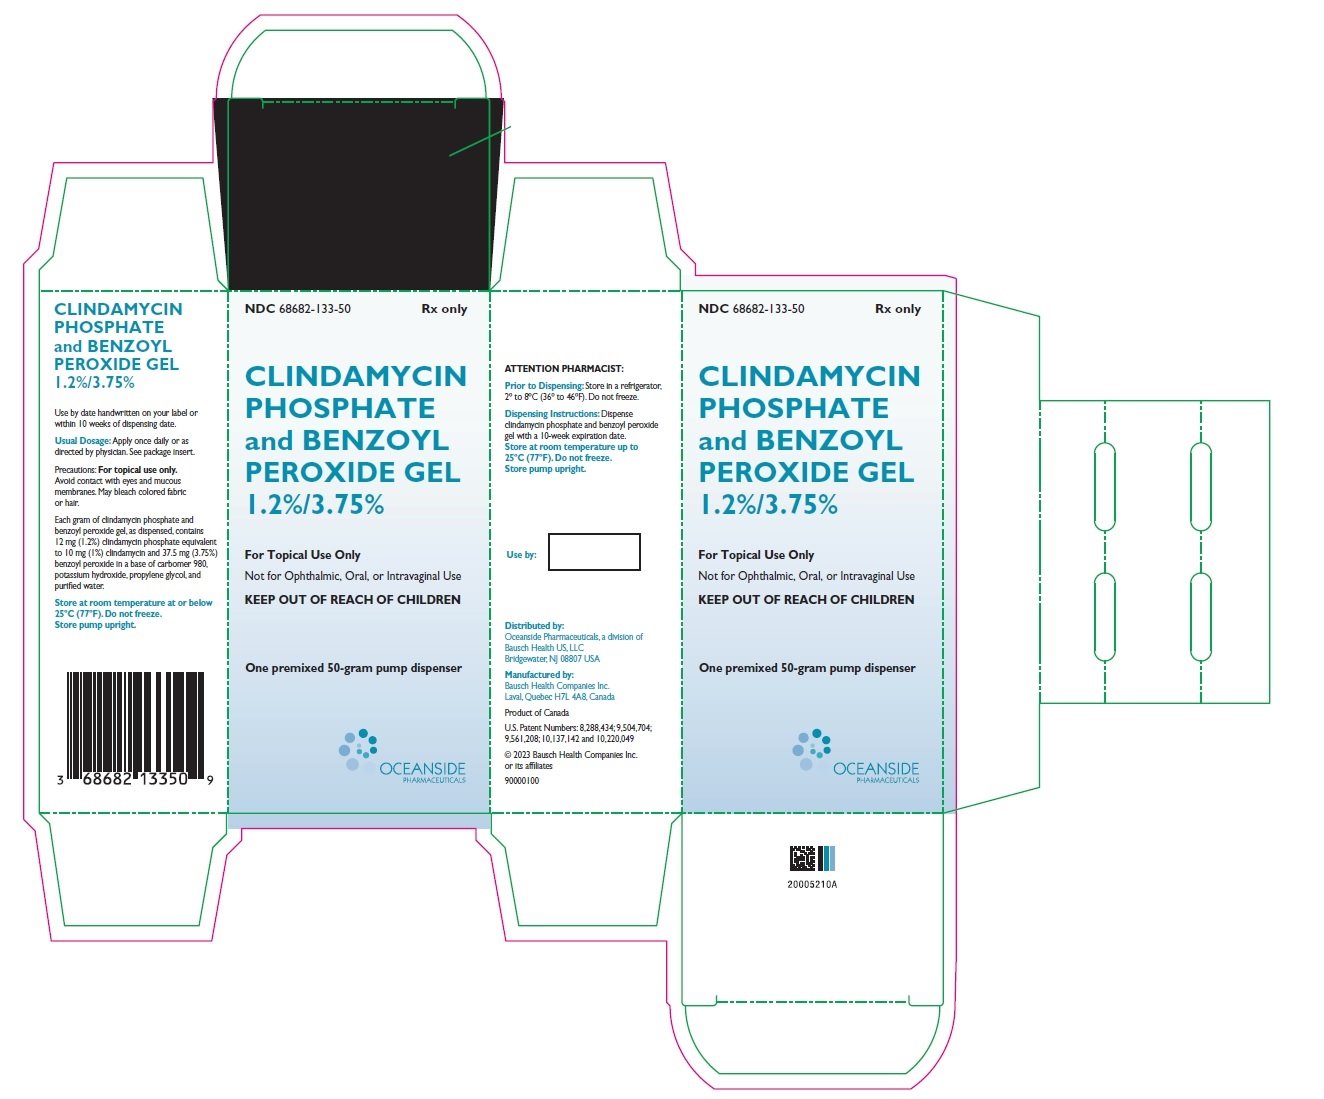
Clindamycin Phosphate and Benzoyl Peroxide 10 mg/g; 37.5 mg/g Gel
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Peroxides class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of clindamycin and benzoyl peroxide is used to treat acne. Clindamycin and benzoyl peroxide are in a class of medications called topical antibiotics. The combination of clindamycin and benzoyl peroxide works by killing the bacteria that cause acne.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 4Q93RCW27E
A synthetic polymer made from acrylic acid that's crosslinked for stability. It acts as a thickener and gelling agent in creams and gels, helping the medicine spread evenly and maintain its texture.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $6.070 | $303.50 / 50 g |
| Medicaid paysCMS SDUD · 12 mo | $5.47 | $273.28 / 50 g |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clindamycin Phosphate and Benzoyl Peroxide 10 mg/g; 37.5 mg/g 45802-0383-01 | Padagis | 50 g | $2.472 | AB | Availability likely | save 59% |
| Clindamycin Phosphate and Benzoyl Peroxide 10 mg/g; 50 mg/g 51672-1403-04 | Sun | 50 g | $2.472 | AB | Availability likely | save 59% |
| Clindamycin Phosphate and Benzoyl Peroxide 10 mg/g; 37.5 mg/g 68308-0127-50 | Mayne | 50 g | $2.472 | AB | Availability likely | save 59% |
| Clindamycin Phosphate and Benzoyl Peroxide 10 mg/g; 37.5 mg/gthis 68682-0133-50 | Oceanside | 1 bottle | $6.070 | AB | FDA listed | — |
| Onexton 10 mg/g; 37.5 mg/g 00187-3050-35 | Bausch | 3.5 g | — | AB | FDA listed | — |
| Clindamycin Phosphate and Benzoyl Peroxide 10 mg/g; 37.5 mg/g 72162-2419-02 | Bryant | 50 g | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8288434 ↗ | Method of use | U-818 | Aug 5, 2029 |
| US 8288434 ↗ | Method of use | U-124 | Aug 5, 2029 |
| US 8288434 ↗ | Method of use | U-134 | Aug 5, 2029 |
| US 9561208 ↗ | Method of use | U-916 | Jun 3, 2029 |
| US 10220049 ↗ | Method of use | U-916 | Jun 3, 2029 |
| US 9504704 ↗ | Method of use | U-134 | Jun 3, 2029 |
| US 9504704 ↗ | Method of use | U-818 | Jun 3, 2029 |
| US 9504704 ↗ | Method of use | U-916 | Jun 3, 2029 |
| US 8288434 ↗ | Method of use | U-124 | Aug 5, 2029 |
| US 8288434 ↗ | Method of use | U-1033 | Aug 5, 2029 |
| US 8288434 ↗ | Method of use | U-921 | Aug 5, 2029 |
| US 9504704 ↗ | Method of use | U-124 | Jun 3, 2029 |
| US 8288434 ↗ | Method of use | U-916 | Aug 5, 2029 |
| US 8895070 ↗ | Method of use | U-124 | Jun 3, 2029 |
| US 10137142 ↗ | Method of use | U-916 | Jun 3, 2029 |
| US 10220049 ↗ | Method of use | U-916 | Jun 3, 2029 |
| US 10624918 ↗ | Method of use | U-916 | Jun 3, 2029 |
| US 8663699 ↗ | Method of use | U-124 | Jun 3, 2029 |
| US 9078870 ↗ | Drug product | — | Jun 3, 2029 |
Is there a generic version of CLINDAMYC-BNZ PEROX 1.2-3.75%?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68682-0133-50 You're viewing this | 1 BOTTLE, PUMP in 1 CARTON (68682-133-50) / 50 g in 1 BOTTLE, PUMP | 2023-10-02 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Clindamycin Phosphate and Benzoyl Peroxide Gel, 1.2%/3.75% is indicated for the topical treatment of acne vulgaris in patients 12 years of age and older. Clindamycin Phosphate and Benzoyl Peroxide Gel is a combination of clindamycin phosphate (a lincosamide antibacterial) and benzoyl peroxide indicated for the topical treatment of acne vulgaris in patients 12 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Before applying clindamycin phosphate and benzoyl peroxide gel, wash the face gently with a mild soap, rinse with warm water, and pat the skin dry. Apply a pea-sized amount of clindamycin phosphate and benzoyl peroxide gel to the face once daily. Avoid the eyes, mouth, mucous membranes, or areas of broken skin.
Use of clindamycin phosphate and benzoyl peroxide gel beyond 12 weeks has not been evaluated. Clindamycin Phosphate and Benzoyl Peroxide Gel is not for oral, ophthalmic, or intravaginal use. • Apply a pea-sized amount of clindamycin phosphate and benzoyl peroxide gel to the face once daily. ( 2 ) • Not for oral, ophthalmic, or intravaginal use.
( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Gel, 1.2%/3.75% Each gram of clindamycin phosphate and benzoyl peroxide gel contains 12 mg (1.2%) clindamycin phosphate, equivalent to 10 mg (1%) clindamycin, and 37.5 mg (3.75%) benzoyl peroxide in a white to off-white, opaque, smooth gel. Gel, 1.2% clindamycin phosphate/3.75% benzoyl peroxide
⛔ Contraindications ▾
4 CONTRAINDICATIONS Clindamycin Phosphate and Benzoyl Peroxide Gel is contraindicated in: • Patients who have demonstrated hypersensitivity (e.g., anaphylaxis) to clindamycin, benzoyl peroxide, any components of the formulation, or lincomycin. ( 4.1 ) • Patients with a history of regional enteritis, ulcerative colitis, or antibiotic-associated colitis. ( 4.2 )
4.1Hypersensitivity Clindamycin Phosphate and Benzoyl Peroxide Gel is contraindicated in those individuals who have shown hypersensitivity to clindamycin, benzoyl peroxide, any components of the formulation, or lincomycin. Anaphylaxis, as well as allergic reactions leading to hospitalization, has been reported in postmarketing use with clindamycin phosphate and benzoyl peroxide gel [see Postmarketing Experience (6.2) ] .
4.2Colitis/Enteritis Clindamycin Phosphate and Benzoyl Peroxide Gel is contraindicated in patients with a history of regional enteritis, ulcerative colitis, or antibiotic-associated colitis [see Warnings and Precautions (5.1) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Colitis: Clindamycin can cause severe colitis, which may result in death. Diarrhea, bloody diarrhea, and colitis (including pseudomembranous colitis) have been reported with the use of clindamycin. Clindamycin Phosphate and Benzoyl Peroxide Gel should be discontinued if significant diarrhea occurs. ( 5.1 ) • Ultraviolet Light and Environmental Exposure: Minimize sun exposure following drug application. ( 5.2 )
5.1Colitis Systemic absorption of clindamycin has been demonstrated following topical use of clindamycin. Diarrhea, bloody diarrhea, and colitis (including pseudomembranous colitis) have been reported with the use of topical and systemic clindamycin. If significant diarrhea occurs, clindamycin phosphate and benzoyl peroxide gel should be discontinued.
Severe colitis has occurred following oral and parenteral administration of clindamycin with an onset of up to several weeks following cessation of therapy. Antiperistaltic agents such as opiates and diphenoxylate with atropine may prolong and/or worsen severe colitis. Severe colitis may result in death.
Studies indicate toxin(s) produced by Clostridia is one primary cause of antibiotic-associated colitis. The colitis is usually characterized by severe persistent diarrhea and severe abdominal cramps and may be associated with the passage of blood and mucus. Stool cultures for Clostridium difficile and stool assay for C. difficile toxin may be helpful diagnostically.
5.2Ultraviolet Light and Environmental Exposure Minimize sun exposure (including use of tanning beds or sun lamps) following drug application.
5.3Concomitant Topical Medications Concomitant topical acne therapy should be used with caution since a possible cumulative irritancy effect may occur, especially with the use of peeling, desquamating, or abrasive agents. If irritancy or dermatitis occurs, reduce frequency of application or temporarily interrupt treatment and resume once the irritation subsides. Treatment should be discontinued if the irritation persists.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reaction is described in more detail in the Warnings and Precautions section of the label: • Colitis [see Warnings and Precautions (5.1) ] . The most common adverse reactions are: burning sensation (0.4%); contact dermatitis (0.4%); pruritus (0.4%); and rash (0.4%). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Oceanside Pharmaceuticals at 1-800-321-4576 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates observed in clinical trials of another drug and may not reflect the rates observed in clinical practice. These adverse reactions occurred in less than 0.5% of subjects treated with clindamycin phosphate and benzoyl peroxide gel: burning sensation (0.4%); contact dermatitis (0.4%); pruritus (0.4%); and rash (0.4%). During the clinical trial, subjects were assessed for local cutaneous signs and symptoms of erythema, scaling, itching, burning and stinging.
Most local skin reactions either were the same as baseline or increased and peaked around Week 4 and were near or improved from baseline levels by Week 12. The percentage of subjects that had symptoms present before treatment (at baseline), during treatment, and the percent with symptoms present at Week 12 are shown in Table 1. Table 1: Percent of Subjects with Local Skin Reactions.
Results from the Phase 3 Trial (N = 243) Before Treatment (Baseline) During Treatment End of Treatment (Week 12) Mild Mod. * Severe Mild Mod. * Severe Mild Mod. * Severe Erythema 20 6 0 28 5 <1 15 2 0 Scaling 10 1 0 19 3 0 10 <1 0 Itching 14 3 <1 15 3 0 7 2 0 Burning 5 <1 <1 7 1 <1 3 <1 0 Stinging 5 <1 0 7 0 <1 3 0 <1 *Mod. = Moderate
6.2Postmarketing Experience Because postmarketing adverse reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Anaphylaxis, as well as allergic reactions leading to hospitalizations, has been reported in postmarketing use of products containing clindamycin phosphate/benzoyl peroxide.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Avoid using clindamycin phosphate and benzoyl peroxide gel in combination with topical or oral erythromycin-containing products because of its clindamycin component. ( 7.1 )
7.1Erythromycin Avoid using clindamycin phosphate and benzoyl peroxide gel in combination with topical or oral erythromycin-containing products due to its clindamycin component. In vitro studies have shown antagonism between erythromycin and clindamycin. The clinical significance of this in vitro antagonism is not known.
7.2Neuromuscular Blocking Agents Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Clindamycin Phosphate and Benzoyl Peroxide Gel should be used with caution in patients receiving such agents.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on clindamycin phosphate and benzoyl peroxide gel use in pregnant women to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. The limited published data on use of clindamycin in pregnant women with exposure during the first trimester are insufficient to inform a drug-associated risk of pregnancy-related adverse outcomes (see Data) . In limited published clinical trials with pregnant women, the systemic administration of clindamycin during the second and third trimesters has not been associated with an increased frequency of major birth defects.
In animal reproduction studies, clindamycin did not cause malformations or embryo-fetal development toxicity in pregnant rats and mice when administered during the period of organogenesis at systemic doses up to 240 times the maximum recommended human dose (MRHD) of 2.5 g clindamycin phosphate and benzoyl peroxide gel, based on body surface area (BSA) comparisons (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of major birth defects, loss, and other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data In limited published trials in pregnant women administered clindamycin during the first trimester of pregnancy, there was no difference in the rate of major birth defects reported among in utero exposed infants compared to unexposed infants. These data cannot definitely establish or exclude any clindamycin-associated risk during pregnancy.
Animal Data Animal reproductive/developmental toxicity studies have not been conducted with clindamycin phosphate and benzoyl peroxide gel or benzoyl peroxide. Developmental toxicity studies of clindamycin performed in pregnant rats and mice administered during the period of organogenesis at oral doses of up to 600 mg/kg/day (240 and 120 times the MRHD for clindamycin, respectively, based on BSA comparisons) or subcutaneous doses of up to 200 mg/kg/day (80 and 40 times the MRHD for clindamycin, respectively, based on BSA comparisons) revealed no malformations or embryo-fetal development toxicity.
8.2Lactation Risk Summary There are no data on the presence of clindamycin or benzoyl peroxide in human milk, the effects on the breastfed child, or the effects on milk production following topical administration. However, clindamycin has been reported to be present in breast milk in small amounts following oral and parenteral administration. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for clindamycin phosphate and benzoyl peroxide gel and any potential adverse effects on the breastfed child from clindamycin phosphate and benzoyl peroxide gel or from the underlying maternal condition.
Clinical Considerations If used during lactation and clindamycin phosphate and benzoyl peroxide gel is applied to the chest, care should be taken to avoid accidental ingestion by the infant.
8.4Pediatric Use Safety and effectiveness of clindamycin phosphate and benzoyl peroxide gel in pediatric patients under the age of 12 years have not been evaluated.
8.5Geriatric Use Clinical trials of clindamycin phosphate and benzoyl peroxide gel did not include sufficient numbers of subjects age 65 years and older to determine whether they respond differently from younger subjects.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on clindamycin phosphate and benzoyl peroxide gel use in pregnant women to evaluate a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. The limited published data on use of clindamycin in pregnant women with exposure during the first trimester are insufficient to inform a drug-associated risk of pregnancy-related adverse outcomes (see Data) . In limited published clinical trials with pregnant women, the systemic administration of clindamycin during the second and third trimesters has not been associated with an increased frequency of major birth defects.
In animal reproduction studies, clindamycin did not cause malformations or embryo-fetal development toxicity in pregnant rats and mice when administered during the period of organogenesis at systemic doses up to 240 times the maximum recommended human dose (MRHD) of 2.5 g clindamycin phosphate and benzoyl peroxide gel, based on body surface area (BSA) comparisons (see Data) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of major birth defects, loss, and other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data In limited published trials in pregnant women administered clindamycin during the first trimester of pregnancy, there was no difference in the rate of major birth defects reported among in utero exposed infants compared to unexposed infants. These data cannot definitely establish or exclude any clindamycin-associated risk during pregnancy.
Animal Data Animal reproductive/developmental toxicity studies have not been conducted with clindamycin phosphate and benzoyl peroxide gel or benzoyl peroxide. Developmental toxicity studies of clindamycin performed in pregnant rats and mice administered during the period of organogenesis at oral doses of up to 600 mg/kg/day (240 and 120 times the MRHD for clindamycin, respectively, based on BSA comparisons) or subcutaneous doses of up to 200 mg/kg/day (80 and 40 times the MRHD for clindamycin, respectively, based on BSA comparisons) revealed no malformations or embryo-fetal development toxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of clindamycin phosphate and benzoyl peroxide gel in pediatric patients under the age of 12 years have not been evaluated.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of clindamycin phosphate and benzoyl peroxide gel did not include sufficient numbers of subjects age 65 years and older to determine whether they respond differently from younger subjects.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Clindamycin: Clindamycin is a lincosamide antibacterial [see Microbiology (12.4) ] . Benzoyl Peroxide: Benzoyl peroxide is an oxidizing agent with bactericidal and keratolytic effects but the precise mechanism of action is unknown.
12.3Pharmacokinetics The systemic absorption of clindamycin phosphate and benzoyl peroxide gel has not been evaluated. The systemic absorption of clindamycin was investigated in an open-label, multiple-dose trial in 16 adult subjects with moderate to severe acne vulgaris treated with 1 gram of a marketed gel containing clindamycin 1%/benzoyl peroxide 2.5% applied to the face once daily for 30 days. This product has the same formulation as clindamycin phosphate and benzoyl peroxide gel but with a lower concentration of benzoyl peroxide.
Twelve subjects (75%) had at least one quantifiable clindamycin plasma concentration above the lower limit of quantification (LOQ = 0.5 ng/mL) on Day 1 or Day 30. On Day 1, the mean (± standard deviation) peak plasma concentrations (C max ) was 0.78 ± 0.22 ng/mL (n=9 with measurable concentrations), and the mean AUC 0-t was 5.29 ± 0.81 h.ng/mL (n=4). On Day 30, the mean C max was 1.22 ± 0.88 ng/mL (n=10), and the mean AUC 0-t was 8.42 ± 6.01 h.ng/mL (n=6).
Clindamycin plasma concentrations were below LOQ in all subjects at 24 hours post-dose on the three tested days (Day 1, 15, and 30). Benzoyl peroxide has been shown to be absorbed by the skin where it is converted to benzoic acid.
12.4Microbiology Clindamycin binds to the 50S ribosomal subunits of susceptible bacteria and prevents elongation of peptide chains by interfering with peptidyl transfer, thereby suppressing bacterial protein synthesis. Clindamycin and benzoyl peroxide individually have been shown to have in vitro activity against Propionibacterium acnes , an organism which has been associated with acne vulgaris. In an in vitro study, the minimum inhibitory concentration (MIC) for benzoyl peroxide against Propionibacterium acnes is 128 mg/L.
The clinical significance of this activity against P. acnes is not known. P. acnes resistance to clindamycin has been documented. Resistance to clindamycin is often associated with resistance to erythromycin.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Clindamycin: Clindamycin is a lincosamide antibacterial [see Microbiology (12.4) ] . Benzoyl Peroxide: Benzoyl peroxide is an oxidizing agent with bactericidal and keratolytic effects but the precise mechanism of action is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Clindamycin Phosphate and Benzoyl Peroxide Gel, 1.2%/3.75% is a white to off-white smooth gel supplied as: NDC 68682-133-50 50 g pump Dispensing Instructions for the Pharmacist • Dispense clindamycin phosphate and benzoyl peroxide gel with a 8-week expiration date. • Specify “Store at room temperature up to 25°C (77°F). Do not freeze.” Storage and Handling • PHARMACIST: Prior to Dispensing: Store in a refrigerator, 2° to 8°C (36° to 46°F). • PATIENT: After Dispensing: Discard unused portion 8 weeks after date of dispensing.
Store at room temperature at or below 25°C (77°F). • Protect from freezing. • Store pump upright. • Keep out of the reach of children • Keep container tightly closed.
📋 Description ▾
11 DESCRIPTION Clindamycin Phosphate and Benzoyl Peroxide Gel is a combination product with two active ingredients in a white to off-white, opaque, smooth, aqueous gel formulation intended for topical use. Clindamycin phosphate is a water-soluble ester of the semisynthetic antibiotic produced by a 7(S)-chloro-substitution of the 7(R)-hydroxyl group of the parent antibiotic lincomycin. The chemical name for clindamycin phosphate is Methyl 7-chloro-6,7,8-trideoxy-6- (1-methyl-trans-4-propyl-L-2-pyrrolidinecarboxamido)-1-thio-L-threo-α-D-galacto-octopyranoside 2-(dihydrogen phosphate).
The structural formula for clindamycin phosphate is represented below: Clindamycin phosphate: Molecular Formula: C 18 H 34 ClN 2 O 8 PS Molecular Weight: 504.97 Benzoyl peroxide is an antibacterial and keratolytic agent. The structural formula for benzoyl peroxide is represented below: Benzoyl peroxide: Molecular Formula: C 14 H 10 O 4 Molecular Weight: 242.23 Clindamycin Phosphate and Benzoyl Peroxide Gel contains the following inactive ingredients: carbomer 980, potassium hydroxide, propylene glycol, and purified water.
Each gram of clindamycin phosphate and benzoyl peroxide gel contains 12 mg (1.2%) clindamycin phosphate, equivalent to 10 mg (1%) clindamycin, and 37.5 mg (3.75%) benzoyl peroxide. chemstructure chemstructure2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). • Patients who develop allergic reactions, such as severe swelling or shortness of breath, should discontinue use and contact their physician immediately. • Clindamycin Phosphate and Benzoyl Peroxide Gel may cause irritation, such as erythema, scaling, itching, or burning, especially when used in combination with other topical acne therapies. • Patients should limit excessive or prolonged exposure to sunlight.
To minimize exposure to sunlight, a hat or other clothing should be worn. Sunscreen may also be used. • Clindamycin Phosphate and Benzoyl Peroxide Gel may bleach hair or colored fabric. Distributed by: Oceanside Pharmaceuticals, a division of Bausch Health US, LLC Bridgewater, NJ 08807 USA Manufactured by: Bausch Health Companies Inc.
Laval, Quebec H7L 4A8, Canada Patented. See https://patents.ortho-dermatologics.com for US patent information. © 2025 Bausch Health Companies Inc. or its affiliates 90000202