
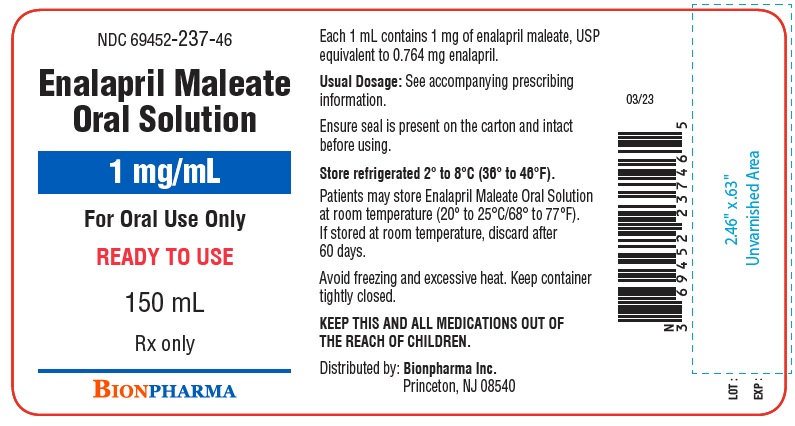
Enalapril maleate oral solution 1 mg/mL Solution — NDC 69452-237-46 (Billing 69452-0237-46)
This is a package of Enalapril maleate oral solution 1 mg/mL Solution from Bionpharma Inc., marketed since Aug 2021 and currently FDA-listed; retail pharmacies pay about $0.7946 per mL (NADAC). It is this product's only package size.
Other active recalls for Enalapril Maleate (different manufacturers) — 5 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 076637
- GCN: 42337
- GPI-14 (Medi-Span): 36100020102020
- HICL (First Databank): 000130
- AHFS class code: 24:32.04.00
- RxCUI (RxNorm): 1435624
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Angiotensin Converting Enzyme Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Enalapril is used alone or in combination with other medications to treat high blood pressure. It is also used in combination with other medications to treat heart failure. Enalapril is in a class of medications called angiotensin-converting enzyme (ACE) inhibitors. It works by decreasing certain chemicals that tighten the blood vessels, so blood flows more smoothly and the heart can pump blood more efficiently. High blood pressure is a common condition, and when not treated it can cause damage to the brain, heart, blood vessels, kidneys, and other parts of the body. Damage to these organs may...
Read the full MedlinePlus article ↗- It treats high blood pressure and heart failure. It is also used when the heart’s pumping function is weak but you don’t have symptoms yet, to slow progression to heart failure. Lo...
- Take it by mouth, as a tablet or oral solution, once or twice a day as prescribed. Food does not affect tablet absorption. Don’t change your dose on your own, and ask me if you mis...
- Most people tolerate it well. You may feel tired or dizzy, especially when starting. Stand up slowly, and tell your doctor if dizziness is bothersome.
- Get emergency help for swelling of the face, lips, tongue or throat, or trouble breathing. Call your doctor for severe stomach pain, yellowing of your skin or eyes, or fainting.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Enalapril Maleate — tap one for details:
Enalapril Maleate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.795 | $119.19 / 150 ml |
| Medicaid paysCMS SDUD · 12 mo | $1.20 | $180.71 / 150 ml |
| Medicare drug plans payPart D · Q2 2026 | $1.39 | $208.80 / 150 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 69452-0237-46 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 150 mL in 1 BOTTLE | 2021-08-11 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Enalapril maleate oral solution 1 mg/mL 31722-0020-15 | Camber | 1 bottle | $0.795 | AB | Availability likely | — |
| Enalapril maleate 1 mg/mL 52536-0401-01 | Wilshire | 1 bottle | $0.795 | AB | Availability likely | — |
| Enalapril Maleate 1 mg/mL 59651-0529-55 | Aurobindo | 1 bottle | $0.795 | AB | Availability likely | — |
| Enalapril Maleate 1 mg/mL 69238-1729-07 | Amneal | 1 bottle | $0.795 | AB | Availability likely | — |
| Enalapril Maleate 1 mg/mL 69238-2141-07 | Amneal | 1 bottle | $0.795 | AB | Discontinued | — |
| Enalapril maleate oral solution 1 mg/mLthis 69452-0237-46 | Bionpharma | 1 bottle | $0.795 | AB | Availability likely | — |
| Enalapril maleate oral solution 1 mg/mL 72603-0247-01 | NorthStar | 1 bottle | $0.795 | AB | Availability likely | — |
| Epaned 1 mg/mL 52652-4001-01 | Azurity | 150 ml | $4.478 | AB | Availability likely | +464% |
| Enalapril Maleate Oral Solution 1 mg/mL 67877-0712-81 | Ascend | 150 ml | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII FV3431923Z
A natural flavoring derived from berry fruits. Added to medicines to improve taste and make them more pleasant to take.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 96K6UQ3ZD4
Sucralose is a synthetic sweetener made from sugar. It's added to medicines to improve taste without adding calories, helping make bitter or unpleasant-tasting drugs easier to take.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue enalapril maleate oral solution as soon as possible. [See Warnings and Precautions ( 5.1 )] Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. [See Warnings and Precautions ( 5.1 )] WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning. When pregnancy is detected, discontinue enalapril maleate oral solution as soon as possible. ( 5.1 ) Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus.
( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Enalapril is an angiotensin-converting enzyme inhibitor indicated for: treatment of symptomatic heart failure. ( 1.2 ) treatment of asymptomatic left ventricular dysfunction, to decrease the rate of development of overt heart failure and reduce hospitalization for heart failure. ( 1.3 )
1.2Heart Failure Enalapril maleate oral solution is indicated for the treatment of symptomatic heart failure, usually in combination with diuretics and digitalis. In these patients, enalapril maleate oral solution increases survival and decreases the frequency of hospitalization.
1.3Asymptomatic Left Ventricular Dysfunction In clinically stable asymptomatic patients with left ventricular dysfunction (ejection fraction ≤35 percent), enalapril maleate oral solution decreases the rate of development of overt heart failure and decreases the incidence of hospitalization for heart failure.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Heart Failure: Initiate at 2.5 mg twice daily. Titrate up to 20 mg twice daily as tolerated. ( 2.2 ) Asymptomatic Left Ventricular Dysfunction: Initiate at 2.5 mg twice daily. Titrate up to 10 mg twice daily. ( 2.3 ) Enalapril maleate oral solution is a ready-to-use solution intended for oral use only.
2.2Heart Failure The recommended initial dose is 2.5 mg twice a day titrated up to a maximum of 20 mg twice a day, as tolerated. Doses are usually given in combination with diuretics and digitalis. In patients with hyponatremia (serum sodium less than 130 mEq/L) or serum creatinine greater than 1.6 mg/dL, the recommended initial dose is 2.5 mg once daily.
Diuretic dose may need to be adjusted to minimize hypovolemia and hypotension. The appearance of hypotension after the initial dose of enalapril maleate oral solution does not preclude subsequent careful dose titration with the drug, following effective management of the hypotension.
2.3Asymptomatic Left Ventricular Dysfunction The recommended initial dose is 2.5 mg twice a day titrated up to a maximum of 10 mg twice a day, as tolerated. Diuretic dose may need to be adjusted.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Enalapril maleate oral solution is a ready-to-use oral solution that contains 1 mg/mL of enalapril maleate, USP. It is a clear, colorless solution with a mixed berry flavor packaged in a 150 mL white, round, high-density polyethylene bottle with a white, polypropylene, child-resistant cap and tamper-evident seal. Each bottle contains 150 mL.
Enalapril maleate oral solution is a ready-to-use oral solution: 1 mg/mL enalapril maleate, USP. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Enalapril is contraindicated in patients with: a history of angioedema or hypersensitivity related to previous treatment with an angiotensin converting enzyme (ACE) inhibitor. [see Warnings and Precautions ( 5.2 )] hereditary or idiopathic angioedema. [see Warnings and Precautions ( 5.2 )] Do not co-administer aliskiren with enalapril in patients with diabetes [see Drug Interactions ( 7.2 )] . Enalapril is contraindicated in combination with a neprilysin inhibitor (e.g., sacubitril). Do not administer enalapril within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor [see Warnings and Precautions ( 5.2 )] .
Hypersensitivity related to previous treatment with an ACEI. ( 4 ) Hereditary or idiopathic angioedema. ( 4 ) Do not co-administer aliskiren in patients with diabetes.
( 4 ) In combination with a neprilysin inhibitor. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Angioedema and Anaphylactoid Reactions. ( 5.2 ) Impaired Renal Function: Assess renal function. ( 5.5 ) Hyperkalemia. ( 5.6 )
5.1Fetal Toxicity Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations. Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death.
When pregnancy is detected, discontinue enalapril as soon as possible [see Use in Specific Populations ( 8.1 )] .
5.2Angioedema and Anaphylactoid Reactions Angioedema Head and Neck Angioedema Angioedema of the face, extremities, lips, tongue, glottis and/or larynx, including some fatal reactions, have occurred in patients treated with angiotensin converting enzyme inhibitors, including enalapril, at any time during treatment. Patients with involvement of the tongue, glottis or larynx are likely to experience airway obstruction, especially those with a history of airway surgery. Enalapril should be promptly discontinued and appropriate therapy and monitoring should be provided until complete and sustained resolution of signs and symptoms of angioedema has occurred.
Patients with a history of angioedema unrelated to ACE inhibitor therapy may be at increased risk of angioedema while receiving an ACE inhibitor [see Contraindications ( 4 )] . ACE inhibitors have been associated with a higher rate of angioedema in black than in non-black patients. Patients receiving co-administration of ACE inhibitor and mTOR (mammalian target of rapamycin) inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema [see Drug Interactions ( 7.6 , 7.7 )].
Intestinal Angioedema Intestinal angioedema has occurred in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal. In some cases, the angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor.
Anaphylactoid Reactions Anaphylactoid Reactions during Desensitization Two patients undergoing desensitizing treatment with hymenoptera venom while receiving ACE inhibitors sustained life-threatening anaphylactoid reactions. Anaphylactoid Reactions during Dialysis Sudden and potentially life-threatening anaphylactoid reactions have occurred in some patients dialyzed with high-flux membranes and treated concomitantly with an ACE inhibitor. In such patients, dialysis must be stopped immediately, and aggressive therapy for anaphylactoid reactions must be initiated.
Symptoms have not been relieved by antihistamines in these situations. In these patients, consideration should be given to using a different type of dialysis membrane or a different class of antihypertensive agent. Anaphylactoid reactions have also been reported in patients undergoing low-density lipoprotein apheresis with dextran sulfate absorption.
5.3Hypotension Enalapril can cause symptomatic hypotension, sometimes complicated by oliguria, progressive azotemia, acute renal failure or death. Patients at risk of excessive hypotension include those with the following conditions or characteristics: heart failure with systolic blood pressure below 100 mmHg, ischemic heart disease, cerebrovascular disease, hyponatremia, high dose diuretic therapy, renal dialysis, or severe volume and/or salt depletion of any etiology. In these patients, enalapril should be started under very close medical supervision and such patients should be followed closely for the first two weeks of treatment and whenever the dose of enalapril and/or diuretic is increased.
Symptomatic hypotension is also… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described elsewhere: Angioedema [see Warnings and Precautions ( 5.2 )] Hypotension [see Warnings and Precautions ( 5.3 )] Hepatic failure [see Warnings and Precautions ( 5.4 )] Renal impairment [see Warnings and Precautions ( 5.5 )] Hyperkalemia [see Warnings and Precautions ( 5.6 )] The most common adverse reactions for patients treated for heart failure (>6%) were hypotension and dizziness. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Bionpharma Inc. at 1-888-235-BION or 1-888-235-2466 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Enalapril has been evaluated for safety in more than 10,000 patients, including over 1,000 patients treated for one year or more. In clinical trials, discontinuation of therapy for clinical adverse experiences was required in 5.7% of patients with heart failure.
Heart Failure In patients treated for heart failure, there was an increased incidence of hypotension 6.7 percent versus 0.6 percent in placebo and dizziness 7.9 percent versus 0.6 percent in placebo.
6.2Other Adverse Reactions from Clinical Studies or Postmarketing Experience The following adverse reactions have been reported in clinical studies or postmarketing experience with enalapril. Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Other serious clinical adverse experiences occurring since the drug was marketed or adverse experiences occurring in 0.5 to 1.0% of patients with hypertension or heart failure in clinical trials are listed below and, within each category, are in order of decreasing severity.
Cardiovascular: Cardiac arrest; myocardial infarction or cerebrovascular accident, possibly secondary to excessive hypotension in high risk patients [see Warnings and Precautions ( 5.3 )] ; pulmonary embolism and infarction; pulmonary edema; rhythm disturbances, including atrial tachycardia and bradycardia; atrial fibrillation; palpitation; Raynaud's phenomenon. Digestive: Ileus, pancreatitis, melena, anorexia, dyspepsia, constipation, glossitis, stomatitis, dry mouth. Hematologic: Rare cases of neutropenia, thrombocytopenia, and bone marrow depression.
Musculoskeletal: Muscle cramps. Nervous/Psychiatric: Depression, confusion, ataxia, somnolence, insomnia, nervousness, peripheral neuropathy (e.g., paresthesia, dysesthesia), dream abnormality. Respiratory: Bronchospasm, rhinorrhea, sore throat and hoarseness, asthma, upper respiratory infection, pulmonary infiltrates, eosinophilic pneumonitis.
Skin: Exfoliative dermatitis, toxic epidermal necrolysis, Stevens-Johnson syndrome, pemphigus, herpes zoster, erythema multiforme, urticaria, pruritus, alopecia, flushing, diaphoresis, photosensitivity. Special Senses: Blurred vision, taste alteration, anosmia, tinnitus, conjunctivitis, dry eyes, tearing. Urogenital: Flank pain, gynecomastia, impotence.
Miscellaneous: A symptom complex has been reported which may include some or all of the following: a positive ANA, an elevated erythrocyte sedimentation rate, arthralgia/arthritis, myalgia/myositis, fever, serositis, vasculitis, leukocytosis, eosinophilia, photosensitivity, dermatologic manifestations.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS In patients who are elderly, volume-depleted (as on diuretic therapy), or with compromised renal function, use with NSAIDs, including selective COX-2 inhibitors, may result in deterioration of renal function, including renal failure. Monitor renal function periodically. ( 7.1 ) Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension and hyperkalemia.
( 7.2 ) Avoid potassium sparing agents in patients with heart failure. ( 7.3 ) Monitor serum lithium levels frequently. ( 7.4 )
7.1Non-Steroidal Anti-Inflammatory Agents (NSAIDs) Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including enalapril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving enalapril and NSAID therapy.
In a clinical pharmacology study, indomethacin or sulindac was administered to hypertensive patients receiving enalapril maleate. In this study, there was no evidence of a blunting of the antihypertensive action of enalapril maleate. However, reports suggest that NSAIDs may diminish the antihypertensive effect of ACE inhibitors.
7.2Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. In most patients no benefit has been associated with using two RAS inhibitors concomitantly. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function and electrolytes in patients on enalapril and other agents that affect the RAS. Do not co-administer aliskiren with enalapril in patients with diabetes. Avoid use of aliskiren with enalapril in patients with renal impairment (GFR <60 mL/min).
7.3Agents Increasing Serum Potassium Enalapril attenuates potassium loss caused by thiazide-type diuretics. Potassium-sparing diuretics (e.g., spironolactone, triamterene, or amiloride), potassium supplements, or potassium-containing salt substitutes may lead to significant increases in serum potassium.
7.4Lithium Lithium toxicity has been reported in patients receiving enalapril and lithium concomitantly which was generally reversible. It is recommended that serum lithium levels be monitored frequently if enalapril is administered concomitantly with lithium.
7.5Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting, and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE inhibitor therapy including enalapril. 7.6 mTOR Inhibitors Patients taking concomitant mTOR inhibitor (e.g., temsirolimus, sirolimus, everolimus) therapy may be at increased risk for angioedema [see Warnings and Precautions ( 5.2 )] .
7.7Neprilysin Inhibitor Patients taking concomitant neprilysin inhibitors may be at increased risk for angioedema [see Warnings and Precautions ( 5.2 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Enalapril is not recommended in neonates and in pediatric patients with glomerular filtration rate <30 mL/min/1.73 m 2 . ( 8.4 ) Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Enalapril can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue enalapril as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the general U.S. population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Adverse reactions in the fetus or in neonates with a history of in utero exposure to enalapril maleate. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, oligohydramnios, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of pregnancy. Patients and physicians should be aware, however, that oligohydraminos may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to enalapril for hypotension, oliguria, and hyperkalemia. If oliguria or hypotension occurs in neonates with a history of in utero exposure to enalapril, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and substituting for disordered renal function.
8.2Lactation Risk Summary Enalapril and enalaprilat have been detected in human breast milk. Because of the potential for severe adverse reactions in the breastfed infant, including hypotension, hyperkalemia, and renal impairment, advise women not to breastfeed during treatment with enalapril.
8.4Pediatric Use Neonates with a history of in utero exposure to enalapril maleate If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Enalapril, which crosses the placenta, has been removed from neonatal circulation by peritoneal dialysis with some clinical benefit, and theoretically may be removed by exchange transfusion, although there is no experience with the latter procedure.
Pediatric patients with heart failure or asymptomatic left ventricular dysfunction Safety and effectiveness of enalapril have not been established in pediatric patients with heart failure or asymptomatic left ventricular dysfunction.
8.5Geriatric Use This drug is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
8.6Race ACE inhibitors, including enalapril, as monotherapy have an effect on blood pressure that is less in black patients than in non-bla… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Enalapril can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue enalapril as soon as possible. The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. In the general U.S. population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Clinical Considerations Adverse reactions in the fetus or in neonates with a history of in utero exposure to enalapril maleate. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, oligohydramnios, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of pregnancy. Patients and physicians should be aware, however, that oligohydraminos may not appear until after the fetus has sustained irreversible injury.
Closely observe infants with histories of in utero exposure to enalapril for hypotension, oliguria, and hyperkalemia. If oliguria or hypotension occurs in neonates with a history of in utero exposure to enalapril, support blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and substituting for disordered renal function.
🧒 Pediatric Use ▾
8.4Pediatric Use Neonates with a history of in utero exposure to enalapril maleate If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Enalapril, which crosses the placenta, has been removed from neonatal circulation by peritoneal dialysis with some clinical benefit, and theoretically may be removed by exchange transfusion, although there is no experience with the latter procedure.
Pediatric patients with heart failure or asymptomatic left ventricular dysfunction Safety and effectiveness of enalapril have not been established in pediatric patients with heart failure or asymptomatic left ventricular dysfunction.
🧓 Geriatric Use ▾
8.5Geriatric Use This drug is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Limited data are available in regard to overdosage in humans. Single oral doses of enalapril above 1,000 mg/kg and ≥1,775 mg/kg were associated with lethality in mice and rats, respectively. The most likely manifestation of overdosage would be hypotension, for which the usual treatment would be intravenous infusion of normal saline solution.
Enalaprilat may be removed from general circulation by hemodialysis and has been removed from neonatal circulation by peritoneal dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Enalapril, after hydrolysis to enalaprilat, inhibits angiotensin-converting enzyme (ACE) in human subjects and animals. ACE is a peptidyl dipeptidase that catalyzes the conversion of angiotensin I to the vasoconstrictor substance, angiotensin II. Angiotensin II also stimulates aldosterone secretion by the adrenal cortex.
The beneficial effects of enalapril in heart failure appear to result primarily from suppression of the renin-angiotensin-aldosterone system. Inhibition of ACE results in decreased plasma angiotensin II, which leads to decreased vasopressor activity and to decreased aldosterone secretion. Although the latter decrease is small, it results in small increases of serum potassium.
In hypertensive patients treated with enalapril maleate tablets alone for up to 48 weeks, mean increases in serum potassium of approximately 0.2 mEq/L were observed. In patients treated with enalapril maleate tablets plus a thiazide diuretic, there was essentially no change in serum potassium [see Warnings and Precautions ( 5.6 )] . Removal of angiotensin II negative feedback on renin secretion leads to increased plasma renin activity.
ACE is identical to kininase, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of enalapril remains to be elucidated.
12.2Pharmacodynamics Heart Failure In trials in patients treated with digitalis and diuretics, treatment with enalapril resulted in decreased systemic vascular resistance, blood pressure, pulmonary capillary wedge pressure and heart size, and increased cardiac output and exercise tolerance. Heart rate was unchanged or slightly reduced, and mean ejection fraction was unchanged or increased. There was a beneficial effect on severity of heart failure as measured by the New York Heart Association (NYHA) classification and on symptoms of dyspnea and fatigue.
Hemodynamic effects were observed after the first dose, and appeared to be maintained in uncontrolled studies lasting as long as four months. Effects on exercise tolerance, heart size, and severity and symptoms of heart failure were observed in placebo-controlled studies lasting from eight weeks to over one year.
12.3Pharmacokinetics The pharmacokinetics of ready-to-use enalapril maleate oral solution was shown to be bioequivalent to that of reconstituted enalapril maleate powder for oral solution under fasted conditions. Reconstituted enalapril maleate powder for oral solution was shown to be bioequivalent to Vasotec ® tablets. Reconstituted enalapril maleate powder for oral solution was also evaluated under fed and fasted conditions.
A high-fat meal reduced the C max of enalapril and enalaprilat by 46% and 36%, respectively. The exposure, as measured by AUC, to enalaprilat was reduced by 23%. The time to peak concentrations (C max ) was delayed by 20 minutes for enalapril and 62 minutes for enalaprilat.
The trough plasma concentrations of enalapril (from 6 to 12 hours) and enalaprilat (from 16 to 36 hours) are similar between fasted and fed administrations. Adults Following oral administration of enalapril maleate tablets, peak serum concentrations of enalapril occur within about one hour. Based on urinary recovery, the extent of absorption of enalapril is approximately 60%.
Enalapril absorption is not influenced by the presence of food in the gastrointestinal tract. Following absorption, enalapril is hydrolyzed to enalaprilat, which is a more potent angiotensin-converting enzyme inhibitor than enalapril; enalaprilat is poorly absorbed when administered orally. Peak serum concentrations of enalaprilat occur three to four hours after an oral dose of enalapril maleate.
Excretion of enalapril is primarily renal. Approximately 94% of the dose is recovered in the urine and feces as enalaprilat or enalapril. The principal components in urine are enalaprilat, accounting for about 40% of the dose, and… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/ STORAGE AND HANDLING Enalapril maleate oral solution is a ready-to-use solution that contains 1 mg/mL of enalapril maleate, USP. It is a clear, colorless oral solution with a mixed berry flavor, packaged in a 150 mL, white, round, high-density polyethylene bottle with a white, polypropylene, child-resistant cap and placed in a carton with tamper-evident seal. Each bottle contains 150 mL.
NDC 69452-237-46 Store refrigerated (2° to 8°C/36° to 46°F) in a tightly closed container. Protect from freezing and excessive heat. Patients may store enalapril maleate oral solution at room temperature (20° to 25°C/68° to 77°F) for up to 60 days.
📋 Description ▾
11 DESCRIPTION Enalapril maleate oral solution is the maleate salt of enalapril, the ethyl ester prodrug of a long-acting angiotensin-converting enzyme inhibitor, enalaprilat. Enalapril maleate is chemically described as (S)-1-[N-[1-(ethoxycarbonyl)-3-phenylpropyl]-L-alanyl]-L-proline, (Z)-2-butenedioate salt (1:1). Its empirical formula is C 20 H 28 N 2 O 5 •C 4 H 4 O 4 , and its structural formula is: Enalapril maleate, USP is an off-white, crystalline powder with a molecular weight of 492.52.
It is practically insoluble in n-heptane (non-polar organic solvent), slightly soluble in acetone (semi-polar organic solvent), sparingly soluble in water, soluble in alcohol, freely soluble in methanol and in dimethyl formamide. Enalapril maleate oral solution is a ready-to-use oral solution. Each 1 mL contains 1 mg of enalapril maleate, USP equivalent to 0.764 mg of enalapril.
Inactive ingredients include methylparaben, mixed berry flavor, propylene glycol, propylparaben, purified water, sorbitol solution 70%, and sucralose. It may also contain hydrochloric acid or sodium hydroxide for pH adjustment. Enalapril maleate oral solution is clear and colorless. structural formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Pregnancy Tell female patients of childbearing age about the consequences of exposure to enalapril during pregnancy. Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible.
Angioedema Angioedema, including laryngeal edema, may occur at any time during treatment with angiotensin-converting enzyme inhibitors, including enalapril. Advise patients to report immediately any signs or symptoms suggesting angioedema (swelling of face, extremities, eyes, lips, or tongue, or difficulty in swallowing or breathing) and to consult with the prescribing physician before taking more drug. Hypotension Caution patients to report lightheadedness, especially during the first few days of therapy.
If actual syncope occurs, tell patients to discontinue the drug until they have consulted with the prescribing physician. Tell patients that excessive perspiration and dehydration may lead to an excessive fall in blood pressure because of reduction in fluid volume. Other causes of volume depletion such as vomiting or diarrhea may also lead to a fall in blood pressure; advise patients to consult with their physician.
Hyperkalemia Tell patients to consult their physician prior to using salt substitutes containing potassium. Vasotec is a registered trademark of Valeant International Bermuda. Distributed by: Bionpharma Inc.
Princeton, NJ 08540 MADE IN INDIA FDA-06 December 2023 948026816
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Heart Failure, Mortality Trials In a multicenter, placebo-controlled clinical trial, 2,569 patients with all degrees of symptomatic heart failure and ejection fraction ≤35 percent were randomized to placebo or enalapril and followed for up to 55 months (SOLVD-Treatment). Use of enalapril was associated with an 11 percent reduction in all-cause mortality and a 30 percent reduction in hospitalization for heart failure. Diseases that excluded patients from enrollment in the study included severe stable angina (>2 attacks/day), hemodynamically significant valvular or outflow tract obstruction, renal failure (creatinine >2.5 mg/dL), cerebral vascular disease (e.g., significant carotid artery disease), advanced pulmonary disease, malignancies, active myocarditis and constrictive pericarditis.
The mortality benefit associated with enalapril does not appear to depend upon digitalis being present. A second multicenter trial used the SOLVD protocol for study of asymptomatic or minimally symptomatic patients. SOLVD-Prevention patients, who had left ventricular ejection fraction ≤35% and no history of symptomatic heart failure, were randomized to placebo (n = 2,117) or enalapril (n = 2,111) and followed for up to 5 years.
The majority of patients in the SOLVD-Prevention trial had a history of ischemic heart disease. A history of myocardial infarction was present in 80 percent of patients, current angina pectoris in 34 percent, and a history of hypertension in 37 percent. No statistically significant mortality effect was demonstrated in this population.
Enalapril-treated subjects had 32% fewer first hospitalizations for heart failure, and 32% fewer total heart failure hospitalizations. Compared to placebo, 32 percent fewer patients receiving enalapril developed symptoms of overt heart failure. Hospitalizations for cardiovascular reasons were also reduced.
There was an insignificant reduction in hospitalizations for any cause in the enalapril treatment group (for enalapril vs. placebo, respectively, 1,166 vs. 1,201 first hospitalizations, 2,649 vs. 2,840 total hospitalizations), although the study was not powered to look for such an effect.
The SOLVD-Prevention trial was not designed to determine whether treatment of asymptomatic patients with low ejection fraction would be superior, with respect to preventing hospitalization, to closer follow-up and use of enalapril at the earliest sign of heart failure. However, under the conditions of follow-up in the SOLVD-Prevention trial (every 4 months at the study clinic; personal physician as needed), 68% of patients on placebo who were hospitalized for heart failure had no prior symptoms recorded which would have signaled initiation of treatment.
The SOLVD-Prevention trial was also not designed to show whether enalapril modified the progression of underlying heart disease. In another multicenter, placebo-controlled trial (CONSENSUS) limited to patients with NYHA Class IV congestive heart failure and radiographic evidence of cardiomegaly, use of enalapril was associated with improved survival. The results are shown in the following table.
CONSENSUS Survival Rates SURVIVAL (%) Six Months One Year VASOTEC (n = 127) 74 64 Placebo (n = 126) 56 48 In both CONSENSUS and SOLVD-Treatment trials, patients were also usually receiving digitalis, diuretics or both.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility There was no evidence of a tumorigenic effect when enalapril was administered for 106 weeks to male and female rats at doses up to 90 mg/kg/day or for 94 weeks to male and female mice at doses up to 90 and 180 mg/kg/day, respectively. These doses are 26 times (in rats and female mice) and 13 times (in male mice) the maximum recommended human daily dose (MRHDD) when compared on a body surface area basis. Neither enalapril maleate nor the active diacid was mutagenic in the Ames microbial mutagen test with or without metabolic activation.
Enalapril was also negative in the following genotoxicity studies: rec-assay, reverse mutation assay with E. coli , sister chromatid exchange with cultured mammalian cells, and the micronucleus test with mice, as well as in an in vivo cytogenic study using mouse bone marrow. There were no adverse effects on reproductive performance of male and female rats treated with up to 90 mg/kg/day of enalapril (26 times the MRHDD when compared on a body surface area basis).
13.2Animal Toxicology and/or Pharmacology In several experimental published studies, rat pups exposed to daily enalapril from birth to post-natal Day 13 (the period of nephrogenesis in this species) developed irreversible renal toxicity. In contrast, treatment after post-natal Day 14 was not toxic to the more mature kidney. Rat kidney development at birth and at 14 days is similar to the human at mid-trimester and in infancy, respectively.
The toxic dosages in these studies were about 10X, on a mg/m 2 basis, the highest recommended oral (0.58 mg/kg/day) pediatric dosages to treat hypertension. Lower dosages were not studied.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - LABEL Bottle label
PRINCIPAL DISPLAY PANEL - CARTON Carton