
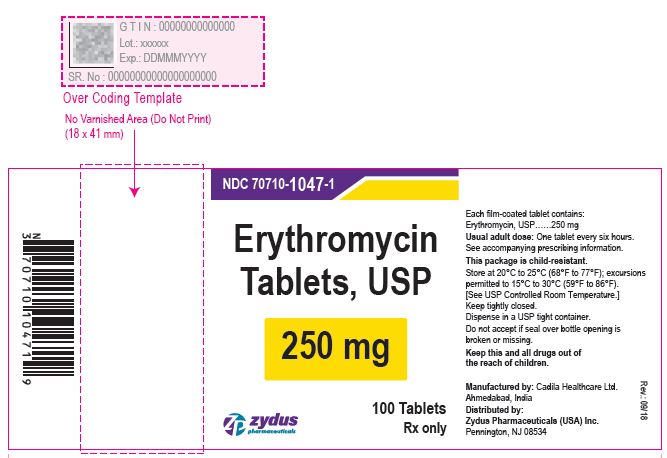
Erythromycin 250 mg Tablet, Film Coated, 100-count — NDC 70710-1047-1 (Billing 70710-1047-01)
This is a package of 100 tablets of Erythromycin 250 mg Tablet, Film Coated from Zydus Pharmaceuticals USA Inc., marketed since Jun 2023 and currently FDA-listed; retail pharmacies pay about $1.96 per tablet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 009260
- GCN: 40720
- GPI-14 (Medi-Span): 03100005000305
- HICL (First Databank): 004022
- AHFS class code: 08:12.12.04
- RxCUI (RxNorm): 197650
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Macrolide class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Erythromycin is used to treat certain infection caused by bacteria including infections of the ears, lungs, sinuses, skin, throat, and reproductive organs. Erythromycin is in a class of medications called macrolide antibiotics. It works by stopping the growth of bacteria. Antibiotics such as erythromycin will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- It’s an antibiotic for infections caused by susceptible bacteria. By mouth, it’s used for mild to moderate upper respiratory tract infections. The IV form covers additional infecti...
- It depends on the product. Ery-tab delayed-release tablets can be taken with or without meals, but work best on an empty stomach. Erythromycin ethylsuccinate tablets and suspension...
- Stomach upset is the most common. That includes nausea, vomiting, belly pain, diarrhea and loss of appetite. These tend to be more likely at higher doses. Call your doctor if they...
- Call for severe or lasting diarrhea, hives or swelling, a severe skin rash, a racing or irregular heartbeat, fainting, yellow skin or eyes, or hearing changes. These can signal ser...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Erythromycin — tap one for details:
Erythromycin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.955 | $195.52 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.93 | $193.27 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $3.39 | $338.81 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 70710-1047-01 You're viewing this | 100 TABLET, FILM COATED in 1 BOTTLE | $1.96 / ea | $195.52 | 2023-06-30 | — | Active |
| 70710-1047-03 70710-1047-3 Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $1.96 / ea | $58.66 | 2023-06-30 | — | Active |
| 70710-1047-05 70710-1047-5 | 500 TABLET, FILM COATED in 1 BOTTLE | — | — | 2023-06-30 | — | Active |
You're viewing one of 3 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($1.96 NADAC).
This pack accounts for about 1.1% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70710-1047-03?
What NDC number is used to bill for this package of Erythromycin 250 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Erythromycin 250 mg 00093-5571-01 | Teva | 100 tablets | $1.955 | AB | Availability likely | — |
| Erythromycin 250 mg 13668-0606-01 | Torrent | 100 tablets | $1.955 | AB | Availability likely | — |
| Erythromycin 250 mg 24338-0102-03 | Arbor | 30 tablets | $1.955 | AB | Availability likely | — |
| Erythromycin 250 mg 52536-0103-03 | Wilshire | 30 tablets | $1.955 | AB | Availability likely | — |
| Erythromycin 250 mgthis 70710-1047-01 | Zydus | 100 tablets | $1.955 | AB | Availability likely | — |
| Erythromycin 250 mg 75834-0242-01 | Nivagen | 100 tablets | $1.955 | AB | Discontinued | — |
| Erythromycin 250 mg 46708-0397-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 50090-5918-05 | A-S | 3 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 51407-0855-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 55289-0075-03 | PD-Rx | 3 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 62332-0397-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 67877-0762-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 70771-1548-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 71209-0100-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 72241-0036-05 | Modavar | 100 tablets | — | AB | FDA listed | — |
| Erythromycin 250 mg 73082-0010-01 | Orange | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE To reduce the development of drug-resistant bacteria and maintain the effectiveness of erythromycin tablets, USP and other antibacterial drugs, erythromycin tablets, USP should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Erythromycin tablets, USP are indicated in the treatment of infections caused by susceptible strains of the designated microorganisms in the diseases listed below: Upper respiratory tract infections of mild to moderate degree caused by Streptococcus pyogenes ; Streptococcus pneumoniae ; Haemophilus influenzae (when used concomitantly with adequate doses of sulfonamides, since many strains of H. influenzae are not susceptible to the erythromycin concentrations ordinarily achieved). (See appropriate sulfonamide labeling for prescribing information).
Lower respiratory tract infections of mild to moderate severity caused by Streptococcus pyogenes or Streptococcus pneumoniae . Listeriosis caused by Listeria monocytogenes . Respiratory tract infections due to Mycoplasma pneumoniae .
Skin and skin structure infections of mild to moderate severity caused by Streptococcus pyogenes or Staphylococcus aureus (resistant staphylococci may emerge during treatment). Pertussis (whooping cough) caused by Bordetella pertussis . Erythromycin is effective in eliminating the organism from the nasopharynx of infected individuals, rendering them noninfectious.
Some clinical studies suggest that erythromycin may be helpful in the prophylaxis of pertussis in exposed susceptible individuals. Diphtheria: Infections due to Corynebacterium diphtheriae , as an adjunct to antitoxin, to prevent establishment of carriers and to eradicate the organism in carriers. Erythrasma: In the treatment of infections due to Corynebacterium minutissimum .
Intestinal amebiasis caused by Entamoeba histolytica (oral erythromycins only). Extraenteric amebiasis requires treatment with other agents. Acute pelvic inflammatory disease caused by Neisseria gonorrhoeae : Erythrocin ® Lactobionate-I.V.
(erythromycin lactobionate for injection, USP) followed by erythromycin base orally, as an alternative drug in treatment of acute pelvic inflammatory disease caused by N. gonorrhoeae in female patients with a history of sensitivity to penicillin. Patients should have a serologic test for syphilis before receiving erythromycin as treatment of gonorrhea and a follow-up serologic test for syphilis after 3 months. Erythromycins are indicated for treatment of the following infections caused by Chlamydia trachomatis : conjunctivitis of the newborn, pneumonia of infancy and urogenital infections during pregnancy.
When tetracyclines are contraindicated or not tolerated, erythromycin is indicated for the treatment of uncomplicated urethral, endocervical or rectal infections in adults due to Chlamydia trachomatis . 3 When tetracyclines are contraindicated or not tolerated, erythromycin is indicated for the treatment of nongonococcal urethritis caused by Ureaplasma urealyticum . 3 Primary syphilis caused by Treponema pallidum .
Erythromycin (oral forms only) is an alternative choice of treatment for primary syphilis in patients allergic to the penicillins. In treatment of primary syphilis, spinal fluid should be examined before treatment and as part of the follow-up after therapy. Legionnaires' Disease caused by Legionella pneumophila .
Although no controlled clinical efficacy studies have been conducted, in vitro and limited preliminary clinical data suggest that erythromycin may be effective in treating Legionnaires' Disease. Prophylaxis Prevention of Initial Attacks of Rheumatic Fever Penicillin is considered by the American… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION In most patients, erythromycin tablets are well absorbed and may be dosed orally without regard to meals. However, optimal blood levels are obtained when erythromycin tablets are given in the fasting state (at least 1/2 hour and preferably 2 hours before meals). Adults The usual dosage of Erythromycin Tablets is one 250 mg tablet four times daily in equally spaced doses or one 500 mg tablet every 12 hours.
Dosage may be increased up to 4 g per day according to the severity of the infection. However, twice-a-day dosing is not recommended when doses larger than 1 g daily are administered. Children Age, weight and severity of the infection are important factors in determining the proper dosage.
The usual dosage is 30 mg/kg/day to 50 mg/kg/day, in equally divided doses. For more severe infections this dosage may be doubled but should not exceed 4 g per day. In the treatment of streptococcal infections of the upper respiratory tract (e.g., tonsillitis or pharyngitis), the therapeutic dosage of erythromycin should be administered for at least ten days.
The American Heart Association suggests a dosage of 250 mg of erythromycin orally, twice a day in long-term prophylaxis of streptococcal upper respiratory tract infections for the prevention of recurring attacks of rheumatic fever in patients allergic to penicillin and sulfonamides. 1 Conjunctivitis of the Newborn Caused by Chlamydia trachomatis Oral erythromycin suspension 50 mg/kg/day in 4 divided doses for at least 2 weeks. 3 Pneumonia of Infancy Caused by Chlamydia trachomatis Although the optimal duration of therapy has not been established, the recommended therapy is oral erythromycin suspension 50 mg/kg/day in 4 divided doses for at least 3 weeks.
Urogenital Infections During Pregnancy Due to Chlamydia trachomatis Although the optimal dose and duration of therapy have not been established, the suggested treatment is 500 mg of erythromycin by mouth four times a day on an empty stomach for at least 7 days. For women who cannot tolerate this regimen, a decreased dose of one erythromycin 500 mg tablet orally every 12 hours or 250 mg by mouth four times a day should be used for at least 14 days. 3 For adults with uncomplicated urethral, endocervical or rectal infections caused by Chlamydia trachomatis, when tetracycline is contraindicated or not tolerated 500 mg of erythromycin by mouth four times a day for at least 7 days.
3 For patients with nongonococcal urethritis caused by Ureaplasma urealyticum when tetracycline is contraindicated or not tolerated 500 mg of erythromycin by mouth four times a day for at least seven days. 3 Primary syphilis 30 to 40 g given in divided doses over a period of 10 days to 15 days. Acute Pelvic Inflammatory Disease Caused by N. gonorrhoeae 500 mg Erythrocin ® Lactobionate-I.V.
(erythromycin lactobionate for injection, USP) every 6 hours for 3 days, followed by 500 mg of erythromycin base orally every 12 hours for 7 days. Intestinal Amebiasis Adults 500 mg every 12 hours or 250 mg every 6 hours for 10 days to 14 days. Children 30 mg/kg/day to 50 mg/kg/day in divided doses for 10 days to 14 days.
Pertussis Although optimal dosage and duration have not been established, doses of erythromycin utilized in reported clinical studies were 40 mg/kg/day to 50 mg/kg/day, given in divided doses for 5 days to 14 days. Legionnaires' Disease Although optimal dosage has not been established, doses utilized in reported clinical data were 1g to 4g daily in divided doses.
⛔ Contraindications ▾
CONTRAINDICATIONS Erythromycin is contraindicated in patients with known hypersensitivity to this antibiotic. Erythromycin is contraindicated in patients taking terfenadine, astemizole, cisapride, pimozide, ergotamine or dihydroergotamine. (See PRECAUTIONS - Drug Interactions ).
Do not use erythromycin concomitantly with HMG CoA reductase inhibitors (statins) that are extensively metabolized by CYP 3A4 (lovastatin or simvastatin), due to the increased risk of myopathy, including rhabdomyolysis.
⚠️ Warnings ▾
WARNINGS Hepatotoxicity There have been reports of hepatic dysfunction, including increased liver enzymes and hepatocellular and/or cholestatic hepatitis, with or without jaundice, occurring in patients receiving oral erythromycin products. QT Prolongation Erythromycin has been associated with prolongation of the QT interval and infrequent cases of arrhythmia. Cases of torsades de pointes have been spontaneously reported during postmarketing surveillance in patients receiving erythromycin.
Fatalities have been reported. Erythromycin should be avoided in patients with known prolongation of the QT interval, patients with ongoing proarrhythmic conditions such as uncorrected hypokalemia or hypomagnesemia, clinically significant bradycardia and in patients receiving Class IA (quinidine, procainamide) or Class III (dofetilide, amiodarone, sotalol) antiarrhythmic agents. Elderly patients may be more susceptible to drug-associated effects on the QT interval.
Syphilis in Pregnancy There have been reports suggesting that erythromycin does not reach the fetus in adequate concentration to prevent congenital syphilis. Infants born to women treated during pregnancy with oral erythromycin for early syphilis should be treated with an appropriate penicillin regimen. Clostridium difficile Associated Diarrhea Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including erythromycin tablets and may range in severity from mild diarrhea to fatal colitis.
Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C.difficile . C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile and surgical evaluation should be instituted as clinically indicated. Drug Interactions Serious adverse reactions have been reported in patients taking erythromycin concomitantly with CYP3A4 substrates. These include colchicine toxicity with colchicine; rhabdomyolysis with simvastatin, lovastatin and atorvastatin; and hypotension with calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem) (see PRECAUTIONS - Drug Interactions ).
There have been post-marketing reports of colchicine toxicity with concomitant use of erythromycin and colchicine. This interaction is potentially life-threatening and may occur while using both drugs at their recommended doses (see PRECAUTIONS - Drug Interactions ). Rhabdomyolysis with or without renal impairment has been reported in seriously ill patients receiving erythromycin concomitantly with lovastatin.
Therefore, patients receiving concomitant lovastatin and erythromycin should be carefully monitored for creatine kinase (CK) and serum transaminase levels. (See package insert for lovastatin).
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The most frequent side effects of oral erythromycin preparations are gastrointestinal and are dose-related. They include nausea, vomiting, abdominal pain, diarrhea and anorexia. Symptoms of hepatitis, hepatic dysfunction and/or abnormal liver function test results may occur (See WARNINGS ).
Onset of pseudomembranous colitis symptoms may occur during or after antibacterial treatment (See WARNINGS ). Erythromycin has been associated with QT prolongation and ventricular arrhythmias, including ventricular tachycardia and torsades de pointes (See WARNINGS ). Allergic reactions ranging from urticaria to anaphylaxis have occurred.
Skin reactions ranging from mild eruptions to erythema multiforme, Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported rarely. There have been reports of interstitial nephritis coincident with erythromycin use. There have been rare reports of pancreatitis and convulsions.
There have been isolated reports of reversible hearing loss occurring chiefly in patients with renal insufficiency and in patients receiving high doses of erythromycin. To report SUSPECTED ADVERSE REACTIONS, contact Zydus Pharmaceuticals (USA) Inc. at 1-877-993-8779 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
Drug Interactions Serious adverse reactions have been reported in patients taking erythromycin concomitantly with CYP3A4 substrates. These include colchicine toxicity with colchicine; rhabdomyolysis with simvastatin, lovastatin and atorvastatin; and hypotension with calcium channel blockers metabolized by CYP3A4 (e.g., verapamil, amlodipine, diltiazem) (see PRECAUTIONS - Drug Interactions ). There have been post-marketing reports of colchicine toxicity with concomitant use of erythromycin and colchicine.
This interaction is potentially life-threatening and may occur while using both drugs at their recommended doses (see PRECAUTIONS - Drug Interactions ). Rhabdomyolysis with or without renal impairment has been reported in seriously ill patients receiving erythromycin concomitantly with lovastatin. Therefore, patients receiving concomitant lovastatin and erythromycin should be carefully monitored for creatine kinase (CK) and serum transaminase levels.
(See package insert for lovastatin).
Drug Interactions Theophylline Erythromycin use in patients who are receiving high doses of theophylline may be associated with an increase in serum theophylline levels and potential theophylline toxicity. In case of theophylline toxicity and/or elevated serum theophylline levels, the dose of theophylline should be reduced while the patient is receiving concomitant erythromycin therapy. There have been published reports suggesting that when oral erythromycin is given concurrently with theophylline there is a decrease in erythromycin serum concentrations of approximately 35%.
The mechanism by which this interaction occurs is unknown. The decrease in erythromycin concentrations due to co-administration of theophylline could result in subtherapeutic concentrations of erythromycin. Hypotension, bradyarrhythmias and lactic acidosis have been observed in patients receiving concurrent verapamil, belonging to the calcium channel blockers drug class.
Concomitant administration of erythromycin and digoxin has been reported to result in elevated digoxin serum levels. There have been reports of increased anticoagulant effects when erythromycin and oral anticoagulants were used concomitantly. Increased anticoagulation effects due to interactions of erythromycin with oral anticoagulants may be more pronounced in the elderly.
Erythromycin is a substrate and inhibitor of the 3A isoform subfamily of the cytochrome p450 enzyme system (CYP3A). Coadministration of erythromycin and a drug primarily metabolized by CYP3A may be associated with elevations in drug concentrations that could increase or prolong both the therapeutic and adverse effects of the concomitant drug. Dosage adjustments may be considered and when possible, serum concentrations of drugs primarily metabolized by CYP3A should be monitored closely in patients concurrently receiving erythromycin.
The following are examples of some clinically significant CYP3A based drug interactions. Interactions with other drugs metabolized by the CYP3A isoform are also possible. The following CYP3A based drug interactions have been observed with erythromycin products in post-marketing experience: Ergotamine/dihydroergotamine Post-marketing reports indicate that co-administration of erythromycin with ergotamine or dihydroergotamine has been associated with acute ergot toxicity characterized by vasospasm and ischemia of the extremities and other tissues including the central nervous system.
Concomitant administration of erythromycin with ergotamine or dihydroergotamine is contraindicated (see CONTRAINDICATIONS ). Triazolobenzodiazepines (such as triazolam and alprazolam) and related benzodiazepines Erythromycin has been reported to decrease the clearance of triazolam and midazolam and thus, may increase the pharmacologic effect of these benzodiazepines. HMG-CoA Reductase Inhibitors Erythromycin has been reported to increase concentrations of HMG-CoA reductase inhibitors (e.g., lovastatin and simvastatin).
Rare report… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects There is no evidence of teratogenicity or any other adverse effect on reproduction in female rats fed erythromycin base by oral gavage at 350 mg/kg/day (approximately twice the maximum recommended human dose on a body surface area) prior to and during mating, during gestation and through weaning. No evidence of teratogenicity or embryotoxicity was observed when erythromycin base was given by oral gavage to pregnant rats and mice at 700 mg/kg/day and to pregnant rabbits at 125 mg/kg/day (approximately 1 to 3 times the maximum recommended human dose).
🧒 Pediatric Use ▾
Pediatric Use See INDICATIONS AND USAGE and DOSAGE AND ADMINISTRATION .
🧓 Geriatric Use ▾
Geriatric Use Elderly patients, particularly those with reduced renal or hepatic function, may be at increased risk for developing erythromycin-induced hearing loss. (See ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION ). Elderly patients may be more susceptible to development of torsades de pointes arrhythmias than younger patients (See WARNINGS ).
Elderly patients may experience increased effects of oral anticoagulant therapy while undergoing treatment with erythromycin (See PRECAUTIONS - Drug Interactions ). Erythromycin Tablets (250 mg) contain 13.364 mg (0.6 mEq) of sodium per tablet. Erythromycin Tablets (500 mg) contain 26.728 mg (1.2 mEq) of sodium per tablet.
The geriatric population may respond with a blunted natriuresis to salt loading. This may be clinically important with regard to such diseases as congestive heart failure.
🆘 Overdosage ▾
OVERDOSAGE In case of overdosage, erythromycin should be discontinued. Overdosage should be handled with the prompt elimination of unabsorbed drug and all other appropriate measures should be instituted. Erythromycin is not removed by peritoneal dialysis or hemodialysis.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Orally administered erythromycin base and its salts are readily absorbed in the microbiologically active form. Interindividual variations in the absorption of erythromycin are, however, observed and some patients do not achieve optimal serum levels. Erythromycin is largely bound to plasma proteins.
After absorption, erythromycin diffuses readily into most body fluids. In the absence of meningeal inflammation, low concentrations are normally achieved in the spinal fluid but the passage of the drug across the blood-brain barrier increases in meningitis. Erythromycin crosses the placental barrier, but fetal plasma levels are low.
The drug is excreted in human milk. Erythromycin is not removed by peritoneal dialysis or hemodialysis. In the presence of normal hepatic function, erythromycin is concentrated in the liver and is excreted in the bile; the effect of hepatic dysfunction on biliary excretion of erythromycin is not known.
After oral administration, less than 5% of the administered dose can be recovered in the active form in the urine. Optimal blood levels are obtained when erythromycin tablets are given in the fasting state (at least 1/2 hour and preferably 2 hours before meals). Bioavailability data are available from Arbor Pharmaceuticals.
Microbiology Mechanism of Action Erythromycin acts by inhibition of protein synthesis by binding 50S ribosomal subunits of susceptible organisms. It does not affect nucleic acid synthesis. Resistance The major route of resistance is modification of the 23S rRNA in the 50S ribosomal subunit to insensitivity while efflux can also be significant.
Interactions with Other Antimicrobials Antagonism exists in vitro between erythromycin and clindamycin, lincomycin and chloramphenicol. Antimicrobial Activity Erythromycin has been shown to be active against most isolates of the following bacteria both in vitro and in clinical infections as described in the INDICATIONS AND USAGE section. Gram-positive Bacteria: Corynebacterium diphtheriae Corynebacterium minutissimum Listeria monocytogenes Staphylococcus aureus (resistant organisms may emerge during treatment) Streptococcus pneumoniae Streptococcus pyogenes Gram-negative Bacteria: Bordetella pertussis Haemophilus influenzae Legionella pneumophila Neisseria gonorrhoeae Other Microorganisms: Chlamydia trachomatis Entamoeba histolytica Mycoplasma pneumoniae Treponema pallidum Ureaplasma urealyticum The following in vitro data are available, but their clinical significance is unknown.
At least 90% of the following bacteria exhibit in vitro minimum inhibitory concentration (MIC) less than or equal to the susceptible breakpoint for erythromycin. However, the efficacy of erythromycin in treating clinical infections due to these bacteria has not been established in adequate and well controlled clinical trials. Gram-positive Bacteria: Viridans group streptococci Gram-negative Bacteria: Moraxella catarrhalis Susceptibility Testing For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Erythromycin Tablets, USP 250 mg are light pink, film coated, oval shaped tablet, debossed with "||||"on one side and plain on the other side and are supplied as follows: NDC 70710-1047-3 in bottles of 30 tablets with child-resistant closure. NDC 70710-1047-1 in bottles of 100 tablets with child-resistant closure. NDC 70710-1047-5 in bottles of 500 tablets.
Erythromycin Tablets, USP 500 mg are light pink, film coated, oval shaped tablet, debossed with "1048" on one side and plain on the other side and are supplied as follows: NDC 70710-1048-3 in bottles of 30 tablets with child-resistant closure. NDC 70710-1048-1 in bottles of 100 tablets with child-resistant closure. NDC 70710-1048-5 in bottles of 500 tablets.
Recommended storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature.]
📋 Description ▾
DESCRIPTION Erythromycin tablets, USP are an antibacterial product containing erythromycin, USP, in a unique, nonenteric film coating for oral administration. Erythromycin tablets are available in two strengths containing either 250 mg or 500 mg of erythromycin base. Erythromycin is produced by a strain of Saccharopolyspora erythraea (formerly Streptomyces erythraeus ) and belongs to the macrolide group of antibiotics.
It is basic and readily forms salts with acids. Erythromycin is a white or slightly yellow powder or colorless or slightly yellow crystals, very slightly soluble to practically insoluble in water and soluble in alcohol, in chloroform and in ether. Erythromycin is known chemically as (3 R *,4 S *,5 S *,6 R *,7 R *,9 R *,11 R *,12 R *,13 S *,14 R *)-4-[(2,6-Dideoxy-3- C -methyl-3- O -methyl-α- L -ribo-hexopyranosyl)oxy]-14-ethyl-7,12,13-trihydroxy-3,5,7,9,11,13-hexamethyl-6-[[3,4,6-trideoxy-3-(dimethylamino)-β- D -xylo-hexopyranosyl]oxy]oxacyclotetradecane-2,10-dione.
The molecular formula is C 37 H 67 NO 13 and the molecular weight is 733.93. The structural formula is: Inactive Ingredients Colloidal silicon dioxide, crospovidone, croscarmellose sodium, D&C red #30 aluminium lake, hydroxypropyl cellulose, hypromellose phthalate, hypromellose, iron oxide red, magnesium stearate, microcrystalline cellulose, polyethylene glycol, povidone (k-30), povidone (k-90), propylene glycol, sodium citrate dihydrate, sorbic acid, sodium hydroxide, sorbitan monooleate, titanium dioxide and talc.
Additionally, each 250 mg tablets contain iron oxide yellow. Image
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including erythromycin tablets should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When erythromycin tablets are prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by erythromycin tablets or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General Prescribing erythromycin tablets in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. Since erythromycin is principally excreted by the liver, caution should be exercised when erythromycin is administered to patients with impaired hepatic function. (See CLINICAL PHARMACOLOGY and WARNINGS ).
Exacerbation of symptoms of myasthenia gravis and new onset of symptoms of myasthenic syndrome has been reported in patients receiving erythromycin therapy. There have been reports of infantile hypertrophic pyloric stenosis (IHPS) occurring in infants following erythromycin therapy. In one cohort of 157 newborns who were given erythromycin for pertussis prophylaxis, seven neonates (5%) developed symptoms of non-bilious vomiting or irritability with feeding and were subsequently diagnosed as having IHPS requiring surgical pyloromyotomy.
A possible dose-response effect was described with an absolute risk of IHPS of 5.1% for infants who took erythromycin for 8 days to 14 days and 10% for infants who took erythromycin for 15 days to 21 days. 2 Since erythromycin may be used in the treatment of conditions in infants which are associated with significant mortality or morbidity (such as pertussis or neonatal Chlamydia trachomatis infections), the benefit of erythromycin therapy needs to be weighed against the potential risk of developing IHPS. Parents should be informed to contact their physician if vomiting or irritability with feeding occurs.
Prolonged or repeated use of erythromycin may result in an overgrowth of nonsusceptible bacteria or fungi. If superinfection occurs, erythromycin should be discontinued and appropriate therapy instituted. When indicated, incision and drainage or other surgical procedures should be performed in conjunction with antibiotic therapy.
Observational studies in humans have reported cardiovascular malformations after exposure to drug products containing erythromycin during early pregnancy. Information for Patients Patients should be counseled that antibacterial drugs including erythromycin tablets should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold).
When erythromycin tablets are prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by erythromycin tablets or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued.
Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible. Drug Interactions Theophylline Erythromycin use in patients who are receiving high doses of theophylline may be associated with an increase in serum theophylline levels and potential theophylline toxicity.
In case of theophylline toxicity and/or elevated serum theophylline levels, the dose of theophylline should be reduced while the patient is receiving concomitant erythromycin therapy. There have been published reports suggesting that when oral erythromycin is given concurrently with theophylline there is a decrease in erythromycin serum concentrations of approximately 35%. The mechanism by which this interaction occurs is unknown.
The decrease in erythromycin concentrations due to co-administration of theophylline could result in… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Erythromycin is excreted in human milk. Caution should be exercised when erythromycin is administered to a nursing woman.
📚 References ▾
REFERENCES Committee on Rheumatic Fever, Endocarditis, and Kawasaki Disease of the Council on Cardiovascular Disease in the Young, the American Heart Association: Prevention of Rheumatic Fever. Circulation. 78(4):1082-1086, October 1988. Honein, M.A., et. al.: Infantile hypertrophic pyloric stenosis after pertussis prophylaxis with erythromycin: a case review and cohort study. The Lancet 1999:354 (9196): 2101-5. Data on file, Arbor Pharmaceuticals, LLC.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 70710-1047-1 in bottle of 100 tablets Erythromycin Tablets USP, 250 mg Rx only 100 tablets ZYDUS NDC 70710-1048-1 in bottle of 100 tablets Erythromycin Tablets USP, 500 mg Rx only 100 tablets ZYDUS Erythromycine Tablets, 250 mg Erythromycin Tablets, 500 mg