
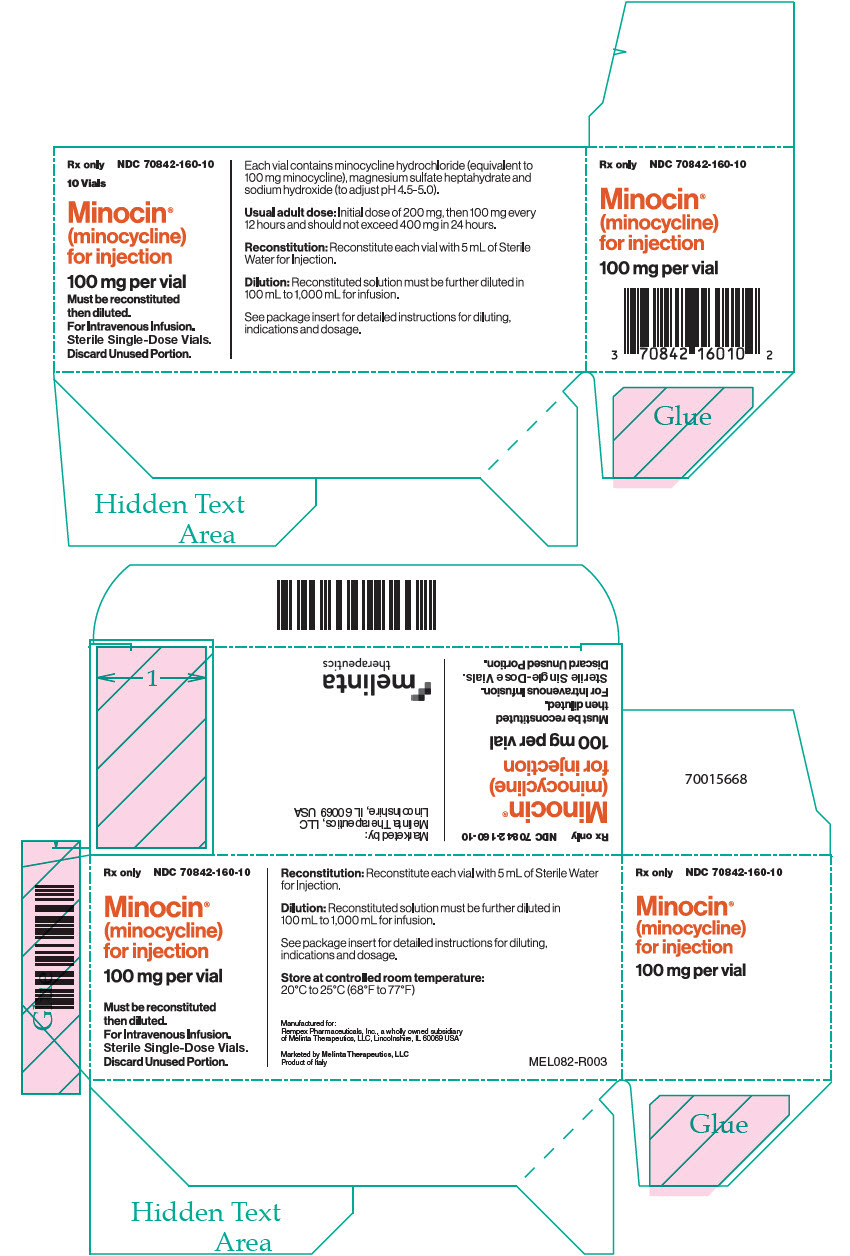
Minocin minocycline hydrochloride 100 mg Injection, 10 vials
Other active recalls for Minocycline Hydrochloride (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Tetracycline-class Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Good news — standard minocycline oral capsules and tablets can be taken with or without food, so you have flexibility there. The most important thing is to take it with a full glas...
- Can I take my minocycline capsule or tablet with food, or does it have to be on an empty stomach?
- The extended-release tablets for acne are typically taken once daily for 12 weeks. As with most acne treatments, you likely won't see dramatic results overnight — it takes time for...
- I've been prescribed the extended-release minocycline tablets for acne. How long does it take to work, and how long do I take it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Minocycline Hydrochloride — tap one for details:
Minocycline Hydrochloride may be associated with lower levels of 11 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
269 mg
UNII SK47B8698T
A mineral compound containing magnesium, sulfate, and water molecules. Used in medicines as a laxative agent and sometimes as a filler or anti-caking ingredient to improve powder flow and stability.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $303.74 | $3,037.44 / 10 injection |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2265 | No ASP payment limit on file for J2265 this quarter. | |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Minocin 100 mgthis 70842-0160-10 | Melinta | 10 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9084802 ↗ | Method of use | U-282 | May 12, 2031 |
| US 9278105 ↗ | Method of use | U-282 | May 12, 2031 |
| US 11944634 ↗ | Drug product | — | Oct 16, 2032 |
| US 12161656 ↗ | Drug product | — | May 12, 2031 |
Is there a generic version of MINOCIN 100 MG VIAL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70842-0160-10 You're viewing this | 10 VIAL in 1 CARTON (70842-160-10) / 1 INJECTION in 1 VIAL (70842-160-01) | 2013-04-19 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE MINOCIN ® Intravenous is indicated in the treatment of the following infections due to susceptible isolates of the designated bacteria: Rocky Mountain spotted fever, typhus fever and the typhus group, Q fever, rickettsialpox and tick fevers caused by rickettsiae. Respiratory tract infections caused by Mycoplasma pneumoniae . Lymphogranuloma venereum caused by Chlamydia trachomatis .
Psittacosis (Ornithosis) due to Chlamydophila psittaci . Trachoma caused by Chlamydia trachomatis , although the infectious agent is not always eliminated, as judged by immunofluorescence. Inclusion conjunctivitis caused by Chlamydia trachomatis .
Nongonococcal urethritis, endocervical, or rectal infections in adults caused by Ureaplasma urealyticum or Chlamydia trachomatis. Relapsing fever due to Borrelia recurrentis . Plague due to Yersinia pestis .
Tularemia due to Francisella tularensis . Cholera caused by Vibrio cholerae . Campylobacter fetus infections caused by Campylobacter fetus .
Brucellosis due to Brucella species (in conjunction with streptomycin). Bartonellosis due to Bartonella bacilliformis . Granuloma inguinale caused by Klebsiella granulomatis .
Minocycline is indicated for the treatment of infections caused by the following Gram-negative bacteria when bacteriologic testing indicates appropriate susceptibility to the drug: Escherichia coli . Enterobacter aerogenes . Shigella species .
Acinetobacter species . Respiratory tract infections caused by Haemophilus influenzae . Respiratory tract and urinary tract infections caused by Klebsiella species .
MINOCIN ® Intravenous is indicated for the treatment of infections caused by the following Gram-positive bacteria when bacteriologic testing indicates appropriate susceptibility to the drug: Upper respiratory tract infections caused by Streptococcus pneumoniae. Skin and skin structure infections caused by Staphylococcus aureus (Note: Minocycline is not the drug of choice in the treatment of any type of staphylococcal infection.) When penicillin is contraindicated, minocycline is an alternative drug in the treatment of the following infections: Meningitis due to Neisseria meningitidis .
Syphilis caused by Treponema pallidum subspecies pallidum . Yaws caused by Treponema pallidum subspecies pertenue . Listeriosis due to Listeria monocytogenes .
Anthrax due to Bacillus anthracis . Vincent's infection caused by Fusobacterium fusiforme. Actinomycosis caused by Actinomyces israelii .
Infections caused by Clostridium species . In acute intestinal amebiasis , minocycline may be a useful adjunct to amebicides. In severe acne , minocycline may be useful adjunctive therapy.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of MINOCIN ® (minocycline) for Injection and other antibacterial drugs, MINOCIN ® (minocycline) for Injection should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION THE USUAL DOSAGE AND FREQUENCY OF ADMINISTRATION OF MINOCYCLINE DIFFERS FROM THAT OF THE OTHER TETRACYCLINES. EXCEEDING THE RECOMMENDED DOSAGE MAY RESULT IN AN INCREASED INCIDENCE OF SIDE EFFECTS. Note: Rapid administration is to be avoided.
Parenteral therapy is indicated only when oral therapy is not adequate or tolerated. Oral therapy should be instituted as soon as possible. If intravenous therapy is given over prolonged periods of time, thrombophlebitis may result.
For Pediatric Patients above 8 years of Age Usual pediatric dose: Initial dose of 4 mg/kg, then 2 mg/kg administered over 60 minutes every 12 hours, not to exceed the usual adult dose. Adults Usual adult dose: Initial dose of 200 mg, then 100 mg administered over 60 minutes every 12 hours and should not exceed 400 mg in 24 hours. The lyophilized powder should be reconstituted with 5 mL Sterile Water for Injection USP and immediately further diluted in 100 mL to 1,000 mL with Sodium Chloride Injection USP, Dextrose Injection USP, or Dextrose and Sodium Chloride Injection USP, or in 250 mL to 1000 mL Lactated Ringer's Injection USP, but not with other solutions containing calcium because a precipitate may form especially in neutral and alkaline solutions.
When diluted in compatible solutions, the pH usually ranges from 4.5 to 6.0. Once diluted into an intravenous bag, MINOCIN ® for Injection may be stored either at room temperature for up to 4 hours or refrigerated at 2 to 8°C (36 to 46°F) for up to 24 hours. Any unused portions must be discarded after that period.
The pharmacokinetics of minocycline in patients with renal impairment (CL CR <80 mL/min) have not been fully characterized. Current data are insufficient to determine if a dosage adjustment is warranted. The total daily dosage should not exceed 200 mg in 24 hours in patients with renal impairment.
However, due to the anti-anabolic effect of tetracyclines, BUN and creatinine should be monitored (See WARNINGS ). Because MINOCIN (minocycline) for Injection contains magnesium sulfate heptahydrate, serum levels of magnesium should be monitored in patients with renal impairment (See DESCRIPTION , PRECAUTIONS ). Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Incompatibilities Additives or other medications should not be added to MINOCIN single-dose vials or infused simultaneously through the same intravenous line including Y-connectors. If the same intravenous line is used for sequential infusion of additional medications, the line should be flushed before and after infusion of MINOCIN with Sodium Chloride Injection USP, Dextrose Injection USP, Dextrose and Sodium Chloride Injection USP, or Lactated Ringer's Injection USP.
⛔ Contraindications ▾
CONTRAINDICATIONS This drug is contraindicated in persons who have shown hypersensitivity to any of the tetracyclines or to any of the components of the product formulation.
⚠️ Warnings ▾
WARNINGS Tooth Development MINOCIN, like other tetracycline-class antibacterials, can cause fetal harm when administered to a pregnant woman. If any tetracycline is used during pregnancy, or if the patient becomes pregnant while taking these drugs, the patient should be apprised of the potential hazard to the fetus. The use of drugs of the tetracycline class during tooth development (last half of pregnancy, infancy, and childhood to the age of 8 years) may cause permanent discoloration of the teeth (yellow-gray-brown).
This adverse reaction is more common during long-term use of the drugs but has been observed following repeated short-term courses. Enamel hypoplasia has also been reported. Tetracycline drugs, therefore, should not be used during tooth development unless other drugs are not likely to be effective or are contraindicated.
Skeletal Development All tetracyclines form a stable calcium complex in any bone-forming tissue. A decrease in the fibula growth rate has been observed in premature human infants given oral tetracycline in doses of 25 mg/kg every six hours. This reaction was shown to be reversible when the drug was discontinued.
Results of animal studies indicate that tetracyclines cross the placenta, are found in fetal tissues, and can have toxic effects on the developing fetus (often related to retardation of skeletal development). Evidence of embryotoxicity has been noted in animals treated early in pregnancy. Dermatologic Reaction Drug Rash with Eosinophilia and Systemic Symptoms (DRESS) including fatal cases have been reported with minocycline use.
Fixed drug eruptions have occurred with minocycline and other tetracyclines. Worsening severity upon subsequent administrations, including generalized bullous fixed drug eruption, has been observed with other tetracyclines (see ADVERSE REACTIONS ). If severe skin reactions occur, discontinue MINOCIN immediately and institute appropriate therapy.
Anti-anabolic Action The anti-anabolic action of the tetracyclines may cause an increase in BUN. While this is not a problem in those with normal renal function, in patients with significantly impaired function, higher serum levels of tetracycline may lead to azotemia, hyperphosphatemia, and acidosis. Under such conditions, monitoring of creatinine and BUN is recommended, and the total daily dosage should not exceed 200 mg in 24 hours (See DOSAGE AND ADMINISTRATION ).
If renal impairment exists, even usual oral or parenteral doses may lead to systemic accumulation of the drug and possible liver toxicity. Photosensitivity Photosensitivity manifested by an exaggerated sunburn reaction has been observed in some individuals taking tetracyclines. This has been reported with minocycline.
Central Nervous System Effects Central nervous system side effects including light-headedness, dizziness or vertigo have been reported. Patients who experience these symptoms should be cautioned about driving vehicles or using hazardous machinery while on minocycline therapy. These symptoms may disappear during therapy and usually disappear rapidly when the drug is discontinued.
Clostridium difficile Associated Diarrhea Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including MINOCIN ® , and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile . C. difficile produces toxins A and B which contribute to the development of CDAD.
Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents.
If CDAD is suspected or confirmed, o…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions have been observed in patients receiving tetracyclines. Body as a whole: Fever, and discoloration of secretions. Gastrointestinal: Anorexia, nausea, vomiting, diarrhea, dyspepsia, stomatitis, glossitis, dysphagia, enamel hypoplasia, enterocolitis, pseudomembranous colitis, pancreatitis, inflammatory lesions (with monilial overgrowth) in the oral and anogenital regions.
These reactions have been caused by both the oral and parenteral administration of tetracyclines. Genitourinary: Vulvovaginitis. Hepatic toxicity: Hyperbilirubinemia, hepatic cholestasis, increases in liver enzymes, fatal hepatic failure, and jaundice.
Hepatitis, including autoimmune hepatitis, and liver failure have been reported (See PRECAUTIONS ). Skin: Alopecia, erythema nodosum, hyperpigmentation of nails, pruritus, toxic epidermal necrolysis, and vasculitis, maculopapular and erythematous rashes. Exfoliative dermatitis has been reported.
Fixed drug eruptions have been reported. Lesions occurring on the glans penis have caused balanitis. Erythema multiforme and Stevens-Johnson syndrome have been reported.
Photosensitivity is discussed above (See WARNINGS ). Pigmentation of the skin and mucous membranes has been reported. Local Reactions: Injection site erythema and injection site pain.
Respiratory: Cough, dyspnea, bronchospasm, exacerbation of asthma, and pneumonitis. Renal toxicity: Interstitial nephritis. Elevations in BUN have been reported and are apparently dose related (See WARNINGS ).
Acute renal failure has been reported. Musculoskeletal: Arthralgia, arthritis, bone discoloration, myalgia, joint stiffness, and joint swelling. Hypersensitivity reactions: Urticaria, angioneurotic edema, polyarthralgia, anaphylaxis/anaphylactoid reaction (including shock and fatalities), anaphylactoid purpura, myocarditis, pericarditis, exacerbation of systemic lupus erythematosus, and pulmonary infiltrates with eosinophilia have been reported.
A lupus-like syndrome and serum sickness-like reactions also have been reported. Blood: Agranulocytosis, hemolytic anemia, thrombocytopenia, leukopenia, neutropenia, pancytopenia, and eosinophilia have been reported. Central Nervous System: Convulsions, dizziness, hypesthesia, paresthesia, sedation, and vertigo.
Pseudotumor cerebri (benign intracranial hypertension) in adults and bulging fontanels in infants (See PRECAUTIONS - General ). Headache has also been reported. Other: Thyroid cancer has been reported in the post-marketing setting in association with minocycline products.
When minocycline therapy is given over prolonged periods, monitoring for signs of thyroid cancer should be considered. When given over prolonged periods, tetracyclines have been reported to produce brown-black microscopic discoloration of the thyroid gland. Cases of abnormal thyroid function have been reported.
Tooth discoloration in pediatric patients less than 8 years of age (See WARNINGS ) and in adults has been reported. Oral cavity discoloration (including tongue, lip, and gum) have been reported. Tinnitus and decreased hearing have been reported in patients on MINOCIN ® (minocycline for injection).
The following syndromes have been reported. In some cases involving these syndromes, death has been reported. As with other serious adverse reactions, if any of these syndromes are recognized, the drug should be discontinued immediately: Hypersensitivity syndrome consisting of cutaneous reaction (such as rash or exfoliative dermatitis), eosinophilia, and one or more of the following: hepatitis, pneumonitis, nephritis, myocarditis, and pericarditis.
Fever and lymphadenopathy may be present. Lupus-like syndrome consisting of positive antinuclear antibody; arthralgia, arthritis, joint stiffness, or joint swelling; and one or more of the following: fever, myalgia, hepatitis, rash, and vasculitis. Serum sickness-like syndrome consisting of fever; urticaria or rash; and arthralgia, arthritis, joint stiffness,…
🔄 Drug Interactions ▾
Drug Interactions Because tetracyclines have been shown to depress plasma prothrombin activity, patients who are on anticoagulant therapy may require downward adjustment of their anticoagulant dosage. Since bacteriostatic drugs may interfere with the bactericidal action of penicillin, it is advisable to avoid giving tetracyclines in conjunction with penicillin. Concurrent use of tetracyclines with oral contraceptives may render oral contraceptives less effective.
Administration of isotretinoin should be avoided shortly before, during, and shortly after minocycline therapy. Each drug alone has been associated with pseudotumor cerebri (See PRECAUTIONS ). Increased risk of ergotism when ergot alkaloids or their derivatives are given with tetracyclines.
MINOCIN ® (minocycline) for Injection contains magnesium sulfate heptahydrate (See DESCRIPTION ). Potentially serious drug interactions may occur when intravenous magnesium sulfate heptahydrate is given concomitantly with CNS depressants, neuromuscular blocking agents and cardiac glycosides.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions False elevations of urinary catecholamine levels may occur due to interference with the fluorescence test.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects (See WARNINGS ) All pregnancies have a background risk of birth defects, loss, or other adverse outcome regardless of drug exposure. There are no adequate and well-controlled studies on the use of minocycline in pregnant women. Minocycline, like other tetracycline-class antibacterials, crosses the placenta and may cause fetal harm when administered to a pregnant woman.
Rare spontaneous reports of congenital anomalies including limb reduction have been reported in post-marketing experience. Only limited information is available regarding these reports; therefore, no conclusion on causal association can be established. If minocycline is used during pregnancy or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus.
Nonteratogenic Effects (See WARNINGS )
🧒 Pediatric Use ▾
Pediatric Use Minocycline is not recommended for use in children below 8 years of age unless the expected benefits of therapy outweigh the risks (See WARNINGS ).
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of intravenous minocycline did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy (See WARNINGS , DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE The adverse events more commonly seen in overdose are dizziness, nausea, and vomiting. No specific antidote for minocycline is known. In case of overdosage, discontinue medication, treat symptomatically, and institute supportive measures. Minocycline is not removed in significant quantities by hemodialysis or peritoneal dialysis.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Following a single dose of Minocin 200 mg administered intravenously to 10 healthy male subjects, serum concentrations of minocycline ranged from 2.52 to 6.63 mcg/mL (average 4.18 mcg/mL) at the end of infusion and 0.82 to 2.64 mcg/mL (average 1.38 mcg/mL) after 12 hours. In a group of 5 healthy male subjects, serum concentrations of minocycline ranged from 1.4 to1.8 mcg/mL at the end of the dosing interval following administration of Minocin 100 mg every 12 hours for three days. When Minocin 200 mg once daily was administered for three days, serum concentrations of minocycline were approximately 1 mcg/mL at 24 hours.
The serum elimination half-life of minocycline following administration of either Minocin 100 mg every 12 hours or 200 mg once daily was not significantly different and ranged from 15 to 23 hours. The serum elimination half-life of minocycline ranged from 11 to 16 hours in subjects with hepatic impairment (n=7) and 18 to 69 hours in subjects with renal impairment (n=5). In comparison, the serum elimination half-life of minocycline ranged from 11 to 17 hours following a single dose of oral minocycline 200 mg in healthy subjects (n=12).
Microbiology Mechanism of Action The tetracyclines are primarily bacteriostatic and are thought to exert their antimicrobial effect by the inhibition of protein synthesis. The tetracyclines, including minocycline, have a similar antimicrobial spectrum of activity against a wide range of Gram-positive and Gram-negative bacteria. Cross-resistance of these bacteria to tetracyclines is common.
List of Microorganisms Minocycline has been shown to be active against most isolates of the following bacteria, both in vitro and in clinical infections as described in the INDICATIONS AND USAGE section: Gram-positive Bacteria Bacillus anthracis Listeria monocytogenes Staphylococcus aureus Streptococcus pneumoniae Gram-negative Bacteria Bartonella bacilliformis Brucella species Klebsiella granulomatis Campylobacter fetus Francisella tularensis Vibrio cholerae Yersinia pestis Acinetobacter species Enterobacter aerogenes Escherichia coli Haemophilus influenzae Klebsiella species Neisseria meningitidis Shigella species Other Microorganisms Actinomyces species Borrelia recurrentis Chlamydophila psittaci Chlamydia trachomatis Clostridium species Entamoeba species Fusobacterium nucleatum subspecies fusiforme Mycobacterium marinum Mycoplasma pneumoniae Propionibacterium acnes Rickettsiae Treponema pallidum subspecies pallidum Treponema pallidum subspecies pertenue Ureaplasma urealyticum Susceptibility Test Methods For specific information regarding susceptibility test interpretive criteria and associated test methods and quality control standards recognized by FDA for this drug, please see: https://www.fda.gov/STIC .
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED MINOCIN ® (minocycline) for Injection is supplied as 100 mg single-dose vials of sterile lyophilized powder. NDC 70842-160-01: 100 mg single-dose vial NDC 70842-160-10: units of 10 × 1 single-dose 100 mg vials Store at Controlled Room Temperature 20° to 25°C (68° to 77°F).
📦 Storage and Handling ▾
Store at Controlled Room Temperature 20° to 25°C (68° to 77°F).
📋 Description ▾
DESCRIPTION MINOCIN (minocycline) for Injection, is a sterile formulation of a semisynthetic derivative of tetracycline. The chemical name of minocycline is 4,7-Bis(dimethylamino)- 1,4,4a,5,5a,6,11,12a-octahydro-3,10,12,12a- tetrahydroxy-1,11-dioxo-2- naphthacenecarboxamide monohydrochloride. Its structural formula is: C 23 H 27 N 3 O 7 ∙HCl M.W.
493.94 MINOCIN is supplied as a sterile yellow to amber lyophilized powder for intravenous infusion. Each vial contains minocycline HCl equivalent to 100 mg minocycline, 269 mg magnesium sulfate heptahydrate (2.2 mEq of magnesium) (an inactive ingredient) and sodium hydroxide (to adjust pH). When reconstituted with 5 mL of Sterile Water for Injection USP the pH ranges from 4.5 to 5.0.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including MINOCIN ® (minocycline) for Injection should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When MINOCIN ® (minocycline) for Injection is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by MINOCIN ® (minocycline) for Injection or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibacterials which usually ends when the antibacterial is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial.
If this occurs, patients should contact their physician as soon as possible.