
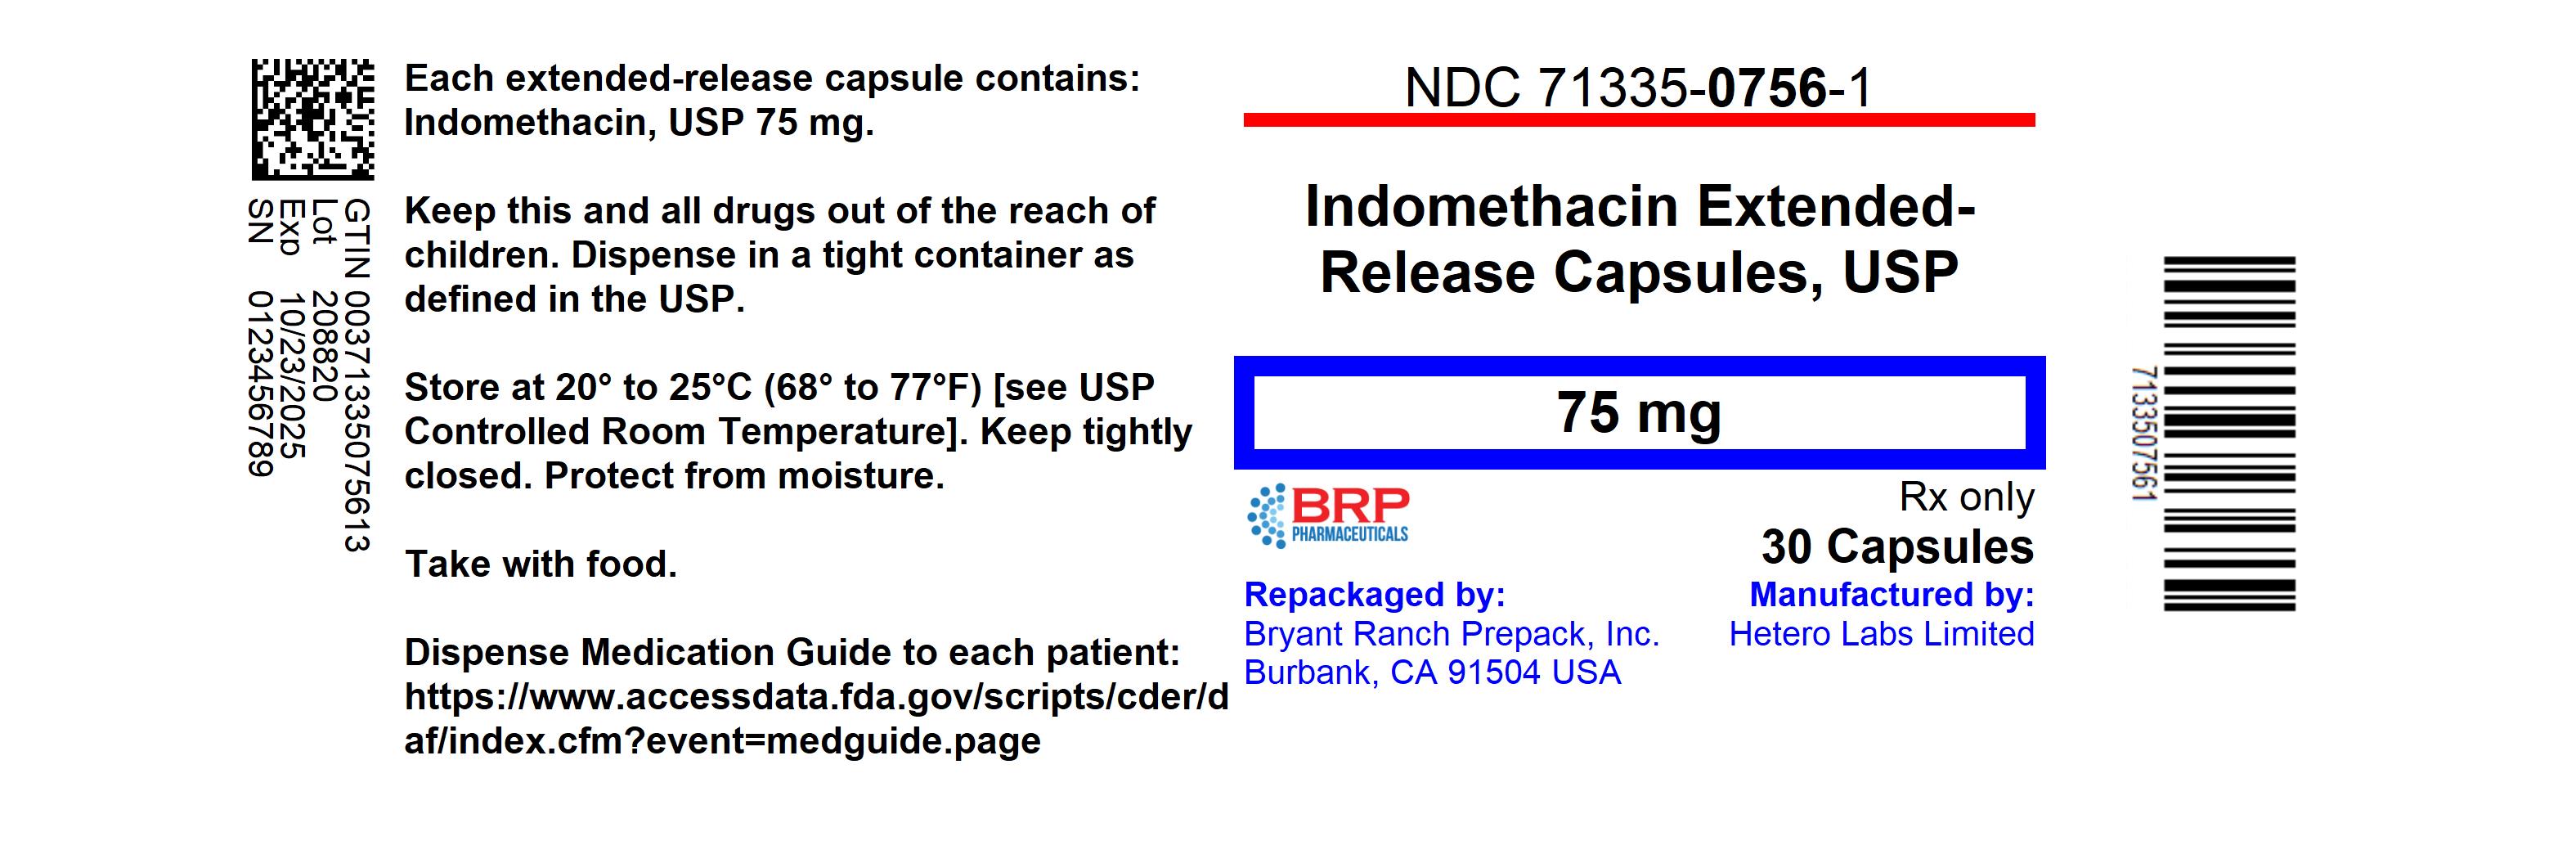
Indomethacin 75 mg Capsule, Extended Release, 90-count
Other active recalls for Indomethacin (different manufacturers) — 5 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Indomethacin is a strong anti-inflammatory medication used mainly for moderate to severe arthritis — including rheumatoid arthritis, osteoarthritis, and ankylosing spondylitis — as...
- Yes — and this is important. Always take indomethacin with food, right after a meal, or with antacids. This helps protect your stomach lining and reduces the chance of stomach upse...
- Common side effects like headache, mild nausea, dizziness, or indigestion are typical and often improve as your body adjusts — taking it with food can help. But call your doctor im...
- What side effects should I just watch for versus call my doctor about right away?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Indomethacin — tap one for details:
Indomethacin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 295O53K152
A mineral element that helps maintain the chemical balance inside the medicine. It's often included as part of salt compounds to stabilize the active ingredient and ensure the medication stays effective.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
16 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.4033 | $36.30 / 90 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Indomethacin 75 mg 10702-0016-01 | KVK-Tech, | 100 capsules | $0.199 | AB | Availability likely | — |
| Indomethacin 75 mg 31722-0565-01 | Camber | 100 capsules | $0.199 | AB | Availability likely | — |
| Indomethacin 75 mg 68084-0411-21 | American | 1 capsule | $0.199 | AB | Availability likely | — |
| indomethacin 75 mg 68462-0325-01 | Glenmark | 100 capsules | $0.199 | AB | Availability likely | — |
| Indomethacin 75 mg 65162-0506-03 | Amneal | 30 capsules | $0.223 | AB | Availability likely | — |
| Indomethacin 75 mg 51655-0443-52 | Northwind | 30 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 55289-0469-10 | PD-Rx | 10 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 63629-1915-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 70518-0515-00 | REMEDYREPACK | 15 capsules | — | AB | Discontinued | — |
| Indomethacin 75 mg 71205-0822-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mgthis 71335-0756-08 | Bryant | 90 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 71335-9754-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 72162-1302-06 | Bryant | 60 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 76420-0029-01 | Asclemed | 1 capsule | — | AB | FDA listed | — |
| Indomethacin ER 75 mg 80425-0271-01 | Advanced | 60 capsules | — | AB | FDA listed | — |
| Indomethacin 75 mg 85766-0034-00 | Sportpharm | 10 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0756-01 | 30 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-1) | 2015-07-24 | Active |
| 71335-0756-02 | 60 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-2) | 2015-07-24 | Active |
| 71335-0756-03 | 14 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-3) | 2015-07-24 | Active |
| 71335-0756-04 | 10 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-4) | 2015-07-24 | Active |
| 71335-0756-05 | 7 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-5) | 2015-07-24 | Active |
| 71335-0756-06 | 15 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-6) | 2015-07-24 | Active |
| 71335-0756-07 | 20 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-7) | 2015-07-24 | Active |
| 71335-0756-08 You're viewing this | 90 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-8) | 2015-07-24 | Active |
| 71335-0756-09 | 100 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-0756-9) | 2015-07-24 | Active |
You're viewing one of 9 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0756-08?
What is the difference between NDC 71335-0756-08 and NDC 71335-0756-05?
What NDC number is used to bill for this package of Indomethacin 75 mg Capsule, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING Cardiovascular Thrombotic Events • Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use [see Warnings and Precautions ]. • Indomethacin extended-release capsules are contraindicated in the setting of coronary artery bypass graft (CABG) surgery [see Contraindications and Warnings ]. Gastrointestinal Risk • NSAIDs cause an increased risk of serious gastrointestinal adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal.
These events can occur at any time during use and without warning symptoms. Elderly patients are at greater risk for serious gastrointestinal events (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS & USAGE Carefully consider the potential benefits and risks of indomethacin extended-release capsules and other treatment options before deciding to use indomethacin extended-release capsules. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). Indomethacin extended-release capsules have been found effective in active stages of the following: 1.
Moderate to severe rheumatoid arthritis including acute flares of chronic disease. 2. Moderate to severe ankylosing spondylitis.
3. Moderate to severe osteoarthritis. 4.
Acute painful shoulder (bursitis and/or tendinitis). Indomethacin extended-release capsules, USP are not recommended for the treatment of acute gouty arthritis. Indomethacin may enable the reduction of steroid dosage in patients receiving steroids for the more severe forms of rheumatoid arthritis.
In such instances the steroid dosage should be reduced slowly and the patients followed very closely for any possible adverse effects. The use of indomethacin in conjunction with aspirin or other salicylates is not recommended. Controlled clinical studies have shown that the combined use of indomethacin and aspirin does not produce any greater therapeutic effect than the use of indomethacin alone.
Furthermore, in one of these clinical studies, the incidence of gastrointestinal side effects was significantly increased with combined therapy. (See PRECAUTIONS,Drug Interactions ).
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION Carefully consider the potential benefits and risks of indomethacin extended-release capsules and other treatment options before deciding to use indomethacin extended-release capsules. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). Indomethacin extended-release capsules 75 mg are available for oral use.
Indomethacin extended-release capsules can be administered once a day and can be substituted for indomethacin 25 mg capsules t.i.d. However, there will be significant differences between the two dosage regimens in indomethacin blood levels, especially after 12 hours (see CLINICAL PHARMACOLOGY ). In addition, indomethacin extended-release capsules 75 mg b.i.d. can be substituted for indomethacin 50 mg capsules t.i.d.
Indomethacin extended-release capsules may be substituted for all the indications of indomethacin capsules except acute gouty arthritis. Adverse reactions appear to correlate with the size of the dose of indomethacin in most patients, but not all. Therefore, every effort should be made to determine the smallest effective dosage for the individual patient.
Always give indomethacin extended-release capsules 75 mg with food, immediately after meals or with antacids to reduce gastric irritation. Pediatric Use : Indomethacin ordinarily should not be prescribed for children 14 years of age and under (see WARNINGS ). Adult Use : Dosage Recommendations for Active Stages of the Following: 1.
Moderate to severe rheumatoid arthritis, including acute flares of chronic disease; moderate to severe ankylosing spondylitis; and moderate to severe osteoarthritis. The following information is provided as background only and refers to immediate-release indomethacin capsules (25 mg or 50 mg): Suggested Dosage : The following recommendations on dosing pertain to immediate-release indomethacin capsules, and provide important information regarding the dosage and administration of indomethacin. The prescriber should be aware of this information when considering and prescribing extended-release indomethacin.
Indomethacin capsules 25 mg b.i.d. or t.i.d. If this is well tolerated, increase the daily dosage by 25 or 50 mg, if required by continuing symptoms, at weekly intervals until a satisfactory response is obtained or until a total daily dose of 150 to 200 mg is reached. DOSES ABOVE THIS AMOUNT GENERALLY DO NOT INCREASE THE EFFECTIVENESS OF THE DRUG.
In patients who have persistent night pain and/or morning stiffness, the giving of a large portion, up to a maximum of 100 mg, of the total daily dose at bedtime, either orally or by rectal suppositories, may be helpful in affording relief. The total daily dose should not exceed 200 mg. In acute flares of chronic rheumatoid arthritis, it may be necessary to increase the dosage by 25 mg or, if required, by 50 mg daily.
The following information refers to Extended-release Indomethacin Capsules (75 mg): If indomethacin extended-release capsules are used for initiating indomethacin treatment, one capsule daily should be the usual starting dose in order to observe patient tolerance since 75 mg per day is the maximum recommended starting dose for indomethacin (see above). If indomethacin extended-release capsules are used to increase the daily dose, patients should be observed for possible signs and symptoms of intolerance since the daily increment will exceed the daily increment recommended for other dosage forms.
For patients who require 150 mg of indomethacin per day and have demonstrated acceptable tolerance, indomethacin extended-release capsules 75 mg may be prescribed as one capsule twice daily. If minor adverse effects develop as the dosage is increased, reduce the dosage rapidly to a tolerated dose and OBSERVE THE PATIENT CLOSELY. If severe adverse reactions occur, STOP THE DRUG.
After the acute phase of the disease is under control, an attempt to reduce the daily dose should be made repeated…
⛔ Contraindications ▾
CONTRAINDICATIONS Indomethacin extended-release capsules are contraindicated in patients with known hypersensitivity to indomethacin. Indomethacin extended-release capsules should not be given to patients who have experienced asthma, urticaria, or allergic-type reactions after taking aspirin or other NSAIDs. Severe, rarely fatal, anaphylactic-like reactions to NSAIDs have been reported in such patients (see WARNINGS: Anaphylactoid Reactions , and Precautions: Preexisting Asthma ).
Indomethacin extended-release capsules is contraindicated for the treatment of perioperative pain in the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Cardiovascular Effects Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as indomethacin, increases the risk of serious gastrointestinal (GI) events [see Warnings ]. Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG [see Contraindications ]. Post-MI Patients Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients.
Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next four years of follow-up. Avoid the use of indomethacin extended-release capsules in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If indomethacin extended-release capsules are used in patients with a recent MI, monitor patients for signs of cardiac ischemia.
Hypertension NSAIDs, including indomethacin extended-release capsules, can lead to onset of new hypertension or worsening of preexisting hypertension, either of which may contribute to the increased incidence of CV events. Patients taking thiazides or loop diuretics may have impaired response to these therapies when taking NSAIDs. NSAIDs, including indomethacin extended-release capsules, should be used with caution in patients with hypertension.
Blood pressure (BP) should be monitored closely during the initiation of NSAID treatment and throughout the course of therapy. Heart Failure and Edema The Coxib and traditional NSAID Trialists’ Collaboration meta-analysis of randomized controlled trials demonstrated an approximately two-fold increase in hospitalizations for heart failure in COX-2 selective-treated patients and nonselective NSAID-treated patients compared to placebo-treated patients. In a Danish National Registry study of patients with heart failure, NSAID use increa…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The adverse reactions for indomethacin capsules listed in the following table have been arranged into two groups: (1) incidence greater than 1%; and (2) incidence less than 1%. The incidence for group (1) was obtained from 33 double-blind controlled clinical trials reported in the literature (1,092 patients). The incidence for group (2) was based on reports in clinical trials, in the literature, and on voluntary reports since marketing.
The probability of a causal relationship exists between indomethacin and these adverse reactions, some of which have been reported only rarely. In controlled clinical trials, the incidence of adverse reactions to indomethacin extended-release capsules and equal 24-hour doses of indomethacin capsules were similar. Incidence greater than 1% GASTROINTESTINAL nausea * with or without vomiting dyspepsia * (including indigestion, heartburn and epigastric pain) diarrhea abdominal distress or pain constipation CENTRAL NERVOUS SYSTEM headache (11.7%) dizziness * vertigo somnolence depression and fatigue (including malaise and listlessness) SPECIAL SENSES tinnitus CARDIOVASCULAR none METABOLIC none INTEGUMENTARY none HEMATOLOGIC none HYPERSENSITIVITY none GENITOURINARY none MISCELLANEOUS none Incidence less than 1% GASTROINTESTINAL anorexia bloating (includes distention) flatulence peptic ulcer gastroenteritis rectal bleeding proctitis single or multiple ulcerations, including perforation and hemorrhage of the esophagus, stomach, duodenum or small and large intestines Intestinal ulceration associated with stenosis and obstruction gastrointestinal bleeding without obvious ulcer formation and perforation of preexisting sigmoid lesions (diverticulum, carcinoma, etc.) development of ulcerative colitis and regional ileitis ulcerative stomatitis toxic hepatitis and jaundice (some fatal cases have been reported) CENTRAL NERVOUS SYSTEM anxiety (includes nervousness) muscle weakness involuntary muscle movements insomnia muzziness psychic disturbances including psychotic episodes mental confusion drowsiness light-headedness syncope paresthesia aggravation of epilepsy and parkinsonism depersonalization coma peripheral neuropathy convulsions dysarthria SPECIAL SENSES ocular-corneal deposits and retinal disturbances, including those of the macula, have been reported in some patients on prolonged therapy with Indomethacin blurred vision diplopia hearing disturbances, deafness CARDIOVASCULAR congestive heart failure hypertension hypotension tachycardia chest pain arrhythmia; palpitations METABOLIC edema weight gain fluid retention flushing or sweating hyperglycemia glycosuria hyperkalemia INTEGUMENTARY pruritus rash; urticaria petechiae or ecchymosis exfoliative dermatitis erythema nodosum loss of hair Stevens-Johnson Syndrome erythema multiforme toxic epidermal necrolysis HEMATOLOGIC leukopenia bone marrow depression anemia secondary to obvious or occult gastrointestinal bleeding aplastic anemia hemolytic anemia agranulocytosis thrombocytopenic purpura disseminated intravascular coagulation HYPERSENSITIVITY acute anaphylaxis acute respiratory distress rapid fall in blood pressure resembling a shock-like state angioedema dyspnea asthma purpura angiitis pulmonary edema fever GENITOURINARY hematuria vaginal bleeding proteinuria, nephrotic syndrome, interstitial nephritis BUN elevation renal insufficiency including renal failure MISCELLANEOUS epistaxis breast changes, including enlargement and tenderness, or gynecomastia * Reactions occurring in 3% to 9% of patients treated with indomethacin.
(Those reactions occurring in less than 3% of the patients are unmarked.) Causal Relationship Unknown : Other reactions have been reported but occurred under circumstances where a causal relationship could not be established. However, in these rarely reported events, the possibility cannot be excluded. Therefore, these observations are being listed to serve as alerting information to physicians: A rare occurrence of…
🔄 Drug / Laboratory Test Interactions ▾
Drug & OR Laboratory Test Interactions Only if positive interactions have been observed. (See 201.57 (f)(4)(N))
🤰 Pregnancy ▾
Pregnancy Pregnancy Teratogenic Effects. Pregnancy Category C Reproductive studies conducted in rats and rabbits have not demonstrated evidence of developmental abnormalities. However, animal reproduction studies are not always predictive of human response.
There are no adequate and well-controlled studies in pregnant women. Nonteratogenic Effects Because of the known effects of nonsteroidal anti-inflammatory drugs on the fetal cardiovascular system (closure of ductus arteriosus), use during pregnancy (particularly late pregnancy) should be avoided.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients below the age of 14 years old have not been established.
🧓 Geriatric Use ▾
Geriatric Use As with any NSAIDs, caution should be exercised in treating the elderly (65 years and older).
🆘 Overdosage ▾
OVERDOSAGE The following symptoms may be observed following overdosage: nausea, vomiting, intense headache, dizziness, mental confusion, disorientation, or lethargy. There have been reports of paresthesias, numbness and convulsions. Treatment is symptomatic and supportive.
The stomach should be emptied as quickly as possible if the ingestion is recent. If vomiting has not occurred spontaneously, the patient should be induced to vomit with syrup of ipecac. If the patient is unable to vomit, gastric lavage should be performed.
Once the stomach has been emptied, 25 g or 50 g of activated charcoal may be given. Depending on the condition of the patient, close medical observation and nursing care may be required. The patient should be followed for several days because gastrointestinal ulceration and hemorrhage have been reported as adverse reactions of indomethacin.
Use of antacids may be helpful. The oral LD 50 of indomethacin in mice and rats (based on 14 day mortality response) was 50 and 12 mg/kg, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Indomethacin is a nonsteroidal drug with anti-inflammatory, antipyretic and analgesic properties. Its mode of action, like that of other anti-inflammatory drugs, is not known. However, its therapeutic action is not due to pituitary-adrenal stimulation.
Indomethacin is a potent inhibitor of prostaglandin synthesis in vitro . Concentrations are reached during therapy which have been demonstrated to have an effect in vivo as well. Prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain in animal models.
Moreover, prostaglandins are known to be among the mediators of inflammation. Since indomethacin is an inhibitor of prostaglandin synthesis, its mode of action may be due to a decrease of prostaglandins in peripheral tissues. Indomethacin has been shown to be an effective anti-inflammatory agent, appropriate for long-term use in rheumatoid arthritis, ankylosing spondylitis, and osteoarthritis.
Indomethacin affords relief of symptoms; it does not alter the progressive course of the underlying disease. Indomethacin suppresses inflammation in rheumatoid arthritis as demonstrated by relief of pain and reduction of fever, swelling and tenderness. Improvement in patients treated with indomethacin for rheumatoid arthritis has been demonstrated by a reduction in joint swelling, average number of joints involved and morning stiffness; by increased mobility as demonstrated by a decrease in walking time; and by improved functional capability as demonstrated by an increase in grip strength.
Indomethacin has been reported to diminish basal and CO 2 stimulated cerebral blood flow in healthy volunteers following acute oral and intravenous administration. In one study, after one week of treatment with orally administered indomethacin, this effect on basal cerebral blood flow had disappeared. The clinical significance of this effect has not been established.
Indomethacin extended-release capsules (75 mg) are designed to release 25 mg of drug initially and the remaining 50 mg over approximately 12 hours (90% of dose absorbed by 12 hours). Plasma concentrations of indomethacin fluctuate less and are more sustained following administration of indomethacin extended-release capsules than following administration of 25 mg indomethacin capsules given at 4 to 6 hour intervals. In multiple-dose comparisons, the mean daily steady state plasma level of indomethacin attained with daily administration of indomethacin extended-release capsules 75 mg was indistinguishable from that following indomethacin 25 mg capsules given at 0, 6 and 12 hours daily.
However, there was a significant difference in indomethacin plasma levels between the two dosage regimens especially after 12 hours. Controlled clinical studies of safety and efficacy in patients with osteoarthritis have shown that one capsule of indomethacin extended-release was clinically comparable to one 25 mg indomethacin capsule t.i.d.; and in controlled clinical studies in patients with rheumatoid arthritis, one capsule of indomethacin extended-release taken in the morning and one in the evening were clinically indistinguishable from one 50 mg capsule of indomethacin t.i.d.
Indomethacin is eliminated via renal excretion, metabolism and biliary excretion. Indomethacin undergoes appreciable enterohepatic circulation. The mean half-life of indomethacin is estimated to be about 4.5 hours.
With a typical therapeutic regimen of 25 or 50 mg t.i.d., the steady state plasma concentrations of indomethacin are an average 1.4 times those following the first dose. Indomethacin exists in the plasma as the parent drug and its desmethyl, desbenzoyl and desmethyldesbenzoyl metabolites, all in the unconjugated form. About 60 percent of an oral dosage is recovered in urine as drug and metabolites (26 percent as indomethacin and its glucuronide) and 33 percent is recovered in feces (1.5 percent as indomethacin).
About 99% of indomethacin is bound to protein in pla…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Indomethacin Extended-release capsules USP 75 mg are size '2’ hard gelatin capsules, with dark yellow cap imprinted with 'H' and clear transparent body imprinted with '105' containing cream spherical pellet: Product: 71335-0756 NDC: 71335-0756-1 30 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-2 60 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-3 14 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-4 10 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-5 7 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-6 15 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-7 20 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-8 90 CAPSULE, EXTENDED RELEASE in a BOTTLE NDC: 71335-0756-9 100 CAPSULE, EXTENDED RELEASE in a BOTTLE Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Protect from moisture Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
DESCRIPTION Indomethacin cannot be considered a simple analgesic and should not be used in conditions other than those recommended under INDICATIONS AND USAGE . Indomethacin is a non-steroidal anti-inflammatory indole derivative designated chemically as 1-(4-chlorobenzoyl)-5-methoxy-2-methyl-1H-indole-3-acetic acid. Indomethacin, USP is practically insoluble in water and sparingly soluble in alcohol.
It has a pKa of 4.5 and is stable in neutral or slightly acidic media and decomposes in strong alkali. The structural formula is: C 19 H 16 ClNO 4 M.W. 357.80 Each extended-release capsule, for oral administration contains 75 mg of indomethacin and the following inactive ingredients: sugar spheres, povidone, mannitol, isopropyl alcohol, talc.
The hard gelatin shell consists of gelatin, iron oxide yellow, titanium dioxide, sodium lauryl sulfate. The imprinting ink contains the following: shellac, dehydrated alcohol, isopropyl alcohol, butyl alcohol, propylene glycol, strong ammonia solution, black iron oxide E172 dye and potassium hydroxide. This product meets USP Drug Release Test 2 Specifications.
IndomethacinERstructure
💬 Information for Patients ▾
Information for Patients Patients should be informed of the following information before initiating therapy with a NSAID and periodically during the course of ongoing therapy. Patients should also be encouraged to read the NSAID Medication Guide that accompanies each prescription dispensed. 1.
Cardiovascular Thrombotic Events Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their health care provider immediately [see Warnings ]. 2. Indomethacin extended-release capsules, like other NSAIDs, can cause GI discomfort and, rarely, serious GI side effects, such as ulcers and bleeding, which may result in hospitalization and even death.
Although serious GI tract ulcerations and bleeding can occur without warning symptoms, patients should be alert for the signs and symptoms of ulcerations and bleeding, and should ask for medical advice when observing any indicative signs or symptoms including epigastric pain, dyspepsia, melena, and hematemesis. Patients should be apprised of the importance of this follow-up (see WARNINGS, Gastrointestinal Effects , Risk of Ulceration, Bleeding, and Perforation ). 3.
Indomethacin extended-release capsules, like other NSAIDs, can cause serious skin side effects such as exfoliative dermatitis, SJS, and TEN, which may result in hospitalization and even death. Although serious skin reactions may occur without warning, patients should be alert for the signs and symptoms of skin rash and blisters, fever, or other signs of hypersensitivity such as itching, and should ask for medical advice when observing any indicative signs or symptoms. Patients should be advised to stop the drug immediately if they develop any type of rash and contact their physicians as soon as possible.
4. Heart Failure And Edema Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur [see Warnings ]. 5.
Patients should be informed of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, jaundice, right upper quadrant tenderness and "flu-like" symptoms). If these occur, patients should be instructed to stop therapy and seek immediate medical therapy. 6.
Patients should be informed of the signs of an anaphylactoid reaction (e.g. difficulty breathing, swelling of the face or throat). If these occur, patients should be instructed to seek immediate emergency help (see WARNINGS ). 7.
In late pregnancy, as with other NSAIDs, indomethacin extended-release capsules should be avoided because it will cause premature closure of the ductus arteriosus.
💬 Medication Guide ▾
SPL MEDGUIDE Indomethacin Extended-release Capsules, USP Medication Guide for Non steroidal Anti-inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: • Increased risk of heart attack or stroke that can lead to death. This risk may happen early in treatment and may increase: o with increasing doses of NSAIDs o with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG).” Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack . • Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: o anytime during use o without warning symptoms o that may cause death The risk of getting an ulcer or bleeding increases with: o past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs o taking medicines called "corticosteroids", "anticoagulants", "SSRIs", or "SNRIs" o increasing doses of NSAIDs o older age o longer use of NSAIDs o poor health o smoking o advanced liver disease o drinking alcohol o bleeding problems NSAIDs should only be used: o exactly as prescribed o at the lowest dose possible for your treatment o for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take a NSAIDs? Do not take an NSAIDs: • if you had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. • right before or after heart bypass surgery.
Before taking NSAIDs, tell your healthcare provider about all of your medical conditions, including if you: • have liver or kidney problems • have high blood pressure • have asthma • are pregnant or plan to become pregnant. Talk to your healthcare provider if you are considering taking NSAIDs during pregnancy. You should not take NSAIDs after 29 weeks of pregnancy. • are breastfeeding or plan to breast feed.
Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements . NSAIDs and some other medicines can interact with each other and cause serious side effects. Do not start taking any new medicine without talking to your healthcare provider first.
What are the possible side effects of NSAIDs? NSAIDs can cause serious side effects, including: See “What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? • new or worse high blood pressure • heart failure • liver problems including liver failure • kidney problems including kidney failure • low red blood cells (anemia) • life-threatening skin reactions • life threatening allergic reactions • Other side effects of NSAIDs include : stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you get any of the following symptoms: • shortness of breath or trouble breathing • slurred speech • chest pain • swelling of the face or throat • weakness in one part or side of your body Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: • nausea • vomit blood • more tired or weaker than usual • there is blood in your bowel movement or it is • diarrhea black and sticky like tar • itching • unusual weight gain • your skin or eyes look yellow • skin rash or blisters with fever • indigestion or stomach pain • swelling of the arms, legs, hands and feet • flu-like symptoms If you take too much of your NSAID, call your healthcare provider…