
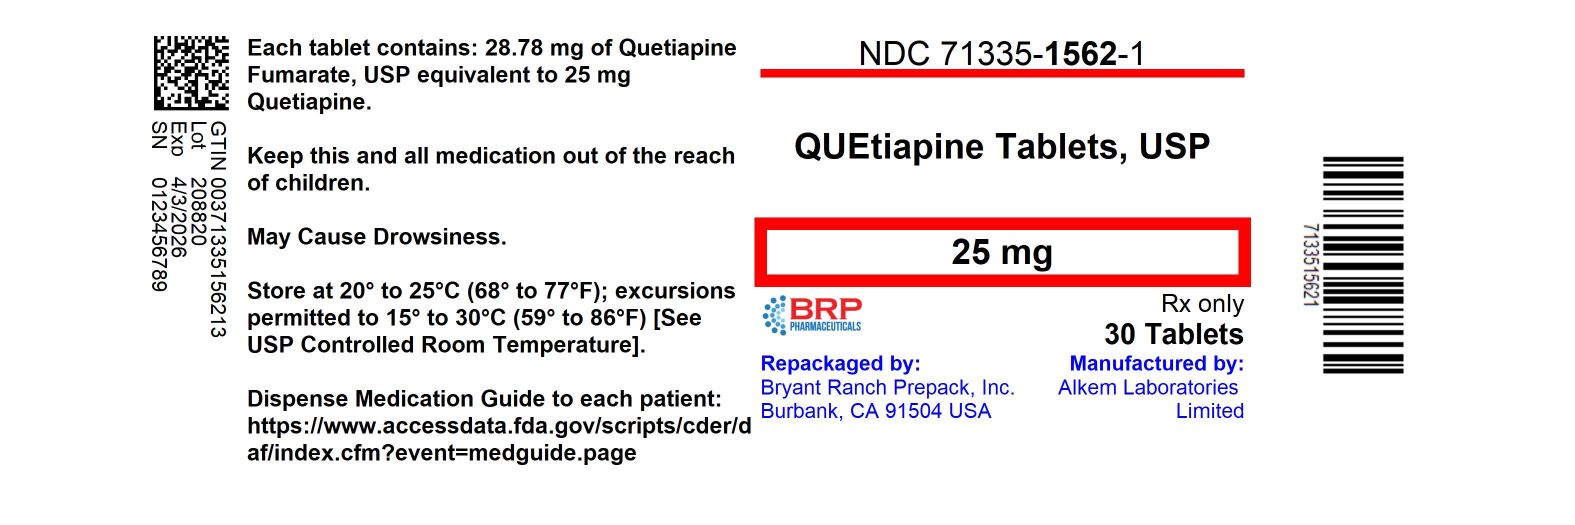
Quetiapine Fumarate 25 mg Tablet, Film Coated, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Atypical Antipsychotic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Quetiapine is used to treat schizophrenia (a mental illness that affects how a person thinks, feels and behaves), bipolar disorder (a disease that causes depression, mania, and other abnormal moods) and major depressive disorder. Quetiapine is in a class of medications called atypical antipsychotics. It works by changing the activity of certain natural substances in the brain.
Read the full MedlinePlus article ↗- Quetiapine is approved to treat schizophrenia, bipolar disorder (both manic episodes and depressive episodes), and — in the extended-release form only — as an add-on to an antidepr...
- It depends on the form. If you're taking the regular tablet, you can take it with or without food — no restrictions. But if you're on the extended-release tablet, you should take i...
- Does it matter if I take quetiapine with food?
- Sleepiness is actually one of the most common side effects — in some studies, more than half of patients reported it. Quetiapine blocks histamine receptors in the brain, which has...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII O7TSZ97GEP
A mineral compound that serves as a filler and binding agent in tablets and capsules. It adds bulk to the medicine and helps hold ingredients together during manufacturing.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 4R4HFI6D95
Polyethylene glycol 4000 is a synthetic polymer derived from petroleum. It serves as a binder, filler, and lubricant in solid dosage forms, and helps control how quickly the medicine dissolves.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1085 | $10.85 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Quetiapine 25 mg 00093-2063-01 | Teva | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine 25 mg 00904-6638-61 | Major | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine Fumarate 25 mg 16571-0717-01 | Rising | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine Fumarate 25 mg 16714-0375-01 | NorthStar | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine Fumarate 25 mg 29300-0147-01 | Unichem | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine Fumarate 25 mg 31722-0764-01 | Camber | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine 25 mg 43547-0518-10 | Solco | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine fumarate 25 mg 47335-0902-18 | Sun | 1000 tablets | $0.023 | — | Discontinued | — |
| Quetiapine Fumarate 25 mg 50268-0630-15 | AvPAK | 50 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine fumarate 25 mg 60687-0327-01 | American | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine Fumarate 25 mg 65862-0489-01 | Aurobindo | 100 tablets | $0.023 | — | Availability likely | — |
| Quetiapine 25 mg 67877-0242-01 | Ascend | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine fumarate 25 mg 68001-0185-00 | BluePoint | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine fumarate 25 mg 68180-0445-01 | Lupin | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine fumarate 25 mg 82009-0095-01 | Quallent | 100 tablets | $0.023 | AB | Availability likely | — |
| Quetiapine 25 mg 16729-0145-01 | Accord | 100 tablets | $0.028 | — | Availability likely | — |
| Quetiapine fumarate 25 mg 33342-0099-11 | Macleods | 100 tablets | $0.036 | AB | FDA listed | — |
| Seroquel 25 mg 00310-0275-10 | AstraZeneca | 100 tablets | $3.711 | AB | Availability likely | — |
| Quetiapine Fumarate 25 mg 00054-0220-20 | Hikma | 100 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 00615-8470-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Quetiapine 25 mg 42291-0695-10 | AvKARE | 1000 tablets | — | AB | Discontinued | — |
| Quetiapine Fumarate 25 mg 46708-0134-10 | Alembic | 100 tablets | — | — | FDA listed | — |
| Quetiapine Fumarate 25 mg 50090-3333-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 51407-0066-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Quetiapine 25 mg 55154-7881-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 60760-0764-30 | ST. | 30 tablets | — | AB | FDA listed | — |
| Seroquel 25 mg 61269-0250-10 | H2-Pharma, | 100 tablets | — | AB | FDA listed | — |
| Quetiapine fumarate 25 mg 63187-0452-03 | Proficient | 3 tablets | — | AB | FDA listed | — |
| Quetiapine fumarate 25 mg 67046-1440-03 | Coupler | 30 tablets | — | — | FDA listed | — |
| Quetiapine fumarate 25 mg 68071-3676-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 68071-3931-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Quetiapine fumarate 25 mg 68788-8764-01 | : | 100 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 68788-8823-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 70518-3747-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 71205-0826-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mgthis 71335-1562-05 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 71335-2679-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 71610-0140-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 72189-0446-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 72865-0264-01 | XLCare | 100 tablets | — | AB | FDA listed | — |
| Quetiapine 25 mg 76420-0512-01 | ASCLEMED | 100 tablets | — | AB | FDA listed | — |
| Quetiapine fumarate 25 mg 87441-0074-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Quetiapine Fumarate 25 mg 70518-4705-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1562-01 | 30 TABLET in 1 BOTTLE (71335-1562-1) | 2020-04-07 | Discontinued by firm |
| 71335-1562-02 | 60 TABLET in 1 BOTTLE (71335-1562-2) | 2020-07-06 | Discontinued by firm |
| 71335-1562-03 | 90 TABLET in 1 BOTTLE (71335-1562-3) | 2021-01-18 | Discontinued by firm |
| 71335-1562-04 | 120 TABLET in 1 BOTTLE (71335-1562-4) | 2022-09-19 | Discontinued by firm |
| 71335-1562-05 You're viewing this | 100 TABLET, FILM COATED in 1 BOTTLE (71335-1562-5) | 2025-06-27 | Active |
You're viewing one of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1562-05?
What is the difference between NDC 71335-1562-05 and NDC 71335-1562-01?
What NDC number is used to bill for this package of Quetiapine Fumarate 25 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS; and SUICIDAL THOUGHTS AND BEHAVIORS Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death [ see Warnings and Precautions (5.1) ]. Quetiapine is not approved for the treatment of patients with dementia-related psychosis [ see Warnings and Precautions (5.1) ]. Suicidal Thoughts and Behaviors Antidepressants increased the risk of suicidal thoughts and behavior in children, adolescents, and young adults in short-term studies.
These studies did not show an increase in the risk of suicidal thoughts and behavior with antidepressant use in patients over age 24; there was a reduction in risk with antidepressant use in patients aged 65 and older [ see Warnings and Precautions (5.2) ]. In patients of all ages who are started on antidepressant therapy, monitor closely for worsening, and for emergence of suicidal thoughts and behaviors. Advise families and caregivers of the need for close observation and communication with the prescriber [ see Warnings and Precautions (5.2) ].
Quetiapine is not approved for use in pediatric patients under ten years of age [ see Use in Specific Populations (8.4) ]. WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS; and SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning . Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death.
Quetiapine tablets is not approved for elderly patients with dementia-related psychosis ( 5.1 ) Suicidal Thoughts and Behaviors Increased risk of suicidal thoughts and behavior in children, adolescents and young adults taking antidepressants ( 5.2 ) Monitor for worsening and emergence of suicidal thoughts and behaviors ( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Quetiapine is an atypical antipsychotic indicated for the treatment of: Schizophrenia ( 1.1 ) Bipolar I disorder manic episodes ( 1.2 ) Bipolar disorder, depressive episodes ( 1.2 )
1.1Schizophrenia Quetiapine is indicated for the treatment of schizophrenia. The efficacy of quetiapine in schizophrenia was established in three 6-week trials in adults and one 6-week trial in adolescents (13 to 17 years). The effectiveness of quetiapine for the maintenance treatment of schizophrenia has not been systematically evaluated in controlled clinical trials [ see Clinical Studies (14.1) ].
1.2Bipolar Disorder Quetiapine is indicated for the acute treatment of manic episodes associated with bipolar I disorder, both as monotherapy and as an adjunct to lithium or divalproex. Efficacy was established in two 12-week monotherapy trials in adults, in one 3-week adjunctive trial in adults, and in one 3-week monotherapy trial in pediatric patients (10 to 17 years) [ see Clinical Studies (14.2) ]. Quetiapine is indicated as monotherapy for the acute treatment of depressive episodes associated with bipolar disorder.
Efficacy was established in two 8-week monotherapy trials in adult patients with bipolar I and bipolar II disorder [ see Clinical Studies (14.2) ]. Quetiapine is indicated for the maintenance treatment of bipolar I disorder, as an adjunct to lithium or divalproex. Efficacy was established in two maintenance trials in adults.
The effectiveness of quetiapine as monotherapy for the maintenance treatment of bipolar disorder has not been systematically evaluated in controlled clinical trials [ see Clinical Studies (14.2) ].
1.3Special Considerations in Treating Pediatric Schizophrenia and Bipolar I Disorder Pediatric schizophrenia and bipolar I disorder are serious mental disorders, however, diagnosis can be challenging. For pediatric schizophrenia, symptom profiles can be variable, and for bipolar I disorder, patients may have variable patterns of periodicity of manic or mixed symptoms. It is recommended that medication therapy for pediatric schizophrenia and bipolar I disorder be initiated only after a thorough diagnostic evaluation has been performed and careful consideration given to the risks associated with medication treatment.
Medication treatment for both pediatric schizophrenia and bipolar I disorder is indicated as part of a total treatment program that often includes psychological, educational and social interventions.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION · Quetiapine tablets, USP can be taken with or without food ( 2.1 ) Indication Initial Dose Recommended Dose Maximum Dose Schizophrenia-Adults (2.2) 25 mg twice daily 150 to 750 mg/day 750 mg/day Schizophrenia-Adolescents (13 to 17 years) (2.2) 25 mg twice daily 400 to 800 mg/day 800 mg/day Bipolar Mania- Adults Monotherapy or as an adjunct to lithium or divalproex (2.2) 50 mg twice daily 400 to 800 mg/day 800 mg/day Bipolar Mania- Children and Adolescents (10 to 17 years), Monotherapy (2.2) 25 mg twice daily 400 to 600 mg/day 600 mg/day Bipolar Depression-Adults (2.2) 50 mg once daily at bedtime 300 mg/day 300 mg/day Geriatric Use: Consider a lower starting dose (50 mg/day), slower titration and careful monitoring during the initial dosing period in the elderly ( 2.3 , 8.5 ) Hepatic Impairment: Lower starting dose (25 mg/day) and slower titration may be needed ( 2.4 , 8.7 , 12.3 )
2.1Important Administration Instructions Quetiapine tablets, USP can be taken with or without food.
2.2Recommended Dosing The recommended initial dose, titration, dose range and maximum quetiapine dose for each approved indication is displayed in Table 1. After initial dosing, adjustments can be made upwards or downwards, if necessary, depending upon the clinical response and tolerability of the patient [ see Clinical Studies ( 14.1 and 14.2 ) ]. Table 1: Recommended Dosing for quetiapine Indication Initial Dose and Titration Recommended Dose Maximum Dose Schizophrenia-Adults Day 1: 25 mg twice daily.
Increase in increments of 25 mg-50 mg divided two or three times on Days 2 and 3 to range of 300 to 400 mg by Day 4. Further adjustments can be made in increments of 25 to 50 mg twice a day, in intervals of not less than 2 days. 150 to 750 mg/day 750 mg/day Schizophrenia- Adolescents (13 to 17 years) Day 1: 25 mg twice daily.
Day 2: Twice daily dosing totaling 100 mg. Day 3: Twice daily dosing totaling 200 mg. Day 4: Twice daily dosing totaling 300 mg.
Day 5: Twice daily dosing totaling 400 mg. Further adjustments should be in increments no greater than 100 mg/day within the recommended dose range of 400-800 mg/day. Based on response and tolerability, may be administered three times daily.
400 to 800 mg/day 800 mg/day Schizophrenia-Maintenance Not applicable. 400 to 800 mg/day 800 mg/day Bipolar Mania- Adults Monotherapy or as an adjunct to lithium or divalproex Day 1: Twice daily dosing totaling 100 mg. Day 2: Twice daily dosing totaling 200 mg.
Day 3: Twice daily dosing totaling 300 mg. Day 4: Twice daily dosing totaling 400 mg. Further dosage adjustments up to 800 mg/day by Day 6 should be in increments of no greater than 200 mg/day.
400 to 800 mg/day 800 mg/day Bipolar Mania- Children and Adolescents (10 to 17 years), Monotherapy Day 1: 25 mg twice daily. Day 2: Twice daily dosing totaling 100 mg. Day 3: Twice daily dosing totaling 200 mg.
Day 4: Twice daily dosing totaling 300 mg. Day 5: Twice daily dosing totaling 400 mg. Further adjustments should be in increments no greater than 100 mg/day within the recommended dose range of 400-600 mg/day.
Based on response and tolerability, may be administered three times daily. 400 to 600 mg/day 600 mg/day Bipolar Depression- Adults Administer once daily at bedtime. Day 1: 50 mg Day 2: 100 mg Day 3: 200 mg Day 4: 300 mg 300 mg/day 300 mg/day Bipolar I Disorder Maintenance Therapy- Adults Administer twice daily totaling 400-800 mg/day as adjunct to lithium or divalproex.
Generally, in the maintenance phase, patients continued on the same dose on which they were stabilized. 400 to 800 mg/day 800 mg/day Maintenance Treatment for Schizophrenia and Bipolar I Disorder Maintenance Treatment– Patients should be periodically reassessed to determine the need for maintenance treatment and the appropriate dose for such treatment [see Clinical Studies (14.2) ] .
2.3Dose Modifications in Elderly Patients Consideration should be given to a slower rate of dose titration and a lower target dose…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS Quetiapine Tablets, USP 25 mg are Peach coloured, film coated, round shape, biconvex tablets, debossed with "262" on other side and plain on other side Quetiapine Tablets, USP 50 mg are White coloured, film coated, round shape, biconvex tablets, debossed with"337" on one side and plain on other side Quetiapine Tablets, USP 100 mg are Yellow coloured film coated, round shape, biconvex tablets, debossed with "261" on one side and plain on other side Quetiapine Tablets, USP 150 mg are Off white to light yellow coloured, film coated, round shape, biconvex tablets, debossed with "353" on one side and plain on other side Quetiapine Tablets, USP 200 mg are White coloured, film coated, round shape, biconvex tablets, debossed with "260" on one side and plain on other side Quetiapine Tablets, USP 300 mg are White coloured, film coated, capsule shaped, biconvex tablets, debossed with "259" on one side and plain on other side Quetiapine Tablets, USP 400 mg are Yellow coloured, film coated, capsule shaped, biconvex tablets, debossed with ''336'' on one side and plain on other side Tablets: 25 mg, 50 mg, 100 mg, 150mg, 200 mg, 300 mg, and 400 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to quetiapine or to any excipients in the quetiapine formulation. Anaphylactic reactions have been reported in patients treated with quetiapine. Known hypersensitivity to quetiapine or any components in the formulation. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS · Cerebrovascular Adverse Reactions: Increased incidence of cerebrovascular adverse reactions (e.g., stroke, transient ischemic attack) has been seen in elderly patients with dementia-related psychoses treated with atypical antipsychotic drugs ( 5.3 ) · Neuroleptic Malignant Syndrome (NMS): Manage with immediate discontinuation and close monitoring ( 5.4 ) · Metabolic Changes: Atypical antipsychotics have been associated with metabolic changes. These metabolic changes include hyperglycemia, dyslipidemia, and weight gain ( 5.5 ) · Hyperglycemia and Diabetes Mellitus: Monitor patients for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness.
Monitor glucose regularly in patients with diabetes or at risk for diabetes · Dyslipidemia: Undesirable alterations have been observed in patients treated with atypical antipsychotics. Appropriate clinical monitoring is recommended, including fasting blood lipid testing at the beginning of, and periodically, during treatment · Weight Gain: Gain in body weight has been observed; clinical monitoring of weight is recommended · Tardive Dyskinesia: Discontinue if clinically appropriate ( 5.6 ) · Hypotension: Use with caution in patients with known cardiovascular or cerebrovascular disease ( 5.7 ) · Increased Blood Pressure in Children and Adolescents: Monitor blood pressure at the beginning of, and periodically during treatment in children and adolescents ( 5.9 ) · Leukopenia, Neutropenia and Agranulocytosis: Monitor complete blood count frequently during the first few months of treatment in patients with a pre-existing low white cell count or a history of leukopenia/neutropenia and discontinue quetiapine at the first sign of a decline in WBC in absence of other causative factors ( 5.10 ) · Cataracts: Lens changes have been observed in patients during long-term quetiapine treatment.
Lens examination is recommended when starting treatment and at 6-month intervals during chronic treatment ( 5.11 ) · Anticholinergic (antimuscarinic) Effects: Use with caution with other anticholinergic drugs and in patients with urinary retention, prostatic hypertrophy, or constipation ( 5.20 )
5.1Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analysis of 17 placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear. quetiapine is not approved for the treatment of patients with dementia-related psychosis [see Boxed Warning ] .
5.2Suicidal Thoughts and Behaviors in Adolescents and Young Adults Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicid…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: Increased mortality in elderly patients with dementia-related psychosis [see Warnings and Precautions (5.1) ] Suicidal thoughts and behaviors in adolescents and young adults [see Warnings and Precautions (5.2) ] Cerebrovascular adverse reactions, including stroke in elderly patients with dementia-related psychosis [see Warnings and Precautions (5.3 )] Neuroleptic Malignant Syndrome (NMS) [see Warnings and Precautions (5.4 )] Metabolic changes (hyperglycemia, dyslipidemia, weight gain) [see Warnings and Precautions (5.5 )] Tardive dyskinesia [see Warnings and Precautions (5.6 )] Hypotension [see Warnings and Precautions (5.7 )] Falls [ see Warnings and Precautions (5.8) ] Increases in blood pressure (children and adolescents) [see Warnings and Precautions ( 5.9 )] Leukopenia, neutropenia and agranulocytosis [see Warnings and Precautions ( 5.10 )] Cataracts [see Warnings and Precautions ( 5.11 )] QT Prolongation [see Warnings and Precautions ( 5.12 )] Seizures [see Warnings and Precautions ( 5.13 )] Hypothyroidism [see Warnings and Precautions ( 5.14 )] Hyperprolactinemia [see Warnings and Precautions ( 5.15 )] Potential for cognitive and motor impairment [see Warnings and Precautions ( 5.16 )] Body temperature regulation [see Warnings and Precautions ( 5.17 )] Dysphagia [see Warnings and Precautions ( 5.18 )] Discontinuation Syndrome [see Warnings and Precautions ( 5.19 )] Anticholinergic (antimuscarinic) Effects [see Warnings and Precautions ( 5.20 )] • Most common adverse reactions (incidence ≥ 5% and twice placebo): Adults: somnolence, dry mouth, dizziness, constipation, asthenia, abdominal pain, postural hypotension, pharyngitis, weight gain, lethargy, ALT increased, dyspepsia ( 6.1 ) • Children and Adolescents: somnolence, dizziness, fatigue, increased appetite, nausea, vomiting, dry mouth, tachycardia, weight increased ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ascend Laboratories, LLC at 1-877-ASC-RX01 (877-272-7901) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Study Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Adults: The information below is derived from a clinical trial database for quetiapine consisting of over 4,300 patients. This database includes 698 patients exposed to quetiapine for the treatment of bipolar depression, 405 patients exposed to quetiapine for the treatment of acute bipolar mania (monotherapy and adjunct therapy), 646 patients exposed to quetiapine for the maintenance treatment of bipolar I disorder as adjunct therapy, and approximately 2600 patients and/or normal subjects exposed to 1 or more doses of quetiapine for the treatment of schizophrenia.
Of these approximately 4,300 subjects, approximately 4,000 (2,300 in schizophrenia, 405 in acute bipolar mania, 698 in bipolar depression, and 646 for the maintenance treatment of bipolar I disorder) were patients who participated in multiple dose effectiveness trials, and their experience corresponded to approximately 2,400 patient-years. The conditions and duration of treatment with quetiapine varied greatly and included (in overlapping categories) open-label and double-blind phases of studies, inpatients and outpatients, fixed-dose and dose-titration studies, and short-term or longer-term exposure.
Adverse reactions were assessed by collecting adverse reactions, results of physical examinations, vital signs, weights, laboratory analyses, ECGs, and results of ophthalmologic examinations. The stated frequencies of adverse reactions represent the proportion of individuals who experienced, at least once, an adverse reaction of the type listed. Adverse Reactions Associated with Discont…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Concomitant use of strong CYP3A4 inhibitors: Reduce quetiapine dose to one sixth when coadministered with strong CYP3A4 inhibitors (e.g., ketoconazole, ritonavir) ( 2.5 , 7.1 , 12.3 ) Concomitant use of strong CYP3A4 inducers: Increase quetiapine dose up to 5 fold when used in combination with a chronic treatment (more than 7-14 days) of potent CYP3A4 inducers (e.g., phenytoin, rifampin, St. John’s wort) ( 2.6 , 7.1 , 12.3 ) Discontinuation of strong CYP3A4 inducers: Reduce quetiapine dose by 5-fold within 7-14 days of discontinuation of CYP3A4 inducers ( 2.6 , 7.1 , 12.3 )
7.1Effect of Other Drugs on Quetiapine The risks of using quetiapine in combination with other drugs have not been extensively evaluated in systematic studies. Given the primary CNS effects of quetiapine, caution should be used when it is taken in combination with other centrally acting drugs. Quetiapine potentiated the cognitive and motor effects of alcohol in a clinical trial in subjects with selected psychotic disorders, and alcoholic beverages should be limited while taking quetiapine.
Quetiapine exposure is increased by the prototype CYP3A4 inhibitors (e.g., ketoconazole, itraconazole, indinavir, ritonavir, nefazodone, etc.) and decreased by the prototype CYP3A4 inducers (e.g., phenytoin, carbamazepine, rifampin, avasimibe, St. John’s wort etc.). Dose adjustment of quetiapine will be necessary if it is co-administered with potent CYP3A4 inducers or inhibitors.
CYP3A4 inhibitors: Coadministration of ketoconazole, a potent inhibitor of cytochrome CYP3A4, resulted in significant increase in quetiapine exposure. The dose of quetiapine should be reduced to one sixth of the original dose if co-administered with a strong CYP3A4 inhibitor [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3)] . CYP3A4 inducers: Coadministration of quetiapine and phenytoin, a CYP3A4 inducer increased the mean oral clearance of quetiapine by 5- fold.
Increased doses of quetiapine up to 5 fold may be required to maintain control of symptoms of schizophrenia in patients receiving quetiapine and phenytoin, or other known potent CYP3A4 inducers [see Dosage and Administration (2.6) and Clinical Pharmacology (12.3)] . When the CYP3A4 inducer is discontinued, the dose of quetiapine should be reduced to the original level within 7-14 days [see Dosage and Administration (2.6)] . Anticholinergic Drugs: Concomitant treatment with quetiapine and other drugs with anticholinergic activity can increase the risk for severe gastrointestinal adverse reactions related to hypomotility.
Quetiapine should be used with caution in patients receiving medications having anticholinergic (antimuscarinic) effects [see Warnings and Precautions (5.20)]. The potential effects of several concomitant medications on quetiapine pharmacokinetics were studied [see Clinical Pharmacology (12.3)] .
7.2Effect of Quetiapine on Other Drugs Because of its potential for inducing hypotension, Quetiapine may enhance the effects of certain antihypertensive agents. Quetiapine may antagonize the effects of levodopa and dopamine agonists. There are no clinically relevant pharmacokinetic interactions of quetiapine on other drugs based on the CYP pathway.
Quetiapine and its metabolites are non-inhibitors of major metabolizing CYP’s (1A2, 2C9, 2C19, 2D6, and 3A4).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS · Pregnancy: May cause extrapyramidal and/or withdrawal symptoms in neonates with third trimester exposure. ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including quetiapine tablets, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/ . Risk Summary Neonates exposed to antipsychotic drugs ( including quetiapine tablet) during the third trimester are at risk for extrapyramidal and/or withdrawal symptoms following delivery (see Clinical Considerations).
Overall available data from published epidemiologic studies of pregnant women exposed to quetiapine have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data). There are risks to the mother associated with untreated schizophrenia, bipolar I, or major depressive disorder, and with exposure to antipsychotics, including, quetiapine tablet during pregnancy (see Clinical Considerations) . In animal studies, embryo-fetal toxicity occurred including delays in skeletal ossification at approximately 1 and 2 times the maximum recommended human dose (MRHD) of 800 mg/day in both rats and rabbits, and an increased incidence of carpal/tarsal flexure (minor soft tissue anomaly) in rabbit fetuses at approximately 2 times the MRHD.
In addition, fetal weights were decreased in both species. Maternal toxicity (observed as decreased body weights and/or death) occurred at 2 times the MRHD in rats and approximately 1-2 times the MRHD in rabbits. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or fetal risk There is a risk to the mother from untreated schizophrenia, or bipolar I disorder, including increased risk of relapse, hospitalization, and suicide.
Schizophrenia and bipolar I disorder are associated with increased adverse perinatal outcomes, including preterm birth. It is not known if this is a direct result of the illness or other comorbid factors. A prospective, longitudinal study followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy.
The women who discontinued antidepressants during pregnancy were more likely to experience a relapse of major depression than women who continued antidepressants. Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Fetal/neonatal adverse reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs, including quetiapine tablets, during the third trimester of pregnancy.
These symptoms varied in severity. Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization.
Data Human Data Published data from observational studies, birth registries, and case reports on the use of atypical antipsychotics during pregnancy do not report a clear association with antipsychotics and major birth defects. A retrospective cohort study from a Medicaid database of 9258 women exposed t…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including quetiapine tablets, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/ . Risk Summary Neonates exposed to antipsychotic drugs ( including quetiapine tablet) during the third trimester are at risk for extrapyramidal and/or withdrawal symptoms following delivery (see Clinical Considerations).
Overall available data from published epidemiologic studies of pregnant women exposed to quetiapine have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data). There are risks to the mother associated with untreated schizophrenia, bipolar I, or major depressive disorder, and with exposure to antipsychotics, including, quetiapine tablet during pregnancy (see Clinical Considerations) . In animal studies, embryo-fetal toxicity occurred including delays in skeletal ossification at approximately 1 and 2 times the maximum recommended human dose (MRHD) of 800 mg/day in both rats and rabbits, and an increased incidence of carpal/tarsal flexure (minor soft tissue anomaly) in rabbit fetuses at approximately 2 times the MRHD.
In addition, fetal weights were decreased in both species. Maternal toxicity (observed as decreased body weights and/or death) occurred at 2 times the MRHD in rats and approximately 1-2 times the MRHD in rabbits. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or fetal risk There is a risk to the mother from untreated schizophrenia, or bipolar I disorder, including increased risk of relapse, hospitalization, and suicide.
Schizophrenia and bipolar I disorder are associated with increased adverse perinatal outcomes, including preterm birth. It is not known if this is a direct result of the illness or other comorbid factors. A prospective, longitudinal study followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy.
The women who discontinued antidepressants during pregnancy were more likely to experience a relapse of major depression than women who continued antidepressants. Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Fetal/neonatal adverse reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs, including quetiapine tablets, during the third trimester of pregnancy.
These symptoms varied in severity. Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization.
Data Human Data Published data from observational studies, birth registries, and case reports on the use of atypical antipsychotics during pregnancy do not report a clear association with antipsychotics and major birth defects. A retrospective cohort study from a Medicaid database of 9258 women exposed to antipsychotics during pregnancy did not indicate an overall increased risk of major birth defects. Animal Data When pregnant rats and rabbits we…
🧒 Pediatric Use ▾
8.4Pediatric Use In general, the adverse reactions observed in children and adolescents during the clinical trials were similar to those in the adult population with few exceptions. Increases in systolic and diastolic blood pressure occurred in children and adolescents and did not occur in adults. Orthostatic hypotension occurred more frequently in adults (4-7%) compared to children and adolescents (< 1%) [see Warnings and Precautions ( 5.7 ) and Adverse Reactions ( 6.1 )].
Schizophrenia The efficacy and safety of quetiapine in the treatment of schizophrenia in adolescents aged 13 to 17 years were demonstrated in one 6-week, double-blind, placebo-controlled trial [see Indications and Usage ( 1.1 ), Dosage and Administration ( 2.2 ), Adverse Reactions ( 6.1 ), and Clinical Studies ( 14.1 )]. Safety and effectiveness of quetiapine in pediatric patients less than 13 years of age with schizophrenia have not been established. Maintenance The safety and effectiveness of quetiapine in the maintenance treatment of bipolar disorder has not been established in pediatric patients less than 18 years of age.
The safety and effectiveness of quetiapine in the maintenance treatment of schizophrenia has not been established in any patient population, including pediatric patients. Bipolar Mania The efficacy and safety of quetiapine in the treatment of mania in children and adolescents ages 10 to 17 years with bipolar I disorder was demonstrated in a 3-week, double-blind, placebo-controlled, multicenter trial [see Indications and Usage ( 1.2 ), Dosage and Administration ( 2.3 ), Adverse Reactions ( 6.1 ), and Clinical Studies ( 14.2 )] .
Safety and effectiveness of quetiapine in pediatric patients less than 10 years of age with bipolar mania have not been established. Bipolar Depression Safety and effectiveness of Quetiapine in pediatric patients less than 18 years of age with bipolar depression have not been established. A clinical trial with SEROQUEL XR was conducted in children and adolescents (10 to 17 years of age) with bipolar depression, efficacy was not established.
Some differences in the pharmacokinetics of quetiapine were noted between children/adolescents (10 to 17 years of age) and adults. When adjusted for weight, the AUC and Cmax of quetiapine were 41% and 39% lower, respectively, in children and adolescents compared to adults. The pharmacokinetics of the active metabolite, norquetiapine, were similar between children/adolescents and adults after adjusting for weight [see Clinical Pharmacology ( 12.3 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Of the approximately 3700 patients in clinical studies with quetiapine, 7% (232) were 65 years of age or over. In general, there was no indication of any different tolerability of quetiapine in the elderly compared to younger adults. Nevertheless, the presence of factors that might decrease pharmacokinetic clearance, increase the pharmacodynamic response to quetiapine, or cause poorer tolerance or orthostasis, should lead to consideration of a lower starting dose, slower titration, and careful monitoring during the initial dosing period in the elderly.
The mean plasma clearance of quetiapine was reduced by 30% to 50% in elderly patients when compared to younger patients [ see Clinical Pharmacology (12.3) and Dosage and Administration (2.3 ) ] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Experience In clinical trials, survival has been reported in acute overdoses of up to 30 grams of quetiapine. Most patients who overdosed experienced no adverse reactions or recovered fully from the reported reactions. Death has been reported in a clinical trial following an overdose of 13.6 grams of quetiapine alone.
In general, reported signs and symptoms were those resulting from an exaggeration of the drug’s known pharmacological effects, i.e., drowsiness, sedation, tachycardia, hypotension, and anticholinergic toxicity including coma and delirium. Patients with pre-existing severe cardiovascular disease may be at an increased risk of the effects of overdose [see Warnings and Precautions ( 5.12 )]. One case, involving an estimated overdose of 9,600 mg, was associated with hypokalemia and first- degree heart block.
In post-marketing experience, there were cases reported of QT prolongation with overdose.
10.2Management of Overdosage Establish and maintain an airway and ensure adequate oxygenation and ventilation. Cardiovascular monitoring should commence immediately and should include continuous electrocardiographic monitoring to detect possible arrhythmias. Appropriate supportive measures are the mainstay of management.
For the most up-to-date information on the management of quetiapine overdosage, contact a certified Regional Poison Control Center (1-800-222-1222).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of quetiapine in the listed indications is unclear. However, the efficacy of quetiapine in these indications could be mediated through a combination of dopamine type 2 (D 2 ) and serotonin type 2 (5HT 2 ) antagonism. The active metabolite, N-desalkyl quetiapine (norquetiapine), has similar activity at D 2 , but greater activity at 5HT2A receptors, than the parent drug (quetiapine).
12.2Pharmacodynamics Quetiapine and its metabolite, norquetiapine, have affinity for multiple neurotransmitter receptors with norquetiapine binding with higher affinity than quetiapine in general. The Ki values for quetiapine and norquetiapine at the dopamine D1 are 428/99.8 nM, at D2 626/489nM, at serotonin 5HT1A 1040/191 nM at 5HT2A 38/2.9 nM, at histamine H1 4.4/1.1 nM, at muscarinic M1 1086/38.3 nM, and at adrenergic α1b 14.6/46.4 nM and, at α2 receptors 617/1290 nM, respectively. Quetiapine and norquetiapine lack appreciable affinity to the benzodiazepine receptors.
Effect on QT Interval In clinical trials, quetiapine was not associated with a persistent increase in QT intervals. However, the QT effect was not systematically evaluated in a thorough QT study. In post marketing experience, there were cases reported of QT prolongation in patients who overdosed on quetiapine [see Overdosage ( 10.1 )] , in patients with concomitant illness, and in patients taking medicines known to cause electrolyte imbalance or increase QT interval.
12.3Pharmacokinetics Adults Quetiapine activity is primarily due to the parent drug. The multiple-dose pharmacokinetics of quetiapine are dose-proportional within the proposed clinical dose range, and quetiapine accumulation is predictable upon multiple dosing. Elimination of quetiapine is mainly via hepatic metabolism with a mean terminal half-life of about 6 hours within the proposed clinical dose range.
Steady-state concentrations are expected to be achieved within two days of dosing. Quetiapine is unlikely to interfere with the metabolism of drugs metabolized by cytochrome P450 enzymes. Children and Adolescents At steady-state the pharmacokinetics of the parent compound, in children and adolescents (10-17 years of age), were similar to adults.
However, when adjusted for dose and weight, AUC and Cmax of the parent compound were 41% and 39% lower, respectively, in children and adolescents than in adults. For the active metabolite, norquetiapine, AUC and C max were 45% and 31% higher, respectively, in children and adolescents than in adults. When adjusted for dose and weight, the pharmacokinetics of the metabolite, norquetiapine, was similar between children and adolescents and adults [see Use in Specific Populations (8.4) ] .
Absorption Quetiapine is rapidly absorbed after oral administration, reaching peak plasma concentrations in 1.5 hours. The tablet formulation is 100% bioavailable relative to solution. The bioavailability of quetiapine is marginally affected by administration with food, with C max and AUC values increased by 25% and 15%, respectively.
Distribution Quetiapine is widely distributed throughout the body with an apparent volume of distribution of 10±4 L/kg. It is 83% bound to plasma proteins at therapeutic concentrations. In vitro , quetiapine did not affect the binding of warfarin or diazepam to human serum albumin.
In turn, neither warfarin nor diazepam altered the binding of quetiapine. Metabolism and Elimination Following a single oral dose of 14C-quetiapine, less than 1% of the administered dose was excreted as unchanged drug, indicating that quetiapine is highly metabolized. Approximately 73% and 20% of the dose was recovered in the urine and feces, respectively.
Quetiapine is extensively metabolized by the liver. The major metabolic pathways are sulfoxidation to the sulfoxide metabolite and oxidation to the parent acid metabolite; both metabolites are pharmacologically inactive. In vitro studies using human liver micros…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of quetiapine in the listed indications is unclear. However, the efficacy of quetiapine in these indications could be mediated through a combination of dopamine type 2 (D 2 ) and serotonin type 2 (5HT 2 ) antagonism. The active metabolite, N-desalkyl quetiapine (norquetiapine), has similar activity at D 2 , but greater activity at 5HT2A receptors, than the parent drug (quetiapine).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Quetiapine tablets, USP 25 mg Peach coloured, film coated, round shape, biconvex tablets, debossed with "262” on one side and plain on other side. NDC 71335-1562-1: 30 Tablets in a BOTTLE NDC 71335-1562-2: 60 Tablets in a BOTTLE NDC 71335-1562-3: 90 Tablets in a BOTTLE NDC 71335-1562-4: 120 Tablets in a BOTTLE NDC 71335-1562-5: 100 Tablets in a BOTTLE Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Quetiapine is an atypical antipsychotic belonging to a chemical class, the dibenzothiazepine derivatives. The chemical designation is 2-[2-(4-dibenzo [ b,f ] [1,4]thiazepin-11-yl-1-piperazinyl) ethoxy]-ethanol fumarate (2:1) (salt). It is present in tablets as the fumarate salt.
All doses and tablet strengths are expressed as milligrams of base, not as fumarate salt. Its molecular formula is C 42 H 50 N 6 O 4 S 2 •C 4 H 4 O 4 and it has a molecular weight of 883.11 (fumarate salt). The structural formula is: Quetiapine fumarate USP is a white to off-white crystalline powder which is moderately soluble in water.
Quetiapine tablets, USP is supplied for oral administration as 25 mg (round peach), 50 mg (round, white), 100 mg (round yellow), 150 mg (round, off white to light yellow), 200 mg (round, white), 300 mg (capsule-shaped, white), and 400 mg (capsule-shaped, yellow) tablets. Inactive ingredients are povidone, dibasic dicalcium phosphate dihydrate, microcrystalline cellulose, sodium starch glycolate, lactose monohydrate, magnesium stearate, hypromellose, polyethylene glycol and titanium dioxide. The 25 mg tablets contain red iron oxide and yellow iron oxide and the 100 mg, 150 mg and 400 mg tablets contain only yellow iron oxide.
Each 25 mg tablet contains 28.78 mg of quetiapine fumarate USP equivalent to 25 mg quetiapine. Each 50 mg tablet contains 57.56 mg of quetiapine fumarate USP equivalent to 50 mg quetiapine. Each 100 mg tablet contains 115.13 mg of quetiapine fumarate USP equivalent to 100 mg quetiapine.
Each 150 mg tablet contains 172.70 mg of quetiapine fumarate USP equivalent to 150 mg quetiapine. Each 200 mg tablet contains 230.27 mg of quetiapine fumarate USP equivalent to 200 mg quetiapine. Each 300 mg tablet contains 345.40 mg of quetiapine fumarate USP equivalent to 300 mg quetiapine.
Each 400 mg tablet contains 460.54 mg of quetiapine fumarate USP equivalent to 400 mg quetiapine.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Patients should be advised of the following issues and asked to alert their prescriber if these occur while taking quetiapine. Increased Mortality in Elderly Patients with Dementia-Related Psychosis Patients and caregivers should be advised that elderly patients with dementia-related psychosis treated with atypical antipsychotic drugs are at increased risk of death compared with placebo.
Quetiapine is not approved for elderly patients with dementia-related psychosis [see Warnings and Precautions ( 5.1 )] . Suicidal Thoughts and Behaviors Patients, their families, and their caregivers should be encouraged to be alert to the emergence of anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, mania, other unusual changes in behavior, worsening of depression, and suicidal ideation, especially early during antidepressant treatment and when the dose is adjusted up or down.
Families and caregivers of patients should be advised to look for the emergence of such symptoms on a day-to-day basis, since changes may be abrupt. Such symptoms should be reported to the patient's prescriber or health professional, especially if they are severe, abrupt in onset, or were not part of the patient's presenting symptoms. Symptoms such as these may be associated with an increased risk for suicidal thinking and behavior and indicate a need for very close monitoring and possibly changes in the medication [see Warnings and Precautions ( 5.2 )].
Neuroleptic Malignant Syndrome (NMS) Patients should be advised to report to their physician any signs or symptoms that may be related to NMS. These may include muscle stiffness and high fever [see Warnings and Precautions ( 5.4 )]. Hyperglycemia and Diabetes Mellitus Patients should be aware of the symptoms of hyperglycemia (high blood sugar) and diabetes mellitus.
Patients who are diagnosed with diabetes, those with risk factors for diabetes, or those that develop these symptoms during treatment should have their blood glucose monitored at the beginning of and periodically during treatment [see Warnings and Precautions ( 5.5 )]. Hyperlipidemia Patients should be advised that elevations in total cholesterol, LDL-cholesterol and triglycerides and decreases in HDL- cholesterol may occur. Patients should have their lipid profile monitored at the beginning of and periodically during treatment [see Warnings and Precautions ( 5.5 )] .
Weight Gain Patients should be advised that they may experience weight gain. Patients should have their weight monitored regularly [see Warnings and Precautions ( 5.5 )]. Orthostatic Hypotension Patients should be advised of the risk of orthostatic hypotension (symptoms include feeling dizzy or lightheaded upon standing, which may lead to falls), especially during the period of initial dose titration, and also at times of re-initiating treatment or increases in dose [see Warnings and Precautions ( 5.7 )] .
Increased Blood Pressure in Children and Adolescents Children and adolescent patients should have their blood pressure measured at the beginning of, and periodically during, treatment [ see Warnings and Precautions ( 5.9 ) ]. Leukopenia/Neutropenia Patients with a pre-existing low WBC or a history of drug induced leukopenia/neutropenia should be advised that they should have their CBC monitored while taking quetiapine. Patients should be advised to talk to their doctor as soon as possible if they have a fever, flu-like symptoms, sore throat, or any other infection as this could be a result of a very low WBC, which may require quetiapine to be stopped and/or treatment to be given [ see Warnings and Precautions ( 5.10 ) ].
Interference with Cognitive and Motor Performance Patients should be advised of the risk of somnolence or sedation (which may lead to falls), especially during the…
💬 Medication Guide ▾
MEDICATION GUIDE Quetiapine Tablets, USP (kwe-TYE-a-peen) Read this Medication Guide before you start taking quetiapine tablets and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about quetiapine? Quetiapine may cause serious side effects, including: 1 . risk of death in the elderly with dementia. Medicines like quetiapine can increase the risk of death in elderly people who have memory loss (dementia).
Quetiapine is not for treating psychosis in the elderly with dementia. 2 . risk of suicidal thoughts or actions (antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions). Talk to your or your family member’s healthcare provider about : o all risks and benefits of treatment with antidepressant medicines. o all treatment choices for depression or other serious mental illness Antidepressant medications may increase suicidal thoughts or actions in some children, teenagers, and young adults within the first few months of treatment.
Depression and other serious mental illnesses are the most important causes of suicidal thoughts and actions. Some people may have a particularly high risk of having suicidal thoughts or actions. These include people who have (or have a family history of) depression, bipolar illness (also called manic-depressive illness), or suicidal thoughts or actions.
How can I watch for and try to prevent suicidal thoughts and actions in myself or a family member? o Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. This is very important when an antidepressant medicine is started or when the dose is changed. o Call the healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings. o Keep all follow-up visits with the healthcare provider as scheduled. Call the healthcare provider between visits as needed, especially if you have concerns about symptoms.
Call a healthcare provider right away if you or your family member has any of the following symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling very agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood What else do I need to know about antidepressant medicines?
Never stop an antidepressant medicine without first talking to your healthcare provider. Stopping an antidepressant medicine suddenly can cause other symptoms. Antidepressants are medicines used to treat depression and other illnesses.
It is important to discuss all the risks of treating depression, and also the risks of not treating it. Patients and their families or other caregivers should discuss all treatment choices with the healthcare provider, not just the use of antidepressants. Antidepressant medicines have other side effects.
Talk to the healthcare provider about the side effects of the medicine prescribed for you or your family member. Antidepressant medicines can interact with other medicines. Know all of the medicines that you or your family member take.
Keep a list of all medicines to show the healthcare provider. Do not start new medicines without first checking with your healthcare provider. Not all antidepressant medicines prescribed for children are FDA approved for use in children.
Talk to your child’s healthcare provider for more information. What is quetiapine? Quetiapine is a prescription medicine used to treat: schizophrenia in people 13 years of age or older bipolar disorder in adults, including: depressive episodes associated with bipolar di…