
Nifedipine 30 mg Tablet, Extended Release, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nifedipine is used to treat high blood pressure and to control angina (chest pain). Nifedipine is in a class of medications called calcium-channel blockers. It lowers blood pressure by relaxing the blood vessels so the heart does not have to pump as hard. It controls chest pain by increasing the supply of blood and oxygen to the heart. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood vessels, kidneys and other parts of the body. Damage to these organs may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss...
Read the full MedlinePlus article ↗- Nifedipine relaxes and widens your blood vessels. If you have high blood pressure, that widening makes it easier for your heart to pump, which brings your numbers down and lowers y...
- What exactly is nifedipine supposed to do for me?
- It depends on your form. If you're taking the extended-release tablet, a high-fat meal can noticeably increase the amount of drug that gets into your bloodstream. That doesn't mean...
- Does it matter if I take nifedipine with food?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nifedipine — tap one for details:
Nifedipine may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3J2P07GVB6
Cellulose acetate is a plant-derived polymer made by chemically modifying cellulose fibers. In medications, it serves as a film-coating material for tablets and capsules to protect the drug, control release, and improve appearance.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 660YQ98I10
Potassium chloride is a mineral salt used in medicines as a buffer and to help maintain the proper pH balance and stability of the formulation during storage and use.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1954 | $17.59 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nifedipine 30 mg 68682-0105-10 | Oceanside | 100 tablets | $0.100 | AB1 | FDA listed | — |
| Nifedipine 30 mg 50742-0620-01 | Ingenus | 100 tablets | $0.124 | AB1 | Availability likely | — |
| Nifedipine 30 mg 59651-0295-01 | Aurobindo | 100 tablets | $0.124 | AB1 | Availability likely | — |
| nifedipine 30 mg 68682-0108-10 | Oceanside | 100 tablets | $0.133 | AB2 | FDA listed | — |
| Nifedipine 30 mg 00904-7208-06 | Major | 1 tablet | $0.135 | AB2 | Availability likely | — |
| Nifedipine 30 mg 24979-0011-12 | Upsher-Smith | 300 tablets | $0.135 | AB2 | Availability likely | — |
| Nifedipine ER 30 mg 50268-0597-15 | AvPAK | 1 tablet | $0.135 | AB2 | Availability likely | — |
| Nifedipine 30 mg 50742-0260-01 | Ingenus | 100 tablets | $0.135 | AB2 | Availability likely | — |
| Nifedipine 30 mg 62135-0521-90 | Chartwell | 90 tablets | $0.135 | AB2 | Availability likely | — |
| Nifedipine 30 mg 62175-0260-37 | Lannett | 100 tablets | $0.135 | AB2 | Availability likely | — |
| Nifedipine 30 mg 67877-0757-01 | Ascend | 100 tablets | $0.135 | AB2 | Availability likely | — |
| Nifedipine 30 mg 68084-0597-01 | American | 1 tablet | $0.135 | AB2 | Availability likely | — |
| Procardia XL 30 mg 00069-2650-41 | Pfizer | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 46708-0732-31 | Alembic | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 50090-6203-00 | A-S | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 50090-6732-00 | A-S | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 51655-0593-26 | Northwind | 90 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 55154-4690-00 | Cardinal | 1 tablet | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 55289-0798-07 | PD-Rx | 7 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 60429-0047-01 | Golden | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 62332-0732-31 | Alembic | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 63187-0875-30 | Proficient | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 67046-0260-03 | Coupler | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 67296-2157-01 | Redpharm | 10 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 68071-2619-03 | NuCare | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 68382-0685-01 | Zydus | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 68788-7642-01 | Preferred | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 70518-2679-00 | REMEDYREPACK | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 70771-1190-00 | Zydus | 1000 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 71205-0963-00 | Proficient | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 71335-1550-01 | Bryant | 30 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 71610-0290-60 | Aphena | 90 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mgthis 72162-1277-09 | Bryant | 90 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 72789-0484-01 | PD-Rx | 100 tablets | — | AB2 | FDA listed | — |
| Nifedipine 30 mg 71610-0144-60 | Aphena | 90 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 50090-5284-00 | A-S | 30 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 71610-0689-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 68382-0688-01 | Zydus | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 67296-2170-01 | Redpharm | 14 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 72162-1887-02 | Bryant | 300 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 72162-2534-01 | Bryant | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 70771-1365-00 | Zydus | 1000 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 51407-0622-01 | Golden | 100 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 63629-9109-01 | Bryant | 300 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 71610-0841-60 | Aphena | 90 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 68071-2838-03 | NuCare | 30 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 51655-0798-26 | Northwind | 90 tablets | — | AB1 | FDA listed | — |
| Nifedipine 30 mg 51655-0990-26 | Northwind | 90 tablets | — | AB2 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72162-1277-01 | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (72162-1277-1) | 2023-05-08 | Active |
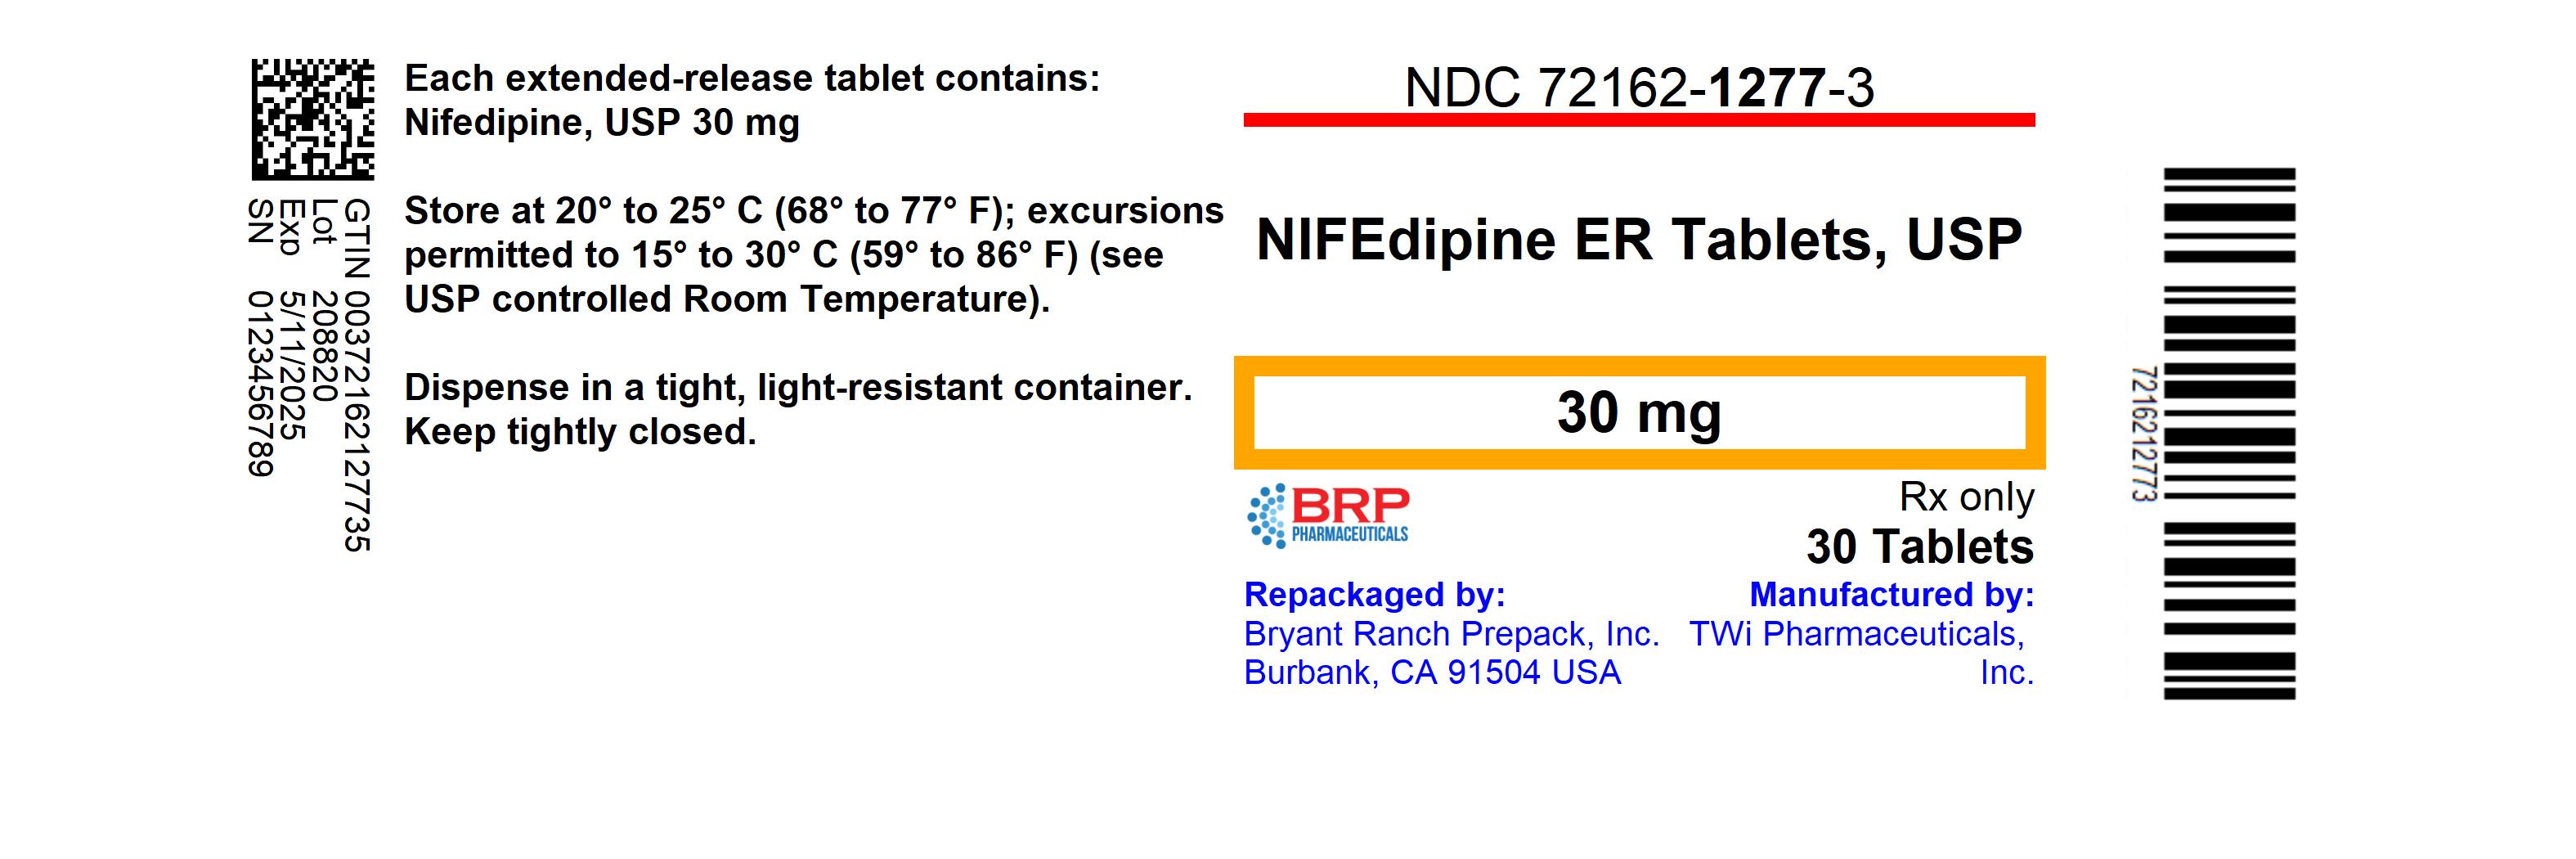
| 72162-1277-03 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (72162-1277-3) | 2023-05-08 | Active |
| 72162-1277-09 You're viewing this | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (72162-1277-9) | 2023-05-08 | Active |
You're viewing one of 3 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 72162-1277-09?
What is the difference between NDC 72162-1277-09 and NDC 72162-1277-03?
What NDC number is used to bill for this package of Nifedipine 30 mg Tablet, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE I. Vasospastic Angina Nifedipine extended-release tablets are indicated for the management of vasospastic angina confirmed by any of the following criteria: 1) classical pattern of angina at rest accompanied by ST segment elevation, 2) angina or coronary artery spasm provoked by ergonovine, or 3) angiographically demonstrated coronary artery spasm. In those patients who have had angiography, the presence of significant fixed obstructive disease is not incompatible with the diagnosis of vasospastic angina, provided that the above criteria are satisfied.
Nifedipine extended-release tablets may also be used where the clinical presentation suggests a possible vasospastic component, but where vasospasm has not been confirmed, e.g., where pain has a variable threshold on exertion, or in unstable angina where electrocardiographic findings are compatible with intermittent vasospasm, or when angina is refractory to nitrates and/or adequate doses of beta blockers. II. Chronic Stable Angina (Classical Effort-Associated Angina) Nifedipine extended-release tablets are indicated for the management of chronic stable angina (effort-associated angina) without evidence of vasospasm in patients who remain symptomatic despite adequate doses of beta blockers and/or organic nitrates or who cannot tolerate those agents.
In chronic stable angina (effort-associated angina), nifedipine has been effective in controlled trials of up to eight weeks duration in reducing angina frequency and increasing exercise tolerance, but confirmation of sustained effectiveness and evaluation of long-term safety in these patients is incomplete. Controlled studies in small numbers of patients suggest concomitant use of nifedipine and beta-blocking agents may be beneficial in patients with chronic stable angina, but available information is not sufficient to predict with confidence the effects of concurrent treatment, especially in patients with compromised left ventricular function or cardiac conduction abnormalities.
When introducing such concomitant therapy, care must be taken to monitor blood pressure closely, since severe hypotension can occur from the combined effects of the drugs. (See WARNINGS ) III. Hypertension Nifedipine extended-release tablets are indicated for the treatment of hypertension, to lower blood pressure.
Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including nifedipine extended-release tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake.
Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hyperten…
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION Dosage must be adjusted according to each patient’s needs. Therapy for either hypertension or angina should be initiated with 30 or 60 mg once daily. Nifedipine Extended-Release Tablets USP should be swallowed whole and should not be bitten or divided.
In general, titration should proceed over a 7 to 14 day period so that the physician can fully assess the response to each dose level and monitor blood pressure before proceeding to higher doses. Since steady-state plasma levels are achieved on the second day of dosing, titration may proceed more rapidly, if symptoms so warrant, provided the patient is assessed frequently. Titration to doses above 120 mg are not recommended.
Angina patients controlled on nifedipine capsules alone or in combination with other antianginal medications may be safely switched to nifedipine extended-release tablets at the nearest equivalent total daily dose (e.g., 30 mg t.i.d. of nifedipine capsules may be changed to 90 mg once daily of nifedipine extended-release tablets). Subsequent titration to higher or lower doses may be necessary and should be initiated as clinically warranted. Experience with doses greater than 90 mg in patients with angina is limited.
Therefore, doses greater than 90 mg should be used with caution and only when clinically warranted. Avoid coadministration of nifedipine with grapefruit juice (see CLINICAL PHARMACOLOGY and PRECAUTIONS: Other Interactions ). No “rebound effect” has been observed upon discontinuation of nifedipine extended-release tablets.
However, if discontinuation of nifedipine is necessary, sound clinical practice suggests that the dosage should be decreased gradually with close physician supervision. Care should be taken when dispensing nifedipine extended-release tablets to assure that the extended release dosage form has been prescribed. Coadministration with Other Antianginal Drugs Sublingual nitroglycerin may be taken as required for the control of acute manifestations of angina, particularly during nifedipine titration.
See PRECAUTIONS, Drug Interactions , for information on coadministration of nifedipine with beta blockers or long-acting nitrates.
⛔ Contraindications ▾
CONTRAINDICATIONS Known hypersensitivity reaction to nifedipine.
⚠️ Warnings ▾
WARNINGS Excessive Hypotension Although in most angina patients the hypotensive effect of nifedipine is modest and well tolerated, occasional patients have had excessive and poorly tolerated hypotension. These responses have usually occurred during initial titration or at the time of subsequent upward dosage adjustment, and may be more likely in patients on concomitant beta blockers. Severe hypotension and/or increased fluid volume requirements have been reported in patients receiving nifedipine together with a beta-blocking agent who underwent coronary artery bypass surgery using high dose fentanyl anesthesia.
The interaction with high dose fentanyl appears to be due to the combination of nifedipine and a beta blocker, but the possibility that it may occur with nifedipine alone, with low doses of fentanyl, in other surgical procedures, or with other narcotic analgesics cannot be ruled out. In nifedipine-treated patients where surgery using high dose fentanyl anesthesia is contemplated, the physician should be aware of these potential problems and, if the patient’s condition permits, sufficient time (at least 36 hours) should be allowed for nifedipine to be washed out of the body prior to surgery.
The following information should be taken into account in those patients who are being treated for hypertension as well as angina: Increased Angina and/or Myocardial Infarction Rarely, patients, particularly those who have severe obstructive coronary artery disease, have developed well documented increased frequency, duration and/or severity of angina or acute myocardial infarction on starting nifedipine or at the time of dosage increase. The mechanism of this effect is not established. Beta Blocker Withdrawal It is important to taper beta blockers if possible, rather than stopping them abruptly before beginning nifedipine.
Patients recently withdrawn from beta blockers may develop a withdrawal syndrome with increased angina, probably related to increased sensitivity to catecholamines. Initiation of nifedipine treatment will not prevent this occurrence and on occasion has been reported to increase it. Congestive Heart Failure Rarely, patients, usually receiving a beta blocker, have developed heart failure after beginning nifedipine.
Patients with tight aortic stenosis may be at greater risk for such an event, as the unloading effect of nifedipine would be expected to be of less benefit, owing to the fixed impedance to flow across the aortic valve in these patients. Gastrointestinal Obstruction Requiring Surgery There have been rare reports of obstructive symptoms in patients with known strictures in association with the ingestion of nifedipine extended-release tablets. Bezoars can occur in very rare cases and may require surgical intervention.
Cases of serious gastrointestinal obstruction have been identified in patients with no known gastrointestinal disease, including the need for hospitalization and surgical intervention. Risk factors for a gastrointestinal obstruction identified from post-marketing reports of nifedipine extended-release tablets (GITS tablet formulation) include alteration in gastrointestinal anatomy (e.g., severe gastrointestinal narrowing, colon cancer, small bowel obstruction, bowel resection, gastric bypass, vertical banded gastroplasty, colostomy, diverticulitis, diverticulosis, and inflammatory bowel disease), hypomotility disorders (e.g., constipation, gastroesophageal reflux disease, ileus, obesity, hypothyroidism, and diabetes) and concomitant medications (e.g., H2-histamine blockers, opiates, nonsteroidal anti-inflammatory drugs, laxatives, anticholinergic agents, levothyroxine, and neuromuscular blocking agents).
Gastrointestinal Ulcers Cases of tablet adherence to the gastrointestinal wall with ulceration have been reported, some requiring hospitalization and intervention.
🤒 Adverse Reactions ▾
ADVERSE EXPERIENCES Over 1000 patients from both controlled and open trials with nifedipine extended-release tablets in hypertension and angina were included in the evaluation of adverse experiences. All side effects reported during nifedipine extended-release tablets therapy were tabulated independent of their causal relation to medication. The most common side effect reported with nifedipine extended-release tablets was edema which was dose related and ranged in frequency from approximately 10% to about 30% at the highest dose studied (180 mg).
Other common adverse experiences reported in placebo-controlled trials include: Nifedipine Extended-Release Tablets (%) (N=707) Placebo (%) (N=266) Adverse Effect Headache 15.8
9.8Fatigue 5.9
4.1Dizziness 4.1
4.5Constipation 3.3
2.3Nausea 3.3
1.9Of these, only edema and headache were more common in nifedipine extended-release tablets patients than placebo patients. The following adverse reactions occurred with an incidence of less than 3.0%. With the exception of leg cramps, the incidence of these side effects was similar to that of placebo alone.
Body as a Whole/Systemic: asthenia, flushing, pain Cardiovascular: palpitations Central Nervous System: insomnia, nervousness, paresthesia, somnolence Dermatologic: pruritus, rash Gastrointestinal: abdominal pain, diarrhea, dry mouth, dyspepsia, flatulence Musculoskeletal: arthralgia, leg cramps Respiratory: chest pain (nonspecific), dyspnea Urogenital: impotence, polyuria Other adverse reactions were reported sporadically with an incidence of 1.0% or less. These include: Body as a Whole/Systemic: face edema, fever, hot flashes, malaise, periorbital edema, rigors Cardiovascular: arrhythmia, hypotension, increased angina, tachycardia, syncope Central Nervous System: anxiety, ataxia, decreased libido, depression, hypertonia, hypoesthesia, migraine, paroniria, tremor, vertigo Dermatologic: alopecia, increased sweating, urticaria, purpura Gastrointestinal: eructation, gastroesophageal reflux, gum hyperplasia, melena, vomiting, weight increase Musculoskeletal: back pain, gout, myalgias Respiratory: coughing, epistaxis, upper respiratory tract infection, respiratory disorder, sinusitis Special Senses: abnormal lacrimation, abnormal vision, taste perversion, tinnitus Urogenital/Reproductive: breast pain, dysuria, hematuria, nocturia Adverse experiences which occurred in less than 1 in 1000 patients cannot be distinguished from concurrent disease states or medications.
The following adverse experiences, reported in less than 1% of patients, occurred under conditions (e.g., open trials, marketing experience) where a causal relationship is uncertain: gastrointestinal irritation, gastrointestinal bleeding, gynecomastia. Gastrointestinal obstruction resulting in hospitalization and surgery, including the need for bezoar removal, has occurred in association with nifedipine extended-release tablets, even in patients with no prior history of gastrointestinal disease. (See WARNINGS ) Cases of tablet adherence to the gastrointestinal wall with ulceration have been reported, some requiring hospitalization and intervention.
In multiple-dose U.S. and foreign controlled studies with nifedipine capsules in which adverse reactions were reported spontaneously, adverse effects were frequent but generally not serious and rarely required discontinuation of therapy or dosage adjustment. Most were expected consequences of the vasodilator effects of nifedipine. Adverse Effect Nifedipine Capsules (%) (N=226) Placebo (%) (N=235) Dizziness, lightheadedness, giddiness 27 15 Flushing, heat sensation 25 8 Headache 23 20 Weakness 12 10 Nausea, heartburn 11 8 Muscle cramps, tremor 8 3 Peripheral edema 7 1 Nervousness, mood changes 7 4 Palpitations 7 5 Dyspnea, cough, wheezing 6 3 Nasal congestion, sore throat 6 8 There is also a large uncontrolled experience in over 2100 patients in the United States.
Most of the patients had vasospastic or resistant angina pectoris, and ab…
🆘 Overdosage ▾
OVERDOSAGE Experience with nifedipine overdosage is limited. Generally, overdosage with nifedipine leading to pronounced hypotension calls for active cardiovascular support, including monitoring of cardiovascular and respiratory function, elevation of extremities, judicious use of calcium infusion, pressor agents, and fluids. Clearance of nifedipine would be expected to be prolonged in patients with impaired liver function.
Since nifedipine is highly protein-bound, dialysis is not likely to be of any benefit. There has been one reported case of massive overdosage with nifedipine extended-release tablets. The main effects of ingestion of approximately 4800 mg of nifedipine extended-release tablets in a young man attempting suicide as a result of cocaine-induced depression was initial dizziness, palpitations, flushing, and nervousness.
Within several hours of ingestion, nausea, vomiting, and generalized edema developed. No significant hypotension was apparent at presentation, 18 hours post-ingestion. Electrolyte abnormalities consisted of a mild, transient elevation of serum creatinine, and modest elevations of LDH and CPK, but normal SGOT.
Vital signs remained stable, no electrocardiographic abnormalities were noted, and renal function returned to normal within 24 to 48 hours with routine supportive measures alone. No prolonged sequelae were observed. The effect of a single 900 mg ingestion of nifedipine capsules in a depressed anginal patient also on tricyclic antidepressants was loss of consciousness within 30 minutes of ingestion, and profound hypotension, which responded to calcium infusion, pressor agents, and fluid replacement.
A variety of ECG abnormalities were seen in this patient with a history of bundle branch block, including sinus bradycardia and varying degrees of AV block. These dictated the prophylactic placement of a temporary ventricular pacemaker, but otherwise resolved spontaneously. Significant hyperglycemia was seen initially in this patient, but plasma glucose levels rapidly normalized without further treatment.
A young hypertensive patient with advanced renal failure ingested 280 mg of nifedipine capsules at one time, with resulting marked hypotension responding to calcium infusion and fluids. No AV conduction abnormalities, arrhythmias, or pronounced changes in heart rate were noted, nor was there any further deterioration in renal function.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Nifedipine is a calcium ion influx inhibitor (slow-channel blocker or calcium ion antagonist) and inhibits the transmembrane influx of calcium ions into cardiac muscle and smooth muscle. The contractile processes of cardiac muscle and vascular smooth muscle are dependent upon the movement of extracellular calcium ions into these cells through specific ion channels. Nifedipine selectively inhibits calcium ion influx across the cell membrane of cardiac muscle and vascular smooth muscle without altering serum calcium concentrations.
Mechanism of Action A) Angina The precise mechanisms by which inhibition of calcium influx relieves angina has not been fully determined, but includes at least the following two mechanisms: 1) Relaxation and Prevention of Coronary Artery Spasm Nifedipine dilates the main coronary arteries and coronary arterioles, both in normal and ischemic regions, and is a potent inhibitor of coronary artery spasm, whether spontaneous or ergonovine-induced. This property increases myocardial oxygen delivery in patients with coronary artery spasm, and is responsible for the effectiveness of nifedipine in vasospastic (Prinzmetal’s or variant) angina.
Whether this effect plays any role in classical angina is not clear, but studies of exercise tolerance have not shown an increase in the maximum exercise rate-pressure product, a widely accepted measure of oxygen utilization. This suggests that, in general, relief of spasm or dilation of coronary arteries is not an important factor in classical angina. 2) Reduction of Oxygen Utilization Nifedipine regularly reduces arterial pressure at rest and at a given level of exercise by dilating peripheral arterioles and reducing the total peripheral vascular resistance (afterload) against which the heart works.
This unloading of the heart reduces myocardial energy consumption and oxygen requirements, and probably accounts for the effectiveness of nifedipine in chronic stable angina. B) Hypertension The mechanism by which nifedipine reduces arterial blood pressure involves peripheral arterial vasodilatation and the resulting reduction in peripheral vascular resistance. The increased peripheral vascular resistance that is an underlying cause of hypertension results from an increase in active tension in the vascular smooth muscle.
Studies have demonstrated that the increase in active tension reflects an increase in cytosolic free calcium. Nifedipine is a peripheral arterial vasodilator which acts directly on vascular smooth muscle. The binding of nifedipine to voltage-dependent and possibly receptor-operated channels in vascular smooth muscle results in an inhibition of calcium influx through these channels.
Stores of intracellular calcium in vascular smooth muscle are limited and thus dependent upon the influx of extracellular calcium for contraction to occur. The reduction in calcium influx by nifedipine causes arterial vasodilation and decreased peripheral vascular resistance which results in reduced arterial blood pressure. Pharmacokinetics and Metabolism Nifedipine is completely absorbed after oral administration.
Plasma drug concentrations rise at a gradual, controlled rate after a nifedipine extended-release tablets dose and reach a plateau at approximately six hours after the first dose. For subsequent doses, relatively constant plasma concentrations at this plateau are maintained with minimal fluctuations over the 24-hour dosing interval. About a four-fold higher fluctuation index (ratio of peak to trough plasma concentration) was observed with the conventional immediate-release nifedipine capsule at t.i.d. dosing than with once daily nifedipine extended-release tablets.
At steady-state, the bioavailability of the nifedipine extended-release tablets is 86% relative to nifedipine capsules. Administration of the nifedipine extended-release tablets in the presence of food slightly alters the early rate of drug absorption, but does not influence the extent o…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Nifedipine Extended-Release Tablets USP are supplied as 30 mg round, biconvex, rose-pink, film-coated tablets with “T011” in black ink on one side and plain on the other side: NDC: 72162-1277-1: 100 Tablets in a BOTTLE NDC: 72162-1277-3: 30 Tablets in a BOTTLE NDC: 72162-1277-9: 90 Tablets in a BOTTLE Store at 20° to 25°C (68° to 77°F). [see USP Controlled Room Temperature] Protect from moisture and humidity.
📋 Description ▾
DESCRIPTION Nifedipine is a drug belonging to a class of pharmacological agents known as the calcium channel blockers. Nifedipine is 3,5-pyridinedicarboxylic acid, 1,4-dihydro-2,6-dimethyl-4-(2-nitrophenyl)-, dimethyl ester, C 17 H 18 N 2 O 6 , and has the structural formula: Nifedipine is a yellow crystalline substance, practically insoluble in water but soluble in ethanol. It has a molecular weight of 346.3.
Nifedipine GITS (Gastrointestinal Therapeutic System) tablet is formulated as a once-a-day controlled-release tablet for oral administration designed to deliver 30, 60, or 90 mg of nifedipine. Inert ingredients in the formulations are: cellulose acetate; ferric oxide; hypromellose; magnesium stearate; polyethylene glycol; polyethylene oxide; potassium chloride; povidone; sodium chloride; titanium dioxide; propylene glycol and black iron oxide. The USP Dissolution Test is pending.
System Components and Performance Nifedipine extended-release tablets are similar in appearance to a conventional tablet. It consists, however, of a semipermeable membrane surrounding an osmotically active drug core. The core itself is divided into two layers: an “active” layer containing the drug, and a “push” layer containing pharmacologically inert (but osmotically active) components.
As water from the gastrointestinal tract enters the tablet, pressure increases in the osmotic layer and “pushes” against the drug layer, releasing drug through the precision laser-drilled tablet orifice in the active layer. Nifedipine extended-release tablets are designed to provide nifedipine at an approximately constant rate over 24 hours. This controlled rate of drug delivery into the gastrointestinal lumen is independent of pH or gastrointestinal motility.
Nifedipine extended-release tablets depend for its action on the existence of an osmotic gradient between the contents of the bi-layer core and fluid in the gastrointestinal tract. Drug delivery is essentially constant as long as the osmotic gradient remains constant, and then gradually falls to zero. Upon swallowing, the biologically inert components of the tablet remain intact during gastrointestinal transit and are eliminated in the feces as an insoluble shell.