
Losartan potassium 100 mg Tablet, Film Coated, 30-count — NDC 72205-143-30 (Billing 72205-0143-30)
This is a package of 30 tablets of Losartan potassium 100 mg Tablet, Film Coated from Novadoz Pharmaceuticals LLC, marketed since Aug 2023 and currently FDA-listed; retail pharmacies pay about $0.0445 per tablet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 038686
- GCN: 14853
- GPI-14 (Medi-Span): 36150040200340
- HICL (First Databank): 009829
- AHFS class code: 24:32.08.00
- RxCUI (RxNorm): 979480
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Angiotensin 2 Receptor Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Losartan is used alone or in combination with other medications to treat high blood pressure. Losartan is also used to decrease the risk of stroke in people who have high blood pressure and a heart condition called left ventricular hypertrophy (enlargement of the walls of the left side of the heart). Losartan may not decrease the risk of stroke in African Americans who have these conditions. This medication is also used to treat kidney disease in people who have type 2 diabetes (condition in which the body does not use insulin normally and therefore cannot control the amount of sugar in the bl...
Read the full MedlinePlus article ↗- Losartan is used mainly to treat high blood pressure in adults and children 6 and older. It's also used to lower the risk of stroke in people who have high blood pressure and an en...
- Cough is much less common with losartan than with ACE inhibitors (like lisinopril). In clinical trials, the rate of cough with losartan was similar to that seen with a placebo. So...
- Does losartan cause a cough like some other blood pressure medicines?
- It's best to check with your doctor or pharmacist first. NSAIDs like ibuprofen and naproxen can reduce how well losartan controls your blood pressure, and they can also put extra s...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Losartan Potassium — tap one for details:
Losartan Potassium may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.045 | $1.34 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1027 | $3.08 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 72205-0143-30 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE | $0.0445 / ea | $1.34 | 2023-08-16 | — | Active |
| 72205-0143-90 72205-143-90 Main listing | 90 TABLET, FILM COATED in 1 BOTTLE | $0.0445 / ea | $4.01 | 2023-08-16 | — | Active |
| 72205-0143-99 72205-143-99 | 1000 TABLET, FILM COATED in 1 BOTTLE | $0.0445 / ea | $44.53 | 2023-08-16 | — | Active |
You're viewing the smallest of 3 pack sizes for this product.
This pack has the lowest per-ea cost of the 3 priced pack sizes ($0.0445 NADAC).
This pack shows little to no recent Medicaid volume — the 90 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 72205-0143-90?
What NDC number is used to bill for this package of Losartan potassium 100 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| LOSARTAN POTASSIUM 100 mg 64380-0935-04 | Strides | 30 tablets | $0.044 | AB | Availability likely | save 1% |
| Losartan Potassium 100 mg 00904-7049-61 | Major | 1 tablet | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 11788-0102-10 | AiPing | 1000 tablets | $0.045 | AB | Availability likely | — |
| Losartan potassium 100 mg 33342-0046-07 | Macleods | 30 tablets | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 43547-0362-03 | Solco | 30 tablets | $0.045 | AB | Availability likely | — |
| Losortan Potassium 100 mg 50268-0506-15 | AvPAK | 1 tablet | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 62332-0029-30 | Alembic | 30 tablets | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 65862-0203-30 | Aurobindo | 30 tablets | $0.045 | — | Availability likely | — |
| Losartan Potassium 100 mg 68084-0348-01 | American | 1 tablet | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 70010-0743-03 | Granules | 30 tablets | $0.045 | AB | Availability likely | — |
| Losartan potassium 100 mgthis 72205-0143-30 | Novadoz | 30 tablets | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 72603-0342-01 | NorthStar | 90 tablets | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 82009-0044-10 | Quallent | 1000 tablets | $0.045 | AB | Availability likely | — |
| Losartan Potassium 100 mg 42571-0112-10 | Micro | 1000 tablets | $0.056 | AB | Discontinued | +25% |
| Cozaar 100 mg 78206-0123-01 | Organon | 30 tablets | $6.140 | AB | Availability likely | +13688% |
| Losartan Potassium 100 mg 00615-7960-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 29300-0146-01 | Unichem | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 31722-0702-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 43063-0954-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 46708-0447-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 50090-3403-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 50090-4712-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 50090-4914-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 51655-0791-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 51655-0828-26 | Northwind | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 55154-2333-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 55154-6643-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Losartan potassium Tablets, 100 mg 59746-0335-01 | Jubilant | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 62207-0743-49 | Granules | 1000 tablets | — | AB | FDA listed | — |
| Losortan Potassium 100 mg 63187-0072-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 63187-0708-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 63187-0808-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Losartan potassium Tablets, 100 mg 63629-2428-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 65841-0731-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 67046-0702-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Losartan potassium Tablets, 100 mg 67046-1511-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| LOSARTAN POTASSIUM 100 mg 68071-2203-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68071-2216-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68071-2344-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68071-3846-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68071-5181-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68180-0378-01 | Lupin | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68382-0137-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 68788-8186-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 70518-0718-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Losartan potassium 100 mg 70518-4289-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 71335-1235-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Losartan Potassium 100 mg 71335-1580-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 71335-2083-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 71610-0083-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 71610-0465-30 | Aphena | 30 tablets | — | AB | FDA listed | — |
| Losartan potassium Tablets, 100 mg 72162-1698-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 72162-2508-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 72189-0097-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 72789-0044-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| LOSARTAN POTASSIUM 100 mg 72789-0165-90 | PD-Rx | 90 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 72865-0143-10 | XLCare | 1000 tablets | — | AB | FDA listed | — |
| Losartan Potassium 100 mg 70518-4695-00 | REMEDYREPACK | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue losartan potassium as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [ see Warnings and Precautions (5.1 )]. WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue losartan potassium as soon as possible. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Losartan potassium tablet is an angiotensin II receptor blocker (ARB) indicated for: Treatment of hypertension, to lower blood pressure in adults and children greater than 6 years old. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.1 ) Reduction of the risk of stroke in patients with hypertension and left ventricular hypertrophy.
There is evidence that this benefit does not apply to Black patients. ( 1.2 ) Treatment of diabetic nephropathy with an elevated serum creatinine and proteinuria in patients with type 2 diabetes and a history of hypertension. ( 1.3 )
1.1Hypertension Losartan potassium tablets are indicated for the treatment of hypertension in adults and pediatric patients 6 years of age and older, to lower blood pressure. Lowering blood pressure lowers the risk of fatal and nonfatal cardiovascular (CV) events, primarily strokes and myocardial infarction. These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes including losartan.
Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake. Many patients will require more than 1 drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program’s Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC).
Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits. The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly.
Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in Black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy. Losartan potassium tablets may be administered with other antihypertensive agents.
1.2Hypertensive Patients with Left Ventricular Hypertrophy Losartan potassium tablets are indicated to reduce the risk of stroke in patients with hypertension and left ventricular hypertrophy, but there is evidence that this benefit does not apply to Black patients [ see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3)].
1.3Nephropathy in Type 2 Diabetic Patients Losartan potassium tablets are indicated for the treatment of diabetic nephropathy with an elevated serum creatinine and proteinuria (urinary albumin to creatinine ratio ≥300 mg/g) in patients with type 2 diabetes and a history of hypertension. In this population, losartan potassium tablets reduces the rate of progression of nep… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension Usual adult dose: 50 mg once daily. ( 2.1 ) Usual pediatric starting dose: 0.7 mg per kg once daily (up to 50 mg). ( 2.1 ) Hypertensive Patients with Left Ventricular Hypertrophy Usual starting dose: 50 mg once daily.
( 2.2 ) Add hydrochlorothiazide 12.5 mg and/or increase losartan potassium to 100 mg followed by an increase to hydrochlorothiazide 25 mg if further blood pressure response is needed. ( 2.2, 14.2 ) Nephropathy in Type 2 Diabetic Patients Usual dose: 50 mg once daily. ( 2.3 ) Increase dose to 100 mg once daily if further blood pressure response is needed.
( 2.3 )
2.1Hypertension Adult Hypertension The usual starting dose of losartan potassium tablets is 50 mg once daily. The dosage can be increased to a maximum dose of 100 mg once daily as needed to control blood pressure [ see Clinical Studies (14.1) ]. A starting dose of 25 mg is recommended for patients with possible intravascular depletion (e.g., on diuretic therapy).
Pediatric Hypertension The usual recommended starting dose is 0.7 mg per kg once daily (up to 50 mg total) administered as a tablet or a suspension [ see Dosage and Administration (2.5) ]. Dosage should be adjusted according to blood pressure response. Doses above 1.4 mg per kg (or in excess of 100 mg) daily have not been studied in pediatric patients [ see Clinical Pharmacology (12.3), Clinical Studies (14.1), and Warnings and Precautions (5.2) ].
Losartan potassium tablets are not recommended in pediatric patients less than 6 years of age or in pediatric patients with estimated glomerular filtration rate less than 30 mL/min/1.73 m2 [ see Use in Specific Populations (8.4), Clinical Pharmacology (12.3) , and Clinical Studies (14) ].
2.2Hypertensive Patients with Left Ventricular Hypertrophy The usual starting dose is 50 mg of losartan potassium once daily. Hydrochlorothiazide 12.5 mg daily should be added and/or the dose of losartan potassium should be increased to 100 mg once daily followed by an increase in hydrochlorothiazide to 25 mg once daily based on blood pressure response [ see Clinical Studies (14.2) ].
2.3Nephropathy in Type 2 Diabetic Patients The usual starting dose is 50 mg once daily. The dose should be increased to 100 mg once daily based on blood pressure response [ see Clinical Studies (14.3) ].
2.4Dosage Modifications in Patients with Hepatic Impairment In patients with mild-to-moderate hepatic impairment the recommended starting dose of losartan potassium is 25 mg once daily. Losartan potassium has not been studied in patients with severe hepatic impairment [ see Use in Specific Populations (8.8) and Clinical Pharmacology (12.3)].
2.5Preparation of Suspension (for 200 mL of a 2.5 mg/mL suspension) Add 10 mL of Purified Water USP to an 8 ounce (240 mL) amber polyethylene terephthalate (PET) bottle containing ten 50 mg losartan potassium tablets. Immediately shake for at least 2 minutes. Let the concentrate stand for 1 hour and then shake for 1 minute to disperse the tablet contents.
Separately prepare a 50/50 volumetric mixture of Ora-Plus™ and Ora-Sweet SF™. Add 190 mL of the 50/50 Ora-Plus™/Ora-Sweet SF™ mixture to the tablet and water slurry in the PET bottle and shake for 1 minute to disperse the ingredients. The suspension should be refrigerated at 2-8°C (36-46°F) and can be stored for up to 4 weeks.
Shake the suspension prior to each use and return promptly to the refrigerator.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • Losartan potassium tablets, USP, 25 mg, are white, oval shaped, biconvex, film-coated tablets, debossed with “ML” on one side and “14” on other side. • Losartan potassium tablets, USP, 50 mg, are white, oval shaped, biconvex, film-coated tablets debossed with “M” and “L” separated by score line on one side and “15” on other side. • Losartan potassium tablets, USP, 100 mg, are white, teardrop shaped, biconvex, film-coated tablets debossed with “ML” on one side and “16” on other side. Tablets: 25 mg; 50 mg; and 100 mg.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Losartan potassium is contraindicated: • In patients who are hypersensitive to any component of this product. • For coadministration with aliskiren in patients with diabetes. Hypersensitivity to any component. ( 4 ) Coadministration with aliskiren in patients with diabetes. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Correct volume or salt depletion prior to administration of losartan potassium. ( 5.2 ) Monitor renal function and potassium in susceptible patients. ( 5.3 , 5.4 )
5.1Fetal Toxicity Losartan potassium can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria,hypotension, renal failure, and death. When pregnancy is detected, discontinue losartan potassium as soon as possible [ see Use in Specific Populations (8.1) ].
5.2Hypotension in Volume- or Salt-Depleted Patients In patients with an activated renin-angiotensin system, such as volume- or salt-depleted patients (e.g., those being treated with high doses of diuretics), symptomatic hypotension may occur after initiation of treatment with losartan potassium. Correct volume or salt depletion prior to administration of losartan potassium [ see Dosage and Administration (2.1) ].
5.3Renal Function Deterioration Changes in renal function including acute renal failure can be caused by drugs that inhibit the renin-angiotensin system and by diuretics. Patients whose renal function may depend in part on the activity of the renin-angiotensin system (e.g., patients with renal artery stenosis, chronic kidney disease, severe congestive heart failure, or volume depletion) may be at particular risk of developing acute renal failure on losartan potassium. Monitor renal function periodically in these patients.
Consider withholding or discontinuing therapy in patients who develop a clinically significant decrease in renal function on losartan potassium [ see Drug Interactions (7.3) and Use in Specific Populations (8.7) ].
5.4Hyperkalemia Monitor serum potassium periodically and treat appropriately. Dosage reduction or discontinuation of losartan potassium may be required [ see Adverse Reactions (6.1) ]. Concomitant use of other drugs that may increase serum potassium may lead to hyperkalemia [ see Drug Interactions (7.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥2% and greater than placebo) are: dizziness, upper respiratory infection, nasal congestion, and back pain. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Novadoz Pharmaceuticals LLC at 1-855-668-2369 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Hypertension Losartan potassium has been evaluated for safety in more than 3300 adult patients treated for essential hypertension and 4058 patients/subjects overall. Over 1200 patients were treated for over 6 months and more than 800 for over one year.
Treatment with losartan potassium was well-tolerated with an overall incidence of adverse events similar to that of placebo. In controlled clinical trials, discontinuation of therapy for adverse events occurred in 2.3% of patients treated with losartan potassium and 3.7% of patients given placebo. In 4 clinical trials involving over 1000 patients on various doses (10-150 mg) of losartan potassium and over 300 patients given placebo, the adverse events that occurred in ≥2% of patients treated with losartan potassium and more commonly than placebo were: dizziness (3% vs.
2%), upper respiratory infection (8% vs. 7%), nasal congestion (2% vs. 1%), and back pain (2% vs.
1%). The following less common adverse reactions have been reported: Blood and lymphatic system disorders: Anemia. Psychiatric disorders: Depression.
Nervous system disorders: Somnolence, headache, sleep disorders, paresthesia, migraine. Ear and labyrinth disorders: Vertigo, tinnitus. Cardiac disorders: Palpitations, syncope, atrial fibrillation, CVA.
Respiratory, thoracic and mediastinal disorders: Dyspnea. Gastrointestinal disorders: Abdominal pain, constipation, nausea, vomiting. Skin and subcutaneous tissue disorders: Urticaria, pruritus, rash, photosensitivity.
Musculoskeletal and connective tissue disorders: Myalgia, arthralgia. Reproductive system and breast disorders: Impotence. General disorders and administration site conditions: Edema.
Cough Persistent dry cough (with an incidence of a few percent) has been associated with ACE-inhibitor use and in practice can be a cause of discontinuation of ACE-inhibitor therapy. Two prospective, parallel-group, double-blind, randomized, controlled trials were conducted to assess the effects of losartan on the incidence of cough in hypertensive patients who had experienced cough while receiving ACE-inhibitor therapy.Patients who had typical ACE-inhibitor cough when challenged with lisinopril, whose cough disappeared on placebo, were randomized to losartan 50 mg, lisinopril 20 mg, or either placebo (one study, n=97) or 25 mg hydrochlorothiazide (n=135).
The double-blind treatment period lasted up to 8 weeks. The incidence of cough is shown in Table 1 below. Table 1 Study 1* HCTZ Losartan Lisinopril Cough 25% 17% 69% Study 2 † Placebo Losartan Lisinopril Cough 35% 29% 62% * Demographics = (89% Caucasian, 64% female) † Demographics = (90% Caucasian, 51% female) These studies demonstrate that the incidence of cough associated with losartan therapy, in a population that all had cough associated with ACE-inhibitor therapy, is similar to that associated with hydrochlorothiazide or placebo therapy.
Cases of cough, including positive re-challenges, have been reported with the use of losartan in postmarketing experience. Hypertensive Patients with Left Ventricular Hypertrophy In the Losartan Intervention for Endpoint (LIFE) study, adverse reactions with losartan potassium were similar to those reported previously for patients with hypertension. Nephropathy in Type 2 Diabetic Patients In the Reduction of Endpoints in NIDDM with the Angiotensin II Receptor Antagonist Losartan (REN… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Agents Increasing Serum Potassium: Risk of hyperkalemia. ( 7.1 ) Lithium: Risk of lithium toxicity. ( 7.2 ) NSAIDs: Increased risk of renal impairment and reduced diuretic, natriuretic, and antihypertensive effects. ( 7.3 ) Dual Inhibition of the Renin-Angiotensin System: Increased risk of renal impairment, hypotension, syncope, and hyperkalemia. ( 7.4 )
7.1Agents Increasing Serum Potassium Coadministration of losartan with other drugs that raise serum potassium levels may result in hyperkalemia. Monitor serum potassium in such patients.
7.2Lithium Increases in serum lithium concentrations and lithium toxicity have been reported during concomitant administration of lithium with angiotensin II receptor antagonists. Monitor serum lithium levels during concomitant use.
7.3Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) Including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, coadministration of NSAIDs, including selective COX-2 inhibitors, with angiotensin II receptor antagonists (including losartan) may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving losartan and NSAID therapy.
The antihypertensive effect of angiotensin II receptor antagonists, including losartan, may be attenuated by NSAIDs, including selective COX-2 inhibitors.
7.4Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, syncope, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. The Veterans Affairs Nephropathy in Diabetes (VA NEPHRON-D) trial enrolled 1448 patients with type 2 diabetes, elevated urinary-albumin-to-creatinine ratio, and decreased estimated glomerular filtration rate (GFR 30 to 89.9 mL/min), randomized them to lisinopril or placebo on a background of losartan therapy and followed them for a median of 2.2 years.
Patients receiving the combination of losartan and lisinopril did not obtain any additional benefit compared to monotherapy for the combined endpoint of decline in GFR, end stage renal disease, or death, but experienced an increased incidence of hyperkalemia and acute kidney injury compared with the monotherapy group. In most patients no benefit has been associated with using two RAS inhibitors concomitantly. In general, avoid combined use of RAS inhibitors.
Closely monitor blood pressure, renal function, and electrolytes in patients on losartan potassium and other agents that affect the RAS. Do not coadminister aliskiren with losartan potassium in patients with diabetes. Avoid use of aliskiren with losartan potassium in patients with renal impairment (GFR <60 mL/min).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Losartan potassium is not recommended in pediatric patients less than 6 years of age or in pediatric patients with glomerular filtration rate less than 30 mL/min/1.73 m2. ( 2.1 , 8.4 ) Hepatic Impairment: Recommended starting dose 25 mg once daily. ( 2.4 , 8.8 , 12.3 )
8.1Pregnancy Risk Summary Losartan potassium can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue losartan potassium as soon as possible (see Clinical Considerations). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
In patients taking losartan potassium during pregnancy, perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. If oligohydramnios is observed, discontinue losartan potassium, unless it is considered lifesaving for the mother.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to losartan potassium for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to losartan potassium, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Data Animal Data Losartan potassium was administered orally to rats during the period of late gestation through lactation (Gestation Day 15 through Lactation Day 20) at doses of 10, 25, and 100 mg/kg/day. Losartan potassium has been shown to produce adverse effects in rat fetuses and neonates, including decreased body weight, delayed physical and behavioral development, mortality and renal toxicity.
With the exception of neonatal weight gain (which was affected at doses as low as 10 mg/kg/day), doses associated with these effects exceeded 25 mg/kg/day (approximately three times the maximum recommended human dose of 100 mg on a mg/m 2 basis). These findings are attributed to drug exposure in late gestation and during lactation. Significant levels of losartan and its active metabolite were shown to… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Losartan potassium can cause fetal harm when administered to a pregnant woman. Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents.
When pregnancy is detected, discontinue losartan potassium as soon as possible (see Clinical Considerations). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death.
Pregnant women with hypertension should be carefully monitored and managed accordingly. Fetal/Neonatal Adverse Reactions Oligohydramnios in pregnant women who use drugs affecting the renin-angiotensin system in the second and third trimesters of pregnancy can result in the following: reduced fetal renal function leading to anuria and renal failure, fetal lung hypoplasia, skeletal deformations, including skull hypoplasia, hypotension, and death. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
In patients taking losartan potassium during pregnancy, perform serial ultrasound examinations to assess the intra-amniotic environment. Fetal testing may be appropriate, based on the week of gestation. If oligohydramnios is observed, discontinue losartan potassium, unless it is considered lifesaving for the mother.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe neonates with histories of in utero exposure to losartan potassium for hypotension, oliguria, and hyperkalemia. In neonates with a history of in utero exposure to losartan potassium, if oliguria or hypotension occurs, support blood pressure and renal perfusion.
Exchange transfusions or dialysis may be required as a means of reversing hypotension and replacing renal function. Data Animal Data Losartan potassium was administered orally to rats during the period of late gestation through lactation (Gestation Day 15 through Lactation Day 20) at doses of 10, 25, and 100 mg/kg/day. Losartan potassium has been shown to produce adverse effects in rat fetuses and neonates, including decreased body weight, delayed physical and behavioral development, mortality and renal toxicity.
With the exception of neonatal weight gain (which was affected at doses as low as 10 mg/kg/day), doses associated with these effects exceeded 25 mg/kg/day (approximately three times the maximum recommended human dose of 100 mg on a mg/m 2 basis). These findings are attributed to drug exposure in late gestation and during lactation. Significant levels of losartan and its active metabolite were shown to be present in rat fetal plasma during late gestation and in rat milk.
🆘 Overdosage ▾
10 OVERDOSAGE Significant lethality was observed in mice and rats after oral administration of 1000 mg/kg and 2000 mg/kg, respectively, about 44 and 170 times the maximum recommended human dose on a mg/m 2 basis. Limited data are available in regard to overdosage in humans. The most likely manifestation of overdosage would be hypotension and tachycardia; bradycardia could occur from parasympathetic (vagal) stimulation.
If symptomatic hypotension should occur, supportive treatment should be instituted. Neither losartan nor its active metabolite can be removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)] is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system, and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues, (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis.Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor. The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor.
Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
12.2Pharmacodynamics Losartan inhibits the pressor effect of angiotensin II (as well as angiotensin I) infusions. A dose of 100 mg inhibits the pressor effect by about 85% at peak with 25-40% inhibition persisting for 24 hours. Removal of the negative feedback of angiotensin II causes a doubling to tripling in plasma renin activity and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Losartan does not affect the response to bradykinin, whereas ACE inhibitors increase the response to bradykinin. Aldosterone plasma concentrations fall following losartan administration. In spite of the effect of losartan on aldosterone secretion, very little effect on serum potassium was observed.
The effect of losartan is substantially present within one week but in some studies the maximal effect occurred in 3-6 weeks. In long-term follow-up studies (without placebo control) the effect of losartan appeared to be maintained for up to a year. There is no apparent rebound effect after abrupt withdrawal of losartan.
There was essentially no change in average heart rate in losartan-treated patients in controlled trials.
12.3Pharmacokinetics Absorption: Following oral administration, losartan is well absorbed and undergoes substantial first-pass metabolism. The systemic bioavailability of losartan is approximately 33%. Mean peak concentrations of losartan and its active metabolite are reached in 1 hour and in 3-4 hours, respectively.
While maximum plasma concentrations of losartan and its active metabolite are approximately equal, the AUC (area under the curve) of the metabolite is about 4 times as great as that of losartan. A meal slows absorption of losartan and decreases its C max but has only minor effects on losartan AUC or on the AUC of the metabolite (~10% decrease). The pharmacokinetics of losartan and its active metabolite are linear with oral losartan doses up to 200 mg and do not change over time.
Distribution: The volume of distribution of losartan and the active metabolite is about 34 liters and 12 liters, respectively. Both losartan and its active metabolite are highly bound to plasma proteins, primarily albumin, with plasma free fractions of 1.3% and 0.2%, respectively. Plasma protein binding is constant over the concentration range achieved with recommended doses.
Studies in rats indicate that losartan crosses the blood-brain barrier poorly, if at all. Metabolism: Losartan is an orally active… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Angiotensin II [formed from angiotensin I in a reaction catalyzed by angiotensin converting enzyme (ACE, kininase II)] is a potent vasoconstrictor, the primary vasoactive hormone of the renin-angiotensin system, and an important component in the pathophysiology of hypertension. It also stimulates aldosterone secretion by the adrenal cortex. Losartan and its principal active metabolite block the vasoconstrictor and aldosterone-secreting effects of angiotensin II by selectively blocking the binding of angiotensin II to the AT 1 receptor found in many tissues, (e.g., vascular smooth muscle, adrenal gland).
There is also an AT 2 receptor found in many tissues but it is not known to be associated with cardiovascular homeostasis.Neither losartan nor its principal active metabolite exhibits any partial agonist activity at the AT 1 receptor, and both have much greater affinity (about 1000-fold) for the AT 1 receptor than for the AT 2 receptor. In vitro binding studies indicate that losartan is a reversible, competitive inhibitor of the AT 1 receptor. The active metabolite is 10 to 40 times more potent by weight than losartan and appears to be a reversible, non-competitive inhibitor of the AT 1 receptor.
Neither losartan nor its active metabolite inhibits ACE (kininase II, the enzyme that converts angiotensin I to angiotensin II and degrades bradykinin), nor do they bind to or block other hormone receptors or ion channels known to be important in cardiovascular regulation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Losartan potassium tablets, USP are supplied as follows: • Losartan potassium tablets, USP, 25 mg, are white, oval shaped, biconvex, film-coated tablets, debossed with “ML” on one side and “14” on other side. Bottles of 90, NDC 72205-141-90 Bottles of 1000, NDC 72205-141-99 • Losartan potassium tablets, USP, 50 mg, are white, oval shaped, biconvex, film-coated tablets debossed with “M” and “L” separated by score line on one side and “15” on other side. Bottles of 30, NDC 72205-142-30 Bottles of 90, NDC 72205-142-90 Bottles of 1000, NDC 72205-142-99 • Losartan potassium tablets, USP, 100 mg, are white, teardrop shaped, biconvex, film-coated tablets debossed with “ML” on one side and “16” on other side.
Bottles of 30, NDC 72205-143-30 Bottles of 90, NDC 72205-143-90 Bottles of 1000, NDC 72205-143-99 Store at 25°C (77°F); excursions permitted to 15-30°C (59-86°F) [see USP Controlled Room Temperature]. Keep container tightly closed. Protect from light.
📋 Description ▾
11 DESCRIPTION Losartan potassium tablets, USP are an angiotensin II receptor blocker acting on the AT 1 receptor subtype. Losartan potassium, a non-peptide molecule, is chemically described as 2-butyl-4-chloro-1-[ p -( o -1 H - tetrazol-5-ylphenyl)benzyl]imidazole-5-methanol monopotassium salt. Its molecular formula is C 22 H 22 ClKN 6 O, and its structural formula is: Losartan potassium, USP is a white to off-white powder with a molecular weight of 461.
It is freely soluble in water, slightly soluble in acetonitrile and practically insoluble in cyclohexane. Oxidation of the 5-hydroxymethyl group on the imidazole ring results in the active metabolite of losartan. Losartan potassium, USP is available as tablets for oral administration containing either 25 mg, 50 mg or 100 mg of losartan potassium and the following inactive ingredients: lactose monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch, hydroxypropyl cellulose, hypromellose, and titanium dioxide.
Losartan potassium 25 mg, 50 mg and 100 mg tablets contain potassium in the following amounts: 2.12 mg (0.054 mEq), 4.24 mg (0.108 mEq) and 8.48 mg (0.216 mEq), respectively. FDA approved dissolution test specifications differ from the USP. str
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Pregnancy Advise female patients of childbearing age about the consequences of exposure to losartan potassium during pregnancy. Discuss treatment options with women planning to become pregnant.
Tell patients to report pregnancies to their physicians as soon as possible [ see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ]. Potassium Supplements Advise patients receiving losartan potassium not to use potassium supplements or salt substitutes containing potassium without consulting their healthcare provider [ see Drug Interactions (7.1) ]. Manufactured by: MSN Laboratories Private Limited Telangana – 509 228, INDIA Distributed by: Novadoz Pharmaceuticals LLC Piscataway, NJ 08854-3714 Revised: 07/2025
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption: Following oral administration, losartan is well absorbed and undergoes substantial first-pass metabolism. The systemic bioavailability of losartan is approximately 33%. Mean peak concentrations of losartan and its active metabolite are reached in 1 hour and in 3-4 hours, respectively.
While maximum plasma concentrations of losartan and its active metabolite are approximately equal, the AUC (area under the curve) of the metabolite is about 4 times as great as that of losartan. A meal slows absorption of losartan and decreases its C max but has only minor effects on losartan AUC or on the AUC of the metabolite (~10% decrease). The pharmacokinetics of losartan and its active metabolite are linear with oral losartan doses up to 200 mg and do not change over time.
Distribution: The volume of distribution of losartan and the active metabolite is about 34 liters and 12 liters, respectively. Both losartan and its active metabolite are highly bound to plasma proteins, primarily albumin, with plasma free fractions of 1.3% and 0.2%, respectively. Plasma protein binding is constant over the concentration range achieved with recommended doses.
Studies in rats indicate that losartan crosses the blood-brain barrier poorly, if at all. Metabolism: Losartan is an orally active agent that undergoes substantial first-pass metabolism by cytochrome P450 enzymes. It is converted, in part, to an active carboxylic acid metabolite that is responsible for most of the angiotensin II receptor antagonism that follows losartan treatment.
About 14% of an orally-administered dose of losartan is converted to the active metabolite. In addition to the active carboxylic acid metabolite, several inactive metabolites are formed. In vitro studies indicate that cytochrome P450 2C9 and 3A4 are involved in the biotransformation of losartan to its metabolites.
Elimination: Total plasma clearance of losartan and the active metabolite is about 600 mL/min and 50 mL/min, respectively, with renal clearance of about 75 mL/min and 25 mL/min, respectively. The terminal half-life of losartan is about 2 hours and of the metabolite is about 6-9 hours. After single doses of losartan administered orally, about 4% of the dose is excreted unchanged in the urine and about 6% is excreted in urine as active metabolite.
Biliary excretion contributes to the elimination of losartan and its metabolites. Following oral 14 C-labeled losartan, about 35% of radioactivity is recovered in the urine and about 60% in the feces. Following an intravenous dose of 14 C-labeled losartan, about 45% of radioactivity is recovered in the urine and 50% in the feces.
Neither losartan nor its metabolite accumulates in plasma upon repeated once-daily dosing. Specific Populations Pediatric: Pharmacokinetic parameters after multiple doses of losartan (average dose 0.7 mg/kg, range 0.36 to 0.97 mg/kg) as a tablet to 25 hypertensive patients aged 6 to 16 years are shown in Table 4 below. Pharmacokinetics of losartan and its active metabolite were generally similar across the studied age groups and similar to historical pharmacokinetic data in adults.
The principal pharmacokinetic parameters in adults and children are shown in the table below. Table 2: Pharmacokinetic Parameters in Hypertensive Adults and Children Age 6-16 Following Multiple Dosing Adults given 50 mg once daily for 7 days N=12 Age 6-16 given 0.7 mg/kg once daily for 7 days N=25 Parent Active Metabolite Parent Active Metabolite AUC 0-24 (ng•hr/mL)* 442 ± 173 1685 ± 452 368 ± 169 1866 ± 1076 C MAX (ng/mL)* 224 ± 82 212 ± 73 141 ± 88 222 ± 127 T 1/2 (h) † 2.1 ± 0.70 7.4 ± 2.4 2.3 ± 0.8 5.6 ±
1.2T PEAK (h) ‡ 0.9 3.5 2.0
4.1CL REN (mL/min)* 56 ± 23 20 ± 3 53 ± 33 17 ± 8 * Mean ± standard deviation † Harmonic mean and standard deviation ‡ Median The bioavailability of the suspension formulation was compared with losartan tablets in healthy adults. The suspension and tablet are similar in their bioavailability with respec… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Losartan inhibits the pressor effect of angiotensin II (as well as angiotensin I) infusions. A dose of 100 mg inhibits the pressor effect by about 85% at peak with 25-40% inhibition persisting for 24 hours. Removal of the negative feedback of angiotensin II causes a doubling to tripling in plasma renin activity and consequent rise in angiotensin II plasma concentration in hypertensive patients.
Losartan does not affect the response to bradykinin, whereas ACE inhibitors increase the response to bradykinin. Aldosterone plasma concentrations fall following losartan administration. In spite of the effect of losartan on aldosterone secretion, very little effect on serum potassium was observed.
The effect of losartan is substantially present within one week but in some studies the maximal effect occurred in 3-6 weeks. In long-term follow-up studies (without placebo control) the effect of losartan appeared to be maintained for up to a year. There is no apparent rebound effect after abrupt withdrawal of losartan.
There was essentially no change in average heart rate in losartan-treated patients in controlled trials.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Hypertension Adult Hypertension The antihypertensive effects of losartan potassium were demonstrated principally in 4 placebo-controlled, 6- to 12-week trials of dosages from 10 to 150 mg per day in patients with baseline diastolic blood pressures of 95-115. The studies allowed comparisons of two doses (50-100 mg/day) as once-daily or twice-daily regimens, comparisons of peak and trough effects, and comparisons of response by gender, age, and race. Three additional studies examined the antihypertensive effects of losartan and hydrochlorothiazide in combination.
The 4 studies of losartan monotherapy included a total of 1075 patients randomized to several doses of losartan and 334 to placebo. The 10- and 25-mg doses produced some effect at peak (6 hours after dosing) but small and inconsistent trough (24 hour) responses. Doses of 50, 100 and 150 mg once daily gave statistically significant systolic/diastolic mean decreases in blood pressure, compared to placebo in the range of 5.5-10.5/3.5-7.5 mmHg, with the 150-mg dose giving no greater effect than 50-100 mg.
Twice-daily dosing at 50-100 mg/day gave consistently larger trough responses than once-daily dosing at the same total dose. Peak (6 hour) effects were uniformly, but moderately, larger than trough effects, with the trough-to-peak ratio for systolic and diastolic responses 50-95% and 60-90%, respectively. Addition of a low dose of hydrochlorothiazide (12.5 mg) to losartan 50 mg once daily resulted in placebo-adjusted blood pressure reductions of 15.5/9.2 mmHg.
Analysis of age, gender, and race subgroups of patients showed that men and women, and patients over and under 65, had generally similar responses. Losartan potassium was effective in reducing blood pressure regardless of race, although the effect was somewhat less in Black patients (usually a low-renin population). Pediatric Hypertension The antihypertensive effect of losartan was studied in one trial enrolling 177 hypertensive pediatric patients aged 6 to 16 years old.
Children who weighed <50 kg received 2.5, 25 or 50 mg of losartan daily and patients who weighed ≥50 kg received 5, 50 or 100 mg of losartan daily. Children in the lowest dose group were given losartan in a suspension formulation [ see Dosage and Administration (2.1) ]. The majority of the children had hypertension associated with renal and urogenital disease.
The sitting diastolic blood pressure (SiDBP) on entry into the study was higher than the 95 th percentile level for the patient’s age, gender, and height. At the end of three weeks, losartan reduced systolic and diastolic blood pressure, measured at trough, in a dose-dependent manner. Overall, the two higher doses (25 to 50 mg in patients <50 kg; 50 to 100 mg in patients ≥50 kg) reduced diastolic blood pressure by 5 to 6 mmHg more than the lowest dose used (2.5 mg in patients <50 kg; 5 mg in patients ≥50 kg).
The lowest dose, corresponding to an average daily dose of 0.07 mg/kg, did not appear to offer consistent antihypertensive efficacy. When patients were randomized to continue losartan at the two higher doses or to placebo after 3 weeks of therapy, trough diastolic blood pressure rose in patients on placebo between 5 and 7 mmHg more than patients randomized to continuing losartan. When the low dose of losartan was randomly withdrawn, the rise in trough diastolic blood pressure was the same in patients receiving placebo and in those continuing losartan, again suggesting that the lowest dose did not have significant antihypertensive efficacy.
Overall, no significant differences in the overall antihypertensive effect of losartan were detected when the patients were analyzed according to age (<, ≥12 years old) or gender. While blood pressure was reduced in all racial subgroups examined, too few non-White patients were enrolled to compare the dose-response of losartan in the non-White subgroup.
14.2Hypertensive Patients with Left Ventricular Hypertrophy The LIFE study… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Losartan potassium was not carcinogenic when administered at maximally tolerated dosages to rats and mice for 105 and 92 weeks, respectively. Female rats given the highest dose (270 mg/kg/day) had a slightly higher incidence of pancreatic acinar adenoma. The maximally tolerated dosages (270 mg/kg/day in rats, 200 mg/kg/day in mice) provided systemic exposures for losartan and its pharmacologically active metabolite that were approximately 160 and 90 times (rats) and 30 and 15 times (mice) the exposure of a 50 kg human given 100 mg per day.
Losartan potassium was negative in the microbial mutagenesis and V-79 mammalian cell mutagenesis assays and in the in vitro alkaline elution and in vitro and in vivo chromosomal aberration assays. In addition, the active metabolite showed no evidence of genotoxicity in the microbial mutagenesis, in vitro alkaline elution, and in vitro chromosomal aberration assays. Fertility and reproductive performance were not affected in studies with male rats given oral doses of losartan potassium up to approximately 150 mg/kg/day.
The administration of toxic dosage levels in females (300/200 mg/kg/day) was associated with a significant (p<0.05) decrease in the number of corpora lutea/female, implants/female, and live fetuses/female at C-section. At 100 mg/kg/day only a decrease in the number of corpora lutea/female was observed. The relationship of these findings to drug-treatment is uncertain since there was no effect at these dosage levels on implants/pregnant female, percent post-implantation loss, or live animals/litter at parturition.
In nonpregnant rats dosed at 135 mg/kg/day for 7 days, systemic exposure (AUCs) for losartan and its active metabolite were approximately 66 and 26 times the exposure achieved in man at the maximum recommended human daily dosage (100 mg).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Losartan potassium was not carcinogenic when administered at maximally tolerated dosages to rats and mice for 105 and 92 weeks, respectively. Female rats given the highest dose (270 mg/kg/day) had a slightly higher incidence of pancreatic acinar adenoma. The maximally tolerated dosages (270 mg/kg/day in rats, 200 mg/kg/day in mice) provided systemic exposures for losartan and its pharmacologically active metabolite that were approximately 160 and 90 times (rats) and 30 and 15 times (mice) the exposure of a 50 kg human given 100 mg per day.
Losartan potassium was negative in the microbial mutagenesis and V-79 mammalian cell mutagenesis assays and in the in vitro alkaline elution and in vitro and in vivo chromosomal aberration assays. In addition, the active metabolite showed no evidence of genotoxicity in the microbial mutagenesis, in vitro alkaline elution, and in vitro chromosomal aberration assays. Fertility and reproductive performance were not affected in studies with male rats given oral doses of losartan potassium up to approximately 150 mg/kg/day.
The administration of toxic dosage levels in females (300/200 mg/kg/day) was associated with a significant (p<0.05) decrease in the number of corpora lutea/female, implants/female, and live fetuses/female at C-section. At 100 mg/kg/day only a decrease in the number of corpora lutea/female was observed. The relationship of these findings to drug-treatment is uncertain since there was no effect at these dosage levels on implants/pregnant female, percent post-implantation loss, or live animals/litter at parturition.
In nonpregnant rats dosed at 135 mg/kg/day for 7 days, systemic exposure (AUCs) for losartan and its active metabolite were approximately 66 and 26 times the exposure achieved in man at the maximum recommended human daily dosage (100 mg).
📄 Package Label / Principal Display Panel ▾
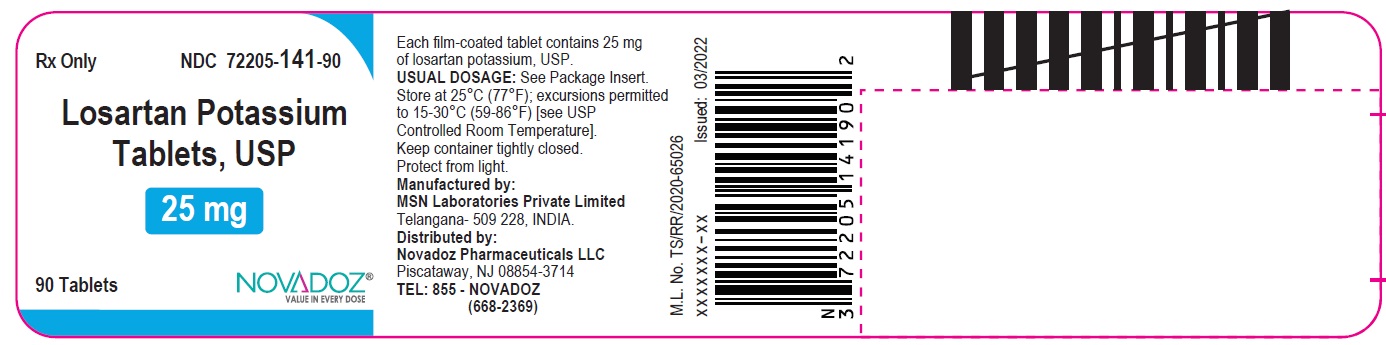
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL Losartan Potassium Tablets-25mg-90's Container Label Losartan Potassium Tablets -25mg-1000's Container Label Losartan Potassium Tablets -50mg-30's Container Label Losartan Potassium Tablets -50mg-90's Container Label Losartan Potassium Tablets -50mg-1000's Container Label Losartan Potassium Tablets -100mg-30's Container Label Losartan Potassium Tablets -100mg-90's Container Label Losartan Potassium Tablets -100mg-1000's Container Label losartan-25mg-90s-cntr losartan-25mg-1000s-cntr losartan-50mg-30s-cntr losartan-50mg-90s-cntr losartan-50mg-1000s-cntr losartan-100mg-30s-cntr losartan-100mg-90s-cntr losartan-100mg-1000s-cntr