
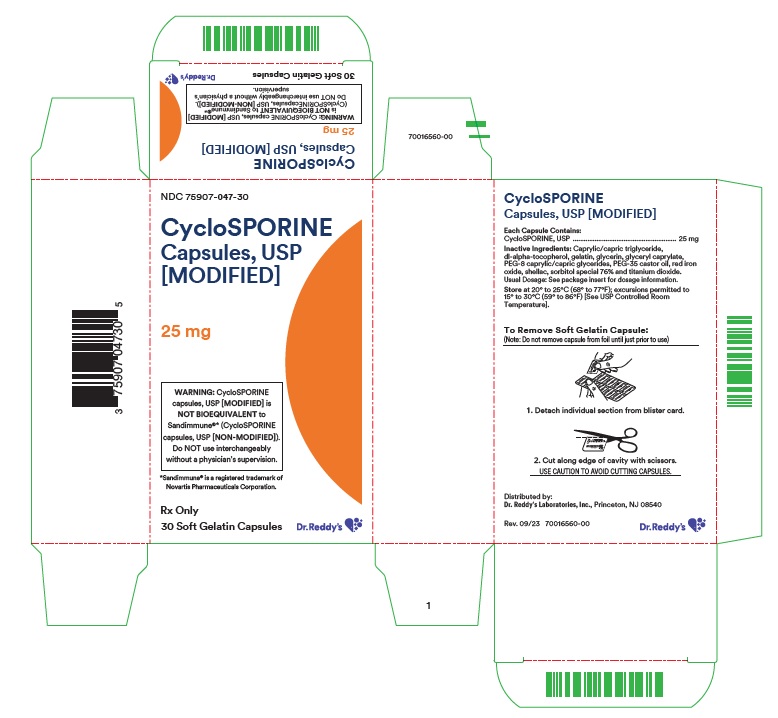
Cyclosporine 25 mg Capsule, Liquid Filled — NDC 75907-047-30 (Billing 75907-0047-30)
This is a package of Cyclosporine 25 mg Capsule, Liquid Filled from Dr. Reddy's Laboratories Inc, marketed since Jul 2024 and currently FDA-listed; retail pharmacies pay about $0.3184 per unit (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 75907-047-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 75907 labeler · 047 product · 30 package
- Package marketed since
- Jul 1, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 7590704730 5
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 023882
- GCN: 13918
- GPI-14 (Medi-Span): 99402020300120
- HICL (First Databank): 010086
- AHFS class code: 52:08.00.00
- RxCUI (RxNorm): 241834
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Calcineurin Inhibitor Immunosuppressant class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Cyclosporine and cyclosporine (modified) are used with other medications to prevent transplant rejection (attack of the transplanted organ by the immune system of the person who received the organ) in people who have received kidney, liver, and heart transplants. Cyclosporine (modified) is also used alone or with methotrexate (Rheumatrex) to treat the symptoms of rheumatoid arthritis (arthritis caused by swelling of the lining of the joints) in patients whose symptoms were not relieved by methotrexate alone. Cyclosporine (modified) is also used to treat psoriasis (a skin disease in which red,...
Read the full MedlinePlus article ↗- It depends on the product. Oral forms help prevent organ rejection after kidney, liver or heart transplants. Some oral products also treat severe rheumatoid arthritis and severe pl...
- Oral modified forms like Neoral and Gengraf are taken twice a day. Keep your timing and meal routine consistent from day to day. Follow your prescriber's directions and the label.
- No, avoid grapefruit and grapefruit juice. They raise cyclosporine levels in your blood, which can increase side effects.
- Not on your own. Modified products such as Neoral and Gengraf are not interchangeable with Sandimmune, and switching needs your doctor's supervision and extra blood level checks.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cyclosporine — tap one for details:
Cyclosporine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.318 | $9.55 / 30 capsule |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7515 | $0.552 / J7515 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 25, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 75907-0047-30 You're viewing this Main listing | 30 BLISTER PACK in 1 BOX / 1 CAPSULE, LIQUID FILLED in 1 BLISTER PACK | 2024-07-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cyclosporine Modified 25 mg 00093-9018-65 | Teva | 1 capsule | $0.314 | AB1 | Availability likely | save 1% |
| Cyclosporine 25 mg 23155-0837-30 | Heritage | 10 capsules | $0.314 | AB1 | Availability likely | save 1% |
| CycloSPORINE, Modfied 25 mg 60505-4630-03 | Apotex | 10 capsules | $0.314 | AB1 | Availability likely | save 1% |
| Cyclosporine 25 mgthis 75907-0047-30 | Dr. | 1 capsule | $0.318 | AB1 | FDA listed | — |
| Gengraf 25 mg 00074-3108-32 | AbbVie | 30 capsules | $1.865 | AB1 | Availability likely | +486% |
| Cyclosporine 25 mg 60505-0133-00 | Apotex | 30 capsules | $2.596 | AB2 | Availability likely | +715% |
| Cyclosporine 25 mg 68084-0879-25 | American | 1 capsule | $2.596 | AB2 | Availability likely | +715% |
| Neoral 25 mg 00078-0246-15 | Novartis | 1 capsule | $2.946 | AB1 | Availability likely | +825% |
| Sandimmune 25 mg 00078-0240-15 | Novartis | 1 capsule | — | AB2 | FDA listed | — |
| Cyclosporine 25 mg 64380-0127-02 | Strides | 10 capsules | — | AB1 | FDA listed | — |
| Cyclosporine 25 mg 59651-0927-03 | Aurobindo | 10 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Feb 25, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H4N855PNZ1
Alpha-tocopherol is a form of vitamin E, a fat-soluble antioxidant derived from natural or synthetic sources. In medicines, it prevents oils and fats from breaking down and becoming rancid, protecting the product's stability and shelf life.
-
UNII 00BT03FSO2
A synthetic liquid derived from plant oils and polyethylene glycol. It serves as a solvent and emulsifier to dissolve and blend active ingredients evenly throughout the medicine.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII TM2TZD4G4A
A plant-derived oily substance used as an emulsifier and solubilizer in medicines. It helps blend water and oil-based ingredients together and improves how the body absorbs certain active drugs.
-
UNII C9H2L21V7U
A fat derived from coconut or palm oil containing shorter fatty acid chains. It serves as a solvent and carrier to help dissolve or suspend active ingredients, improving absorption and stability in liquid formulations.
-
UNII 6D4M1DAL6O
Polyoxyl 35 castor oil is a synthetic compound made by chemically treating castor oil. It works as a solubilizer and emulsifier to help dissolve and evenly mix oily and water-based ingredients in medicines.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Dr. Reddy's Laboratories Inc labeler code 75907
- Estazolam 2 mg Tablet NDC 75907-029-01
- Liothyronine Sodium 5 ug Tablet NDC 75907-039-01
- Trimethoprim 100 mg Tablet NDC 75907-043-01
- Diltiazem Hydrochloride Extended-Release 60 mg Capsule, Extended Release NDC 75907-044-01
- Diltiazem Hydrochloride Extended-Release 90 mg Capsule, Extended Release NDC 75907-045-01
- Diltiazem Hydrochloride Extended-Release 120 mg Capsule, Extended Release NDC 75907-046-01
- Cyclosporine 100 mg Capsule, Liquid Filled NDC 75907-048-30
- Methylphenidate Hydrochloride (LA) 10 mg Capsule, Extended Release NDC 75907-049-01
- Methylphenidate Hydrochloride (LA) 20 mg Capsule, Extended Release NDC 75907-050-01
- Methylphenidate Hydrochloride (LA) 30 mg Capsule, Extended Release NDC 75907-051-01
- Methylphenidate Hydrochloride (LA) 40 mg Capsule, Extended Release NDC 75907-052-01
- Methylphenidate Hydrochloride (LA) 60 mg Capsule, Extended Release NDC 75907-053-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Only physicians experienced in management of systemic immunosuppressive therapy for the indicated disease should prescribe cyclosporine [MODIFIED]. At doses used in solid organ transplantation, only physicians experienced in immunosuppressive therapy and management of organ transplant recipients should prescribe cyclosporine [MODIFIED]. Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources.
The physician responsible for maintenance therapy should have complete information requisite for the follow-up of the patient. Cyclosporine [MODIFIED], a systemic immunosuppressant, may increase the susceptibility to infection and the development of neoplasia. In kidney, liver, and heart transplant patients, cyclosporine [MODIFIED] may be administered with other immunosuppressive agents.
Increased susceptibility to infection and the possible development of lymphoma and other neoplasms may result from the increase in the degree of immunosuppression in transplant patients. Cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED] have increased bioavailability in comparison to Sandimmune® Sandimmune® is a registered trademark of Novartis Pharmaceuticals Corporation. soft gelatin capsules (cyclosporine capsules) and Sandimmune® oral solution (cyclosporine oral solution). Cyclosporine [MODIFIED] and Sandimmune® are not bioequivalent and cannot be used interchangeably without physician supervision.
For a given trough concentration, cyclosporine exposure will be greater with cyclosporine [MODIFIED] than with Sandimmune®. If a patient who is receiving exceptionally high doses of Sandimmune® is converted to cyclosporine [MODIFIED], particular caution should be exercised. Cyclosporine blood concentrations should be monitored in transplant and rheumatoid arthritis patients taking cyclosporine [MODIFIED] to avoid toxicity due to high concentrations.
Dose adjustments should be made in transplant patients to minimize possible organ rejection due to low concentrations. Comparison of blood concentrations in the published literature with blood concentrations obtained using current assays must be done with detailed knowledge of the assay methods employed. (see DOSAGE AND ADMINISTRATION ).
For Psoriasis Patients (See also Boxed WARNINGS above) Psoriasis patients previously treated with PUVA and to a lesser extent, methotrexate or other immunosuppressive agents, UVB, coal tar, or radiation therapy, are at an increased risk of developing skin malignancies when taking cyclosporine [MODIFIED]. Cyclosporine, the active ingredient in cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED], in recommended dosages, can cause systemic hypertension and nephrotoxicity. The risk increases with increasing dose and duration of cyclosporine therapy.
Renal dysfunction, including structural kidney damage, is a potential consequence of cyclosporine, and therefore, renal function must be monitored during therapy.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Kidney, Liver, and Heart Transplantation Cyclosporine capsules, USP [MODIFIED] and cyclosporine oral solution, USP [MODIFIED] are indicated for the prophylaxis of organ rejection in kidney, liver, and heart allogeneic transplants. Cyclosporine capsules, USP [MODIFIED] and cyclosporine oral solution, USP [MODIFIED] have been used in combination with azathioprine and corticosteroids. Rheumatoid Arthritis Cyclosporine capsules, USP [MODIFIED] and cyclosporine oral solution, USP [MODIFIED] are indicated for the treatment of patients with severe active, rheumatoid arthritis where the disease has not adequately responded to methotrexate.
Cyclosporine capsules, USP [MODIFIED] and cyclosporine oral solution, USP [MODIFIED] can be used in combination with methotrexate in rheumatoid arthritis patients who do not respond adequately to methotrexate alone. Psoriasis Cyclosporine capsules, USP [MODIFIED] and cyclosporine oral solution, USP [MODIFIED] are indicated for the treatment of adult, nonimmunocompromised patients with severe (i.e., extensive and/or disabling), recalcitrant, plaque psoriasis who have failed to respond to at least one systemic therapy (e.g., PUVA, retinoids, or methotrexate) or in patients for whom other systemic therapies are contraindicated, or cannot be tolerated.
While rebound rarely occurs, most patients will experience relapse with cyclosporine, USP [MODIFIED] as with other therapies upon cessation of treatment.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Cyclosporine Capsules [Modified] (Soft Gelatin) and CYCLOSPORINE ORAL SOLUTION [MODIFIED] Cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED] have increased bioavailability in comparison to Sandimmune® (cyclosporine capsules and cyclosporine oral solution). Cyclosporine [MODIFIED] and Sandimmune® are not bioequivalent and cannot be used interchangeably without physician supervision. The daily dose of cyclosporine [MODIFIED] should always be given in two divided doses (b.i.d.).
It is recommended that cyclosporine [MODIFIED] be administered on a consistent schedule with regard to time of day and relation to meals. Grapefruit and grapefruit juice affect metabolism, increasing blood concentration of cyclosporine, thus should be avoided. Specific Populations Renal Impairment in Kidney, Liver and Heart Transplantation Cyclosporine undergoes minimal renal elimination and its pharmacokinetics do not appear to be significantly altered in patients with end-stage renal disease who receive routine hemodialysis treatments ( See CLINICAL PHARMACOLOGY ).
However, due to its nephrotoxic potential ( See WARNINGS ), careful monitoring of renal function is recommended; cyclosporine dosage should be reduced if indicated. ( See WARNINGS and PRECAUTIONS ) Renal Impairment in Rheumatoid Arthritis and Psoriasis Patients with impaired renal function should not receive cyclosporine. ( see CONTRAINDICATIONS , WARNINGS and PRECAUTIONS ) Hepatic Impairment The clearance of cyclosporine may be significantly reduced in severe liver disease patients ( See CLINICAL PHARMACOLOGY ).
Dose reduction may be necessary in patients with severe liver impairment to maintain blood concentrations within the recommended target range. ( See WARNINGS and PRECAUTIONS ) Newly Transplanted Patients The initial oral dose of cyclosporine [MODIFIED] can be given 4 to 12 hours prior to transplantation or be given postoperatively. The initial dose of cyclosporine [MODIFIED] varies depending on the transplanted organ and the other immunosuppressive agents included in the immunosuppressive protocol.
In newly transplanted patients, the initial oral dose of cyclosporine [MODIFIED] is the same as the initial oral dose of Sandimmune®. Suggested initial doses are available from the results of a 1994 survey of the use of Sandimmune® in U.S. transplant centers. The mean ± SD initial doses were 9±3 mg/kg/day for renal transplant patients (75 centers), 8±4 mg/kg/day for liver transplant patients (30 centers), and 7±3 mg/kg/day for heart transplant patients (24 centers).
Total daily doses were divided into two equal daily doses. The cyclosporine [MODIFIED] dose is subsequently adjusted to achieve a pre-defined cyclosporine blood concentration. ( See Blood Concentration Monitoring in Transplant Patients , below ) If cyclosporine trough blood concentrations are used, the target range is the same for cyclosporine [MODIFIED] as for Sandimmune®.
Using the same trough concentration target range for cyclosporine [MODIFIED] as for Sandimmune® results in greater cyclosporine exposure when cyclosporine [MODIFIED] is administered. ( See Pharmacokinetics, Absorption ) Dosing should be titrated based on clinical assessments of rejection and tolerability. Lower cyclosporine [MODIFIED] doses may be sufficient as maintenance therapy.
Adjunct therapy with adrenal corticosteroids is recommended initially. Different tapering dosage schedules of prednisone appear to achieve similar results. A representative dosage schedule based on the patient's weight started with 2 mg/kg/day for the first 4 days tapered to 1 mg/kg/day by 1 week, 0.6 mg/kg/day by 2 weeks, 0.3 mg/kg/day by 1 month, and 0.15 mg/kg/day by 2 months and thereafter as a maintenance dose.
Steroid doses may be further tapered on an individualized basis depending on status of patient and function of graft. Adjustments in dosage of prednisone must be made according to the clinical situation. Conversion from… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS General Cyclosporine [MODIFIED] is contraindicated in patients with a hypersensitivity to cyclosporine or to any of the ingredients of the formulation. Rheumatoid Arthritis Rheumatoid arthritis patients with abnormal renal function, uncontrolled hypertension, or malignancies should not receive cyclosporine [MODIFIED]. Psoriasis Psoriasis patients who are treated with cyclosporine [MODIFIED] should not receive concomitant PUVA or UVB therapy, methotrexate or other immunosuppressive agents, coal tar or radiation therapy.
Psoriasis patients with abnormal renal function, uncontrolled hypertension, or malignancies should not receive cyclosporine [MODIFIED].
⚠️ Warnings ▾
WARNINGS (See also Boxed WARNING ) All Patients Cyclosporine, the active ingredient in cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED], can cause nephrotoxicity and hepatotoxicity. The risk increases with increasing doses of cyclosporine. Renal dysfunction including structural kidney damage is a potential consequence of cyclosporine [MODIFIED] and therefore renal function must be monitored during therapy.
Care should be taken in using cyclosporine with nephrotoxic drugs . (See PRECAUTIONS ) Patients receiving cyclosporine [MODIFIED] require frequent monitoring of serum creatinine. (See Special Monitoring under DOSAGE AND ADMINISTRATION ) Elderly patients should be monitored with particular care, since decreases in renal function also occur with age.
If patients are not properly monitored and doses are not properly adjusted, cyclosporine therapy can be associated with the occurrence of structural kidney damage and persistent renal dysfunction. An increase in serum creatinine and BUN may occur during cyclosporine [MODIFIED] therapy and reflect a reduction in the glomerular filtration rate. Impaired renal function at any time requires close monitoring, and frequent dosage adjustment may be indicated.
The frequency and severity of serum creatinine elevations increase with dose and duration of cyclosporine therapy. These elevations are likely to become more pronounced without dose reduction or discontinuation. Because cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED] are not bioequivalent to Sandimmune® (cyclosporine), conversion from cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED] to Sandimmune® using a 1:1 ratio (mg/kg/day) may result in lower cyclosporine blood concentrations.
Conversion from cyclosporine [MODIFIED] to Sandimmune® should be made with increased monitoring to avoid the potential of underdosing. Kidney, Liver, and Heart Transplant Nephrotoxicity Cyclosporine, the active ingredient of cyclosporine [MODIFIED], can cause nephrotoxicity and hepatotoxicity when used in high doses. It is not unusual for serum creatinine and BUN levels to be elevated during cyclosporine therapy.
These elevations in renal transplant patients do not necessarily indicate rejection, and each patient must be fully evaluated before dosage adjustment is initiated. Based on the historical Sandimmune® experience with oral solution, nephrotoxicity associated with cyclosporine had been noted in 25% of cases of renal transplantation, 38% of cases of cardiac transplantation, and 37% of cases of liver transplantation. Mild nephrotoxicity was generally noted 2 to 3 months after renal transplant and consisted of an arrest in the fall of the pre-operative elevations of BUN and creatinine at a range of 35 to 45 mg/dL and 2 to 2.5 mg/dL respectively.
These elevations were often responsive to cyclosporine dosage reduction. More overt nephrotoxicity was seen early after transplantation and was characterized by a rapidly rising BUN and creatinine. Since these events are similar to renal rejection episodes, care must be taken to differentiate between them.
This form of nephrotoxicity is usually responsive to cyclosporine dosage reduction. Although specific diagnostic criteria which reliably differentiate renal graft rejection from drug toxicity have not been found, a number of parameters have been significantly associated with one or the other. It should be noted, however, that up to 20% of patients may have simultaneous nephrotoxicity and rejection.
Nephrotoxicity vs. Rejection Parameter Nephrotoxicity Rejection History Donor >50 years old or hypotensive Prolonged kidney preservation Prolonged anastomosis time Concomitant nephrotoxic drugs Anti-donor immune response Retransplant patient Clinical Often >6 weeks postop p < 0.01, Prolonged initial nonfunction (acute tubular necrosis) Often <4 weeks postop Fever >37.5°C Weight gain >0.5 kg Graft swelling and tenderness Decrease in daily… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Kidney, Liver, and Heart Transplantation The principal adverse reactions of cyclosporine therapy are renal dysfunction, tremor, hirsutism, hypertension, and gum hyperplasia. Hypertension Hypertension, which is usually mild to moderate, may occur in approximately 50% of patients following renal transplantation and in most cardiac transplant patients. Glomerular Capillary Thrombosis Glomerular capillary thrombosis has been found in patients treated with cyclosporine and may progress to graft failure.
The pathologic changes resembled those seen in the hemolytic-uremic syndrome and included thrombosis of the renal microvasculature, with platelet-fibrin thrombi occluding glomerular capillaries and afferent arterioles, microangiopathic hemolytic anemia, thrombocytopenia, and decreased renal function. Similar findings have been observed when other immunosuppressives have been employed post-transplantation. Hypomagnesemia Hypomagnesemia has been reported in some, but not all, patients exhibiting convulsions while on cyclosporine therapy.
Although magnesium depletion studies in normal subjects suggest that hypomagnesemia is associated with neurologic disorders, multiple factors, including hypertension, high dose methylprednisolone, hypocholesterolemia, and nephrotoxicity associated with high plasma concentrations of cyclosporine appear to be related to the neurological manifestations of cyclosporine toxicity. Clinical Studies In controlled studies, the nature, severity, and incidence of the adverse events that were observed in 493 transplanted patients treated with cyclosporine [MODIFIED] were comparable with those observed in 208 transplanted patients who received Sandimmune® (cyclosporine) in these same studies when the dosage of the two drugs was adjusted to achieve the same cyclosporine blood trough concentrations.
Based on the historical experience with Sandimmune®, the following reactions occurred in 3% or greater of 892 patients involved in clinical trials of kidney, heart, and liver transplants. Randomized Kidney Patients Cyclosporine Patients (Sandimmune®) Body System Adverse Reactions Sandimmune® (N=227)% Azathioprine (N=228)% Kidney (N=705)% Heart (N=112)% Liver (N=75)% Genitourinary Renal Dysfunction 32 6 25 38 37 Cardiovascular Hypertension 26 18 13 53 27 Cramps 4 <1 2 <1 0 Skin Hirsutism 21 <1 21 28 45 Acne 6 8 2 2 1 Central Nervous System Tremor 12 0 21 31 55 Convulsions 3 1 1 4 5 Headache 2 <1 2 15 4 Gastrointestinal Gum Hyperplasia 4 0 9 5 16 Diarrhea 3 <1 3 4 8 Nausea/Vomiting 2 <1 4 10 4 Hepatotoxicity <1 <1 4 7 4 Abdominal Discomfort <1 0 <1 7 0 Autonomic Nervous System Paresthesia 3 0 1 2 1 Flushing <1 0 4 0 4 Hematopoietic Leukopenia 2 19 <1 6 0 Lymphoma <1 0 1 6 1 Respiratory Sinusitis <1 0 4 3 7 Miscellaneous Gynecomastia <1 0 <1 4 3 Among 705 kidney transplant patients treated with cyclosporine oral solution (Sandimmune®) in clinical trials, the reason for treatment discontinuation was renal toxicity in 5.4%, infection in 0.9%, lack of efficacy in 1.4%, acute tubular necrosis in 1%, lymphoproliferative disorders in 0.3%, hypertension in 0.3%, and other reasons in 0.7% of the patients.
The following reactions occurred in 2% or less of cyclosporine-treated patients: allergic reactions, anemia, anorexia, confusion, conjunctivitis, edema, fever, brittle fingernails, gastritis, hearing loss, hiccups, hyperglycemia, migraine (cyclosporine [MODIFIED]) muscle pain, peptic ulcer, thrombocytopenia, tinnitus. The following reactions occurred rarely: anxiety, chest pain, constipation, depression, hair breaking, hematuria, joint pain, lethargy, mouth sores, myocardial infarction, night sweats, pancreatitis, pruritus, swallowing difficulty, tingling, upper GI bleeding, visual disturbance, weakness, weight loss.
Patients receiving immunosuppressive therapies, including cyclosporine and cyclosporine -containing regimens, are at increased risk of infections (viral, bacterial, fungal, parasitic). Both generaliz… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions A. Effect of Drugs and Other Agents on Cyclosporine Pharmacokinetics and/or Safety All of the individual drugs cited below are well substantiated to interact with cyclosporine. In addition, concomitant use of nonsteroidal anti-inflammatory drugs with cyclosporine, particularly in the setting of dehydration, may potentiate renal dysfunction.
Caution should be exercised when using other drugs which are known to impair renal function. ( See WARNINGS, Nephrotoxicity ) Drugs That May Potentiate Renal Dysfunction Antibiotics Antineoplastics Antifungals Anti-inflammatory Drugs ciprofloxacin gentamicin tobramycin vancomycin trimethoprim with sulfamethoxazole melphalan amphotericin B ketoconazole azapropazon colchicine diclofenac naproxen sulindac Gastrointestinal Agents Immunosuppressives Other Drugs cimetidine ranitidine tacrolimus fibric acid derivatives (e.g. bezafibrate, fenofibrate) methotrexate During the concomitant use of a drug that may exhibit additive or synergistic renal impairment with cyclosporine, close monitoring of renal function (in particular serum creatinine) should be performed.
If a significant impairment of renal function occurs, the dosage of the coadministered drug should be reduced or an alternative treatment considered. Cyclosporine is extensively metabolized by CYP 3A isoenzymes, in particular CYP3A4, and is a substrate of the multidrug efflux transporter P-glycoprotein. Various agents are known to either increase or decrease plasma or whole blood concentrations of cyclosporine usually by inhibition or induction of CYP3A4 or P-glycoprotein transporter or both.
Compounds that decrease cyclosporine absorption such as orlistat should be avoided. Appropriate cyclosporine [MODIFIED]dosage adjustment to achieve the desired cyclosporine concentrations is essential when drugs that significantly alter cyclosporine concentrations are used concomitantly. (See Blood Concentration Monitoring ) 1.
Drugs That Increase Cyclosporine Concentrations Calcium Channel Blockers Antibiotics Other Drugs diltiazem azithromycin allopurinol nicardipine clarithromycin amiodarone verapamil erythromycin bromocriptine quinupristin/dalfopristin colchicine Antifungals danazol fluconazole Glucocorticoids imatinib itraconazole methylprednisolone metoclopramide ketoconazole nefazodone voriconazole oral contraceptives HIV protease inhibitors The HIV protease inhibitors (e.g., indinavir, nelfinavir, ritonavir, and saquinavir) are known to inhibit cytochrome P-450 3A and thus could potentially increase the concentrations of cyclosporine, however no formal studies of the interaction are available.
Care should be exercised when these drugs are administered concomitantly. Grapefruit Juice Grapefruit and grapefruit juice affect metabolism, increasing blood concentrations of cyclosporine, thus should be avoided. 2.
Drugs/Dietary Supplements That Decrease Cyclosporine Concentrations Antibiotics Anticonvulsants Other Drugs/Dietary Supplements nafcillin rifampin carbamazepine oxcarbazepine phenobarbital phenytoin bosentan octreotide orlistat sulfinpyrazone St. John's Wort terbinafine ticlopidine Bosentan Coadministration of bosentan (250 - 1000 mg every 12 hours based on tolerability) and cyclosporine (300 mg every 12 hours for 2 days then dosing to achieve a C min of 200-250 ng/mL) for 7 days in healthy subjects resulted in decreases in the cyclosporine mean dose-normalized AUC, C max , and trough concentration of approximately 50%, 30% and 60%, respectively, compared to when cyclosporine was given alone ( See Effect of Cyclosporine on the Pharmacokinetics and/or Safety of Other Drugs or Agents ).
Coadministration of cyclosporine with bosentan should be avoided. Boceprevir Coadministration of boceprevir (800 mg three times daily for 7 days) and cyclosporine (100 mg single dose) in healthy subjects resulted in increases in the mean AUC and C max of cyclosporine approximately 2.7-fold and 2-fold, respectively, compared to when cyclospori… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to cyclosporine during pregnancy. Encourage women who are taking cyclosporine during pregnancy to enroll in the Transplant Pregnancy Registry International (TPRI) by calling 1-877-955-8677 or visiting https://www.transplantpregnancyregistry.org. Risk Summary Available data from published literature, including the Transplant Pregnancy Registry International, observational cohort studies, case-controlled studies, meta-analysis, case series, and case reports, over decades of use with cyclosporine in pregnancy have not identified a drug associated risk of major birth defects, or miscarriage.
Adverse maternal or fetal outcomes including hypertension, preeclampsia, preterm birth, and low birth weight are increased in patients treated with cyclosporine. However, patients receiving cyclosporine during pregnancy have underlying medical conditions and may be treated with concomitant medications that limit the interpretability of these findings (see Data ). Embryo-fetal developmental (EFD) studies in rats and rabbits with cyclosporine have shown embryo-fetal toxicity at dose levels below the maximum recommended human dose (MRHD) based on body surface area (BSA).
The alcohol content of cyclosporine should be taken into account when given to pregnant women (see WARNINGS , Special Excipients ). The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data Available data from the National Transplantation Pregnancy Registry (NTPR) including 622 pregnancies in renal, liver, and heart transplant recipients exposed to cyclosporine during pregnancy found that the overall rate of major birth defects, live birth rates, and miscarriage rates were comparable to the general population.
Maternal and fetal adverse outcomes, including the rate of hypertension, preeclampsia, premature births, and low birth weight infants appear to be increased in transplant recipients treated with cyclosporine compared to the general population. However, these patients have underlying medical conditions that confound the above findings. Animal Data Animal studies have shown reproductive toxicity in rats and rabbits.
Three EFD studies (two oral and one intravenous) are available in rats. In two EFD studies, pregnant rats were orally administered with cyclosporine either at doses of 10, 17, 30, 100 and 300 mg/kg/day or 4, 10 and 25 mg/kg/day from gestation day (GD) 6 to 15 or from GD 7 to 17, respectively. Maternal toxicity characterized by mortality, clinical signs of toxicity and impaired body weight gain were observed at 30 mg/kg/day and above.
Cyclosporine was embryo- and fetotoxic as indicated by increased embryonic mortality and reduced fetal weight together with skeletal retardations in rats at 25 mg/kg/day and above. In addition, ventricular septal defect was observed at 25 mg/kg/day in fetuses. In the first study, the oral no observed effect level (NOEL) for both dams and fetuses was 17 mg/kg/day (0.2 times the MRHD based on BSA).
In the other oral study, the NOEL for dams and fetuses were 10 and 4 mg/kg/day (0.13 and 0.05 times the MRHD based on BSA), respectively. In the IV EFD study, rats were administered with 3, 6 and 12 mg/kg/day of cyclosporine from GD 7 to 17. An increase in post implantation loss was observed at 12 mg/kg/day; ventricular septal defect was observed at ≥ 6 mg/kg/day in fetuses.
The IV NOEL for dams and fetus were 6 and 3 mg/kg/day (0.08 and 0.04 times the MRHD, respectively, based on BSA), respectively, after IV administration. In rabbits, cyclosporine was orally administered at dose level… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
Pediatric Use Although no adequate and well-controlled studies have been completed in children, transplant recipients as young as one year of age have received cyclosporine [MODIFIED] with no unusual adverse effects. The safety and efficacy of cyclosporine [MODIFIED] treatment in children with juvenile rheumatoid arthritis or psoriasis below the age of 18 have not been established.
🧓 Geriatric Use ▾
Geriatric Use In rheumatoid arthritis clinical trials with cyclosporine, 17.5% of patients were age 65 or older. These patients were more likely to develop systolic hypertension on therapy, and more likely to show serum creatinine rises greater than or equal to 50% above the baseline after 3 to 4 months of therapy. Clinical studies of cyclosporine [MODIFIED] in transplant and psoriasis patients did not include a sufficient number of subjects aged 65 and over to determine whether they respond differently from younger subjects.
Other reported clinical experiences have not identified differences in response between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE There is a minimal experience with cyclosporine overdosage. Forced emesis can be of value up to 2 hours after administration of cyclosporine [MODIFIED]. Transient hepatotoxicity and nephrotoxicity may occur which should resolve following drug withdrawal.
Oral doses of cyclosporine up to 10 g (about 150 mg/kg) have been tolerated with relatively minor clinical consequences, such as vomiting, drowsiness, headache, tachycardia and, in a few patients, moderately severe, reversible impairment of renal function. However, serious symptoms of intoxication have been reported following accidental parenteral overdosage with cyclosporine in premature neonates. General supportive measures and symptomatic treatment should be followed in all cases of overdosage.
Cyclosporine is not dialyzable to any great extent, nor is it cleared well by charcoal hemoperfusion. The oral dosage at which half of experimental animals are estimated to die is 31 times, 39 times, and >54 times the human maintenance dose for transplant patients (6 mg/kg; corrections based on body surface area) in mice, rats, and rabbits.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Cyclosporine is a potent immunosuppressive agent that in animals prolongs survival of allogeneic transplants involving skin, kidney, liver, heart, pancreas, bone marrow, small intestine, and lung. Cyclosporine has been demonstrated to suppress some humoral immunity and to a greater extent, cell-mediated immune reactions such as allograft rejection, delayed hypersensitivity, experimental allergic encephalomyelitis, Freund's adjuvant arthritis, and graft vs. host disease in many animal species for a variety of organs.
The effectiveness of cyclosporine results from specific and reversible inhibition of immunocompetent lymphocytes in the G 0 - and G 1 -phase of the cell cycle. T-lymphocytes are preferentially inhibited. The T-helper cell is the main target, although the T-suppressor cell may also be suppressed.
Cyclosporine also inhibits lymphokine production and release including interleukin-2. No effects on phagocytic function (changes in enzyme secretions, chemotactic migration of granulocytes, macrophage migration, carbon clearance in vivo ) have been detected in animals. Cyclosporine does not cause bone marrow suppression in animal models or man.
Pharmacokinetics The immunosuppressive activity of cyclosporine is primarily due to parent drug. Following oral administration, absorption of cyclosporine is incomplete. The extent of absorption of cyclosporine is dependent on the individual patient, the patient population, and the formulation.
Elimination of cyclosporine is primarily biliary with only 6% of the dose (parent drug and metabolites) excreted in urine. The disposition of cyclosporine from blood is generally biphasic, with a terminal half-life of approximately 8.4 hours (range 5 to 18 hours). Following intravenous administration, the blood clearance of cyclosporine (assay: HPLC) is approximately 5 to 7 mL/min/kg in adult recipients of renal or liver allografts.
Blood cyclosporine clearance appears to be slightly slower in cardiac transplant patients. Cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED] are bioequivalent. Cyclosporine oral solution [MODIFIED] diluted with orange juice or apple juice is bioequivalent to cyclosporine oral solution [MODIFIED] diluted with water.
The effect of milk on the bioavailability of cyclosporine when administered as cyclosporine oral solution [MODIFIED] has not been evaluated. The relationship between administered dose and exposure (area under the concentration versus time curve, AUC) is linear within the therapeutic dose range. The intersubject variability (total, %CV) of cyclosporine exposure (AUC) when cyclosporine [MODIFIED] or Sandimmune® is administered ranges from approximately 20% to 50% in renal transplant patients.
This intersubject variability contributes to the need for individualization of the dosing regimen for optimal therapy ( see DOSAGE AND ADMINISTRATION ). Intrasubject variability of AUC in renal transplant recipients (%CV) was 9% to 21% for cyclosporine [MODIFIED] and 19% to 26% for Sandimmune®. In the same studies, intrasubject variability of trough concentrations (%CV) was 17% to 30% for cyclosporine [MODIFIED] and 16% to 38% for Sandimmune®.
Absorption Cyclosporine [MODIFIED] has increased bioavailability compared to Sandimmune® (cyclosporine). The absolute bioavailability of cyclosporine administered as Sandimmune® is dependent on the patient population, estimated to be less than 10% in liver transplant patients and as great as 89% in some renal transplant patients. The absolute bioavailability of cyclosporine administered as cyclosporine [MODIFIED] has not been determined in adults.
In studies of renal transplant, rheumatoid arthritis and psoriasis patients, the mean cyclosporine AUC was approximately 20% to 50% greater and the peak blood cyclosporine concentration (C max ) was approximately 40% to 106% greater following administration of cyclosporine [MODIFIED] compared to following administration of Sandimmune®. The… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cyclosporine Capsules, USP [MODIFIED] 25 mg — Off-white, oval, soft gelatin capsules. Imprinted in red: PA09 Packages of 30 unit-dose blisters. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature] 100 mg — Off-white, oblong, soft gelatin capsules.
Imprinted in red: PA20 Packages of 30 unit-dose blisters. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature] Cyclosporine Oral Solution, USP [MODIFIED] A light yellow liquid supplied in 50 mL bottles containing 100 mg/mL and a 4 mL dosing syringe with case. Store and Dispense In the original container at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Do not store in the refrigerator. Once opened, the contents must be used within two months. At temperatures below 68°F (20°C) the solution may gel; light flocculation or the formation of a light sediment or flakes may also form.
Allow contents to reach room temperature to reverse these effects. There is no impact on product performance or dose.
📦 Storage and Handling ▾
Cyclosporine Capsules, USP [MODIFIED] 25 mg — Off-white, oval, soft gelatin capsules. Imprinted in red: PA09 Packages of 30 unit-dose blisters. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature] 100 mg — Off-white, oblong, soft gelatin capsules.
Imprinted in red: PA20 Packages of 30 unit-dose blisters. Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]
Store and Dispense In the original container at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. Do not store in the refrigerator. Once opened, the contents must be used within two months. At temperatures below 68°F (20°C) the solution may gel; light flocculation or the formation of a light sediment or flakes may also form. Allow contents to reach room temperature to reverse these effects. There is no impact on product performance or dose.
📋 Description ▾
DESCRIPTION Cyclosporine capsules, USP [MODIFIED] and cyclosporine oral solution, USP [MODIFIED] are oral formulations of cyclosporine that immediately forms a microemulsion in an aqueous environment. Cyclosporine, the active principle in cyclosporine capsules [MODIFIED] and cyclosporine oral solution, USP [MODIFIED], is a cyclic polypeptide immunosuppressant agent consisting of 11 amino acids. It is produced as a metabolite by the fungus species Beauveria nivea .
Chemically, cyclosporine is designated as [ R -[ R *, R *-( E )]]-cyclic-(L-alanyl-D-alanyl- N -methyl-L-leucyl- N -methyl-L-leucyl- N -methyl-L-valyl-3-hydroxy- N , 4-dimethyl-L-2-amino-6-octenoyl-L-α-amino-butyryl- N -methylglycyl- N -methyl-L-leucyl-L-valyl- N -methyl-L-leucyl). Each soft gelatin cyclosporine capsule, USP [Modified] for oral administration contains 25 mg or 100 mg of cyclosporine, USP. In addition, each capsule contains the following inactive ingredients: Caprylic/capric triglyceride, dl-alpha-tocopherol, gelatin, glycerin, glyceryl caprylate, PEG-8 caprylic/capric glycerides, PEG-35 castor oil, red iron oxide, shellac, sorbitol special 76% and titanium dioxide USP.
Cyclosporine oral solution, USP [MODIFIED] contains 100 mg/mL of cyclosporine, USP. Inactive ingredients: Caprylic/capric triglyceride, dl-alpha-tocopherol, glyceryl caprylate, PEG-8 caprylic/capric glycerides, PEG-35 castor oil. The chemical structure of cyclosporine, USP (also known as cyclosporin A) is:
💬 Information for Patients ▾
Information for Patients Patients should be advised that any change of cyclosporine formulation should be made cautiously and only under physician supervision because it may result in the need for a change in dosage. Patients should be informed of the necessity of repeated laboratory tests while they are receiving cyclosporine. Patients should be advised of the potential risks during pregnancy and informed of the increased risk of neoplasia.
Patients should also be informed of the risk of hypertension and renal dysfunction. Patients should be advised that during treatment with cyclosporine, vaccination may be less effective and the use of live attenuated vaccines should be avoided. Patients should be given careful dosage instructions.
Cyclosporine oral solution [MODIFIED] should be diluted, preferably with orange or apple juice that is at room temperature. The combination of cyclosporine oral solution [MODIFIED] with milk can be unpalatable. Patients should be advised to take cyclosporine [MODIFIED] on a consistent schedule with regard to time of day and relation to meals.
Grapefruit and grapefruit juice affect metabolism, increasing blood concentration of cyclosporine, thus should be avoided. Cyclosporine may impact the ability to drive and use machines. Patients should be advised to exercise care when driving or using machines if they experience neurological disturbances including confusion, somnolence, or dizziness and discuss with their healthcare provider (see WARNINGS and ADVERSE REACTIONS ).
⚠️ Precautions ▾
PRECAUTIONS General Hypertension Cyclosporine is the active ingredient of cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED]. Hypertension is a common side effect of cyclosporine therapy which may persist. ( See ADVERSE REACTIONS and DOSAGE AND ADMINISTRATION for monitoring recommendations.) Mild or moderate hypertension is encountered more frequently than severe hypertension and the incidence decreases over time.
In recipients of kidney, liver, and heart allografts treated with cyclosporine, antihypertensive therapy may be required. (See Special Monitoring of Rheumatoid Arthritis and Psoriasis Patients .) However, since cyclosporine may cause hyperkalemia, potassium-sparing diuretics should not be used. While calcium antagonists can be effective agents in treating cyclosporine-associated hypertension, they can interfere with cyclosporine metabolism.
( See Drug Interactions .) Vaccination During treatment with cyclosporine, vaccination may be less effective; and the use of live attenuated vaccines should be avoided. Special Monitoring of Rheumatoid Arthritis Patients Before initiating treatment, a careful physical examination, including blood pressure measurements (on at least two occasions) and two creatinine levels to estimate baseline should be performed. Blood pressure and serum creatinine should be evaluated every 2 weeks during the initial 3 months and then monthly if the patient is stable.
It is advisable to monitor serum creatinine and blood pressure always after an increase of the dose of nonsteroidal anti-inflammatory drugs and after initiation of new nonsteroidal anti-inflammatory drug therapy during cyclosporine [MODIFIED] treatment. If coadministered with methotrexate, CBC and liver function tests are recommended to be monitored monthly. ( See also PRECAUTIONS, General, Hypertension ) In patients who are receiving cyclosporine, the dose of cyclosporine [MODIFIED] should be decreased by 25% to 50% if hypertension occurs.
If hypertension persists, the dose of cyclosporine [MODIFIED] should be further reduced or blood pressure should be controlled with anti-hypertensive agents. In most cases, blood pressure has returned to baseline when cyclosporine was discontinued. In placebo-controlled trials of rheumatoid arthritis patients, systolic hypertension (defined as an occurrence of two systolic blood pressure readings >140 mm Hg) and diastolic hypertension (defined as two diastolic blood pressure readings >90 mm Hg) occurred in 33% and 19% of patients treated with cyclosporine, respectively.
The corresponding placebo rates were 22% and 8%. Special Monitoring of Psoriasis Patients Before initiating treatment, a careful dermatological and physical examination, including blood pressure measurements (on at least two occasions) should be performed. Since cyclosporine [MODIFIED] is an immunosuppressive agent, patients should be evaluated for the presence of occult infection on their first physical examination and for the presence of tumors initially, and throughout treatment with cyclosporine [MODIFIED].
Skin lesions not typical for psoriasis should be biopsied before starting cyclosporine [MODIFIED]. Patients with malignant or premalignant changes of the skin should be treated with cyclosporine [MODIFIED] only after appropriate treatment of such lesions and if no other treatment option exists. Baseline laboratories should include serum creatinine (on two occasions), BUN, CBC, serum magnesium, potassium, uric acid, and lipids.
The risk of cyclosporine nephropathy is reduced when the starting dose is low (2.5 mg/kg/day), the maximum dose does not exceed 4 mg/kg/day, serum creatinine is monitored regularly while cyclosporine is administered, and the dose of cyclosporine [MODIFIED] is decreased when the rise in creatinine is greater than or equal to 25% above the patient's pretreatment level. The increase in creatinine is generally reversible upon timely decrease of the dose of cyclosporine [MODIFIED] or… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Risk Summary Cyclosporine and its metabolites are present in human milk following oral and intravenous administration. Adverse effects on the breastfed infant have not been reported. There are no data on the effects of the drug on milk production.
The alcohol content of NEORAL should be taken into account when given to lactating women (see WARNINGS , Special Excipients ). Lactating women are encouraged to avoid additional alcohol intake during treatment. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for NEORAL and any potential adverse effects on the breastfed infant from NEORAL or from the underlying maternal condition.
🧬 Pharmacokinetics ▾
Pharmacokinetics The immunosuppressive activity of cyclosporine is primarily due to parent drug. Following oral administration, absorption of cyclosporine is incomplete. The extent of absorption of cyclosporine is dependent on the individual patient, the patient population, and the formulation.
Elimination of cyclosporine is primarily biliary with only 6% of the dose (parent drug and metabolites) excreted in urine. The disposition of cyclosporine from blood is generally biphasic, with a terminal half-life of approximately 8.4 hours (range 5 to 18 hours). Following intravenous administration, the blood clearance of cyclosporine (assay: HPLC) is approximately 5 to 7 mL/min/kg in adult recipients of renal or liver allografts.
Blood cyclosporine clearance appears to be slightly slower in cardiac transplant patients. Cyclosporine capsules [MODIFIED] and cyclosporine oral solution [MODIFIED] are bioequivalent. Cyclosporine oral solution [MODIFIED] diluted with orange juice or apple juice is bioequivalent to cyclosporine oral solution [MODIFIED] diluted with water.
The effect of milk on the bioavailability of cyclosporine when administered as cyclosporine oral solution [MODIFIED] has not been evaluated. The relationship between administered dose and exposure (area under the concentration versus time curve, AUC) is linear within the therapeutic dose range. The intersubject variability (total, %CV) of cyclosporine exposure (AUC) when cyclosporine [MODIFIED] or Sandimmune® is administered ranges from approximately 20% to 50% in renal transplant patients.
This intersubject variability contributes to the need for individualization of the dosing regimen for optimal therapy ( see DOSAGE AND ADMINISTRATION ). Intrasubject variability of AUC in renal transplant recipients (%CV) was 9% to 21% for cyclosporine [MODIFIED] and 19% to 26% for Sandimmune®. In the same studies, intrasubject variability of trough concentrations (%CV) was 17% to 30% for cyclosporine [MODIFIED] and 16% to 38% for Sandimmune®.
Absorption Cyclosporine [MODIFIED] has increased bioavailability compared to Sandimmune® (cyclosporine). The absolute bioavailability of cyclosporine administered as Sandimmune® is dependent on the patient population, estimated to be less than 10% in liver transplant patients and as great as 89% in some renal transplant patients. The absolute bioavailability of cyclosporine administered as cyclosporine [MODIFIED] has not been determined in adults.
In studies of renal transplant, rheumatoid arthritis and psoriasis patients, the mean cyclosporine AUC was approximately 20% to 50% greater and the peak blood cyclosporine concentration (C max ) was approximately 40% to 106% greater following administration of cyclosporine [MODIFIED] compared to following administration of Sandimmune®. The dose normalized AUC in de novo liver transplant patients administered cyclosporine [MODIFIED] 28 days after transplantation was 50% greater and C max was 90% greater than in those patients administered Sandimmune®.
AUC and C max are also increased (cyclosporine [MODIFIED] relative to Sandimmune®) in heart transplant patients, but data are very limited. Although the AUC and C max values are higher on cyclosporine [MODIFIED] relative to Sandimmune®, the pre-dose trough concentrations (dose-normalized) are similar for the two formulations. Following oral administration of cyclosporine [MODIFIED], the time to peak blood cyclosporine concentrations (T max ) ranged from 1.5 to 2 hours.
The administration of food with cyclosporine [MODIFIED] decreases the cyclosporine AUC and C max . A high fat meal (669 kcal, 45 grams fat) consumed within one-half hour before cyclosporine [MODIFIED] administration decreased the AUC by 13% and C max by 33%. The effects of a low fat meal (667 kcal, 15 grams fat) were similar.
The effect of T-tube diversion of bile on the absorption of cyclosporine from cyclosporine [MODIFIED] was investigated in eleven de novo liver transplant patients. When t… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
Clinical Studies In controlled studies, the nature, severity, and incidence of the adverse events that were observed in 493 transplanted patients treated with cyclosporine [MODIFIED] were comparable with those observed in 208 transplanted patients who received Sandimmune® (cyclosporine) in these same studies when the dosage of the two drugs was adjusted to achieve the same cyclosporine blood trough concentrations. Based on the historical experience with Sandimmune®, the following reactions occurred in 3% or greater of 892 patients involved in clinical trials of kidney, heart, and liver transplants.
Randomized Kidney Patients Cyclosporine Patients (Sandimmune®) Body System Adverse Reactions Sandimmune® (N=227)% Azathioprine (N=228)% Kidney (N=705)% Heart (N=112)% Liver (N=75)% Genitourinary Renal Dysfunction 32 6 25 38 37 Cardiovascular Hypertension 26 18 13 53 27 Cramps 4 <1 2 <1 0 Skin Hirsutism 21 <1 21 28 45 Acne 6 8 2 2 1 Central Nervous System Tremor 12 0 21 31 55 Convulsions 3 1 1 4 5 Headache 2 <1 2 15 4 Gastrointestinal Gum Hyperplasia 4 0 9 5 16 Diarrhea 3 <1 3 4 8 Nausea/Vomiting 2 <1 4 10 4 Hepatotoxicity <1 <1 4 7 4 Abdominal Discomfort <1 0 <1 7 0 Autonomic Nervous System Paresthesia 3 0 1 2 1 Flushing <1 0 4 0 4 Hematopoietic Leukopenia 2 19 <1 6 0 Lymphoma <1 0 1 6 1 Respiratory Sinusitis <1 0 4 3 7 Miscellaneous Gynecomastia <1 0 <1 4 3 Among 705 kidney transplant patients treated with cyclosporine oral solution (Sandimmune®) in clinical trials, the reason for treatment discontinuation was renal toxicity in 5.4%, infection in 0.9%, lack of efficacy in 1.4%, acute tubular necrosis in 1%, lymphoproliferative disorders in 0.3%, hypertension in 0.3%, and other reasons in 0.7% of the patients.
The following reactions occurred in 2% or less of cyclosporine-treated patients: allergic reactions, anemia, anorexia, confusion, conjunctivitis, edema, fever, brittle fingernails, gastritis, hearing loss, hiccups, hyperglycemia, migraine (cyclosporine [MODIFIED]) muscle pain, peptic ulcer, thrombocytopenia, tinnitus. The following reactions occurred rarely: anxiety, chest pain, constipation, depression, hair breaking, hematuria, joint pain, lethargy, mouth sores, myocardial infarction, night sweats, pancreatitis, pruritus, swallowing difficulty, tingling, upper GI bleeding, visual disturbance, weakness, weight loss.
Patients receiving immunosuppressive therapies, including cyclosporine and cyclosporine -containing regimens, are at increased risk of infections (viral, bacterial, fungal, parasitic). Both generalized and localized infections can occur. Pre-existing infections may also be aggravated.
Fatal outcomes have been reported ( see Warnings ). Infectious Complication In Historical Randomized Studies In Renal Transplant Patients Using Sandimmune® Complication Cyclosporine Treatment (N=227) Azathioprine with Steroids Some patients also received ALG. (N=228) % of Complications % of Complications Septicemia 5.3
4.8Abscesses 4.4
5.3Systemic Fungal Infection 2.2
3.9Local Fungal Infection 7.5
9.6Cytomegalovirus 4.8
12.3Other Viral Infections 15.9
18.4Urinary Tract Infections 21.1
20.2 Wound and Skin Infections 7
10.1Pneumonia 6.2 9.2
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies were carried out in male and female rats and mice. In the 78-week mouse study, evidence of a statistically significant trend was found for lymphocytic lymphomas in females, and the incidence of hepatocellular carcinomas in mid-dose(0.03 times the maximum recommended human dose (MRHD) based on body surface area (BSA) males significantly exceeded the control value. In the 24-month rat study, pancreatic islet cell adenomas significantly exceeded the control rate in the low dose level (0.006 times the MRHD based on BSA).
The hepatocellular carcinomas and pancreatic islet cell adenomas were not dose related. Published reports indicate that co-treatment of hairless mice with UV irradiation and cyclosporine or other immunosuppressive agents shorten the time to skin tumor formation compared to UV irradiation alone. Cyclosporine has not been found to be mutagenic/genotoxic in the Ames Test, the V79-HGPRT Test, the micronucleus test in mice and Chinese hamsters, the chromosome-aberration tests in Chinese hamster bone-marrow, the mouse dominant lethal assay, and the DNA-repair test in sperm from treated mice.
A recent study analyzing sister chromatid exchange (SCE) induction by cyclosporine using human lymphocytes in vitro gave indication of a positive effect (i.e., induction of SCE), at high concentrations in this system. In a fertility study in rats, increased perinatal mortality and impaired postnatal development of F1 pups were observed at 15 mg/kg/day (0.2 times the MRHD based on BSA). No adverse effects on fertility and reproduction were observed up to 5 mg/kg/day (0.06 times the MRHD based on BSA) in male and female rats.
Widely distributed papillomatosis of the skin was observed after chronic treatment of dogs with cyclosporine at 9 times the human initial psoriasis treatment dose of 2.5 mg/kg, where doses are expressed on a body surface area basis. This papillomatosis showed a spontaneous regression upon discontinuation of cyclosporine. An increased incidence of malignancy is a recognized complication of immunosuppression in recipients of organ transplants and patients with rheumatoid arthritis and psoriasis.
The most common forms of neoplasms are non-Hodgkin's lymphoma and carcinomas of the skin. The risk of malignancies in cyclosporine recipients is higher than in the normal, healthy population but similar to that in patients receiving other immunosuppressive therapies. Reduction or discontinuance of immunosuppression may cause the lesions to regress.
In psoriasis patients on cyclosporine, development of malignancies, especially those of the skin has been reported. ( See WARNINGS ) Skin lesions not typical for psoriasis should be biopsied before starting cyclosporine treatment. Patients with malignant or premalignant changes of the skin should be treated with cyclosporine only after appropriate treatment of such lesions and if no other treatment option exists.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 25 mg Capsule Blister Pack Box NDC 75907-047-30 CycloSPORINE Capsules, USP [MODIFIED] 25 mg WARNING: CycloSPORINE capsules, USP [MODIFIED] is NOT BIOEQUIVALENT to Sandimmune ® * (CycloSPORINE capsules, USP [NON-MODIFIED]). Do NOT use interchangeably without a physician's supervision. *Sandimmune ® is a registered trademark of Novartis Pharmaceuticals Corporation. Rx Only 30 Soft Gelatin Capsules Dr. Reddys's Laboratories, Inc
PRINCIPAL DISPLAY PANEL - 100 mg Capsule Blister Pack Box NDC 75907-048-30 CycloSPORINE Capsules, USP [MODIFIED] 100 mg WARNING: CycloSPORINE capsules, USP [MODIFIED] is NOT BIOEQUIVALENT to Sandimmune ® * (CycloSPORINE capsules, USP [NON-MODIFIED]). Do NOT use interchangeably without a physician's supervision. *Sandimmune ® is a registered trademark of Novartis Pharmaceuticals Corporation. Rx Only 30 Soft Gelatin Capsules Dr. Reddy's Laboratories, Inc