
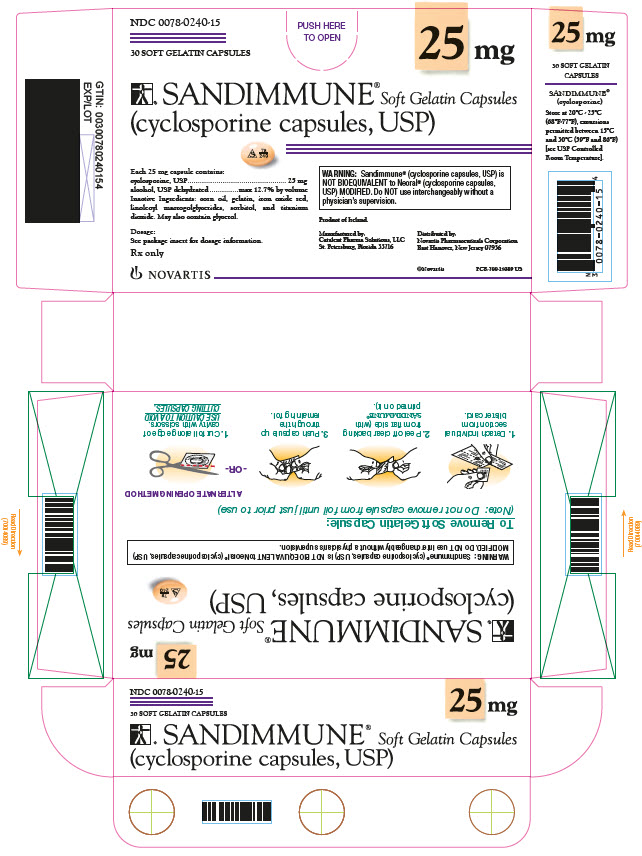
Sandimmune cyclosporine 25 mg Capsule, Liquid Filled
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcineurin Inhibitor Immunosuppressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- The IV injection form of Sandimmune is specifically reserved for patients who can't swallow or tolerate the capsules right away — like right before or after transplant surgery. As...
- Why am I getting cyclosporine as an injection instead of a pill?
- The main thing to know is that about 1 in 1,000 people can have a serious allergic reaction (called anaphylaxis) to Sandimmune injection — likely from the oil used in the IV formul...
- What side effects should I actually watch out for during the infusion?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cyclosporine — tap one for details:
Cyclosporine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII D5340Y2I9G
Castor oil is a natural plant-based oil used in medicines as a lubricant, laxative agent, and solvent. It helps medicine ingredients dissolve or flow smoothly and can aid bowel movement in formulations designed for that purpose.
-
UNII 8470G57WFM
Corn oil is a vegetable oil extracted from corn kernels. It's used in medicines as a solvent to dissolve active ingredients and help the body absorb them, and sometimes as a lubricant in capsules.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 6UYK2W1W1E
A natural oil extracted from olives. It acts as an emollient and lubricant in formulations, helping to soften ingredients and improve how the medicine spreads or flows.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.41 | — |
| Medicare Part B allowsASP · J7515 | $0.552 / J7515 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| CycloSPORINE, Modfied 25 mg 60505-4630-03 | Apotex | 10 capsules | $0.317 | AB1 | Availability likely | — |
| Cyclosporine 25 mg 23155-0837-30 | Heritage | 10 capsules | $0.317 | AB1 | Availability likely | — |
| Cyclosporine Modified 25 mg 00093-9018-65 | Teva | 1 capsule | $0.317 | AB1 | Availability likely | — |
| Cyclosporine 25 mg 75907-0047-30 | Dr. | 1 capsule | $0.318 | AB1 | FDA listed | — |
| Gengraf 25 mg 00074-3108-32 | AbbVie | 30 capsules | $1.865 | AB1 | Availability likely | — |
| Cyclosporine 25 mg 60505-0133-00 | Apotex | 30 capsules | $2.578 | AB2 | Availability likely | — |
| Cyclosporine 25 mg 68084-0879-25 | American | 1 capsule | $2.578 | AB2 | Availability likely | — |
| Neoral 25 mg 00078-0246-15 | Novartis | 1 capsule | $2.946 | AB1 | Availability likely | — |
| Sandimmune 25 mgthis 00078-0240-15 | Novartis | 1 capsule | — | AB2 | FDA listed | — |
| Cyclosporine 25 mg 64380-0127-02 | Strides | 10 capsules | — | AB1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00078-0240-15 You're viewing this | 30 BLISTER PACK in 1 PACKAGE (0078-0240-15) / 1 CAPSULE, LIQUID FILLED in 1 BLISTER PACK (0078-0240-61) | 1990-03-02 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RECOMMENDATIONS FOR USE, USE WITH CORTICOSTERIODS, RISKS WITH INAPPROPRIATE SWITCHING, and MONITORING CYCLOSPORINE BLOOD LEVELS Recommendations for Use Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe Sandimmune. Patients receiving Sandimmune should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physician responsible for maintenance therapy should have complete information requisite for the follow-up of the patient.
Use with Corticosteroids Sandimmune should be administered with adrenal corticosteroids but not with other immunosuppressive agents. Increased susceptibility to infection and the possible development of lymphoma may result from immunosuppression. Risks with Inappropriate Switching Between Neoral Capsules (MODIFIED) and Sandimmune Capsules Do not switch between Sandimmune capsules, 25 mg to Neoral capsules, MODIFIED, 25 mg (or between Sandimmune capsules, 100 mg to Neoral capsules, MODIFIED 100 mg) on a mg-to-mg basis to achieve the same total daily cyclosporine dosage.
Inappropriate switching may lead to increased cyclosporine exposure which may increase the risk of cyclosporine-associated adverse reactions or decreased cyclosporine exposure which may decrease the efficacy of cyclosporine. Monitoring Cyclosporine Blood Levels The absorption of cyclosporine during chronic administration of Sandimmune capsules was found to be erratic. It is recommended that patients taking the Sandimmune capsules over a period of time be monitored at repeated intervals for cyclosporine blood concentrations and subsequent dosage adjustments be made in order to avoid toxicity due to high concentrations and possible organ rejection due to low absorption of cyclosporine.
This is of special importance in liver transplants. Numerous assays are being developed to measure blood concentrations of cyclosporine. Comparison of concentrations in published literature to patient concentrations using current assays must be done with detailed knowledge of the assay methods employed (see DOSAGE AND ADMINISTRATION, Blood Concentration Monitoring) .
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Sandimmune capsules and Sandimmune injection, in combination with adrenal corticosteroids, are indicated for the: Prophylaxis of organ rejection in kidney, liver, and heart allogeneic transplants. Treatment of chronic rejection in patients previously treated with other immunosuppressive agents. Because of the risk of anaphylaxis, Sandimmune injection should be reserved for patients who are unable to take the Sandimmune capsules.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Recommended Dosage for Sandimmune Capsules Sandimmune (cyclosporine capsules) 25 mg and 100 mg and Neoral (cyclosporine capsules), MODIFIED 25 mg and 100 mg are not mutually substitutable on a mg-to-mg basis due to differences in pharmacokinetic profiles. If it is appropriate to switch from Neoral capsules, MODIFIED, to Sandimmune capsules, increase the frequency of cyclosporine monitoring (the cyclosporine dosage may need to be increased to reach the desired cyclosporine exposure and reduce the risk of insufficient efficacy).
If it is appropriate to switch from Sandimmune capsules to Neoral capsules, increase the frequency of cyclosporine monitoring (the cyclosporine dosage may need to be decreased to reach the desired cyclosporine exposure and reduce the risk of cyclosporine-related adverse reactions). The initial oral dose of Sandimmune capsules should be given 4 to 12 hours prior to transplantation as a single dose of 15 mg/kg. Although a daily single dose of 14 to 18 mg/kg was used in most clinical trials, few centers continue to use the highest dose, most favoring the lower end of the scale.
There is a trend towards use of even lower initial doses for renal transplantation in the ranges of 10 to 14 mg/kg/day. The initial single daily dose is continued postoperatively for 1 to 2 weeks and then tapered by 5% per week to a maintenance dose of 5 to 10 mg/kg/day. Some centers have successfully tapered the maintenance dose to as low as 3 mg/kg/day in selected renal transplant patients without an apparent rise in rejection rate.
See Blood Concentration Monitoring, below . Recommended Dosage of the Sandimmune Capsules in Patients with Renal Impairment Cyclosporine undergoes minimal renal elimination and its pharmacokinetics do not appear to be significantly altered in patients with end-stage renal disease who receive routine hemodialysis treatments (see CLINICAL PHARMACOLOGY) . However, due to its nephrotoxic potential (see WARNINGS) , careful monitoring of renal function is recommended; cyclosporine dosage should be reduced if indicated (see WARNINGS and PRECAUTIONS) .
Recommended Dosage of the Sandimmune Capsules in Patients with Hepatic Impairment The clearance of cyclosporine may be significantly reduced in severe liver disease patients (see CLINICAL PHARMACOLOGY) . Dose reduction may be necessary in patients with severe liver impairment to maintain blood concentrations within the recommended target range (see WARNINGS and PRECAUTIONS) . Recommended Dosage of the Sandimmune Capsules in Pediatric Patients In pediatric usage, the same dose and dosing regimen may be used as in adults although in several studies, children have required and tolerated higher doses than those used in adults.
Adjunct therapy with adrenal corticosteroids is recommended. Different tapering dosage schedules of prednisone appear to achieve similar results. A dosage schedule based on the patient’s weight started with 2.0 mg/kg/day for the first 4 days tapered to 1.0 mg/kg/day by 1 week, 0.6 mg/kg/day by 2 weeks, 0.3 mg/kg/day by 1 month, and 0.15 mg/kg/day by 2 months and thereafter as a maintenance dose.
Another center started with an initial dose of 200 mg tapered by 40 mg/day until reaching 20 mg/day. After 2 months at this dose, a further reduction to 10 mg/day was made. Adjustments in dosage of prednisone must be made according to the clinical situation.
Sandimmune capsules should be administered on a consistent schedule with regard to time of day and relation to meals. Recommended Dosage for Sandimmune Injection Sandimmune injection is for infusion only. Patients unable to take Sandimmune capsules pre- or postoperatively may be treated with Sandimmune Injection, for intravenous use.
Sandimmune injection is administered at 1/3 the oral dosage of Sandimmune capsules. The initial dose of Sandimmune injection should be given 4 to 12 hours prior to transplantation as a single intravenous dose of 5 to 6 mg/kg/day. This daily sin…
⛔ Contraindications ▾
CONTRAINDICATIONS Sandimmune capsules and Sandimmune injection are contraindicated in patients with a hypersensitivity reaction to cyclosporine. Sandimmune injection is also contraindicated in patients with a history of a hypersensitivity reaction to Cremophor ® EL (polyoxyethylated castor oil).
⚠️ Warnings ▾
WARNINGS Kidney, Liver, and Heart Transplant Sandimmune, when used in high dosages, can cause hepatotoxicity and nephrotoxicity (see BOXED WARNING) . Nephrotoxicity It is not unusual for serum creatinine and Blood Urea Nitrogen (BUN) levels to be elevated during Sandimmune therapy. These elevations in renal transplant patients do not necessarily indicate rejection, and each patient must be fully evaluated before dosage adjustment is initiated.
Nephrotoxicity has been noted in 25% of cases of renal transplantation, 38% of cases of cardiac transplantation, and 37% of cases of liver transplantation. Mild nephrotoxicity was generally noted 2 to 3 months after transplant and consisted of an arrest in the fall of the preoperative elevations of BUN and creatinine at a range of 35 to 45 mg/dl and 2.0 to 2.5 mg/dl, respectively. These elevations were often responsive to dosage reduction.
More overt nephrotoxicity was seen early after transplantation and was characterized by a rapidly rising BUN and creatinine. Since these events are similar to rejection episodes, care must be taken to differentiate between them. This form of nephrotoxicity is usually responsive to Sandimmune dosage reduction.
Although specific diagnostic criteria which reliably differentiate renal graft rejection from drug toxicity have not been found, a number of parameters have been significantly associated to one or the other. It should be noted however, that up to 20% of patients may have simultaneous nephrotoxicity and rejection. a p < 0.05, b p < 0.01, c p < 0.001, d p < 0.0001. Nephrotoxicity vs.
Rejection Parameter Nephrotoxicity Rejection History Donor > 50 years old or hypotensive Antidonor immune response Prolonged kidney preservation Retransplant patient Prolonged anastomosis time Concomitant nephrotoxic drugs Clinical Often > 6 weeks postop b Often < 4 weeks postop b Prolonged initial nonfunction (acute tubular necrosis) Fever > 37.5°C Weight gain > 0.5 kg Graft swelling and tenderness Decrease in daily urine volume > 500 mL (or 50%) Laboratory CyA serum trough level > 200 ng/mL CyA serum trough level < 150 ng/mL Gradual rise in Cr (< 0.15 mg/dL/day) a Rapid rise in Cr (> 0.3 mg/dL/day) a Cr plateau < 25% above baseline Cr > 25% above baseline BUN/Cr ≥ 20 BUN/Cr < 20 Biopsy Arteriolopathy (medial hypertrophy a , hyalinosis, nodular deposits, intimal thickening, endothelial vacuolization, progressive scarring) Endovasculitis c (proliferation a , intimal arteritis b , necrosis, sclerosis) Tubular atrophy, isometric vacuolization, isolated calcifications Tubulitis with RBC b and WBC b casts, some irregular vacuolization Minimal edema Interstitial edema c and hemorrhage b Mild focal infiltrates c Diffuse moderate to severe mononuclear infiltrates d Diffuse interstitial fibrosis, often striped form Glomerulitis (mononuclear cells) c Aspiration Cytology CyA deposits in tubular and endothelial cells Inflammatory infiltrate with mononuclear phagocytes, macrophages, lymphoblastoid cells, and activated T-cells Fine isometric vacuolization of tubular cells These strongly express HLA-DR antigens Urine Cytology Tubular cells with vacuolization and granularization Degenerative tubular cells, plasma cells, and lymphocyturia > 20% of sediment Manometry Intracapsular pressure < 40 mm Hg b Intracapsular pressure > 40 mm Hg b Ultrasonography Unchanged graft cross-sectional area Increase in graft cross-sectional area AP diameter ≥ Transverse diameter Magnetic Resonance Imagery Normal appearance Loss of distinct corticomedullary junction, swelling, image intensity of parachyma approaching that of psoas, loss of hilar fat Radionuclide Scan Normal or generally decreased perfusion Patchy arterial flow Decrease in tubular function Decrease in perfusion > decrease in tubular function ( 131 I-hippuran) > decrease in perfusion ( 99m Tc DTPA) Increased uptake of Indium 111 labeled platelets or Tc-99m in colloid Therapy Responds to decreased cyclosporine Responds to increased steroids…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The principal adverse reactions of Sandimmune therapy are renal dysfunction, tremor, hirsutism, hypertension, and gum hyperplasia. Hypertension Hypertension, which is usually mild to moderate, may occur in approximately 50% of patients following renal transplantation and in most cardiac transplant patients. Glomerular Capillary Thrombosis Glomerular capillary thrombosis has been found in patients treated with cyclosporine and may progress to graft failure.
The pathologic changes resemble those seen in the hemolytic-uremic syndrome and include thrombosis of the renal microvasculature, with platelet-fibrin thrombi occluding glomerular capillaries and afferent arterioles, microangiopathic hemolytic anemia, thrombocytopenia, and decreased renal function. Similar findings have been observed when other immunosuppressives have been employed post transplantation. Hypomagnesemia Hypomagnesemia has been reported in some, but not all, patients exhibiting convulsions while on cyclosporine therapy.
Although magnesium-depletion studies in normal subjects suggest that hypomagnesemia is associated with neurologic disorders, multiple factors, including hypertension, high-dose methylprednisolone, hypocholesterolemia, and nephrotoxicity associated with high plasma concentrations of cyclosporine appear to be related to the neurological manifestations of cyclosporine toxicity. Adverse Reactions in Clinical Studies The following reactions occurred in 3% or greater of 892 patients involved in clinical trials of kidney, heart, and liver transplants: Randomized Kidney Patients All Sandimmune-Treated Patients Sandimmune Azathioprine Kidney Heart Liver Body System/ (N = 227) (N = 228) (N = 705) (N = 112) (N = 75) Adverse Reactions % % % % % Genitourinary Renal Dysfunction 32 6 25 38 37 Cardiovascular Hypertension 26 18 13 53 27 Cramps 4 < 1 2 < 1 0 Skin Hirsutism 21 < 1 21 28 45 Acne 6 8 2 2 1 Central Nervous System Tremor 12 0 21 31 55 Convulsions 3 1 1 4 5 Headache 2 < 1 2 15 4 Gastrointestinal Gum Hyperplasia 4 0 9 5 16 Diarrhea 3 < 1 3 4 8 Nausea/Vomiting 2 < 1 4 10 4 Hepatotoxicity < 1 < 1 4 7 4 Abdominal Discomfort < 1 0 < 1 7 0 Autonomic Nervous System Paresthesia 3 0 1 2 1 Flushing < 1 0 4 0 4 Hematopoietic Leukopenia 2 19 < 1 6 0 Lymphoma < 1 0 1 6 1 Respiratory Sinusitis < 1 0 4 3 7 Miscellaneous Gynecomastia < 1 0 < 1 4 3 The following reactions occurred in 2% or less of patients: allergic reactions, anemia, anorexia, confusion, conjunctivitis, edema, fever, brittle fingernails, gastritis, hearing loss, hiccups, hyperglycemia, muscle pain, peptic ulcer, thrombocytopenia, tinnitus.
The following reactions occurred rarely: anxiety, chest pain, constipation, depression, hair breaking, hematuria, joint pain, lethargy, mouth sores, myocardial infarction, night sweats, pancreatitis, pruritus, swallowing difficulty, tingling, upper GI bleeding, visual disturbance, weakness, weight loss. Sandimmune was discontinued on a temporary basis and then restarted in 18 additional patients. Renal Transplant Patients in Whom Therapy Was Discontinued Randomized Patients All Sandimmune-Treated Patients Sandimmune Azathioprine (N = 227) (N = 228) (N = 705) Reason for Discontinuation % % % Renal Toxicity 5.7 0
5.4Infection 0 0.4
0.9Lack of Efficacy 2.6 0.9
1.4Acute Tubular Necrosis 2.6 0
1.0Lymphoma/Lymphoproliferative Disease 0.4 0
0.3 Hypertension 0 0
0.3Hematological Abnormalities 0 0.4 0 Other 0 0
0.7Patients receiving immunosuppressive therapies, including cyclosporine and cyclosporine-containing regimens, are at increased risk of infections (viral, bacterial, fungal, and parasitic). Both generalized and localized infections can occur. Preexisting infections may also be aggravated.
Fatal outcomes have been reported (see WARNINGS) . *Some patients also received ALG. Infectious Complications in the Randomized Renal Transplant Patients Sandimmune Treatment Standard Treatment* (N = 227) (N = 228) Complication % of Complications % of Complic…
🔄 Drug Interactions ▾
Drug Interactions A. Effect of Drugs and Other Agents on Cyclosporine Pharmacokinetics and/or Safety All of the individual drugs cited below are well substantiated to interact with cyclosporine. In addition, concomitant use of nonsteroidal anti-inflammatory drugs (NSAIDs) with cyclosporine, particularly in the setting of dehydration, may potentiate renal dysfunction.
Caution should be exercised when using other drugs which are known to impair renal function (see WARNINGS, Nephrotoxicity) . Drugs That May Potentiate Renal Dysfunction Antibiotics Antineoplastic Antifungals Anti-Inflammatory Drugs Gastrointestinal Agents Immunosuppressives Other Drugs ciprofloxacin melphalan amphotericin B azapropazon cimetidine tacrolimus fibric acid derivatives (e.g., bezafibrate, fenofibrate) gentamicin ketoconazole colchicine ranitidine methotrexate tobramycin diclofenac trimethoprim with sulfamethoxazole naproxen vancomycin sulindac During the concomitant use of a drug that may exhibit additive or synergistic renal impairment potential with cyclosporine, close monitoring of renal function (in particular serum creatinine) should be performed.
If a significant impairment of renal function occurs, reduction in the dosage of cyclosporine and/or coadministered drug or an alternative treatment should be considered. Cyclosporine is extensively metabolized by CYP 3A isoenzymes, in particular CYP3A4, and is a substrate of the multidrug efflux transporter P-glycoprotein. Various agents are known to either increase or decrease plasma or whole blood concentrations of cyclosporine usually by inhibition or induction of CYP3A4 or P-glycoprotein transporter or both.
Compounds that decrease cyclosporine absorption, such as orlistat, should be avoided. Appropriate Sandimmune dosage adjustment to achieve the desired cyclosporine concentrations is essential when drugs that significantly alter cyclosporine concentrations are used concomitantly (see DOSAGE AND ADMINISTRATION, Blood Concentration Monitoring) . 1.
Drugs That Increase Cyclosporine Concentrations Calcium Channel Blockers Antifungals Antibiotics Glucocorticoids Other Drugs diltiazem fluconazole azithromycin methylprednisolone allopurinol nicardipine itraconazole clarithromycin amiodarone verapamil ketoconazole erythromycin bromocriptine voriconazole quinupristin/ dalfopristin colchicine danazol imatinib metoclopramide nefazodone oral contraceptives HIV Protease inhibitors The HIV protease inhibitors (e.g., indinavir, nelfinavir, ritonavir, and saquinavir) are known to inhibit cytochrome P-450 3A and thus could potentially increase the concentrations of cyclosporine, however, no formal studies of the interaction are available.
Care should be exercised when these drugs are administered concomitantly. Grapefruit Juice Grapefruit and grapefruit juice affect metabolism, increasing blood concentrations of cyclosporine, thus should be avoided. 2.
Drugs/Dietary Supplements That Decrease Cyclosporine Concentrations Antibiotics Anticonvulsants Other Drugs / Dietary Supplements nafcillin carbamazepine bosentan St. John’s Wort rifampin oxcarbazepine octreotide phenobarbital orlistat phenytoin sulfinpyrazone terbinafine ticlopidine Bosentan Concomitant use of bosentan (250 to 1000 mg every 12 hours based on tolerability) and cyclosporine (300 mg every 12 hours for 2 days then dosing to achieve a C min of 200 to 250 ng/mL) for 7 days in healthy subjects resulted in decreases in the cyclosporine mean dose-normalized AUC, C max , and trough concentration of approximately 50%, 30% and 60%, respectively, compared to when cyclosporine was given alone (see also Effect of Cyclosporine on the Pharmacokinetics and/or Safety of Other Drugs or Agents) .
Concomitant use of cyclosporine with bosentan should be avoided. Boceprevir Concomitant use of boceprevir (800 mg three times daily for 7 days) and cyclosporine (100 mg single dose) in healthy subjects resulted in increases in the mean AUC and C max of cyclosporine approximate…
🤰 Pregnancy ▾
Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to cyclosporine, including Sandimmune, during pregnancy. Encourage women who are taking Sandimmune during pregnancy to enroll in the Transplant Pregnancy Registry International (TPRI) by calling 1-877-955-8677 or visiting https://www.transplantpregnancyregistry.org . Risk Summary Available data from published literature, including the Transplant Pregnancy Registry International, observational cohort studies, case-controlled studies, meta-analysis, case series, and case reports, over decades of use with cyclosporine in pregnancy have not identified a drug associated risk of major birth defects, or miscarriage.
Adverse maternal or fetal outcomes, including hypertension, preeclampsia, preterm birth, and low birth weight are increased in patients treated with cyclosporine. However, patients receiving cyclosporine during pregnancy have underlying medical conditions and may be treated with concomitant medications that limit the interpretability of these findings (see Data) . Embryo-fetal developmental (EFD) studies in rats and rabbits with cyclosporine have shown embryo-fetal toxicity at dose levels below the MRHD based on BSA.
The alcohol content of Sandimmune should be considered when given to pregnant women (see WARNINGS, Special Excipients) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data Available data from the National Transplantation Pregnancy Registry (NTPR) including 622 pregnancies in renal, liver, and heart transplant recipients exposed to cyclosporine during pregnancy found that the overall rate of major birth defects, live birth rates, and miscarriage rates were comparable to the general population.
Maternal and fetal adverse outcomes, including the rate of hypertension, preeclampsia, premature births, and low birth weight infants appear to be increased in transplant recipients treated with cyclosporine compared to the general population. However, these patients have underlying medical conditions that confound the above findings. Animal Data Animal studies have shown reproductive toxicity in rats and rabbits.
Three EFD studies (two oral and one intravenous) are available in rats. In two EFD studies, pregnant rats were orally administered with cyclosporine either at doses of 10, 17, 30, 100 and 300 mg/kg/day or 4, 10 and 25 mg/kg/day from gestation day (GD) 6 to 15 or from GD 7 to 17, respectively. Maternal toxicity characterized by mortality, clinical signs of toxicity and impaired body weight gain were observed at 30 mg/kg/day and above.
Cyclosporine was embryo- and fetotoxic as indicated by increased embryonic mortality and reduced fetal weight together with skeletal retardations in rats at 25 mg/kg/day and above. In addition, ventricular septal defect was observed at 25 mg/kg/day in fetuses. In the first study, the oral no observed effect level (NOEL) for both dams and fetuses was 17 mg/kg/day (0.2 times the MRHD based on BSA).
In the other oral study, the NOEL for dams and fetuses were 10 and 4 mg/kg/day (0.13 and 0.05 times the MRHD based on BSA), respectively. In the IV EFD study, rats were administered with 3, 6 and 12 mg/kg/day of cyclosporine from GD 7 to 17. An increase in post implantation loss was observed at 12 mg/kg/day; ventricular septal defect was observed at ≥ 6 mg/kg/day in fetuses.
The IV NOEL for dams and fetus were 6 and 3 mg/kg/day (below the MRHD based on BSA), respectively after IV administration. In rabbits, cyclosporine was orally administered at dose levels of 10, 30, 100 or 300 mg/kg/day from GD 6 to 18. At 100 mg/kg/day and…
🧒 Pediatric Use ▾
Pediatric Use Although no adequate and well-controlled studies have been conducted in children, patients as young as 6 months of age have received cyclosporine with no unusual adverse effects.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of Sandimmune did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently from younger adult patients. Other reported clinical experience has not identified differences in responses between patients aged 65 and over and younger adult patients. In general, dosage selection for patients aged 65 and over should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE There is a minimal experience with cyclosporine overdosage. Because of the slow absorption of cyclosporine, forced emesis and gastric lavage would be of value up to 2 hours after administration. Transient hepatotoxicity and nephrotoxicity may occur, which should resolve following drug withdrawal.
Oral doses of cyclosporine up to 10 g (about 150 mg/kg) have been associated with vomiting, drowsiness, headache, tachycardia, and in a few patients, moderately severe, reversible impairment of renal function. However, serious symptoms of cyclosporine intoxication have been reported following accidental parenteral overdosage with cyclosporine in premature neonates. The oral LD 50 is 2329 mg/kg in mice, 1480 mg/kg in rats, and > 1000 mg/kg in rabbits.
The intravenous LD 50 is 148 mg/kg in mice, 104 mg/kg in rats, and 46 mg/kg in rabbits. General supportive measures and symptomatic treatment should be followed in all cases of cyclosporine overdosage. Cyclosporine is not dialyzable to any great extent, nor is it cleared well by charcoal hemoperfusion.
If a cyclosporine overdose occurs, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Cyclosporine is a potent immunosuppressive agent, which in animals prolongs survival of allogeneic transplants involving skin, heart, kidney, pancreas, bone marrow, small intestine, and lung. Cyclosporine has been demonstrated to suppress some humoral immunity and to a greater extent, cell-mediated reactions, such as allograft rejection, delayed hypersensitivity, experimental allergic encephalomyelitis, Freund’s adjuvant arthritis, and graft vs. host disease in many animal species for a variety of organs.
Successful kidney, liver, and heart allogeneic transplants have been performed in man using cyclosporine. The exact mechanism of action of cyclosporine is not known. Experimental evidence suggests that the effectiveness of cyclosporine is due to specific and reversible inhibition of immunocompetent lymphocytes in the G 0 - or G 1 -phase of the cell cycle.
T-lymphocytes are preferentially inhibited. The T-helper cell is the main target, although the T-suppressor cell may also be suppressed. Cyclosporine also inhibits lymphokine production and release, including interleukin-2 or T-cell growth factor (TCGF).
No functional effects on phagocytic (changes in enzyme secretions not altered, chemotactic migration of granulocytes, macrophage migration, carbon clearance in vivo ) or tumor cells (growth rate, metastasis) can be detected in animals. Cyclosporine does not cause bone marrow suppression in animal models or man. Pharmacokinetics The absorption of cyclosporine from the gastrointestinal tract is incomplete and variable.
Peak concentrations (C max ) in blood and plasma are achieved at about 3.5 hours. C max and area under the plasma or blood concentration/time curve (AUC) increase with the administered dosage; for blood, the relationship is curvilinear (parabolic) between 0 and 1400 mg. As determined by a specific assay, C max is approximately 1.0 ng/mL/mg of dose for plasma and 2.7 to 1.4 ng/mL/mg of dose for blood (for low to high doses).
Compared to an intravenous infusion, the absolute bioavailability of soft gelatin capsules is approximately 30%. Cyclosporine is distributed largely outside the blood volume. In blood, the distribution is concentration dependent.
Approximately 33% to 47% is in plasma, 4% to 9% in lymphocytes, 5% to 12% in granulocytes, and 41% to 58% in erythrocytes. At high concentrations, the uptake by leukocytes and erythrocytes becomes saturated. In plasma, approximately 90% is bound to proteins, primarily lipoproteins.
The disposition of cyclosporine from blood is biphasic with a terminal half-life of approximately 19 hours (range, 10 to 27 hours). Elimination is primarily biliary with only 6% of the dose excreted in the urine. Cyclosporine is extensively metabolized but there is no major metabolic pathway.
Only 0.1% of the dose is excreted in the urine as unchanged drug. Of 15 metabolites characterized in human urine, 9 have been assigned structures. The major pathways consist of hydroxylation of the Cγ-carbon of 2 of the leucine residues, Cη-carbon hydroxylation, and cyclic ether formation (with oxidation of the double bond) in the side chain of the amino acid 3-hydroxyl- N ,4-dimethyl-L-2-amino-6-octenoic acid and N -demethylation of N -methyl leucine residues.
Hydrolysis of the cyclic peptide chain or conjugation of the aforementioned metabolites do not appear to be important biotransformation pathways. Pharmacokinetics in Specific Populations Pharmacokinetics in Patients with Renal Impairment In a study performed in 4 subjects with end-stage renal disease (creatinine clearance < 5 mL/min), an intravenous infusion of 3.5 mg/kg of cyclosporine over 4 hours administered at the end of a hemodialysis session resulted in a mean volume of distribution (Vdss) of
3.49L/kg and systemic clearance (CL) of 0.369 L/hr/kg. This systemic CL (0.369 L/hr/kg) was approximately two thirds of the mean systemic CL (0.56 L/hr/kg) of cyclosporine in historical control subjects wit…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Sandimmune ® (cyclosporine capsules) USP 25 mg: Oval, pink with “ 78/240”. Unit dose packages of 30 capsules, 3 blister cards of 10 capsules………………………………………………………….NDC 0078-0240-15 100 mg: Oblong, dusty rose with “ 78/241”. Unit dose packages of 30 capsules, 3 blister cards of 10 capsules………………………………………………………….NDC 0078-0241-15 Store and Dispense: Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature] .
An odor may be detected upon opening the unit dose container, which will dissipate shortly thereafter. This odor does not affect the quality of the product. Sandimmune ® (cyclosporine injection) USP For intravenous infusion only.
Supplied as a 5 mL sterile ampul containing 50 mg of cyclosporine per mL, in boxes of 10 ampuls…………………………………………………………………..NDC 0078-0109-01 Store and Dispense: At temperatures below 30°C (86°F). Protect from light. *Cremophor ® is the registered trademark of BASF Aktiengesellschaft. Distributed by: Novartis Pharmaceuticals Corporation East Hanover, New Jersey 07936 © Novartis Revised: March 2026 T2026-06 Sandoz logo
📋 Description ▾
DESCRIPTION Cyclosporine, the active principle in Sandimmune (cyclosporine capsules) and in Sandimmune (cyclosporine injection) is a cyclic polypeptide immunosuppressant agent consisting of 11 amino acids. It is produced as a metabolite by the fungus species Beauveria nivea . Chemically, cyclosporine is designated as [ R -[ R *, R *-( E )]]-cyclic(L-alanyl-D-alanyl- N -methyl-L-leucyl- N -methyl-L-leucyl- N -methyl-L-valyl-3-hydroxy- N ,4-dimethyl-L-2-amino-6-octenoyl-L-α-amino-butyryl- N -methylglycyl- N -methyl-L-leucyl-L-valyl- N -methyl-L-leucyl).
The chemical structure of cyclosporine (also known as cyclosporin A) is Sandimmune ® (cyclosporine capsules) USP are available in 25 mg and 100 mg strengths. Each 25 mg capsule contains: cyclosporine, USP…………………………………………………………………………………………25 mg alcohol, USP dehydrated………………………………………………………………max 12.7% by volume Each 100 mg capsule contains: cyclosporine, USP……………………………………………………………………………………….100 mg alcohol, USP dehydrated………………………………………………………………max 12.7% by volume Inactive ingredients include corn oil, gelatin, iron oxide red, linoleoyl macrogolglycerides, sorbitol, and titanium dioxide.
May also contain glycerol. 100 mg capsules may contain iron oxide yellow. Sandimmune ® (cyclosporine injection) USP is available in a 5 mL sterile ampul for intravenous administration.
Each mL contains: cyclosporine, USP…………………………………………………………………………………………50 mg *Cremophor ® EL (polyoxyethylated castor oil)………………………………………………………..650 mg alcohol, Ph. Helv. ……………………………………………………………………………32.9% by volume nitrogen………………………………………………………………………………………………………….qs The injection must be diluted further with 0.9% Sodium Chloride Injection or 5% Dextrose Injection using appropriate aseptic technique before use. chemical structure of cyclosporine
💬 Information for Patients ▾
Information for Patients Patients should be advised that a switch of their current cyclosporine formulation to another cyclosporine formulation should be made cautiously and only under health care provider supervision because it may result in the need for a change in dosage (see PRECAUTIONS and DOSAGE AND ADMINISTRATION). Patients should be informed of the necessity of repeated laboratory tests while they are receiving Sandimmune. They should be given careful dosage instructions, advised of the potential risks during pregnancy, and informed of the increased risk of neoplasia.
Cyclosporine may impact the ability to drive and use machines. Patients should be advised to exercise care when driving or using machines if they experience neurological disturbances, including confusion, somnolence, or dizziness and discuss with their healthcare provider (see WARNINGS and ADVERSE REACTIONS) .