
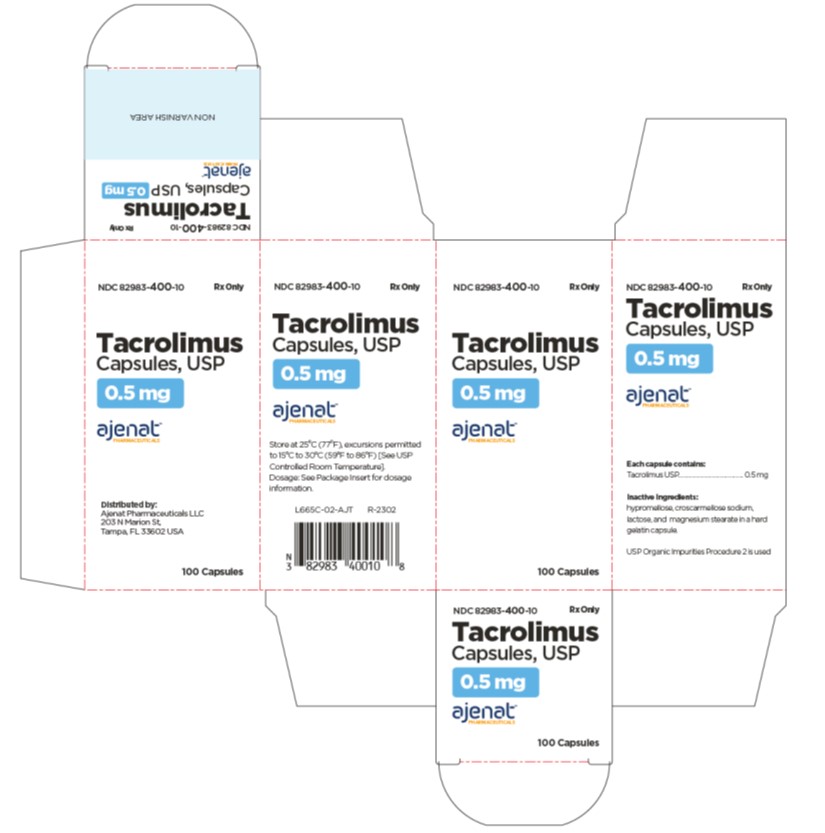
Tacrolimus .5 mg Capsule, 100-count
Other active recalls for Tacrolimus (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcineurin Inhibitor Immunosuppressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tacrolimus (Astagraf XL, Envarsus XR, Prograf) is used along with other medications to prevent rejection (attack of a transplanted organ by the immune system of a person receiving the organ) in people who have received a kidney transplant. Tacrolimus (Prograf) is also used along with other medications to prevent rejection in people who have received a liver, lung, or heart transplant. Tacrolimus is in a class of medications called immunosupressants. It works by decreasing the activity of the immune system to prevent it from attacking the transplanted organ.
Read the full MedlinePlus article ↗- That's a great question, and it's one of the most important things to understand. Your body's immune system doesn't just stop trying to attack the new organ once you leave the hosp...
- Why do I have to take tacrolimus even when I feel completely fine?
- It actually does matter — but the key is being consistent, not choosing one over the other. Food can change how much tacrolimus your body absorbs, so if you always take it the same...
- Does it matter if I take tacrolimus with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tacrolimus — tap one for details:
Tacrolimus may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII Y6O7T4G8P9
Hydrated silica is a fine powder form of silicon dioxide with absorbed water. It works as an anti-caking agent and absorbent in medicines, helping powders stay free-flowing and preventing clumping.
-
UNII B1QE5P712K
Hypromellose 2208 is a plant-derived thickening agent that dissolves in water. It's used as a binder to help hold tablet ingredients together and as a coating on pills to control how quickly the medicine releases in your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3779 | $37.79 / 100 capsules |
| Medicare Part B allowsASP · J7507 | $0.200 / J7507 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tacrolimus .5 mg 00378-2045-01 | Mylan | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 00781-2102-01 | Sandoz | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 00904-6623-61 | Major | 100 capsules | $0.126 | AB | Availability likely | — |
| tacrolimus .5 mg 16714-0098-01 | NORTHSTAR | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 51079-0817-20 | MylanInstitutional | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 55111-0525-01 | Dr. | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 59746-0798-01 | Jubilant | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 67877-0278-01 | Ascend | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 68084-0449-01 | American | 100 capsules | $0.126 | AB | Availability likely | — |
| tacrolimus .5 mg 68462-0685-01 | Glenmark | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 70377-0014-11 | Biocon | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 82009-0164-01 | Quallent | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 85972-0101-01 | Stellon | 100 capsules | $0.126 | AB | Availability likely | — |
| Tacrolimus .5 mg 16729-0041-01 | Accord | 100 capsules | $0.147 | BX | Availability likely | — |
| Prograf .5 mg 00469-0607-73 | Astellas | 100 capsules | $3.662 | AB | Availability likely | — |
| Tacrolimus .5 mg 43817-0421-01 | Panacea | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 48433-0092-20 | Safecor | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 54288-0134-01 | BPI | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 60429-0377-01 | Golden | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 63629-8725-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 63629-9581-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 64380-0720-01 | Strides | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 65897-0009-01 | Hangzhou | 100 capsules | — | — | FDA listed | — |
| Tacrolimus .5 mg 68254-5004-01 | CONCORD | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus .5 mg 71335-2189-01 | Bryant | 60 capsules | — | BX | FDA listed | — |
| Tacrolimus .5 mgthis 82983-0400-10 | Ajenat | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 82983-0400-10 You're viewing this | 100 CAPSULE in 1 BOTTLE (82983-400-10) | 2023-01-31 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNINGS: MALIGNANCIES AND SERIOUS INFECTIONS • Increased risk of development of lymphoma and other malignancies, particularly of the skin, due to immunosuppression [see Warnings and Precautions ( 5.2 )]. • Increased susceptibility to bacterial, viral, fungal, and protozoal infections, including opportunistic infections [ see Warnings and Precautions ( 5.3 , 5.4 , 5.5 )]. • Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe tacrolimus. Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources.
The physician responsible for maintenance therapy should have complete information requisite for the follow-up of the patient [ see Warnings and Precautions ( 5.1 )]. BOXED WARNING: MALIGNANCIES AND SERIOUS INFECTIONS See full prescribing information for complete boxed warning •Increased risk of development of lymphoma and other malignancies, particularly of the skin, due to immunosuppression ( 5.2 )•Increased susceptibility to bacterial, viral, fungal, and protozoal infections, including opportunistic infections ( 5.3 , 5.4 , 5.5 )•Only Physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe Tacrolimus ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tacrolimus is a calcineurin-inhibitor immunosuppressant indicated for • Prophylaxis of organ rejection in patients receiving allogeneic liver, kidney or heart transplants ( 1.1 , 1.2 , 1.3 ) • Use concomitantly with adrenal corticosteroids; in kidney and heart transplant, use in conjunction with azathioprine or mycophenolate mofetil (MMF) ( 1.1 , 1.2 , 1.3 ) • Limitations of Use ( 1.4 ): • Do not use simultaneously with cyclosporine • Intravenous use reserved for patients who can not tolerate capsules orally • Use with sirolimus is not recommended in liver and heart transplant; use with sirolimus in kidney transplant has not been established
1.1Prophylaxis of Organ Rejection in Kidney Transplant Tacrolimus Capsules is indicated for the prophylaxis of organ rejection in patients receiving allogeneic kidney transplants. It is recommended that tacrolimus be used concomitantly with azathioprine or mycophenolate mofetil (MMF) and adrenal corticosteroids [ see Clinical Studies ( 14.1 )] . Therapeutic drug monitoring is recommended for all patients receiving tacrolimus [ see Dosage and Administration ( 2.6 )].
1.2Prophylaxis of Organ Rejection in Liver Transplant Tacrolimus Capsules is indicated for the prophylaxis of organ rejection in patients receiving allogeneic liver transplants. It is recommended that tacrolimus be used concomitantly with adrenal corticosteroids [ see Clinical Studies ( 14.2 )]. Therapeutic drug monitoring is recommended for all patients receiving tacrolimus[ see Dosage and Administration ( 2.6 )].
1.3Prophylaxis of Organ Rejection in Heart Transplant Tacrolimus Capsules is indicated for the prophylaxis of organ rejection in patients receiving allogeneic heart transplants. It is recommended that tacrolimus capsules be used concomitantly with azathioprine or mycophenolate mofetil (MMF) and adrenal corticosteroids [ see Clinical Studies ( 14.3 )]. Therapeutic drug monitoring is recommended for all patients receiving tacrolimus capsules [ see Dosage and Administration ( 2.6 )].
1.4Limitations of Use Tacrolimus Capsules should not be used simultaneously with cyclosporine [ see Dosage and Administration ( 2.5 )]. Use with sirolimus is not recommended in liver and heart transplant. The safety and efficacy of tacrolimus with sirolimus has not been established in kidney transplant [ see Warnings and Precautions ( 5.12 )]. Intravenous use reserved for patients who cannot tolerate capsules orally.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Summary of Initial Oral Dosage Recommendation and Observed Whole Blood Trough Concentrations ( 2.1 , 2.2 ) Patient Population Recommended Tacrolimus Initial Oral Dosage (two divided doses every 12 hours) Observed Whole Blood Trough Concentrations Adult Kidney transplant patients In combination with azathioprine 0.2 mg/kg/day month 1-3: 7-20 ng/mL month 4-12: 5-15 ng/mL In combination with MMF/IL-2 receptor antagonist 0.1 mg/kg/day month 1-12: 4-11 ng/mL Adult Liver transplant 0.10-0.15 mg/kg/day month 1-12: 5-20 ng/mL Pediatric Liver transplant 0.15-0.20 mg/kg/day month 1-12: 5-20 ng/mL Adult Heart transplant 0.075 mg/kg/day month 1-3: 10-20 ng/mL month ≥4: 5-15 ng/mL • Careful and frequent monitoring of tacrolimus trough concentrations is recommended; Black patients may require higher doses in order to achieve comparable trough concentrations ( 2.1 ) • Hepatic/Renal impaired patients should receive doses at the lowest value of the recommended initial oral dosing range ( 2.3 , 2.4 ) • Administer capsules consistently with or without food; do not drink grapefruit juice ( 2.5 , 7.2 )
2.1Dosage in Adult Kidney, Liver or Heart Transplant Patients The initial oral dosage recommendations for adult patients with kidney, liver or heart transplants along with recommendations for whole blood trough concentrations are shown in Table 1. The initial dose of tacrolimus should be administered no sooner than 6 hours after transplantation in the liver and heart transplant patients. In kidney transplant patients, the initial dose of tacrolimus may be administered within 24 hours of transplantation, but should be delayed until renal function has recovered.
For blood concentration monitoring details [ see Dosage and Administration ( 2.6 )] Table 1. Summary of Initial Oral Dosage Recommendations and Observed Whole Blood Trough Concentrations in Adults Patient Population Recommended Tacrolimus Initial Oral Dosage Note: daily doses should be administered as two divided doses, every 12 hours Observed Tacrolimus Whole Blood Trough Concentrations Adult kidney transplant patients month 1-3: 7-20 ng/mL In combination with azathioprine 0.2 mg/kg/day month 4-12: 5-15 ng/mL In combination with MMF/IL-2 receptor antagonist a 0.1 mg/kg/day month 1-12: 4-11 ng/mL Adult liver transplant patients 0.10-0.15 mg/kg/day month 1-12: 5-20 ng/mL Adult heart transplant patients 0.075 mg/kg/day month 1-3: 10-20 ng/mL month ≥4: 5-15 ng/mL a) In a second smaller trial, the initial dose of tacrolimus was 0.15-0.2 mg/kg/day and observed tacrolimus concentrations were 6-16 ng/mL during month 1-3 and 5-12 ng/mL during month 4-12 [ see Clinical Studies ( 14.1 )].
Dosing should be titrated based on clinical assessments of rejection and tolerability. Lower tacrolimus dosages than the recommended initial dosage may be sufficient as maintenance therapy. Adjunct therapy with adrenal corticosteroids is recommended early post-transplant.
The data in kidney transplant patients indicate that the Black patients required a higher dose to attain comparable trough concentrations compared to Caucasian patients Table 2. Table 1. Comparative Dose and Trough Concentrations Based on Race Time After Transplant Caucasian n=114 Black n=56 Dose (mg/kg) Trough Concentrations (ng/mL) Dose (mg/kg) Trough Concentrations (ng/mL) Day 7 0.18 12.0 0.23
10.9Month 1 0.17 12.8 0.26
12.9Month 6 0.14 11.8 0.24
11.5Month 12 0.13 10.1 0.19
11.0Initial Dose – Injection Tacrolimus injection should be used only as a continuous IV infusion and when the patient cannot tolerate oral administration of tacrolimus capsules. Tacrolimus injection should be discontinued as soon as the patient can tolerate oral administration of tacrolimus, usually within 2-3 days. In a patient receiving an IV infusion, the first dose of oral therapy should be given 8-12 hours after discontinuing the IV infusion.
The observed trough concentrations described above pertain to oral administration of tacrolimus onl…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS •Oblong, hard capsule for oral administration contains anhydrous tacrolimus USP as follows: o Tacrolimus Capsules USP, 0.5 mg are white to off white powder filled in hard gelatin capsule of size ‘4’, yellow opaque cap and yellow opaque body imprinted “ BP 665” twice on the body and imprinted “0.5 mg” twice on the cap with red ink.. o Tacrolimus Capsules USP, 1 mg are white to off white powder filled in hard gelatin capsule of size ‘4’, white opaque cap and white opaque body imprinted “ BP 666” twice on the body and imprinted “1 mg” twice on the cap with red ink. o Tacrolimus Capsules USP, 5 mg are white to off white powder filled in hard gelatin capsule of size ‘4’, salmon opaque cap and salmon opaque body imprinted “ BP 667” on the body and imprinted “5 mg” twice on the cap with white ink. • Capsules: 0.5 mg, 1 mg and 5 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Tacrolimus capsules are contraindicated in patients with a hypersensitivity to tacrolimus. Tacrolimus injection is contraindicated in patients with a hypersensitivity to HCO-60 (polyoxyl 60 hydrogenated castor oil). Hypersensitivity symptoms reported include dyspnea, rash, pruritus, and acute respiratory distress syndrome [see Adverse Reactions (6)]. Hypersensitivity to tacrolimus or HCO-60 (polyoxyl 60 hydrogenated castor oil)( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS •Lymphoma and Other Malignancies: Risk of lymphomas, including post transplant lymphoproliferative disorder (PLTD); appears related to intensity and duration of use. Avoid prolonged exposure to UV light and sunlight ( 5.2 ) •Serious infections: Increased risk of bacterial, viral, fungal and protozoal infections, including opportunistic infections: combination immunosuppression should be used with caution ( 5.3 ) •Polyoma Virus Infections: Serious, sometimes fatal outcomes, including polyoma virus-associated nephropathy (PVAN), mostly due to BK virus, and JC virus-associated progressive multifocal leukoencephalopathy (PML); consider reducing immunosuppression ( 5.4 ) •Cytomegalovirus (CMV) Infections: Increased risk of CMV viremia and disease; consider reducing immunosuppression ( 5.5 ) •New Onset Diabetes After Transplant: Monitor blood glucose ( 5.6 ) •Nephrotoxicity: Acute and/or chronic; reduce the dose; use caution with other nephrotoxic drugs ( 5.7 ) •Neurotoxicity: Risk of Posterior Reversible Encephalopathy Syndrome, monitor for neurologic abnormalities; reduce or discontinue tacrolimus and other immunosuppressants ( 5.8 ) •Hyperkalemia: Monitor serum potassium levels.
Careful consideration should be given prior to use of other agents also associated with hyperkalemia ( 5.9 ) •Hypertension: May require antihypertensive therapy. Monitor relevant drug-drug interactions ( 5.10 ) •Anaphylactic Reactions with IV formulation: Observe patients receiving Tacrolimus injection for signs and symptoms of anaphylaxis ( 5.11 ) •Use with Sirolimus: Not recommended in liver and heart transplant due to increased risk of serious adverse reactions ( 5.12 ) •Myocardial Hypertrophy: Consider dosage reduction or discontinuation ( 5.15 ) •Immunizations: Use of live vaccines should be avoided ( 5.16 ) •Pure Red Cell Aplasia: Discontinuation should be considered ( 5.17 )
5.1Management of Immunosuppression Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should use tacrolimus. Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physicians responsible for maintenance therapy should have complete information requisite for the follow up of the patient [ see Boxed Warning ].
5.2Lymphoma and Other Malignancies Patients receiving immunosuppressants, including tacrolimus, are at increased risk of developing lymphomas and other malignancies, particularly of the skin [ see Boxed Warning ]. The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. As usual for patients with increased risk for skin cancer, exposure to sunlight and UV light should be limited by wearing protective clothing and using a sunscreen with a high protection factor.
Post transplant lymphoproliferative disorder (PTLD) has been reported in immunosuppressed organ transplant recipients. The majority of PTLD events appear related to Epstein Barr Virus (EBV) infection. The risk of PTLD appears greatest in those individuals who are EBV seronegative, a population which includes many young children.
5.3Serious Infections Patients receiving immunosuppressants, including tacrolimus, are at increased risk of developing bacterial, viral, fungal, and protozoal infections, including opportunistic infections [ see Boxed Warning and Warnings and Precautions ( 5.4 , 5.5 )]. These infections may lead to serious, including fatal, outcomes. Because of the danger of oversuppression of the immune system which can increase susceptibility to infection, combination immunosuppressant therapy should be used with caution.
5.4Polyoma Virus Infections Patients receiving immunosuppressants, including Tacrolimus, are at increased risk for opportunistic infections, including polyoma virus infections. Polyoma virus infections in transplant patients may have serious, and someti…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious and otherwise important adverse drug reactions are discussed in greater detail in other sections of labeling: • Lymphoma and Other Malignancies [ see Boxed Warning, Warnings and Precautions ( 5.2 )] • Serious Infections [ see Boxed Warning, Warnings and Precautions ( 5.3 )] • Polyoma Virus Infections [ see Boxed Warning, Warnings and Precautions ( 5.4 )] • CMV Infections [ see Boxed Warning, Warnings and Precautions ( 5.5 )] • New Onset Diabetes After Transplant [ see Warnings and Precautions ( 5.6 )] • Nephrotoxicity [ see Warnings and Precautions ( 5.7 )] • Neurotoxicity [ see Warnings and Precautions ( 5.8 )] • Hyperkalemia [ see Warnings and Precautions ( 5.9 )] • Hypertension [ see Warnings and Precautions ( 5.10 )] • Anaphylaxis with Tacrolimus Injection [ see Warnings and Precautions ( 5.11 )] • Myocardial Hypertrophy [ see Warnings and Precautions ( 5.15 )] • Pure Red Cell Aplasia [ see Warnings and Precautions ( 5.17 )] • Gastrointestinal Perforation [ see Warnings and Precautions ( 5.18 )] •Kidney Transplant: The most common adverse reactions ( ≥ 30%) were infection, tremor, hypertension, abnormal renal function, constipation, diarrhea, headache, abdominal pain, insomnia, nausea, hypomagnesemia, urinary tract infection, hypophosphatemia, peripheral edema, asthenia, pain, hyperlipidemia, hyperkalemia, and anemia ( 6.1 ) •Liver Transplant: The most common adverse reactions (≥ 40%) were tremor, headache, diarrhea, hypertension, nausea, abnormal renal function, abdominal pain, insomnia, paresthesia, anemia, pain, fever, asthenia, hyperkalemia, hypomagnesemia, and hyperglycemia ( 6.1 ) •Heart Transplant: The most common adverse reactions (≥ 15%) were abnormal renal function, hypertension, diabetes mellitus, CMV infection, tremor, hyperglycemia, leukopenia, infection, anemia, bronchitis, pericardial effusion, urinary tract infection and hyperlipemia ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Ajenat Pharmaceuticals LLC at 1-727-234-8872 or FDA at 1-800-FDA-1088 www.fda.gov/medwatch
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In addition, the clinical trials were not designed to establish comparative differences across study arms with regards to the adverse reactions discussed below. Kidney Transplant The incidence of adverse reactions was determined in three randomized kidney transplant trials.
One of the trials used azathioprine (AZA) and corticosteroids and two of the trials used mycophenolate mofetil (MMF) and corticosteroids concomitantly for maintenance immunosuppression. Tacrolimus-based immunosuppression in conjunction with azathioprine and corticosteroids following kidney transplantation was assessed in trial where 205 patients received Tacrolimus based immunosuppression and 207 patients received cyclosporine based immunosuppression. The trial population had a mean age of 43 years (mean±sd was 43±13 years on Tacrolimus and 44±12 years on cyclosporine arm), the distribution was 61% male, and the composition was White (58%), Black (25%), Hispanic (12%) and Other (5%).
The 12 month post-transplant information from this trial is presented below. The most common adverse reactions ( ≥30%) observed in Tacrolimus-treated kidney transplant patients are: infection, tremor, hypertension, abnormal renal function, constipation, diarrhea, headache, abdominal pain, insomnia, nausea, hypomagnesemia, urinary tract infection, hypophosphatemia, peripheral edema, asthenia, pain, hyperlipidemia, hyperkalemia and anemia. Adverse reactions that occurred in ≥15% of kidney transplant patients treated with Tacrolimus in conjunction with azathioprine are presented below: Table 3.
Kidney Transplantation: Adverse Reactions Occurring in ≥15% of…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Since tacrolimus is metabolized mainly by CYP3A enzymes, drugs or substances known to inhibit these enzymes may increase tacrolimus whole blood concentrations. Drugs known to induce CYP3A enzymes may decrease tacrolimus whole blood concentrations [ see Warnings and Precautions ( 5.13 )] and Clinical Pharmacology ( 12.3 )].Dose adjustments may be needed along with frequent monitoring of tacrolimus whole blood trough concentrations when tacrolimus is administered with CYP3A inhibitors or inducers. In addition, patients should be monitored for adverse reactions including changes in renal function and QT prolongation [ see Warnings and Precautions ( 5.7 ) and ( 5.14 )] • Mycophenolic Acid Products: Can increase MPA exposure after crossover from cyclosporine to tacrolimus; monitor for MPA-related adverse reactions and adjust MMF or MPA-dose as needed ( 7.1 ) • Nelfinavir and Grapefruit Juice: Increased tacrolimus concentrations via CYP3A inhibition; avoid concomitant use ( 7.2 , 7.3 ) • CYP3A Inhibitors: Increased tacrolimus concentrations; monitor concentrations and adjust tacrolimus dose as needed with concomitant use ( 5.13 , 7.3 , 7.4 , 7.5 , 7.6 ) • CYP3A4 Inducers: Decreased tacrolimus concentrations; monitor concentrations and adjust tacrolimus dose as needed with concomitant use ( 5.13 , 7.7 , 7.8 , 7.9 )
7.1Mycophenolic Acid Products With a given dose of mycophenolic acid (MPA) products, exposure to MPA is higher with tacrolimus co-administration than with cyclosporine co-administration because cyclosporine interrupts the enterohepatic recirculation of MPA while tacrolimus does not. Clinicians should be aware that there is also a potential for increased MPA exposure after crossover from cyclosporine to tacrolimus in patients concomitantly receiving MPA-containing products.
7.2Grapefruit Juice Grapefruit juice inhibits CYP3A-enzymes resulting in increased tacrolimus whole blood trough concentrations, and patients should avoid eating grapefruit or drinking grapefruit juice with tacrolimus [ see Dosage and Administration ( 2.5 )].
7.3Protease Inhibitors Most protease inhibitors inhibit CYP3A enzymes and may increase tacrolimus whole blood concentrations. It is recommended to avoid concomitant use of tacrolimus with nelfinavir unless the benefits outweigh the risks [ see Clinical Pharmacology ( 12.3 )]. Whole blood concentrations of tacrolimus are markedly increased when co-administered with telaprevir or with boceprevir [ see Clinical Pharmacology ( 12.3 )].
Monitoring of tacrolimus whole blood concentrations and tacrolimus associated adverse reactions, and appropriate adjustments in the dosing regimen of tacrolimus are recommended when tacrolimus and protease inhibitors (e.g., ritonavir, telaprevir, boceprevir) are used concomitantly.
7.4Antifungal Agents Frequent monitoring of whole blood concentrations and appropriate dosage adjustments of tacrolimus are recommended when concomitant use of the following antifungal drugs with tacrolimus is initiated or discontinued [ see Clinical Pharmacology ( 12.3 )]. Azoles: Voriconazole, posaconazole, itraconazole, ketoconazole, fluconazole and clotrimazole inhibit CYP3A metabolism of tacrolimus and increase tacrolimus whole blood concentrations. When initiating therapy with voriconazole or posaconazole in patients already receiving tacrolimus, it is recommended that the tacrolimus dose be initially reduced to one-third of the original dose and the subsequent tacrolimus doses be adjusted based on the tacrolimus whole blood concentrations.
Caspofungin is an inducer of CYP3A and decreases whole blood concentrations of tacrolimus.
7.5Calcium Channel Blockers Verapamil, diltiazem, nifedipine, and nicardipine inhibit CYP3A metabolism of tacrolimus and may increase tacrolimus whole blood concentrations. Monitoring of whole blood concentrations and appropriate dosage adjustments of tacrolimus are recommended when these calcium channel blocking drugs and tacrolimus are…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: Based on animal data may cause fetal harm. Use only if the potential benefit justifies the risk ( 8.1 ) • Nursing Mothers: Discontinue nursing taking into consideration importance of drug to mother ( 8.3 ) • Hepatic/Renal impaired patients: Administer at the lower end of the recommended starting dose. Monitor renal function in patients with impaired renal function ( 2.3 , 2.4 , 8.6 , 8.7 )
8.1Pregnancy Pregnancy Category C - There are no adequate and well-controlled studies in pregnant women. Tacrolimus is transferred across the placenta. The use of tacrolimus during pregnancy in humans has been associated with neonatal hyperkalemia and renal dysfunction.
Tacrolimus given orally to pregnant rabbits at 0.5 to 4.3 times the clinical dose and pregnant rats at 0.8 to 6.9 times the clinical dose was associated with an increased incidence of fetal death in utero, fetal malformations (cardiovascular, skeletal, omphalocele, and gallbladder agenesis) and maternal toxicity. Tacrolimus should be used during pregnancy only if the potential benefit to the mother justifies the potential risk to the fetus. In pregnant rabbits, tacrolimus at oral doses of 0.32 and 1.0 mg/kg, 0.5 to 4.3 times the clinical dose range (0.075 – 0.2 mg/kg) based on body surface area, was associated with maternal toxicity as well as an increased incidence of abortions.
At the 1 mg/kg dose, fetal rabbits showed an increased incidence of malformations (ventricular hypoplasia, interventricular septal defect, bulbous aortic arch, stenosis of ductus arteriosus, interrupted ossification of vertebral arch, vertebral and rib malformations, omphalocele, and gallbladder agenesis) and developmental variations. In pregnant rats, tacrolimus at oral doses of 3.2 mg/kg, 2.6 to 6.9 times the clinical dose range was associated with maternal toxicity, an increase in late resorptions, decreased numbers of live births, and decreased pup weight and viability.
Tacrolimus, given orally to pregnant rats after organogenesis and during lactation at 1.0 and 3.2 mg/kg, 0.8 to 6.9 times the recommended clinical dose range was associated with reduced pup weights and pup viability (3.2 mg/kg only); among the high dose pups that died early, an increased incidence of kidney hydronephrosis was observed.
8.3Nursing Mothers Tacrolimus is excreted in human milk. As the effect of chronic exposure to tacrolimus in healthy infants is not established, patients maintained on tacrolimus should discontinue nursing taking into consideration importance of drug to the mother.
8.4Pediatric Use The safety and efficacy of tacrolimus in pediatric kidney and heart transplant patients have not been established. Successful liver transplants have been performed in pediatric patients (ages up to 16 years) using tacrolimus. Two randomized active-controlled trials of tacrolimus in primary liver transplantation included 56 pediatric patients.
Thirty-one patients were randomized to tacrolimus-based and 25 to cyclosporine-based therapies. Additionally, a minimum of 122 pediatric patients were studied in an uncontrolled trial of tacrolimus in living related donor liver transplantation. Pediatric patients generally required higher doses of tacrolimus to maintain blood trough concentrations of tacrolimus similar to adult patients [ see Dosage and Administration ( 2.2 )].
8.5Geriatric Use Clinical trials of tacrolimus did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
8.6 Use in Renal Impairment The pharmacokinetics of tacrolimus in…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C - There are no adequate and well-controlled studies in pregnant women. Tacrolimus is transferred across the placenta. The use of tacrolimus during pregnancy in humans has been associated with neonatal hyperkalemia and renal dysfunction.
Tacrolimus given orally to pregnant rabbits at 0.5 to 4.3 times the clinical dose and pregnant rats at 0.8 to 6.9 times the clinical dose was associated with an increased incidence of fetal death in utero, fetal malformations (cardiovascular, skeletal, omphalocele, and gallbladder agenesis) and maternal toxicity. Tacrolimus should be used during pregnancy only if the potential benefit to the mother justifies the potential risk to the fetus. In pregnant rabbits, tacrolimus at oral doses of 0.32 and 1.0 mg/kg, 0.5 to 4.3 times the clinical dose range (0.075 – 0.2 mg/kg) based on body surface area, was associated with maternal toxicity as well as an increased incidence of abortions.
At the 1 mg/kg dose, fetal rabbits showed an increased incidence of malformations (ventricular hypoplasia, interventricular septal defect, bulbous aortic arch, stenosis of ductus arteriosus, interrupted ossification of vertebral arch, vertebral and rib malformations, omphalocele, and gallbladder agenesis) and developmental variations. In pregnant rats, tacrolimus at oral doses of 3.2 mg/kg, 2.6 to 6.9 times the clinical dose range was associated with maternal toxicity, an increase in late resorptions, decreased numbers of live births, and decreased pup weight and viability.
Tacrolimus, given orally to pregnant rats after organogenesis and during lactation at 1.0 and 3.2 mg/kg, 0.8 to 6.9 times the recommended clinical dose range was associated with reduced pup weights and pup viability (3.2 mg/kg only); among the high dose pups that died early, an increased incidence of kidney hydronephrosis was observed.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of tacrolimus in pediatric kidney and heart transplant patients have not been established. Successful liver transplants have been performed in pediatric patients (ages up to 16 years) using tacrolimus. Two randomized active-controlled trials of tacrolimus in primary liver transplantation included 56 pediatric patients.
Thirty-one patients were randomized to tacrolimus-based and 25 to cyclosporine-based therapies. Additionally, a minimum of 122 pediatric patients were studied in an uncontrolled trial of tacrolimus in living related donor liver transplantation. Pediatric patients generally required higher doses of tacrolimus to maintain blood trough concentrations of tacrolimus similar to adult patients [ see Dosage and Administration ( 2.2 )].
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of tacrolimus did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Limited overdosage experience is available. Acute overdosages of up to 30 times the intended dose have been reported. Almost all cases have been asymptomatic and all patients recovered with no sequelae.
Acute overdosage was sometimes followed by adverse reactions consistent with those listed in Adverse Reactions ( 6 ) (including tremors, abnormal renal function, hypertension, and peripheral edema); in one case of acute overdosage, transient urticaria and lethargy were observed. Based on the poor aqueous solubility and extensive erythrocyte and plasma protein binding, it is anticipated that tacrolimus is not dialyzable to any significant extent; there is no experience with charcoal hemoperfusion. The oral use of activated charcoal has been reported in treating acute overdoses, but experience has not been sufficient to warrant recommending its use.
General supportive measures and treatment of specific symptoms should be followed in all cases of overdosage. In acute oral and IV toxicity studies, mortalities were seen at or above the following doses: in adult rats, 52 times the recommended human oral dose; in immature rats, 16 times the recommended oral dose; and in adult rats, 16 times the recommended human IV dose (all based on body surface area corrections).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tacrolimus inhibits T-lymphocyte activation, although the exact mechanism of action is not known. Experimental evidence suggests that tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin is then formed and the phosphatase activity of calcineurin inhibited.
This effect may prevent the dephosphorylation and translocation of nuclear factor of activated T-cells (NF-AT), a nuclear component thought to initiate gene transcription for the formation of lymphokines (such as interleukin-2, gamma interferon). The net result is the inhibition of T-lymphocyte activation (i.e., immunosuppression). Tacrolimus prolongs the survival of the host and transplanted graft in animal transplant models of liver, kidney, heart, bone marrow, small bowel and pancreas, lung and trachea, skin, cornea, and limb.
In animals, tacrolimus has been demonstrated to suppress some humoral immunity and, to a greater extent, cell-mediated reactions such as allograft rejection, delayed type hypersensitivity, collagen-induced arthritis, experimental allergic encephalomyelitis, and graft versus host disease.
12.3Pharmacokinetics Tacrolimus activity is primarily due to the parent drug. The pharmacokinetic parameters (mean±S.D.) of Tacrolimus have been determined following intravenous (IV) and/or oral (PO) administration in healthy volunteers, and in kidney transplant, liver transplant, and heart transplant patients (Table 14). Table 12.
Pharmacokinetics Parameters (mean±S.D.) of Tacrolimus in Healthy Volunteers and Patients Population N Route (Dose) Parameters C max (ng/mL) T max (hr) AUC (ng hr/mL) t 1/2 (hr) CI (L/hr/kg) V (L/kg) Healthy Volunteers 8 IV (0.025 mg/kg/4hr) a a 598 b ± 125 34.2 ± 7.7 0.040 ± 0.009 1.91 ± 0.31 16 PO (5 mg) 29.7 ± 7.2 1.6 ± 0.7 243 c ± 73 34.8 ± 11.4 0.041 d ± 0.008 1.94d ±
0.53Kidney Transplant Patients 26 IV (0.02 mg/kg/12 hr) a a 294 e ± 262 18.8 ± 16.7 0.083 ± 0.050 1.41 ±
0.66PO (0.2 mg/kg/day) 19.2 ± 10.3 3.0 203 e ± 42 f f f PO (0.3 mg/kg/day) 24.2 ± 15.8 1.5 288 e ± 93 f f f Liver Transplant Patients 17 IV (0.05 mg/kg/12 hr) a a 3300 e ± 2130 11.7 ± 3.9 0.053 ± 0.017 0.85 ±
0.30PO (0.3 mg/kg/day) 68.5 ± 30 2.3 ± 1.5 519 e ± 179 f f f Heart Transplant Patients 11 IV (0.01 mg/kg/day as a continuous infusion) a a 954 g ± 334 23.6 ± 9.22 0.051 ± 0.015 f 11 PO (0.075 mg/kg/day)h 14.7 ± 7.79 2.1 [0.5-6] i 82.7 j ± 63.2 a f f 14 PO (0.15 mg/kg/day) h 24.5 ± 13.7 1.5 [0.4-4] i 142j ± 116 a f f a) not applicable b) AUC 0-120 c) AUC 0-72 d) Corrected for individual bioavailability e) AUC 0-inf f) not applicable g) AUC 0-t h) Determined after the first dose i) Median [range] j) AUC 0-12 Due to intersubject variability in Tacrolimus pharmacokinetics, individualization of dosing regimen is necessary for optimal therapy [ see Dosage and Administration ( 2.6 )].Pharmacokinetic data indicate that whole blood concentrations rather than plasma concentrations serve as the more appropriate sampling compartment to describe Tacrolimus pharmacokinetics.
Absorption Absorption of Tacrolimus from the gastrointestinal tract after oral administration is incomplete and variable. The absolute bioavailability of Tacrolimus was 17±10% in adult kidney transplant patients (N=26), 22±6% in adult liver transplant patients (N=17), 23±9% in adult heart transplant patients (N=11) and 18±5% in healthy volunteers (N=16). A single dose trial conducted in 32 healthy volunteers established the bioequivalence of the 1 mg and 5 mg capsules.
Another single dose trial in 32 healthy volunteers established the bioequivalence of the 0.5 mg and 1 mg capsules. Tacrolimus maximum blood concentrations(C max ) and area under the curve (AUC) appeared to increase in a dose-proportional fashion in 18 fasted healthy volunteers receiving a single oral dose of 3, 7, and 10 mg. In 18 kidney transplant patients, Tacrolimus trough concentrations from 3 to 30 ng/mL measured…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tacrolimus inhibits T-lymphocyte activation, although the exact mechanism of action is not known. Experimental evidence suggests that tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin is then formed and the phosphatase activity of calcineurin inhibited.
This effect may prevent the dephosphorylation and translocation of nuclear factor of activated T-cells (NF-AT), a nuclear component thought to initiate gene transcription for the formation of lymphokines (such as interleukin-2, gamma interferon). The net result is the inhibition of T-lymphocyte activation (i.e., immunosuppression). Tacrolimus prolongs the survival of the host and transplanted graft in animal transplant models of liver, kidney, heart, bone marrow, small bowel and pancreas, lung and trachea, skin, cornea, and limb.
In animals, tacrolimus has been demonstrated to suppress some humoral immunity and, to a greater extent, cell-mediated reactions such as allograft rejection, delayed type hypersensitivity, collagen-induced arthritis, experimental allergic encephalomyelitis, and graft versus host disease.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1Tacrolimus Capsules USP Tacrolimus Capsules USP, 0.5 mg are white to off white powder filled in hard gelatin capsule of size ‘4’, yellow opaque cap and yellow opaque body imprinted “ BP 665” twice on the body and imprinted “0.5 mg” twice on the cap with red ink. Bottles of 100. NDC 82983-400-10 Tacrolimus Capsules USP, 1 mg are white to off white powder filled in hard gelatin capsule of size ‘4’, white opaque cap and white opaque body imprinted “ BP 666" twice on the body and imprinted “1 mg” twice on the cap with red ink.
Bottles of 100. NDC 82983-401-10 Tacrolimus Capsules USP, 5 mg are white to off white powder filled in hard gelatin capsule of size ‘4’, salmon opaque cap and salmon opaque body imprinted “ BP 667” on the body and imprinted “5 mg” twice on the cap with white ink. Bottles of 100.
NDC 82983-402-10 Note: Tacrolimus capsules are not filled to maximum capsule capacity. Capsule contains labeled amount. Store and Dispense Store at 25°C (77°F); excursions permitted to 15°C-30°C (59°F-86°F).[See USP Controlled Room Temperature].
📋 Description ▾
12 DESCRIPTION Tacrolimus Capsules, USP are available for oral administration as capsules containing the equivalent of 0.5 mg, 1 mg or 5 mg of anhydrous tacrolimus USP. Inactive ingredients include anhydrous lactose NF DT, hypromellose USP, croscarmellose sodium NF, and magnesium stearate NF. The 0.5 mg capsule shell contains gelatin, titanium dioxide and yellow iron oxide, the 1 mg capsule shell contains gelatin and titanium dioxide, and the 5 mg capsule shell contains gelatin, titanium dioxide and red iron oxide.
Non-volatile components of the ink are Shellac Glaze, Iron Oxide Red, and Simethicone USP. Tacrolimus USP, previously known as FK506, is the active ingredient in tacrolimus capsules, USP. Tacrolimus is a macrolide immunosuppressant produced by Streptomyces tsukubaensis.
Chemically, tacrolimus is designated as [3S [3R* [E (1S*, 3S* 4S*)], 4S*, 5R*, 8S*, 9E, 12R* 14R* 15S* 16R* 18S* 19S* 26aR*]] -5,6,8,11,12,13,14,15,16,17,18,19,24,25,26,26a-hexadecahydro-5,19-dihydroxy-3-[2-(4-hydroxy-3-methoxycyclohexyl)-1-methylethenyl]-14,16-dimethoxy-4,10,12,18-tetramethyl-8-(2-propenyl)-15,19-epoxy-3H-pyrido[2,1-c][1,4] oxaazacyclotricosine-1,7,20,21(4H,23H)-tetrone, monohydrate. The chemical structure of tacrolimus is: Tacrolimus has an empirical formula of C 44 H 69 NO 12 •H2O and a formula weight of 822.03.
Tacrolimus appears as white crystals or crystalline powder. It is practically insoluble in water, freely soluble in ethanol, and very soluble in methanol and chloroform. USP Dissolution Test 6 is used.
USP Organic Impurities Procedure 2 is used. chemicalstructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Administration Advise patients to: •Take Tacrolimus at the same 12-hour intervals everyday to achieve consistent blood concentrations. •Take Tacrolimus consistently either with or without food because the presence and composition of food decreases the bioavailability of Tacrolimus. •Not to eat grapefruit or drink grapefruit juice in combination with Tacrolimus [ see Drug Interactions ( 7.2 )].
17.2Development of Lymphoma and Other Malignancies Inform patients they are at increased risk of developing lymphomas and other malignancies, particularly of the skin, due to immunosuppression. Advise patients to limit exposure to sunlight and ultraviolet (UV) light by wearing protective clothing and use a sunscreen with a high protection factor [ see Warnings and Precautions ( 5.2 )].
17.3Increased Risk of Infection Inform patients they are at increased risk of developing a variety of infections, including opportunistic infections, due to immunosuppression and to contact their physician if they develop any symptoms of infection [ see Warnings and Precautions ( 5.3 , 5.4 , 5.5 , )].
17.4New Onset Diabetes After Transplant Inform patients that Tacrolimus can cause diabetes mellitus and should be advised to contact their physician if they develop frequent urination, increased thirst or hunger [ see Warnings and Precautions ( 5.6 )].
17.5Nephrotoxicity Inform patients that tacrolimus can have toxic effects on the kidney that should be monitored. Advise patients to attend all visits and complete all blood tests ordered by their medical team [ see Warnings and Precautions ( 5.7 )].
17.6Neurotoxicity Inform patients that they are at risk of developing adverse neurologic effects including seizure, altered mental status, and tremor. Advise patients to contact their physician should they develop vision changes, deliriums, or tremors [ see Warnings and Precautions ( 5.8 )].
17.7Hyperkalemia Inform patients that Tacrolimus can cause hyperkalemia. Monitoring of potassium levels may be necessary, especially with concomitant use of other drugs known to cause hyperkalemia [ see Warnings and Precautions ( 5.9 )].
17.8Hypertension Inform patients that tacrolimus can cause high blood pressure which may require treatment with anti-hypertensive therapy [ see Warnings and Precautions ( 5.10 )].
17.9Drug Interactions Instruct patients to tell their health care providers when they start or stop taking all the medicines, including prescription medicines and non-prescription medicines, natural or herbal remedies, nutritional supplements and vitamins [ see Drug Interactions ( 7 )].
17.10Pregnant Women and Nursing Mothers Instruct patients to tell their healthcare provider if they plan to become pregnant or breast-feed their infant [ see Use in Specific Populations ( 8.1 , 8.3 )]
17.11Immunizations Inform patients that tacrolimus can interfere with the usual response to immunizations and that they should avoid live vaccines [ see Warnings and Precaution s ( 5.16 )]. Rx Only Product of USA Distributed By: Ajenat Pharmaceuticals LLC 203 N Marion St, Tampa, FL 33602 USA L54I-AJT R-2302 Rev: 12/19