
Glucosamine Chondroitin Wtih Tart Cherry Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Glucosamine Chondroitin Wtih Tart Cherry against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Glucosamine Chondroitin Wtih Tart Cherry is a dietary supplement by Nature's Answer with 12 active ingredients. Its ingredients are commonly taken for common cold and immune support, antioxidant support, skin health and collagen formation.Based on those ingredients, 607 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Evening Primrose Oil, Vitamin C, Glucosamine. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer
Ask about any prescription or over-the-counter medication and we check it for interactions with Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
This liquid formula contains 11 active ingredients. The main structural components are glucosamine and chondroitin sulfate, both targeted at joint health.
Supporting nutrients include vitamin C (an antioxidant), zinc, manganese, and boron (all minerals with roles in tissue and bone metabolism), potassium, and MSM. The formula also includes tart cherry juice concentrate and sweet cherry, plants traditionally used for inflammatory support, plus evening primrose oil, which supplies a type of fatty acid called GLA.
The product contains several inactive ingredients that serve as the liquid base and stabilizers—glycerin, water, fructose, natural flavors, soy lecithin, orange oil, xanthan gum, agave syrup, vitamin E acetate, and trace minerals.
Does it work?
Strong evidence
Glucosamine is likely effective for osteoarthritis, the main condition this product targets. Chondroitin sulfate is possibly effective for osteoarthritis and cataracts.
Vitamin C is effective for preventing vitamin C deficiency and possibly effective for exercise-induced respiratory infections, cataracts, and atrial fibrillation. Tart cherry is possibly effective for athletic performance.
Boron is likely effective for boron deficiency and possibly effective for vaginal yeast infections. Zinc is effective for zinc deficiency and possibly effective for acne and age-related macular degeneration.
For other uses claimed on this product—such as manganese for osteoarthritis, sweet cherry for heart disease or diabetes, and evening primrose oil for general wellness—the evidence is either insufficient or suggests the ingredient may not work.
How safe is it?
Well-documented data
Most ingredients in this product are generally well tolerated at typical supplement doses. Vitamin C is safe at normal amounts but can cause stomach cramping, diarrhea, nausea, and heartburn at very high doses, and may trigger kidney stones in susceptible people.
Zinc, at recommended levels, is well tolerated; excess can cause nausea, diarrhea, and a metallic taste. Potassium from food is fine, but supplements can raise blood potassium to dangerous levels, especially in people with kidney problems.
Manganese is safe in normal amounts but high doses carry a rare risk of Parkinson-like nerve damage. Boron is safe in small amounts but high doses are toxic.
Tart cherry and sweet cherry are generally well tolerated as food; in concentrated supplement form, some people report stomach pain or loose stools. Glucosamine and chondroitin are mostly well tolerated but can cause bloating, constipation, diarrhea, or nausea.
Evening primrose oil may cause stomach upset, and rare allergic reactions including anaphylaxis have been reported across glucosamine products. Pregnancy and breastfeeding: vitamin C and potassium are likely safe from normal dietary amounts; boron should be avoided in pregnancy due to potential harm to the fetus and avoided while breastfeeding.
Glucosamine and chondroitin have insufficient safety data and are best avoided during pregnancy and breastfeeding unless your doctor advises. Tart cherry and sweet cherry as food are likely safe in pregnancy, but concentrated supplements lack safety data.
Evening primrose oil evidence is unclear and should be avoided in pregnancy unless directed. No pregnancy/breastfeeding data is on file for zinc or manganese.
Meds to double-check
Major interaction found
Before taking this product, check with your pharmacist if you take warfarin or other blood thinners (Major severity). Also double-check if you use hormonal contraceptives or hormone replacement therapy, thyroid medication (levothyroxine), antibiotic medications (especially quinolones, tetracyclines, or cephalexin), HIV medications, potassium-sparing diuretics, ACE inhibitors, or blood pressure medications called angiotensin receptor blockers.
Evening primrose oil in this product may also interact with lithium, antipsychotic medications, and certain cancer drugs. If you take chemotherapy or antipsychotics, ask your pharmacist specifically about this product.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
This product may help with joint and bone health if you have osteoarthritis, but its value depends on your other medications. If you take warfarin, a blood thinner, hormonal birth control, thyroid medication, antibiotics, HIV drugs, chemotherapy, lithium, or blood pressure medications, you need to check this with your pharmacist first—interactions are real and could affect how your drugs work or raise safety risks.
Talk to your pharmacist before starting, especially if you have kidney problems or take multiple medications.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 10 of 11 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Mar 23, 2018.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Glucosamine Chondroitin Wtih Tart Cherry, straight from the product label.
| Brand | Nature's Answer |
|---|---|
| Barcode (UPC) | 083000261572 |
| Net contents | 16 fl. Oz.; 480 mL |
| Market status | On market |
| Date entered into DSLD | Mar 23, 2018 |
| DSLD ID | 174838 |
| Product type | Other Combinations |
| Supplement form | Liquid |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Calories | 30 Calorie(s) | -- |
| Total Carbohydrates | 8 Gram(s) | 3% |
| Sugar | 2 Gram(s) | -- |
| Vitamin C | 500 mg | 833% |
| Boron | 50 mcg | -- |
| Zinc | 1.6 mg | 11% |
| Manganese | 0.9 mg | 45% |
| MSM | 750 mg | -- |
| Sweet Cherry | 50 mg | -- |
| Potassium | 5 mg | 1% |
| Tart Cherry juice concentrate | 1400 mg | -- |
| Glucosamine | 1000 mg | -- |
| Evening Primrose Oil | 50 mg | -- |
| Chondroitin Sulfate | 300 mg | -- |
Other ingredients: Glycerin, purified Water, Fructose, Natural Flavors, hydroxylated Soy Lecithin, Orange Oil, Xanthan Gum, Agave Syrup, Vitamin E Acetate, Quik-Sorb, Trace Minerals
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
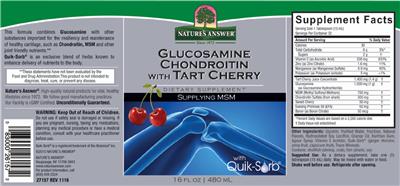
This formula combines Glucosamine with other substances important for the resiliency and maintenance of healthy cartilage, such as Chondroitin, MSM and other joint friendly nutrients.
Supplying MSM
With Quik-Sorb
Contains: Shellfish (shrimp, crab), fish (shark), soy.
Brand IP Statement(s)
Quik-Sorb is an exclusive blend of herbs known to enhance delivery of nutrients to the body.
Nature's Answer. High-quality natural products for vital, healthy lifestyles since 1972.
Quik-Sorb is a registered trademark of Bio-Botanica Inc. 2015 Nature's Answer
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
General Statements
We follow good manufacturing practices. Our facility is cGMP certified. Unconditionally Guaranteed.
Since 1972
Precautions
Warning: Keep out of reach of children.
Do not use if safety seal is damaged or missing.
If you are pregnant, nursing, taking any medications, planning any medical procedure or have a medical condition, consult with your healthcare practitioner before use.
Contains: Shellfish (shrimp, crab), fish (shark), soy.
General
27157 REV 1116
FDA Statement of Identity
Dietary Supplement
Suggested/Recommended/Usage/Directions
Suggested Use: As a dietary supplement, take one (1) tablespoon (15 mL) daily. May be mixed with water or food. Shake well before use.
Storage
Refrigerate after opening.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer
These are the 12 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Tbsp Dosage formLiquid Servings per container32 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sugar
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsBoron
No knowninteractions
Boron is a trace mineral found in many plant foods and sold as a supplement, mainly promoted for bone, joint, and hormone health. The human evidence f...
Boron monograph & interactionsZinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsManganese
Interacts with83 drugs
Manganese is an essential trace mineral your body needs in small amounts for bone formation, metabolism, and antioxidant defense, and most people get...
Manganese monograph & interactionsMSM
Sweet Cherry
No knowninteractions
Sweet cherry (Prunus avium) is a popular fruit rich in antioxidants and natural plant pigments, and it is sometimes used as a supplement for gout, sor...
Sweet Cherry monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsTart Cherry juice concentrate
No knowninteractions
Sour cherry (often sold as tart cherry or Montmorency cherry) is a fruit-based supplement rich in antioxidants that people use for muscle recovery, jo...
Tart Cherry juice concentrate monograph & interactionsGlucosamine
Interacts with170 drugs
Glucosamine is a natural compound found in cartilage and joint fluid, and it is one of the most popular supplements for osteoarthritis, especially of...
Glucosamine monograph & interactionsEvening Primrose Oil
Interacts with233 drugs
Evening primrose oil is a seed oil rich in gamma-linolenic acid (GLA), an omega-6 fatty acid, that is popularly used for skin conditions, PMS, and bre...
Evening Primrose Oil monograph & interactionsChondroitin Sulfate
Interacts with2 drugs
Chondroitin sulfate is a naturally occurring building block of cartilage that is widely taken, often with glucosamine, for osteoarthritis joint pain....
Chondroitin Sulfate monograph & interactionsOther (inactive) ingredients: Glycerin, Purified Water, Fructose, Natural Flavors, Hydroxylated Soy Lecithin, Orange Oil, Xanthan Gum, Agave Syrup, Vitamin E Acetate, Quik-Sorb, Trace Minerals. These complete the product’s ingredient list but are not active constituents.
Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer Drug Interactions
HelloPharmacist Interaction Report
Glucosamine Chondroitin With Tart Cherry by Nature's Answer is a liquid supplement with multiple ingredients that interact with medications.
The most serious interaction involves glucosamine and warfarin (a blood thinner): glucosamine may boost warfarin's effects and raise your bleeding risk. Two case reports document significant increases in bleeding measures (INR) in patients already stable on warfarin who added glucosamine/chondroitin.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C in this product interacts with several drug types. It may increase blood levels of hormonal contraceptives and hormone replacement therapy by up to 55% under some circumstances.
At high doses, it can reduce how well your body absorbs warfarin and may interfere with certain chemotherapy drugs (alkylating agents and antitumor antibiotics) by counteracting their free-radical-generating action. Vitamin C also increases absorption of levothyroxine (thyroid medication), which could require dose adjustment, and modestly reduces levels of the HIV drug indinavir and the psychiatric medication fluphenazine.
Zinc interacts with multiple antibiotic classes—quinolones, tetracyclines, and cephalexin are all less well absorbed when taken with zinc—as well as penicillamine (used for rheumatoid arthritis and copper poisoning), the HIV drugs ritonavir and integrase inhibitors, and the cancer drug cisplatin. Potassium in the formula raises the risk of dangerously high blood potassium levels (hyperkalemia) if you take potassium-sparing diuretics, ACE inhibitors, or angiotensin receptor blockers.
Evening primrose oil may thin the blood further if combined with anticoagulants or antiplatelet drugs, and may interact with lithium, phenothiazine antipsychotics, and the HIV drug combination lopinavir/ritonavir. Manganese theoretically reduces quinolone and tetracycline absorption and may raise toxicity risk with antipsychotics.
Altogether, these interactions span 602 individual medications.
We could not check MSM, as we hold no data for it. Please use the medication checker below with your exact prescriptions before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Glucosamine Chondroitin Wtih Tart Cherry?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Glucosamine Chondroitin Wtih Tart Cherry interact with 607 drugs. Click any drug to see the details.
7 of the 12 ingredients in Glucosamine Chondroitin Wtih Tart Cherry interact with drugs. Each result below shows which ingredient is responsible. Evening Primrose Oil Vitamin C Glucosamine Manganese Zinc Potassium Chondroitin Sulfate
WarfarinWarfarin
How Warfarin interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 4 ingredients. Tap an ingredient for the detail:
GlucosamineWarfarin (coumadin) Major
Interaction Summary
Glucosamine might increase the anticoagulant effects of warfarin and increase the risk of bruising and bleeding.
Read the full Glucosamine + Warfarin interactionVitamin CWarfarin (coumadin) Moderate
Interaction Summary
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Read the full Vitamin C + Warfarin interactionEvening Primrose OilCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose may increase the levels and clinical effects of CYP2C9 substrates.
Read the full Evening Primrose Oil + Warfarin interactionChondroitin SulfateWarfarin (coumadin) Moderate
Interaction Summary
Taking chondroitin in combination with glucosamine might increase the anticoagulant effects of warfarin.
Read the full Chondroitin Sulfate + Warfarin interactionWarfarin SodiumCoumadin, Panwarfin, Sofarin
How Warfarin Sodium interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 4 ingredients. Tap an ingredient for the detail:
GlucosamineWarfarin (coumadin) Major
Interaction Summary
Glucosamine might increase the anticoagulant effects of warfarin and increase the risk of bruising and bleeding.
Read the full Glucosamine + Warfarin Sodium interactionVitamin CWarfarin (coumadin) Moderate
Interaction Summary
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Read the full Vitamin C + Warfarin Sodium interactionEvening Primrose OilCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose may increase the levels and clinical effects of CYP2C9 substrates.
Read the full Evening Primrose Oil + Warfarin Sodium interactionChondroitin SulfateWarfarin (coumadin) Moderate
Interaction Summary
Taking chondroitin in combination with glucosamine might increase the anticoagulant effects of warfarin.
Read the full Chondroitin Sulfate + Warfarin Sodium interactionAbciximabReoPro
How Abciximab interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Abciximab interactionAbrocitinibCibinqo
How Abrocitinib interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Evening Primrose OilCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose may increase the levels and clinical effects of CYP2C9 substrates.
Read the full Evening Primrose Oil + Abrocitinib interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
Evening Primrose OilPhenothiazines Moderate
Interaction Summary
Theoretically, taking evening primrose oil with phenothiazines might increase the risk of convulsions.
Read the full Evening Primrose Oil + Acepromazine interactionManganeseAntipsychotic Drugs Moderate
Interaction Summary
Theoretically, the risk for manganese toxicity might increase when taken with antipsychotic drugs.
Read the full Manganese + Acepromazine interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 3 ingredients. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Acetaminophen, Aspirin interactionGlucosamineAcetaminophen (tylenol, Others) Minor
Interaction Summary
Acetaminophen might interfere with the activity of glucosamine sulfate by interacting with the sulfate portion.
Read the full Glucosamine + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 3 ingredients. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Acetaminophen, Aspirin, Caffeine interactionVitamin CAspirin, Acetaminophen (tylenol, Others) Minor
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionGlucosamineAcetaminophen (tylenol, Others) Minor
Interaction Summary
Acetaminophen might interfere with the activity of glucosamine sulfate by interacting with the sulfate portion.
Read the full Glucosamine + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, IbuprofenCombogesic
How Acetaminophen, Ibuprofen interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 3 ingredients. Tap an ingredient for the detail:
Evening Primrose OilCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose may increase the levels and clinical effects of CYP2C9 substrates.
Read the full Evening Primrose Oil + Acetaminophen, Ibuprofen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Ibuprofen interactionGlucosamineAcetaminophen (tylenol, Others) Minor
Interaction Summary
Acetaminophen might interfere with the activity of glucosamine sulfate by interacting with the sulfate portion.
Read the full Glucosamine + Acetaminophen, Ibuprofen interactionAcetophenazineTindal
How Acetophenazine interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
ManganeseAntipsychotic Drugs Moderate
Interaction Summary
Theoretically, the risk for manganese toxicity might increase when taken with antipsychotic drugs.
Read the full Manganese + Acetophenazine interactionAcetylsalicylic AcidEntrophen
How Acetylsalicylic Acid interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Acetylsalicylic Acid interactionVitamin CAspirin Minor
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Acetylsalicylic Acid interactionAlginic Acid, Aluminum HydroxideRafton
How Alginic Acid, Aluminum Hydroxide interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Alginic Acid, Aluminum Hydroxide interactionAlteplase, TpaActilyse, Activase
How Alteplase, Tpa interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Alteplase, Tpa interactionAltretamineHexalen
How Altretamine interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAlkylating Agents Moderate
Interaction Summary
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
Read the full Vitamin C + Altretamine interactionAluminum Acetate, Benzethonium ChlorideBuro-Sol Otic Solution
How Aluminum Acetate, Benzethonium Chloride interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Acetate, Benzethonium Chloride interactionAluminum ChlorideAluminum Chloride, Anhydrol Forte, Driclor, Drysol
How Aluminum Chloride interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Chloride interactionAluminum HydroxideAlu-Cap, Amphojel, Gaviscon
How Aluminum Hydroxide interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide interactionAluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium HydroxideAscriptin Codeine #2
How Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
Vitamin CAspirin, Aluminum Moderate
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionEvening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAluminum Hydroxide, Aspirin, Magnesium HydroxideAscriptin
How Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interactionVitamin CAspirin, Aluminum Moderate
Interaction Summary
Acidification of the urine by vitamin C might increase aspirin levels.
Read the full Vitamin C + Aluminum Hydroxide, Aspirin, Magnesium Hydroxide interactionAluminum Hydroxide, Magnesium Hydroxide (otc Drug)Maalox, Mucogel
How Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide, Magnesium Hydroxide (otc Drug) interactionAluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug)Mylanta
How Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum Hydroxide, Magnesium Hydroxide, Simethicone (otc Drug) interactionAluminum, CalciumDomeboro
How Aluminum, Calcium interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum, Calcium interactionAluminum, Magnesium (otc Drug)Almagel
How Aluminum, Magnesium (otc Drug) interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum, Magnesium (otc Drug) interactionAluminum, Magnesium Hydroxide (otc Drug)Wingel
How Aluminum, Magnesium Hydroxide (otc Drug) interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Vitamin CAluminum Moderate
Interaction Summary
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Read the full Vitamin C + Aluminum, Magnesium Hydroxide (otc Drug) interactionAmilorideAmilamont, Midamor
How Amiloride interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
PotassiumPotassium-sparing Diuretics Moderate
Interaction Summary
Concomitant use increases the risk of hyperkalemia.
Read the full Potassium + Amiloride interactionZincAmiloride (midamor) Minor
Interaction Summary
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Read the full Zinc + Amiloride interactionAmiloride, HydrochlorothiazideAmil-Co, Amilzide, Moduret 25, Moduretic
How Amiloride, Hydrochlorothiazide interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
PotassiumPotassium-sparing Diuretics Moderate
Interaction Summary
Concomitant use increases the risk of hyperkalemia.
Read the full Potassium + Amiloride, Hydrochlorothiazide interactionZincAmiloride (midamor) Minor
Interaction Summary
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Read the full Zinc + Amiloride, Hydrochlorothiazide interactionAmitriptyline, PerphenazineEtrafon, Etrafon-A, Etrafon-Forte, Triavil
How Amitriptyline, Perphenazine interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
Evening Primrose OilCytochrome P450 2c9 (cyp2c9) Substrates, Phenothiazines Moderate
Interaction Summary
Theoretically, evening primrose may increase the levels and clinical effects of CYP2C9 substrates.
Read the full Evening Primrose Oil + Amitriptyline, Perphenazine interactionManganeseAntipsychotic Drugs Moderate
Interaction Summary
Theoretically, the risk for manganese toxicity might increase when taken with antipsychotic drugs.
Read the full Manganese + Amitriptyline, Perphenazine interactionAmlodipine Besylate, BenazeprilLotrel
How Amlodipine Besylate, Benazepril interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
PotassiumAce Inhibitors (aceis) Moderate
Interaction Summary
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
Read the full Potassium + Amlodipine Besylate, Benazepril interactionAmphotericin, TetracyclineMysteclin-F
How Amphotericin, Tetracycline interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 2 ingredients. Tap an ingredient for the detail:
ZincTetracycline Antibiotics Moderate
Interaction Summary
Zinc might reduce levels of tetracycline antibiotics.
Read the full Zinc + Amphotericin, Tetracycline interactionManganeseTetracycline Antibiotics Moderate
Interaction Summary
Theoretically, manganese might reduce the absorption of tetracycline antibiotics.
Read the full Manganese + Amphotericin, Tetracycline interactionAnacaulase-bcdbNexoBrid
How Anacaulase-bcdb interacts with Glucosamine Chondroitin Wtih Tart Cherry — through 1 ingredient. Tap an ingredient for the detail:
Evening Primrose OilAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Evening Primrose Oil + Anacaulase-bcdb interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Glucosamine Chondroitin Wtih Tart Cherry with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Evening Primrose Oil
Anticoagulant/Antiplatelet Drugs
Theoretically, evening primrose oil may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Evening primrose oil contains gamma linolenic acid (GLA). There is preliminary clinical evidence that GLA can reduce platelet aggregation and prolong bleeding time.
Lithium
Theoretically, concomitant use of lithium with evening primrose oil might decrease lithium levels and effects.
In a case report, a patient on a stable dose of lithium for 10 years experienced a reduction in lithium levels after taking evening primrose oil 500 mg daily. Baseline levels were 0.69 mmol/L, which decreased to 0.37 mmol/L after 2 months and 0.23 mmol/L after 3 months of use. Lithium levels increased within 6 weeks of discontinuing evening primrose oil, to 0.73 mmol/L; no clinical effects were noted.
Lopinavir/Ritonavir (Kaletra)
Theoretically, evening primrose oil might increase the levels and effects of lopinavir.
In a case report, an HIV patient who took evening primrose oil (Efamol) along with lopinavir/ritonavir experienced an increase in serum levels of lopinavir to 15.2 mg/L. Six weeks after discontinuing evening primrose oil, levels of lopinavir returned to the normal range of 5-10 mg/L. When re-challenged with evening primrose oil for a week, the patient's lopinavir levels increased from 6.69 to 8.11 mg/L. It is suspected that evening primrose oil increases levels of lopinavir by inhibiting cytochrome P450 3A4 (CYP3A4), which metabolizes lopinavir. However, this effect has not been reported in other research.
Phenothiazines
Theoretically, taking evening primrose oil with phenothiazines might increase the risk of convulsions.
Evening primrose oil contains gamma-linolenic acid (GLA). There is some concern that taking supplements containing GLA might cause seizures, or lower the seizure threshold, when taken with phenothiazines. In one report, three patients with schizophrenia who had received phenothiazines developed EEG changes suggestive of temporal lobe epilepsy after starting treatment with GLA, although none experienced an actual seizure. In another report, two patients with schizophrenia who were stabilized on phenothiazines developed seizures when evening primrose oil 4 grams daily was added. One of these patients had a prior history of seizures. It is unclear whether evening primrose oil had any additive epileptogenic effects with the phenothiazines; there is no evidence that taking evening primrose oil alone causes seizures.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, evening primrose may increase the levels and clinical effects of CYP2C9 substrates.
In vitro research shows that linoleic acid, a constituent of evening primrose oil, inhibits CYP2C9.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Glucosamine
Warfarin (Coumadin)
Glucosamine might increase the anticoagulant effects of warfarin and increase the risk of bruising and bleeding.
In two individual case reports, glucosamine/chondroitin combinations were associated with a significant increase in international normalized ratio (INR) in patients previously stabilized on warfarin. In one case, the increase in INR occurred only after tripling the dose of a glucosamine/chondroitin supplement from 500 mg/400 mg daily to 1500/1200 mg daily. Additionally, 20 voluntary case reports to the U.S. Food & Drug Administration (FDA) have linked glucosamine plus chondroitin with increased INR, bruising, and bleeding in patients who were also taking warfarin. There have also been 20 additional case reports to the World Health Organization (WHO) that link glucosamine alone to increased INR in patients taking warfarin. The mechanism of this interaction is unclear. Glucosamine is a small component of heparin, but is not thought to have anticoagulant activity; however, animal research suggests that it might have antiplatelet activity.
Topoisomerase Ii Inhibitors
Theoretically glucosamine may induce resistance to topoisomerase II inhibitors.
In vitro research suggests that glucosamine might induce resistance to etoposide (VP16, VePesid) and doxorubicin (Adriamycin) by reducing inhibition of topoisomerase II, an enzyme required for DNA replication in tumor cells. This effect has not been reported in humans.
Acetaminophen (Tylenol, Others)
Acetaminophen might interfere with the activity of glucosamine sulfate by interacting with the sulfate portion.
Anecdotal reports suggest that adding glucosamine to an acetaminophen regimen might decrease pain control in patients with osteoarthritis. Some research suggests that the sulfate portion of glucosamine sulfate might contribute to its effect in osteoarthritis. Since acetaminophen metabolism requires sulfur and reduces serum sulfate concentrations, acetaminophen could theoretically interfere with the action of glucosamine sulfate. Conversely, the administration of sulfate could theoretically decrease the effectiveness of acetaminophen in sulfate-deficient people by increasing its clearance.
Antidiabetes Drugs
Despite initial concerns, it is unlikely that glucosamine will interfere with the effects of antidiabetes drugs.
In vitro and animal research has suggested that glucosamine might increase insulin resistance or decrease insulin production. This has raised concerns that taking glucosamine might worsen diabetes and decrease the effectiveness of diabetes drugs. However, clinical research suggests that glucosamine does not have adverse effects on blood glucose or glycated hemoglobin (HbA1C) in healthy, obese, or type 2 diabetes patients.
Manganese
Antipsychotic Drugs
Theoretically, the risk for manganese toxicity might increase when taken with antipsychotic drugs.
Hallucinations and behavioral changes have been reported in a patient with liver disease who was taking haloperidol and manganese. Researchers speculate that taking manganese along with haloperidol, phenothiazine-derivatives, or other antipsychotic medications might increase the risk of manganese toxicity in some patients.
Quinolone Antibiotics
Theoretically, manganese might reduce the absorption of quinolone antibiotics.
Manganese is a multivalent cation. Interactions resulting in reduced quinolone absorption have been reported between quinolones and other multivalent cations, such as calcium and iron.
Tetracycline Antibiotics
Theoretically, manganese might reduce the absorption of tetracycline antibiotics.
Manganese is a multivalent cation. Interactions resulting in reduced tetracycline absorption have been reported between tetracyclines and other multivalent cations, such as calcium and iron.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Chondroitin Sulfate
Warfarin (Coumadin)
Taking chondroitin in combination with glucosamine might increase the anticoagulant effects of warfarin. However, the effect of chondroitin alone is unclear.
There have been multiple reports of increased international normalized ratio (INR) in patients taking warfarin with glucosamine, with or without chondroitin. The lack of reports with chondroitin alone seem to suggest that the interactions occurring in these reports may have been due to glucosamine. In two individual case reports, glucosamine/chondroitin combinations were associated with a significant increase in INR in patients previously stabilized on warfarin. Additionally, 20 voluntary case reports to the US Food & Drug Administration (FDA) have linked glucosamine plus chondroitin with increased INR, bruising, and bleeding in patients who were also taking warfarin. There have also been 20 additional case reports to the World Health Organization (WHO) that link glucosamine alone, without chondroitin, to increased INR in patients taking warfarin.
Brand information
Manufacturer and brand details for Glucosamine Chondroitin Wtih Tart Cherry, from the product label.
Nature's Answer
See all Nature's Answer products- Name
- Nature's Answer
- City
- Hauppauge
- State
- NY
- ZipCode
- 11788-3943
- Phone Number
- (800) 439-2324
- Web Address
- www.naturesanswer.com
Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer: Common Questions
Does Glucosamine Chondroitin Wtih Tart Cherry by Nature's Answer interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Will this help my osteoarthritis?
Is it safe to take while pregnant or breastfeeding?
What are the most common side effects?
Can I take this with my blood thinner?
Does this product have any fillers?
What is evening primrose oil for in this formula?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Glucosamine Chondroitin Wtih Tart Cherry is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Glucosamine Chondroitin Wtih Tart Cherry’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Vitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographBoron
Boron is a trace mineral found in many plant foods and sold as a supplement, mainly promoted for bone, joint, and hormone health. The human evidence for most of these uses is limited or prel...
Read the full Boron monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographManganese
Interacts with 83 drugsManganese is an essential trace mineral your body needs in small amounts for bone formation, metabolism, and antioxidant defense, and most people get enough from a normal diet. Supplements m...
Read the full Manganese monograph → Herb & supplement monographSweet Cherry
Sweet cherry (Prunus avium) is a popular fruit rich in antioxidants and natural plant pigments, and it is sometimes used as a supplement for gout, sore muscles, and sleep. The research that...
Read the full Sweet Cherry monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographSour Cherry
Sour cherry (often sold as tart cherry or Montmorency cherry) is a fruit-based supplement rich in antioxidants that people use for muscle recovery, joint and gout symptoms, and sleep. Early...
Read the full Sour Cherry monograph → Herb & supplement monographGlucosamine
Interacts with 170 drugsGlucosamine is a natural compound found in cartilage and joint fluid, and it is one of the most popular supplements for osteoarthritis, especially of the knee. The evidence is mixed, with so...
Read the full Glucosamine monograph → Herb & supplement monographEvening Primrose
Interacts with 233 drugsEvening primrose oil is a seed oil rich in gamma-linolenic acid (GLA), an omega-6 fatty acid, that is popularly used for skin conditions, PMS, and breast pain. The evidence behind most of th...
Read the full Evening Primrose monograph → Herb & supplement monographChondroitin Sulfate
Interacts with 2 drugsChondroitin sulfate is a naturally occurring building block of cartilage that is widely taken, often with glucosamine, for osteoarthritis joint pain. The evidence is mixed—some people report...
Read the full Chondroitin Sulfate monograph →Sources & How We Checked
Glucosamine Chondroitin Wtih Tart Cherry's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 298 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Boron 6 references
- Ellenhorn MJ, et al. Ellenhorn's Medical Toxicology: Diagnoses and Treatment of Human Poisoning. 2nd ed. Baltimore, MD: Williams & Wilkins, 1997.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Thai L, Hart LL. Boric acid vaginal suppositories. Ann Pharmacother 1993;27:1355-7.
- Acs N, Banhidy F, Puho E, Czeizel AE. Teratogenic effects of vaginal boric acid treatment during pregnancy. Int J Gynaecol Obstet 2006;93:55-6. PubMed
- Garabrant, D. H., Bernstein, L., Peters, J. M., and Smith, T. J. Respiratory and eye irritation from boron oxide and boric acid dusts. J Occup Med 1984;26(8):584-586. PubMed
- Hjelm C, Harari F, Vahter M. Pre- and postnatal environmental boron exposure and infant growth: results from a mother-child cohort in northern Argentina. Environ Res 2019;171:60-8. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Manganese 21 references
- Hansten PD, Horn JR. Hansten and Horn's Drug Interactions Analysis and Management. Vancouver, CAN:Appl Therapeut, 1999.
- Barrington WW, Angle CR, Willcockson NK, et al. Autonomic function in manganese alloy workers. Environ Res 1998;78:50-8. PubMed
- Hauser RA, Zesiewicz TA, Martinez C, et al. Blood manganese correlates with brain magnetic resonance imaging changes in patients with liver disease. Can J Neurol Sci 1996;23:95-8. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Lee JW. Manganese intoxication. Arch Neurol 2000;57:597-9.. PubMed
- Powers KM, Smith-Weller T, Franklin GM, et al. Parkinson's disease risks associated with dietary iron, manganese, and other nutrient intakes. Neurology 2003;60:1761-6.. PubMed
- McMillan, D. E. A brief history of the neurobehavioral toxicity of manganese: some unanswered questions. Neurotoxicology 1999;20(2-3):499-507.
- Gerber, G. B., Leonard, A., and Hantson, P. Carcinogenicity, mutagenicity and teratogenicity of manganese compounds. Crit Rev Oncol Hematol. 2002;42(1):25-34. PubMed
- Jiang, Y. and Zheng, W. Cardiovascular toxicities upon manganese exposure. Cardiovasc.Toxicol 2005;5(4):345-354. PubMed
- Mehta, R. and Reilly, J. J. Manganese levels in a jaundiced long-term total parenteral nutrition patient: potentiation of haloperidol toxicity? Case report and literature review. JPEN J Parenter.Enteral Nutr 1990;14(4):428-430. PubMed
- Nemery, B. Metal toxicity and the respiratory tract. Eur Respir.J 1990;3(2):202-219. DOI
- Vanek VW, Borum P, Buchman A, et al. A.S.P.E.N. position paper: recommendations for changes in commercially available parenteral multivitamin and multi-trace element products. Nutr Clin Pract. 2012;27:440-491.doi: 10.1177/0884533612446706 PubMed
- Schuh MJ. Possible Parkinson's disease induced by chronic manganese supplement ingestion. Consult Pharm. 2016;31(12):698-703. doi: 10.4140/TCP.n.2016.698. PubMed
- Baker B, Ali A, Isenring L. Recommendations for manganese supplementation to adult patients receiving long-term home parenteral nutrition: an analysis of the supporting evidence. Nutr Clin Pract 2016;31(2):180-5. doi: 10.1177/0884533615591600. PubMed
- Ho CSH, Ho RCM, Quek AML. Chronic manganese toxicity associated with voltage-gated potassium channel complex antibodies in a relapsing neuropsychiatric disorder. Int J Environ Res Public Health 2018;15(4). pii: E783. doi: 10.3390/ijerph15040783. PubMed
- Yamamoto M, Sakurai K, Eguchi A, et al.; Japan Environment and Children's Study Group: Association between blood manganese level during pregnancy and birth size: the Japan environment and children's study (JECS). Environ Res 2019;172:117-26. PubMed
- Li D, Ge X, Liu Z, et al. Association between long-term occupational manganese exposure and bone quality among retired workers. Environ Sci Pollut Res Int 2020;27(1):482-9. PubMed
- Martin KV, Sucharew H, Dietrich KN, et al. Co-exposure to manganese and lead and pediatric neurocognition in East Liverpool, Ohio. Environ Res 2021;202:111644. PubMed
- Racette BA, Nelson G, Dlamini WW, et al. Depression and anxiety in a manganese-exposed community. Neurotoxicology 2021;85:222-33. PubMed
- Ruiz-Azcona L, Fernández-Olmo I, Expósito A, et al. Impact of environmental airborne manganese exposure on cognitive and motor functions in adults: a systematic review and meta-analysis. Int J Environ Res Public Health 2021;18(8):4075. PubMed
- Uyar E, Gurkas E, Aksu AU, et al. Can therapeutic plasma exchange be life-saving in life-threatening manganese intoxication?. Transfus Apher Sci 2022;61(4):103417. PubMed
Sweet Cherry 3 references
- Serrano M, Guillen F, Martinez-Romero D, et al. Chemical constiuents and antioxidant activity of sweet cherry at different ripening stages. J Agric Food Chem 2005;53:2741-5.
- Ballmer-Weber BK, Scheurer S, Fritsche P, et al. Component-resolved diagnosis with recombinant allergens in patients with cherry allergy. J Allergy Clin Immunol 2002;110:167-73. PubMed
- Goncalves B, Landbo AK, Knudsen D, et al. Effect of ripeness and postharvest storage on the phenolic profiles of Cherries (Prunus avium L.). J Agric Food Chem 2004;52:523-30.
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Sour Cherry 4 references
- Schumacher HR, Pullman-Mooar S, Gupta SR, et al. Randomized double-blind crossover study of the efficacy of a tart cherry juice blend in treatment of osteoarthritis (OA) of the knee. Osteoarthritis Cartilage 2013;21(8):1035-41. PubMed
- Seymour EM, Warber SM, Kirakosyan A, et al. Anthocyanin pharmacokinetics and dose-dependent plasma antioxidant pharmacodynamics following whole tart cherry intake in healthy humans. J Funct Food 2014;11:509-16. DOI
- Elliot DL, Kuehl KS, Jones KD, Dulacki K. Using an eccentric exercise-testing protocol to assess the beneficial effects of tart cherry juice in fibromyalgia patients. Integ Med 2010;9(6):25-9.
- Soltanifar A, Moharreri F, Bakhtiari E, Hosseinpour A. The Effect of Adding Sour Cherry Concentrate to The Usual Treatment of Attention Deficit Hyperactivity Disorder In 6 To 12 Years Old Children. J Atten Disord 2023;27(2):214-219. PubMed
Glucosamine 58 references
- Adams ME. Hype about glucosamine. Lancet 1999;354:353-4. PubMed
- Balkan B, Dunning BE. Glucosamine inhibits glucokinase in vitro and produces a glucose-specific impairment of in vivo insulin secretion in rats. Diabetes 1994;43:1173-9. PubMed
- Giaccari A, Morviducci L, Zorretta D, et al. In vivo effects of glucosamine on insulin secretion and insulin sensitivity in the rat: possible relevance to the maladaptive responses to chronic hyperglycaemia. Diabetologia 1995;38:518-24. PubMed
- Holmang A, Nilsson C, Niklasson M, et al. Induction of insulin resistance by glucosamine reduces blood flow but not interstitial levels of either glucose or insulin. Diabetes 1999;48:106-11. PubMed
- Houpt JB, McMillan R, Wein C, Paget-Dellio SD. Effect of glucosamine hydrochloride in the treatment of pain of osteoarthritis of the knee. J Rheumatol 1999;26:2423-30.
- Barclay TS, Tsourounis C, McCart GM. Glucosamine. Ann Pharmacother 1998;32:574-9.
- Shankar RR, Zhu JS, Baron AD. Glucosamine infusion in rats mimics the beta-cell dysfunction of non-insulin-dependent diabetes mellitus. Metabolism 1998;47:573-7.
- Almada A, Harvey P, Platt K. Effects of chronic oral glucosamine sulfate on fasting insulin resistance index (FIRI) in non-diabetic individuals. FASEB J 2000;14:A750.
- Reginster JY, Deroisy R, Rovati LC, et al. Long-term effects of glucosamine sulfate on osteoarthritis progression: a randomised, placebo-controlled trial. Lancet 2001;357:251-6.
- Does glucosamine increase serum lipid levels and blood pressure? Pharmacist's Letter/Prescriber's Letter 2001;17(11):171115.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Monauni T, Zenti MG, Cretti A, et al. Effects of glucosamine infusion on insulin secretion and insulin action in humans. Diabetes 2000;49:926-35. PubMed
- Pouwels MJ, Jacobs JR, Span PN, et al. Short-term glucosamine infusion does not affect insulin sensitivity in humans. J Clin Endocrinol Metab 2001;86:2099-103. DOI
- Yun J, Tomida A, Nagata K, Tsuruo T. Glucose-regulated stresses confer resistance to VP-16 in human cancer cells through a decreased expression of DNA topoisomerase II. Oncol Res 1995;7:583-90.
- Pavelka K, Gatterova J, Olejarova M, et al. Glucosamine sulfate use and delay of progression of knee osteoarthritis: A 3-year, randomized, placebo-controlled, double-blind study. Arch Intern Med 2002;162:2113-23. PubMed
- Tallia AF, Cardone DA. Asthma exacerbation associated with glucosamine-chondroitin supplement. J Am Board Fam Pract 2002;15:481-4..
- Scroggie DA, Albright A, Harris MD. The effect of glucosamine-chondroitin supplementation on glycosylated hemoglobin levels in patients with type 2 diabetes mellitus: a placebo-controlled, double-blinded, randomized clinical trial. Arch Intern Med 2003; PubMed
- Hoffer LJ, Kaplan LN, Hamadeh MJ, et al. Sulfate could mediate the therapeutic effect of glucosamine sulfate. Metabolism 2001;50:767-70.. PubMed
- Yu JG, Boies SM, Olefsky JM. The effect of oral glucosamine sulfate on insulin sensitivity in human subjects. Diabetes Care 2003;26:1941-2. PubMed
- Danao-Camara T. Potential side effects of treatment with glucosamine and chondroitin. Arthritis Rheum 2000;43:2853. PubMed
- Guillaume MP, Peretz A. Possible association between glucosamine treatment and renal toxicity: comment on the letter by Danao-Camara. Arthritis Rheum 2001;44:2943-4. PubMed
- Rozenfeld V, Crain JL, Callahan AK. Possible augmentation of warfarin effect by glucosamine-chondroitin. Am J Health Syst Pharm 2004;61:306-307. PubMed
- Tannis AJ, Barban J, Conquer JA. Effect of glucosamine supplementation on fasting and non-fasting plasma glucose and serum insulin concentrations in healthy individuals. Osteoarthritis Cartilage 2004;12:506-11. PubMed
- Bush TM, Rayburn KS, Holloway SW, et al. Adverse interactions between herbal and dietary substances and prescription medications: a clinical survey. Altern Ther Health Med 2007;13:30-5.
- Stumpf JL, Lin SW. Effect of glucosamine on glucose control. Ann Pharmacother 2006;40:694-8. PubMed
- Pham T, Cornea A, Blick KE, et al. Oral glucosamine in doses used to treat osteoarthritis worsens insulin resistance. Am J Med Sci 2007;333:333-9. PubMed
- Muniyappa R, Karne RJ, Hall G, et al. Oral glucosamine for 6 weeks at standard doses does not cause or worsen insulin resistance or endothelial dysfunction in lean or obese subjects. Diabetes 2006;55:3142-50. PubMed
- Knudsen J, Sokol GH. Potential glucosamine-warfarin interaction resulting in increased international normalized ratio: Case report and review of the literature and MedWatch database. Pharmacotherapy 2008;28:540-8. PubMed
- Yue QY, Strandell J, Myrberg O. Concomitant use of glucosamine potentiates the effect of warfarin. Jan 2006. Drug Safety 29(10):911-1010. DOI
- Rozendaal RM, Koes BW, van Osch GJVM, et al. Effect of glucosamine sulfate on hip osteoarthritis: A randomized trial. Ann Intern Med 2008;148:268-77. PubMed
- Baron AD, Zhu JS, Zhu JH, et al. Glucosamine induces insulin resistance in vivo by affecting GLUT 4 translocation in skeletal muscle. Implications for glucose toxicity. J Clin Invest 1995;96(6):2792-801. PubMed
- Nelson BA, Robinson KA, Buse MG. High glucose and glucosamine induce insulin resistance via different mechanisms in 3T3-L1 adipocytes. Diabetes 2000;49(6):981-91. PubMed
- Giordano N, Fioravanti A, Papakostas P, et al. The efficacy and tolerability of glucosamine sulfate in the treatment of knee osteoarthritis: a randomized, double-blind, placebo-controlled trial. Curr Ther Res Clin Exp 2009;70(3):185-196. PubMed
- Shaygannejad, V., Janghorbani, M., Savoj, M. R., and Ashtari, F. Effects of adjunct glucosamine sulfate on relapsing-remitting multiple sclerosis progression: preliminary findings of a randomized, placebo-controlled trial. Neurol Res 2010;32(9):981-985. PubMed
- Cahlin, B. J. and Dahlstrom, L. No effect of glucosamine sulfate on osteoarthritis in the temporomandibular joints--a randomized, controlled, short-term study. Oral Surg Oral Med Oral Pathol Oral Radiol Endod 2011;112(6):760-766. PubMed
- Cerda C, Bruguera M, Parés A. Hepatotoxicity associated with glucosamine and chondroitin sulfate in patients with chronic liver disease. World J Gastroenterol 2013;19(32):5381-4. PubMed
- Hochberg MC, Martel-Pelletier J, Monfort J, Möller I, Castillo JR, Arden N,Berenbaum F, Blanco FJ, Conaghan PG, Doménech G, Henrotin Y, Pap T, Richette P, Sawitzke A, du Souich P, Pelletier JP; on behalf of the MOVES Investigation Group. Combined chondroi
- von Felden J, Montani M, Kessebohm K, Stickel F. Drug-induced acute liver injury mimicking autoimmune hepatitis after intake of dietary supplements containing glucosamine and chondroitin sulfate. Int J Clin Pharmacol Ther 2013;51(3):219-23. PubMed
- Provenza JR, Shinjo SK, Silva JM, Peron CR, Rocha FA. Combined glucosamine and chondroitin sulfate, once or three times daily, provides clinically relevant analgesia in knee osteoarthritis. Clin Rheumatol 2015;34:1455-62. PubMed
- Ossendza RA, Grandval P, Chinoune F, Rocher F, Chapel F, Bernardini D. [Acute cholestatic hepatitis due to glucosamine forte]. Gastroenterol Clin Biol. 2007 Apr;31(4):449-50.
- Audimoolam VK, Bhandari S. Acute interstitial nephritis induced by glucosamine. Nephrol Dial Transplant 2006;21(7):2031. PubMed
- Greenlee H, Crew KD, Shao T, Kranwinkel G, Kalinsky K, Maurer M, Brafman L, Insel B, Tsai WY, Hershman DL. Phase II study of glucosamine with chondroitin on aromatase inhibitor-associated joint symptoms in women with breast cancer. Support Care Cancer 201 PubMed
- Wilkens, P., Scheel, I. B., Grundnes, O., Hellum, C., and Storheim, K. Effect of glucosamine on pain-related disability in patients with chronic low back pain and degenerative lumbar osteoarthritis: a randomized controlled trial. JAMA 2010;304(1):45-52. PubMed
- Simon RR, Marks V, Leeds AR, Anderson JW. A comprehensive review of oral glucosamine use and effects on glucose metabolism in normal and diabetic individuals. Diabetes Metab Res Rev 2011;27(1):14-27. PubMed
- Smidt D, Torpet LA, Nauntofte B, Heegaard KM, Pedersen AM. Associations between labial and whole salivary flow rates, systemic diseases and medications in a sample of older people. Community Dent Oral Epidemiol 2010;38(5):422-35. PubMed
- Wangroongsub Y, Tanavalee A, Wilairatana V, Ngarmukos S. Comparable clinical outcomes between glucosamine sulfate-potassium chloride and glucosamine sulfate sodium chloride in patients with mild and moderate knee osteoarthritis: a randomized, double-blind
- Chopra A, Saluja M, Tillu G, Venugopalan A, Sarmukaddam S, Raut AK, Bichile L, Narsimulu G, Handa R, Patwardhan B. A Randomized Controlled Exploratory Evaluation of Standardized Ayurvedic Formulations in Symptomatic Osteoarthritis Knees: A Government of I
- Swinburne LM. Glucosamine sulphate and osteoarthritis. Lancet 2001;357(9268):1617. PubMed
- Murphy RK, Ketzler L, Rice RD, Johnson SM, Doss MS, Jaccoma EH. Oral glucosamine supplements as a possible ocular hypertensive agent. JAMA Ophthalmol 2013;131(7):955-7. PubMed
- Kimball AB, Kaczvinsky JR, Li J, et al. Reduction in the appearance of facial hyperpigmentation after use of moisturizers with a combination of topical niacinamide and N-acetyl glucosamine: results of a randomized, double-blind, vehicle-controlled trial.
- Ma H, Li X, Sun D, et al. Association of habitual glucosamine use with risk of cardiovascular disease: prospective study in UK Biobank. BMJ. 2019 May 14;365:l1628. PubMed
- Hoban C, Byard R, Musgrave I. Hypersensitive adverse drug reactions to glucosamine and chondroitin preparations in Australia between 2000 and 2011. Postgrad Med J. 2019 Oct 9. pii: postgradmedj-2019-136957. PubMed
- Tenti S, Veronese N, Cheleschi S, et al. Prescription-grade crystalline glucosamine sulfate as an add-on therapy to conventional treatments in erosive osteoarthritis of the hand: results from a 6-month observational retrospective study. Aging Clin Exp Res PubMed
- Yu H, Wu J, Chen H, et al. Glucosamine use is associated with a higher risk of cardiovascular diseases in patients with osteoarthritis: results from a large study in 685,778 subjects. Nutrients 2022;14(18):3694. PubMed
- Chu EC, Huang KHK, Cheung G, Ng G, Lin A. Delayed Skin Allergy to Glucosamine Chondroitin Supplement. Cureus 2023;15(3):e36310. PubMed
- Lila AM, Alekseeva LI, Baranov AA, et al. Chondroitin sulfate and glucosamine combination in patients with knee and hip osteoarthritis: A long-term observational study in Russia. World J Orthop 2023;14(6):443-457. PubMed
- Lehrer S, Morello T, Karrasch C, Rheinstein PH, Danias J. Effect of Glucosamine on Intraocular Pressure and Risk of Developing Glaucoma. J Glaucoma 2023. PubMed
- Rabade A, Viswanatha GL, Nandakumar K, Kishore A. Evaluation of efficacy and safety of glucosamine sulfate, chondroitin sulfate, and their combination regimen in the management of knee osteoarthritis: a systematic review and meta-analysis. Inflammopharmac PubMed
Evening Primrose 33 references
- Shaw D, Leon C, Kolev S, Murray V. Traditional remedies and food supplements: a 5-year toxicological study (1991-1995). Drug Saf 1997;17:342-56.
- Laivuori H, Hovatta O, Viinikka L, et al. Dietary supplementation with primrose oil or fish oil does not change urinary excretion of prostacyclin and thromboxane metabolites in pre-eclamptic women. Prostaglandins Leukot Essent Fatty Acids 1993;49:691-4. PubMed
- Dove D, Johnson P. Oral evening primrose oil: its effect on length of pregnancy and selected intrapartum outcomes in low-risk nulliparous women (abstract). J Nurse Midwifery 1999;44:320-4. PubMed
- Guivernau M, Meza N, Barja P, Roman O. Clinical and experimental study on the long-term effect of dietary gamma-linolenic acid on plasma lipids, platelet aggregation, thromboxane formation, and prostacyclin production. Prostaglandins Leukot Essent Fatty A PubMed
- Cant A, Shay J, Horrobin DF. The effect of maternal supplementation with linoleic and gamma- linolenic acids on the fat composition and content of human milk: a placebo-controlled trial. J Nutr Sci Vitaminol (Tokyo) 1991;37:573-9. PubMed
- Keen H, Payan J, Allawi J, et al. Treatment of diabetic neuropathy with gamma-linolenic acid. The gamma-Linolenic Acid Multicenter Trial Group. Diabetes Care 1993;16:8-15.
- Blommers J, de Lange-De Klerk ES, Kuik DJ, et al. Evening primrose oil and fish oil for severe chronic mastalgia: a randomized, double-blind, controlled trial. Am J Obstet Gynecol 2002;187:1389-94.. DOI
- Cheung KL. Management of cyclical mastalgia in oriental women: pioneer experience of using gamolenic acid (Efamast) in Asia. Aust N Z J Surg 1999;69:492-4..
- Das UN. The lipids that matter from infant nutrition to insulin resistance. Prostaglandins Leukot Essent Fatty Acids 2002;67:1-12. PubMed
- Wedig KE, Whitsett JA. Down the primrose path: petechiae in a neonate exposed to herbal remedy for parturition. J Pediatr 2008;152:140, 140.e1. PubMed
- Ty-Torredes KA. The effect of oral evening primrose oil on bishop score and cervical length amongst term gravidas. Am J Obstet Gynecol. 2006;195(6 Suppl 1):S30.
- Moodley J and Norman RJ. Attempts at dietary alteration of prostaglandin pathways in the management of pre-eclampsia. Prostaglandins Leukot Essent Fatty Acids 1989;37(3):145-147. PubMed
- Tong M. [Treatment of hyperlipemia with evening primrose oil capsules]. Zhong Xi Yi Jie He Za Zhi. 1988;8:469-71, 452-3.
- Holman CP and Bell AF. A trial of evening primrose oil in the treatment of chronic schizophrenia. J Orhtomolecular Psych 1983;12:302-304.
- Vaddadi KS. The use of gamma-linolenic acid and linoleic acid to differentiate between temporal lobe epilepsy and schizophrenia. Prostaglandins Med 1981;6(4):375-379. PubMed
- Zou L, Harkey MR, and Henderson GL. Effects of herbal components on cDNA-expressed cytochrome P450 enzyme catalytic activity. Life Sci 8-16-2002;71(13):1579-1589. PubMed
- Yoon, S., Lee, J., and Lee, S. The therapeutic effect of evening primrose oil in atopic dermatitis patients with dry scaly skin lesions is associated with the normalization of serum gamma-interferon levels. Skin Pharmacol Appl.Skin Physiol 2002;15(1):20- PubMed
- Bamford, J. T., Gibson, R. W., and Renier, C. M. Atopic eczema unresponsive to evening primrose oil (linoleic and gamma- linolenic acids). J Am.Acad.Dermatol. 1985;13(6):959-965.
- Preece PE, Hanslip JI Gilbert L. Evening primrose oil (Efamol) for mastalgia. In: Horrobin DF. Clinical Uses of Essential Fatty Acids . Montreal, Quebec: Eden;1982.
- Parveen, S. Sarwar G. Ali M. Channa G. A. Danazol versus oil of evening primrose in the treatment of mastalgia. Pakistan Journal of Surgery. 2007;23(1):10-13.
- Belch JJF, Shaw B, O'Dowd A, et al. Evening primrose oil (Efamol) as a treatment for cold-induced vasospasm (Raynaud's phenomenon). Prog Lipid Res 1986;25:335-40.
- Johnson, M., Ostlund, S., Fransson, G., Kadesjo, B., and Gillberg, C. Omega-3/omega-6 fatty acids for attention deficit hyperactivity disorder: a randomized placebo-controlled trial in children and adolescents. J.Atten.Disord. 2009;12(5):394-401. PubMed
- Farzaneh F, Fatehi S, Sohrabi MR, Alizadeh K. The effect of oral evening primrose oil on menopausal hot flashes: a randomized clinical trial. Arch Gynecol Obstet 2013;288(5):1075-9. PubMed
- Puri BK. The safety of evening primrose oil in epilepsy. Prostaglandins Leukotrienes Essential Fatty Acids 2007;77:101-3. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Osman M, Badawi E. Evening primrose oil reducing serum lithium concentration. Ther Adv Psychopharmacol. 2016 Oct;6(5):343-44. PubMed
- Kalati M, Kashanian M, Jahdi F, Naseri M, Haghani H, SHeikhansari N. Evening primrose oil and labour, is it effective? A randomized clinical trial. J Obstet Gynaecol. 2018 Feb 9:1-5.
- Sharif SN, Darsareh F. Impact of evening primrose oil consumption on psychological symptoms of postmenopausal women: a randomized double-blinded placebo-controlled clinical trial. Menopause. 2020;27(2):194-198. PubMed
- Shahraki AD, Mirhoseini S, Movahedi M, Hajihashemy M, Haghollahi F. Comparative Study of the Effect of Vaginal use of Primrose Oil with Misoprostol on Cervical Preparation of Prim Gravid Women: A Double-blind Clinical Trial. Adv Biomed Res 2023;12:78. PubMed
- Shahinfar S, Abedi P, Jahanfar S, Khajehpoor M, Chashmyazdan M. The effect of evening primrose oil on cervical ripening and birth outcomes: A systematic review and meta-analysis. Heliyon 2023;9(2):e13414. PubMed
- Mahmoodinasab M, Loripoor M, Vazirinejad R, Aminzadeh F. Effect of misoprostol with and without evening primrose (Oenothera biennis) on induction of missed abortion. Avicenna J Phytomed 2023;13(5):454-462.
- Hashemi H, Hasanpoor-Azghady SB, Farahani M, Amiri-Farahani L. Comparison of the effect of vaginal misoprostol and evening primrose oil capsule with misoprostol alone on the consequences of abortion in women with intrauterine fetal death: a randomized cli
- Ariana S, Amjadi N, Kazemi SN, Ahmadli Z. The Use of Evening Primrose Oil for Cervical Ripening in Low-Risk Women with Term Pregnancy: A Randomized Double-Blinded Controlled Trial. Complement Med Res 2024;31(3):215-221. PubMed
Chondroitin Sulfate 22 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Tallia AF, Cardone DA. Asthma exacerbation associated with glucosamine-chondroitin supplement. J Am Board Fam Pract 2002;15:481-4..
- Danao-Camara T. Potential side effects of treatment with glucosamine and chondroitin. Arthritis Rheum 2000;43:2853. PubMed
- Rozenfeld V, Crain JL, Callahan AK. Possible augmentation of warfarin effect by glucosamine-chondroitin. Am J Health Syst Pharm 2004;61:306-307. PubMed
- Clegg DO, Reda DJ, Harris CL, et al. Glucosamine, chondroitin sulfate, and the two in combination for painful knee osteoarthritis. N Engl J Med 2006;354:795-808. DOI
- Knudsen J, Sokol GH. Potential glucosamine-warfarin interaction resulting in increased international normalized ratio: Case report and review of the literature and MedWatch database. Pharmacotherapy 2008;28:540-8. PubMed
- Yue QY, Strandell J, Myrberg O. Concomitant use of glucosamine potentiates the effect of warfarin. Jan 2006. Drug Safety 29(10):911-1010. DOI
- Nordling, J. and van, Ophoven A. Intravesical glycosaminoglycan replenishment with chondroitin sulphate in chronic forms of cystitis. A multi-national, multi-centre, prospective observational clinical trial. Arzneimittelforschung. 2008;58(7):328-335. PubMed
- Nickel, J. C., Egerdie, B., Downey, J., Singh, R., Skehan, A., Carr, L., and Irvine-Bird, K. A real-life multicentre clinical practice study to evaluate the efficacy and safety of intravesical chondroitin sulphate for the treatment of interstitial cystit
- Oliviero, U., Sorrentino, G. P., De Paola, P., Tranfaglia, E., D'Alessandro, A., Carifi, S., Porfido, F. A., Cerio, R., Grasso, A. M., Policicchio, D., and . Effects of the treatment with matrix on elderly people with chronic articular degeneration. Drug
- Crowley, D. C., Lau, F. C., Sharma, P., Evans, M., Guthrie, N., Bagchi, M., Bagchi, D., Dey, D. K., and Raychaudhuri, S. P. Safety and efficacy of undenatured type II collagen in the treatment of osteoarthritis of the knee: a clinical trial. Int.J.Med.Sc PubMed
- Nickel, J. C., Egerdie, R. B., Steinhoff, G., Palmer, B., and Hanno, P. A multicenter, randomized, double-blind, parallel group pilot evaluation of the efficacy and safety of intravesical sodium chondroitin sulfate versus vehicle control in patients with
- Sawitzke, A. D., Shi, H., Finco, M. F., Dunlop, D. D., Harris, C. L., Singer, N. G., Bradley, J. D., Silver, D., Jackson, C. G., Lane, N. E., Oddis, C. V., Wolfe, F., Lisse, J., Furst, D. E., Bingham, C. O., Reda, D. J., Moskowitz, R. W., Williams, H. J.
- Wildi, L. M., Raynauld, J. P., Martel-Pelletier, J., Beaulieu, A., Bessette, L., Morin, F., Abram, F., Dorais, M., and Pelletier, J. P. Chondroitin sulphate reduces both cartilage volume loss and bone marrow lesions in knee osteoarthritis patients starti
- Pavelka and et al. Double-blind, dose effect study of oral cs 4 & 6 1200mg, 800mg, 200mg against placebo in the treatment of femorotibial osteoarthritis. Wular Rheumatol Liter 1998;27(suppl 2):63.
- Cerda C, Bruguera M, Parés A. Hepatotoxicity associated with glucosamine and chondroitin sulfate in patients with chronic liver disease. World J Gastroenterol 2013;19(32):5381-4. PubMed
- von Felden J, Montani M, Kessebohm K, Stickel F. Drug-induced acute liver injury mimicking autoimmune hepatitis after intake of dietary supplements containing glucosamine and chondroitin sulfate. Int J Clin Pharmacol Ther 2013;51(3):219-23. PubMed
- Provenza JR, Shinjo SK, Silva JM, Peron CR, Rocha FA. Combined glucosamine and chondroitin sulfate, once or three times daily, provides clinically relevant analgesia in knee osteoarthritis. Clin Rheumatol 2015;34:1455-62. PubMed
- Ossendza RA, Grandval P, Chinoune F, Rocher F, Chapel F, Bernardini D. [Acute cholestatic hepatitis due to glucosamine forte]. Gastroenterol Clin Biol. 2007 Apr;31(4):449-50.
- Greenlee H, Crew KD, Shao T, Kranwinkel G, Kalinsky K, Maurer M, Brafman L, Insel B, Tsai WY, Hershman DL. Phase II study of glucosamine with chondroitin on aromatase inhibitor-associated joint symptoms in women with breast cancer. Support Care Cancer 201 PubMed
- Chu EC, Huang KHK, Cheung G, Ng G, Lin A. Delayed Skin Allergy to Glucosamine Chondroitin Supplement. Cureus 2023;15(3):e36310. PubMed
- Lila AM, Alekseeva LI, Baranov AA, et al. Chondroitin sulfate and glucosamine combination in patients with knee and hip osteoarthritis: A long-term observational study in Russia. World J Orthop 2023;14(6):443-457. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC