
High Potency Iron 36 mg Ingredients & Drug Interactions
What is this page for?
First and foremost: checking High Potency Iron 36 mg against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
High Potency Iron 36 mg is a dietary supplement by Protocol For Life Balance with 1 active ingredient. Its ingredients are commonly taken for iron-deficiency anemia, low iron stores during pregnancy, fatigue from iron deficiency.Based on those ingredients, 80 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Iron. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against High Potency Iron 36 mg by Protocol For Life Balance
Ask about any prescription or over-the-counter medication and we check it for interactions with High Potency Iron 36 mg by Protocol For Life Balance — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of High Potency Iron 36 mg by Protocol For Life Balance
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
This product contains one active ingredient: iron 36 mg per capsule, a mineral your body uses to carry oxygen in your blood and support energy production. The remaining ingredients are inactive — rice flour, cellulose, stearic acid, and silica — which are fillers and binders that hold the capsule together.
Does it work?
Strong evidence
Iron is effective for treating iron deficiency anemia (the most common form) and anemia of chronic disease, where your body either doesn't have enough iron or can't use it properly. It's also effective for iron deficiency that develops during pregnancy.
For heart failure, the evidence is less complete — iron is possibly effective, which means there's some data suggesting it may help, but the evidence isn't as strong or established.
How safe is it?
Well-documented data
Iron is generally well tolerated when you take the recommended dose, but excess iron can be toxic, so use it only when there's a real need — don't take it as general insurance. The most common side effects are gastrointestinal: abdominal pain, constipation, diarrhea, nausea, and vomiting.
Serious side effects are rare but have included reports of stomach or intestinal ulcers. During pregnancy, iron is often recommended and considered likely safe, but your prenatal care provider should guide the dose for your situation.
While breastfeeding, iron at appropriate doses is generally considered acceptable, though check with your provider first. There's been some debate in the research about whether very high iron intake or high iron stores raise the risk of heart disease, but the majority of studies have found no link.
Meds to double-check
Moderate interaction found
If you take any levodopa (Parkinson's), tetracycline or quinolone antibiotics, bisphosphonates (osteoporosis medication), levothyroxine (thyroid), methyldopa (blood pressure), mycophenolate mofetil (immunosuppressant), or penicillamine, double-check the spacing requirements with your pharmacist before adding this iron supplement — all of these are Moderate severity interactions that you can manage by separating doses.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
If you have iron deficiency anemia or a related condition and your doctor or pharmacist has recommended this product, it's effective and generally well tolerated at the dose prescribed. However, if you take any medications — especially antibiotics, thyroid medication, bisphosphonates, or drugs for Parkinson's disease or blood pressure — you'll need to space out your doses carefully or you may end up with medication that doesn't work as well.
Talk to your pharmacist before you start.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 1 of 1 active ingredient matched to our full ingredient reviews (monographs). Based on the product label dated Mar 25, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about High Potency Iron 36 mg, straight from the product label.
| Brand | Protocol For Life Balance |
|---|---|
| Barcode (UPC) | 707359114449 |
| Net contents | 90 Veg Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Mar 25, 2025 |
| DSLD ID | 326443 |
| Product type | Mineral |
| Supplement form | Capsule |
| Dietary claims / uses | Nutrient, All Other, Structure/Function |
| Intended target group(s) | Vegan, Vegetarian, Adult (18 - 50 Years), Gluten Free, Dairy Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for High Potency Iron 36 mg by Protocol For Life Balance, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Iron | 36 mg | 200% |
Other ingredients: Rice Flour, Cellulose, Stearic Acid, Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Suggested/Recommended/Usage/Directions
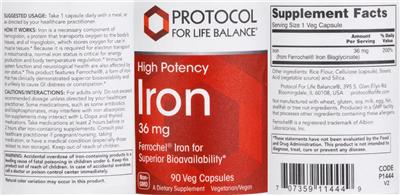
Suggested usage: Take 1 capsule daily with a meal, or as directed by your healthcare practitioner.
Formulation
How it works: Iron is a necessary component of hemoglobin, a protein that transports oxygen to the body's tissues, and of myoglobin, which stores oxygen for use in muscle tissue. Because it is required for electron transport in mitochondria, normal iron status is critical for energy production and body temperature regulation. Immune system function and neurological health are also affected by iron status.
Natural color variation may occur in this product.
Non-GMO
Vegetarian/vegan
Not manufactured with wheat, gluten, soy, milk, egg, fish, shellfish or tree nut ingredients.
Formula
This product features Ferrochel, a form of iron that has clinically demonstrated superior bioavailability and is unlikely to cause GI distress or constipation.
Ferrochel Iron for superior bioavailability
Precautions
Cautions/interactions: For adults only. Keep out of reach of children.
Do not exceed recommended dosage unless directed by your healthcare practitioner.
Some medications, such as some antibiotics and bisphosphonates, may interfere with iron absorption. Iron supplements may interact with L-Dopa and thyroid medications. Take medications at least 2 hours before or 2 hours after iron-containing supplements. Consult your healthcare practitioner if pregnant/nursing, taking medication, or have a medical condition (especially those related to iron storage).
Warning: Accidental overdose of iron containing products is a leading cause of fatal poisoning in children under 6. Keep this product out of reach of children. In case of accidental overdose, call a doctor or poison control center immediately.
Not manufactured with wheat, gluten, soy, milk, egg, fish, shellfish or tree nut ingredients. Produced in a GMP facility that processes other ingredients containing these allergens.
FDA Statement of Identity
A Dietary Supplement
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
High Potency Iron 36 mg by Protocol For Life Balance label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in High Potency Iron 36 mg by Protocol For Life Balance
This is the 1 active ingredient this product is made of. Select it to open its full monograph.
Serving size1 Veg Capsule(s) Dosage formCapsule Servings per container90 Amounts shown are per serving.
Iron
Interacts with80 drugs
Iron is an essential mineral your body needs to make hemoglobin and carry oxygen in the blood. Supplements are mainly useful for treating or preventin...
Iron monograph & interactionsOther (inactive) ingredients: Rice Flour, Cellulose, Stearic Acid, Silica. These complete the product’s ingredient list but are not active constituents.
High Potency Iron 36 mg by Protocol For Life Balance Drug Interactions
HelloPharmacist Interaction Report
High Potency Iron 36 mg by Protocol For Life Balance does interact with a number of medications.
Iron's main mechanism is binding to drugs in your stomach and gut, which stops your body from absorbing them properly — essentially locking them up so they can't work.
Read the full breakdown — every affected drug type, severity by severity
The most serious interactions are Moderate in severity. Iron can reduce absorption of levodopa (used for Parkinson's disease) by roughly half, which may weaken its effect on your symptoms.
It also significantly reduces absorption of tetracycline antibiotics — by 50 to 90 percent — so those antibiotics won't work as well to fight infection. Similarly, iron binds to quinolone antibiotics (like ciprofloxacin), bisphosphonates (osteoporosis medications), levothyroxine (thyroid hormone), methyldopa (blood pressure medicine), mycophenolate mofetil (an immunosuppressant), and penicillamine (used for Wilson's disease and rheumatoid arthritis), lowering levels of all of them.
The good news: you can prevent most of these interactions by spacing doses. For tetracycline antibiotics, take iron at least 2 hours before or 4 hours after.
For levodopa, quinolones, levothyroxine, methyldopa, and penicillamine, separate doses by at least 2 hours. For mycophenolate mofetil and bisphosphonates, allow 4 to 6 hours before, or 2 hours after.
Altogether, these interactions span 79 individual medications. Use the medication checker on this page to verify your exact prescriptions before you start.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against High Potency Iron 36 mg?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in High Potency Iron 36 mg interact with 80 drugs. Click any drug to see the details.
1 of the 1 ingredient in High Potency Iron 36 mg interact with drugs. Each result below shows which ingredient is responsible. Iron
AlendronateBinosto, Fosamax
How Alendronate interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBisphosphonates Moderate
Interaction Summary
Iron reduces the absorption of bisphosphonates.
Read the full Iron + Alendronate interactionAlendronate Sodium
How Alendronate Sodium interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBisphosphonates Moderate
Interaction Summary
Iron reduces the absorption of bisphosphonates.
Read the full Iron + Alendronate Sodium interactionAlendronate Sodium, CholecalciferolFosamax Plus D
How Alendronate Sodium, Cholecalciferol interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBisphosphonates Moderate
Interaction Summary
Iron reduces the absorption of bisphosphonates.
Read the full Iron + Alendronate Sodium, Cholecalciferol interactionAmphotericin, TetracyclineMysteclin-F
How Amphotericin, Tetracycline interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Amphotericin, Tetracycline interactionBenserazide, LevodopaMadopar, Prolopa
How Benserazide, Levodopa interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronLevodopa Moderate
Interaction Summary
Iron might decrease levodopa levels by reducing its absorption.
Read the full Iron + Benserazide, Levodopa interactionBictegravir, Emtricitabine, Tenofovir AlafenamideBiktarvy
How Bictegravir, Emtricitabine, Tenofovir Alafenamide interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Bictegravir, Emtricitabine, Tenofovir Alafenamide interactionBismuth Subsalicylate, Metronidazole, TetracyclineHelidac
How Bismuth Subsalicylate, Metronidazole, Tetracycline interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Bismuth Subsalicylate, Metronidazole, Tetracycline interactionCarbidopa, LevodopaDhivy, Rytary, Sinemet, Sinemet CR
How Carbidopa, Levodopa interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronLevodopa Moderate
Interaction Summary
Iron might decrease levodopa levels by reducing its absorption.
Read the full Iron + Carbidopa, Levodopa interactionCarbidopa, Levodopa, EntacaponeStalevo
How Carbidopa, Levodopa, Entacapone interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronLevodopa Moderate
Interaction Summary
Iron might decrease levodopa levels by reducing its absorption.
Read the full Iron + Carbidopa, Levodopa, Entacapone interactionChlorothiazide, MethyldopaAldochlor, Aldoclor 150, Aldoclor 250
How Chlorothiazide, Methyldopa interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronMethyldopa (aldomet) Moderate
Interaction Summary
Iron might decrease methyldopa levels by reducing its absorption.
Read the full Iron + Chlorothiazide, Methyldopa interactionChlortetracyclineAureomycin
How Chlortetracycline interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Chlortetracycline interactionCinoxacinCinobac
How Cinoxacin interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronQuinolone Antibiotics Moderate
Interaction Summary
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Read the full Iron + Cinoxacin interactionCiprofloxacinCiloxan, Cipro, Cipro IV, Cipro XR, Ciprobay, Otiprio
How Ciprofloxacin interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronQuinolone Antibiotics Moderate
Interaction Summary
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Read the full Iron + Ciprofloxacin interactionClinafloxacinClinafloxacin
How Clinafloxacin interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronQuinolone Antibiotics Moderate
Interaction Summary
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Read the full Iron + Clinafloxacin interactionCobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide FumarateGenvoya
How Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Cobicistat, Elvitegravir, Emtricitabine, Tenofovir Alafenamide Fumarate interactionDarunavir, Cobicistat, Emtricitabine, Tenofovir AlafenamideSymtuza
How Darunavir, Cobicistat, Emtricitabine, Tenofovir Alafenamide interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Darunavir, Cobicistat, Emtricitabine, Tenofovir Alafenamide interactionDemeclocyclineDeclomycin
How Demeclocycline interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Demeclocycline interactionDenosumabProlia, XGEVA
How Denosumab interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronDenosumab (prolia, Others) Moderate
Interaction Summary
Administration of intravenous iron within one month of denosumab administration might increase the risk of severe hypophosphatemia and hypocalcemia.
Read the full Iron + Denosumab interactionDolutegravirTivicay
How Dolutegravir interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronDolutegravir (tivicay) Moderate
Interaction Summary
Iron might decrease dolutegravir levels by reducing its absorption.
Read the full Iron + Dolutegravir interactionDolutegravir, Emtricitabine, Tenofovir AlafenamideDolutegravir, Emtricitabine, Tenofovir Alafenamide
How Dolutegravir, Emtricitabine, Tenofovir Alafenamide interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronDolutegravir (tivicay), Bictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease dolutegravir levels by reducing its absorption.
Read the full Iron + Dolutegravir, Emtricitabine, Tenofovir Alafenamide interactionDolutegravir, RilpivirineJuluca
How Dolutegravir, Rilpivirine interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronDolutegravir (tivicay) Moderate
Interaction Summary
Iron might decrease dolutegravir levels by reducing its absorption.
Read the full Iron + Dolutegravir, Rilpivirine interactionDoripenemDoribax
How Doripenem interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronQuinolone Antibiotics, Tetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Read the full Iron + Doripenem interactionDoxycyclineDoryx, Doxy, Doxy-D, Doxycin, Doxycycline Injection, Doxylin +6 more
How Doxycycline interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Doxycycline interactionDoxycycline HyclateActiclate, Acticlate Cap, Lymepak
How Doxycycline Hyclate interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Doxycycline Hyclate interactionDoxycycline MonohydrateErfacea
How Doxycycline Monohydrate interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Doxycycline Monohydrate interactionDoxycylineDoxychel
How Doxycyline interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronTetracycline Antibiotics Moderate
Interaction Summary
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Read the full Iron + Doxycyline interactionElvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil FumarateStribild
How Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Elvitegravir, Cobicistat, Emtricitabine, Tenofovir Disoproxil Fumarate interactionEmtricitabineEmtriva
How Emtricitabine interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Emtricitabine interactionEmtricitabine, Rilpivirine, TenofovirComplera
How Emtricitabine, Rilpivirine, Tenofovir interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Emtricitabine, Rilpivirine, Tenofovir interactionEmtricitabine, Rilpivirine, Tenofovir AlafenamideOdefsey
How Emtricitabine, Rilpivirine, Tenofovir Alafenamide interacts with High Potency Iron 36 mg — through 1 ingredient. Tap an ingredient for the detail:
IronBictegravir/emtricitabine/tenofovir Alafenamide (biktarvy) Moderate
Interaction Summary
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Read the full Iron + Emtricitabine, Rilpivirine, Tenofovir Alafenamide interactionEach ingredient & the kinds of drugs it affects
For each ingredient in High Potency Iron 36 mg with known interactions, here are the types of medications it can affect. Open any type for the detail — or search your exact drug in the checker above.
Iron
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and iron can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, iron containing products.
Bisphosphonates
Iron reduces the absorption of bisphosphonates.
Advise patients that doses of bisphosphonates should be separated by at least two hours from doses of all other medications, including supplements such as iron. Divalent cations, including iron, can decrease absorption of bisphosphonates by forming insoluble complexes in the gastrointestinal tract.
Denosumab (Prolia, Others)
Administration of intravenous iron within one month of denosumab administration might increase the risk of severe hypophosphatemia and hypocalcemia.
A case of severe hypocalcemia (albumin corrected calcium 6.88 mg/dL, ionized calcium 3.68 mg/dL) and hypophosphatemia (<0.5 mg/dL) with respiratory acidosis, QT interval prolongation, and nonsustained ventricular tachycardia was reported in a 76-year-old male who had received an iron polymaltose infusion within 2 weeks of a subcutaneous injection of denosumab. Serum parathyroid hormone was also elevated (348 pg/mL). Subsequent iron infusions with iron polymaltose and ferric carboxymaltose were followed by transient hypophosphatemia, but without hypocalcemia. Additionally, a literature review describes 6 additional cases of hypophosphatemia and hypocalcemia in patients 52-92 years of age who had been administered intravenous iron as either ferric carboxymaltose or iron polymaltose and subcutaneous denosumab within 1-4 weeks of each other.
Dolutegravir (Tivicay)
Iron might decrease dolutegravir levels by reducing its absorption.
Advise patients to take dolutegravir at least 2 hours before or 6 hours after taking iron. Pharmacokinetic research shows that iron can decrease the absorption of dolutegravir from the gastrointestinal tract through chelation. When taken under fasting conditions, a single dose of ferrous fumarate 324 mg orally along with dolutegravir 50 mg reduces overall exposure to dolutegravir by 54%.
Integrase Inhibitors
Theoretically, taking iron along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Iron is a divalent cation. There is concern that iron may decrease the absorption of integrase inhibitors from the gastrointestinal tract through chelation. One pharmacokinetic study shows that iron can decrease blood levels of the specific integrase inhibitor dolutegravir through chelation. Also, other pharmacokinetic research shows that other divalent cations such as calcium can decrease the absorption and levels of some integrase inhibitors through chelation.
Levodopa
Iron might decrease levodopa levels by reducing its absorption.
Advise patients to separate doses of levodopa and iron as much as possible. There is some evidence in healthy people that iron forms chelates with levodopa, reducing the amount of levodopa absorbed by around 50%. The clinical significance of this hasn't been determined.
Levothyroxine (Synthroid, Others)
Iron might decrease levothyroxine levels by reducing its absorption.
Advise patients to separate levothyroxine and iron doses by at least 2 hours. Iron can decrease the absorption and efficacy of levothyroxine by forming insoluble complexes in the gastrointestinal tract.
Methyldopa (Aldomet)
Iron might decrease methyldopa levels by reducing its absorption.
Advise patients to separate methyldopa and iron doses by at least 2 hours. Iron can decrease the absorption of methyldopa from the gastrointestinal tract through chelation, resulting in increases in blood pressure.
Mycophenolate Mofetil (Cellcept)
Theoretically, iron might decrease mycophenolate mofetil levels by reducing its absorption.
Advise patients to take iron 4-6 hours before, or 2 hours after, mycophenolate mofetil. It has been suggested that a decrease of absorption is possible, probably by forming nonabsorbable chelates. However, mycophenolate pharmacokinetics are not affected by iron supplementation in available clinical research.
Penicillamine (Cuprimine, Depen)
Iron might decrease penicillamine levels by reducing its absorption.
Advise patients to separate penicillamine and iron doses by at least 2 hours. Oral iron supplements can reduce absorption of penicillamine by 30% to 70%, probably due to chelate formation. In people with Wilson's disease, this interaction has led to reduced efficacy of penicillamine.
Quinolone Antibiotics
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Advise patients to separate quinolone antibiotics and iron doses by at least 2 hours. Iron decreases the absorption of quinolones due to formation of insoluble complexes in the gastrointestinal tract.
Tetracycline Antibiotics
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Advise patients to take iron at least 2 hours before or 4 hours after tetracycline antibiotics. Concomitant use can decrease absorption of tetracycline antibiotics from the gastrointestinal tract by 50% to 90%.
Chloramphenicol
Theoretically, taking chloramphenicol with iron might reduce the response to iron therapy in iron deficiency anemia.
Chloramphenicol interferes with erythrocyte maturation. However, since chloramphenicol isn't usually taken for prolonged periods, this isn't likely to be clinically significant.
Brand information
Manufacturer and brand details for High Potency Iron 36 mg, from the product label.
Protocol For Life Balance
See all Protocol For Life Balance products- Name
- Protocol For Life Balance
- Street Address
- 395 S. Glen Ellyn Rd.
- City
- Bloomingdale
- State
- IL
- ZipCode
- 60108
- Web Address
- protocolforlife.com
High Potency Iron 36 mg by Protocol For Life Balance: Common Questions
Does High Potency Iron 36 mg by Protocol For Life Balance interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Will iron help my energy if I don't have anemia?
What are the most common side effects?
Can I take this iron while I'm pregnant?
Is it safe to breastfeed while taking this?
Why can't I take this iron with my antibiotic?
Will iron interact with my thyroid medication?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if High Potency Iron 36 mg is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind High Potency Iron 36 mg’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sources & How We Checked
High Potency Iron 36 mg's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 72 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Iron 72 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Bruner AB, Joffe A, Duggan AK, et al. Randomized study of cognitive effects of iron supplementation in non- anaemic iron-deficient adolescent girls. Lancet 1996;348:992-6.
- Ullen H, Augustsson K, Gustavsson C, Steineck G. Supplementary iron intake and risk of cancer: reversed causality? Cancer Lett 1997;114:215-6.
- Reunanen A, Takkunen H, Knekt P, et al. Body iron stores, dietary iron intake and coronary heart disease mortality. J Intern Med 1995;238:223-30. PubMed
- Lund EK, Wharf SG, Fairweather-Tait SJ, Johnson IT. Oral ferrous sulfate supplements increase the free radical-generating capacity of feces from healthy volunteers. Am J Clin Nutr 1999;69:250-5.
- Rehman A, Collis CS, Yang M, et al. The effects of iron and vitamin C co-supplementation on oxidative damage to DNA in healthy volunteers. Biochem Biophys Res Comm 1998;246:293-8. PubMed
- Klipstein-Grobusch K, Grobbee DE, den Breeijen JH, et al. Dietary iron and risk of myocardial infarction in the Rotterdam Study. Am J Epidemiol 1999;149:421-8. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Campbell N, Paddock V, Sundaram R. Alteration of methyldopa absorption, metabolism, and blood pressure control by ferrous sulfate and ferrous gluconate. Clin Pharmacol Ther 1988;43:381-6..
- Schumann K, Borch-Iohnsen B, Hentze MW, Marx JJ. Tolerable upper intakes for dietary iron set by the US Food and Nutrition Board (commentary). Am J Clin Nutr 2002;76:499-500. PubMed
- Tuomainen TP, Punnonen K, Nyyssonen K, Salonen JT. Association between body iron stores and the risk of acute myocardial infarction in men. Circulation 1998;97:1461-6.. PubMed
- Salonen JT, Nyyssonen K, Korpela H, et al. High stored iron levels are associated with excess risk of myocardial infarction in Eastern Finnish men. Circulation 1992;86:803-11.. PubMed
- Campbell NRC, Hasinoff B. Ferrous sulfate reduces levodopa bioavailability: Chelation as a possible mechanism. Clin Pharmacol Ther 1989;45:220-5.. PubMed
- Campbell NRC, Hasinoff BB, Stalts H, et al. Ferrous sulfate reduces thyroxine efficacy in patients with hypothyroidism. Ann Int Med 1992;117:1010-3.. PubMed
- Kiechl S, Willeit J, Egger G, et al. Body iron stores and the risk of carotid atherosclerosis: prospective results from the Bruneck study. Circulation 1997;96:3300-07. PubMed
- Comparison of oral iron supplements. Pharmacist's Letter / Prescriber's Letter 2008;24(8):240811.
- Tran T., Wax J. R., Philput C., Steinfeld J. D., Ingardia C. J. Intentional iron overdose in pregnancy--management and outcome. J Emerg Med 2000;18(2):225-228. PubMed
- Toblli J. E., Brignoli, R. Iron(III)-hydroxide polymaltose complex in iron deficiency anemia / review and meta-analysis. Arzneimittelforschung 2007;57(6A):431-438. PubMed
- Köpcke W., Sauerland M. C. Meta-analysis of efficacy and tolerability data on iron proteinsuccinylate in patients with iron deficiency anemia of different severity. Arzneimittelforschung 1995;45(11):1211-1216.
- Campbell N. R., Campbell R. R., Hasinoff B. B. Ferrous sulfate reduces methyldopa absorption: methyldopa: iron complex formation as a likely mechanism. Clin Invest Med 1990;13(6):329-332.
- Morii M., Ueno K., Ogawa A., Kato R., Yoshimura H., Wada K., Hashimoto H., Takada M., Tanaka K., Nakatani T., Shibakawa M. Impairment of mycophenolate mofetil absorption by iron ion. Clin Pharmacol Ther 2000;68(6):613-616. PubMed
- Gelone D. K., Park J. M., Lake K. D. Lack of an effect of oral iron administration on mycophenolic acid pharmacokinetics in stable renal transplant recipients. Pharmacotherapy 2007;27(9):1272-1278. PubMed
- Ducray P. S., Banken L., Gerber M., Boutouyrie B., Zandt H. Absence of an interaction between iron and mycophenolate mofetil absorption. Br J Clin Pharmacol 2006;62(4):492-495. PubMed
- Lorenz M., Wolzt M., Weigel G., Puttinger H., Hörl W. H., Födinger M., Speiser W., Sunder-Plassmann G. Ferrous sulfate does not affect mycophenolic acid pharmacokinetics in kidney transplant patients. Am J Kidney Dis 2004;43(6):1098-1103. PubMed
- Osman M. A., Patel R. B., Schuna A., Sundstrom W. R., Welling P. G. Reduction in oral penicillamine absorption by food, antacid, and ferrous sulfate. Clin Pharmacol Ther 1983;33(4):465-470. PubMed
- Michael, B., Coyne, D. W., Fishbane, S., Folkert, V., Lynn, R., Nissenson, A. R., Agarwal, R., Eschbach, J. W., Fadem, S. Z., Trout, J. R., Strobos, J., and Warnock, D. G. Sodium ferric gluconate complex in hemodialysis patients: adverse reactions compar
- Zhang, X., Ouyang, J., Wieczorek, R., and DeSoto, F. Iron medication-induced gastric mucosal injury. Pathol.Res Pract 2009;205(8):579-581. PubMed
- Barbieri, P. G. [To-day exposure to occupational carcinogens and their effects. The experience of the rubber industry, iron metallurgy, asphalt work and aviculture]. Epidemiol.Prev 2009;33(4-5 Suppl 2):94-105.
- Macedo, A. and Cardoso, S. [Routine iron supplementation in pregnancy]. Acta Med Port. 2010;23(5):785-792.
- Bastide, N. M., Pierre, F. H., and Corpet, D. E. Heme iron from meat and risk of colorectal cancer: a meta-analysis and a review of the mechanisms involved. Cancer Prev Res (Phila) 2011;4(2):177-184. PubMed
- Stevens, R. G. Iron and the risk of cancer. Med Oncol Tumor Pharmacother. 1990;7(2-3):177-181. PubMed
- van den, Hombergh J., Dalderop, E., and Smit, Y. Does iron therapy benefit children with severe malaria-associated anaemia? A clinical trial with 12 weeks supplementation of oral iron in young children from the Turiani Division, Tanzania. J.Trop.Pediatr. PubMed
- Liabeuf S, Gras V, Moragny J, et al. Ulceration of the oral mucosa following direct contact with ferrous sulfate in elderly patients: a case report and a review of the French National Pharmacovigilance Database. Clin Interv Aging. 2014 Apr 25;9:737-40. PubMed
- Qiao L, Feng Y. Intakes of heme iron and zinc and colorectal cancer incidence: a meta-analysis of prospective studies. Cancer Causes Control. 2013 Jun;24(6):1175-83. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Song I, Borland J, Arya N, Wynne B, Piscitelli S. Pharmacokinetics of dolutegravir when administered with mineral supplements in healthy adult subjects. J Clin Pharmacol. 2015;55(5):490-6. PubMed
- Esan MO, Boele van Hensbroek M, Nkhoma E, et al. Iron supplementation in HIV infected Malawian children with anemia: a double-blind, randomized, controlled trial. Clin Inf Dis 2013;57(11):1626-34.doi:10.1093/cid/cit528. PubMed
- Zlotkin S, Newton S, Aimone AM, et al. Effect of iron fortification on malaria incidence in infants and young children in Ghana: a randomized trial. JAMA 2013;310(9):938-47. PubMed
- Khambalia AZ, Aimone A, Nagubandi P, et al. High maternal iron status, dietary iron intake and iron supplement use in pregnancy and risk of gestational diabetes mellitus: a prospective study and systematic review. Diabet Med. 2016;33(9):1211-21. PubMed
- Kinnunen TI, Luoto R, Helin A, Hemminki E. Supplemental iron intake and the risk of glucose intolerance in pregnancy: re-analysis of a randomised controlled trial in Finland. Matern Child Nutr. 2016;12(1):74-84.
- Low MS, Speedy J, Styles CE, De-Regil LM, Pasricha SR. Daily iron supplementation for improving anaemia, iron status and health in menstruating women. Cochrane Database Syst Rev. 2016;4:CD009747. PubMed
- Melit LE, Marginean CO, Mocanu S, Marginean MO. A rare case of iron-pill induced gastritis in a female teenager: A case report and a review of the literature. Medicine (Baltimore). 2017;96(30):e7550. PubMed
- Neuberger A, Okebe J, Yahav D, Paul M. Oral iron supplements for children in malaria-endemic areas. Cochrane Database Syst Rev. 2016;2:CD006589. PubMed
- Peña-Rosas JP, De-Regil LM, Gomez Malave H, Flores-Urrutia MC, Dowswell T. Intermittent oral iron supplementation during pregnancy. Cochrane Database Syst Rev. 2015;(10):CD009997. PubMed
- Brabin B, Gies S, Roberts SA, et al. Excess risk of preterm birth with periconceptional iron supplementation in a malaria endemic area: analysis of secondary data on birth outcomes in a double blind randomized controlled safety trial in Burkina Faso. Mala PubMed
- Kaundal R, Bhatia P, Jain A, et al. Randomized controlled trial of twice-daily versus alternate-day oral iron therapy in the treatment of iron-deficiency anemia. Ann Hematol 2020;99(1):57-63. PubMed
- Li N, Zhao G, Wu W, et al. The efficacy and safety of vitamin C for iron supplementation in adult patients with iron deficiency anemia: A randomized clinical trial. JAMA Netw Open. 2020;3(11):e2023644.<br> PubMed
- Houston BL, Hurrie D, Graham J, et al. Efficacy of iron supplementation on fatigue and physical capacity in non-anaemic iron-deficient adults: a systematic review of randomised controlled trials. BMJ Open. 2018;8(4):e019240. PubMed
- Koch RM, Tchernodrinski S, Principe DR. Case report: Rapid onset, ischemic-type gastritis after initiating oral iron supplementation. Front Med (Lausanne) 2022;9:1010897. PubMed
- Milman NT. Iron supplementation in pregnant Danish women revisited: Effects on prepartum and postpartum iron deficiency, anemia, serum erythropoietin; including iron status, erythropoietin and anthropometrics in newborns. A randomized, placebo-controlled
- Rogozinska E, Daru J, Nicolaides M, et al. Iron preparations for women of reproductive age with iron deficiency anaemia in pregnancy (FRIDA): a systematic review and network meta-analysis. Lancet Haematol 2021;8(7):e503-e512. PubMed
- Shah AA, Donovan K, Seeley C, et al. Risk of infection associated with administration of intravenous iron: A systematic review and meta-analysis. JAMA Netw Open 2021;4(11):e2133935. PubMed
- Gamad N, Saha PK, Sharma P, Suri V, Chakrabarti A, Saha L. A randomized controlled trial comparing the efficacy, tolerability, and cost of oral iron preparations in iron-deficiency anemia in pregnancy. J Obstet Gynaecol Res 2021;47(11):3828-3841. PubMed
- El-Hawy MA, Abd Al-Salam SA, Bahbah WA. Comparing oral iron bisglycinate chelate, lactoferrin, lactoferrin with iron and iron polymaltose complex in the treatment of children with iron deficiency anemia. Clin Nutr ESPEN 2021;46:367-371. PubMed
- Adams A, Scheckel B, Habsaoui A, et al. Intravenous iron versus oral iron versus no iron with or without erythropoiesis- stimulating agents (ESA) for cancer patients with anaemia: a systematic review and network meta-analysis. Cochrane Database Syst Rev 2 PubMed
- Kancherla K, Constantin H, Kanawati A, Graham E. Iron-induced Hypophosphatemic Osteomalacia-An Atypical Case of Bilateral Femoral Stress Fractures. J Am Acad Orthop Surg Glob Res Rev 2023;7(5):e22. PubMed
- Shi R, Marin JG, Beaulieu M. Skin staining following intravenous iron extravasation in a patient with chronic kidney disease: A case report. Can J Kidney Health Dis 2023;10:20543581231165705. PubMed
- Varandas C, Vieira J, Correia CJ, et al. Hypersensitivity reactions to iron products: 10-year experience in a Portuguese tertiary Centre. Eur Ann Allergy Clin Immunol 2023.
- Jara Vidal M, López García MC, Quílez Toboso RP. Kounis syndrome after intravenous iron administration. Med Clin (Barc) 2023. DOI
- Jara Vidal M, Ruiz de Assín Valverde A, Aznar Rodríguez S. Severe hypophospathemia secondary to intravenous iron. Med Clin (Barc) 2023. DOI
- Samões B, Silva B, Martins A, et al. Hypophosphatemic osteomalacia induced by intravenous iron therapy: a case report. Joint Bone Spine 2023;90(5):105586. PubMed
- Seng NW, Barco JB, Wong MH, et al. Hypophosphatemia related to intravenous iron therapy with ferric carboxymaltose: A case series. Transfus Med 2023. PubMed
- Fernandez-Flores A, Fernandez-Parrado M, Alzoghby-Abi Chaker J, Angulo AG. Axillary cutaneous hemosiderosis in a patient with hyperhidrosis, after intravenous iron infusion. Am J Dermatopathol 2023;45(7):463-465. PubMed
- Ye S, Grill V, Luo J, Nguyen HH. Concurrent Denosumab and Parenteral Iron Therapy Precipitating Severe Hypocalcemia and Hypophosphatemia. JCEM Case Rep 2024;2(2):luae005. PubMed
- Yerigeri K. Hemochromatosis in an Adult Female With Previous Iron Deficiency Anemia on Iron Supplementation. Cureus 2023;15(12):e50166. PubMed
- Meyers M, Salmon M, Libert I, Klášterský J. A meta-analysis on the risk of infection associated with intravenous iron therapy in cancer-associated anaemia: a double-edged sword?. Curr Opin Oncol 2024;36(4):223-232. PubMed
- Short V, Allen R, Earley CJ, et al. A randomized double-blind pilot study to evaluate the efficacy, safety, and tolerability of intravenous iron versus oral iron for the treatment of restless legs syndrome in patients with iron deficiency anemia. Am J Hem PubMed
- Bellos I, Frountzas M, Pergialiotis V. Comparative Risk of Hypophosphatemia Following the Administration of Intravenous Iron Formulations: A Network Meta-Analysis. Transfus Med Rev 2020;34(3):188-194. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC