
Optimized Tryptophan Plus Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Optimized Tryptophan Plus against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Optimized Tryptophan Plus is a dietary supplement by Life Extension with 5 active ingredients. Its ingredients are commonly taken for sleep problems, low mood and depression, anxiety.Based on those ingredients, 1,371 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Perluxan, Niacin, L-Tryptophan. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Optimized Tryptophan Plus by Life Extension
Ask about any prescription or over-the-counter medication and we check it for interactions with Optimized Tryptophan Plus by Life Extension — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Optimized Tryptophan Plus by Life Extension
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Partial disclosure
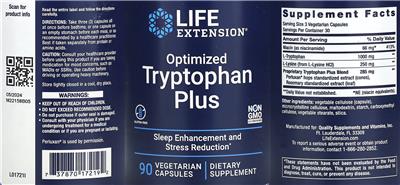
Optimized Tryptophan Plus contains 5 ingredients. The active components are L-tryptophan (an amino acid your body converts to serotonin and melatonin), niacin (a B vitamin), L-lysine (another amino acid), rosemary leaf extract, and hops extract (Perluxan).
The product also includes several inactive ingredients—cellulose, microcrystalline cellulose, maltodextrin, starch, carboxymethyl cellulose, stearate, and silica—which serve as fillers, binders, and flow agents in the capsule.
Does it work?
Not established
The evidence for this product's ingredients is mixed. L-tryptophan is rated possibly ineffective for depression and has insufficient evidence for anxiety, athletic performance, bruxism, and premenstrual dysphoric disorder.
Niacin is likely effective for pellagra (a rare B3-deficiency disease) and possibly effective for HIV-related lipid problems and metabolic syndrome. L-lysine is possibly effective for cold sores but has insufficient evidence for growth, pressure ulcers, and diabetic ulcers.
Rosemary leaf is possibly effective for memory but has insufficient evidence for cognitive decline, hair loss, and fatty liver disease. Hops extract (Perluxan) has insufficient evidence for anxiety, insomnia, ADHD, cognitive decline, sexual dysfunction, and digestion problems.
How safe is it?
Well-documented data
L-tryptophan is generally well tolerated but commonly causes belching, diarrhea, drowsiness, dry mouth, flatulence, headache, heartburn, lightheadedness, nausea, stomach pain, blurred vision, and vomiting. Rarely, it has been linked to eosinophilia-myalgia syndrome (EMS), a serious neurological disorder—though nearly all documented cases in the U.S. came from contaminated L-tryptophan from a single Japanese manufacturer in the late 1980s.
Niacin in high supplemental doses can cause flushing (up to 70% of users), liver problems, and gastrointestinal upset. L-lysine is generally well tolerated at typical doses but may cause stomach upset and abdominal pain; one rare case of kidney problems has been reported.
Rosemary extract can cause allergic reactions and, topically, photosensitivity or contact dermatitis. Hops is generally well tolerated short-term but may cause drowsiness; occupational exposure is linked to respiratory issues.
Pregnancy and breastfeeding: the safety data advises against L-tryptophan and hops in pregnancy; for L-lysine and rosemary, there isn't enough data to know either way, so talk with your doctor. For breastfeeding, the same caution applies to L-lysine, rosemary, and hops.
High-dose niacin should be avoided in pregnancy unless prescribed, but food amounts and standard prenatal vitamins are fine.
Meds to double-check
Major interaction found
Check before taking this product if you use CNS depressants (sleeping pills, anxiety drugs, narcotics—major severity), serotonergic drugs (antidepressants, migraine drugs), blood pressure drugs, blood thinners (anticoagulants or antiplatelet drugs), diabetes medications, statins, or aspirin and salicylate-containing pain relievers. All of these have documented moderate or major interactions with one or more ingredients here.
The bottom line
Scorecard at a glancePartially disclosed formula with no established evidence rating for its marketed use. Major medication interactions have been identified, and safety information is well characterized.
This product combines amino acids and botanicals with interactions affecting over 1,300 medications and serious CNS depressant concerns. If you take sedating drugs, blood thinners, diabetes medications, blood pressure drugs, or any serotonergic medication (like antidepressants), check your specific prescriptions before starting.
Pregnant or breastfeeding people should discuss it with their pharmacist or doctor first.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 5 of 5 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Apr 24, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Optimized Tryptophan Plus, straight from the product label.
| Brand | Life Extension |
|---|---|
| Barcode (UPC) | 737870172192 |
| Net contents | 90 Vegetarian Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Apr 24, 2025 |
| DSLD ID | 328618 |
| Product type | Botanical With Nutrients |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Optimized Tryptophan Plus by Life Extension, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| L-Tryptophan | 1000 mg | -- |
| Niacin | 66 mg NE | 413% |
| L-Lysine | 250 mg | -- |
| Rosemary Leaf Extract | 0 NP | -- |
| Proprietary Tryptophan Plus Blend | 285 mg | -- |
| Perluxan | 0 NP | -- |
Other ingredients: Cellulose, Microcrystalline Cellulose, Maltodextrin, Starch, Carboxymethyl Cellulose, Stearate, Silica
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
General Statements
Scan for product info
Precautions
Read the entire label and follow the directions carefully.
Caution: Consult your healthcare provider before using this product if you are taking medication for mood concerns, such as MAOIs or SSRIs.
Use caution before driving or operating heavy machinery.
Warnings: Keep out of reach of children.
Do not exceed recommended dose. Do not purchase if outer seal is damaged.
Consult with your physician if you are undergoing treatment for a medical condition or if you are pregnant or lactating.
To report a serious adverse event or obtain product information, contact 1-866-280-2852.
Suggested/Recommended/Usage/Directions
Directions: Take three (3) capsules all at once before bedtime, or one capsule on an empty stomach before each meal, or as recommended by a healthcare practitioner. Best if taken separately from protein or amino acids.
Storage
Store tightly closed in a cool, dry place.
Brand IP Statement(s)
Perluxan is used by permission.
Formulation
Gluten free Non GMO LE Certified
Sleep enhancement and stress reduction
Seals/Symbols
Non GMO LE Certified
FDA Statement of Identity
Dietary Supplement
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Optimized Tryptophan Plus by Life Extension label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Optimized Tryptophan Plus by Life Extension
These are the 5 active ingredients this product is made of. Select any to open its full monograph.
Serving size3 Vegetarian Capsule(s) Dosage formCapsule Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
L-Tryptophan
Interacts with394 drugs
L-tryptophan is an essential amino acid the body uses to make serotonin and melatonin, and people take it to support sleep and mood. The evidence for...
L-Tryptophan monograph & interactionsNiacin
Interacts with727 drugs
Niacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescr...
Niacin monograph & interactionsL-Lysine
Interacts with1 drug
Lysine is an essential amino acid your body cannot make on its own, so it must come from food or supplements. People most often take extra lysine to t...
L-Lysine monograph & interactionsProprietary Tryptophan Plus Blend
Other (inactive) ingredients: Cellulose, Microcrystalline Cellulose, Maltodextrin, Starch, Carboxymethyl Cellulose, Stearate, Silica. These complete the product’s ingredient list but are not active constituents.
Optimized Tryptophan Plus by Life Extension Drug Interactions
HelloPharmacist Interaction Report
Optimized Tryptophan Plus by Life Extension has documented interactions with a substantial number of medications.
The most serious concern is L-tryptophan's major-severity interaction with CNS depressants (drugs that slow the brain and nervous system), which can cause additive sedative effects and increased drowsiness—a risk that clinical research confirms L-tryptophan itself can trigger.
Read the full breakdown — every affected drug type, severity by severity
L-tryptophan also interacts moderately with serotonergic drugs (medications that work on serotonin in the brain), raising the theoretical risk of serotonin syndrome and related effects. Niacin in this product moderately interacts with antihypertensive drugs, hepatotoxic drugs, anticoagulants and antiplatelet drugs, antidiabetes drugs, statins, allopurinol, bile acid sequestrants, and probenecid.
Rosemary leaf extract moderately interacts with anticoagulant and antiplatelet drugs, antidiabetes drugs, and salicylate-containing drugs like aspirin and salsalate. Hops (Perluxan) moderately interacts with CNS depressants and estrogens, with minor interactions involving certain enzyme substrates.
L-lysine carries a minor interaction with 5-HT4 agonists.
Altogether, these interactions span 1,351 individual medications. Use the medication checker below to verify your prescriptions and over-the-counter drugs before starting this supplement.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Optimized Tryptophan Plus?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Optimized Tryptophan Plus interact with 1,371 drugs. Click any drug to see the details.
5 of the 5 ingredients in Optimized Tryptophan Plus interact with drugs. Each result below shows which ingredient is responsible. Perluxan Niacin L-Tryptophan Rosemary Leaf Extract L-Lysine
AcepromazineAtravet
How Acepromazine interacts with Optimized Tryptophan Plus — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acepromazine interactionPerluxanCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acepromazine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Caffeine, Codeine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Butalbital, Caffeine, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Caffeine, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Butalbital, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Butalbital, Codeine Phosphate interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Butalbital, Codeine Phosphate interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Butalbital, Codeine Phosphate interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Codeine interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Caffeine, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Codeine, Salicylamide interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Codeine, Salicylamide interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Caffeine, Codeine, Salicylamide interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Caffeine, Dihydrocodeine interactionPerluxanCytochrome P450 3a4 (cyp3a4) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, hops extract might alter metabolism of CYP3A4 substrates; however, this effect may not be clinically significant.
Read the full Perluxan + Acetaminophen, Caffeine, Dihydrocodeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Caffeine, Dihydrocodeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanSerotonergic Drugs, Cns Depressants Major
Interaction Summary
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
Read the full L-tryptophan + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionPerluxanCns Depressants, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, OpiumHista-Derfule
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanSerotonergic Drugs, Cns Depressants Major
Interaction Summary
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
Read the full L-tryptophan + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionAcetaminophen, Chlorzoxazone, CodeineAcetazone Forte C8, Parafon Forte C8
How Acetaminophen, Chlorzoxazone, Codeine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Chlorzoxazone, Codeine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Chlorzoxazone, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Chlorzoxazone, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Chlorzoxazone, Codeine interactionAcetaminophen, CodeineTylenol No.3, Tylenol w/ Codeine
How Acetaminophen, Codeine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Codeine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Codeine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Codeine interactionAcetaminophen, Codeine, DoxylamineMersyndol
How Acetaminophen, Codeine, Doxylamine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine, Doxylamine interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Codeine, Doxylamine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Codeine, Doxylamine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Codeine, Doxylamine interactionAcetaminophen, Codeine, MethocarbamolAcetaminophen, Codeine, Methocarbamol, Robaxacet 8
How Acetaminophen, Codeine, Methocarbamol interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Codeine, Methocarbamol interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Codeine, Methocarbamol interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Codeine, Methocarbamol interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Codeine, Methocarbamol interactionAcetaminophen, Dichloralantipyrine, IsomethepteneAmidrine, Midchlor, Migquin, Migratine
How Acetaminophen, Dichloralantipyrine, Isometheptene interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichloralantipyrine, Isometheptene interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Dichloralantipyrine, Isometheptene interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Dichloralantipyrine, Isometheptene interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionAcetaminophen, Dichloralphenazone, IsomethepteneMidrin
How Acetaminophen, Dichloralphenazone, Isometheptene interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichloralphenazone, Isometheptene interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Dichloralphenazone, Isometheptene interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Dichloralphenazone, Isometheptene interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionAcetaminophen, Dichlorophenazone, IsometheptaneIsocom
How Acetaminophen, Dichlorophenazone, Isometheptane interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Dichlorophenazone, Isometheptane interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Dichlorophenazone, Isometheptane interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Dichlorophenazone, Isometheptane interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionAcetaminophen, DiphenhydramineTylenol PM, Tylenol PM Ex Strength
How Acetaminophen, Diphenhydramine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Diphenhydramine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Diphenhydramine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Diphenhydramine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Diphenhydramine interactionAcetaminophen, Diphenhydramine, PseudoephedrineChildren's Tylenol Allergy, Cold Control, Contac Night Allergy Relief
How Acetaminophen, Diphenhydramine, Pseudoephedrine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionAcetaminophen, HydrocodoneAnexsia, Anodynos DHC, Azdone, Co-Gesic, Doucet, Lorcet +9 more
How Acetaminophen, Hydrocodone interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Hydrocodone interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Hydrocodone interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Hydrocodone interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Hydrocodone interactionAcetaminophen, MeperidineDemerol APAP
How Acetaminophen, Meperidine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanSerotonergic Drugs, Cns Depressants Major
Interaction Summary
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
Read the full L-tryptophan + Acetaminophen, Meperidine interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Meperidine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Meperidine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Meperidine interactionAcetaminophen, OxycodonePercocet, Roxicet, Tylox, Xartemis XR
How Acetaminophen, Oxycodone interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Oxycodone interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Oxycodone interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Oxycodone interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Oxycodone interactionAcetaminophen, PentazocineTalacen
How Acetaminophen, Pentazocine interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Pentazocine interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Pentazocine interactionPerluxanCns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetaminophen, Pentazocine interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Pentazocine interactionAcetaminophen, PropoxypheneDarvocet-N 100, Darvocet-N 50, E-Lor, Wygesic
How Acetaminophen, Propoxyphene interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetaminophen, Propoxyphene interactionPerluxanCytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants Moderate
Interaction Summary
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
Read the full Perluxan + Acetaminophen, Propoxyphene interactionNiacinHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Niacin + Acetaminophen, Propoxyphene interactionRosemary Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Rosemary Leaf Extract + Acetaminophen, Propoxyphene interactionAcetazolamideAk-Zol, Diamox
How Acetazolamide interacts with Optimized Tryptophan Plus — through 3 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Acetazolamide interactionNiacinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
Read the full Niacin + Acetazolamide interactionPerluxanCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Acetazolamide interactionAlfentanilAlfenta
How Alfentanil interacts with Optimized Tryptophan Plus — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Alfentanil interactionPerluxanCytochrome P450 3a4 (cyp3a4) Substrates, Cns Depressants Moderate
Interaction Summary
Theoretically, hops extract might alter metabolism of CYP3A4 substrates; however, this effect may not be clinically significant.
Read the full Perluxan + Alfentanil interactionAlprazolamNiravam, Xanax
How Alprazolam interacts with Optimized Tryptophan Plus — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Alprazolam interactionPerluxanCns Depressants, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Alprazolam interactionAluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium HydroxideAscriptin Codeine #2
How Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interacts with Optimized Tryptophan Plus — through 4 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionRosemary Leaf ExtractAspirin, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as aspirin.
Read the full Rosemary Leaf Extract + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionNiacinAspirin, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Large doses of aspirin might alter the clearance of niacin.
Read the full Niacin + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionPerluxanCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Aluminum Hydroxide, Aspirin, Codeine Phosphate, Magnesium Hydroxide interactionAminoglutethimideCytadren
How Aminoglutethimide interacts with Optimized Tryptophan Plus — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aminoglutethimide interactionPerluxanCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Aminoglutethimide interactionAminophylline, Amobarbital, EphedrineAmesec
How Aminophylline, Amobarbital, Ephedrine interacts with Optimized Tryptophan Plus — through 2 ingredients. Tap an ingredient for the detail:
L-tryptophanCns Depressants Major
Interaction Summary
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Read the full L-tryptophan + Aminophylline, Amobarbital, Ephedrine interactionPerluxanCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Read the full Perluxan + Aminophylline, Amobarbital, Ephedrine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Optimized Tryptophan Plus with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Perluxan
Cns Depressants
Theoretically, concomitant use of hops with sedative drugs might cause additive sedation.
Some animal research shows that hops has sedative effects.
Estrogens
Theoretically, concomitant use of large amounts of hops might interfere with hormone replacement therapy due to competition for estrogen receptors.
In vitro research suggests that certain hops constituents can competitively bind to estrogen receptors. However, most hops extracts contain very small amounts of these constituents.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Hops extract does not seem to affect the metabolism of CYP1A2 substrates.
In vitro research suggests that flavonoid constituents of hops inhibit CYP1A2 enzyme activity. However, a pharmacokinetic study in healthy postmenopausal patients shows that taking a standardized extract of spent hops containing prenylated phenols, as 59.5 mg twice daily for 2 weeks, does not affect levels of caffeine, a CYP1A2 probe substrate.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, hops extract might alter metabolism of CYP3A4 substrates; however, this effect may not be clinically significant.
Animal research suggests that specific constituents of hops, called lupulones, can induce hepatic CYP3A4 enzyme activity. However, a pharmacokinetic study in healthy postmenopausal patients with normal metabolism shows that taking a standardized extract of spent hops containing prenylated phenols, as 59.5 mg twice daily for 2 weeks, decreases the concentration of alprazolam, a CYP3A4 probe substrate, by 7.6%. This reduction is unlikely to be clinically relevant.
Niacin
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
L-Tryptophan
Cns Depressants
Theoretically, concomitant use of L-tryptophan with CNS depressants might cause additive sedative effects.
Clinical research shows that L-tryptophan can cause fatigue and drowsiness.
Serotonergic Drugs
Theoretically, combining L-tryptophan with serotonergic drugs might cause additive serotonergic effects.
L-tryptophan is a precursor to serotonin. Theoretically, combining serotonergic drugs with L-tryptophan might increase the risk of serotonergic side effects, including serotonin syndrome and cerebral vasoconstrictive disorders.
Rosemary Leaf Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, rosemary may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that rosemary inhibits platelet aggregation.
Antidiabetes Drugs
Theoretically, taking rosemary with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research shows that rosemary extract can decrease blood glucose levels in diabetic models. However, research in humans is conflicting. Although rosemary powder decreased blood glucose levels in healthy adults, no change in blood glucose levels was seen in adults with type 2 diabetes, most of whom were taking antidiabetes drugs.
Aspirin
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as aspirin.
Rosemary is reported to contain salicylates.
Choline Magnesium Trisalicylate (Trilisate)
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as choline magnesium trisalicylate.
Rosemary is reported to contain salicylate.
Salsalate (Disalcid)
Theoretically, rosemary might have additive effects with salicylate-containing drugs such as salsalate.
Rosemary is reported to contain salicylate.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, rosemary might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that rosemary induces CYP1A2 enzymes. This effect has not been reported in humans.
L-Lysine
5-Ht4 Agonists
Theoretically, lysine may reduce the effects of 5-HT4 agonists.
Animal research suggests that L-lysine is a partial serotonin receptor 4 (5-HT4) antagonist and inhibits diarrhea induced by the 5-HT4 agonist, 5-hydroxytryptophane.
Brand information
Manufacturer and brand details for Optimized Tryptophan Plus, from the product label.
Life Extension
See all Life Extension products- Name
- Quality Supplements and Vitamins, Inc.
- City
- Ft. Lauderdale
- State
- FL
- ZipCode
- 33309
- Phone Number
- 1-866-280-2852
- Web Address
- LifeExtension.com
Optimized Tryptophan Plus by Life Extension: Common Questions
Does Optimized Tryptophan Plus by Life Extension interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take this while pregnant?
What is L-tryptophan supposed to do?
Will this help me sleep?
What are the most common side effects?
Is L-tryptophan safe after the EMS scare in 1989?
Can I take this with my depression medication?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Optimized Tryptophan Plus is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Optimized Tryptophan Plus’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
L-tryptophan
Interacts with 394 drugsL-tryptophan is an essential amino acid the body uses to make serotonin and melatonin, and people take it to support sleep and mood. The evidence for supplement use is limited and mixed, and...
Read the full L-tryptophan monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph → Herb & supplement monographLysine
Interacts with 1 drugLysine is an essential amino acid your body cannot make on its own, so it must come from food or supplements. People most often take extra lysine to try to prevent or shorten cold sores, but...
Read the full Lysine monograph → Herb & supplement monographRosemary
Interacts with 372 drugsRosemary is a fragrant Mediterranean herb that is safe and flavorful in normal food amounts. Some early research suggests possible benefits for memory, mood, and hair growth, but the evidenc...
Read the full Rosemary monograph → Herb & supplement monographHops
Interacts with 863 drugsHops are most often used for sleep and mild anxiety, frequently combined with valerian, but the human evidence is limited and not very strong. They are generally well tolerated when used sho...
Read the full Hops monograph →Sources & How We Checked
Optimized Tryptophan Plus's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 126 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
L-tryptophan 18 references
- Messiha FS. Fluoxetine: adverse effects and drug-drug interactions. J Toxicol Clin Toxicol 1993;31:603-30. PubMed
- Devoe LD, Castillo RA, Searle NS. Maternal dietary substrates and human fetal biophysical activity. The effects of tryptophan and glucose on fetal breathing movements. Am J Obstet Gynecol 1986;155:135-9. DOI
- Lieberman HR, Corkin S, Spring BJ. The effects of dietary neurotransmitter precursors on human behavior. Am J Clin Nutr 1985;42:366-70. PubMed
- U. S. Food and Drug Administration, Center for Food Safety and Applied Nutrition, Office of Nutritional Products, Labeling, and Dietary Supplements. Information Paper on L-Tryptophan and 5-hydroxy-L-tryptophan, February 2001.
- Sullivan EA, Kamb ML, Jones JL, et al. The natural history of eosinophilia-myalgia syndrome in a tryptophan-exposed cohort in South Carolina. Arch Intern Med 1996;156:973-9. DOI
- Philen RM, Hill RH, Flanders WD, et al. Tryptophan contaminants associated with eosinophilia-myalgia syndrome. Am J Epidemiol 1993;138:154-9. PubMed
- Bohme A, Wolter M, Hoelzer D. L-tryptophan-related eosinophilia-myalgia syndrome possibly associated with a chronic B-lymphocytic leukemia. Ann Hematol 1998;77:235-8. PubMed
- Singhal AB, Caviness VS, Begleiter AF, et al. Cerebral vasoconstriction and stroke after use of serotonergic drugs. Neurology 2002;58:130-3. PubMed
- Priori R, Conti F, Luan FL, et al. Chronic fatigue: a peculiar evolution of eosinophilia myalgia syndrome following treatment with L-tryptophan in four Italian adolescents. Eur J Pediatr 1994;153:344-6..
- Klein R, Berg PA. A comparative study on antibodies to nucleoli and 5-hydroxytryptamine in patients with fibromyalgia syndrome and tryptophan-induced eosinophilia-myalgia syndrome. Clin Investig 1994;72:541-9.. PubMed
- Simat TJ, Kleeberg KK, Muller B, Sierts A. Synthesis, formation, and occurrence of contaminants in biotechnologically manufactured L-tryptophan. Adv Exp Med Biol 1999;467:469-80.. PubMed
- Shaw K, Turner J, Del Mar C. Tryptophan and 5-hydroxytryptophan for depression. Cochrane Database Syst Rev 2002;(1):CD003198. PubMed
- Kilbourne EM, Philen RM, Kamb ML, Falk H. Tryptophan produced by Showa Denko and epidemic eosinophilia-myalgia syndrome. J Rheumatol Suppl 1996;46:81-8.
- Horwitz RI, Daniels SR. Bias or biology: evaluating the epidemiologic studies of L-tryptophan and the eosinophilia-myalgia syndrome. J Rheumatol Suppl 1996;46:60-72.
- Shapiro S. Epidemiologic studies of the association of L-tryptophan with the eosinophilia-myalgia syndrome: a critique. J Rheumatol Suppl 1996;46:44-58.
- Mayeno AN, Gleich GJ. The eosinophilia-myalgia syndrome: lessons from Germany. Mayo Clin Proc 1994;69:702-4. PubMed
- Carr L, Ruther E, Berg PA, Lehnert H. Eosinophilia-myalgia syndrome in Germany: an epidemiologic review. Mayo Clin Proc 1994;69:620-5. PubMed
- Ullrich SS, Fitzgerald PCE, Giesbertz P, Steinert RE, Horowitz M, Feinle-Bisset C. Effects of intragastric administration of tryptophan on the blood glucose response to a nutrient drink and energy intake, in lean and obese men. Nutrients 2018;10(4). pii: PubMed
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Lysine 7 references
- Thein DJ, Hurt WC. Lysine as a prophylactic agent in the treatment of recurrent herpes simplex labialis. Oral Surg Oral Med Oral Pathol 1984;58:659-66. PubMed
- McCune MA, Perry HO, Muller SA, O'Fallon WM. Treatment of recurrent herpes simplex infections with L-lysine monohydrochloride. Cutis 1984;34:366-73.
- DiGiovanna JJ, Blank H. Failure of lysine in frequently recurrent herpes simplex infection. Treatment and prophylaxis. Arch Dermatol 1984;120:48-51. DOI
- Milman N, Scheibel J, Jessen O. Lysine prophylaxis in recurrent herpes simplex labialis: a double-blind, controlled crossover study. Acta Derm Venereol 1980;60:85-7.
- Griffith RS, Walsh DE, Myrmel KH, et al. Success of L-lysine therapy in frequently recurrent herpes simplex infection. Treatment and prophylaxis. Dermatologica 1987;175:183-90. DOI
- Lo JC, Chertow GM, Rennke H, Seifter JL. Fanconi's syndrome and tubulointerstitial nephritis in association with L-lysine ingestion. Am J Kidney Dis 1996;28:614-7. PubMed
- Smriga M, Torii K. L-Lysine acts like a partial serotonin receptor 4 antagonist and inhibits serotonin-mediated intestinal pathologies and anxiety in rats. Proc Natl Acad Sci U S A. 2003 Dec 23;100(26):15370-5.
Rosemary 20 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- Foster S, Tyler VE. Tyler's Honest Herbal: A Sensible Guide to the Use of Herbs and Related Remedies. 3rd ed., Binghamton, NY: Haworth Herbal Press, 1993.
- The Review of Natural Products by Facts and Comparisons. St. Louis, MO: Wolters Kluwer Co., 1999.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Cartier LC, Lehrer A, Malo JL. Occupational asthma caused by aromatic herbs. Allergy 1996;51:647-9. DOI
- Burkhard PR, Burkhardt K, Haenggeli CA, Landis T. Plant-induced seizures: reappearance of an old problem. J Neurol 1999;246:667-70. PubMed
- Swain AR, Dutton SP, Truswell AS. Salicylates in foods. J Am Diet.Assoc 1985;85(8):950-60. DOI
- Zhu BT, Loder DP, Cai MX, et al. Dietary administration of an extract from rosemary leaves enhances the liver microsomal metabolism of endogenous estrogens and decreases their uterotropic action in CD-1 mice. Carcinogenesis 1998;19(10):1821-7. PubMed
- Debersac P, Heydel JM, Amiot MJ, et al. Induction of cytochrome P450 and/or detoxication enzymes by various extracts of rosemary: description of specific patterns. Food Chem Toxicol 2001;39(9):907-18. PubMed
- Debersac P, Vernevaut MF, Amiot MJ, et al. Effects of a water-soluble extract of rosemary and its purified component rosmarinic acid on xenobiotic-metabolizing enzymes in rat liver. Food Chem Toxicol 2001;39(2):109-17. PubMed
- Lee JJ, Jin YR, Lee JH, et al. Antiplatelet activity of carnosic acid, a phenolic diterpene from Rosmarinus officinalis. Planta Med 2007;73(2):121-7.
- Yamamoto J, Yamada K, Naemura A, et al. Testing various herbs for antithrombotic effect. Nutrition 2005;21(5):580-7. PubMed
- Naemura A, Ura M, Yamashita T, et al. Long-term intake of rosemary and common thyme herbs inhibits experimental thrombosis without prolongation of bleeding time. Thromb Res 2008;122(4):517-22. PubMed
- Lee JJ, Jin YR, Lim Y, et al. Antiplatelet activity of carnosol is mediated by the inhibition of TXA2 receptor and cytosolic calcium mobilization. Vascul Pharmacol 2006;45:148-53. PubMed
- Bakirel, T., Bakirel, U., Keles, O. U., Ulgen, S. G., and Yardibi, H. In vivo assessment of antidiabetic and antioxidant activities of rosemary (Rosmarinus officinalis) in alloxan-diabetic rabbits. J Ethnopharmacol 2-28-2008;116(1):64-73. PubMed
- Erenmemisoglu, A., Saraymen, R., and Ustun, S. Effect of a Rosmarinus officinalis leave extract on plasma glucose levels in normoglycaemic and diabetic mice. Pharmazie 1997;52(8):645-646.
- Valones MAA, Silva ICG, Gueiros LAM, Leão JC, Caldas AF Jr, Carvalho AAT. Clinical assessment of rosemary-based toothpaste (Rosmarinus officinalis Linn.): A randomized controlled double-blind study. Braz Dent J. 2019;30(2):146-151. PubMed
- Quirarte-Báez SM, Zamora-Perez AL, Reyes-Estrada CA, et al. A shortened treatment with rosemary tea (rosmarinus officinalis) instead of glucose in patients with diabetes mellitus type 2 (TSD). J Popul Ther Clin Pharmacol. 2019;26(4):e18-e28.
- Al Jamal A. Effect of rosemary (Rosmarinus officinalis) on lipid profiles and blood glucose in human diabetic patients (type-2). African J. Biochem. Res. 2014;8(8):147-50. DOI
Hops 15 references
- Newall CA, Anderson LA, Philpson JD. Herbal Medicine: A Guide for Healthcare Professionals. London, UK: The Pharmaceutical Press, 1996.
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Zava DT, Dollbaum CM, Blen M. Estrogen and progestin bioactivity of foods, herbs, and spices. Proc Soc Exp Biol Med 1998;217:369-78. PubMed
- Milligan SR, Kalita JC, Heyerick A, et al. Identification of a potent phytoestrogen in hops (Humulus lupulus L.) and beer. J Clin Endocrinol Metab 1999;84:2249-52.. PubMed
- Milligan SR, Kalita JC, Pocock V, et al. The endocrine activities of 8-prenylnaringenin and related hop (Humulus lupulus L.) flavonoids. J Clin Endocrinol Metab 2000;85:4912-5.. DOI
- Henderson MC, Miranda CL, Stevens JF, et al. In vitro inhibition of human P450 enzymes by prenylated flavonoids from hops, Humulus lupulus. Xenobiotica 2000;30:235-51.. PubMed
- Mannering, G. J., Shoeman, J. A., and Deloria, L. B. Identification of the antibiotic hops component, colupulone, as an inducer of hepatic cytochrome P-4503A in the mouse. Drug Metab Dispos 1992;20(2):142-147. DOI
- Skorska, C., Mackiewicz, B., Gora, A., Golec, M., and Dutkiewicz, J. Health effects of inhalation exposure to organic dust in hops farmers. Ann.Univ Mariae.Curie Sklodowska [Med] 2003;58(1):459-465.
- Schiller, H., Forster, A., Vonhoff, C., Hegger, M., Biller, A., and Winterhoff, H. Sedating effects of Humulus lupulus L. extracts. Phytomedicine. 2006;13(8):535-541. PubMed
- van Hunsel, F. P. and Kampschoer, P. [Postmenopausal bleeding and dietary supplements: a possible causal relationship with hop- and soy-containing preparations]. Ned.Tijdschr.Geneeskd. 2012;156(41):A5095.
- Fenselau, C. and Talalay, P. Is oestrogenic activity present in hops? Food Cosmet.Toxicol. 1973;11(4):597-602. PubMed
- Godnic-Cvar, J., Zuskin, E., Mustajbegovic, J., Schachter, E. N., Kanceljak, B., Macan, J., Ilic, Z., and Ebling, Z. Respiratory and immunological findings in brewery workers. Am J Ind Med 1999;35(1):68-75. DOI
- Lee KM, Jung JS, Song DK, and et al. Effects of Humulus lupulus extract on the central nervous system in mice. Planta Med 1993;59(Suppl):A691.
- Assessment report on Humulus lupulus L., flos. European Medicines Agency, 2014. Available at: https://www.ema.europa.eu/en/documents/herbal-report/final-assessment-report-humulus-lupulus-l-flos_en.pdf. Accessed September 29, 2021.
- van Breemen RB, Chen L, Tonsing-Carter A, et al. Pharmacokinetic Interactions of a Hop Dietary Supplement with Drug Metabolism in Perimenopausal and Postmenopausal Women. J Agric Food Chem. 2020;68(18):5212-5220. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC