
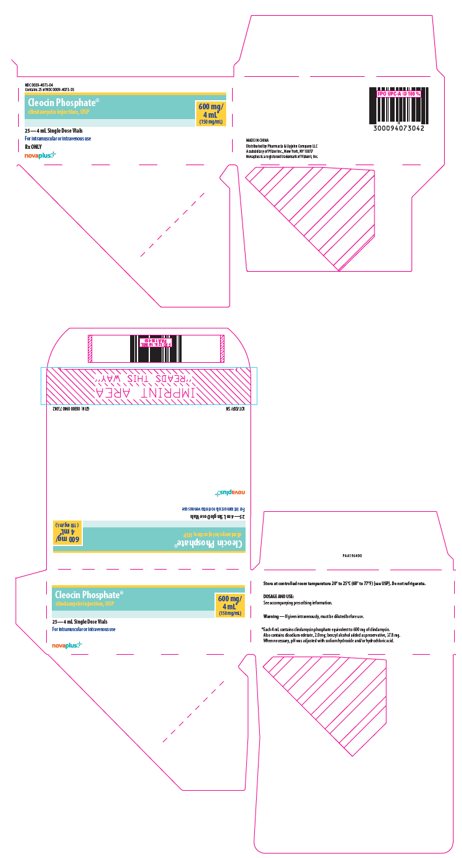
Cleocin Phosphate clindamycin 150 mg/mL Injection, Solution — NDC 0009-4073-04 (Billing 00009-4073-04)
This is a package of Cleocin Phosphate clindamycin 150 mg/mL Injection, Solution from Pharmacia & Upjohn Company LLC, marketed since Nov 2019 and currently FDA-listed, this package's marketing is listed to end Nov 2026. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0009-4073-04 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0009 labeler · 4073 product · 04 package
- Package marketed since
- Nov 18, 2019
- Package marketing ended
- Nov 30, 2026
- Sample package
- No — commercial package
- Barcode (UPC-A, from the NDC)
- 3 0009407304 2
- Medicaid fills, this package
- 11 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Clindamycin Phosphate (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 009344
- GCN: 40843
- GPI-14 (Medi-Span): 16220020302032
- HICL (First Databank): 004045
- AHFS class code: 08:12.28.20
- RxCUI (RxNorm): 1737244
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Lincosamide Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Clindamycin injection is used to treat certain types of bacterial infections. Clindamycin is in a class of medications called lincomycin antibiotics. It works by slowing or stopping the growth of bacteria. Antibiotics such as clindamycin will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- It treats serious bacterial infections, such as anaerobic infections, skin, lung, abdominal, gynecological, and bone and joint infections, depending on the product. It is often use...
- Swallow them with a full glass of water and stay upright for at least 30 minutes afterward. This helps prevent irritation of your throat. Take it as often as your prescriber says a...
- Rash, nausea, vomiting, stomach pain and itching are among the more commonly reported effects. Call your doctor right away if you get severe, watery or bloody diarrhea, even weeks...
- What side effects are normal, and when should I call you?
Patient education
Supplement & herbal interactions
Clindamycin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $7.56 | $756.05 / 100 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.6876 | $68.76 / 100 ml |
| Medicare Part B allowsASP · J0736 | $1.974 / J0736 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00009-4073-04 You're viewing this Main listing | 25 VIAL in 1 CARTON / 4 mL in 1 VIAL | 2019-11-18 | Nov 30, 2026 | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cleocin Phosphate 150 mg/mL 00009-3051-02 | Pharmacia | 25 vials | $1.224 | AP | Availability likely | — |
| Cleocin Phosphate 150 mg/mL 00009-0870-26 | Pharmacia | 25 vials | $1.224 | AP | Availability likely | — |
| Cleocin Phosphate 150 mg/mL 00009-0775-26 | Pharmacia | 25 vials | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mLthis 00009-4073-04 | Pharmacia | 25 vials | — | AP | FDA listed | — |
| Clindamycin 150 mg/mL 00404-9838-02 | Henry | 1 vial | — | AP | Discontinued | — |
| Clindamycin 150 mg/mL 25021-0115-51 | Sagent | 1 bottle | — | AP | Discontinued | — |
| Clindamycin 150 mg/mL 71872-7192-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 71872-7197-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 84549-0775-26 | ProPharma | 4 ml | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 71872-7165-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Clindamycin 150 mg/mL 71872-7191-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 71872-7200-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Clindamycin 150 mg/mL 71872-7284-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 00009-0728-09 | Pharmacia | 5 vials | — | AP | Discontinued | — |
| Cleocin Phosphate 150 mg/mL 00009-0902-18 | Pharmacia | 25 vials | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 00404-9837-02 | Henry | 1 vial | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 00009-5095-06 | Pharmacia | 25 vials | — | AP | FDA listed | — |
| Cleocin Phosphate 150 mg/mL 71872-7324-01 | Medical | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
9.45 mg / 1 mL
UNII LKG8494WBH
Benzyl alcohol is a clear liquid used as a preservative and solvent in medicines. It helps prevent bacterial and fungal growth and dissolves other ingredients to create uniform liquid formulations.
-
0.5 mg / 1 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Pharmacia & Upjohn Company LLC labeler code 00009
- Cleocin T clindamycin phosphate 10 mg/mL Lotion NDC 0009-3329-01
- Prepidil dinoprostone .5 mg/3g Gel NDC 0009-3359-01
- Cleocin clindamycin phosphate 20 mg/g Cream NDC 0009-3448-01
- Depo-Medrol methylprednisolone acetate 80 mg/mL Injection, Suspension NDC 0009-3475-01
- Caverject Alprostadil 20.5 ug/mL Injection, Powder, Lyophilized, For Solution NDC 0009-3701-05
- Corvert ibutilide fumarate .1 mg/mL Injection, Solution NDC 0009-3794-01
- Depo-SubQ Provera medroxyprogesterone acetate 104 mg/.65mL Injection, Suspension NDC 0009-4709-13
- Dexamethasone Acetate 1 kg/kg Powder NDC 0009-5010-01
- Dexamethasone 1 kg/kg Powder NDC 0009-5019-01
- Testosterone 1 kg/kg Powder NDC 0009-5020-02
- Progesterone 1 kg/kg Powder NDC 0009-5023-01
- Dexamethasone Acetate Anhydrous 1 kg/kg Powder NDC 0009-5025-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Clostridioides difficile -associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including CLEOCIN PHOSPHATE and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile . Because CLEOCIN PHOSPHATE therapy has been associated with severe colitis which may end fatally, it should be reserved for serious infections where less toxic antimicrobial agents are inappropriate, as described in the INDICATIONS AND USAGE section.
It should not be used in patients with nonbacterial infections such as most upper respiratory tract infections. C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibacterial drug use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial drug use not directed against C. difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibacterial drug treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE CLEOCIN PHOSPHATE products are indicated in the treatment of serious infections caused by susceptible anaerobic bacteria. CLEOCIN PHOSPHATE products are also indicated in the treatment of serious infections due to susceptible strains of streptococci, pneumococci, and staphylococci. Its use should be reserved for penicillin-allergic patients or other patients for whom, in the judgment of the physician, a penicillin is inappropriate.
Because of the risk of antibacterial drug-associated pseudomembranous colitis, as described in the BOXED WARNING , before selecting clindamycin the physician should consider the nature of the infection and the suitability of less toxic alternatives (e.g., erythromycin). Bacteriologic studies should be performed to determine the causative organisms and their susceptibility to clindamycin. Indicated surgical procedures should be performed in conjunction with antibacterial drug therapy.
CLEOCIN PHOSPHATE is indicated in the treatment of serious infections caused by susceptible strains of the designated organisms in the conditions listed below: Lower respiratory tract infections including pneumonia, empyema, and lung abscess caused by anaerobes, Streptococcus pneumoniae, other streptococci (except E. faecalis ), and Staphylococcus aureus. Skin and skin structure infections caused by Streptococcus pyogenes, Staphylococcus aureus , and anaerobes. Gynecological infections including endometritis, nongonococcal tubo-ovarian abscess, pelvic cellulitis, and postsurgical vaginal cuff infection caused by susceptible anaerobes.
Intra-abdominal infections including peritonitis and intra-abdominal abscess caused by susceptible anaerobic organisms. Septicemia caused by Staphylococcus aureus , streptococci (except Enterococcus faecalis ), and susceptible anaerobes. Bone and joint infections including acute hematogenous osteomyelitis caused by Staphylococcus aureus and as adjunctive therapy in the surgical treatment of chronic bone and joint infections due to susceptible organisms.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of CLEOCIN PHOSPHATE and other antibacterial drugs, CLEOCIN PHOSPHATE should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION If diarrhea occurs during therapy, this antibacterial drug should be discontinued (see WARNING box). Clindamycin phosphate IM administration should be used undiluted . Clindamycin phosphate IV administration should be diluted (see Dilution for IV use and IV infusion rates below).
Adults Parenteral (IM or IV Administration) Serious infections due to aerobic gram-positive cocci and the more susceptible anaerobes (NOT generally including Bacteroides fragilis , Peptococcus species and Clostridium species other than Clostridium perfringens ): 600–1200 mg/day in 2, 3 or 4 equal doses. More severe infections, particularly those due to proven or suspected Bacteroides fragilis, Peptococcus species, or Clostridium species other than Clostridium perfringens : 1200–2700 mg/day in 2, 3 or 4 equal doses. For more serious infections, these doses may have to be increased.
In life-threatening situations due to either aerobes or anaerobes these doses may be increased. Doses of as much as 4800 mg daily have been given intravenously to adults. (see Dilution for IV use and IV Infusion Rates section below).
Single intramuscular injections of greater than 600 mg are not recommended. Alternatively, drug may be administered in the form of a single rapid infusion of the first dose followed by continuous IV infusion as follows: Table 2: Serum Clindamycin Levels Maintained, Rapid Infusion Rate and Maintenance Infusion Rate To maintain serum clindamycin levels Rapid infusion rate Maintenance infusion rate Above 4 mcg/mL 10 mg/min for 30 min 0.75 mg/min Above 5 mcg/mL 15 mg/min for 30 min 1.00 mg/min Above 6 mcg/mL 20 mg/min for 30 min 1.25 mg/min Pediatric Patients 1 month of age to 16 years Parenteral (IM or IV) Administration 20 to 40 mg/kg/day in 3 or 4 equal doses.
The higher doses would be used for more severe infections. Clindamycin should be dosed based on total body weight regardless of obesity. As an alternative to dosing on a body weight basis, pediatric patients may be dosed on the basis of square meters body surface: 350 mg/m 2 /day for serious infections and 450 mg/m 2 /day for more severe infections.
Parenteral therapy may be changed to oral CLEOCIN PEDIATRIC ® Flavored Granules (clindamycin palmitate hydrochloride) or CLEOCIN HCl ® Capsules (clindamycin hydrochloride) when the condition warrants and at the discretion of the physician. In cases of β-hemolytic streptococcal infections, treatment should be continued for at least 10 days. Pediatric Patients less than 1 month The recommended dosage is 15 to 20 mg/kg/day in 3 to 4 equal doses.
(see Table 3) regarding the dosing regimen for pediatric patients with post-menstrual age (PMA) less than or equal to 32 weeks, or greater than 32 weeks to less than or equal to 40 weeks. Table 3: Dosing Regimens for Pediatric Patients with PMA less than or equal to 32 weeks, or greater than 32 weeks to less than or equal to 40 weeks PMA (weeks) Dose (mg/kg) Dosing Interval (hours) PMA: Post-Menstrual age Less than or equal to 32 5 8 Greater than or equal to 32 to less than or equal to 40 7 8 Dilution for IV use and IV Infusion Rates The concentration of clindamycin in diluent for infusion should not exceed 18 mg per mL.
Infusion rates should not exceed 30 mg per minute. The usual infusion dilutions and rates are as follows: Dose Diluent Time 300 mg 50 mL 10 min 600 mg 50 mL 20 min 900 mg 50–100 mL 30 min 1200 mg 100 mL 40 min Administration of more than 1200 mg in a single 1-hour infusion is not recommended. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
Dilution and Compatibility Physical and biological compatibility studies monitored for 24 hours at room temperature have demonstrated no inactivation or incompatibility with the use of CLEOCIN PHOSPHATE Sterile Solution (clindamycin phosphate) in IV solutions containing sodium chloride, glucose, calcium or potassium, an… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS This drug is contraindicated in individuals with a history of hypersensitivity to preparations containing clindamycin or lincomycin.
⚠️ Warnings ▾
WARNINGS See BOXED WARNING . Clostridioides difficile -Associated Diarrhea Clostridioides difficile -associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including CLEOCIN PHOSPHATE, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial drug use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial drug use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial drug treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
Anaphylactic and Severe Hypersensitivity Reactions Anaphylactic shock and anaphylactic reactions have been reported (see ADVERSE REACTIONS ). Severe hypersensitivity reactions, including acute myocardial ischemia with or without myocardial infarction, and severe skin reactions such as toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens‑Johnson syndrome (SJS), some with fatal outcome, have been reported (see ADVERSE REACTIONS ). In case of such an anaphylactic or severe hypersensitivity reaction, discontinue treatment permanently and institute appropriate therapy.
A careful inquiry should be made concerning previous sensitivities to drugs and other allergens. Benzyl Alcohol Toxicity in Neonates ("Gasping Syndrome") This product contains benzyl alcohol as a preservative. The administration of intravenous solutions containing the preservative benzyl alcohol has been associated with the "gasping syndrome", and death in neonates.
Symptoms include a striking onset of gasping respiration, hypotension, bradycardia, and cardiovascular collapse. Although the normal therapeutic dose of this product delivers amounts of benzyl alcohol that are substantially lower than those reported in association with the "gasping syndrome", the minimum amount of benzyl alcohol at which toxicity may occur is not known and total daily benzyl alcohol exposure may be increased by concomitant medications. The risk of benzyl alcohol toxicity depends on the quantity administered and the liver and kidneys' capacity to detoxify the chemical.
Premature and low birth weight infants may be more likely to develop toxicity. Nephrotoxicity Clindamycin is potentially nephrotoxic and cases with acute kidney injury have been reported. Consider monitoring of renal function particularly in patients with pre-existing renal dysfunction or those taking concomitant nephrotoxic drugs.
In case of acute kidney injury, discontinue CLEOCIN PHOSPHATE when no other etiology is identified. Usage in Meningitis Since clindamycin does not diffuse adequately into the cerebrospinal fluid, the drug should not be used in the treatment of meningitis.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following reactions have been reported with the use of clindamycin. Infections and Infestations: Clostridioides difficile colitis Gastrointestinal: Antibacterial drug-associated colitis (see WARNINGS ), pseudomembranous colitis, abdominal pain, nausea, and vomiting. The onset of pseudomembranous colitis symptoms may occur during or after antibacterial treatment (see WARNINGS ).
An unpleasant or metallic taste has been reported after intravenous administration of the higher doses of clindamycin phosphate. Hypersensitivity Reactions: Maculopapular rash and urticaria have been observed during drug therapy. Generalized mild to moderate morbilliform-like skin rashes are the most frequently reported of all adverse reactions.
Severe skin reactions such as toxic epidermal necrolysis, some with fatal outcome, have been reported (see WARNINGS ). Cases of acute generalized exanthematous pustulosis (AGEP), erythema multiforme, some resembling Stevens-Johnson syndrome, have been associated with clindamycin. Anaphylactic shock, anaphylactic reaction, hypersensitivity, and acute myocardial ischemia with or without myocardial infarction occurring as part of an allergic reaction have also been reported (see WARNINGS ).
Cutaneous vasculitis and symmetrical drug-related intertriginous and flexural exanthema have also been reported. Skin and Mucous Membranes: Pruritus, vaginitis, angioedema and rare instances of exfoliative dermatitis have been reported (see Hypersensitivity Reactions ). Liver: Jaundice and abnormalities in liver function tests have been observed during clindamycin therapy.
Renal: Acute kidney injury (see WARNINGS ). Hematopoietic: Transient neutropenia (leukopenia) and eosinophilia have been reported. Reports of agranulocytosis and thrombocytopenia have been made.
No direct etiologic relationship to concurrent clindamycin therapy could be made in any of the foregoing. Immune System: Drug reaction with eosinophilia and systemic symptoms (DRESS) cases have been reported. Local Reactions: Injection site irritation, pain, induration and sterile abscess have been reported after intramuscular injection and thrombophlebitis after intravenous infusion.
Reactions can be minimized or avoided by giving deep intramuscular injections and avoiding prolonged use of indwelling intravenous catheters. Musculoskeletal: Polyarthritis cases have been reported. Cardiovascular: Cardiopulmonary arrest and hypotension have been reported following too rapid intravenous administration (see DOSAGE AND ADMINISTRATION ).
🔄 Drug Interactions ▾
Drug Interactions Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents. Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent by CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite N-desmethylclindamycin.
Therefore, inhibitors of CYP3A4 and CYP3A5 may increase plasma concentrations of clindamycin and inducers of these isoenzymes may reduce plasma concentrations of clindamycin. In the presence of strong CYP3A4 inhibitors, monitor for adverse reactions. In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness.
In vitro studies indicate that clindamycin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2E1 or CYP2D6 and only moderately inhibits CYP3A4.
🤰 Pregnancy ▾
Pregnancy Teratogenic effects In clinical trials with pregnant women, the systemic administration of clindamycin during the second and third trimesters, has not been associated with an increased frequency of congenital abnormalities. Clindamycin should be used during the first trimester of pregnancy only if clearly needed. There are no adequate and well-controlled studies in pregnant women during the first trimester of pregnancy.
Because animal reproduction studies are not always predictive of the human response, this drug should be used during pregnancy only if clearly needed. Reproduction studies performed in rats and mice using oral doses of clindamycin up to 600 mg/kg/day (2.1 and 1.1 times the highest recommended adult human dose based on mg/m 2 , respectively) or subcutaneous doses of clindamycin up to 250 mg/kg/day (0.9 and 0.5 times the highest recommended adult human dose based on mg/m 2 , respectively) revealed no evidence of teratogenicity.
CLEOCIN PHOSPHATE Sterile Solution contains benzyl alcohol. Benzyl alcohol can cross the placenta (See WARNINGS ).
🧒 Pediatric Use ▾
Pediatric Use When CLEOCIN PHOSPHATE Sterile Solution is administered to the pediatric population (birth to 16 years) appropriate monitoring of organ system functions is desirable (see CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION ) .
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of clindamycin did not include sufficient numbers of patients age 65 and over to determine whether they respond differently from younger patients. However, other reported clinical experience indicates that antibacterial drug-associated colitis and diarrhea (due to Clostridioides difficile ) seen in association with most antibacterial drugs occur more frequently in the elderly (>60 years) and may be more severe. These patients should be carefully monitored for the development of diarrhea.
Pharmacokinetic studies with clindamycin have shown no clinically important differences between young and elderly subjects with normal hepatic function and normal (age-adjusted) renal function after oral or intravenous administration.
🆘 Overdosage ▾
OVERDOSAGE Significant mortality was observed in mice at an intravenous dose of 855 mg/kg and in rats at an oral or subcutaneous dose of approximately 2618 mg/kg. In the mice, convulsions and depression were observed. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Distribution Biologically inactive clindamycin phosphate is converted to active clindamycin. By the end of short-term intravenous infusion, peak serum concentrations of active clindamycin are reached. After intramuscular injection of clindamycin phosphate, peak concentrations of active clindamycin are reached within 3 hours in adults and 1 hour in pediatric patients.
Serum concentrations of clindamycin can be maintained above the in vitro minimum inhibitory concentrations for most indicated organisms by administration of clindamycin phosphate every 8 to 12 hours in adults and every 6 to 8 hours in pediatric patients, or by continuous intravenous infusion. An equilibrium state is reached by the third dose. No significant concentrations of clindamycin are attained in the cerebrospinal fluid even in the presence of inflamed meninges.
Metabolism In vitro studies in human liver and intestinal microsomes indicated that clindamycin is predominantly metabolized by Cytochrome P450 3A4 (CYP3A4), with minor contribution from CYP3A5, to form clindamycin sulfoxide and a minor metabolite, N-desmethylclindamycin. Excretion Biologically inactive clindamycin phosphate disappears from the serum with 6 minutes of the average elimination half-life; however, the average serum elimination half-life of active clindamycin is about 3 hours in adults and 2½ hours in pediatric patients.
Specific Populations Patients with Renal/Hepatic Impairment The elimination half-life of clindamycin is increased slightly in patients with markedly reduced renal or hepatic function. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum. Dosage schedules do not need to be modified in patients with renal or hepatic disease.
Geriatric Patients Pharmacokinetic studies in elderly volunteers (61–79 years) and younger adults (18–39 years) indicate that age alone does not alter clindamycin pharmacokinetics (clearance, elimination half-life, volume of distribution, and area under the serum concentration-time curve) after IV administration of clindamycin phosphate. After oral administration of clindamycin hydrochloride, the average elimination half-life is increased to approximately 4.0 hours (range 3.4–5.1 h) in the elderly, compared to 3.2 hours (range 2.1–4.2 h) in younger adults.
The extent of absorption, however, is not different between age groups and no dosage alteration is necessary for the elderly with normal hepatic function and normal (age-adjusted) renal function 1 . Pharmacokinetics in Pediatric Patients with PMA ≤32 weeks, or >32 to ≤40 weeks Systemic clearance (CL) in premature infants increases with increases in body weight (kg) and post-menstrual age (PMA). The dosing regimens for pediatric patients ≤32 weeks PMA (5 mg/kg) and >32 to ≤40 weeks PMA (7 mg/kg), both administered intravenously every 8 hours, achieve exposures comparable to therapeutic exposures in adults (weighing 70 kg) administered clindamycin 600 mg every 8 hours (Table 1).
Table 1: Predicted Drug Exposure (Mean ± SD) of Clindamycin in Adults and in Pediatric Patients with PMA ≤32 weeks, or >32 to ≤40 weeks Age Adult (70 kg) PMA ≤32 weeks PMA>32 – ≤40 weeks PMA: post-menstrual age; AUC ss,0–8 hour : area under the concentration-time curve during a dosing interval at steady state; C max,ss : maximum drug concentration at steady state; C min,ss : minimum or trough drug concentration at steady state. Dose (every 8 hours) 600 mg 5 mg/kg 7 mg/kg AUC ss,0–8 hour (mcg∙h/mL) 50.5 (30.95) 52.5 (17.0) 55.9 (23.55) C max,ss (mcg/mL) 12.0 (3.49) 9.0 (2.02) 10.5 (2.79) C min,ss (mcg/mL) 3.1 (3.34) 4.6 (2.00) 4.4 (2.77) Obese Pediatric Patients Aged 2 to Less than 18 Years and Obese Adults Aged 18 to 20 Years An analysis of pharmacokinetic data in obese pediatric patients aged 2 to less than 18 years and obese adults aged 18 to 20 years demonstrated that clindamycin clearance and volume of distribution, normalized by total body weight, are comparabl… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanism of Action Clindamycin inhibits bacterial protein synthesis by binding to the 23S RNA of the 50S subunit of the ribosome. Clindamycin is bacteriostatic.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Each mL of CLEOCIN PHOSPHATE Sterile Solution contains clindamycin phosphate equivalent to 150 mg clindamycin, 0.5 mg disodium edetate, 9.45 mg benzyl alcohol added as preservative. When necessary, pH is adjusted with sodium hydroxide and/or hydrochloric acid. CLEOCIN PHOSPHATE is available in the following packages: 25–2 mL vials NDC 0009-3051-02 25–4 mL vials NDC 0009-4073-04 25–6 mL vials NDC 0009-5095-06 Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP].
📦 Storage and Handling ▾
Store at controlled room temperature 20° to 25°C (68° to 77°F) [see USP].
📋 Description ▾
DESCRIPTION CLEOCIN PHOSPHATE Sterile Solution in vials contains clindamycin phosphate, a water soluble ester of clindamycin and phosphoric acid. Each mL contains the equivalent of 150 mg clindamycin, 0.5 mg disodium edetate and 9.45 mg benzyl alcohol added as preservative in each mL. Clindamycin is a semisynthetic antibacterial drug produced by a 7(S)-chloro-substitution of the 7(R)-hydroxyl group of the parent compound lincomycin.
The chemical name of clindamycin phosphate is L- threo -α-D- galacto- Octopyranoside, methyl-7-chloro-6,7,8-trideoxy-6-[[(1-methyl-4-propyl-2-pyrrolidinyl)carbonyl] amino]-1-thio-, 2-(dihydrogen phosphate), (2 S-trans )-. The molecular formula is C 18 H 34 CIN 2 0 8 PS and the molecular weight is 504.96. The structural formula is represented below: Chemical Structure
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including CLEOCIN PHOSPHATE should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When CLEOCIN PHOSPHATE is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by CLEOCIN PHOSPHATE or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibacterial drugs which usually ends when the antibacterial drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug.
If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General Review of experience to date suggests that a subgroup of older patients with associated severe illness may tolerate diarrhea less well. When clindamycin is indicated in these patients, they should be carefully monitored for change in bowel frequency. CLEOCIN PHOSPHATE products should be prescribed with caution in individuals with a history of gastrointestinal disease, particularly colitis.
CLEOCIN PHOSPHATE should be prescribed with caution in atopic individuals. Certain infections may require incision and drainage or other indicated surgical procedures in addition to antibacterial drug therapy. The use of CLEOCIN PHOSPHATE may result in overgrowth of nonsusceptible organisms-particularly yeasts.
Should superinfections occur, appropriate measures should be taken as indicated by the clinical situation. CLEOCIN PHOSPHATE should not be injected intravenously undiluted as a bolus, but should be infused over at least 10–60 minutes as directed in the DOSAGE AND ADMINISTRATION section. Clindamycin dosage modification is not necessary in patients with renal disease.
In patients with moderate to severe liver disease, prolongation of clindamycin half-life has been found. However, it was postulated from studies that when given every eight hours, accumulation should rarely occur. Therefore, dosage modification in patients with liver disease may not be necessary.
However, periodic liver enzyme determinations should be made when treating patients with severe liver disease. Prescribing CLEOCIN PHOSPHATE in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. Information for Patients Patients should be counseled that antibacterial drugs including CLEOCIN PHOSPHATE should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When CLEOCIN PHOSPHATE is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by CLEOCIN PHOSPHATE or other antibacterial drugs in the future.
Diarrhea is a common problem caused by antibacterial drugs which usually ends when the antibacterial drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug. If this occurs, patients should contact their physician as soon as possible.
Laboratory Tests During prolonged therapy periodic liver and kidney function tests and blood counts should be performed. Drug Interactions Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents.
Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent by CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite N-desmethylclindamycin. Therefore, inhibitors of CYP3A4 and CYP3A5 may increase plasma concentrations of clindamycin and inducers of these isoenzymes may reduce plasma concentrations of clindamycin. In the presence of strong CYP3A4 inhibitors, monitor for adverse reactions.
In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness. In vitro studies indicate that clindamycin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2E1 or CYP2D6 and only moderately inhibits CYP3A4. Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Limited published data based on breast milk sampling reports that clindamycin appears in human breast milk in the range of less than 0.5 to 3.8 mcg/mL at dosages of 150 mg orally to 600 mg intravenously. Clindamycin has the potential to cause adverse effects on the breast-fed infant's gastrointestinal flora. If oral or intravenous clindamycin is required by a nursing mother, it is not a reason to discontinue breastfeeding, but an alternate drug may be preferred.
Monitor the breast-fed infant for possible adverse effects on the gastrointestinal flora, such as diarrhea, candidiasis (thrush, diaper rash) or rarely, blood in the stool indicating possible antibacterial drug-associated colitis. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for clindamycin and any potential adverse effects on the breast-fed child from clindamycin or from the underlying maternal condition.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies in animals have not been performed with clindamycin to evaluate carcinogenic potential. Genotoxicity tests performed included a rat micronucleus test and an Ames Salmonella reversion test. Both tests were negative.
Fertility studies in rats treated orally with up to 300 mg/kg/day (approximately 1.1 times the highest recommended adult human dose based on mg/m 2 ) revealed no effects on fertility or mating ability.
📚 References ▾
REFERENCES 1. Smith RB, Phillips JP: Evaluation of CLEOCIN HCl and CLEOCIN Phosphate in an Aged Population. Upjohn TR 8147-82-9122-021, December 1982.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 2 mL Vial Label NDC 0009-3051-01 Rx ONLY Cleocin Phosphate ® clindamycin injection, USP 2 mL Vial For intramuscular or intravenous use novaplus ™ 300 mg/ 2 mL* (150 mg/mL) PRINCIPAL DISPLAY PANEL - 2 mL Vial Label
PRINCIPAL DISPLAY PANEL - 2 mL Vial Carton NDC 0009-3051-02 Contains 25 of NDC 0009-3051-01 Cleocin Phosphate ® clindamycin injection, USP 300 mg/ 2 mL* (150 mg/mL) 25—2 mL Single Dose Vials For intramuscular or intravenous use Rx ONLY novaplus ™ PRINCIPAL DISPLAY PANEL - 2 mL Vial Carton
PRINCIPAL DISPLAY PANEL - 4 mL Vial Label NDC 0009-4073-03 Rx ONLY Cleocin Phosphate ® clindamycin injection, USP 4 mL Vial For intramuscular or intravenous use novaplus ™ 600 mg/ 4 mL* (150 mg/mL) PRINCIPAL DISPLAY PANEL - 4 mL Vial Label
PRINCIPAL DISPLAY PANEL - 4 mL Vial Carton NDC 0009-4073-04 Contains 25 of NDC 0009-4073-03 Cleocin Phosphate ® clindamycin injection, USP 600 mg/ 4 mL* (150 mg/mL) 25—4 mL Single Dose Vials For intramuscular or intravenous use Rx ONLY novaplus ™ PRINCIPAL DISPLAY PANEL - 4 mL Vial Carton
PRINCIPAL DISPLAY PANEL - 6 mL Vial Label NDC 0009-5095-05 Rx ONLY Cleocin Phosphate ® clindamycin injection, USP 6 mL Vial For intramuscular or intravenous use novaplus ™ 900 mg/ 6 mL* (150 mg/mL) PRINCIPAL DISPLAY PANEL - 6 mL Vial Label
PRINCIPAL DISPLAY PANEL - 6 mL Vial Carton NDC 0009-5095-06 Contains 25 of NDC 0009-5095-05 Cleocin Phosphate ® clindamycin injection, USP 900 mg/ 6 mL* (150 mg/mL) 25—6 mL Single Dose Vials For intramuscular or intravenous use Rx ONLY novaplus ™ PRINCIPAL DISPLAY PANEL - 6 mL Vial Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |