
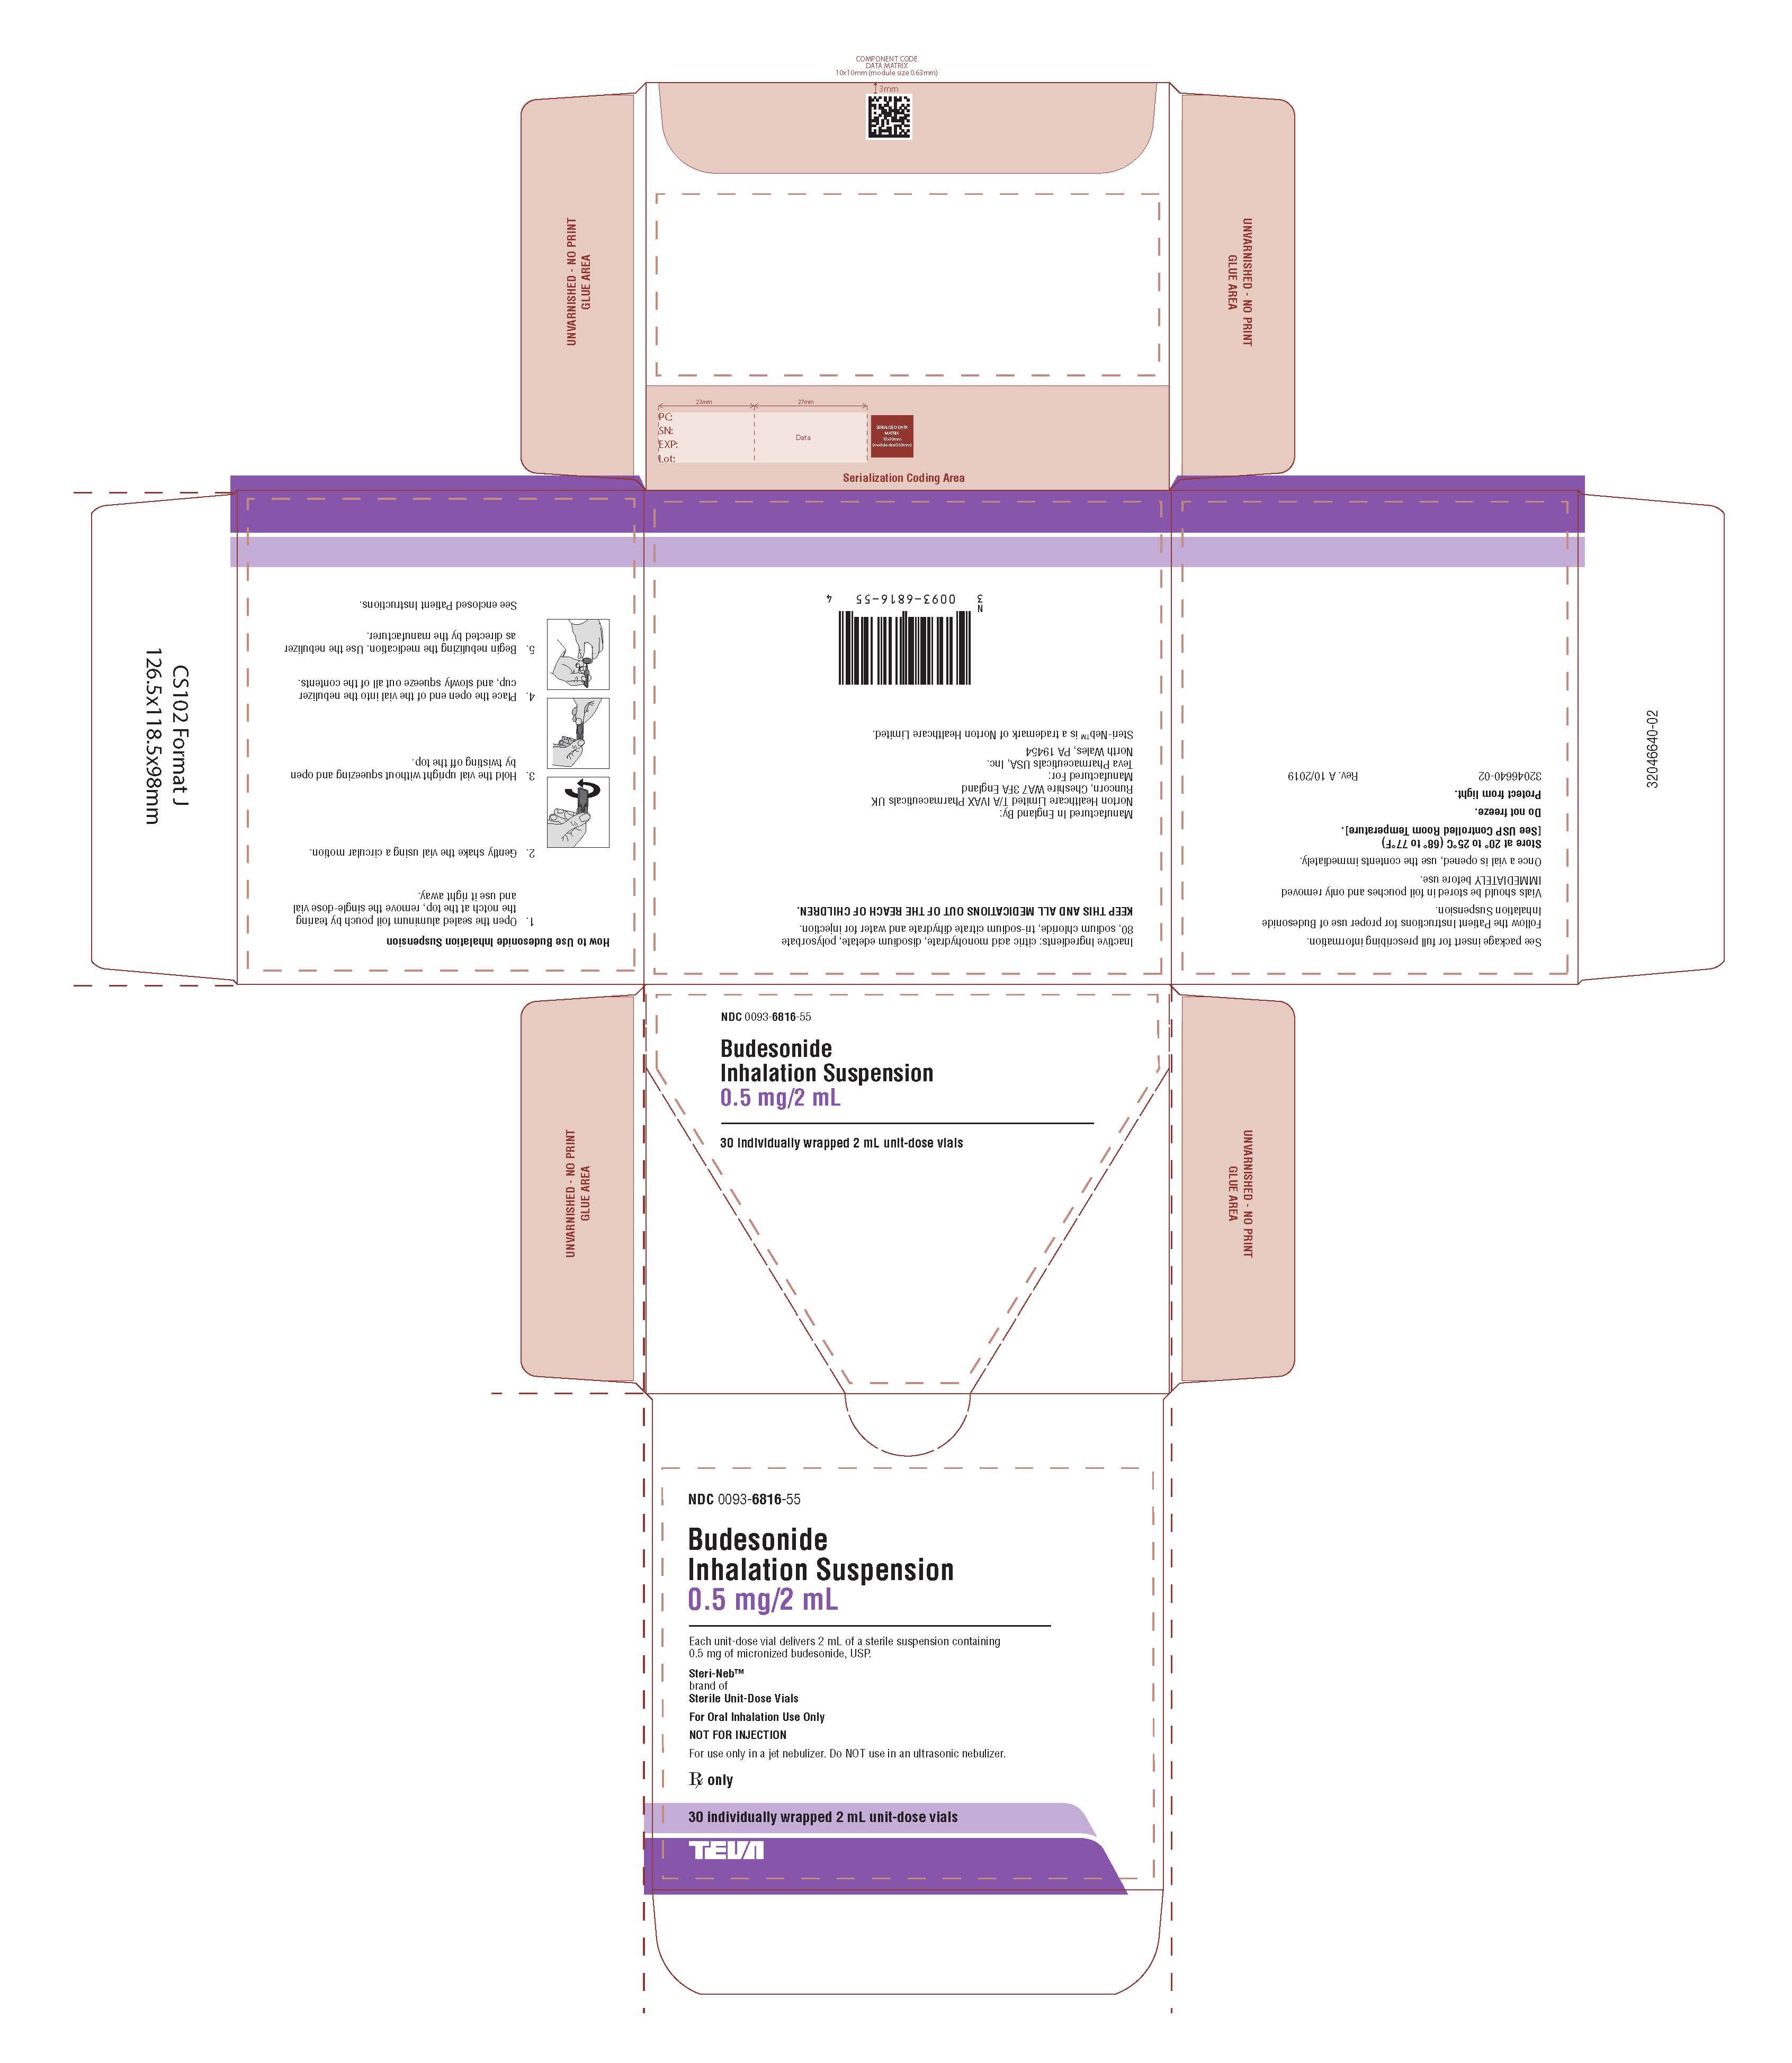
Budesonide .5 mg/2mL Suspension
Other active recalls for Budesonide (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Budesonide is used to prevent difficulty breathing, chest tightness, wheezing, and coughing caused by asthma. Budesonide powder for oral inhalation (Pulmicort Flexhaler) is used in adults and children 6 years of age and older. Budesonide suspension (liquid) for oral inhalation (Pulmicort Respules) is used in children 12 months to 8 years of age. Budesonide belongs to a class of medications called corticosteroids. It works by decreasing swelling and irritation in the airways to allow for easier breathing.
Read the full MedlinePlus article ↗- No — and this is really important to understand. Budesonide inhalation suspension is a daily controller medication, not a rescue treatment. It works by slowly calming inflammation...
- My child has asthma. Can I use this nebulizer treatment when they're having an attack?
- You may start to notice some improvement in your child's asthma symptoms within 2 to 8 days of starting treatment. But full benefit — where the airways are as calm and well-control...
- Yes, please do — it makes a real difference. Inhaled steroids like budesonide can leave a small amount of residue in the mouth and throat, which can lead to a yeast infection calle...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Budesonide — tap one for details:
Budesonide may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.704 | $42.21 / 60 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.8554 | $51.32 / 60 ml |
| Medicare drug plans payPart D · Q2 2026 | $1.20 | $72.14 / 60 ml |
| Medicare Part B allowsASP · J7626 | $1.092 / J7626 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Budesonide .5 mg/2mLthis 00093-6816-55 | Teva | 30 pouches | $0.703 | AN | Availability likely | — |
| Budesonide Inhalation .5 mg/2mL 00115-1689-74 | Amneal | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide .5 mg/2mL 00487-9701-01 | Nephron | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide .5 mg/2mL 47335-0632-49 | Sun | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide .5 mg/2mL 59651-0585-30 | Aurobindo | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide Inhalation .5 mg/2mL 60687-0524-83 | American | 30 pouches | $0.703 | AN | Availability likely | — |
| Budesonide .5 mg/2mL 62135-0823-84 | Chartwell | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide .5 mg/2mL 64980-0639-03 | Rising | 30 pouches | $0.703 | AN | Availability likely | — |
| budesonide inhalation .5 mg/2mL 68180-0984-30 | Lupin | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide Inhalation Suspension .5 mg/2mL 69097-0319-53 | Cipla | 30 pouches | $0.703 | AN | Availability likely | — |
| Budesonide Inhalation Suspension .5 mg/2mL 76282-0641-38 | Exelan | 6 pouches | $0.703 | AN | Availability likely | — |
| Budesonide .5 mg/2mL 00781-7516-87 | Sandoz | 6 pouches | $0.730 | — | Discontinued | +4% |
| Pulmicort Respules .5 mg/2mL 00186-1989-04 | AstraZeneca | 6 pouches | $4.909 | AN | Availability likely | +598% |
| Budesonide .5 mg/2mL 50090-6586-00 | A-S | 6 pouches | — | AN | FDA listed | — |
| budesonide inhalation .5 mg/2mL 50090-7126-00 | A-S | 6 pouches | — | AN | FDA listed | — |
| Budesonide .5 mg/2mL 55154-4849-05 | Cardinal | 5 vials | — | AN | FDA listed | — |
| Budesonide Inhalation Suspension .5 mg/2mL 68788-7314-03 | Preferred | 6 pouches | — | AN | FDA listed | — |
| budesonide inhalation .5 mg/2mL 68788-8503-03 | Preferred | 6 pouches | — | AN | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00093-6816-55 You're viewing this | 30 POUCH in 1 CARTON (0093-6816-55) / 1 VIAL, SINGLE-DOSE in 1 POUCH / 2 mL in 1 VIAL, SINGLE-DOSE | $0.7035 / mL | $42.21 | 2019-01-11 | Active |
| 00093-6816-73 | 6 POUCH in 1 CARTON (0093-6816-73) / 5 VIAL, SINGLE-DOSE in 1 POUCH (0093-6816-45) / 2 mL in 1 VIAL, SINGLE-DOSE (0093-6816-19) | $0.7035 / mL | $42.21 | 2008-11-19 | Active |
| 00093-6816-76 | 2 POUCH in 1 CARTON (0093-6816-76) / 5 VIAL, SINGLE-DOSE in 1 POUCH / 2 mL in 1 VIAL, SINGLE-DOSE | — | — | 2008-11-19 | Active |
This pack has the lowest per-mL cost of the 2 priced pack sizes ($0.7035 NADAC).
This pack accounts for about 9.5% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 00093-6816-55?
What NDC number is used to bill for this package of Budesonide .5 mg/2mL Suspension?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Budesonide inhalation suspension is an inhaled corticosteroid indicated for: Maintenance treatment of asthma and as prophylactic therapy in children 12 months to 8 years of age ( 1 ) Limitations of Use : Not indicated for the relief of acute bronchospasm ( 1 )
1.1Maintenance Treatment of Asthma Budesonide inhalation suspension is indicated for the maintenance treatment of asthma and as prophylactic therapy in children 12 months to 8 years of age. Limitations of Use: Budesonide inhalation suspension is NOT indicated for the relief of acute bronchospasm.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended starting dose and highest recommended dose of budesonide inhalation suspension, based on prior asthma therapy, are listed in the following table. Previous Therapy Recommended Starting Dose Highest Recommended Dose Bronchodilators alone 0.5 mg total daily dose administered either once daily or twice daily in divided doses 0.5 mg total daily dose Inhaled Corticosteroids 0.5 mg total daily dose administered either once daily or twice daily in divided doses 1 mg total daily dose Oral Corticosteroids 1 mg total daily dose administered as 0.5 mg twice daily 1 mg total daily dose Recommended dosing based on previous therapy ( 2 ).
Start with the lowest recommended dose: Bronchodilators alone: 0.5 mg once daily or 0.25 mg twice daily Inhaled corticosteroids: 0.5 mg once daily or 0.25 mg twice daily up to 0.5 mg twice daily Oral corticosteroids: 0.5 mg twice daily In symptomatic children not responding to non-steroidal therapy, a starting dose of 0.25 mg once daily may be considered If once-daily treatment does not provide adequate control, the total daily dose should be increased and/or administered as a divided dose. Once asthma stability is achieved, titrate the dose downwards.
For inhalation use via compressed air driven jet nebulizers only (not for use with ultrasonic devices). Not for injection. ( 2.2 )
2.1Dosing Recommendations Dosing recommendations based on previous therapy are as follows: Bronchodilators alone: 0.5 mg once daily or 0.25 mg twice daily Inhaled corticosteroids: 0.5 mg once daily or 0.25 mg twice daily up to 0.5 mg twice daily Oral corticosteroids: 0.5 mg twice daily In symptomatic children not responding to non-steroidal therapy, a starting dose of 0.25 mg once daily may be considered. If once-daily treatment does not provide adequate control, the total daily dose should be increased and/or administered as a divided dose.
In all patients, it is desirable to downward-titrate to the lowest effective dose once asthma stability is achieved.
2.2Directions for Use Budesonide inhalation suspension should be administered via jet nebulizer connected to an air compressor with an adequate air flow, equipped with a mouthpiece or suitable face mask. Ultrasonic nebulizers are not suitable for the adequate administration of budesonide inhalation suspension and, therefore, are NOT recommended. The effects of mixing budesonide inhalation suspension with other nebulizable medications have not been adequately assessed.
Budesonide inhalation suspension should be administered separately in the nebulizer [see Patient Counseling Information ( 17.1 ) ]. A Pari-LC-Jet Plus ® Nebulizer (with face mask or mouthpiece) connected to a Pari Master ® compressor was used to deliver budesonide inhalation suspension to each patient in 3 U.S. controlled clinical studies. The safety and efficacy of budesonide inhalation suspension delivered by other nebulizers and compressors have not been established.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Budesonide inhalation suspension is available in two strengths, each containing 2 mL: 0.25 mg/2 mL and 0.5 mg/2 mL. Budesonide inhalation suspension is supplied in sealed aluminum foil pouches, each containing one single-dose vial. There are 30 vials in a carton. Each single-dose vial contains 2 mL of sterile liquid suspension. Inhalation suspension: 0.25 mg/2 mL, 0.5 mg/2 mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS The use of budesonide inhalation suspension is contraindicated in the following conditions: Primary treatment of status asthmaticus or other acute episodes of asthma where intensive measures are required. Hypersensitivity to budesonide or any of the ingredients of budesonide inhalation suspension [see Warnings and Precautions ( 5.3 ), Description ( 11 ), Adverse Reactions ( 6.2 ) ]. Primary treatment of status asthmaticus or other acute episodes of asthma where intensive measures are required ( 4 ) Hypersensitivity to any of the ingredients in budesonide inhalation suspension ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Localized Infections: Candida albicans infection of the mouth and throat may occur. Monitor patients periodically for signs of adverse effects on the oral cavity. Advise patients to rinse the mouth following inhalation ( 5.1 ) Deterioration of Disease and Acute Asthma Episodes: Do not use for the relief of acute bronchospasm ( 5.2 ) Hypersensitivity Reactions: Anaphylaxis, rash, contact dermatitis, urticaria, angioedema, and bronchospasm have been reported with use of budesonide inhalation suspension.
Discontinue budesonide inhalation suspension if such reactions occur ( 5.3 ) Immunosuppression: Potential worsening of infections (e.g., existing tuberculosis, fungal, bacterial, viral, or parasitic infection; or ocular herpes simplex). Use with caution in patients with these infections. More serious or even fatal course of chickenpox or measles can occur in susceptible patients ( 5.4 ) Transferring Patients from Systemic Corticosteroid Therapy: Risk of impaired adrenal function when transferring from oral steroids.
Taper patients slowly from systemic corticosteroids if transferring to budesonide inhalation suspension ( 5.5 ) Hypercorticism and Adrenal Suppression: May occur with very high dosages or at the regular dosage in susceptible individuals. If such changes occur, reduce budesonide inhalation suspension slowly. ( 5.6 ) Reduction in Bone Mineral Density with Long-term Administration: Monitor patients with major risk factors for decreased bone mineral content ( 5.7 ) Effects on Growth: Monitor growth of pediatric patients ( 5.8 ) Glaucoma and Cataracts: Close monitoring is warranted ( 5.9 ) Paradoxical Bronchospasm: Discontinue budesonide inhalation suspension and institute alternative therapy if paradoxical bronchospasm occurs ( 5.10 ) Eosinophilic Conditions and Churg-Strauss Syndrome: Be alert to eosinophilic conditions ( 5.11 )
5.1Local Effects In clinical trials with budesonide inhalation suspension, localized infections with Candida albicans occurred in the mouth and pharynx in some patients. The incidences of localized infections of Candida albicans were similar between the placebo and budesonide inhalation suspension treatment groups. If these infections develop, they may require treatment with appropriate local or systemic antifungal therapy and/or discontinuance of treatment with budesonide inhalation suspension.
Patients should rinse the mouth after inhalation of budesonide inhalation suspension.
5.2Deterioration of Disease and Acute Asthma Episodes Budesonide inhalation suspension is not a bronchodilator and is not indicated for the rapid relief of acute bronchospasm or other acute episodes of asthma. Patients should be instructed to contact their physician immediately if episodes of asthma not responsive to their usual doses of bronchodilators occur during the course of treatment with budesonide inhalation suspension. During such episodes, patients may require therapy with oral corticosteroids.
5.3Hypersensitivity Reactions Including Anaphylaxis Hypersensitivity reactions including anaphylaxis, rash, contact dermatitis, urticaria, angioedema, and bronchospasm have been reported with use of budesonide inhalation suspension. Discontinue budesonide inhalation suspension if such reactions occur [see Contraindications ( 4 ) ].
5.4Immunosuppression Patients who are on drugs that suppress the immune system are more susceptible to infection than healthy individuals. Chicken pox and measles, for example, can have a more serious or even fatal course in susceptible children or adults using corticosteroids. In children or adults who have not had these diseases, or been properly immunized, particular care should be taken to avoid exposure.
How the dose, route, and duration of corticosteroid administration affect the risk of developing a disseminated infection is not known. The contribution of the underlying disease and/or prior corticosteroid treatment to the risk is also not known. If exposed…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Systemic and inhaled corticosteroid use may result in the following: Candida albicans Infection [see Warnings and Precautions ( 5.1 ) ] Hypersensitivity Reactions Including Anaphylaxis [see Warnings and Precautions ( 5.3 ) ] Immunosuppression [see Warnings and Precautions ( 5.4 ) ] Hypercorticism and Adrenal Suppression [see Warnings and Precautions ( 5.6 ) ] Reduction in Bone Mineral Density [see Warnings and Precautions ( 5.7 ) ] Growth Effects in Pediatric Patients [see Warnings and Precautions ( 5.8 ), Use in Specific Populations ( 8.4 ) ] Glaucoma, Increased Intraocular Pressure and Cataracts [see Warnings and Precautions ( 5.9 ) ] Eosinophilic Conditions and Churg-Strauss Syndrome [see Warnings and Precautions ( 5.11 ) ] Most common adverse reactions (incidence > 3%) are respiratory infection, rhinitis, coughing, otitis media, viral infection, moniliasis, gastroenteritis, vomiting, diarrhea, abdominal pain, ear infection, epistaxis, conjunctivitis, rash ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva Pharmaceuticals USA, Inc. at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The incidence of common adverse reactions is based on three double-blind, placebo-controlled, randomized U.S. clinical trials in which 945 patients, 12 months to 8 years of age, (98 patients ≥12 months and <2 years of age; 225 patients ≥2 and <4 years of age; and 622 patients ≥4 and ≤8 years of age) were treated with budesonide inhalation suspension (0.25 to 1 mg total daily dose for 12 weeks) or vehicle placebo.
The incidence and nature of adverse events reported for budesonide inhalation suspension was comparable to that reported for placebo. The following table shows the incidence of adverse events in U.S. controlled clinical trials, regardless of relationship to treatment, in patients previously receiving bronchodilators and/or inhaled corticosteroids. This population included a total of 605 male and 340 female patients and 78.4% were Caucasian, 13.8% African American, 5.5% Hispanic and 2.3% Other.
Table 1 - Adverse Reactions Occurring at an Incidence of ≥3% in at Least One Active Treatment Group Where the Incidence was Higher With Budesonide Inhalation Suspension Than Placebo Budesonide Inhalation Suspension Vehicle Placebo (n = 227) % Total Daily Dose 0.25 mg (n=178) % 0.5 mg (n = 223) % 1 mg (n = 317) % Adverse Events Respiratory System Disorder Respiratory Infection 36 34 35 38 Rhinitis 9 7 11 12 Coughing 5 5 9 8 Resistance Mechanism Disorders Otitis Media 11 12 11 9 Viral Infection 3 4 5 3 Moniliasis 2 4 3 4 Gastrointestinal System Disorders Gastroenteritis 4 5 5 5 Vomiting 3 2 4 4 Diarrhea 2 4 4 2 Abdominal Pain 2 3 2 3 Hearing and Vestibular Disorders Ear Infection 4 2 4 5 Platelet, Bleeding and Clotting Disorders Epistaxis 1 2 4 3 Vision Disorders Conjunctivitis 2 <1 4 2 Skin and Appendages Disorders Rash 3 <1 4 2 The information below includes all adverse reactions by system organ class with an incidence of 1 to < 3%, in at least one budesonide inhalation suspension treatment group where the incidence was higher with budesonide inhalation suspension than with placebo, regardless of relationship to treatment.
Blood and lymphatic system disorders: cervical lymphadenopathy Ear and labyrinth disorders: earache General disorders and administration site conditions: fatigue, flu-like disorder Immune system disorders: allergic reaction Infections and infestations: eye infection, herpes simplex, external ear infection, infection Injury, poisoning and procedural complication: fracture Metabolism and nutrition disorders: anorexia Musculoskeletal and connective tissue disorders: myalgia Nervous system disorders:…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong Cytochrome P450 3A4 Inhibitors (e.g., ritonavir): Use with caution. May cause increased systemic corticosteroid effects ( 5.12 , 7.1 )
7.1Inhibitors of Cytochrome P450 3A4 The main route of metabolism of corticosteroids, including budesonide, is via cytochrome P450 (CYP) isoenzyme 3A4 (CYP3A4). After oral administration of ketoconazole, a strong inhibitor of CYP3A4, the mean plasma concentration of orally administered budesonide increased. Concomitant administration of a CYP3A4 inhibitor may inhibit the metabolism of, and increase the systemic exposure to, budesonide.
Caution should be exercised when considering the coadministration of budesonide inhalation suspension with long-term ketoconazole and other known strong CYP3A4 inhibitors (e.g., ritonavir, atazanavir, clarithromycin, indinavir, itraconazole, nefazodone, nelfinavir, saquinavir, telithromycin) [ see Warnings and Precautions ( 5.12 ), Clinical Pharmacology ( 12.3 ) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate well-controlled studies of budesonide inhalation suspension in pregnant women. However, there are published studies on the use of budesonide, the active ingredient in budesonide inhalation suspension, in pregnant women. In animal reproduction studies, budesonide, administered by the subcutaneous route, caused structural abnormalities, was embryocidal, and reduced fetal weights in rats and rabbits at less than the maximum recommended human daily inhalation dose (MRHDID), but these effects were not seen in rats that received inhaled doses approximately 2 times the MRHDID ( see Data ).
Studies of pregnant women have not shown that inhaled budesonide increases the risk of abnormalities when administered during pregnancy. Experience with oral corticosteroids suggests that rodents are more prone to structural abnormalities from corticosteroid exposure than humans. The estimated background risk of major birth defects and miscarriage of the indicated populations is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal risk In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal adverse outcomes such as preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. Pregnant women with asthma should be closely monitored and medication adjusted as necessary to maintain optimal asthma control.
Labor or Delivery There are no well-controlled human studies that have investigated the effects of budesonide inhalation suspension during labor and delivery. Data Human Data Studies of pregnant women have not shown that inhaled budesonide increases the risk of abnormalities when administered during pregnancy. The results from a large population-based prospective cohort epidemiological study reviewing data from three Swedish registries covering approximately 99% of the pregnancies from 1995 to 1997 (i.e., Swedish Medical Birth Registry; Registry of Congenital Malformations; Child Cardiology Registry) indicate no increased risk for congenital malformations from the use of inhaled budesonide during early pregnancy.
Congenital malformations were studied in 2014 infants born to mothers reporting the use of inhaled budesonide for asthma in early pregnancy (usually 10 to 12 weeks after the last menstrual period), the period when most major organ malformations occur. The rate of recorded congenital malformations was similar compared to the general population rate (3.8% vs. 3.5%, respectively).
In addition, after exposure to inhaled budesonide, the number of infants born with orofacial clefts was similar to the expected number in the normal population (4 children vs. 3.3, respectively). These same data were utilized in a second study bringing the total to 2534 infants whose mothers were exposed to inhaled budesonide.
In this study, the rate of congenital malformations among infants whose mothers were exposed to inhaled budesonide during early pregnancy was not different from the rate for all newborn babies during the same period (3.6%). Animal Data In a fertility and reproduction study, male rats were subcutaneously dosed for 9 weeks and females for 2 weeks prior to pairing and throughout the mating period. Females were dosed up until weaning of their offspring.
Budesonide caused a decrease in prenatal viability and viability in the pups at birth and during lactation, along with a decrease in maternal body-weight gain, at doses 0.2 times the MRHDID (on a mcg/m 2 basis at maternal subcutaneous doses of 20 mcg/kg/day and above). No such effects were noted at a dose 0.05 times the MRHDID (on a mcg/m 2 basis at a maternal subcutaneous dose of 5 mcg/kg/day). In an embryo-fetal development stu…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate well-controlled studies of budesonide inhalation suspension in pregnant women. However, there are published studies on the use of budesonide, the active ingredient in budesonide inhalation suspension, in pregnant women. In animal reproduction studies, budesonide, administered by the subcutaneous route, caused structural abnormalities, was embryocidal, and reduced fetal weights in rats and rabbits at less than the maximum recommended human daily inhalation dose (MRHDID), but these effects were not seen in rats that received inhaled doses approximately 2 times the MRHDID ( see Data ).
Studies of pregnant women have not shown that inhaled budesonide increases the risk of abnormalities when administered during pregnancy. Experience with oral corticosteroids suggests that rodents are more prone to structural abnormalities from corticosteroid exposure than humans. The estimated background risk of major birth defects and miscarriage of the indicated populations is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal risk In women with poorly or moderately controlled asthma, there is an increased risk of several perinatal adverse outcomes such as preeclampsia in the mother and prematurity, low birth weight, and small for gestational age in the neonate. Pregnant women with asthma should be closely monitored and medication adjusted as necessary to maintain optimal asthma control.
Labor or Delivery There are no well-controlled human studies that have investigated the effects of budesonide inhalation suspension during labor and delivery. Data Human Data Studies of pregnant women have not shown that inhaled budesonide increases the risk of abnormalities when administered during pregnancy. The results from a large population-based prospective cohort epidemiological study reviewing data from three Swedish registries covering approximately 99% of the pregnancies from 1995 to 1997 (i.e., Swedish Medical Birth Registry; Registry of Congenital Malformations; Child Cardiology Registry) indicate no increased risk for congenital malformations from the use of inhaled budesonide during early pregnancy.
Congenital malformations were studied in 2014 infants born to mothers reporting the use of inhaled budesonide for asthma in early pregnancy (usually 10 to 12 weeks after the last menstrual period), the period when most major organ malformations occur. The rate of recorded congenital malformations was similar compared to the general population rate (3.8% vs. 3.5%, respectively).
In addition, after exposure to inhaled budesonide, the number of infants born with orofacial clefts was similar to the expected number in the normal population (4 children vs. 3.3, respectively). These same data were utilized in a second study bringing the total to 2534 infants whose mothers were exposed to inhaled budesonide.
In this study, the rate of congenital malformations among infants whose mothers were exposed to inhaled budesonide during early pregnancy was not different from the rate for all newborn babies during the same period (3.6%). Animal Data In a fertility and reproduction study, male rats were subcutaneously dosed for 9 weeks and females for 2 weeks prior to pairing and throughout the mating period. Females were dosed up until weaning of their offspring.
Budesonide caused a decrease in prenatal viability and viability in the pups at birth and during lactation, along with a decrease in maternal body-weight gain, at doses 0.2 times the MRHDID (on a mcg/m 2 basis at maternal subcutaneous doses of 20 mcg/kg/day and above). No such effects were noted at a dose 0.05 times the MRHDID (on a mcg/m 2 basis at a maternal subcutaneous dose of 5 mcg/kg/day). In an embryo-fetal development study in pregnant rabbits dosed d…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in children six months to 12 months of age has been evaluated but not established. Safety and effectiveness in children 12 months to 8 years of age have been established [see Clinical Pharmacology ( 12.2 ), Adverse Reactions ( 6.1 ) ]. A 12 week study in 141 pediatric patients 6 to 12 months of age with mild to moderate asthma or recurrent/persistent wheezing was conducted.
All patients were randomized to receive either 0.5 mg or 1 mg of budesonide inhalation suspension or placebo once daily. Adrenal-axis function was assessed with an ACTH stimulation test at the beginning and end of the study, and mean changes from baseline in this variable did not indicate adrenal suppression in patients who received budesonide inhalation suspension versus placebo. However, on an individual basis, 7 patients in this study (6 in the budesonide inhalation suspension treatment arms and 1 in the placebo arm) experienced a shift from having a normal baseline stimulated cortisol level to having a subnormal level at Week 12 [ see Clinical Pharmacology ( 12.2 ) ].
Pneumonia was observed more frequently in patients treated with budesonide inhalation suspension than in patients treated with placebo, (N = 2, 1, and 0) in the budesonide inhalation suspension 0.5 mg, 1 mg, and placebo groups, respectively. A dose dependent effect on growth was also noted in this 12 week trial. Infants in the placebo arm experienced an average growth of 3.7 cm over 12 weeks compared with 3.5 cm and 3.1 cm in the budesonide inhalation suspension 0.5 mg and 1 mg arms respectively.
This corresponds to estimated mean (95% CI) reductions in 12 week growth velocity between placebo and budesonide inhalation suspension 0.5 mg of 0.2 cm (-0.6 to 1.0) and between placebo and budesonide inhalation suspension 1 mg of 0.6 cm (-0.2 to 1.4). These findings support that the use of budesonide inhalation suspension in infants 6 to 12 months of age may result in systemic effects and are consistent with findings of growth suppression in other studies with inhaled corticosteroids. Controlled clinical studies have shown that inhaled corticosteroids may cause a reduction in growth velocity in pediatric patients.
In these studies, the mean reduction in growth velocity was approximately one centimeter per year (range 0.3 to 1.8 cm per year) and appears to be related to dose and duration of exposure. This effect has been observed in the absence of laboratory evidence of hypothalamic-pituitary-adrenal (HPA)-axis suppression, suggesting that growth velocity is a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA-axis function. The long-term effects of this reduction in growth velocity associated with orally inhaled corticosteroids, including the impact on final adult height, are unknown.
The potential for “catch up” growth following discontinuation of treatment with orally inhaled corticosteroids has not been adequately studied. In a study of asthmatic children 5 to 12 years of age, those treated with budesonide administered via a dry powder inhaler 200 mcg twice daily (n=311) had a 1.1 centimeter reduction in growth compared with those receiving placebo (n=418) at the end of one year; the difference between these two treatment groups did not increase further over three years of additional treatment.
By the end of four years, children treated with the budesonide dry powder inhaler and children treated with placebo had similar growth velocities. Conclusions drawn from this study may be confounded by the unequal use of corticosteroids in the treatment groups and inclusion of data from patients attaining puberty during the course of the study. The growth of pediatric patients receiving inhaled corticosteroids, including budesonide inhalation suspension, should be monitored routinely (e.g., via stadiometry).
The potential growth effects of prolonged treatment should be weighed against clinical…
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 215 patients in 3 clinical trials of budesonide inhalation suspension in adult patients, 65 (30%) were 65 years of age or older, while 22 (10%) were 75 years of age or older. No overall differences in safety were observed between these patients and younger patients, and other reported clinical or medical surveillance experience has not identified differences in responses between the elderly and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE The potential for acute toxic effects following overdose of budesonide inhalation suspension is low. If inhaled corticosteroids are used at excessive doses for prolonged periods, systemic corticosteroid effects such as hypercorticism or growth suppression may occur [see Warnings and Precautions ( 5.6 ) ].
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Budesonide is an anti-inflammatory corticosteroid that exhibits potent glucocorticoid activity and weak mineralocorticoid activity. In standard in vitro and animal models, budesonide has approximately a 200 fold higher affinity for the glucocorticoid receptor and a 1000 fold higher topical anti-inflammatory potency than cortisol (rat croton oil ear edema assay). As a measure of systemic activity, budesonide is 40 times more potent than cortisol when administered subcutaneously and 25 times more potent when administered orally in the rat thymus involution assay.
The clinical significance of these findings is unknown. The activity of budesonide inhalation suspension is due to the parent drug, budesonide. In glucocorticoid receptor affinity studies, the 22R form was two times as active as the 22S epimer.
In vitro studies indicated that the two forms of budesonide do not interconvert. The precise mechanism of corticosteroid actions on inflammation in asthma is not well known. Inflammation is an important component in the pathogenesis of asthma.
Corticosteroids have been shown to have a wide range of inhibitory activities against multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in allergic- and non-allergic-mediated inflammation. The anti-inflammatory actions of corticosteroids may contribute to their efficacy in asthma. Studies in asthmatic patients have shown a favorable ratio between topical anti-inflammatory activities and systemic corticosteroid effects over a wide dose range of inhaled budesonide in a variety of formulations and delivery systems including an inhalation-driven, multi-dose dry powder inhaler and the inhalation suspension for nebulization.
This is explained by a combination of a relatively high local anti-inflammatory effect, extensive first pass hepatic degradation of orally absorbed drug (85 to 95%) and the low potency of metabolites (see below).
12.2Pharmacodynamics The therapeutic effects of conventional doses of orally inhaled budesonide are largely explained by its direct local action on the respiratory tract. To confirm that systemic absorption is not a significant factor in the clinical efficacy of inhaled budesonide, a clinical study in adult patients with asthma was performed comparing 400 mcg budesonide administered via a pressurized metered dose inhaler with a tube spacer to 1400 mcg of oral budesonide and placebo. The study demonstrated the efficacy of inhaled budesonide but not orally administered budesonide, even though systemic budesonide exposure was comparable for both treatments, indicating that the inhaled treatment is working locally in the lung.
Thus, the therapeutic effect of conventional doses of orally inhaled budesonide are largely explained by its direct action on the respiratory tract. Improvement in the control of asthma symptoms following inhalation of budesonide inhalation suspension can occur within 2 to 8 days of beginning treatment, although maximum benefit may not be achieved for 4 to 6 weeks. Budesonide administered via a dry powder inhaler has been shown in various challenge models (including histamine, methacholine, sodium metabisulfite, and adenosine monophosphate) to decrease bronchial hyperresponsiveness in asthmatic patients.
The clinical relevance of these models is not certain. Pre-treatment with budesonide administered as 1600 mcg daily (800 mcg twice daily) via a dry powder inhaler for 2 weeks reduced the acute (early-phase reaction) and delayed (late-phase reaction) decrease in FEV 1 following inhaled allergen challenge. HPA Axis Effects The effects of budesonide inhalation suspension on the hypothalamic-pituitary-adrenal (HPA) axis were studied in three, 12 week, double-blind, placebo-controlled studies in 293 pediatric patients, 6 months to 8 years of age, with persistent asthma.
For mos…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Budesonide is an anti-inflammatory corticosteroid that exhibits potent glucocorticoid activity and weak mineralocorticoid activity. In standard in vitro and animal models, budesonide has approximately a 200 fold higher affinity for the glucocorticoid receptor and a 1000 fold higher topical anti-inflammatory potency than cortisol (rat croton oil ear edema assay). As a measure of systemic activity, budesonide is 40 times more potent than cortisol when administered subcutaneously and 25 times more potent when administered orally in the rat thymus involution assay.
The clinical significance of these findings is unknown. The activity of budesonide inhalation suspension is due to the parent drug, budesonide. In glucocorticoid receptor affinity studies, the 22R form was two times as active as the 22S epimer.
In vitro studies indicated that the two forms of budesonide do not interconvert. The precise mechanism of corticosteroid actions on inflammation in asthma is not well known. Inflammation is an important component in the pathogenesis of asthma.
Corticosteroids have been shown to have a wide range of inhibitory activities against multiple cell types (e.g., mast cells, eosinophils, neutrophils, macrophages, and lymphocytes) and mediators (e.g., histamine, eicosanoids, leukotrienes, and cytokines) involved in allergic- and non-allergic-mediated inflammation. The anti-inflammatory actions of corticosteroids may contribute to their efficacy in asthma. Studies in asthmatic patients have shown a favorable ratio between topical anti-inflammatory activities and systemic corticosteroid effects over a wide dose range of inhaled budesonide in a variety of formulations and delivery systems including an inhalation-driven, multi-dose dry powder inhaler and the inhalation suspension for nebulization.
This is explained by a combination of a relatively high local anti-inflammatory effect, extensive first pass hepatic degradation of orally absorbed drug (85 to 95%) and the low potency of metabolites (see below).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Illustrated Patient's Instructions for Use accompany each package of budesonide inhalation suspension. Budesonide inhalation suspension, 0.25 mg/2 mL is supplied in a single-dose vial. Each single-dose vial contains 2 mL of sterile liquid suspension, supplied in unit-dose cartons of 30 (NDC 0093-6815-55) individually pouched vials.
Budesonide inhalation suspension, 0.5 mg/2 mL is supplied in a single-dose vial. Each single-dose vial contains 2 mL of sterile liquid suspension, supplied in unit-dose cartons of 30 (NDC 0093-6816-55) individually pouched vials. Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Protect from light. Any opened vial must be used promptly. Gently shake the vial using a circular motion before use.
Keep out of reach of children. Do not freeze.
📋 Description ▾
11 DESCRIPTION Budesonide, USP, the active component of budesonide inhalation suspension, is a corticosteroid designated chemically as ( RS )-11β,16α,17,21-tetrahydroxypregna-1,4-diene-3,20-dione cyclic 16,17-acetal with butyraldehyde. Budesonide, USP is provided as a mixture of two epimers (22R and 22S) and it has the following structural formula: Budesonide, USP is a white to off-white, tasteless, odorless powder that is practically insoluble in water and in heptane, sparingly soluble in ethanol, and freely soluble in chloroform.
Its partition coefficient between octanol and water at pH 7.4 is 1.6 x 10 3 . Budesonide inhalation suspension is a sterile suspension for inhalation via jet nebulizer and contains the active ingredient budesonide, USP (micronized), and the inactive ingredients: citric acid monohydrate, disodium edetate, polysorbate 80, sodium chloride, tri-sodium citrate dihydrate and water for injection. Two dose strengths are available in single-dose vials: 0.25 mg and 0.5 mg per 2 mL vial.
For budesonide inhalation suspension, like all other nebulized treatments, the amount delivered to the lungs will depend on patient factors, the jet nebulizer utilized, and compressor performance. Using the Pari-LC-Jet Plus ® Nebulizer/Pari Master ® compressor system, under in vitro conditions, the mean delivered dose at the mouthpiece (% nominal dose) was approximately 17% at a mean flow rate of
5.5L/min. The mean nebulization time was 5 minutes or less. Budesonide inhalation suspension should be administered from jet nebulizers at adequate flow rates, via face masks or mouthpieces [see Dosage and Administration ( 2 ) ]. Chemical structure for budesonide
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION
17.1Administration With a Jet Nebulizer Patients should be advised that budesonide inhalation suspension should be administered with a jet nebulizer connected to a compressor with an adequate air flow, equipped with a mouthpiece or suitable face mask. Ultrasonic nebulizers are not suitable for the adequate administration of budesonide inhalation suspension and, therefore, are not recommended. The effects of mixing budesonide inhalation suspension with other nebulizable medications have not been adequately assessed.
Budesonide inhalation suspension should be administered separately in the nebulizer [see Dosage and Administration ( 2 ) ].
17.2Oral Candidiasis Patients should be advised that localized infections with Candida albicans occurred in the mouth and pharynx in some patients. If oropharyngeal candidiasis develops, it should be treated with appropriate local or systemic (i.e., oral) antifungal therapy while still continuing therapy with budesonide inhalation suspension, but at times therapy with budesonide inhalation suspension may need to be temporarily interrupted under close medical supervision. Rinsing the mouth after inhalation is advised [see Warnings and Precautions ( 5.1 ) ].
17.3Not for Acute Symptoms Budesonide inhalation suspension is not meant to relieve acute asthma symptoms and extra doses should not be used for that purpose. Acute symptoms should be treated with an inhaled, short-acting beta 2 -agonist such as albuterol. (The healthcare professional should provide that patient with such medication and instruct the patient in how it should be used).
Patients should be instructed to notify their healthcare professional immediately if they experience any of the following: Decreasing effectiveness of inhaled, short-acting beta 2 -agonists Need for more inhalations than usual of inhaled, short-acting beta 2 -agonists Significant decrease in lung function as outlined by the physician Patients should not stop therapy with budesonide inhalation suspension without physician/provider guidance since symptoms may recur after discontinuation [see Warnings and Precautions ( 5.2 ) ].
17.4Hypersensitivity Including Anaphylaxis Hypersensitivity reactions including anaphylaxis, rash, contact dermatitis, urticaria, angioedema, and bronchospasm have been reported with use of budesonide inhalation suspension. Discontinue budesonide inhalation suspension if such reactions occur [see Contraindications ( 4 ), Warnings and Precautions ( 5.3 )].
17.5Immunosuppression Patients who are on immunosuppressant doses of corticosteroids should be warned to avoid exposure to chickenpox or measles and, if exposed, to consult their physician without delay. If exposure to such a person occurs, and the child has not had chicken pox or been properly vaccinated, a physician should be consulted without delay. Patients should be informed of potential worsening of existing tuberculosis, fungal, bacterial, viral, or parasitic infections, or ocular herpes simplex [see Warnings and Precautions ( 5.4 )].
17.6Hypercorticism and Adrenal Suppression Patients should be advised that budesonide inhalation suspension may cause systemic corticosteroid effects of hypercorticism and adrenal suppression. Additionally, patients should be instructed that deaths due to adrenal insufficiency have occurred during and after transfer from systemic corticosteroids. Patients should taper slowly from systemic corticosteroids if transferring to budesonide inhalation suspension [ see Warnings and Precautions ( 5.6 ) ].
17.7Reduction in Bone Mineral Density Patients who are at an increased risk for decreased BMD should be advised that the use of corticosteroids may pose an additional risk [see Warnings and Precautions ( 5.7 ) ].
17.8Reduced Growth Velocity Patients should be informed that orally inhaled corticosteroids, including budesonide inhalation suspension, may cause a reduction in growth velocity when administered to pediatric pa…