
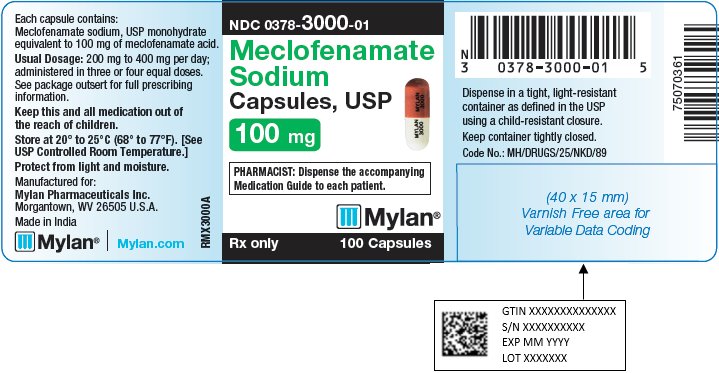
Meclofenamate Sodium 100 mg Capsule, 100-count — NDC 0378-3000-01 (Billing 00378-3000-01)
This is a package of 100 capsules of Meclofenamate Sodium 100 mg Capsule from Mylan Pharmaceuticals Inc., marketed since Sep 1986 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0378-3000-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0378 labeler · 3000 product · 01 package
- Package marketed since
- Sep 3, 1986
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 100 EA per package
- Barcode (UPC)
- 0303783000015, 0303782150018
- Medicaid fills, this package
- 85 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008367
- GCN: 35810
- GPI-14 (Medi-Span): 66100040100110
- HICL (First Databank): 003730
- AHFS class code: 28:08.04.04
- RxCUI (RxNorm): 618552
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
Clinical
Meclofenamate is used to relieve pain, tenderness, swelling, and stiffness caused by osteoarthritis (arthritis caused by a breakdown of the lining of the joints), rheumatoid arthritis (arthritis caused by swelling of the lining of the joints), juvenile arthritis(chronic inflammatory disease causing pain, swelling and stiffness in joints of children), ankylosing spondylitis (type of arthritis that can cause inflammation in the spine and other joints), acute painful shoulder(pain and immobility in shoulder that happens suddenly for a number of reasons), and acute gouty arthritis(sudden attack of...
Read the full MedlinePlus article ↗- It is an NSAID used in adults for fever and mild to moderate pain. It also treats arthritis symptoms, painful periods and heavy menstrual bleeding. It is also used for ankylosing s...
- Take the capsules by mouth, as often as your prescriber directs. If your stomach gets upset, take them with meals or milk. Food can lower how much drug you absorb, so ask me about...
- Diarrhea is the most common side effect, and nausea and stomach pain are also common. Tell your doctor if diarrhea is severe, because a lower dose may help. Black or bloody stools,...
- Aspirin is generally not recommended with meclofenamate because it raises the risk of side effects. Check with me before combining it with any other pain reliever. Tell us if you t...
Patient education
Supplement & herbal interactions
Meclofenamate may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $6.32 | $632.10 / 100 capsules |
| Medicare drug plans payPart D · Q2 2026 | $5.59 | $559.36 / 100 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00378-3000-01 You're viewing this Main listing | 100 CAPSULE in 1 BOTTLE, PLASTIC | 1986-09-03 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Meclofenamate Sodium 100 mgthis 00378-3000-01 | Mylan | 100 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Meclofenamate inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII PN2ZH5LOQY
A synthetic red dye approved by the FDA for use in foods, medicines, and cosmetics. It serves as a colorant to make tablets, capsules, and liquids visually distinctive for product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Mylan Pharmaceuticals Inc. labeler code 00378
- Trifluoperazine Hydrochloride 10 mg Tablet, Film Coated NDC 0378-2410-01
- Phenytek extended phenytoin sodium 200 mg Capsule, Extended Release NDC 0378-2670-01
- Ferric Citrate 210 mg Tablet, Film Coated NDC 0378-2895-20
- Telmisartan 20 mg Tablet NDC 0378-2920-77
- Telmisartan 40 mg Tablet NDC 0378-2921-77
- Telmisartan 80 mg Tablet NDC 0378-2922-77
- Candesartan Cilexetil and Hydrochlorothiazide 16 mg; 12.5 mg Tablet NDC 0378-3001-77
- Candesartan Cilexetil and Hydrochlorothiazide 32 mg; 25 mg Tablet NDC 0378-3003-77
- Fenofibrate 48 mg Tablet, Film Coated NDC 0378-3065-77
- Fenofibrate 145 mg Tablet, Film Coated NDC 0378-3066-05
- Doxepin Hydrochloride 25 mg Capsule NDC 0378-3125-01
- Prazosin Hydrochloride 5 mg Capsule NDC 0378-3205-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Cardiovascular Thrombotic Events • Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use (see WARNINGS and PRECAUTIONS ). • Meclofenamate sodium capsules are contraindicated in the setting of coronary artery bypass graft (CABG) surgery (see CONTRAINDICATIONS and WARNINGS ). Gastrointestinal Risk • NSAIDs cause an increased risk of serious gastrointestinal adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal.
These events can occur at any time during use and without warning symptoms. Elderly patients are at greater risk for serious gastrointestinal events. (See WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carefully consider the potential benefits and risks of meclofenamate sodium capsules and other treatment options before deciding to use meclofenamate sodium capsules. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). Meclofenamate sodium capsules are indicated: • For reduction of fever in adults • For relief of mild to moderate pain in adults • For relief of signs and symptoms of juvenile arthritis. • For relief of the signs and symptoms of rheumatoid arthritis • For relief of the signs and symptoms of osteoarthritis. • For treatment of primary dysmenorrhea. • For acute or long-term use in the relief of signs and symptoms of the following: 1.
Ankylosing spondylitis 2. Acute painful shoulder (Acute subacromial bursitis/supraspinatus tendinitis) 3. Acute gouty arthritis Meclofenamate sodium capsules are also indicated for the treatment of idiopathic heavy menstrual blood loss (see CLINICAL PHARMACOLOGY and PRECAUTIONS ).
As with all nonsteroidal anti-inflammatory drugs, selection of meclofenamate sodium capsules require a careful assessment of the benefit/risk ratio (see WARNINGS , PRECAUTIONS and ADVERSE REACTIONS ). Meclofenamate sodium capsules are not recommended in children because adequate studies to demonstrate safety and efficacy have not been carried out.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Carefully consider the potential benefits and risks of meclofenamate sodium capsules and other treatment options before deciding to use meclofenamate sodium capsules. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). After observing the response to initial therapy with meclofenamate sodium capsules, the dose and frequency should be adjusted to suit an individual patient's needs.
Usual Dosage For Mild to Moderate Pain The recommended dose is 50 mg every 4 to 6 hours. Doses of 100 mg may be needed in some patients for optimal pain relief (see CLINICAL PHARMACOLOGY ). However, the daily dose should not exceed 400 mg (see ADVERSE REACTIONS ).
For excessive menstrual blood loss and primary dysmenorrheal The recommended dose of meclofenamate sodium is 100 mg 3 times a day, for up to 6 days, starting at the onset of menstrual flow. For rheumatoid arthritis and osteoarthritis (including acute exacerbations of chronic disease) The dosage is 200 mg to 400 mg per day, administered in three or four equal doses. Therapy should be initiated at the lower dosage, then increased as necessary to improve clinical response.
The dosage should be individually adjusted for each patient, depending on the severity of the symptoms and the clinical response. The daily dosage should not exceed 400 mg per day. The smallest dosage of meclofenamate sodium that yields clinical control should be employed.
Although improvement may be seen in some patients in a few days, 2 to 3 weeks of treatment may be required to obtain the optimum therapeutic benefit. After a satisfactory response has been achieved, the dosage should be adjusted as required. A lower dosage may suffice for long-term administration.
If gastrointestinal complaints occur (see WARNINGS and PRECAUTIONS ), meclofenamate sodium may be administered with meals or with milk (see CLINICAL PHARMACOLOGY for a description of food effects). If intolerance occurs, the dosage may need to be reduced. Therapy should be terminated if any severe adverse reactions occur.
⛔ Contraindications ▾
CONTRAINDICATIONS Meclofenamate sodium capsules are contraindicated in patients with known hypersensitivity to meclofenamate sodium. Meclofenamate sodium capsules should not be given to patients who have experienced asthma, urticaria, or allergic-type reactions after taking aspirin or other NSAIDs. Severe, rarely fatal, anaphylactic-like reactions to NSAIDs have been reported in such patients (see WARNINGS: Anaphylactoid Reactions and PRECAUTIONS: Preexisting Asthma ).
Meclofenamate sodium capsules are contraindicated in the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Cardiovascular Effects Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to 3 years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as meclofenamate sodium, increases the risk of serious gastrointestinal (GI) events (see WARNINGS ). Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10 to 14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG (see CONTRAINDICATIONS ). Post-MI Patients Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients.
Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next 4 years of follow-up. Avoid the use of meclofenamate sodium capsules in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If meclofenamate sodium capsules are used in patients with a recent MI, monitor patients for signs of cardiac ischemia.
Hypertension NSAIDs, including meclofenamate sodium, can lead to onset of new hypertension or worsening of preexisting hypertension, either of which may contribute to the increased incidence of CV events. Patients taking thiazides or loop diuretics may have impaired response to these therapies when taking NSAIDs. NSAIDs, including meclofenamate sodium, should be used with caution in patients with hypertension.
Blood pressure (BP) should be monitored closely during the initiation of NSAID treatment and throughout the course of therapy. Heart Failure and Edema The Coxib and traditional NSAID Trialists’ Collaboration meta-analysis of randomized controlled trials demonstrated an approximately 2-fold increase in hospitalizations for heart failure in COX-2 selective-treated patients and nonselective NSAID-treated patients compared to placebo-treated patients. In a Danish National Registry study of patients with heart failure, NSAID use increased the risk of MI, hospitalization for heart failure,… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Incidence Greater Than 1% The following adverse reactions were observed in clinical trials and included observations from more than 2,700 patients, 594 of whom were treated for one year and 248 for at least 2 years. Gastrointestinal The most frequently reported adverse reactions associated with meclofenamate sodium involve the gastrointestinal system. In controlled studies of up to 6 months duration, these disturbances occurred in the following decreasing order of frequency with the approximate incidences in parentheses: diarrhea (10% to 33%), nausea with or without vomiting (11%), other gastrointestinal disorders (10%), and abdominal pain * .
In long-term uncontrolled studies of up to 4 years duration, one third of the patients had at least one episode of diarrhea some time during meclofenamate sodium therapy. In approximately 4% of the patients in controlled studies, diarrhea was severe enough to require discontinuation of meclofenamate sodium. The occurrence of diarrhea is dose related, generally subsides with dose reduction, and clears with termination of therapy.
The incidence of diarrhea in patients with osteoarthritis is generally lower than that reported in patients with rheumatoid arthritis. Other reactions less frequently reported were pyrosis * , flatulence * , anorexia, constipation, stomatitis, and peptic ulcer. The majority of the patients with peptic ulcer had either a history of ulcer disease or were receiving concomitant anti-inflammatory drugs, including corticosteroids which are known to produce peptic ulceration.
Cardiovascular: edema Dermatologic: rash * , urticaria, pruritus Central Nervous System: headache * , dizziness * Special Senses: tinnitus * Incidence between 3% and 9%. Those reactions occurring in 1% to 3% of patients are not marked with an asterisk. Incidence Less Than 1%—Probably Causally Related The following adverse reactions were reported less frequently than 1% during controlled clinical trials and through voluntary reports since marketing.
The probability of a causal relationship exists between the drug and these adverse reactions. Gastrointestinal: bleeding and/or perforation with or without obvious ulcer formation, colitis, cholestatic jaundice Renal: renal failure Hematologic: neutropenia, thrombocytopenic purpura, leukopenia, agranulocytosis, hemolytic anemia, eosinophilia, decrease in hemoglobin and/or hematocrit Dermatologic: erythema multiforme, Stevens-Johnson Syndrome, exfoliative dermatitis, toxic epidermal necrolysis (TEN), and fixed drug eruption (FDE) Hepatic: alteration of liver function tests Allergic: lupus and serum sickness-like symptoms Incidence Less Than 1%—Causal Relationship Unknown Other reactions have been reported but under conditions where a causal relationship could not be established.
However, in these rarely reported events, that possibility cannot be excluded. Therefore, these observations are listed to alert physicians. Cardiovascular: palpitations Central Nervous System: malaise, fatigue, paresthesia, insomnia, depression Special Senses: blurred vision, taste disturbances, decreased visual acuity, temporary loss of vision, reversible loss of color vision, retinal changes including macular fibrosis, macular and perimacular edema, conjunctivitis, iritis Renal: nocturia Gastrointestinal: paralytic ileus Dermatologic: erythema nodosum, hair loss
🔄 Drug Interactions ▾
Drug Interactions ACE-inhibitors Reports suggest that NSAIDs may diminish the antihypertensive effect of ACE-inhibitors. This interaction should be given consideration in patients taking NSAIDs concomitantly with ACE-inhibitors. Aspirin When meclofenamate sodium in administered with aspirin, its protein binding is reduced, although the clearance of free meclofenamate sodium is not altered.
The clinical significance of this interaction is not known; however, as with other NSAIDs, concomitant administration of meclofenamate sodium capsules and aspirin is not generally recommended because of the potential of increased adverse effects. Furosemide Clinical studies, as well as post-marketing observations, have shown that meclofenamate sodium can reduce the natriuretic effect-of furosemide and thiazides in some patients. This response has been attributed to inhibition of renal prostaglandin synthesis.
During concomitant therapy with NSAIDs, the patient should be observed closely for signs of renal failure (see PRECAUTIONS: Renal Effects ), as well as to assure diuretic efficacy. Lithium NSAIDs have produced an elevation of plasma lithium levels and a reduction in renal lithium clearance. The mean minimum lithium concentration increased 15% and the renal clearance was decreased by approximately 20%.
These effects have been attributed to inhibition of renal prostaglandin synthesis by the NSAID. Thus, when NSAIDs and lithium are administered concurrently, subjects should be observed carefully for signs of lithium toxicity. Methotrexate NSAIDs have been reported to competitively inhibit methotrexate accumulation in rabbit kidney slices.
This may indicate that they could enhance the toxicity of methotrexate. Caution should be used when NSAIDs are administered concomitantly with methotrexate. Warfarin The effects of warfarin and NSAIDs on GI bleeding are synergistic, such that users of both drugs together have a risk of serious GI bleeding higher than users of either drug alone.
🤰 Pregnancy ▾
Pregnancy Risk Summary Use of NSAIDs, including meclofenamate sodium capsules, can cause premature closure of the fetal ductus arteriosus and fetal renal dysfunction leading to oligohydramnios and, in some cases, neonatal renal impairment. Because of these risks, limit dose and duration of meclofenamate sodium capsules use between about 20 and 30 weeks of gestation, and avoid meclofenamate sodium capsules use at about 30 weeks of gestation and later in pregnancy (see WARNINGS: Fetal Toxicity ). Premature Closure of Fetal Ductus Arteriosus Use of NSAIDs, including meclofenamate sodium capsules, at about 30 weeks gestation or later in pregnancy increases the risk of premature closure of the fetal ductus arteriosus.
Oligohydramnios/Neonatal Renal Impairment Use of NSAIDs at about 20 weeks gestation or later in pregnancy has been associated with cases of fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. Data from observational studies regarding other potential embryofetal risks of NSAID use in women in the first or second trimesters of pregnancy are inconclusive. Animal reproductive studies conducted in rats and rabbits have not demonstrated evidence of developmental abnormalities.
However, animal reproduction studies are not always predictive of human response. Based on animal data, prostaglandins have been shown to have an important role in endometrial vascular permeability, blastocyst implantation, and decidualization. In animal studies, administration of prostaglandin synthesis inhibitors such as meclofenamate, resulted in increased pre- and post-implantation loss.
Prostaglandins also have been shown to have an important role in fetal kidney development. In published animal studies, prostaglandin synthesis inhibitors have been reported to impair kidney development when administered at clinically relevant doses. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Premature Closure of Fetal Ductus Arteriosus Avoid use of NSAIDs in women at about 30 weeks gestation and later in pregnancy, because NSAIDs, including meclofenamate sodium capsules, can cause premature closure of the fetal ductus arteriosus (see WARNINGS: Fetal Toxicity ).
Oligohydramnios/Neonatal Renal Impairment If an NSAID is necessary at about 20 weeks gestation or later in pregnancy, limit the use to the lowest effective dose and shortest duration possible. If meclofenamate sodium capsules treatment extends beyond 48 hours, consider monitoring with ultrasound for oligohydramnios. If oligohydramnios occurs, discontinue meclofenamate sodium capsules and follow up according to clinical practice (see WARNINGS: Fetal Toxicity ).
Data Human Data Premature Closure of Fetal Ductus Arteriosus Published literature reports that the use of NSAIDs at about 30 weeks of gestation and later in pregnancy may cause premature closure of the fetal ductus arteriosus. Oligohydramnios/Neonatal Renal Impairment Published studies and postmarketing reports describe maternal NSAID use at about 20 weeks gestation or later in pregnancy associated with fetal renal dysfunction leading to oligohydramnios, and in some cases, neonatal renal impairment. These adverse outcomes are seen, on average, after days to weeks of treatment, although oligohydramnios has been infrequently reported as soon as 48 hours after NSAID initiation.
In many cases, but not all, the decrease in amniotic fluid was transient and reversible with cessation of the drug. There have been a limited number of case reports of maternal NSAID use and neonatal renal dysfunction without oligohydramnios, some of whi… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients below the age of 14 have not been established.
🧓 Geriatric Use ▾
Geriatric Use As with any NSAIDs, caution should be exercised in treating the elderly (65 years and older).
🆘 Overdosage ▾
OVERDOSAGE The following is based on the little information available concerning overdosage with meclofenamate sodium and related compounds. After a massive overdose, CNS stimulation may be manifested by irrational behavior, marked agitation and generalized seizures. Following this phase, renal toxicity (falling urine output, rising creatinine, abnormal urinary cellular elements) may be noted with possible oliguria or anuria and azotemia.
A 24 year-old male was anuric for approximately one week after ingesting an overdose of 6 to 7 grams of meclofenamate sodium. Spontaneous diuresis and recovery subsequently occurred. Management consists of emptying the stomach by emesis or lavage and instilling an ample dose of activated charcoal into the stomach.
There is some evidence that charcoal will actively absorb meclofenamate sodium, but dialysis or hemoperfusion may be less effective because of plasma protein binding. The seizures should be controlled by an appropriate anticonvulsant regimen. Attention should be directed throughout, by careful monitoring, to the preservation of vital functions and fluid-electrolyte balance.
Dialysis may be required to correct serious azotemia or electrolyte imbalance.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics Meclofenamate sodium is a nonsteroidal agent which has demonstrated anti-inflammatory, analgesic, and antipyretic activity in laboratory animals. The mode of action, like that of other nonsteroidal anti-inflammatory agents, is not known. Therapeutic action does not result from pituitary-adrenal stimulation.
In animal studies, meclofenamate sodium was found to inhibit prostaglandin synthesis and to compete for binding at the prostaglandin receptor site. In vitro, meclofenamate sodium was found to be an inhibitor of human leukocyte 5-lipoxygenase activity. These properties may be responsible for the anti-inflammatory action of meclofenamate sodium.
There is no evidence that meclofenamate sodium alters the course of the underlying disease. In several human isotope studies, meclofenamate sodium, at a dosage of 300 mg/day, produced a fecal blood loss of 1 to 2 mL per day, and 2 to 3 mL per day at 400 mg/day. Aspirin, at a dosage of 3.6 g/day, caused a fecal blood loss of 6 mL per day.
In a multiple-dose, 1-week study in normal human volunteers, meclofenamate sodium had little or no effect on collagen-induced platelet aggregation, platelet count, or bleeding time. In comparison, aspirin suppressed collagen-induced platelet aggregation and increased bleeding time. The concomitant administration of antacids (aluminum and magnesium hydroxides) does not interfere with absorption of meclofenamate sodium.
Pharmacokinetics Meclofenamate sodium is rapidly absorbed in man following single and multiple oral doses with peak plasma concentrations occurring in 0.5 to 2 hours. Based on a comparison to a suspension of meclofenamic acid, meclofenamate sodium is completely bioavailable. The plasma concentrations of meclofenamic acid decline monoexponentially following oral administration.
In a study in ten healthy subjects following a single oral dose the apparent elimination half-life ranged from 0.8 to 5.3 hours. After the administration of meclofenamate sodium for 14 days every 8 hours, the apparent elimination half-life ranged from 0.8 to 2.1 hours with no evidence of accumulation of meclofenamic acid in plasma (see Table). TABLE SUMMARY OF MECLOFENAMATE SODIUM PHARMACOKINETIC PARAMETERS Mean (Range) Parameter Values (n = 10) Meclofenamic Acid 100 mg Administered every 8 hours for 14 days Metabolite I 3-Hydroxymethyl metabolite of meclofenamic acid with 20% activity of meclofenamate sodium in vitro C max mcg/mL Peak plasma concentration 4.8 (1.8 to 7.2) 1 (0.5 to 1.5) t max hr Time to peak plasma concentration 0.9 (0.5 to 1.5) 2.4 (0.5 to 4) C min mcg/mL Trough plasma concentration 0.2 (0.5 to 1.5) 0.4 (0.2 to 1.1) Cl/F mL/ min Oral clearance 206 (126 to 342) --- Vd/F liters Oral distribution volume 23.3 (9.1 to 43.2) --- t 1⁄2 hr Elimination half-life 1.3 (0.8 to 2.1)
15.3Estimated from mean data % of Dose in Urine Unconjugated 0 --- 0.5 (0 to 1.2) Total 2.7 (0 to 4.5) 21.6 (7.5 to 32.6) Meclofenamic acid is extensively metabolized to an active metabolite (Metabolite I; 3-hydroxymethyl metabolite of meclofenamic acid) and at least six other less well characterized minor metabolites. Only this Metabolite I has been shown in vitro to inhibit cyclooxygenase activity with approximately one fifth the activity of meclofenamate sodium. Metabolite I (3-hydroxymethyl metabolite of meclofenamic acid) with a mean half-life of approximately 15 hours did accumulate following multiple dosing.
After the administration of 100 mg meclofenamate sodium for 14 days every 8 hours, Metabolite I reached a peak plasma concentration of only 1 mcg/mL. By contrast, the peak concentration was 4.8 mcg/mL for the parent compound on both days 1 and 14. Therefore, the accumulation of Metabolite I is probably not clinically significant.
Approximately 70% of the administered dose is excreted by the kidneys with 8% to 35% excreted as predominantly conjugated species of meclofenamic acid and Metabolite I (see Table). Other metabolites, whos… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Meclofenamate Sodium Capsules, USP are available containing either 50 mg or 100 mg of meclofenamic acid as the sodium salt. The 50 mg capsules are hard-shell gelatin capsules with a coral opaque cap and a coral opaque body filled with an off-white powder blend. The capsules are axially printed with MYLAN over 2150 in black ink on both the cap and body.
They are available as follows: NDC 0378-2150-01 bottles of 100 capsules The 100 mg capsules are hard-shell gelatin capsules with a coral opaque cap and a white opaque body filled with an off-white powder blend. The capsules are axially printed with MYLAN over 3000 in black ink on both the cap and body. They are available as follows: NDC 0378-3000-01 bottles of 100 capsules Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture.
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
DESCRIPTION Meclofenamate sodium is N-(2,6-dichloro-m-tolyl) anthranilic acid, sodium salt, monohydrate. It is an anti-inflammatory drug for oral administration. Meclofenamate sodium capsules, USP contain 50 mg or 100 mg meclofenamic acid as the sodium salt and the following inactive ingredients: colloidal silicon dioxide, D&C Yellow No.
10, FD&C Blue No. 1, FD&C Red No. 3, gelatin, magnesium stearate, microcrystalline cellulose, pregelatinized starch (corn), sodium lauryl sulfate and titanium dioxide.
In addition, the imprinting ink contains black iron oxide, D&C Yellow No. 10 Aluminum Lake, FD&C Blue No. 1 Aluminum Lake, FD&C Blue No.
2 Aluminum Lake, FD&C Red No. 40 Aluminum Lake, propylene glycol and shellac glaze. The structural formula of meclofenamate sodium is: Molecular Formula: C 14 H 10 Cl 2 NNaO 2 •H 2 O It is a white to creamy white, odorless to almost odorless, crystalline powder with melting point 287° to 291°C, molecular weight 336.15, and it is freely soluble in water.
Each meclofenamate sodium capsule contains 7 mg of sodium. Meclofenamate Sodium Structural Formula
💬 Information for Patients ▾
Information for Patients Patients should be informed of the following information before initiating therapy with an NSAID and periodically during the course of ongoing therapy. Patients should also be encouraged to read the NSAID Medication Guide that accompanies each prescription dispensed. 1.
Cardiovascular Thrombotic Events: Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their healthcare provider immediately (see WARNINGS ). 2. Meclofenamate sodium, like other NSAIDs, can cause GI discomfort and, rarely, serious GI side effects, such as ulcers and bleeding, which may result in hospitalization and even death.
Although serious GI tract ulcerations and bleeding can occur without warning symptoms, patients should be alert for the signs and symptoms of ulcerations and bleeding, and should ask for medical advice when observing any indicative sign or symptoms including epigastric pain, dyspepsia, melena, and hematemesis. Patients should be apprised of the importance of this follow-up (see WARNINGS: Gastrointestinal Effects: Risk of Ulceration, Bleeding, and Perforation ). 3.
Serious Skin Reactions, including DRESS: Advise patients to stop taking meclofenamate sodium capsules immediately if they develop any type of rash or fever and to contact their healthcare provider as soon as possible (see WARNINGS ). 4. Heart Failure and Edema: Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur (see WARNINGS ).
5. Patients should be informed of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, jaundice, right upper quadrant tenderness, and “flu-like” symptoms). If these occur, patients should be instructed to stop therapy and seek immediate medical therapy.
6. Patients should be informed of the signs of an anaphylactoid reaction (e.g., difficulty breathing, swelling of the face or throat). If these occur, patients should be instructed to seek immediate emergency help (see WARNINGS ).
7. Fetal Toxicity: Inform pregnant women to avoid use of meclofenamate sodium capsules and other NSAIDs starting at 30 weeks gestation because of the risk of the premature closing of the fetal ductus arteriosus. If treatment with meclofenamate sodium capsules is needed for a pregnant woman between about 20 to 30 weeks gestation, advise her that she may need to be monitored for oligohydramnios, if treatment continues for longer than 48 hours (see WARNINGS: Fetal Toxicity , PRECAUTIONS: Pregnancy ).
💬 Medication Guide ▾
Medication Guide for Nonsteroidal Anti-inflammatory Drugs (NSAIDs) What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)? NSAIDs can cause serious side effects, including: • Increased risk of a heart attack or stroke that can lead to death . This risk may happen early in treatment and may increase: o with increasing doses of NSAIDs o with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a “coronary artery bypass graft (CABG)." Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. • Increased risk of bleeding, ulcers, and tears (perforation) of the esophagus (tube leading from the mouth to the stomach), stomach and intestines: o anytime during use o without warning symptoms o that may cause death The risk of getting an ulcer or bleeding increases with: o past history of stomach ulcers, or stomach or intestinal bleeding with use of NSAIDs o taking medicines called “corticosteroids”, “anticoagulants”, “SSRIs”, or “SNRIs” o increasing doses of NSAIDs o longer use of NSAIDs o smoking o drinking alcohol o older age o poor health o advanced liver disease o bleeding problems NSAIDs should only be used: o exactly as prescribed o at the lowest dose possible for your treatment o for the shortest time needed What are NSAIDs?
NSAIDs are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as different types of arthritis, menstrual cramps, and other types of short-term pain. Who should not take NSAIDs? Do not take NSAIDs: • if you have had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAIDs. • right before or after heart bypass surgery.
Before taking NSAIDs, tell your healthcare provider about all of your medical conditions, including if you: • have liver or kidney problems • have high blood pressure • have asthma • are pregnant or plan to become pregnant. Taking NSAIDs at about 20 weeks of pregnancy or later may harm your unborn baby. If you need to take NSAIDs for more than 2 days when you are between 20 and 30 weeks of pregnancy, your healthcare provider may need to monitor the amount of fluid in your womb around your baby.
You should not take NSAIDs after about 30 weeks of pregnancy. • are breastfeeding or plan to breast feed. Tell your healthcare provider about all of the medicines you take, including prescription or over-the-counter medicines, vitamins or herbal supplements. NSAIDs and some other medicines can interact with each other and cause serious side effects.
Do not start taking any new medicine without talking to your healthcare provider first. What are the possible side effects of NSAIDs? NSAIDs can cause serious side effects, including: See “What is the most important information I should know about medicines called Nonsteroidal Anti-inflammatory Drugs (NSAIDs)?” • new or worse high blood pressure • heart failure • liver problems including liver failure • kidney problems including kidney failure • low red blood cells (anemia) • life-threatening skin reactions • life threatening allergic reactions • Other side effects of NSAIDs include: stomach pain, constipation, diarrhea, gas, heartburn, nausea, vomiting, and dizziness.
Get emergency help right away if you get any of the following symptoms: • shortness of breath or trouble breathing • chest pain • weakness in one part or side of your body • slurred speech • swelling of the face or throat Stop taking your NSAID and call your healthcare provider right away if you get any of the following symptoms: • nausea • more tired or weaker than usual • diarrhea • itching • your skin or eyes look yellow • indigestion or stomach pain • flu-like symptoms • vomit blood • there is blood in your bowel movement or it is black and sticky like tar • unusual weight gain • skin ra… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS General Meclofenamate sodium cannot be expected to substitute for corticosteroids or to treat corticosteroid insufficiency. Abrupt discontinuation of corticosteroids may lead to disease exacerbation. Patients on prolonged corticosteroid therapy should have their therapy tapered slowly if a decision is made to discontinue corticosteroids.
The pharmacological activity of meclofenamate sodium in reducing fever and inflammation may diminish the utility of these diagnostic signs in detecting complications of presumed noninfectious, painful conditions. Hepatic Effects Borderline elevations of one or more liver tests may occur in up to 15% of patients taking NSAIDs including meclofenamate sodium. These laboratory abnormalities may progress, may remain unchanged, or may be transient with continuing therapy.
Notable elevations of ALT or AST (approximately 3 or more times the upper limit of normal) have been reported in approximately 1% of patients in clinical trials with NSAIDs. In addition, rare cases of severe hepatic reactions, including jaundice and fatal fulminant hepatitis, liver necrosis and hepatic failure, some of them with fatal outcomes have been reported. A patient with symptoms and/or signs suggesting liver dysfunction, or in whom an abnormal liver test has occurred, should be evaluated for evidence of the development of a more severe hepatic reaction while on therapy with meclofenamate sodium.
If clinical signs and symptoms consistent with liver disease develop, or if systemic manifestations occur (e.g., eosinophilia, rash, etc.), meclofenamate sodium should be discontinued. Hematological Effects Anemia is sometimes seen in patients receiving NSAIDs, including meclofenamate sodium. This may be due to fluid retention, occult or gross GI blood loss, or an incompletely described effect upon erythropoiesis.
Patients on long-term treatment with NSAIDs, including meclofenamate sodium, should have their hemoglobin or hematocrit checked if they exhibit any signs or symptoms of anemia. NSAIDs inhibit platelet aggregation and have been shown to prolong bleeding time in some patients. Unlike aspirin, their effect on platelet function is quantitatively less, of shorter duration, and reversible.
Patients receiving meclofenamate sodium who may be adversely affected by alterations in platelet function, such as those with coagulation disorders or patients receiving anticoagulants, should be carefully monitored. Preexisting Asthma Patients with asthma may have aspirin-sensitive asthma. The use of aspirin in patients with aspirin-sensitive asthma has been associated with severe bronchospasm which can be fatal.
Since cross reactivity, including bronchospasm, between aspirin and other nonsteroidal anti-inflammatory drugs has been reported in such aspirin-sensitive patients, meclofenamate sodium should not be administered to patients with this form of aspirin sensitivity and should be used with caution in patients with preexisting asthma. Information for Patients Patients should be informed of the following information before initiating therapy with an NSAID and periodically during the course of ongoing therapy. Patients should also be encouraged to read the NSAID Medication Guide that accompanies each prescription dispensed.
1. Cardiovascular Thrombotic Events: Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their healthcare provider immediately (see WARNINGS ). 2.
Meclofenamate sodium, like other NSAIDs, can cause GI discomfort and, rarely, serious GI side effects, such as ulcers and bleeding, which may result in hospitalization and even death. Although serious GI tract ulcerations and bleeding can occur without warning symptoms, patients should be alert for the signs and symptoms of ulcerations and bleeding, and should ask for medical advice when observing any indicative sign or sy… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human-milk and because of the potential for serious adverse reactions in nursing infants from meclofenamate sodium, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
🧬 Pharmacokinetics ▾
Pharmacokinetics Meclofenamate sodium is rapidly absorbed in man following single and multiple oral doses with peak plasma concentrations occurring in 0.5 to 2 hours. Based on a comparison to a suspension of meclofenamic acid, meclofenamate sodium is completely bioavailable. The plasma concentrations of meclofenamic acid decline monoexponentially following oral administration.
In a study in ten healthy subjects following a single oral dose the apparent elimination half-life ranged from 0.8 to 5.3 hours. After the administration of meclofenamate sodium for 14 days every 8 hours, the apparent elimination half-life ranged from 0.8 to 2.1 hours with no evidence of accumulation of meclofenamic acid in plasma (see Table). TABLE SUMMARY OF MECLOFENAMATE SODIUM PHARMACOKINETIC PARAMETERS Mean (Range) Parameter Values (n = 10) Meclofenamic Acid 100 mg Administered every 8 hours for 14 days Metabolite I 3-Hydroxymethyl metabolite of meclofenamic acid with 20% activity of meclofenamate sodium in vitro C max mcg/mL Peak plasma concentration 4.8 (1.8 to 7.2) 1 (0.5 to 1.5) t max hr Time to peak plasma concentration 0.9 (0.5 to 1.5) 2.4 (0.5 to 4) C min mcg/mL Trough plasma concentration 0.2 (0.5 to 1.5) 0.4 (0.2 to 1.1) Cl/F mL/ min Oral clearance 206 (126 to 342) --- Vd/F liters Oral distribution volume 23.3 (9.1 to 43.2) --- t 1⁄2 hr Elimination half-life 1.3 (0.8 to 2.1)
15.3Estimated from mean data % of Dose in Urine Unconjugated 0 --- 0.5 (0 to 1.2) Total 2.7 (0 to 4.5) 21.6 (7.5 to 32.6) Meclofenamic acid is extensively metabolized to an active metabolite (Metabolite I; 3-hydroxymethyl metabolite of meclofenamic acid) and at least six other less well characterized minor metabolites. Only this Metabolite I has been shown in vitro to inhibit cyclooxygenase activity with approximately one fifth the activity of meclofenamate sodium. Metabolite I (3-hydroxymethyl metabolite of meclofenamic acid) with a mean half-life of approximately 15 hours did accumulate following multiple dosing.
After the administration of 100 mg meclofenamate sodium for 14 days every 8 hours, Metabolite I reached a peak plasma concentration of only 1 mcg/mL. By contrast, the peak concentration was 4.8 mcg/mL for the parent compound on both days 1 and 14. Therefore, the accumulation of Metabolite I is probably not clinically significant.
Approximately 70% of the administered dose is excreted by the kidneys with 8% to 35% excreted as predominantly conjugated species of meclofenamic acid and Metabolite I (see Table). Other metabolites, whose excretion rates are unknown, account for the remaining 35% to 62% of the dose excreted in the urine. The remainder of the administered dose (approximately 30%) is eliminated in the feces (apparently through biliary excretion).
There is insufficient experience to know if meclofenamate sodium or its metabolites accumulate in patients with compromised renal or hepatic function. Therefore, meclofenamate sodium should be used with caution in these patients (see PRECAUTIONS ). Trace amounts of meclofenamate sodium are excreted in human breast milk.
Meclofenamic acid is greater than 99% bound to plasma proteins over a wide drug concentration range. Unlike most NSAIDs, which when administered with food have a decrease in rate but not in extent of absorption, meclofenamic acid is decreased in both. It has been reported that following the administration of meclofenamate sodium capsules one-half hour after a meal, the average extent of bioavailability decreased by 26%, the average peak concentration (C max ) decreased 4-fold and the time to C max was delayed by 3 hours.
🧬 Pharmacodynamics ▾
Pharmacodynamics Meclofenamate sodium is a nonsteroidal agent which has demonstrated anti-inflammatory, analgesic, and antipyretic activity in laboratory animals. The mode of action, like that of other nonsteroidal anti-inflammatory agents, is not known. Therapeutic action does not result from pituitary-adrenal stimulation.
In animal studies, meclofenamate sodium was found to inhibit prostaglandin synthesis and to compete for binding at the prostaglandin receptor site. In vitro, meclofenamate sodium was found to be an inhibitor of human leukocyte 5-lipoxygenase activity. These properties may be responsible for the anti-inflammatory action of meclofenamate sodium.
There is no evidence that meclofenamate sodium alters the course of the underlying disease. In several human isotope studies, meclofenamate sodium, at a dosage of 300 mg/day, produced a fecal blood loss of 1 to 2 mL per day, and 2 to 3 mL per day at 400 mg/day. Aspirin, at a dosage of 3.6 g/day, caused a fecal blood loss of 6 mL per day.
In a multiple-dose, 1-week study in normal human volunteers, meclofenamate sodium had little or no effect on collagen-induced platelet aggregation, platelet count, or bleeding time. In comparison, aspirin suppressed collagen-induced platelet aggregation and increased bleeding time. The concomitant administration of antacids (aluminum and magnesium hydroxides) does not interfere with absorption of meclofenamate sodium.
🔬 Clinical Studies ▾
Clinical Studies Controlled clinical trials comparing meclofenamate sodium with aspirin demonstrated comparable efficacy in rheumatoid arthritis. The meclofenamate sodium treated patients had fewer reactions involving the special senses, specifically tinnitus, but more gastrointestinal reactions, specifically diarrhea. The incidence of patients who discontinued therapy due to adverse reactions was similar for both the meclofenamate sodium and aspirin-treated groups.
The improvement with meclofenamate sodium reported by patients and the reduction of the disease activity as evaluated by both physicians and patients with rheumatoid arthritis are associated with a significant reduction in number of tender joints, severity of tenderness, and duration of morning stiffness. The improvement reported by patients and as evaluated by physicians in patients treated with meclofenamate sodium for osteoarthritis is associated with a significant reduction in night pain, pain on walking, degree of starting pain, and pain on passive motion.
The function of knee joints also improved significantly. Meclofenamate sodium has been used in combination with gold salts or corticosteroids in patients with rheumatoid arthritis. Studies have demonstrated that meclofenamate sodium contributes to the improvement of patients’ conditions while maintained on gold salts or corticosteroids.
Data are inadequate to demonstrate that meclofenamate sodium in combination with salicylates produces greater improvement than that achieved with meclofenamate sodium alone. In controlled clinical trials of patients with mild to moderate pain, meclofenamate sodium 50 mg provided significant pain relief. In these studies of episiotomy and dental pain, meclofenamate sodium 100 mg demonstrated additional benefit in some patients.
The onset of analgesic effect was generally within one hour and the duration of action was 4 to 6 hours. In controlled clinical trials of patients with dysmenorrhea, meclofenamate sodium 100 mg t.i.d. provided significant reduction in the symptoms associated with dysmenorrhea. In randomized double-blind crossover trials of meclofenamate sodium 100 mg t.i.d. versus placebo in women with heavy menstrual blood loss (MBL), meclofenamate sodium treatment was usually associated with a reduction in menstrual flow.
The graph below is a scatter plot of menstrual flow from the average of two menstrual periods on meclofenamate sodium treatments (vertical axis) versus two menstrual periods on placebo (horizontal axis) for 55 women. Of note, although the amount of reduction in MBL was variable, some degree of reduction occurred in 90% of women in this study. Scattergram of Menstrual Flow Average of Two Periods on Each Treatment of 55 Women from Three Clinical Trials The points on the graph represent the mean MBL for each subject when treated for two periods with placebo and two periods with meclofenamate sodium.
To ease in interpretation, the following examples may be helpful. Point A represents a woman who had MBL of 459 mL while on placebo, and 405 mL on meclofenamate sodium. Point B represents a woman who had MBL of 472 mL while on placebo, and 64 mL when treated with meclofenamate sodium.
In association with this reduction in menstrual blood loss, the duration of menses was decreased by one day; tampon/pad usage was decreased by an average of two per day on the 2 days of heaviest flow; and symptoms of dysmenorrhea were significantly reduced. Scattergram of Menstrual Flow Average of Two Periods on Each Treatment of 55 Women from Three Clinical Trials
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 50 mg NDC 0378-2150-01 Meclofenamate Sodium Capsules, USP 50 mg PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 100 Capsules Each capsule contains: Meclofenamate sodium, USP monohydrate equivalent to 50 mg of meclofenamate acid. Usual Dosage: 200 mg to 400 mg per day; administered in three or four equal doses.
See package outsert for full prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture.
Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A. Made in India Viatris.com RMX2150A2 Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed.
Code No.: MH/DRUGS/25/NKD/89 Meclofenamate Sodium Capsules 50 mg Bottle Label
PRINCIPAL DISPLAY PANEL – 100 mg NDC 0378-3000-01 Meclofenamate Sodium Capsules, USP 100 mg PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 100 Capsules Each capsule contains: Meclofenamate sodium, USP monohydrate equivalent to 100 mg of meclofenamate acid. Usual Dosage: 200 mg to 400 mg per day; administered in three or four equal doses.
See package outsert for full prescribing information. Keep this and all medication out of the reach of children. Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture.
Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A. Made in India Viatris.com RMX3000A2 Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed.
Code No.: MH/DRUGS/25/NKD/89 Meclofenamate Sodium Capsules 100 mg Bottle Label
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |