
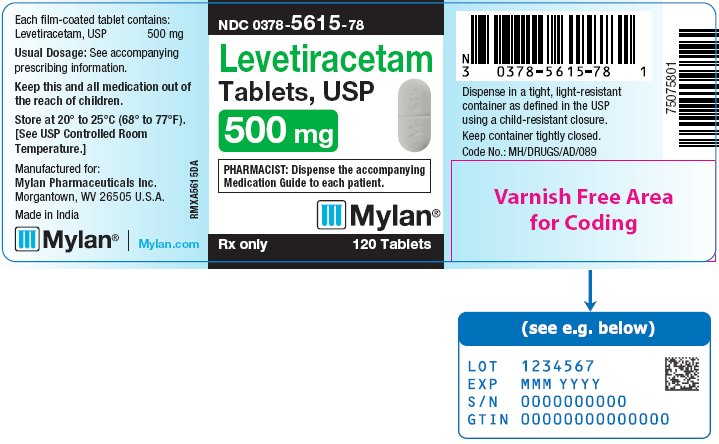
Levetiracetam 500 mg Tablet, Film Coated, 120-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Other antiepileptics class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Levetiracetam is an anti-seizure medicine. Depending on the product and your age, it can be used to treat partial-onset seizures (seizures starting in one part of the brain), myocl...
- What is levetiracetam actually used for?
- It can, especially when you first start taking it. Drowsiness, fatigue, and dizziness are among the most common side effects and tend to be most noticeable in the first few weeks....
- Will levetiracetam make me feel tired or foggy?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Levetiracetam — tap one for details:
Levetiracetam may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 0VUT3PMY82
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. In medicines, it forms protective coatings on tablets or capsules, controls how fast the drug releases, and thickens liquid formulations.
-
UNII 1IVH67816N
Hypromellose 2910 is a plant-derived cellulose compound used as a thickener and film-former in medicines. It helps control how quickly the medication dissolves and creates protective coatings on tablets or capsules.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII VH2XOU12IE
Polydextrose is a synthetic polymer made from dextrose (sugar) that acts as a bulking agent and filler in medicines. It helps give tablets and capsules proper volume and texture while often adding slight sweetness.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.074 | $8.87 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2394 | $28.73 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1374 | $16.49 / 120 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Levetiracetam 500 mgthis 00378-5615-78 | Mylan | 120 tablets | $0.074 | — | Availability likely | — |
| Levetiracetam 500 mg 00904-7124-61 | Major | 1 tablet | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 16714-0035-01 | NorthStar | 120 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 27808-0264-01 | Cranbury | 120 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 31722-0537-05 | Camber | 500 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 43547-0222-11 | Solco | 1000 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 50228-0471-05 | ScieGen | 500 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 51079-0821-20 | Mylan | 1 tablet | $0.074 | — | Availability likely | — |
| Levetiracetam 500 mg 60687-0657-01 | American | 1 tablet | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 65862-0246-05 | Aurobindo | 500 tablets | $0.074 | — | Availability likely | — |
| Levetiracetam 500 mg 67877-0769-05 | Ascend | 500 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 68001-0403-03 | BluePoint | 500 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 68180-0113-02 | Lupin | 500 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 72205-0095-92 | Novadoz | 120 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 82009-0122-05 | Quallent | 500 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 69102-0105-01 | OWP | 120 tablets | $0.074 | AB | Availability likely | — |
| Levetiracetam 500 mg 13668-0015-05 | Torrent | 500 tablets | $0.095 | AB | FDA listed | +28% |
| Keppra 500 mg 50474-0595-40 | UCB, | 120 tablets | $9.916 | AB | Availability likely | +13316% |
| Spritam 500 mg 43485-0102-60 | Aprecia | 1 tablet | $10.241 | — | Availability likely | +13756% |
| Levetiracetam 500 mg 00615-8499-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 43063-0499-60 | PD-Rx | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 43063-0617-60 | PD-Rx | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 43547-0881-15 | Solco | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 48433-0052-20 | Safecor | 1 tablet | — | — | FDA listed | — |
| Levetiracetam 500 mg 50090-1333-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 50090-7521-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 50090-7717-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 50090-7768-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 50090-7820-00 | A-S | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 50405-0301-01 | SOHM, | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 51655-0325-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 55111-0182-01 | Dr. | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 55154-3367-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Levetiracetam 500 mg 55154-5699-00 | Cardinal | 1 tablet | — | — | FDA listed | — |
| Levetiracetam 500 mg 63187-0360-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 63629-4137-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 64980-0605-01 | Rising | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 65162-0529-16 | Amneal | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 67046-0420-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 67046-2094-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 68788-8254-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 68788-8843-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 70010-0522-03 | Granules | 30 tablets | — | — | FDA listed | — |
| Levetiracetam 500 mg 70518-1108-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 70518-1796-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Levetiracetam 500 mg 70518-4301-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 71335-0694-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 71335-2282-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 71335-9757-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 72189-0229-60 | DIRECT | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 72789-0152-60 | PD-Rx | 60 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 72865-0188-05 | XLCare | 500 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 76282-0247-12 | Exelan | 120 tablets | — | — | FDA listed | — |
| Levetiracetam 500 mg 76494-0529-12 | Prinston | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 80425-0565-01 | Advanced | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 80425-0566-01 | Advanced | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 87063-0191-12 | ASCLEMED | 120 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 87234-0035-01 | Injecta | 1 tablet | — | AB | FDA listed | — |
| Levetiracetam 500 mg 87441-0046-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Levetiracetam 500 mg 66993-0101-60 | Prasco | 1 tablet | — | — | FDA listed | — |
| Levetiracetam 500 mg 70518-1772-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00378-5615-05 | 500 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (0378-5615-05) | $0.0739 / ea | $36.96 | 2008-11-04 | Active |
| 00378-5615-78 You're viewing this | 120 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (0378-5615-78) | $0.0739 / ea | $8.87 | 2008-11-04 | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.0739 NADAC).
This pack accounts for about 38% of this product's recent Medicaid fills; most go to the 500 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 00378-5615-78?
What is the difference between NDC 00378-5615-78 and NDC 00378-5615-05?
What NDC number is used to bill for this package of Levetiracetam 500 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Levetiracetam is indicated for the treatment of partial-onset seizures in patients 1 month of age and older ( 1.1 ) Levetiracetam is indicated for adjunctive therapy for the treatment of: • Myoclonic seizures in patients 12 years of age and older with juvenile myoclonic epilepsy ( 1.2 ) • Primary generalized tonic-clonic seizures in patients 6 years of age and older with idiopathic generalized epilepsy ( 1.3 )
1.1Partial-Onset Seizures Levetiracetam is indicated for the treatment of partial-onset seizures in patients 1 month of age and older.
1.2Myoclonic Seizures in Patients with Juvenile Myoclonic Epilepsy Levetiracetam is indicated as adjunctive therapy for the treatment of myoclonic seizures in patients 12 years of age and older with juvenile myoclonic epilepsy.
1.3Primary Generalized Tonic-Clonic Seizures Levetiracetam is indicated as adjunctive therapy for the treatment of primary generalized tonic-clonic seizures in patients 6 years of age and older with idiopathic generalized epilepsy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Use the oral solution for pediatric patients with body weight ≤ 20 kg ( 2.1 ) • For pediatric patients, use weight-based dosing for the oral solution with a calibrated measuring device (not a household teaspoon or tablespoon) ( 2.1 ) Partial-Onset Seizures (monotherapy or adjunctive therapy) • 1 Month to < 6 Months: 7 mg/kg twice daily; increase by 7 mg/kg twice daily every 2 weeks to recommended dose of 21 mg/kg twice daily ( 2.2 ) • 6 Months to < 4 Years: 10 mg/kg twice daily; increase by 10 mg/kg twice daily every 2 weeks to recommended dose of 25 mg/kg twice daily ( 2.2 ) • 4 Years to < 16 Years: 10 mg/kg twice daily; increase by 10 mg/kg twice daily every 2 weeks to recommended dose of 30 mg/kg twice daily ( 2.2 ) • Adults 16 Years and Older: 500 mg twice daily; increase by 500 mg twice daily every 2 weeks to a recommended dose of 1500 mg twice daily ( 2.2 ) Myoclonic Seizures in Adults and Pediatric Patients 12 Years and Older • 500 mg twice daily; increase by 500 mg twice daily every 2 weeks to recommended dose of 1500 mg twice daily ( 2.3 ) Primary Generalized Tonic-Clonic Seizures • 6 Years to < 16 Years: 10 mg/kg twice daily, increase in increments of 10 mg/kg twice daily every 2 weeks to recommended dose of 30 mg/kg twice daily ( 2.4 ) • Adults 16 Years and Older: 500 mg twice daily, increase by 500 mg twice daily every 2 weeks to recommended dose of 1500 mg twice daily ( 2.4 ) Adult Patients with Impaired Renal Function • Dose adjustment is recommended, based on the patient’s estimated creatinine clearance ( 2.5 , 8.6 )
2.1Important Administration Instructions Levetiracetam is given orally with or without food. The levetiracetam dosing regimen depends on the indication, age group, dosage form (tablets or oral solution), and renal function. Prescribe the oral solution for pediatric patients with body weight ≤ 20 kg.
Prescribe the oral solution or tablets for pediatric patients with body weight above 20 kg. When using the oral solution in pediatric patients, dosing is weight-based (mg per kg) using a calibrated measuring device (not a household teaspoon or tablespoon). Levetiracetam tablets should be swallowed whole.
Levetiracetam tablets should not be chewed or crushed.
2.2Dosing for Partial-Onset Seizures The recommended dosing for monotherapy and adjunctive therapy is the same; as outlined below. Adults 16 Years of Age and Older Initiate treatment with a daily dose of 1000 mg/day, given as twice-daily dosing (500 mg twice daily). Additional dosing increments may be given (1000 mg/day additional every 2 weeks) to a maximum recommended daily dose of 3000 mg.
There is no evidence that doses greater than 3000 mg/day confer additional benefit. Pediatric Patients 1 Month to < 6 Months Initiate treatment with a daily dose of 14 mg/kg in 2 divided doses (7 mg/kg twice daily). Increase the daily dose every 2 weeks by increments of 14 mg/kg to the recommended daily dose of 42 mg/kg (21 mg/kg twice daily).
In the clinical trial, the mean daily dose was 35 mg/kg in this age group. 6 Months to < 4 Years Initiate treatment with a daily dose of 20 mg/kg in 2 divided doses (10 mg/kg twice daily). Increase the daily dose in 2 weeks by an increment of 20 mg/kg to the recommended daily dose of 50 mg/kg (25 mg/kg twice daily).
If a patient cannot tolerate a daily dose of 50 mg/kg, the daily dose may be reduced. In the clinical trial, the mean daily dose was 47 mg/kg in this age group. 4 Years to < 16 Years Initiate treatment with a daily dose of 20 mg/kg in 2 divided doses (10 mg/kg twice daily).
Increase the daily dose every 2 weeks by increments of 20 mg/kg to the recommended daily dose of 60 mg/kg (30 mg/kg twice daily). If a patient cannot tolerate a daily dose of 60 mg/kg, the daily dose may be reduced. In the clinical trial, the mean daily dose was 44 mg/kg.
The maximum daily dose was 3000 mg/day. For levetiracetam tablets dosing in pediatric patients weighing 20 to 40 kg, initiate treatment with…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Levetiracetam Tablets, USP are available containing 500 mg, 750 mg or 1000 mg of levetiracetam, USP. • The 500 mg tablets are white, film-coated, modified capsule-shaped, scored tablets debossed with M to the left of the score and 615 to the right of the score on one side of the tablet and blank on the other side. • The 750 mg tablets are white, film-coated, modified capsule-shaped, scored tablets debossed with M to the left of the score and 617 to the right of the score on one side of the tablet and blank on the other side. • The 1000 mg tablets are white, film-coated, modified capsule-shaped, scored tablets debossed with M to the left of the score and 619 to the right of the score on one side of the tablet and blank on the other side. • 500 mg, 750 mg, and 1000 mg film-coated, scored tablets ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Levetiracetam is contraindicated in patients with a hypersensitivity to levetiracetam. Reactions have included anaphylaxis and angioedema [see Warnings and Precautions (5.4) ] . Known hypersensitivity to levetiracetam; angioedema and anaphylaxis have occurred ( 4 , 5.4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Behavioral abnormalities including psychotic symptoms, suicidal ideation, irritability, and aggressive behavior have been observed; monitor patients for psychiatric signs and symptoms ( 5.1 ) • Suicidal Behavior and Ideation: Monitor patients for new or worsening depression, suicidal thoughts/behavior, and/or unusual changes in mood or behavior ( 5.2 ) • Monitor for somnolence and fatigue and advise patients not to drive or operate machinery until they have gained sufficient experience on levetiracetam ( 5.3 ) • Serious Dermatological Reactions: Discontinue levetiracetam at the first sign of rash unless clearly not drug related ( 5.5 ) • Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity: Discontinue if no alternative etiology ( 5.6 ) • Coordination Difficulties: Monitor for ataxia, abnormal gait, and incoordination.
Advise patients to not drive or operate machinery until they have gained experience on levetiracetam ( 5.7 ) • Withdrawal Seizures: Levetiracetam must be gradually withdrawn ( 5.8 )
5.1Behavioral Abnormalities and Psychotic Symptoms Levetiracetam may cause behavioral abnormalities and psychotic symptoms. Patients treated with levetiracetam should be monitored for psychiatric signs and symptoms. Behavioral abnormalities In clinical studies, 13% of adult levetiracetam-treated patients and 38% of pediatric levetiracetam-treated patients (4 to 16 years of age) compared to 6% and 19% of adult and pediatric placebo-treated patients, experienced non-psychotic behavioral symptoms (reported as aggression, agitation, anger, anxiety, apathy, depersonalization, depression, emotional lability, hostility, hyperkinesias, irritability, nervousness, neurosis, and personality disorder).
A randomized double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioral effects of levetiracetam as adjunctive therapy in pediatric patients (4 to 16 years of age). The results from an exploratory analysis indicated a worsening in levetiracetam-treated patients on aggressive behavior (one of eight behavior dimensions) as measured in a standardized and systematic way using a validated instrument, the Achenbach Child Behavior Checklist (CBCL/6-18). In clinical studies in pediatric patients 1 month to < 4 years of age, irritability was reported in 12% of the levetiracetam-treated patients compared to 0% of placebo-treated patients.
In clinical studies, 1.7% of adult levetiracetam-treated patients discontinued treatment due to behavioral adverse reactions, compared to 0.2% of placebo-treated patients. The treatment dose was reduced in 0.8% of adult levetiracetam-treated patients and in 0.5% of placebo-treated patients. Overall, 11% of levetiracetam-treated pediatric patients experienced behavioral symptoms associated with discontinuation or dose reduction, compared to 6% of placebo-treated patients.
Psychotic symptoms In clinical studies, 1% of levetiracetam-treated adult patients, 2% of levetiracetam-treated pediatric patients 4 to 16 years of age, and 17% of levetiracetam-treated pediatric patients 1 month to < 4 years of age experienced psychotic symptoms, compared to 0.2%, 2%, and 5% in the corresponding age groups treated with placebo. In a controlled study that assessed the neurocognitive and behavioral effects of levetiracetam in pediatric patients 4 to 16 years of age, 1.6% of levetiracetam-treated patients experienced paranoia, compared to 0% of placebo-treated patients.
In the same study, 3.1% of levetiracetam-treated patients experienced confusional state, compared to 0% of placebo-treated patients [see Use in Specific Populations (8.4) ] . In clinical studies, two (0.3%) levetiracetam-treated adult patients were hospitalized and their treatment was discontinued due to psychosis. Both events, reported as psychosis, developed within the first week of treatment and resolved within 1 to 2 weeks following treatment discontinuation.
There was…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more details in other sections of labeling: • Behavior Abnormalities and Psychotic Symptoms [see Warnings and Precautions (5.1) ] • Suicidal Behavior and Ideation [see Warnings and Precautions (5.2) ] • Somnolence and Fatigue [see Warnings and Precautions (5.3) ] • Anaphylaxis and Angioedema [see Warnings and Precautions (5.4) ] • Serious Dermatological Reactions [see Warnings and Precautions (5.5) ] • Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions (5.6) ] • Coordination Difficulties [see Warnings and Precautions (5.7) ] • Hematologic Abnormalities [see Warnings and Precautions (5.9) ] • Increase in Blood Pressure [see Warnings and Precautions (5.10) ] Most common adverse reactions (incidence ≥ 5% more than placebo) include: • Adult patients: somnolence, asthenia, infection and dizziness ( 6.1 ) • Pediatric patients: fatigue, aggression, nasal congestion, decreased appetite, and irritability ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Mylan at 1-877-446-3679 (1-877-4-INFO-RX) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Partial-Onset Seizures Adults In controlled clinical studies in adults with partial-onset seizures [see Clinical Studies (14.1) ] , the most common adverse reactions in patients receiving levetiracetam in combination with other AEDs, for events with rates greater than placebo, were somnolence, asthenia, infection, and dizziness.
Of the most common adverse reactions in adults experiencing partial-onset seizures, asthenia, somnolence, and dizziness occurred predominantly during the first 4 weeks of treatment with levetiracetam. Table 3 lists adverse reactions that occurred in at least 1% of adult epilepsy patients receiving levetiracetam in placebo-controlled studies and were numerically more common than in patients treated with placebo. In these studies, either levetiracetam or placebo was added to concurrent AED therapy.
Table 3: Adverse Reactions in Pooled Placebo-Controlled, Adjunctive Studies in Adults Experiencing Partial-Onset Seizures Levetiracetam (N = 769) % Placebo (N = 439) % Asthenia 15 9 Somnolence 15 8 Headache 14 13 Infection 13 8 Dizziness 9 4 Pain 7 6 Pharyngitis 6 4 Depression 4 2 Nervousness 4 2 Rhinitis 4 3 Anorexia 3 2 Ataxia 3 1 Vertigo 3 1 Amnesia 2 1 Anxiety 2 1 Cough Increased 2 1 Diplopia 2 1 Emotional Lability 2 0 Hostility 2 1 Paresthesia 2 1 Sinusitis 2 1 In controlled adult clinical studies, 15% of patients receiving levetiracetam and 12% receiving placebo either discontinued or had a dose reduction as a result of an adverse reaction.
Table 4 lists the most common (> 1%) adverse reactions that resulted in discontinuation or dose reduction and that occurred more frequently in levetiracetam-treated patients than in placebo-treated patients. Table 4: Adverse Reactions that Resulted in Discontinuation or Dose Reduction in Placebo-Controlled Studies in Adult Patients Experiencing Partial-Onset Seizures Adverse Reaction Levetiracetam (N = 769) % Placebo (N = 439) % Somnolence 4 2 Dizziness 1 0 Pediatric Patients 4 Years to < 16 Years The adverse reaction data presented below was obtained from a pooled analysis of two controlled pediatric clinical studies in pediatric patients 4 to 16 years of age with partial-onset seizures.
The most common adverse reactions in pediatric patients receiving levetiracetam in combination with other AEDs, for events with rates greater than placebo, were fatigue, aggression, nasal congestion, decreased appetite, and irritability. Table 5 lists adverse reactions from the pooled pediatric controlled studies (4 to 16 y…
🔄 Drug Interactions ▾
Drug Interactions In vitro data on metabolic interactions indicate that levetiracetam is unlikely to produce, or be subject to, pharmacokinetic interactions. Levetiracetam and its major metabolite, at concentrations well above C max levels achieved within the therapeutic dose range, are neither inhibitors of, nor high affinity substrates for, human liver cytochrome P450 isoforms, epoxide hydrolase or UDP-glucuronidation enzymes. In addition, levetiracetam does not affect the in vitro glucuronidation of valproic acid.
Potential pharmacokinetic interactions of or with levetiracetam were assessed in clinical pharmacokinetic studies (phenytoin, valproate, warfarin, digoxin, oral contraceptive, probenecid) and through pharmacokinetic screening in the placebo-controlled clinical studies in epilepsy patients. Phenytoin Levetiracetam (3000 mg daily) had no effect on the pharmacokinetic disposition of phenytoin in patients with refractory epilepsy. Pharmacokinetics of levetiracetam were also not affected by phenytoin.
Valproate Levetiracetam (1500 mg twice daily) did not alter the pharmacokinetics of valproate in healthy volunteers. Valproate 500 mg twice daily did not modify the rate or extent of levetiracetam absorption or its plasma clearance or urinary excretion. There also was no effect on exposure to and the excretion of the primary metabolite, ucb L057.
Other Antiepileptic Drugs Potential drug interactions between levetiracetam and other AEDs (carbamazepine, gabapentin, lamotrigine, phenobarbital, phenytoin, primidone and valproate) were also assessed by evaluating the serum concentrations of levetiracetam and these AEDs during placebo-controlled clinical studies. These data indicate that levetiracetam does not influence the plasma concentration of other AEDs and that these AEDs do not influence the pharmacokinetics of levetiracetam. Effect of AEDs in Pediatric Patients There was about a 22% increase of apparent total body clearance of levetiracetam when it was co-administered with enzyme-inducing AEDs.
Dose adjustment is not recommended. Levetiracetam had no effect on plasma concentrations of carbamazepine, valproate, topiramate, or lamotrigine. Oral Contraceptives Levetiracetam (500 mg twice daily) did not influence the pharmacokinetics of an oral contraceptive containing 0.03 mg ethinyl estradiol and 0.15 mg levonorgestrel, or of the luteinizing hormone and progesterone levels, indicating that impairment of contraceptive efficacy is unlikely.
Coadministration of this oral contraceptive did not influence the pharmacokinetics of levetiracetam. Digoxin Levetiracetam (1000 mg twice daily) did not influence the pharmacokinetics and pharmacodynamics (ECG) of digoxin given as a 0.25 mg dose every day. Coadministration of digoxin did not influence the pharmacokinetics of levetiracetam.
Warfarin Levetiracetam (1000 mg twice daily) did not influence the pharmacokinetics of R and S warfarin. Prothrombin time was not affected by levetiracetam. Coadministration of warfarin did not affect the pharmacokinetics of levetiracetam.
Probenecid Probenecid, a renal tubular secretion blocking agent, administered at a dose of 500 mg four times a day, did not change the pharmacokinetics of levetiracetam 1000 mg twice daily. C ss max of the metabolite, ucb L057, was approximately doubled in the presence of probenecid while the fraction of drug excreted unchanged in the urine remained the same. Renal clearance of ucb L057 in the presence of probenecid decreased 60%, probably related to competitive inhibition of tubular secretion of ucb L057.
The effect of levetiracetam on probenecid was not studied.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Plasma levels of levetiracetam may be decreased and therefore need to be monitored closely during pregnancy. Based on animal data, may cause fetal harm ( 5.11 , 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), including levetiracetam, during pregnancy. Encourage women who are taking levetiracetam during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Prolonged experience with levetiracetam in pregnant women has not identified a drug-associated risk of major birth defects or miscarriage, based on published literature, which includes data from pregnancy registries and reflects experience over two decades [see Human Data ] .
In animal studies, levetiracetam produced developmental toxicity (increased embryofetal and offspring mortality, increased incidences of fetal structural abnormalities, decreased embryofetal and offspring growth, neurobehavioral alterations in offspring) at doses similar to human therapeutic doses [see Animal Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations Levetiracetam blood levels may decrease during pregnancy [see Warnings and Precautions (5.11) ] . Physiological changes during pregnancy may affect levetiracetam concentration. Decrease in levetiracetam plasma concentrations has been observed during pregnancy.
This decrease is more pronounced during the third trimester. Dose adjustments may be necessary to maintain clinical response. Data Human Data While available studies cannot definitively establish the absence of risk, data from the published literature and pregnancy registries have not established an association with levetiracetam use during pregnancy and major birth defects or miscarriage.
Animal Data When levetiracetam (0, 400, 1200, or 3600 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, reduced fetal weights and increased incidence of fetal skeletal variations were observed at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on embryofetal developmental in rats (1200 mg/kg/day) is approximately 4 times the maximum recommended human dose (MRHD) of 3000 mg on a body surface area (mg/m 2 ) basis.
Oral administration of levetiracetam (0, 200, 600, or 1800 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality and incidence of fetal skeletal variations at the mid and high dose and decreased fetal weights and increased incidence of fetal malformations at the high dose, which was associated with maternal toxicity. The no-effect dose for adverse effects on embryofetal development in rabbits (200 mg/kg/day) is approximately equivalent to the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam (0, 70, 350, or 1800 mg/kg/day) to female rats throughout pregnancy and lactation led to an increased incidence of fetal skeletal variations, reduced fetal body weight, and decreased growth in offspring at the mid and high doses and increased pup mortality and neurobehavioral alterations in offspring at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on pre-and postnatal development in rats (70 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam to rats during the latter part of gestation and throughout lactation produced no adverse developmental or maternal effects at doses of up to 1800 mg/kg/day (6 times the MRHD on a mg/m 2…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antiepileptic drugs (AEDs), including levetiracetam, during pregnancy. Encourage women who are taking levetiracetam during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org/. Risk Summary Prolonged experience with levetiracetam in pregnant women has not identified a drug-associated risk of major birth defects or miscarriage, based on published literature, which includes data from pregnancy registries and reflects experience over two decades [see Human Data ] .
In animal studies, levetiracetam produced developmental toxicity (increased embryofetal and offspring mortality, increased incidences of fetal structural abnormalities, decreased embryofetal and offspring growth, neurobehavioral alterations in offspring) at doses similar to human therapeutic doses [see Animal Data ] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. The background risk of major birth defects and miscarriage for the indicated population is unknown.
Clinical Considerations Levetiracetam blood levels may decrease during pregnancy [see Warnings and Precautions (5.11) ] . Physiological changes during pregnancy may affect levetiracetam concentration. Decrease in levetiracetam plasma concentrations has been observed during pregnancy.
This decrease is more pronounced during the third trimester. Dose adjustments may be necessary to maintain clinical response. Data Human Data While available studies cannot definitively establish the absence of risk, data from the published literature and pregnancy registries have not established an association with levetiracetam use during pregnancy and major birth defects or miscarriage.
Animal Data When levetiracetam (0, 400, 1200, or 3600 mg/kg/day) was administered orally to pregnant rats during the period of organogenesis, reduced fetal weights and increased incidence of fetal skeletal variations were observed at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on embryofetal developmental in rats (1200 mg/kg/day) is approximately 4 times the maximum recommended human dose (MRHD) of 3000 mg on a body surface area (mg/m 2 ) basis.
Oral administration of levetiracetam (0, 200, 600, or 1800 mg/kg/day) to pregnant rabbits during the period of organogenesis resulted in increased embryofetal mortality and incidence of fetal skeletal variations at the mid and high dose and decreased fetal weights and increased incidence of fetal malformations at the high dose, which was associated with maternal toxicity. The no-effect dose for adverse effects on embryofetal development in rabbits (200 mg/kg/day) is approximately equivalent to the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam (0, 70, 350, or 1800 mg/kg/day) to female rats throughout pregnancy and lactation led to an increased incidence of fetal skeletal variations, reduced fetal body weight, and decreased growth in offspring at the mid and high doses and increased pup mortality and neurobehavioral alterations in offspring at the highest dose tested. There was no evidence of maternal toxicity. The no-effect dose for adverse effects on pre-and postnatal development in rats (70 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration of levetiracetam to rats during the latter part of gestation and throughout lactation produced no adverse developmental or maternal effects at doses of up to 1800 mg/kg/day (6 times the MRHD on a mg/m 2 basis).
Pregnancy Levetiracetam levels may decrease during pregnancy [see Warnings and Precautions (5.11) and Use in Specific Populations (8.1) ].
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of levetiracetam for the treatment of partial-onset seizures in patients 1 month to 16 years of age have been established [see Clinical Pharmacology (12.3) and Clinical Studies (14.1) ] . The dosing recommendation in these pediatric patients varies according to age group and is weight-based [see Dosage and Administration (2.2) ] . The safety and effectiveness of levetiracetam as adjunctive therapy for the treatment of myoclonic seizures in adolescents 12 years of age and older with juvenile myoclonic epilepsy have been established [see Clinical Studies (14.2) ] .
The safety and effectiveness of levetiracetam as adjunctive therapy for the treatment of primary generalized tonic-clonic seizures in pediatric patients 6 years of age and older with idiopathic generalized epilepsy have been established [see Clinical Studies (14.3) ] . Safety and effectiveness for the treatment of partial-onset seizures in pediatric patients below the age of 1 month; adjunctive therapy for the treatment of myoclonic seizures in pediatric patients below the age of 12 years; and adjunctive therapy for the treatment of primary generalized tonic-clonic seizures in pediatric patients below the age of 6 years have not been established.
A 3-month, randomized, double-blind, placebo-controlled study was performed to assess the neurocognitive and behavioral effects of levetiracetam as adjunctive therapy in 98 (levetiracetam N = 64, placebo N = 34) pediatric patients, ages 4 to 16 years old, with partial seizures that were inadequately controlled. The target dose was 60 mg/kg/day . Neurocognitive effects were measured by the Leiter-R Attention and Memory (AM) Battery, which measures various aspects of a child's memory and attention.
Although no substantive differences were observed between the placebo and drug treated groups in the median change from baseline in this battery, the study was not adequate to assess formal statistical non-inferiority of the drug and placebo. The Achenbach Child Behavior Checklist (CBCL/6-18), a standardized validated tool used to assess a child’s competencies and behavioral/emotional problems, was also assessed in this study. An analysis of the CBCL/6-18 indicated on average a worsening in levetiracetam-treated patients in aggressive behavior, one of the eight syndrome scores [see Warnings and Precautions (5.1) ] .
Juvenile Animal Toxicity Data Studies of levetiracetam in juvenile rats (dosed on postnatal days 4 through 52) and dogs (dosed from postnatal weeks 3 through 7) at doses of up to 1800 mg/kg/day (approximately 7 and 24 times, respectively, the maximum recommended pediatric dose of 60 mg/kg/day on a mg/m 2 basis) did not demonstrate adverse effects on postnatal development.
🧓 Geriatric Use ▾
8.5Geriatric Use There were 347 subjects in clinical studies of levetiracetam that were 65 and over. No overall differences in safety were observed between these subjects and younger subjects. There were insufficient numbers of elderly subjects in controlled trials of epilepsy to adequately assess the effectiveness of levetiracetam in these patients.
Levetiracetam is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs, Symptoms and Laboratory Findings of Acute Overdosage in Humans The highest known dose of levetiracetam received in the clinical development program was 6000 mg/day. Other than drowsiness, there were no adverse reactions in the few known cases of overdose in clinical trials. Cases of somnolence, agitation, aggression, depressed level of consciousness, respiratory depression and coma were observed with levetiracetam overdoses in postmarketing use.
10.2Management of Overdose There is no specific antidote for overdose with levetiracetam. If indicated, elimination of unabsorbed drug should be attempted by emesis or gastric lavage; usual precautions should be observed to maintain airway. General supportive care of the patient is indicated including monitoring of vital signs and observation of the patient’s clinical status.
A Certified Poison Control Center should be contacted for up to date information on the management of overdose with levetiracetam.
10.3Hemodialysis Standard hemodialysis procedures result in significant clearance of levetiracetam (approximately 50% in 4 hours) and should be considered in cases of overdose. Although hemodialysis has not been performed in the few known cases of overdose, it may be indicated by the patient's clinical state or in patients with significant renal impairment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanism(s) by which levetiracetam exerts its antiepileptic effect is unknown. A saturable and stereoselective neuronal binding site in rat brain tissue has been described for levetiracetam. Experimental data indicate that this binding site is the synaptic vesicle protein SV2A, thought to be involved in the regulation of vesicle exocytosis.
Although the molecular significance of levetiracetam binding to SV2A is not understood, levetiracetam and related analogs showed a rank order of affinity for SV2A which correlated with the potency of their antiseizure activity in audiogenic seizure-prone mice. These findings suggest that the interaction of levetiracetam with the SV2A protein may contribute to the antiepileptic mechanism of action of the drug.
12.2Pharmacodynamics Effects on QTc Interval The effect of levetiracetam on QTc prolongation was evaluated in a randomized, double-blind, positive-controlled (moxifloxacin 400 mg) and placebo-controlled crossover study of levetiracetam (1000 mg or 5000 mg) in 52 healthy subjects. The upper bound of the 90% confidence interval for the largest placebo-adjusted, baseline-corrected QTc was below 10 milliseconds. Therefore, there was no evidence of significant QTc prolongation in this study.
12.3Pharmacokinetics The pharmacokinetics of levetiracetam are similar when used as monotherapy or as adjunctive therapy for the treatment of partial-onset seizures. Absorption and Distribution Absorption of levetiracetam is rapid, with peak plasma concentrations occurring in about an hour following oral administration in fasted subjects. The oral bioavailability of levetiracetam tablets is 100% and the tablets and oral solution are bioequivalent in rate and extent of absorption.
Food does not affect the extent of absorption of levetiracetam but it decreases C max by 20% and delays T max by 1.5 hours. The pharmacokinetics of levetiracetam are linear over the dose range of 500-5000 mg. Steady state is achieved after 2 days of multiple twice-daily dosing.
Levetiracetam and its major metabolite are less than 10% bound to plasma proteins; clinically significant interactions with other drugs through competition for protein binding sites are therefore unlikely. Metabolism Levetiracetam is not extensively metabolized in humans. The major metabolic pathway is the enzymatic hydrolysis of the acetamide group, which produces the carboxylic acid metabolite, ucb L057 (24% of dose) and is not dependent on any liver cytochrome P450 isoenzymes.
The major metabolite is inactive in animal seizure models. Two minor metabolites were identified as the product of hydroxylation of the 2-oxo-pyrrolidine ring (2% of dose) and opening of the 2-oxo-pyrrolidine ring in position 5 (1% of dose). There is no enantiomeric interconversion of levetiracetam or its major metabolite.
Elimination Levetiracetam plasma half-life in adults is 7 ± 1 hour and is unaffected by either dose or repeated administration. Levetiracetam is eliminated from the systemic circulation by renal excretion as unchanged drug which represents 66% of administered dose. The total body clearance is 0.96 mL/min/kg and the renal clearance is 0.6 mL/min/kg.
The mechanism of excretion is glomerular filtration with subsequent partial tubular reabsorption. The metabolite ucb L057 is excreted by glomerular filtration and active tubular secretion with a renal clearance of 4 mL/min/kg. Levetiracetam elimination is correlated to creatinine clearance.
Levetiracetam clearance is reduced in patients with renal impairment [see Use in Specific Populations (8.6) and Dosage and Administration (2.5) ]. Specific Populations Elderly Pharmacokinetics of levetiracetam were evaluated in 16 elderly subjects (age 61-88 years) with creatinine clearance ranging from 30 to 74 mL/min. Following oral administration of twice-daily dosing for 10 days, total body clearance decreased by 38% and the half-life was 2.5 hours longer in the…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanism(s) by which levetiracetam exerts its antiepileptic effect is unknown. A saturable and stereoselective neuronal binding site in rat brain tissue has been described for levetiracetam. Experimental data indicate that this binding site is the synaptic vesicle protein SV2A, thought to be involved in the regulation of vesicle exocytosis.
Although the molecular significance of levetiracetam binding to SV2A is not understood, levetiracetam and related analogs showed a rank order of affinity for SV2A which correlated with the potency of their antiseizure activity in audiogenic seizure-prone mice. These findings suggest that the interaction of levetiracetam with the SV2A protein may contribute to the antiepileptic mechanism of action of the drug.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Levetiracetam Tablets, USP are available containing 500 mg, 750 mg or 1000 mg of levetiracetam, USP. The 500 mg tablets are white, film-coated, modified capsule-shaped, scored tablets debossed with M to the left of the score and 615 to the right of the score on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-5615-78 bottles of 120 tablets NDC 0378-5615-05 bottles of 500 tablets The 750 mg tablets are white, film-coated, modified capsule-shaped, scored tablets debossed with M to the left of the score and 617 to the right of the score on one side of the tablet and blank on the other side.
They are available as follows: NDC 0378-5617-78 bottles of 120 tablets NDC 0378-5617-05 bottles of 500 tablets The 1000 mg tablets are white, film-coated, modified capsule-shaped, scored tablets debossed with M to the left of the score and 619 to the right of the score on one side of the tablet and blank on the other side. They are available as follows: NDC 0378-5619-91 bottles of 60 tablets
16.2Storage Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. PHARMACIST: Dispense a Medication Guide with each prescription.
📋 Description ▾
11 DESCRIPTION Levetiracetam is an antiepileptic drug available as 500 mg (white), 750 mg (white) and 1000 mg (white) tablets for oral administration. The chemical name of levetiracetam, a single enantiomer, is (-)-( S )-α-Ethyl-2-oxo-1-pyrrolidineacetamide, its molecular formula is C 8 H 14 N 2 O 2 and its molecular weight is 170.21. Levetiracetam is chemically unrelated to existing antiepileptic drugs (AEDs).
It has the following structural formula: Levetiracetam, USP is a white to off-white crystalline powder with a faint odor and a bitter taste. It is very soluble in water (104.0 g/100 mL). It is freely soluble in chloroform (65.3 g/100 mL) and in methanol (53.6 g/100 mL), soluble in ethanol (16.5 g/100 mL), sparingly soluble in acetonitrile (5.7 g/100 mL) and practically insoluble in n-hexane.
(Solubility limits are expressed as g/100 mL solvent.) Levetiracetam tablets, USP contain the labeled amount of levetiracetam. Inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose, magnesium stearate, microcrystalline cellulose, polydextrose, polyethylene glycol, povidone, sodium lauryl sulfate, titanium dioxide and triacetin. Meets USP Dissolution Test 2.
Levetiracetam Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Psychiatric Reactions and Changes in Behavior Advise patients that levetiracetam may cause changes in behavior (e.g. aggression, agitation, anger, anxiety, apathy, depression, hostility, and irritability) and psychotic symptoms [see Warnings and Precautions (5.1) ] . Suicidal Behavior and Ideation Counsel patients, their caregivers, and/or families that antiepileptic drugs (AEDs), including levetiracetam tablets, may increase the risk of suicidal thoughts and behavior and advise patients to be alert for the emergence or worsening of symptoms of depression; unusual changes in mood or behavior; or suicidal thoughts, behavior, or thoughts about self-harm.
Advise patients, their caregivers, and/or families to immediately report behaviors of concern to a healthcare provider [see Warnings and Precautions (5.2) ] . Effects on Driving or Operating Machinery Inform patients that levetiracetam may cause dizziness and somnolence. Inform patients not to drive or operate machinery until they have gained sufficient experience on levetiracetam to gauge whether it adversely affects their ability to drive or operate machinery [see Warnings and Precautions (5.3) ] .
Anaphylaxis and Angioedema Advise patients to discontinue levetiracetam and seek medical care if they develop signs and symptoms of anaphylaxis or angioedema [see Warnings and Precautions (5.4) ]. Dermatological Adverse Reactions Advise patients that serious dermatological adverse reactions have occurred in patients treated with levetiracetam and instruct them to call their physician immediately if a rash develops [see Warnings and Precautions (5.5) ] . DRESS/Multiorgan Hypersensitivity Instruct patients and caregivers that a fever or rash associated with signs of other organ system involvement (e.g., lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately.
Levetiracetam should be discontinued immediately if a serious hypersensitivity reaction is suspected [see Warnings and Precautions (5.6) ] . Withdrawal of Levetiracetam Advise patients and caregivers not to discontinue use of levetiracetam without consulting with their healthcare provider. Levetiracetam should normally be gradually withdrawn to reduce the potential of increased seizure frequency and status epilepticus [see Warnings and Precautions (5.8) ].
Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during levetiracetam therapy. Encourage patients to enroll in the North American Antiepileptic Drug (NAAED) pregnancy registry if they become pregnant [see Use in Specific Populations (8.1) ].
💬 Medication Guide ▾
Medication Guide Levetiracetam Tablets, USP (lee'' ve tye ra' se tam) Read this Medication Guide before you start taking levetiracetam and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about levetiracetam? Like other antiepileptic drugs, levetiracetam may cause suicidal thoughts or actions in a very small number of people, about 1 in 500 people taking it. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: • thoughts about suicide or dying • attempts to commit suicide • new or worse depression • new or worse anxiety • feeling agitated or restless • panic attacks • trouble sleeping (insomnia) • new or worse irritability • acting aggressive, being angry, or violent • acting on dangerous impulses • an extreme increase in activity and talking (mania) • other unusual changes in behavior or mood Do not stop levetiracetam without first talking to a healthcare provider . • Stopping levetiracetam suddenly can cause serious problems.
Stopping a seizure medicine suddenly can cause seizures that will not stop (status epilepticus). • Suicidal thoughts or actions can be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes. How can I watch for early symptoms of suicidal thoughts and actions? • Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. • Keep all follow-up visits with your healthcare provider as scheduled.
Call your healthcare provider between visits as needed, especially if you are worried about symptoms What is levetiracetam? Levetiracetam is a prescription medicine taken by mouth that is used to treat partial-onset seizures in people 1 month of age and older. Levetiracetam is a prescription medicine taken by mouth that is used with other medicines to treat: • myoclonic seizures in people 12 years of age and older with juvenile myoclonic epilepsy. • primary generalized tonic-clonic seizures in people 6 years of age and older with certain types of generalized epilepsy.
It is not known if levetiracetam is safe or effective in children under: • 1 month of age to treat partial-onset seizures • 12 years of age to treat myoclonic seizures • 6 years of age to treat primary generalized tonic-clonic seizures Before taking your medicine, make sure you have received the correct medicine. Compare the name above with the name on your bottle and the appearance of your medicine with the description of levetiracetam provided below. Tell your pharmacist immediately if you think you have been given the wrong medicine.
Who should not take levetiracetam? Do not take levetiracetam if you are allergic to levetiracetam. What should I tell my healthcare provider before starting levetiracetam?
Before taking levetiracetam, tell your healthcare provider about all of your medical conditions, including if you: • have or have had depression, mood problems or suicidal thoughts or behavior. • have kidney problems. • are pregnant or planning to become pregnant. It is not known if levetiracetam will harm your unborn baby. You and your healthcare provider will have to decide if you should take levetiracetam while you are pregnant.
If you become pregnant while taking levetiracetam, talk to your healthcare provider about registering with the North American Antiepileptic Drug Pregnancy Registry. You can enroll in this registry by calling 1-888-233-2334 or go to http://www.aedpregnancyregistry.org. The purpose of this registry is to collect information about the safety of levetiracetam and other antiepileptic medicine during pregnancy. • are breastfeeding or plan to breastfeed.
Levetiracetam can pass into your breast milk. It is not known if the levetiracetam that passes into your breast mi…