
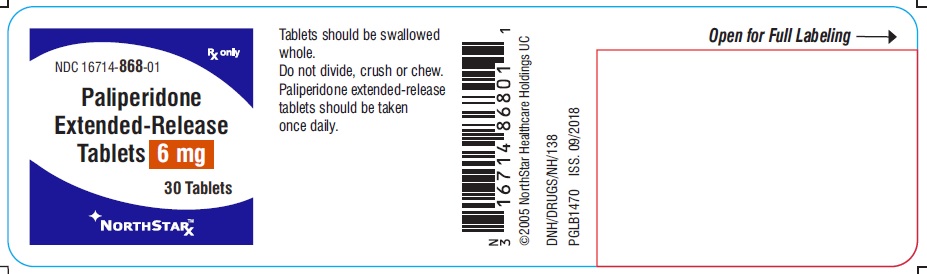
Paliperidone 6 mg Tablet, Film Coated, Extended Release, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Atypical Antipsychotic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Paliperidone is an antipsychotic medication used to treat schizophrenia and schizoaffective disorder. It works by calming overactive signals in the brain — specifically blocking ce...
- What exactly does paliperidone do — why did my doctor prescribe it?
- Yes — swallow the tablet whole. Don't chew it, crush it, or split it. The tablet is specially designed to release the medication slowly over the day, and breaking it would release...
- I've been prescribed the tablet form. Is there anything special about how I take it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Paliperidone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII 7Z8S9VYZ4B
Ethylcellulose is a plant-derived thickener and film-former made by chemically modifying cellulose. It's used as a binder to hold tablet ingredients together, a coating to control how quickly medicine is released, or a thickener in liquid formulations.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
16 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.015 | $30.44 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.89 | $56.68 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $2.23 | $66.86 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Paliperidone 6 mg 00904-6936-61 | Major | 1 tablet | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mgthis 16714-0868-01 | NorthStar | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 27808-0224-01 | Tris | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 31722-0319-30 | Camber | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 43975-0351-03 | ANI | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 47335-0766-83 | Sun | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 60687-0470-01 | American | 1 tablet | $1.014 | AB | Availability likely | — |
| paliperidone 6 mg 62332-0805-30 | Alembic | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 65162-0282-03 | Amneal | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 69367-0434-30 | Westminster | 30 tablets | $1.014 | AB | Availability likely | — |
| Paliperidone 6 mg 72819-0159-03 | Archis | 30 tablets | $1.014 | — | Availability likely | — |
| Invega 6 mg 50458-0551-01 | Janssen | 30 tablets | $12.390 | AB | Availability likely | +1121% |
| Paliperidone 6 mg 27241-0278-30 | Ajanta | 30 tablets | — | AB | FDA listed | — |
| Paliperidone 6 mg 42291-0917-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| paliperidone 6 mg 46708-0805-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Paliperidone 6 mg 67046-1630-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Paliperidone 6 mg 70518-4268-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Paliperidone 6 mg 72162-2650-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Paliperidone 6 mg 72658-1255-01 | Eskayef | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 16714-0868-01 You're viewing this | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (16714-868-01) | 2018-10-15 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS Elderly patients with dementia-related psychos is treated with antipsychotic drugs are at an increased risk of death. Paliperidone extended-release tablets are not approved for the treatment of patients with dementia-related psychosis. [see Warnings and Precautions (5.1)] WARNING: INCREASED MORTALITY IN ELDERLY PATIENTS WITH DEMENTIA-RELATED PSYCHOSIS See full prescribing information for complete boxed warning . Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death.
Paliperidone extended-release tablets are not approved for use in patients with dementia-related psychosis. (5.1)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Paliperidone is an atypical antipsychotic agent indicated for Treatment of schizophrenia ( 1.1 ) • Adults: Efficacy was established in three 6-week trials and one maintenance trial. ( 14.1 ) • Adolescents (ages 12 to 17): Efficacy was established in one 6-week trial. ( 14.1 ) Treatment of schizoaffective disorder as monotherapy and as an adjunct to mood stabilizers and/or antidepressants.
( 1.2 ) • Efficacy was established in two 6-week trials in adult patients. ( 14.2 )
1.1Schizophrenia Paliperidone extended-release tablets are indicated for the treatment of schizophrenia [see Clinical Studies (14.1 )] . The efficacy of paliperidone extended-release tablets in schizophrenia was established in three 6-week trials in adults and one 6-week trial in adolescents, as well as one maintenance trial in adults.
1.2Schizoaffective Disorder Paliperidone extended-release tablets are indicated for the treatment of schizoaffective disorder as monotherapy and an adjunct to mood stabilizers and/or antidepressant therapy [see Clinical Studies (14.2 )] . The efficacy of paliperidone extended-release tablets in schizoaffective disorder was established in two 6-week trials in adults.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initial Dose Recommended Dose Maximum Dose Schizophrenia - adults ( 2.1 ) 6 mg/day 3 to 12 mg/day 12 mg/day Schizophrenia-adolescents ( 2.1 ) Weight < 51kg 3 mg/day 3 to 6 mg/day 6 mg/day Weight ≥ 51kg 3 mg/day 3 to 12 mg/day 12 mg/day Schizoaffective disorder - adults ( 2.2 ) 6 mg/day 3 to 12 mg/day 12 mg/day Tablet should be swallowed whole and should not be chewed, divided, or crushed. ( 2.3 )
2.1Schizophrenia Adults The recommended dose of paliperidone extended-release tablets for the treatment of schizophrenia in adults is 6 mg administered once daily. Initial dose titration is not required. Although it has not been systematically established that doses above 6 mg have additional benefit, there was a general trend for greater effects with higher doses.
This must be weighed against the dose-related increase in adverse reactions. Thus, some patients may benefit from higher doses, up to 12 mg/day, and for some patients, a lower dose of 3 mg/day may be sufficient. Dose increases above 6 mg/day should be made only after clinical reassessment and generally should occur at intervals of more than 5 days.
When dose increases are indicated, increments of 3 mg/day are recommended. The maximum recommended dose is 12 mg/day. In a longer-term study, paliperidone has been shown to be effective in delaying time to relapse in patients with schizophrenia who were stabilized on paliperidone for 6 weeks [see Clinical Studies (14)] .
Paliperidone extended-release tablets should be prescribed at the lowest effective dose for maintaining clinical stability and the physician should periodically reevaluate the long-term usefulness of the drug in individual patients. Adolescents (12 to 17 years of age) The recommended starting dose of paliperidone extended-release tablets for the treatment of schizophrenia in adolescents 12 to 17 years of age is 3 mg administered once daily. Initial dose titration is not required.
Dose increases, if considered necessary, should be made only after clinical reassessment and should occur at increments of 3 mg/day at intervals of more than 5 days. Prescribers should be mindful that, in the adolescent schizophrenia study, there was no clear enhancement to efficacy at the higher doses, i.e., 6 mg for subjects weighing less than 51 kg and 12 mg for subjects weighing 51 kg or greater, while adverse events were dose-related.
2.2Schizoaffective Disorder The recommended dose of paliperidone extended-release tablets for the treatment of schizoaffective disorder in adults is 6 mg administered once daily. Initial dose titration is not required. Some patients may benefit from lower or higher doses within the recommended dose range of 3 to 12 mg once daily.
A general trend for greater effects was seen with higher doses. This trend must be weighed against dose-related increase in adverse reactions. Dosage adjustment, if indicated, should occur only after clinical reassessment.
Dose increases, if indicated, generally should occur at intervals of more than 4 days. When dose increases are indicated, increments of 3 mg/day are recommended. The maximum recommended dose is 12 mg/day.
2.3Administration Instructions Paliperidone extended-release tablets can be taken with or without food. Paliperidone extended-release tablets must be swallowed whole with the aid of liquids. Tablets should not be chewed, divided, or crushed.
2.4Use with Risperidone Concomitant use of paliperidone extended-release tablets with risperidone has not been studied. Since paliperidone is the major active metabolite of risperidone, consideration should be given to the additive paliperidone exposure if risperidone is coadministered with paliperidone extended-release tablets.
2.5Dosage in Special Populations Renal Impairment Dosing must be individualized according to the patient’s renal function status. For patients with mild renal impairment (creatinine clearance ≥ 50 mL/min to < 80 mL/min), the recommended initial dose of paliperido…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Paliperidone extended-release tablets are available in the following strengths and colors: 1.5 mg (brown), 3 mg (white to off-white), 6 mg (yellow), and 9 mg (pink). All tablets are circular shaped and are imprinted with either “744”, “765”, “766”, or “767”. Tablets: 1.5 mg, 3 mg, 6 mg, and 9 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Paliperidone is contraindicated in patients with a known hypersensitivity to either paliperidone or risperidone, or to any of the excipients in the paliperidone extended-release tablet formulation. Hypersensitivity reactions, including anaphylactic reactions and angioedema, have been reported in patients treated with risperidone and in patients treated with paliperidone. Paliperidone is a metabolite of risperidone.
Known hypersensitivity to paliperidone, risperidone, or to any excipients in paliperidone extended-release tablets.( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cerebrovascular Adverse Reactions: An increased incidence of cerebrovascular adverse reactions (e.g. stroke, transient ischemic attack, including fatalities) has been seen in elderly patients with dementia-related psychoses treated with atypical antipsychotics. ( 5.2 ) Neuroleptic Malignant Syndrome: Manage with immediate discontinuation of drug and close monitoring. ( 5.3) QT Prolongation: Increase in QT interval, avoid use with drugs that also increase QT interval and in patients with risk factors for prolonged QT interval.
( 5.4 ) Tardive Dyskinesia: Discontinue drug if clinically appropriate. ( 5.5 ) Metabolic Changes: Atypical antipsychotic drugs have been associated with metabolic changes that may increase cardiovascular/ cerebrovascular risk. These metabolic changes include hyperglycemia, dyslipidemia, and weight gain.
( 5.6) Hyperglycemia and Diabetes Mellitus: Monitor patients for symptoms of hyperglycemia including polydipsia, polyuria, polyphagia, and weakness. Monitor glucose regularly in patients with diabetes or at risk for diabetes. ( 5.6 ) Dyslipidemia: Undesirable alterations have been observed in patients treated with atypical antipsychotics.
( 5.6 ) Weight Gain: Significant weight gain has been reported. Monitor weight gain. ( 5.6 ) Hyperprolactinemia: Prolactin elevations occur and persist during chronic administration.
( 5.7 ) Gastrointestinal Narrowing: Obstructive symptoms may result in patients with gastrointestinal disease. ( 5.8 ) Orthostatic Hypotension and Syncope: Use with caution in patients with known cardiovascular or cerebrovascular disease and patients predisposed to hypotension. ( 5.9 ) Leukopenia, Neutropenia, and Agranulocytosis: has been reported with antipsychotics, including paliperidone.
Patients with a history of a clinically significant low white blood cell count (WBC) or a drug-induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and discontinuation of paliperidone should be considered at the first sign of a clinically significant decline in WBC in the absence of other causative factors. ( 5.11 ) Potential for Cognitive and Motor Impairment: Use caution when operating machinery. ( 5.12 ) Seizures: Use cautiously in patients with a history of seizures or with conditions that lower the seizure threshold.
( 5.13 )
5.1Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of 17 placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear.
Paliperidone is not approved for the treatment of dementia-related psychosis [see Boxed Warning].
5.2Cerebrovascular Adverse Reactions, Including Stroke, in Elderly Patients with Dementia-Related Psychosis In placebo-controlled trials with risperidone, aripiprazole, and olanzapine in elderly subjects with dementia, there was a higher incidence of cerebrovascular adverse reactions (cerebrovascular accidents and transient ischemic attacks) including fatalitie…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in more detail in other sections of the labeling: Increased mortality in elderly patients with dementia-related psychosis [see Boxed Warning and Warnings and Precautions (5.1)] Cerebrovascular adverse reactions, including stroke, in elderly patients with dementia-related psychosis [see Warnings and Precautions (5.2)] Neuroleptic malignant syndrome [see Warnings and Precautions (5.3)] QT prolongation [see Warnings and Precautions (5.4)] Tardive dyskinesia [see Warnings and Precautions (5.5)] Metabolic changes [see Warnings and Precautions (5.6)] Hyperprolactinemia [see Warnings and Precautions (5.7)] Potential for gastrointestinal obstruction [see Warnings and Precautions (5.8)] Orthostatic hypotension and syncope [see Warnings and Precautions (5.9)] Falls [see Warnings and Precautions (5.10)] Leukopenia, neutropenia, and agranulocytosis [see Warnings and Precautions (5.11)] Potential for cognitive and motor impairment [see Warnings and Precautions (5.12)] Seizures [see Warnings and Precautions (5.13)] Dysphagia [see Warnings and Precautions (5.14)] Priapism [see Warnings and Precautions (5.15)] Disruption of body temperature regulation [see Warnings and Precautions (5.16)] Commonly observed adverse reactions (incidence ≥ 5% and at least twice that for placebo) were (6) Adults with schizophrenia: extrapyramidal symptoms, tachycardia, and akathisia.
Adolescents with schizophrenia: somnolence, akathisia, tremor, dystonia, cogwheel rigidity, anxiety, weight increased, and tachycardia. Adults with schizoaffective disorder: extrapyramidal symptoms, somnolence, dyspepsia, constipation, weight increased, and nasopharyngitis. To report SUSPECTED ADVERSE REACTIONS, contact NorthStar RxLLC at 1-800-206-7821 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience The most common adverse reactions in clinical trials in adult subjects with schizophrenia (reported in 5% or more of subjects treated with paliperidone and at least twice the placebo rate in any of the dose groups) were extrapyramidal symptoms, tachycardia, and akathisia. The most common adverse reactions in clinical trials in adult patients with schizoaffective disorder (reported in 5% or more of subjects treated with paliperidone and at least twice the placebo rate) were extrapyramidal symptoms, somnolence, dyspepsia, constipation, weight increased, and nasopharyngitis.
The most common adverse reactions that were associated with discontinuation from clinical trials in adult subjects with schizophrenia (causing discontinuation in 2% of paliperidone-treated subjects) were nervous system disorders. The most common adverse reactions that were associated with discontinuation from clinical trials in adult subjects with schizoaffective disorder were gastrointestinal disorders, which resulted in discontinuation in 1% of paliperidone-treated subjects. [see Adverse Reactions (6)] . The safety of paliperidone was evaluated in 1205 adult subjects with schizophrenia who participated in three placebo-controlled, 6-week, double-blind trials, of whom 850 subjects received paliperidone at fixed doses ranging from 3 mg to 12 mg once daily.
The information presented in this section was derived from pooled data from these three trials. Additional safety information from the placebo-controlled phase of the long-term maintenance study, in which subjects received paliperidone at daily doses within the range of 3 mg to 15 mg (n=104), is also included. The safety of paliperidone was evaluated in 150 adolescent subjects 12 to 17 years of age with schizophrenia who received paliperidone in the dose range of 1.5 mg to 12 mg/day in a 6-week, double-blind, placebo-controlled trial.
The safety of paliperidone was also evaluated in 622 adult subjects with schizoaffective disorder who participated in two placebo-controlled, 6-week, double-blind trials. In one of these trials, 206 subjects were assigned to one of two dos…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Centrally-acting drugs: Due to CNS effects, use caution in combination. Avoid alcohol. ( 7.1 ) Drugs that may cause orthostatic hypotension: An additive effect may be observed when coadministered with paliperidone.
( 7.1 ) Strong CYP3A4/P-glycoprotein (P-gp) inducers: It may be necessary to increase the dose of paliperidone when a strong inducer of both CYP3A4 and P-gp (e.g., carbamazepine) is coadministered. Conversely, on discontinuation of the strong inducer, it may be necessary to decrease the dose of paliperidone. ( 7.2 ) Coadministration of divalproex sodium increased C max and AUC of paliperidone by approximately 50%.
Adjust dose of paliperidone if necessary based on clinical assessment. ( 7.2 )
7.1Potential for Paliperidone to Affect Other Drugs Given the primary CNS effects of paliperidone [see Adverse Reactions (6.1, 6.2)] , paliperidone should be used with caution in combination with other centrally acting drugs and alcohol. Paliperidone may antagonize the effect of levodopa and other dopamine agonists. Because of its potential for inducing orthostatic hypotension, an additive effect may be observed when paliperidone is administered with other therapeutic agents that have this potential [see Warnings and Precautions (5.9)] .
Paliperidone is not expected to cause clinically important pharmacokinetic interactions with drugs that are metabolized by cytochrome P450 isozymes. In vitro studies in human liver microsomes showed that paliperidone does not substantially inhibit the metabolism of drugs metabolized by cytochrome P450 isozymes, including CYP1A2, CYP2A6, CYP2C8/9/10, CYP2D6, CYP2E1, CYP3A4, and CYP3A5. Therefore, paliperidone is not expected to inhibit clearance of drugs that are metabolized by these metabolic pathways in a clinically relevant manner.
Paliperidone is also not expected to have enzyme inducing properties. Paliperidone is a weak inhibitor of P-glycoprotein (P-gp) at high concentrations. No in vivo data are available and the clinical relevance is unknown.
Pharmacokinetic interaction between lithium and paliperidone is unlikely. In a drug interaction study, coadministration of paliperidone (12 mg once daily for 5 days) with divalproex sodium extended-release tablets (500 mg to 2000 mg once daily) did not affect the steady-state pharmacokinetics (AUC24h and C max ,ss) of valproate in 13 patients stabilized on valproate. In a clinical study, subjects on stable doses of valproate had comparable valproate average plasma concentrations when paliperidone 3 to 15 mg/day was added to their existing valproate treatment.
7.2Potential for Other Drugs to Affect Paliperidone Paliperidone is not a substrate of CYP1A2, CYP2A6, CYP2C9, and CYP2C19, so that an interaction with inhibitors or inducers of these isozymes is unlikely. While in vitro studies indicate that CYP2D6 and CYP3A4 may be minimally involved in paliperidone metabolism, in vivo studies do not show decreased elimination by these isozymes and they contribute to only a small fraction of total body clearance. In vitro studies have shown that paliperidone is a P-gp substrate.
Coadministration of paliperidone 6 mg once daily with carbamazepine, a strong inducer of both CYP3A4 and P-glycoprotein (P-gp), at 200 mg twice daily caused a decrease of approximately 37% in the mean steady-state C max and AUC of paliperidone. This decrease is caused, to a substantial degree, by a 35% increase in renal clearance of paliperidone. A minor decrease in the amount of drug excreted unchanged in the urine suggests that there was little effect on the CYP metabolism or bioavailability of paliperidone during carbamazepine coadministration.
On initiation of carbamazepine, the dose of paliperidone should be re-evaluated and increased if necessary. Conversely, on discontinuation of carbamazepine, the dose of paliperidone should be re-evaluated and decreased if necessary. Paliperidone is metabolized to a limited extent by CYP2D6 [see Clinical Pharmacology (12…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Renal impairment: Dosing must be individualized according to renal function status. (2.5) Elderly: Same as for younger adults (adjust dose according to renal function status). (2.4) Pregnancy: May cause extrapyramidal and/or withdrawal symptoms in neonates with third trimester exposure.
(8.1) Pediatric Use: Safety and effectiveness in the treatment of schizophrenia not established in patients less than 12 years of age. Safety and effectiveness in the treatment of schizoaffective disorder not established in patients less than 18 years of age. (8.4)
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including paliperidone, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/. Risk Summary Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery ( see Clinical Considerations ).
Overall, available data from published epidemiologic studies of pregnant women exposed to paliperidone have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes ( see Data ). There are risks to the mother associated with untreated schizophrenia and with exposure to antipsychotics, including paliperidone, during pregnancy ( see Clinical Considerations ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. In animal reproduction studies, there were no increases in fetal abnormalities when pregnant rats and rabbits were treated with paliperidone during the period of organogenesis with up to 8 times the maximum recommended human dose (MRHD) based on mg/m 2 body surface area.
Additional reproduction toxicity studies were conducted with orally administered risperidone, which is extensively converted to paliperidone (see Animal data). Clinical Considerations Disease-associated maternal and/or embryo/fetal risk There is a risk to the mother from untreated schizophrenia, including increased risk of relapse, hospitalization, and suicide. Schizophrenia are associated with increased adverse perinatal outcomes, including preterm birth.
It is not known if this is a direct result of the illness or other comorbid factors. Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs, including paliperidone, during the third trimester of pregnancy. These symptoms have varied in severity.
Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization. Data Human Data Published data from observational studies, birth registries, and case reports on the use of atypical antipsychotics during pregnancy do not report a clear association with antipsychotics and major birth defects.
A prospective observational study including 6 women treated with risperidone, the parent compound of paliperidone, demonstrated placental passage of risperidone and paliperidone. A retrospective cohort study from a Medicaid database of 9258 women exposed to antipsychotics during pregnancy did not indicate an overall increased risk for major birth def…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to atypical antipsychotics, including paliperidone, during pregnancy. Healthcare providers are encouraged to register patients by contacting the National Pregnancy Registry for Atypical Antipsychotics at 1-866-961-2388 or online at http://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/. Risk Summary Neonates exposed to antipsychotic drugs during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery ( see Clinical Considerations ).
Overall, available data from published epidemiologic studies of pregnant women exposed to paliperidone have not established a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes ( see Data ). There are risks to the mother associated with untreated schizophrenia and with exposure to antipsychotics, including paliperidone, during pregnancy ( see Clinical Considerations ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. In animal reproduction studies, there were no increases in fetal abnormalities when pregnant rats and rabbits were treated with paliperidone during the period of organogenesis with up to 8 times the maximum recommended human dose (MRHD) based on mg/m 2 body surface area.
Additional reproduction toxicity studies were conducted with orally administered risperidone, which is extensively converted to paliperidone (see Animal data). Clinical Considerations Disease-associated maternal and/or embryo/fetal risk There is a risk to the mother from untreated schizophrenia, including increased risk of relapse, hospitalization, and suicide. Schizophrenia are associated with increased adverse perinatal outcomes, including preterm birth.
It is not known if this is a direct result of the illness or other comorbid factors. Fetal/Neonatal Adverse Reactions Extrapyramidal and/or withdrawal symptoms, including agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress, and feeding disorder have been reported in neonates who were exposed to antipsychotic drugs, including paliperidone, during the third trimester of pregnancy. These symptoms have varied in severity.
Monitor neonates for extrapyramidal and/or withdrawal symptoms and manage symptoms appropriately. Some neonates recovered within hours or days without specific treatment; others required prolonged hospitalization. Data Human Data Published data from observational studies, birth registries, and case reports on the use of atypical antipsychotics during pregnancy do not report a clear association with antipsychotics and major birth defects.
A prospective observational study including 6 women treated with risperidone, the parent compound of paliperidone, demonstrated placental passage of risperidone and paliperidone. A retrospective cohort study from a Medicaid database of 9258 women exposed to antipsychotics during pregnancy did not indicate an overall increased risk for major birth defects. There was a small increase in the risk of major birth defects (RR= 1.26, 95% CI 1.02 to 1.56) and of cardiac malformations (RR=1.26, 95% CI 0.88 to 1.81) in a subgroup of 1566 women exposed to the parent compound of paliperidone, risperidone, during the first trimester of pregnancy; however, there is no mechanism of action to explain the difference in malformation rates.
Animal Data In animal reproduction studies, there were no increases in fetal abnormalities when pregnant rats and rabbits were treated with paliperidone during the period of organogenesis with up to 8 tim…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of paliperidone in the treatment of schizophrenia were evaluated in 150 adolescent subjects 12 to 17 years of age with schizophrenia who received paliperidone in the dose range of 1.5 mg to 12 mg/day in a 6-week, double-blind, placebo-controlled trial. Safety and effectiveness of paliperidone for the treatment of schizophrenia in patients < 12 years of age have not been established. Safety and effectiveness of paliperidone for the treatment of schizoaffective disorder in patients < 18 years of age have not been studied.
Juvenile Animal Studies In a study in which juvenile rats were treated with oral paliperidone from days 24 to 73 of age, a reversible impairment of performance in a test of learning and memory was seen, in females only, with a no-effect dose of 0.63 mg/kg/day, which produced plasma levels (AUC) of paliperidone similar to those in adolescents at MRHD of 12 mg/day. No other consistent effects on neurobehavioral or reproductive development were seen up to the highest dose tested (2.5 mg/kg/day), which produced plasma levels of paliperidone 2 to 3 times those in adolescents.
Juvenile dogs were treated for 40 weeks with oral risperidone, which is extensively metabolized to paliperidone in animals and humans, at doses of 0.31, 1.25, or 5 mg/kg/day. Decreased bone length and density were seen with a no-effect dose of 0.31 mg/kg/day, which produced plasma levels (AUC) of risperidone plus paliperidone which were similar to those in children and adolescents receiving the MRHD of risperidone. In addition, a delay in sexual maturation was seen at all doses in both males and females.
The above effects showed little or no reversibility in females after a 12-week drug-free recovery period. The long-term effects of paliperidone on growth and sexual maturation have not been fully evaluated in children and adolescents.
🧓 Geriatric Use ▾
8.5Geriatric Use The safety, tolerability, and efficacy of paliperidone were evaluated in a 6-week placebo-controlled study of 114 elderly subjects with schizophrenia (65 years of age and older, of whom 21 were 75 years of age and older). In this study, subjects received flexible doses of paliperidone (3 mg to 12 mg once daily). In addition, a small number of subjects 65 years of age and older were included in the 6-week placebo-controlled studies in which adult schizophrenic subjects received fixed doses of paliperidone (3 mg to 15 mg once daily) [see Clinical Studies (14)] .
There were no subjects ≥ 65 years of age in the schizoaffective disorder studies. Overall, of the total number of subjects in schizophrenia clinical studies of paliperidone (n = 1,796), including those who received paliperidone or placebo, 125 (7%) were 65 years of age and older and 22 (1.2%) were 75 years of age and older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in response between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
This drug is known to be substantially excreted by the kidney and clearance is decreased in patients with moderate to severe renal impairment [see Clinical Pharmacology (12.3)] , who should be given reduced doses. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Dosage and Administration (2.5)] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Experience While experience with paliperidone overdose is limited, among the few cases of overdose reported in pre-marketing trials, the highest estimated ingestion of paliperidone was 405 mg. Observed signs and symptoms included extrapyramidal symptoms and gait unsteadiness. Other potential signs and symptoms include those resulting from an exaggeration of paliperidone’s known pharmacological effects, i.e., drowsiness and somnolence, tachycardia and hypotension, and QT prolongation.
Torsade de pointes and ventricular fibrillation have been reported in a patient in the setting of overdose. Paliperidone is the major active metabolite of risperidone. Overdose experience reported with risperidone can be found in the OVERDOSAGE section of the risperidone package insert.
10.2Management of Overdosage There is no specific antidote to paliperidone, therefore, appropriate supportive measures should be instituted and close medical supervision and monitoring should continue until the patient recovers. Consideration should be given to the extended-release nature of the product when assessing treatment needs and recovery. Multiple drug involvement should also be considered.
In case of acute overdose, establish and maintain an airway and ensure adequate oxygenation and ventilation. Administration of activated charcoal together with a laxative should be considered. The possibility of obtundation, seizures, or dystonic reaction of the head and neck following overdose may create a risk of aspiration with induced emesis.
Cardiovascular monitoring should commence immediately, including continuous electrocardiographic monitoring for possible arrhythmias. If antiarrhythmic therapy is administered, disopyramide, procainamide, and quinidine carry a theoretical hazard of additive QT-prolonging effects when administered in patients with an acute overdose of paliperidone. Similarly, the alpha-blocking properties of bretylium might be additive to those of paliperidone, resulting in problematic hypotension.
Hypotension and circulatory collapse should be treated with appropriate measures, such as intravenous fluids and/or sympathomimetic agents (epinephrine and dopamine should not be used, since beta stimulation may worsen hypotension in the setting of paliperidone-induced alpha blockade). In cases of severe extrapyramidal symptoms, anticholinergic medication should be administered.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Paliperidone is the major active metabolite of risperidone. The mechanism of action of paliperidone in schizophrenia is unclear. However, the drug's therapeutic effect in schizophrenia could be mediated through a combination of central dopamine Type 2 (D 2 ) and serotonin Type 2 (5HT 2A ) receptor antagonism.
12.2Pharmacodynamics In vitro , paliperidone acts as an antagonist at the central dopamine Type 2 (D 2 ) and serotonin Type 2 (5HT 2A ) receptors, with binding affinities (Ki values) of 1.6 to 2.8 nM for D 2 and 0.8 to 1.2 nM for 5HT 2A receptors. Paliperidone is also active as an antagonist at the α 1 and α 2 adrenergic receptors and H 1 histaminergic receptors, which may explain some of the other effects of the drug. Paliperidone has no affinity for cholinergic muscarinic or β 1 - and β 2 -adrenergic receptors.
The pharmacological activity of the (+)- and (-)- paliperidone enantiomers is qualitatively and quantitatively similar in vitro .
12.3Pharmacokinetics Following a single dose, the plasma concentrations of paliperidone gradually rise to reach peak plasma concentration (C max ) approximately 24 hours after dosing. The pharmacokinetics of paliperidone following paliperidone administration are dose-proportional within the available dose range. The terminal elimination half-life of paliperidone is approximately 23 hours.
Steady-state concentrations of paliperidone are attained within 4 to 5 days of dosing with paliperidone in most subjects. The mean steady-state peak: trough ratio for an paliperidone dose of 9 mg was 1.7 with a range of 1.2 to 3.1. Following administration of paliperidone, the (+) and (-) enantiomers of paliperidone interconvert, reaching an AUC (+) to (-) ratio of approximately 1.6 at steady state.
Absorption and Distribution The absolute oral bioavailability of paliperidone following paliperidone administration is 28%. Administration of a 12 mg paliperidone extended-release tablet to healthy ambulatory subjects with a standard high-fat/high-caloric meal gave mean C max and AUC values of paliperidone that were increased by 60% and 54%, respectively, compared with administration under fasting conditions. Clinical trials establishing the safety and efficacy of paliperidone were carried out in subjects without regard to the timing of meals.
While paliperidone can be taken without regard to food, the presence of food at the time of paliperidone administration may increase exposure to paliperidone [see Dosage and Administration (2.3)] . Based on a population analysis, the apparent volume of distribution of paliperidone is 487 L. The plasma protein binding of racemic paliperidone is 74%.
Metabolism and Elimination Although in vitro studies suggested a role for CYP2D6 and CYP3A4 in the metabolism of paliperidone, in vivo results indicate that these isozymes play a limited role in the overall elimination of paliperidone [see Drug Interactions (7)] . One week following administration of a single oral dose of 1 mg immediate-release 14 C-paliperidone to 5 healthy volunteers, 59% (range 51% to 67%) of the dose was excreted unchanged into urine, 32% (26% to 41%) of the dose was recovered as metabolites, and 6% to 12% of the dose was not recovered.
Approximately 80% of the administered radioactivity was recovered in urine and 11% in the feces. Four primary metabolic pathways have been identified in vivo , none of which could be shown to account for more than 10% of the dose: dealkylation, hydroxylation, dehydrogenation, and benzisoxazole scission. Population pharmacokinetic analyses found no difference in exposure or clearance of paliperidone between extensive metabolizers and poor metabolizers of CYP2D6 substrates.
Special Populations Renal Impairment The dose of paliperidone should be reduced in patients with moderate or severe renal impairment [see Dosage and Administration (2.5)] . The disposition of a single dose paliperidone 3 mg extended-release tablet was…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Paliperidone is the major active metabolite of risperidone. The mechanism of action of paliperidone in schizophrenia is unclear. However, the drug's therapeutic effect in schizophrenia could be mediated through a combination of central dopamine Type 2 (D 2 ) and serotonin Type 2 (5HT 2A ) receptor antagonism.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Paliperidone extended-release tablets are available in the following strengths and packages. 1.5 mg tablets are brown, circular, biconvex, beveled edged, film-coated tablets imprinted with “744” in black ink on one side and plain on the other side. NDC Number Size 16714-866-01 Bottle of 30 Tablets with Child Resistant Cap 3 mg tablets are white to off-white, circular, biconvex, beveled edged, film-coated tablets imprinted with “765” in black ink on one side and plain on the other side.
NDC Number Size 16714-867-01 Bottle of 30 Tablets with Child Resistant Cap 6 mg tablets are yellow, circular, biconvex, beveled edged, film-coated tablets imprinted with “766” in black ink on one side and plain on the other side. NDC Number Size 16714-868-01 Bottle of 30 Tablets with Child Resistant Cap 9 mg tablets are pink, circular, biconvex, beveled edged, film-coated tablets imprinted with “767” in black ink on one side and plain on the other side. NDC Number Size 16714-869-01 Bottle of 30 Tablets with Child Resistant Cap Storage and Handling Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° and 30°C (59° and 86°F) [see USP Controlled Room Temperature].
Protect from moisture. Keep out of reach of children.
📋 Description ▾
11 DESCRIPTION Paliperidone extended-release tablet contains paliperidone USP, an atypical antipsychotic belonging to the chemical class of benzisoxazole derivatives. Paliperidone contains a racemic mixture of (+)- and (-)- paliperidone. The chemical name is (±)-3-[2-[4-(6-fluoro-1,2-benzisoxazol-3-yl)-1-piperidinyl]ethyl]-6,7,8,9-tetrahydro-9-hydroxy-2-methyl-4H-pyrido[1,2-a]pyrimidin-4-one.
Its molecular formula is C 23 H 27 FN 4 O 3 and its molecular weight is 426.49. The structural formula is: Paliperidone is sparingly soluble in 0.1N HCl and methylene chloride; practically insoluble in water, 0.1N NaOH, and hexane; and slightly soluble in N,N-dimethylformamide. Paliperidone extended-release tablets are intended for oral administration and are available in 1.5 mg (brown), 3 mg (white to off-white), 6 mg (yellow), and 9 mg (pink) strengths.
Paliperidone extended-release tablets are formulated as a polymer matrix based once-a-day controlled release tablet for oral use. Inactive ingredients are polyethylene oxide, hypromellose, anhydrous lactose, magnesium stearate, ethyl cellulose, triethyl citrate, talc, titanium dioxide and polyethylene glycol. The 1.5 mg and 6 mg tablets also contain lactose monohydrate, iron oxide yellow and iron oxide red.
The 9 mg tablets also contain lactose monohydrate and iron oxide red. Imprinting ink contains shellac glaze, iron oxide black, N-butyl alcohol, propylene glycol and ammonium hydroxide. Delivery System Components and Performance Paliperidone extended release tablets employ a film-coated hydrophilic hydrogel matrix to deliver paliperidone at a controlled rate over 24 hours.
The system comprises of: a core consists of the drug, rate-controlling polymer (forming hydrogel) and other excipients with pH independent coat surrounding core, comprising of water soluble and insoluble polymer and a film coat over it. Upon ingestion outer film coat dissolves exposing the coated tablet to the gastric fluids. Once the water soluble polymer from coat gets dissolved, pores are formed which allow penetration of fluid inside the membrane leading to hydration of core-forming hydrogel.
Drug release occurs via slow diffusion out of the gel layer and subsequent gel erosion. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Physicians are advised to discuss the following issues with patients for whom they prescribe paliperidone. Neuroleptic Malignant Syndrome (NMS) Counsel patients about a potentially fatal adverse reaction, Neuroleptic Malignant Syndrome (NMS), that has been reported in association with administration of antipsychotic drugs. Advise patients, family members, or caregivers to contact their healthcare provider or report to the emergency room if they experience signs and symptoms of NMS, including hyperpyrexia, muscle rigidity, altered mental status including delirium, and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis, and cardiac dysrhythmia) [see Warnings and Precautions (5.3)] .
Tardive Dyskinesia Counsel patients on the signs and symptoms of tardive dyskinesia and to contact their healthcare provider if these abnormal movements occur [see Warnings and Precautions (5.5)] . Metabolic Changes Educate patients about the risk of metabolic changes, how to recognize symptoms of hyperglycemia and diabetes mellitus, and the need for specific monitoring, including blood glucose, lipids, and weight [see Warnings and Precautions (5.6)] . Orthostatic Hypotension Educate patients about the risk of orthostatic hypotension and syncope, particularly at the time of initiating treatment, re-initiating treatment, or increasing the dose [see Warnings and Precautions (5.9)] .
Leukopenia/Neutropenia Advise patients with a pre-existing low WBC or a history of drug-induced leukopenia/neutropenia they should have their CBC monitored while taking paliperidone [see Warnings and Precautions (5.11)] . Hyperprolactinemia Counsel patients on signs and symptoms of hyperprolactinemia that may be associated with chronic use of paliperidone. Advise them to seek medical attention if they experience any of the following: amenorrhea or galactorrhea in females, erectile dysfunction or gynecomastia in males [see Warnings and Precautions (5.7)] .
Interference with Cognitive and Motor Performanc e Caution patients about performing activities requiring mental alertness, such as operating hazardous machinery, or operating a motor vehicle, until they are reasonably certain that paliperidone therapy does not affect them adversely [see Warnings and Precautions (5.12)] . Priapism Advise patients of the possibility of painful or prolonged penile erections (priapism). Instruct the patient to seek immediate medical attention in the event of priapism [see Warnings and Precautions (5.15)] .
Heat Exposure and Dehydratio n Counsel patients on the importance of avoiding overheating and dehydration [see Warnings and Precautions (5.16)] . Concomitant Medication Advise patients to inform their healthcare providers if they are taking, or plan to take, any prescription or over-the-counter drugs, as there is a potential for interactions [see Drug Interactions (7)] . Alcohol Advise patients to avoid alcohol while taking paliperidone [see Drug Interactions (7.1)] .
Administration Patients should be informed that paliperidone should be swallowed whole with the aid of liquids. Tablets should not be chewed, divided, or crushed [see Dosage and Administration (2.3)] . Pregnancy Advise patients to notify their healthcare provider if they become pregnant or intend to become pregnant during treatment with paliperidone.
Advise patients that paliperidone may cause extrapyramidal and/or withdrawal symptoms in a neonate. Advise patients that there is a pregnancy registry that monitors pregnancy outcomes in women exposed to paliperidone extended-release tablets during pregnancy [see Use in Specific Populations (8.1)] . Lactation Advise breastfeeding women using paliperidone to monitor infants for somnolence, failure to thrive, jitteriness, and extrapyramidal symptoms (tremors and abnormal muscle movements) and to seek medical care if they notice these signs [see Use in Specific Populations (8.2)] .
Infertility Advise female…